BNP and NT-proBNP show up everywhere in CHF questions—ED dyspnea workups, chronic HF management, even test-day “rule-in/rule-out” traps. The good news: you can get most USMLE points from three patterns: where they come from, how to interpret them, and when they mislead you.
Tip #1: Know the Source + Trigger (and the One-Liner)
High-yield one-liner: Stretch a ventricle → it releases BNP (and NT-proBNP) → you pee/salt more and vasodilate to unload the heart.
What they are
- BNP (B-type natriuretic peptide): the active hormone
- NT-proBNP: the inactive N-terminal fragment released in equal proportion
Where they come from
- Primarily ventricular myocytes (think: volume/pressure overload → ventricular wall stress)
What they do (BNP physiology you can test)
BNP counters RAAS and sympathetic tone by promoting:
- Natriuresis/diuresis (↑ GFR, ↓ Na⁺ reabsorption)
- Vasodilation
- ↓ Renin and ↓ aldosterone
- ↓ Sympathetic activity
USMLE connection: In heart failure, BNP is elevated as a compensatory response—so high BNP doesn’t mean “BNP is causing HF,” it means the ventricle is stressed.
Tip #2: Use the “BNP = Breathless? Not Pulmonary.” Rule (ED Dyspnea Pearl)
High-yield one-liner: High BNP/NT-proBNP supports cardiogenic dyspnea; low values make HF unlikely.
Quick interpretation framework (what NBME-style questions want)
- Low BNP/NT-proBNP → argues against acute decompensated HF as the cause of dyspnea
- High BNP/NT-proBNP → supports HF (but interpret in context—see Tip #3)
Common Step-style use case
COPD vs HF exacerbation
- COPD flare: wheeze, hyperinflation, chronic CO₂ retention (often normal BNP)
- HF: pulmonary edema, S3, orthopnea, JVD (often elevated BNP)
A rapid comparison table
| Condition | BNP/NT-proBNP | Why |
|---|---|---|
| Acute decompensated HF | ↑ | Ventricular stretch |
| Pulmonary edema (cardiogenic) | ↑ | Same mechanism |
| COPD/asthma exacerbation | Often normal | No primary ventricular stretch |
| Pulmonary embolism | Can be ↑ | RV strain can increase natriuretic peptides |
Test-day phrasing tip: When the stem says “helps distinguish cardiac vs pulmonary cause of dyspnea,” they’re pointing you to BNP/NT-proBNP.
Tip #3: Memorize the 3 Big Confounders (Age, Kidneys, Obesity)
BNP and NT-proBNP are great—but they’re not immune to classic USMLE “gotchas.”
The “AKO” mnemonic: Age, Kidneys, Obesity
Use it like a mental filter before you overcall HF.
A = Age (older patients trend higher)
- Baseline natriuretic peptide levels can rise with age.
- Practical takeaway: borderline elevations are less specific in elderly patients.
K = Kidneys (renal failure → higher, especially NT-proBNP)
- Reduced clearance contributes to elevation.
- NT-proBNP is more affected by decreased GFR than BNP (commonly tested nuance).
O = Obesity (lower levels than expected)
- Obese patients can have falsely lower BNP/NT-proBNP, so a “normal-ish” value doesn’t fully exclude HF if the clinical picture screams volume overload.
Bonus Step fact: HFrEF vs HFpEF
- Both HFrEF and HFpEF can elevate BNP/NT-proBNP because both can increase filling pressures/wall stress.
- HFpEF is common in: older patients, long-standing HTN, concentric LVH.
Visual/Mnemonic Device: “BNP is the Ventricular Stress Text”
Picture your ventricle as a stressed-out student:
Ventricle stretched → sends a text: “BNP!”
And BNP replies with three actions (“DVA”):
- Diuresis / natriuresis
- Vasodilation
- Anti-RAAS (↓ renin, ↓ aldosterone)
One-liner to memorize:
“Stretched ventricle texts BNP → DVA: Diurese, Vasodilate, Anti-RAAS.”
Rapid-Fire USMLE Takeaways (the stuff you want on test day)
- BNP/NT-proBNP rise with ventricular wall stress (classically HF).
- Low BNP/NT-proBNP makes HF unlikely in acute dyspnea workups.
- Renal failure elevates values (NT-proBNP especially); obesity lowers them.
- BNP is part of the body’s attempt to counterbalance RAAS—HF is still a net “RAAS-on” state despite BNP being high.
- BNP is associated with ventricles, while ANP is more atrial (classic pairing).
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
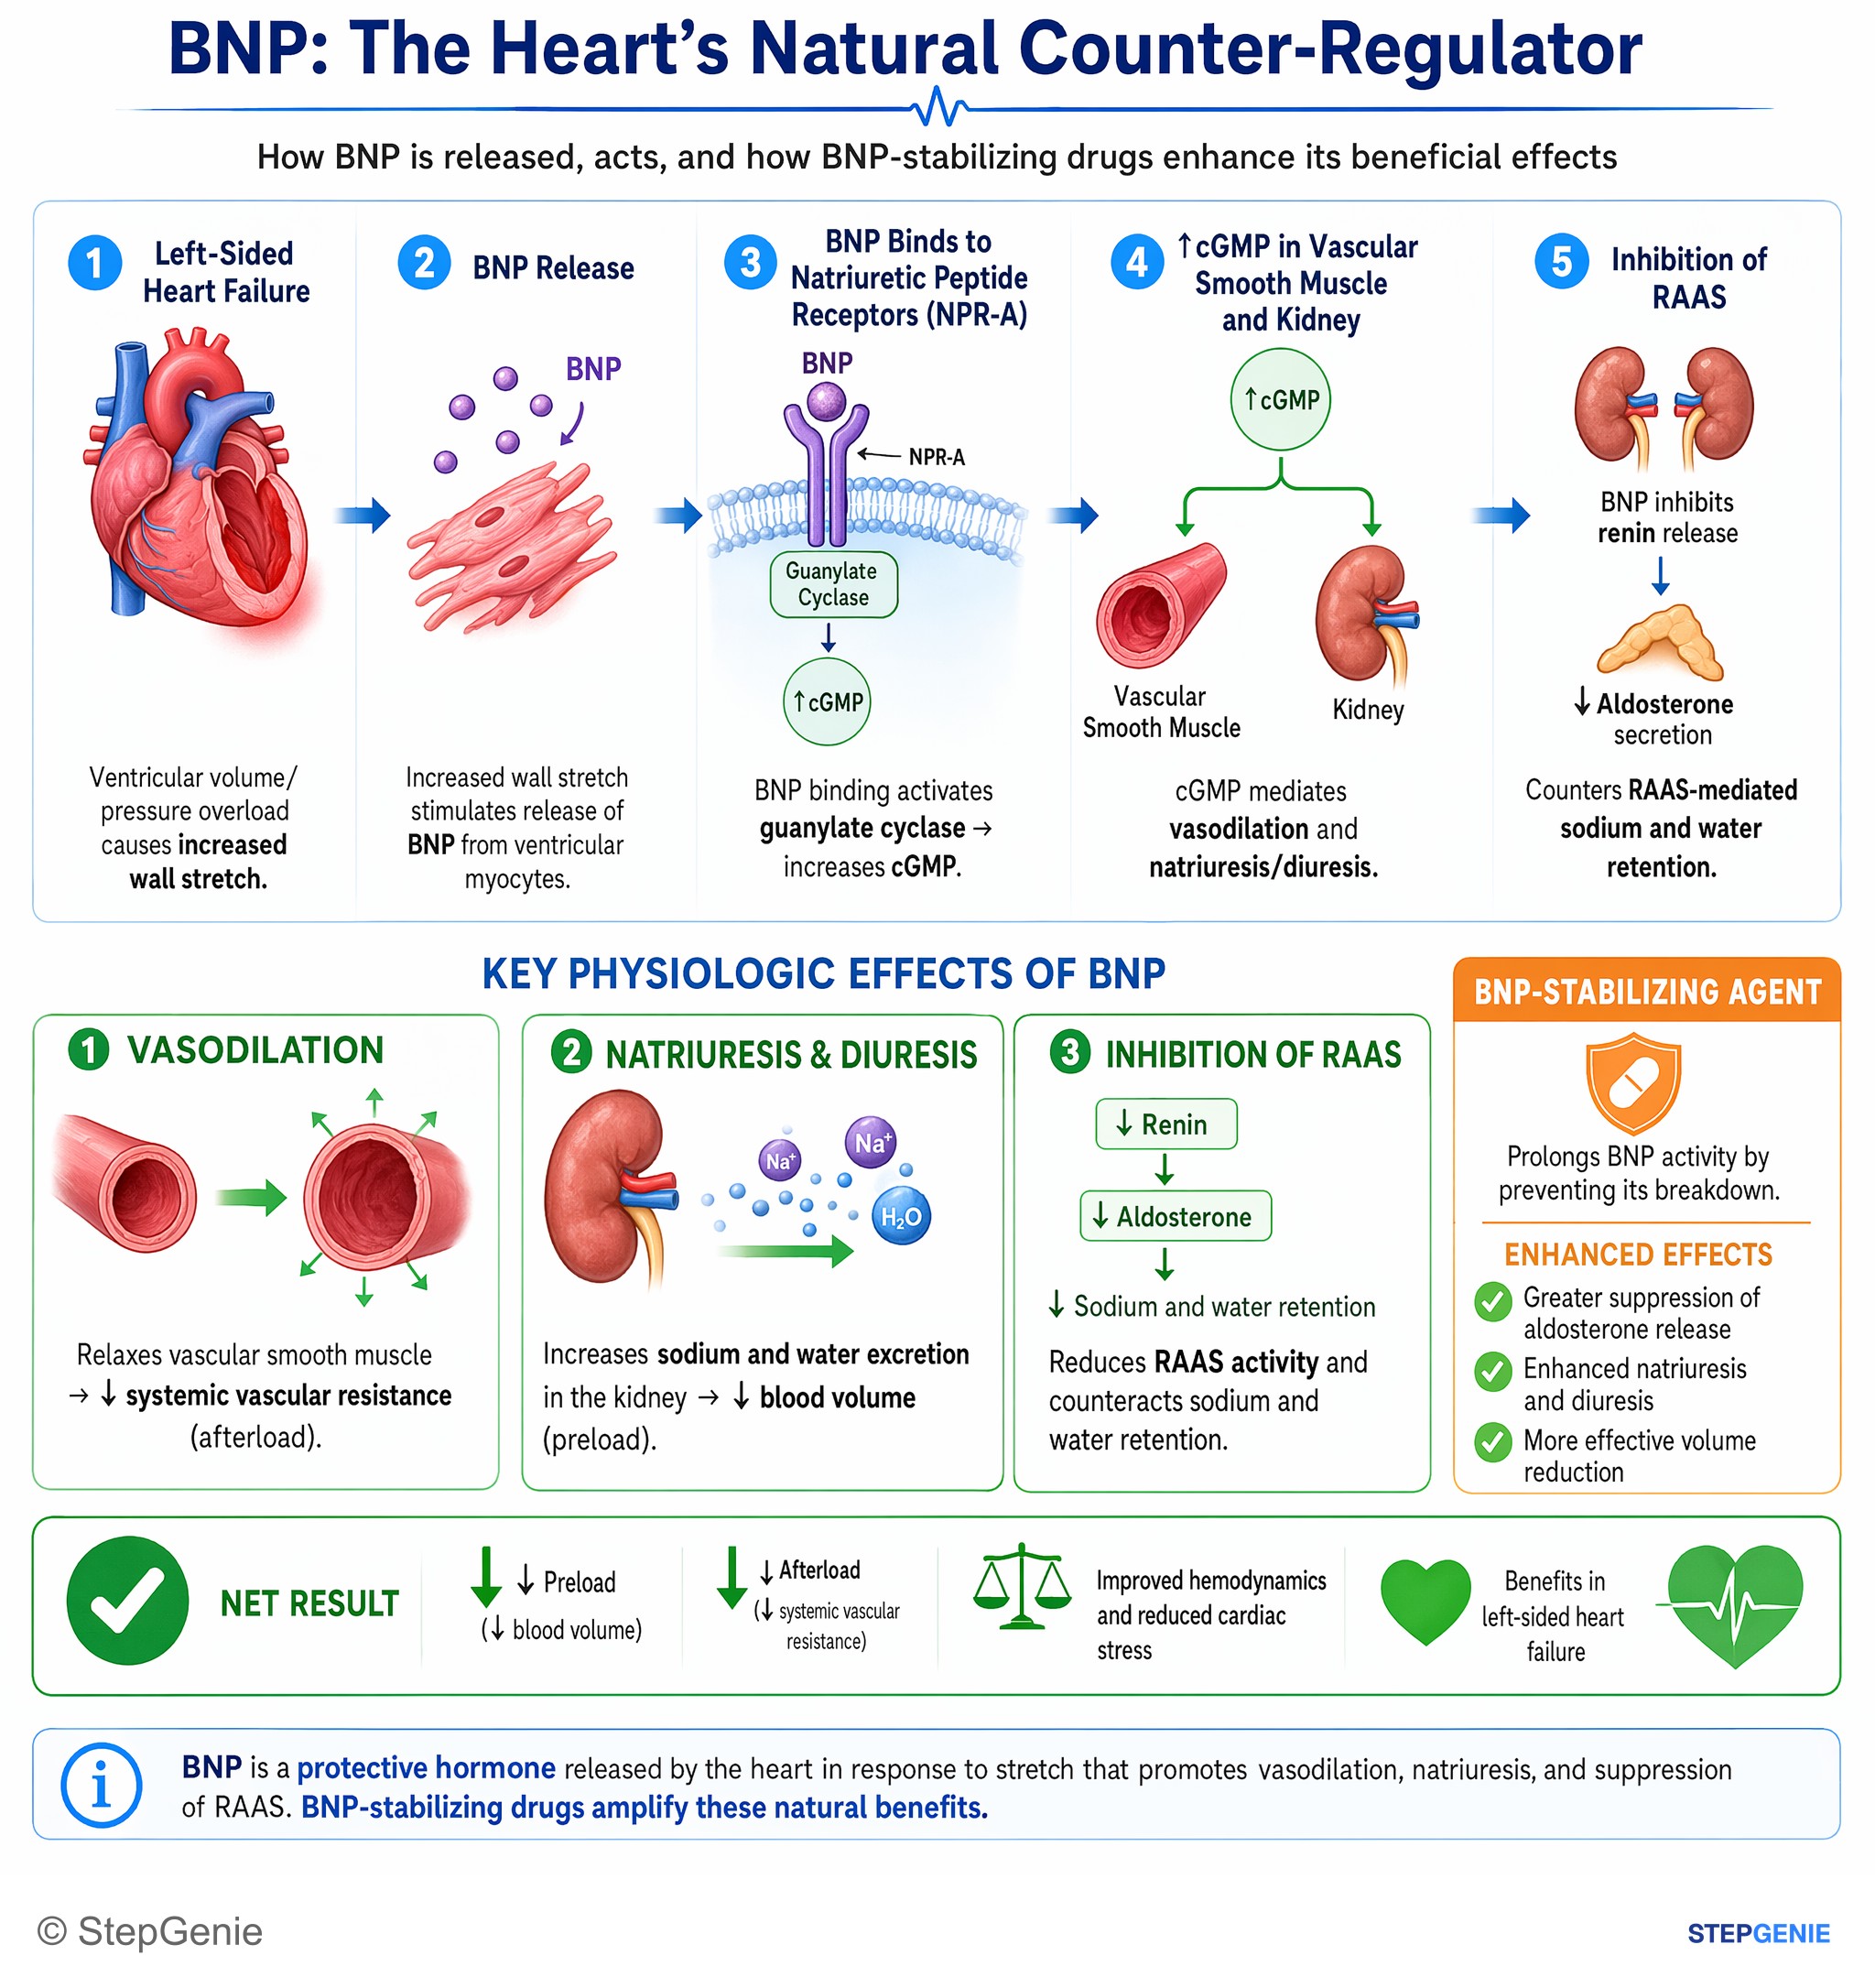
BNP from ventricular stretch activates guanylate cyclase → ↑cGMP → vasodilation, natriuresis, and ↓renin–aldosterone; BNP-stabilizing…
USMLE Step 1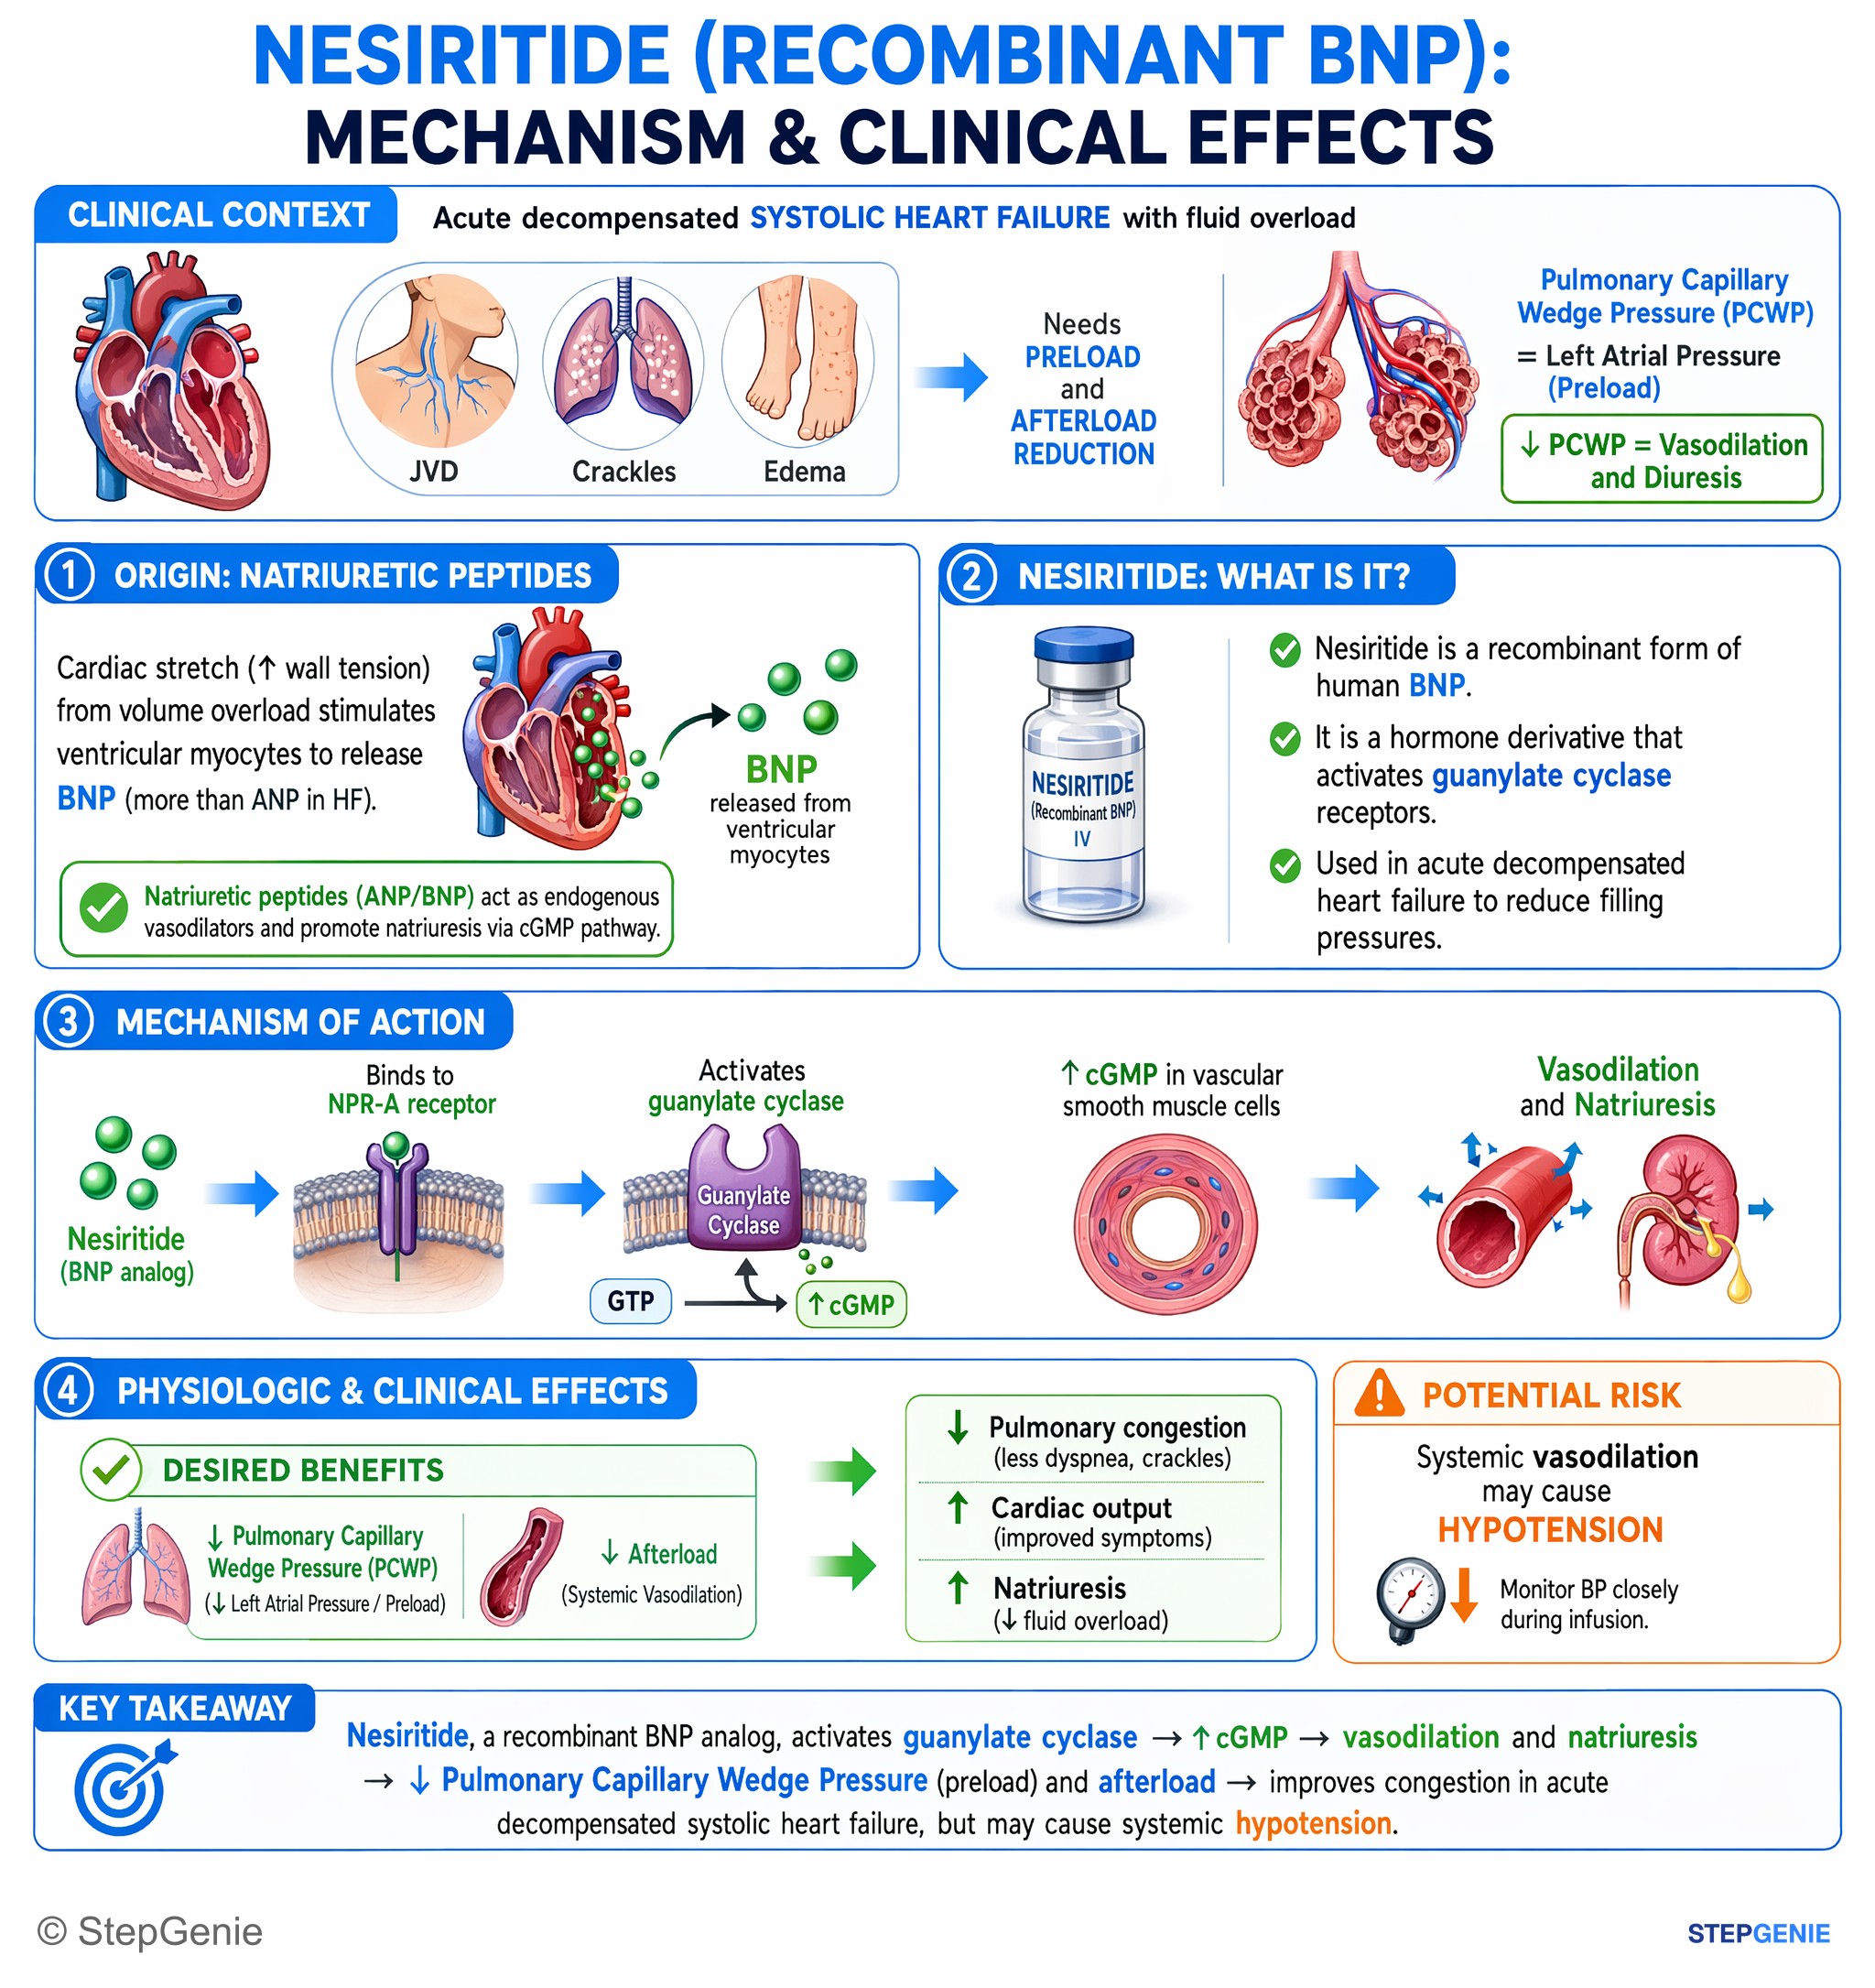
Nesiritide, a recombinant BNP analog, activates guanylate cyclase → ↑cGMP → vasodilation, ↓pulmonary capillary wedge pressure, but may…
USMLE Step 1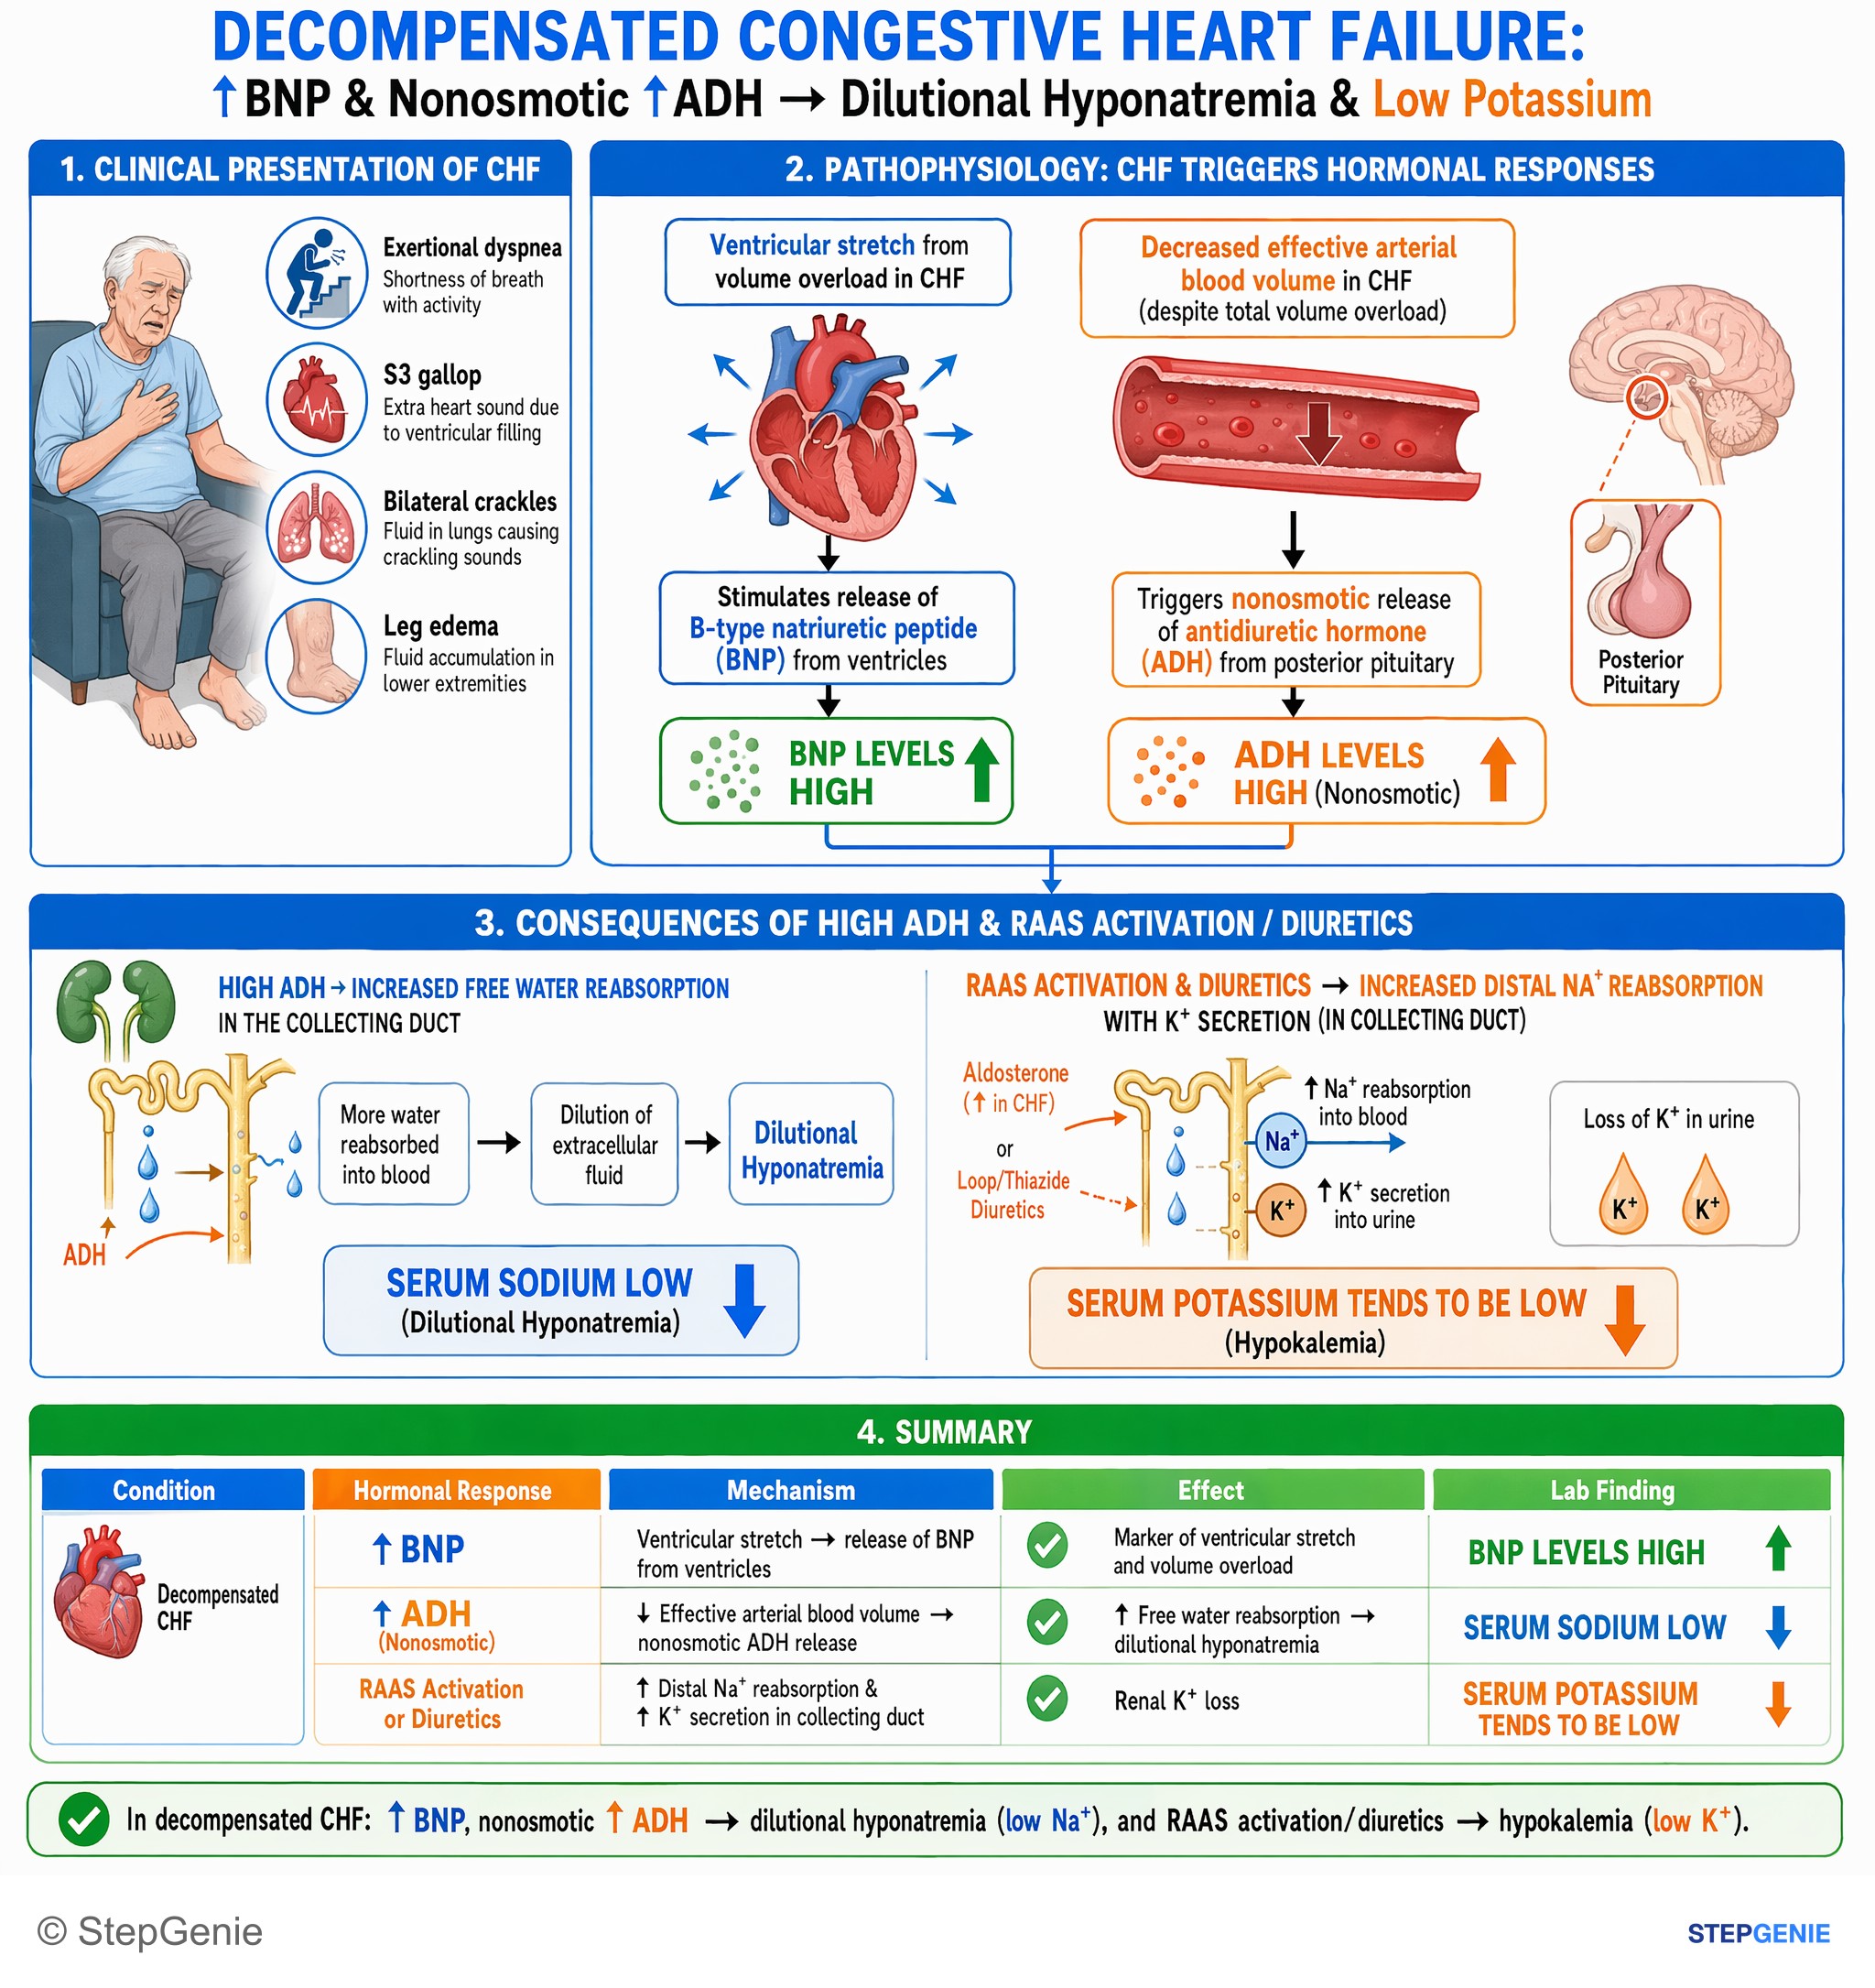
Decompensated congestive heart failure → ↑BNP + nonosmotic ↑ADH → dilutional hyponatremia; chronic diuretics/RAAS activation often cause…
USMLE Step 1Frequently Asked Questions
What triggers BNP and NT-proBNP release in heart failure?
BNP and NT-proBNP are released when the ventricle is stretched. They come primarily from ventricular myocytes in response to volume or pressure overload that increases ventricular wall stress. BNP is the active hormone, while NT-proBNP is the inactive fragment released in equal proportion. Their elevation in heart failure reflects a compensatory response to ventricular stress rather than BNP causing the disease.
What does BNP do physiologically when the ventricle is under stress?
BNP promotes natriuresis, diuresis, and vasodilation to unload the heart. It counteracts RAAS and sympathetic tone by increasing GFR, decreasing sodium reabsorption, lowering renin and aldosterone, and reducing sympathetic activity. A useful way to remember it is that a stretched ventricle releases BNP, which then helps the body diurese, vasodilate, and oppose RAAS activation.
How do BNP and NT-proBNP help distinguish heart failure from a pulmonary cause of dyspnea?
High BNP or NT-proBNP supports a cardiogenic cause of dyspnea, while low values make acute decompensated heart failure unlikely. This is especially useful in test-style comparisons such as COPD versus heart failure exacerbation. COPD flare often has wheeze, hyperinflation, and chronic CO2 retention with often normal BNP, whereas heart failure more often has pulmonary edema, S3, orthopnea, JVD, and elevated BNP.
What are the big BNP and NT-proBNP confounders you need to remember?
The main confounders are age, kidney function, and obesity. Older patients can have higher baseline natriuretic peptide levels, so borderline elevations are less specific. Renal failure raises levels because of reduced clearance, and NT-proBNP is more affected by decreased GFR than BNP. Obesity can produce falsely lower BNP or NT-proBNP values, so a normal-ish result does not fully exclude heart failure if the clinical picture strongly suggests volume overload.
Can BNP be elevated in conditions other than HFrEF?
Yes, BNP can also be elevated in HFpEF and even in pulmonary embolism. Both HFrEF and HFpEF can raise BNP or NT-proBNP because both increase filling pressures or wall stress. Pulmonary embolism can also elevate natriuretic peptides because right ventricular strain can trigger their release. That is why elevated values support heart failure but still need to be interpreted in clinical context.