You’re in the middle of a timed block, and the stem is screaming “collapse + no pulse,” but the ECG strip looks like a chaotic scribble. Ventricular fibrillation (VF) is one of those diagnoses where pattern recognition saves lives—and where the distractors are designed to punish fuzzy thinking about rhythms, pulses, and shockability. Let’s break it down the way a great q-bank explanation would: what VF is, what you do immediately, and why every wrong answer is tempting.
Tag: Cardiovascular > ECG Interpretation
The Clinical Vignette (Classic USMLE Style)
A 62-year-old man with a history of coronary artery disease suddenly collapses while walking to the bathroom in the hospital. He is unresponsive. No carotid pulse is palpated. The monitor shows a chaotic, irregular waveform with no identifiable P waves or QRS complexes. A nurse asks what to do next.
Most likely diagnosis: Ventricular fibrillation
Next best step: Immediate unsynchronized defibrillation + CPR
What Ventricular Fibrillation Actually Means (Mechanism + ECG)
Pathophysiology (why the pulse is absent)
VF is disorganized ventricular electrical activity → no coordinated contraction → zero effective cardiac output → no pulse.
ECG hallmarks
- Chaotic, irregular waveform
- No identifiable QRS complexes
- No organized atrial activity you can meaningfully track
- Can be coarse VF (bigger amplitude) or fine VF (low amplitude; can mimic asystole)
High-yield: VF is a shockable rhythm (along with pulseless VT). Asystole and PEA are not shockable.
Correct Answer: Immediate Defibrillation (Unsynchronized Shock)
Why defibrillation works
Defibrillation delivers a high-energy shock that simultaneously depolarizes a critical mass of myocardium, “resetting” electrical activity and allowing the SA node (or another pacemaker) to regain control.
What you do in real life (ACLS logic, Step-friendly)
If VF/pulseless VT:
- Start CPR
- Defibrillate ASAP (unsynchronized)
- Resume CPR immediately after shock
- Epinephrine and amiodarone are add-ons after early shocks/CPR (timing varies by algorithm details, but Step questions reward “shock now”)
Key test phrase: “Pulseless + VF on monitor” → defibrillate
Why Every Distractor Matters (and Why It’s Wrong)
Below are common answer choices that show up with VF vignettes—and the exact reasoning that separates them.
Distractor 1: Synchronized Cardioversion
Why it’s tempting: You remember “electricity fixes arrhythmias,” and cardioversion sounds right.
Why it’s wrong for VF:
- Cardioversion requires synchronization to the R wave to avoid shocking during the vulnerable T wave (R-on-T phenomenon).
- VF has no organized QRS complexes to sync to.
- Attempting to cardiovert wastes precious seconds.
Use synchronized cardioversion for:
- Unstable atrial fibrillation/flutter
- Unstable SVT
- Unstable monomorphic VT with a pulse
Quick rule:
- Pulse present + unstable → synchronized cardioversion
- No pulse (VF/pVT) → defibrillation
Distractor 2: Adenosine
Why it’s tempting: The “fast rhythm drug” reflex.
Why it’s wrong for VF:
- Adenosine transiently blocks AV nodal conduction → helps re-entrant SVTs involving the AV node.
- VF isn’t an AV-node-dependent rhythm and is immediately fatal without shock/CPR.
Adenosine is for:
- Stable, regular, narrow-complex tachycardia (e.g., AVNRT)
- Sometimes used diagnostically for certain regular wide-complex rhythms when stable—but never for pulseless arrest rhythms.
Distractor 3: Atropine
Why it’s tempting: You associate collapse with “bradycardia.”
Why it’s wrong for VF:
- VF is not a bradyarrhythmia—it’s chaos with no effective rhythm to speed up.
- Atropine is for symptomatic bradycardia (e.g., AV block, sinus brady) with a pulse.
Atropine is for:
- Unstable bradycardia (symptomatic)
Not for VF, not for PEA, not for asystole in modern algorithms.
Distractor 4: Amiodarone (as the next step)
Why it’s tempting: You recall “amiodarone for VF/VT.”
Why it’s wrong as the first move:
- In VF arrest, electricity and compressions come first.
- Antiarrhythmics help reduce recurrent VF after defibrillation attempts, but they don’t replace the need for immediate shock.
When amiodarone appears in VF/pVT scenarios:
- Refractory VF/pVT after defibrillation/CPR (classically after multiple shocks)
High-yield antiarrhythmic associations:
- Amiodarone: VT, VF (refractory), AF rhythm control; many toxicities (thyroid, lung, liver, cornea, skin)
- Lidocaine: alternative for ventricular arrhythmias (esp. ischemia-related), less common in questions but still fair game
Distractor 5: Epinephrine (as the next step)
Why it’s tempting: You remember epinephrine is given in cardiac arrest.
Why it’s wrong as the first move in VF:
- VF is shockable; early defibrillation is the most definitive therapy.
- Epinephrine is used during arrest to improve coronary and cerebral perfusion pressure during CPR, but it’s not the “one move” that fixes VF.
Step-style framing:
- If the question asks “next best step” with VF/pulseless VT and no interventions yet → defibrillate.
- If it asks about adjuncts during ongoing ACLS → epinephrine is appropriate.
Distractor 6: Transcutaneous Pacing
Why it’s tempting: “Electrical therapy” again.
Why it’s wrong for VF:
- Pacing requires myocardium that can respond in an organized manner.
- VF is disorganized electrical activity; pacing won’t capture meaningfully.
Pacing is for:
- Symptomatic bradycardia not responding to atropine
- Certain high-grade AV blocks
Distractor 7: Asystole
Why it’s tempting: Fine VF can look like a flatline, especially on a bad tracing.
How to avoid the trap:
- VF often shows some baseline waviness (fine fibrillatory activity), while true asystole is essentially flat.
- Check:
- Leads/monitor connections
- Gain settings
- More than one lead
Management difference (very high-yield):
- VF/pulseless VT: shock
- Asystole/PEA: no shock → CPR + epinephrine + fix causes
Rapid-Fire Table: VF vs Common Lookalikes
| Rhythm | ECG Clue | Pulse? | Shockable? | Immediate Action |
|---|---|---|---|---|
| Ventricular fibrillation | Chaotic, no QRS | No | Yes | Defibrillate + CPR |
| Pulseless VT | Wide, regular QRS | No | Yes | Defibrillate + CPR |
| Torsades de pointes | Polymorphic VT “twisting” | Often unstable; can be pulseless | If pulseless → yes | If unstable/pulseless: shock; give Mg; correct causes |
| Atrial fibrillation | Irregularly irregular, QRS present | Yes (usually) | No | Rate control/anticoag; cardioversion if unstable |
| Asystole | Flatline | No | No | CPR + epi + reversible causes |
| PEA | Organized electrical activity | No | No | CPR + epi + reversible causes |
High-Yield Add-On: The Reversible Causes You Should Think About
When the rhythm is PEA/asystole, you hunt H’s and T’s. VF is often ischemic, but once you’re in arrest mode, Step questions may ask what to correct to prevent recurrence.
H’s:
- Hypovolemia
- Hypoxia
- Hydrogen ion (acidosis)
- Hypo-/hyperkalemia
- Hypothermia
T’s:
- Tension pneumothorax
- Tamponade
- Toxins
- Thrombosis (pulmonary)
- Thrombosis (coronary)
Common VF trigger on exams: acute MI (coronary thrombosis) → ischemia → ventricular arrhythmia.
Exam-Winning Takeaways (What to Remember Under Time Pressure)
- VF = chaotic ECG + no pulse → defibrillate (unsynchronized) + CPR
- Synchronized cardioversion is for unstable tachyarrhythmias with a pulse
- Adenosine is for stable, regular narrow-complex SVT, not arrest rhythms
- Amiodarone/epi are important in ACLS, but they’re not the first move for VF when “next step” is asked
- Always anchor on two questions:
- Is there a pulse?
- Is the rhythm shockable (VF/pVT) or non-shockable (PEA/asystole)?
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
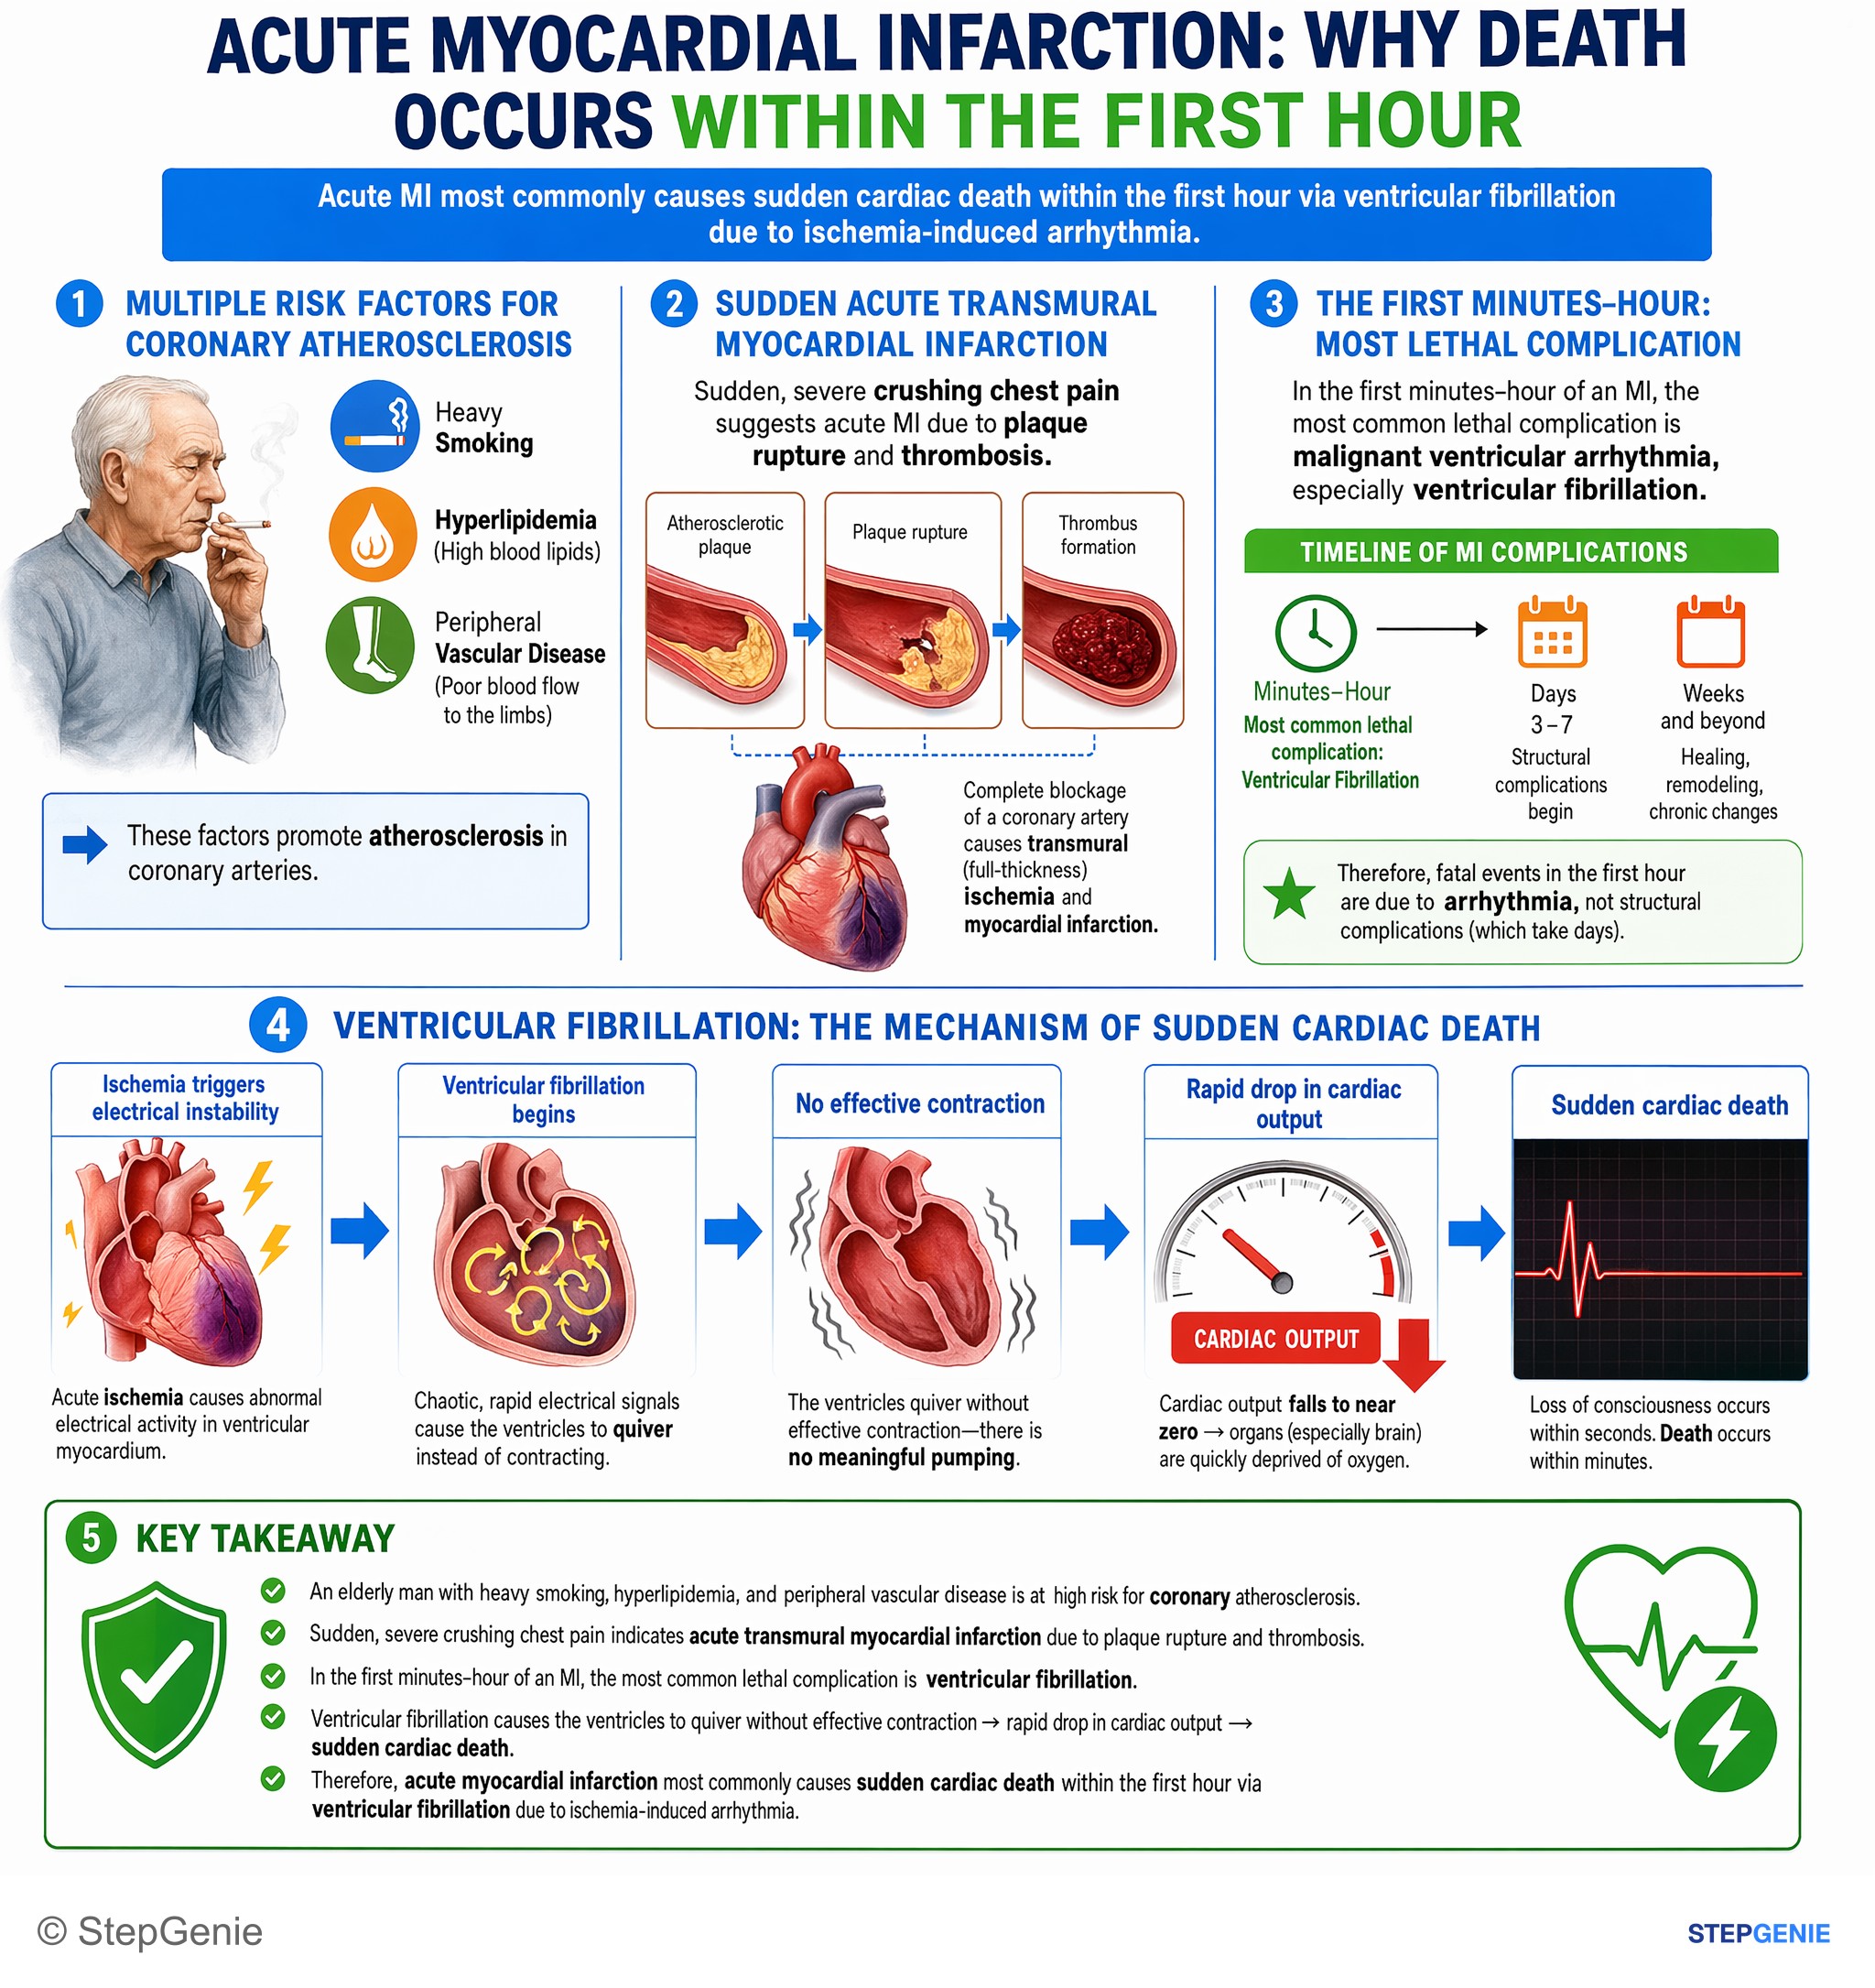
Acute myocardial infarction most commonly causes sudden cardiac death within the first hour via ventricular fibrillation due to…
USMLE Step 2Frequently Asked Questions
What ECG pattern points to ventricular fibrillation instead of another arrest rhythm?
Ventricular fibrillation shows a chaotic, irregular waveform with no identifiable P waves or QRS complexes. That pattern reflects disorganized ventricular electrical activity rather than any coordinated rhythm. VF can be coarse or fine, and fine VF may mimic asystole, so recognizing the lack of organized complexes is critical when interpreting an arrest rhythm.
Why does ventricular fibrillation cause no pulse?
Ventricular fibrillation causes no pulse because the ventricles are firing in a completely disorganized way and do not contract effectively. Without coordinated ventricular contraction, there is zero effective cardiac output. Blood is not pumped forward, so the patient becomes pulseless even though electrical activity is still present on the monitor.
What is the next best step for pulseless ventricular fibrillation?
The next best step is immediate unsynchronized defibrillation with CPR. VF is a shockable rhythm, and early shock is the definitive treatment because it simultaneously depolarizes a critical mass of myocardium and can reset cardiac electrical activity. In exam-style questions, when the patient is pulseless and in VF with no interventions yet, shock and compressions come before medications.
How do you tell defibrillation from synchronized cardioversion in a rhythm question?
Use defibrillation when the patient has no pulse and the rhythm is VF or pulseless VT, and use synchronized cardioversion when a pulse is present but the patient is unstable. Synchronized cardioversion requires an organized QRS complex so the shock can be timed to the R wave. In VF there are no identifiable QRS complexes, so synchronization is not possible.
Why isn’t amiodarone or epinephrine the first move in ventricular fibrillation?
Amiodarone and epinephrine are not the first move because defibrillation and CPR come first in VF. Amiodarone is used for refractory VF or pulseless VT after defibrillation and CPR, while epinephrine is an adjunct during cardiac arrest to improve coronary and cerebral perfusion pressure during compressions. Neither replaces the need for immediate shock in an untreated shockable rhythm.