A good Q-bank question on atrial fibrillation (AF) doesn’t just test whether you can recognize an irregularly irregular rhythm—it tests whether you can not get baited by look-alikes, and whether you know what to do next when the patient is stable vs unstable. Let’s break down a classic vignette and make every answer choice teach you something.
Tag: Cardiovascular > ECG Interpretation
The Vignette (Classic Q-Bank Style)
A 72-year-old man with hypertension and type 2 diabetes presents with 2 days of palpitations and mild shortness of breath. He denies chest pain. Vitals: T 37°C, BP 128/76, HR 138/min, RR 18, SpO₂ 97% on room air. Exam shows an irregular pulse. ECG shows:
- Narrow QRS complexes
- Irregularly irregular R-R intervals
- No consistent P waves; baseline appears “wavy”
Which of the following is the most likely diagnosis?
A. Atrial fibrillation
B. Atrial flutter
C. Multifocal atrial tachycardia
D. Ventricular tachycardia
E. Sinus rhythm with premature atrial contractions
Correct Answer: Atrial fibrillation
Why it’s AF (ECG “must-haves”)
AF is defined by:
- Irregularly irregular rhythm (no repeating pattern)
- Absent organized P waves
- Fibrillatory baseline (may be subtle)
- Usually narrow QRS unless preexisting bundle branch block or aberrancy
What’s going on physiologically?
- Chaotic atrial activation (often from triggers near pulmonary veins) → atria quiver instead of contracting effectively
- AV node conducts impulses variably → irregular ventricular response
- Loss of atrial kick can worsen symptoms, especially in older patients or those with diastolic dysfunction
High-yield next steps (USMLE-style management)
Management hinges on hemodynamic stability and duration.
1) Decide if unstable
Unstable AF = hypotension, altered mental status, ischemic chest pain, acute heart failure/pulmonary edema, shock → synchronized cardioversion.
2) If stable: rate vs rhythm + anticoagulation
- Rate control (common initial move):
- β-blocker (e.g., metoprolol) or non-DHP CCB (diltiazem/verapamil)
- Add digoxin sometimes in HFrEF or sedentary patients (less effective during exertion)
- Rhythm control (select patients): cardioversion, ablation, antiarrhythmics (e.g., amiodarone in structural heart disease)
- Anticoagulation: based on stroke risk
- Use CHA₂DS₂-VASc (Step 2 loves this)
CHA₂DS₂-VASc (know it cold)
| Risk factor | Points |
|---|---|
| Congestive heart failure | 1 |
| Hypertension | 1 |
| Age ≥75 | 2 |
| Diabetes mellitus | 1 |
| Stroke/TIA/thromboembolism | 2 |
| Vascular disease (MI/PAD/aortic plaque) | 1 |
| Age 65–74 | 1 |
| Sex category (female) | 1 |
Anticoagulate most patients with score ≥2 (and many with ≥1 depending on sex-specific thresholds and current guidelines). On exams, if stroke risk is meaningfully elevated, anticoagulation is usually the teaching point.
Cardioversion timing rule (high yield)
- If AF duration >48 hours or unknown:
- Anticoagulate for 3 weeks before cardioversion OR perform TEE-guided cardioversion (if no atrial thrombus)
- Then anticoagulate 4 weeks after cardioversion
- If <48 hours: cardioversion can be performed with periprocedural anticoagulation depending on stroke risk and scenario
Systematically Destroying the Distractors
B. Atrial flutter
How it tries to fool you: can also present with palpitations and tachycardia and may look “busy” on ECG.
Key ECG distinction
- Flutter waves (“sawtooth”), best in II, III, aVF
- Atrial rate ~250–350/min
- Ventricular response often regular with a fixed conduction ratio (e.g., 2:1 → ventricular rate ~150)
Quick compare: AF vs flutter
| Feature | Atrial fibrillation | Atrial flutter |
|---|---|---|
| Rhythm | Irregularly irregular | Often regular (fixed block) |
| Baseline | Fibrillatory, chaotic | Sawtooth flutter waves |
| Atrial activity | Disorganized | Organized macro-reentry |
Exam trap: “Sawtooth + regular ~150” = flutter with 2:1 block until proven otherwise.
C. Multifocal atrial tachycardia (MAT)
How it tries to fool you: irregular rhythm and tachycardia can mimic AF.
Key ECG distinction
- Irregularly irregular, BUT you still see distinct P waves
- At least 3 different P-wave morphologies
- Variable PR intervals
Clinical association (Step 2 favorite)
- Strongly linked to COPD exacerbation, hypoxemia, theophylline use
- Treat by correcting underlying cause (oxygenation, electrolytes), sometimes verapamil
Rule of thumb:
If it’s irregular and you can clearly identify multiple different P waves → think MAT, not AF.
D. Ventricular tachycardia (VT)
How it tries to fool you: tachycardia + palpitations; sometimes “wide-complex tachycardia” appears in similar question stems.
Key ECG distinction
- Wide QRS (usually ≥120 ms)
- Often regular rhythm
- AV dissociation, fusion beats, capture beats may be present
High-yield clinical reasoning
- In adults, especially with structural heart disease, wide-complex tachycardia = VT until proven otherwise.
Why this isn’t VT here: the vignette gives narrow QRS and an irregularly irregular rhythm—classic AF with rapid ventricular response (RVR).
E. Sinus rhythm with premature atrial contractions (PACs)
How it tries to fool you: “irregular rhythm” on exam or pulse; PACs can create irregularity.
Key ECG distinction
- Underlying sinus rhythm is present
- Normal P waves precede most QRS complexes
- Occasional early beat with an abnormal P wave morphology
- Often followed by a noncompensatory pause
How to not get tricked:
PACs create intermittent irregularity; AF creates continuous irregularly irregular rhythm with no consistent P waves.
Rapid Recognition: AF vs Look-Alikes (Exam-Speed Checklist)
If the rhythm is irregular…
Ask:
- Are there organized P waves?
- No → AF
- Yes → consider MAT (≥3 morphologies) or PACs
- Is it sawtooth?
- Yes → atrial flutter
- Is the QRS wide?
- Yes → treat as VT until proven otherwise
High-Yield AF Facts USMLE Loves
Causes/associations (think “atrial stretch + triggers”)
- HTN, CAD, mitral valve disease (esp. mitral stenosis), heart failure
- Hyperthyroidism
- Alcohol (“holiday heart”)
- Obstructive sleep apnea
- Post-op (esp. cardiac surgery)
- Pulmonary disease (can overlap with MAT)
Major complication: stroke
- Thrombus formation in left atrial appendage
- Embolic stroke risk drives anticoagulation decisions
Rate control meds: what to pick when
- β-blocker / diltiazem: first-line if stable
- Amiodarone: can help with rhythm control; useful in HFrEF when other agents limited
- Avoid AV nodal blockers in AF + WPW
- If AF with WPW: use procainamide or ibutilide; unstable → cardioversion
- Why: blocking AV node can force conduction down accessory pathway → VF
Takeaway
Atrial fibrillation is more than “irregularly irregular.” On test day, the win is distinguishing it from flutter (sawtooth/regular), MAT (≥3 P morphologies, COPD), VT (wide-complex, treat as VT), and PACs (sinus rhythm with occasional early atrial beats). If you can explain why each distractor is wrong, you’ll almost never miss an AF ECG question again.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
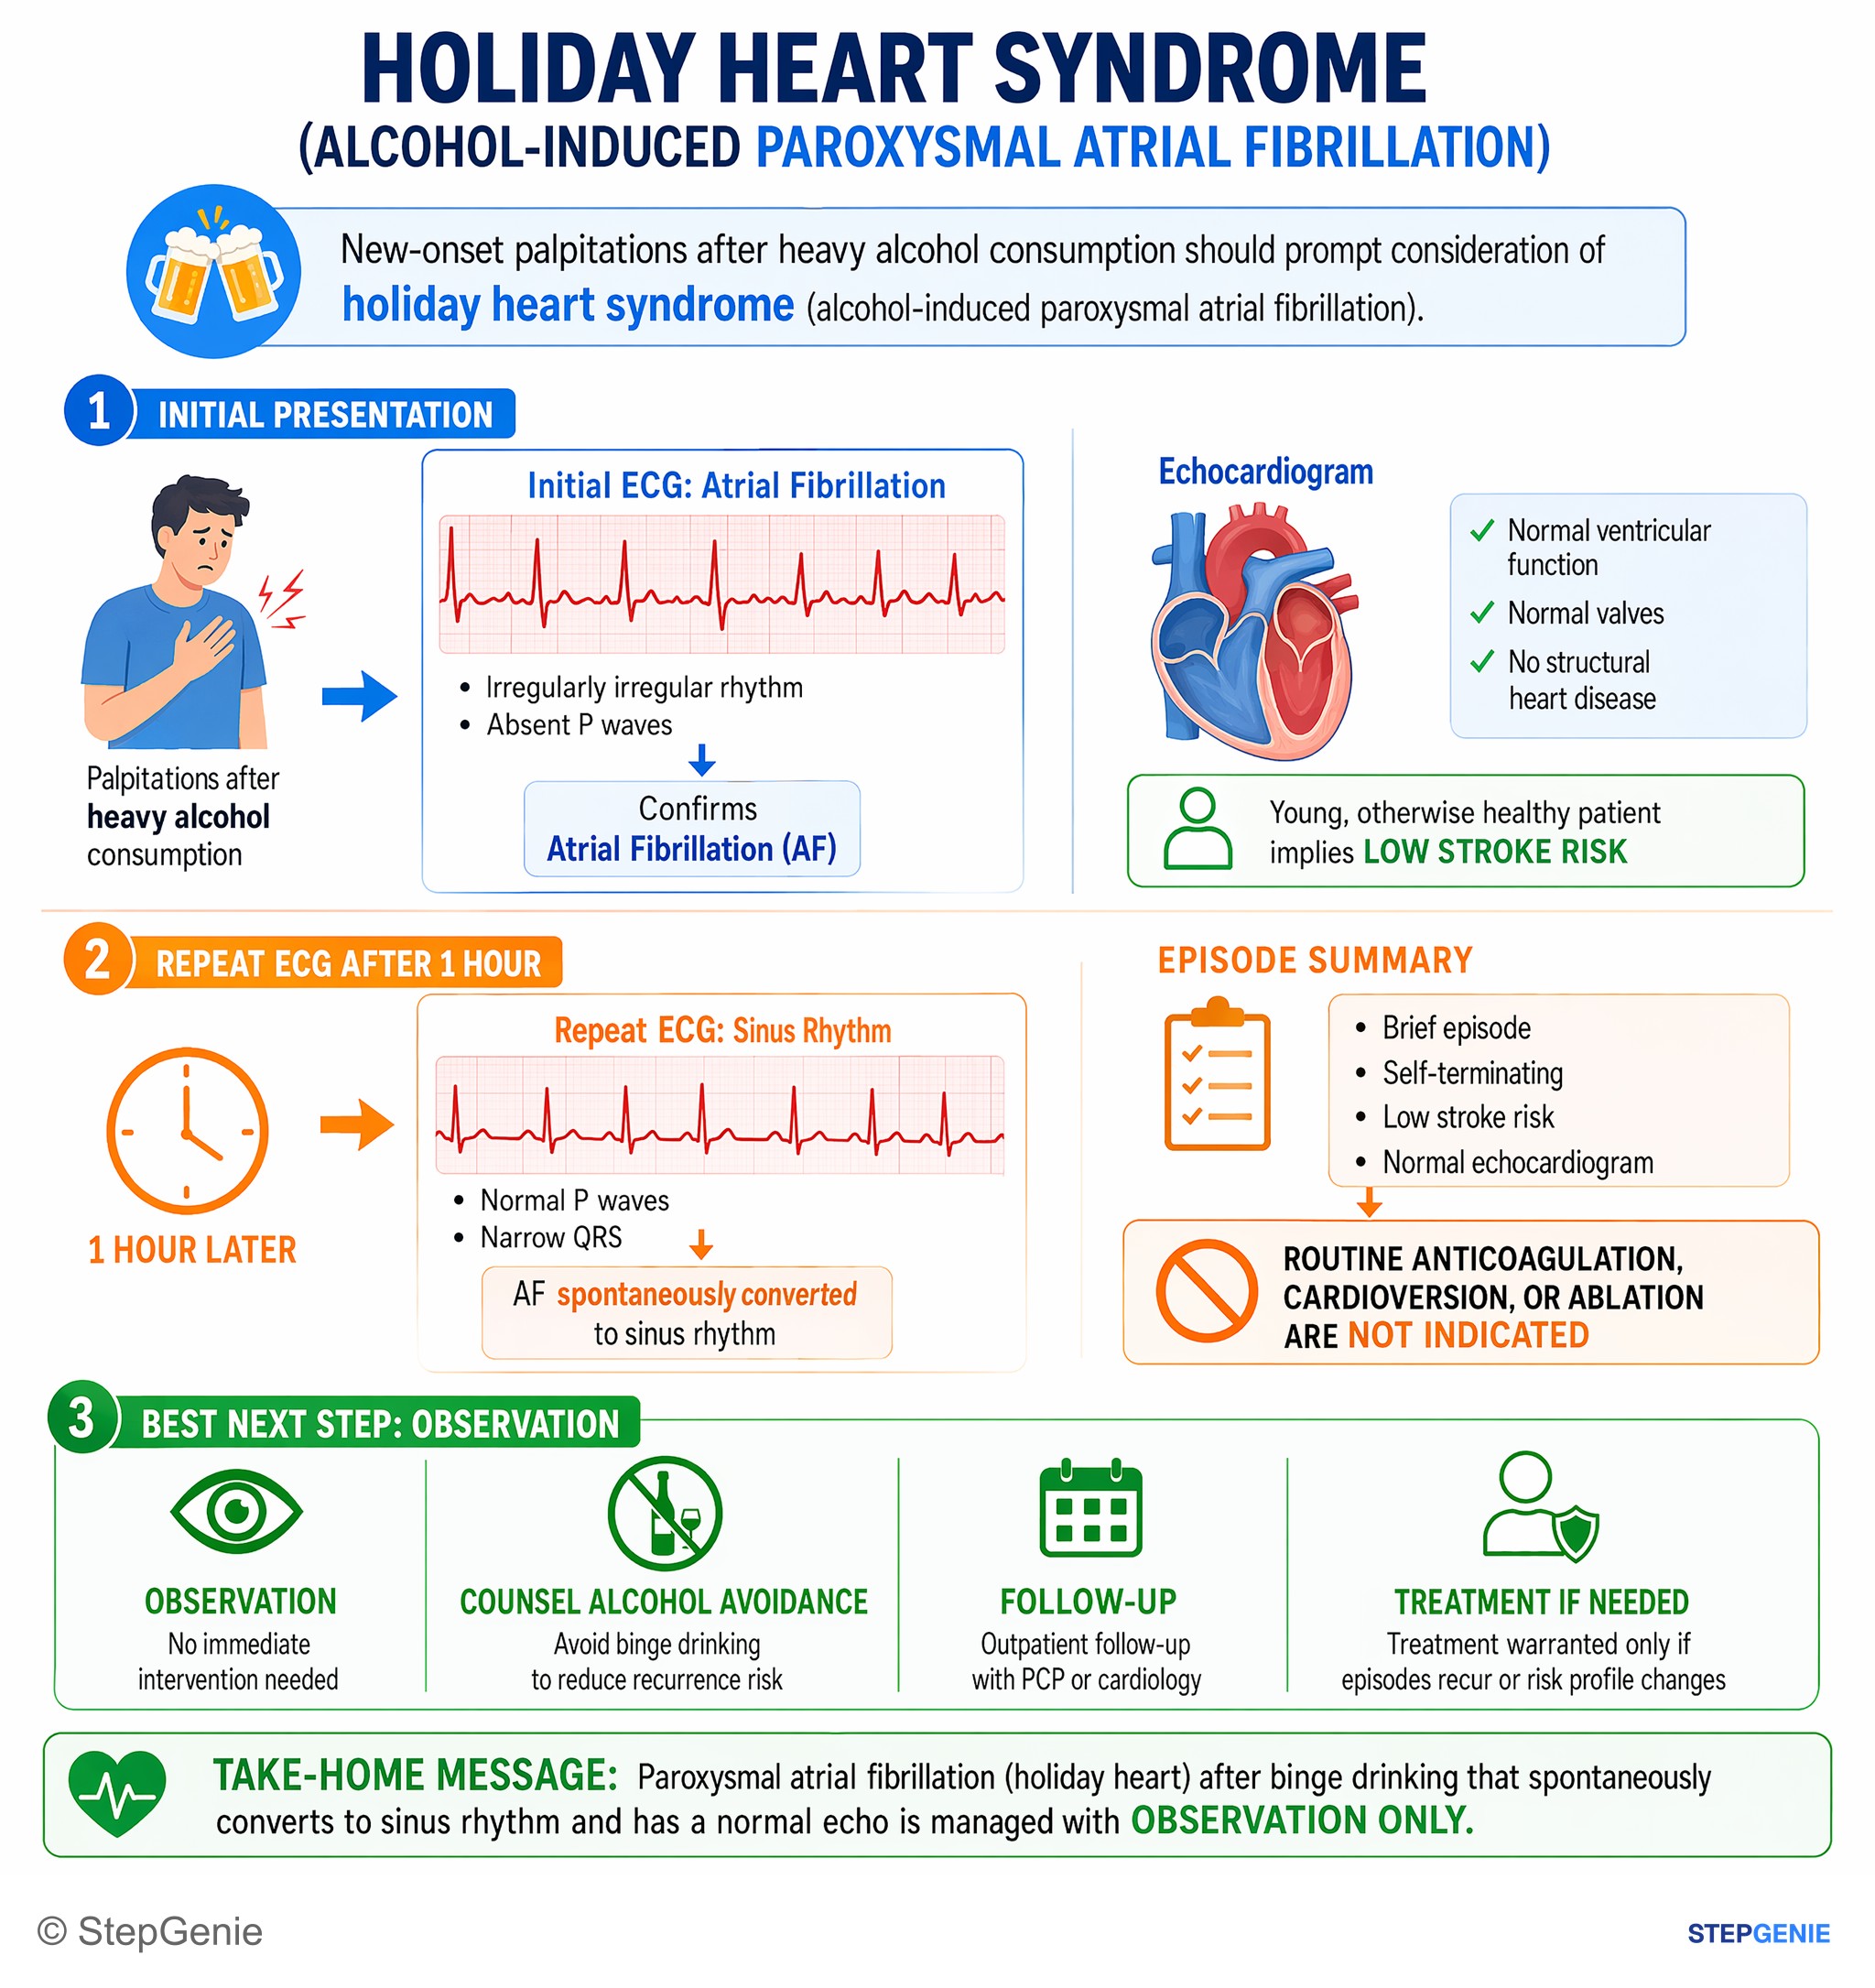
Paroxysmal atrial fibrillation (holiday heart) after binge drinking that spontaneously converts to sinus rhythm and has normal echo is…
USMLE Step 2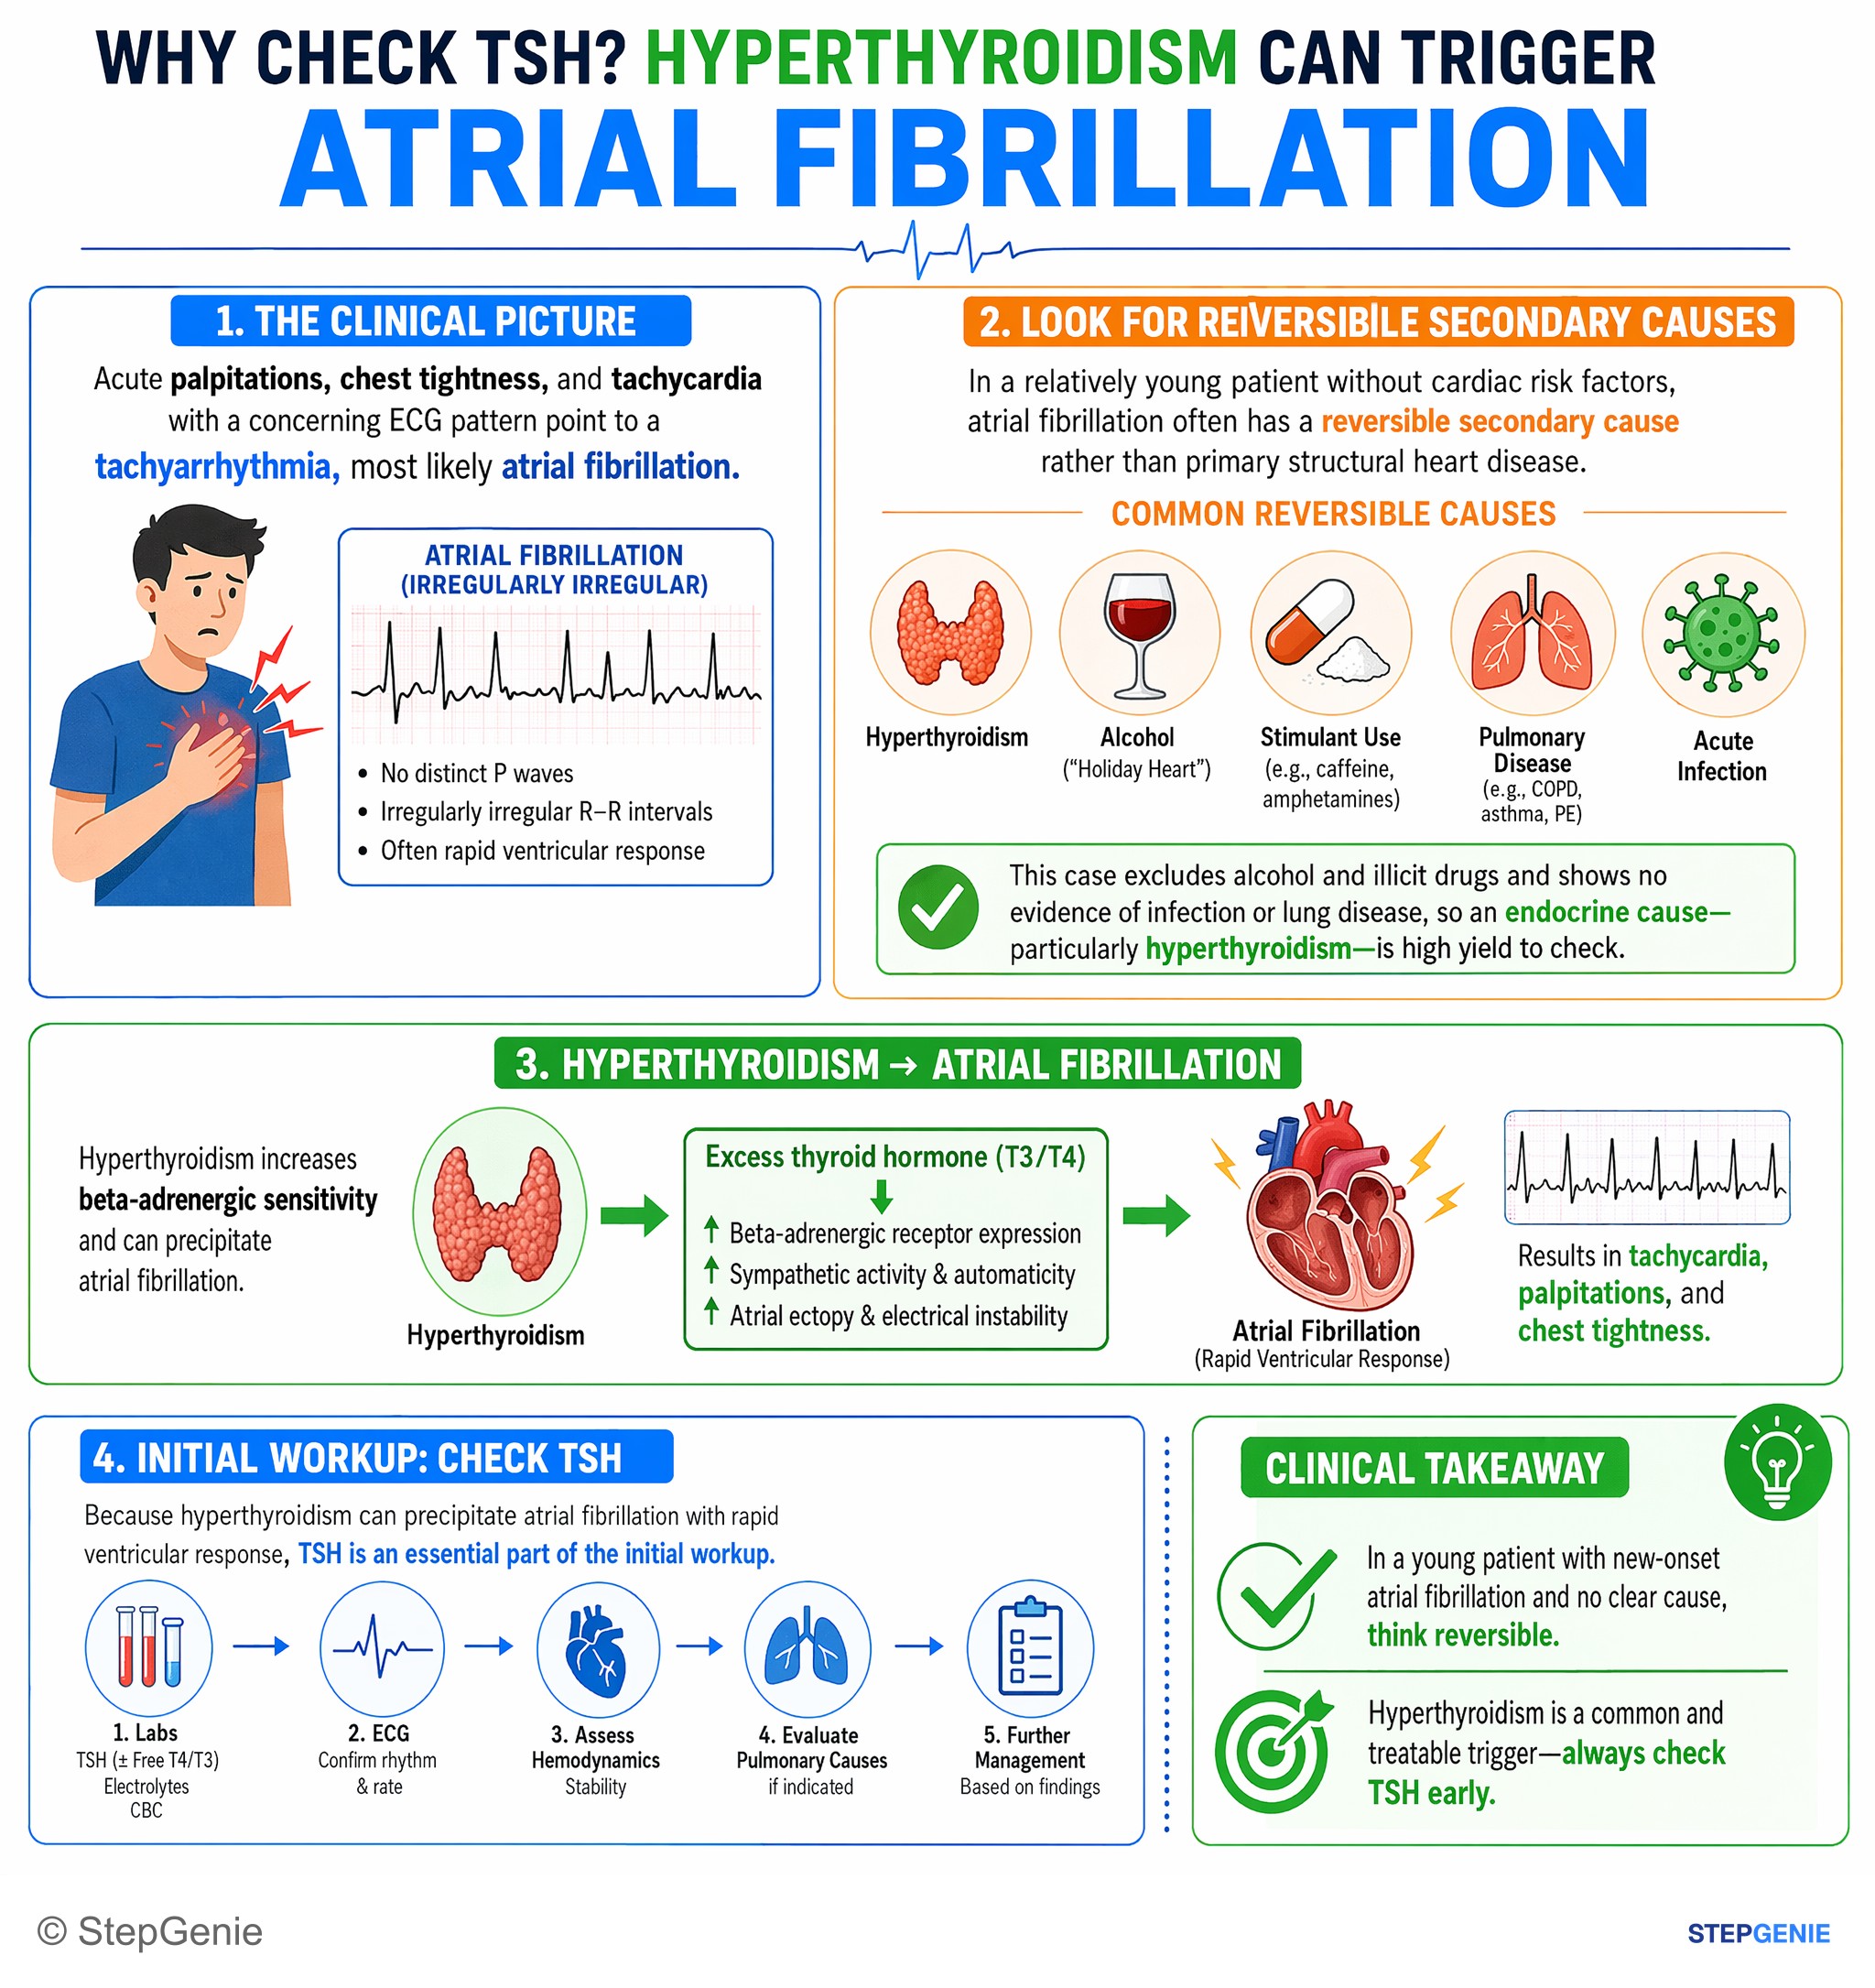
Atrial fibrillation with rapid ventricular response can be precipitated by hyperthyroidism; initial workup includes checking TSH levels.
USMLE Step 2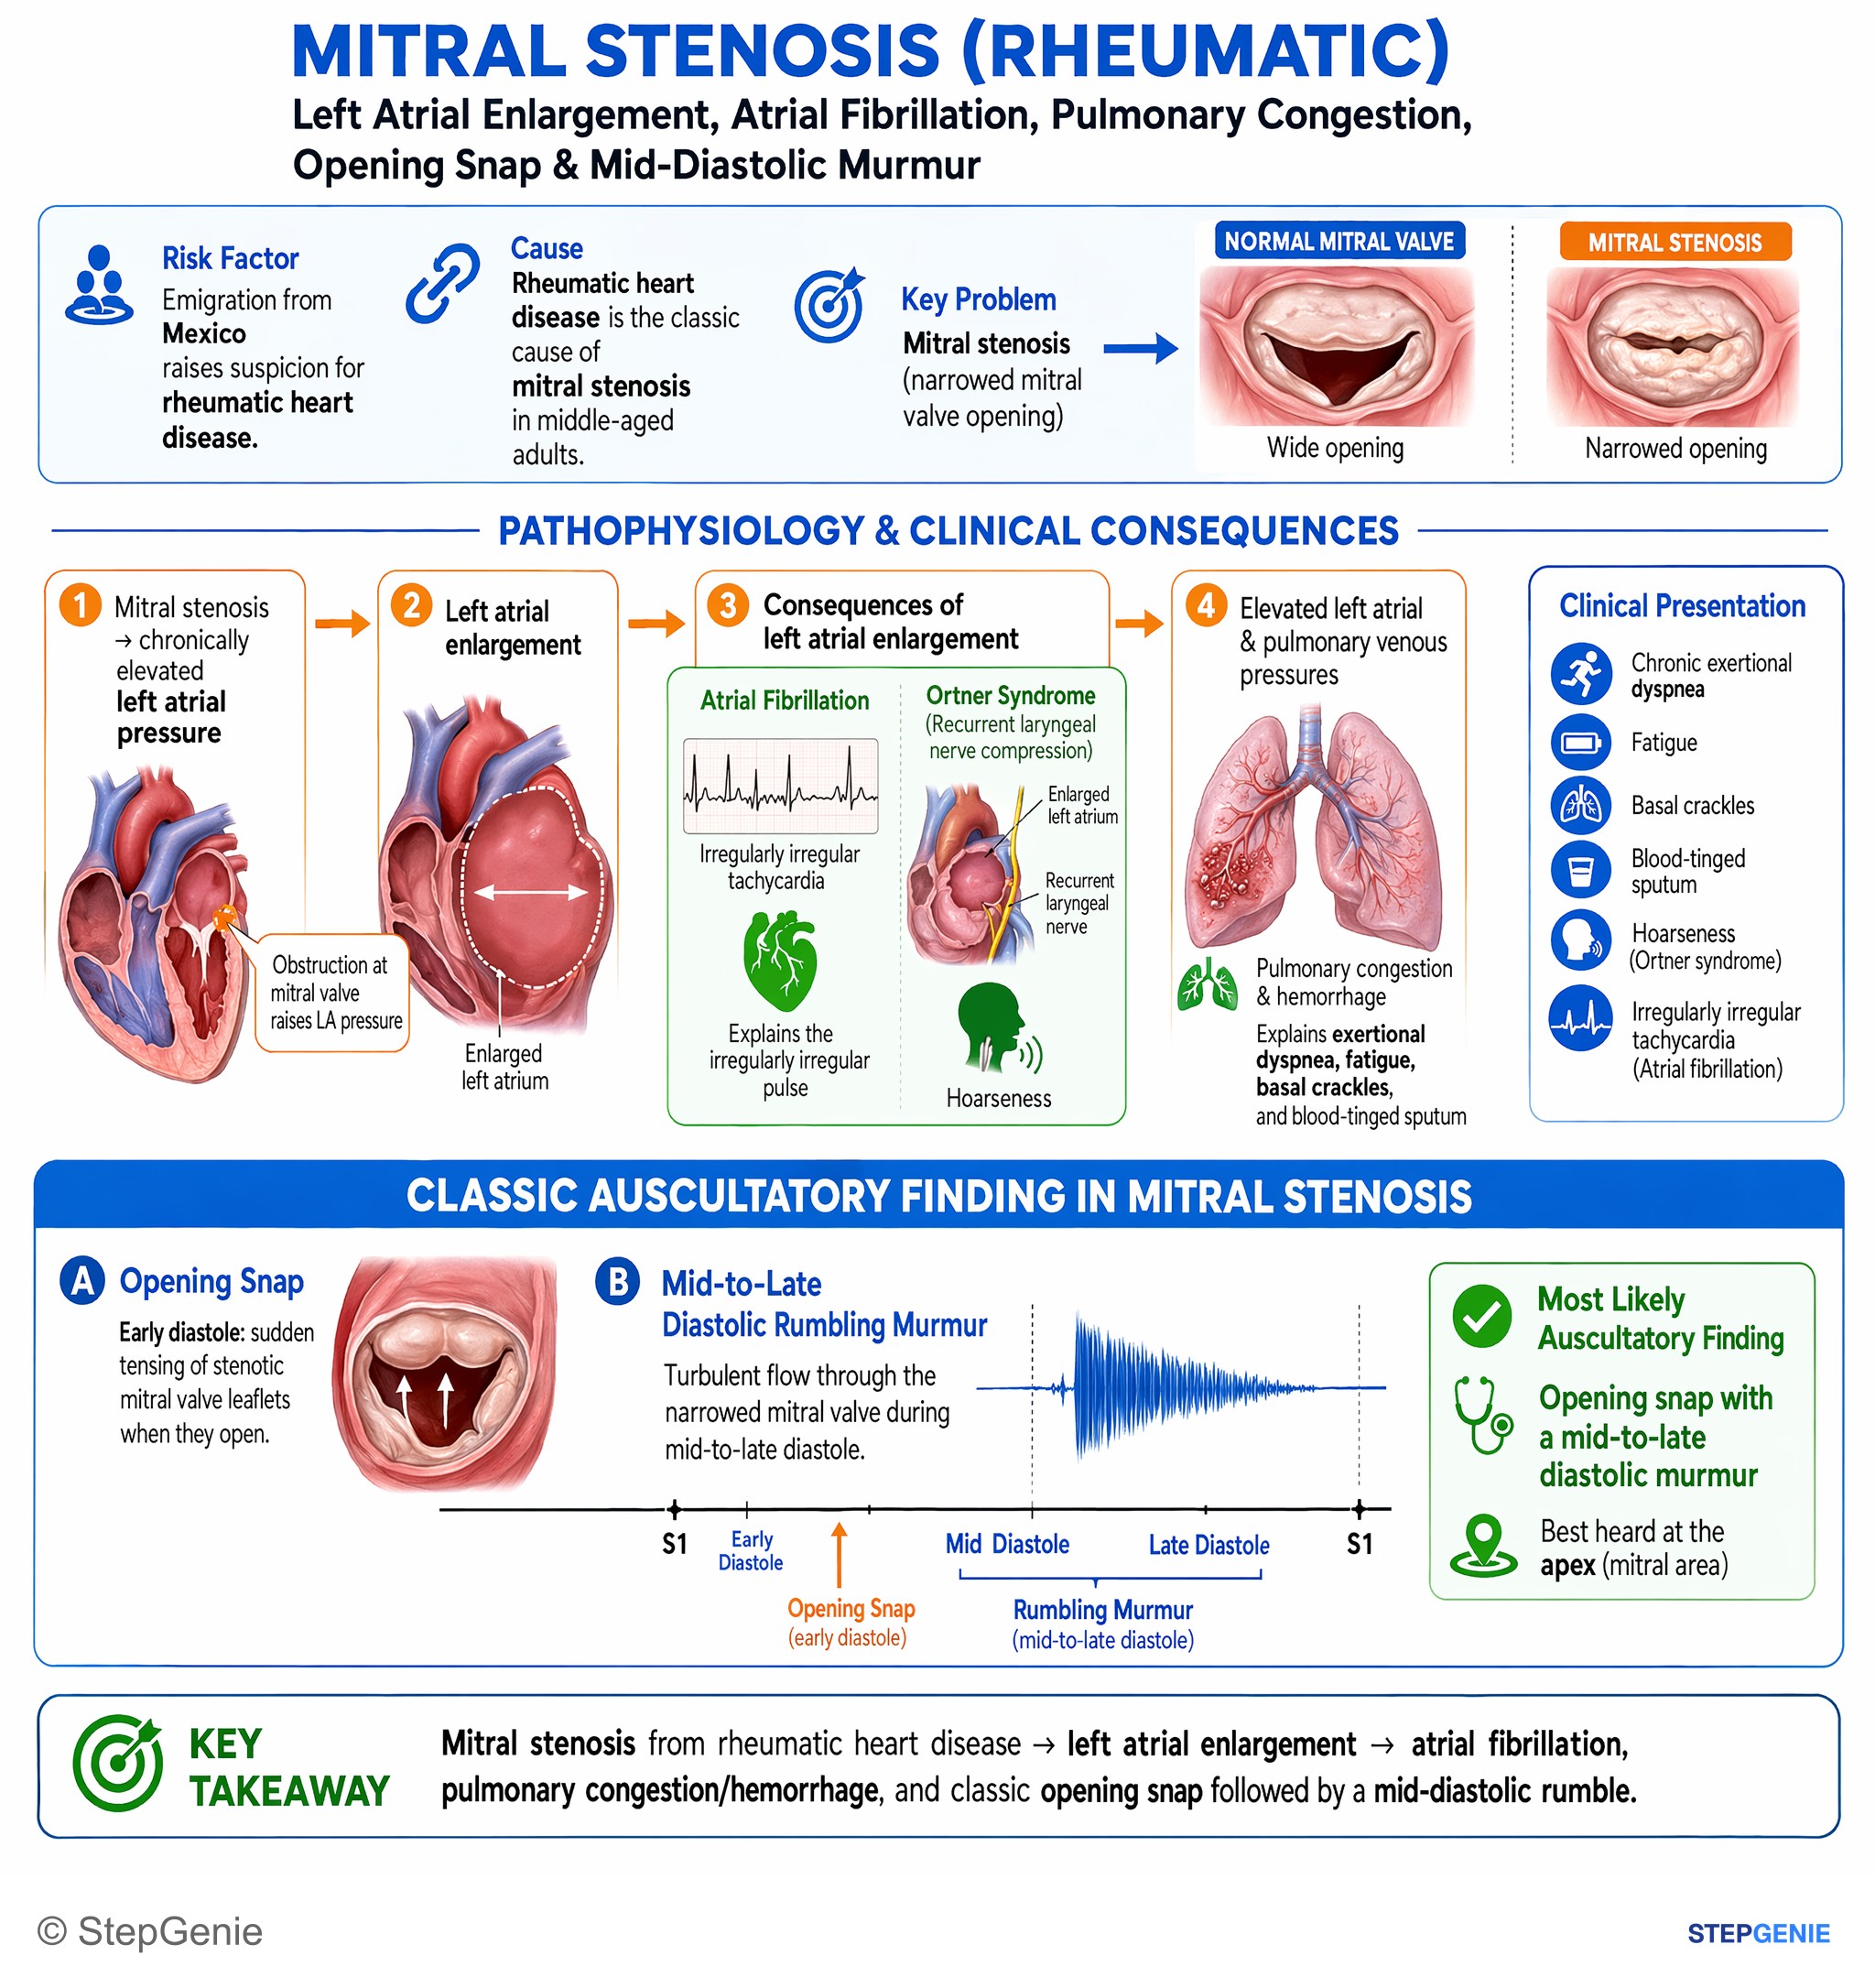
Mitral stenosis from rheumatic heart disease → left atrial enlargement, atrial fibrillation, pulmonary congestion; classic opening snap +…
USMLE Step 1Frequently Asked Questions
How do you recognize atrial fibrillation on ECG?
Atrial fibrillation is recognized by an irregularly irregular rhythm with no consistent P waves and a fibrillatory or wavy baseline. The QRS is usually narrow unless there is a preexisting bundle branch block or aberrant conduction. On exam questions, the combination of irregular R-R intervals plus absent organized P waves is the key clue that points to AF.
How do you tell atrial fibrillation from atrial flutter on an ECG?
Atrial fibrillation is usually irregularly irregular, while atrial flutter often has a regular ventricular response with a fixed conduction ratio. Flutter also shows classic sawtooth flutter waves, especially in leads II, III, and aVF, and the atrial rate is typically around 250 to 350 per minute. A regular rate near 150 with sawtooth waves strongly suggests flutter with 2:1 block rather than AF.
How do you tell multifocal atrial tachycardia from atrial fibrillation?
Multifocal atrial tachycardia is distinguished from atrial fibrillation by the presence of distinct P waves. MAT is also irregularly irregular, but it shows at least three different P-wave morphologies and variable PR intervals. Atrial fibrillation, in contrast, has no organized P waves. A strong clinical clue for MAT is a COPD exacerbation, hypoxemia, or theophylline use.
What do you do first for stable vs unstable atrial fibrillation?
The first step is to decide whether the patient is hemodynamically stable. Unstable atrial fibrillation, such as with hypotension, altered mental status, ischemic chest pain, acute heart failure or pulmonary edema, or shock, requires synchronized cardioversion. If the patient is stable, initial management commonly focuses on rate control with a beta-blocker or a non-dihydropyridine calcium channel blocker, while also considering rhythm control and anticoagulation.
When do you need anticoagulation around cardioversion for atrial fibrillation?
If atrial fibrillation has lasted more than 48 hours or the duration is unknown, anticoagulate for 3 weeks before cardioversion or use TEE-guided cardioversion if no atrial thrombus is seen. Anticoagulation is then continued for 4 weeks after cardioversion. If AF is present for less than 48 hours, cardioversion can be performed with periprocedural anticoagulation depending on stroke risk and the clinical scenario.