A venous return curve plots venous return against right atrial pressure (RAP): flow falls as RAP rises, reaches zero at the mean systemic filling pressure (x-intercept, about 7 mmHg in Guyton's dogs) and levels off below 0 mmHg as the great veins collapse. Volume and venous tone shift the curve; resistance changes its slope.
Draw the cardiac function (Frank-Starling) curve on the same axes and the two cross at the steady-state operating point, normally about 5 L/min at a RAP near 0 mmHg. Exam questions move one or both curves and ask where the new crossing lies.
The graph comes from Arthur Guyton's animal experiments in the 1950s and 1960s. Critics argue that cardiac output sets RAP rather than the reverse, yet some, such as Brengelmann, still plot the same curve (Levy's "vascular function curve") to find the steady state, so exam answers do not change.
Venous return curve: axes, equation and three landmarks
The x-axis is RAP, which is essentially the same as central venous pressure. The y-axis is venous return, which equals cardiac output (CO) at steady state because the circulation is a closed loop. Klabunde calls it the systemic vascular function curve.
In Guyton's model:
where MSFP is the mean systemic filling pressure and RVR the resistance to venous return. The driving gradient is under 10 mmHg, so a few mmHg matter: in animals with reflexes blocked, each 1 mmHg rise in RAP cut venous return by about 14%.
| Landmark | What it is | What moves it |
|---|---|---|
| x-intercept | MSFP: the pressure throughout the circulation once flow stops | Blood volume and venous tone |
| Slope | −1/RVR: the steeper the curve, the lower the RVR | Resistance to venous return (veins count far more than arterioles) |
| Plateau | Flow limit as the great veins collapse below about 0 mmHg | Falls when RVR rises; moves with the pressure around the veins |
Venous return chart: what shifts each curve
| Change | Example | Venous return curve | Cardiac function curve | New steady state |
|---|---|---|---|---|
| ↑ Blood volume | Transfusion, IV fluids, renal salt and water retention | Parallel shift right (MSFP ↑) | No change | CO ↑, RAP ↑ |
| ↓ Blood volume | Hemorrhage, dehydration | Parallel shift left (MSFP ↓) | No change | CO ↓, RAP ↓ |
| ↑ Venous tone | Sympathetic venoconstriction | Shift right (MSFP ↑) | No change | CO ↑, RAP ↑ |
| ↓ Venous tone | Nitroglycerin, loss of sympathetic tone, anaphylaxis | Shift left (MSFP ↓) | No change | CO ↓, RAP ↓ |
| ↑ Arteriolar resistance (TPR) | Arteriolar constriction | Flatter, same MSFP | Down (more afterload) | CO ↓; RAP changes little |
| ↓ Arteriolar resistance | Hydralazine | Steeper, same MSFP | Up slightly (less afterload) | CO ↑; RAP changes little |
| Arteriovenous fistula | Large dialysis fistula | Much steeper, same MSFP, higher plateau | Up slightly (less afterload) | CO ↑ (high-output state) |
| ↑ Contractility or heart rate | Cardiac sympathetic stimulation, dobutamine | No change | Up and left | CO ↑ modestly, RAP ↓ |
| ↓ Contractility | Systolic heart failure, large MI | No change at first | Down and right | CO ↓, RAP ↑ |
Three rules generate the whole chart:
- Volume and venous tone move the x-intercept (parallel shifts).
- Resistance tilts the curve around a fixed MSFP. TPR is also afterload, so it moves the cardiac curve too: CO moves opposite to TPR.
- Contractility, heart rate and afterload move the cardiac curve. A pure inotrope slides the operating point up and to the left.
Mean systemic filling pressure: what sets it and real values
MSFP is the pressure the systemic circulation settles at when flow stops; Guyton fibrillated the heart and pumped blood from arteries to veins so pressures equalized in less than 7 seconds. The mean circulatory filling pressure, which includes the heart and lungs, is almost the same.
MSFP sits near venous, not arterial, pressure. Veins are about 10–20 times more compliant than arteries (one review says 40 times) and hold about 70% of the blood volume, so when the heart stops, arterial pressure falls at least 10-fold more than venous pressure rises.
Only the stressed volume, the blood that actually stretches vessel walls, creates this pressure:
The unstressed volume just fills the vessels. The stressed share is small: about 15% of blood volume in Guyton-school data with reflexes blocked, about 25–30% in recent reviews. So MSFP is sensitive: with reflexes blocked, losing 15% of blood volume (about 1 L in an adult) drops MSFP from 7 to 0 mmHg. Venoconstriction recruits unstressed into stressed volume, and sympathetic activity alone spans MSFP from about 5 mmHg (complete sympathetic inhibition) to 18 mmHg or more (maximal stimulation).
| Setting | MSFP |
|---|---|
| Dogs with reflexes blocked, normal volume (Guyton) | About 7 mmHg |
| Klabunde's textbook value (heart fibrillated, baroreflex blocked) | About 8 mmHg |
| Anesthetized patients, 7.5 seconds into induced ventricular fibrillation | 10.2 ± 3.5 mmHg |
| ICU patients, 1 minute after death | 12.8 ± 5.6 mmHg (higher in those on norepinephrine) |
| Ventilated patients after cardiac surgery (extrapolated) | 18.8 ± 4.5 mmHg |
| Cardiac surgery and septic shock patients | 15–33 mmHg |
Human numbers are rough: in 82 patients, arterial and central venous pressures were still about 13 mmHg apart after about 13 seconds of induced fibrillation, and bedside extrapolations may overestimate MSFP. Use about 7 mmHg as the textbook number.
TPR and resistance to venous return: slope, not intercept
Raising RVR flattens the curve and lowers its plateau without moving MSFP; lowering RVR steepens it and raises the plateau.
The exam rule: arteriolar constriction (↑ TPR) flattens the venous return curve and, through afterload, pulls the cardiac function curve down, so CO falls; arteriolar dilation does the reverse. MSFP barely changes because total vascular compliance is mostly venous. RAP changes little and its direction varies: in Klabunde's analysis an arterial dilator raises RAP when the heart is normal (blood shifts to the venous side) but lowers it in ventricular failure, where the afterload effect dominates.
What the physiology adds:
- Arterioles count less than veins. Guyton weighted each resistance by the capacitance of its segment. In Young's calculation, adding resistance equal to 20% of the total to the arteries cuts venous return by about 6%; adding the same amount to the veins cuts it by about 53%. Maximal sympathetic stimulation raises RVR by only about 20%.
- Real vasopressors also constrict veins. Phenylephrine raises preload and afterload and slows the heart reflexly, so its effect on CO varies. Norepinephrine recruits unstressed volume and raises MSFP, yet after cardiac surgery a higher dose lowered CO in about half of patients because RVR rose more than MSFP.
Why the venous return curve plateaus
When RAP falls below the pressure around the great veins, they collapse, and further falls in RAP add no flow (a "vascular waterfall"). With the chest closed, the curve bends between about −2 and −4 mmHg and is flat below −4 mmHg, at roughly 20–30% above normal flow; with the chest open, the plateau starts at 0 mmHg.
- A stronger heart alone barely raises CO. It pulls RAP toward the plateau: strong sympathetic stimulation of the heart alone leaves CO slightly higher or unchanged while RAP falls. Large rises need the venous return curve to move (more volume, venoconstriction or arteriolar dilation).
- Heart rate alone does not set CO. In Guyton's dogs, pacing the heart faster did not change CO until an aortocaval fistula raised venous return.
Cardiac function curve and the operating point
The cardiac function curve is a Frank-Starling curve with CO, not stroke volume, on the y-axis and RAP, now the independent variable, on the x-axis. It is steep near the normal point (raising filling pressure from normal to 1–2 mmHg can double output) and flattens once the muscle fibers reach their most effective length. The heart's side is covered in the Frank-Starling mechanism flowchart and the pressure-volume loop mnemonic.
- Up and left: more inotropy, faster heart rate (up to about 80–100% above normal; beyond that, filling time falls) and less afterload.
- Down and right: systolic dysfunction, slower heart rate and more afterload. In severe failure the curve is nearly flat at high filling volumes.
- Right, from pressure outside the heart: an open chest, positive-pressure breathing and tamponade (which also flattens the curve) mean a higher RAP is needed for the same output.
The crossing point is the only CO and RAP that suit both heart and vessels; any mismatch between output and return is quickly corrected.
Worked shifts: hemorrhage, transfusion, heart failure, inotropes, exercise and more
Hemorrhage. Losing stressed volume lowers MSFP (parallel left shift): CO and RAP fall. The baroreceptor reflex then constricts veins, recruiting unstressed volume, constricts arterioles and speeds and strengthens the heart; CO recovers only partly until blood and fluids restore MSFP.
Transfusion or a fluid bolus. The curve shifts right: CO and RAP rise. The gain fades over minutes to hours as stretched vessels relax and fluid leaves the capillaries. On the flat part of the cardiac curve, fluid raises RAP as much as MSFP, and CO does not change.
Systolic heart failure. The cardiac curve shifts down and right: CO falls and RAP rises. Salt and water retention, venoconstriction and arteriolar constriction then shift the venous return curve right and flatten it, partly restoring CO but only by raising venous pressures, which drives pulmonary and systemic edema (see Starling forces). Once the operating point reaches the plateau, more volume only raises RAP. Treatment lifts the cardiac curve (inotropes, afterload reduction) or shifts the venous return curve left (diuretics, venodilators); the extreme is cardiogenic shock.
Positive inotropes. The cardiac curve moves up and left along an unchanged venous return curve: CO rises modestly and RAP falls. Dobutamine also dilates veins, but its inotropic effect dominates; in a failing heart, raising contractility restores output far more.
Exercise. Both curves move. Contracting limb and abdominal muscles squeeze the veins and can more than double MSFP at once; venoconstriction adds to it; metabolic dilation in working muscle (up to 15 times resting flow) lowers RVR; and sympathetic drive lifts the cardiac curve. In Young's model of maximal exercise in an untrained adult, CO reaches about 20 L/min at a RAP near 2 mmHg.
Arteriovenous fistula. Blood bypasses arteriolar and capillary resistance, so RVR falls: the curve steepens around the same MSFP, its plateau rises and CO rises. Over time, renin-angiotensin-aldosterone activation retains salt and water, raising MSFP: high-output heart failure, with warm extremities and a wide pulse pressure.
Sepsis. Venodilation and capillary leak lower MSFP (left shift); arteriolar dilation lowers RVR and afterload, which helps explain the hyperdynamic phase; septic cardiomyopathy can flatten the cardiac curve.
Breathing, positive-pressure ventilation, Valsalva and posture
- Spontaneous inspiration lowers RAP by several mmHg while abdominal venous pressure may rise, so venous return transiently increases; expiration does the opposite.
- Positive-pressure ventilation and PEEP raise RAP but also raise MSFP (the mechanism is debated). In anesthetized patients, raising airway pressure from 0 to 15 cmH₂O raised RAP from 7.3 to 10.0 mmHg and MSFP from 10.2 to 12.7 mmHg: the gradient held, yet stroke volume fell by about 23%, which reviews read as a rise in RVR. In a pig study, PEEP of 5–10 cmH₂O left flow and RVR unchanged; RVR has been reported to rise only at higher PEEP, probably as the great veins collapse where they join the atrium, and a 2022 review attributes most of the fall in CO at moderate PEEP to right ventricular afterload.
- Pressure around the heart, as in tension pneumothorax or tamponade, also cuts venous return.
- Valsalva maneuver (forced expiration against a closed glottis) compresses the thoracic veins and heart: RAP rises sharply, yet filling falls, so CO and then arterial pressure drop. What this does to murmurs is covered in heart murmur maneuvers.
- Standing up lowers RAP and pools blood in the legs; paradoxically, venous return, CO and arterial pressure fall until the baroreceptor reflex responds. Late pregnancy compressing the vena cava also reduces venous return.
Where physiologists disagree about Guyton's model
- Guyton's reading: MSFP, the elastic recoil of stretched vessels, drives blood toward the heart; RAP is the back pressure; the heart is permissive, pumping what returns.
- The critics: Levy (1979) read RAP purely as a consequence of flow. Brengelmann argues that mean circulatory pressure "has no physical meaning as a driving pressure behind venous return"; in his words, "It is cardiac output that determines central venous pressure in steady states." Beard and Feigl (2011) note that pump output was the causal variable in Guyton's experiments and suggest removing the venous return concept from teaching.
- The defenders: the model's predictions have been reproduced in animals and patients; Berger and Takala report a pig experiment with complete heart bypass that supported RAP as a back pressure, and a 2022 review calls the model the most suitable description of circulatory failure.
- What it means for you: even Brengelmann plots the two curves together to find the steady state; the dispute is over cause and effect. The x-intercept is real (the pressure when flow stops); what critics reject is calling it a pressure that pushes blood.
USMLE traps: classic teaching vs current evidence
| Trap | What's actually true |
|---|---|
| TPR shifts the venous return curve sideways | TPR changes the slope, not MSFP, and moves the cardiac curve through afterload: CO moves opposite to TPR |
| Vasopressors act only on arterioles | Norepinephrine and phenylephrine also constrict veins, which raises MSFP |
| A stronger heart raises CO a lot | Only modestly in a normal circulation; the venous side limits output |
| Heart failure raises MSFP | Pump failure alone raises RAP along the same venous return curve; MSFP rises only with fluid retention or venoconstriction |
| Fluids always raise CO | Not on the flat part of the cardiac curve, where RAP and MSFP rise together |
| MSFP is about 7 mmHg in patients | 7 mmHg comes from dogs with reflexes blocked; ICU estimates run about 13–33 mmHg |
| Valsalva raises RAP, so it raises preload | RAP rises but filling falls, so preload and CO fall |
| PEEP lowers CO only by raising RAP | MSFP rises too; RVR and right ventricular afterload also matter |
More cardiovascular walkthroughs are on the Cardiology hub.
Worked USMLE-style vignettes
Vignette 1: the drug. In a physiology laboratory, a healthy volunteer receives an IV infusion of a drug. Cardiac output rises from 5.0 to 6.0 L/min while right atrial pressure falls from 2 to 0 mmHg. Estimated mean systemic filling pressure does not change. Which drug best explains these results?
- A. Normal saline bolus
- B. Nitroglycerin
- C. Phenylephrine
- D. Dobutamine
- E. Propranolol
Answer: D. Dobutamine, a β₁ agonist, shifts the cardiac function curve up; with the venous return curve unchanged, the operating point slides up and to the left, so CO rises and RAP falls.
- A: saline raises MSFP (right shift), so CO rises but RAP rises too.
- B: nitroglycerin mainly dilates veins, lowering MSFP, so CO and RAP both fall.
- C: phenylephrine constricts arteries and veins, raising afterload and MSFP and slowing the heart reflexly; its effect on CO varies, and venoconstriction raises RAP rather than lowering it.
- E: propranolol blocks β₁ receptors, lowering heart rate and contractility, so CO falls and RAP rises.
Vignette 2: the bleed. A 24-year-old man loses about 1 L of blood after a motorcycle crash. Before compensatory reflexes act, which set of changes is expected?
- A. MSFP ↓, RAP ↓, CO ↓
- B. MSFP unchanged, RAP ↓, CO ↓
- C. MSFP unchanged, RAP ↑, CO ↓
- D. MSFP ↑, RAP ↑, CO ↑
- E. MSFP unchanged, RAP ↓, CO ↑
Answer: A. Losing stressed volume lowers MSFP; the venous return curve shifts left in parallel and meets the unchanged cardiac curve lower and to the left.
- B: a rise in resistance to venous return alone (flatter curve, same intercept).
- C: depressed cardiac function, as after a large MI.
- D: transfusion or venoconstriction.
- E: a positive inotrope.
Vignette 3: the fistula. A 62-year-old man has a large upper-arm arteriovenous fistula created for hemodialysis. Minutes after it opens, cardiac output rises and right atrial pressure rises slightly; mean systemic filling pressure is unchanged. Which change best explains the rise in output?
- A. Lower resistance to venous return
- B. Higher blood volume
- C. Higher venous tone
- D. Higher contractility
- E. Faster heart rate
Answer: A. The fistula bypasses arteriolar and capillary resistance, steepening the venous return curve around an unchanged MSFP, so it meets the cardiac curve higher and slightly to the right.
- B and C would raise MSFP (right shift); salt and water retention comes later, not within minutes.
- D: an inotrope alone raises CO only modestly and lowers RAP.
- E: in Guyton's dogs, pacing alone did not raise CO until a fistula increased venous return.
Vignette 4: the diuretic. A 70-year-old woman with decompensated systolic heart failure has a right atrial pressure of 18 mmHg, cardiac output of 3.0 L/min and leg edema. After IV furosemide removes 2 L of fluid, right atrial pressure falls to 10 mmHg but cardiac output barely changes. What best explains this?
- A. Furosemide increased contractility
- B. Diuresis lowered MSFP, moving the operating point along the flat part of the cardiac function curve
- C. Diuresis increased resistance to venous return
- D. Fluid removal shifted the cardiac function curve up
- E. RAP has no effect on cardiac output
Answer: B. Diuresis lowers blood volume and MSFP, shifting the venous return curve left along the flat segment of her depressed cardiac curve, so RAP falls with little loss of output.
- A and D: a higher cardiac curve would have raised CO.
- C: removing fluid lowers MSFP, not RVR; in hypovolemia MSFP falls while resistance to venous return stays the same.
- E: on the steep part of the curve, RAP changes CO a lot; only on the plateau does it not.
Key takeaways
- Venous return curve: venous return against RAP; x-intercept = MSFP (about 7 mmHg in Guyton's dogs, higher in patients); slope = −1/RVR; plateau below about 0 mmHg = venous collapse.
- Volume or venous tone ↑ → right shift; ↓ → left shift. Resistance changes the slope; TPR also moves the cardiac curve through afterload, so CO moves opposite to TPR.
- Cardiac function curve: up with inotropy, heart rate or lower afterload; down with systolic failure or higher afterload.
- Signatures: fluids CO↑ RAP↑; inotrope CO↑ RAP↓; heart failure CO↓ RAP↑; hemorrhage CO↓ RAP↓; AV fistula CO↑ with a steeper curve.
- Evidence check: patient MSFP runs higher than the textbook 7 mmHg, and physiologists still dispute whether RAP limits venous return or follows cardiac output.
Sources
- Klabunde RE. Cardiac and Systemic Vascular Function Curves — Cardiovascular Physiology Concepts (2023)
- Klabunde RE. Venous Return: Hemodynamics — Cardiovascular Physiology Concepts (2023)
- Klabunde RE. Central Venous Pressure — Cardiovascular Physiology Concepts (2023)
- Klabunde RE. Hemodynamics of a Valsalva Maneuver — Cardiovascular Physiology Concepts (2023)
- Young DB. Control of Cardiac Output, Chapter 2: Venous Return — NCBI Bookshelf (2010)
- Young DB. Control of Cardiac Output, Chapter 3: Cardiac Function — NCBI Bookshelf (2010)
- Young DB. Control of Cardiac Output, Chapter 4: Integrated Analysis of Cardiac Output Control — NCBI Bookshelf (2010)
- Young DB. Control of Cardiac Output, Chapter 6: Analysis of Cardiac Output Control in Response to Challenges — NCBI Bookshelf (2010)
- Persichini R, et al. Venous return and mean systemic filling pressure: physiology and clinical applications — Critical Care (2022)
- Berger D, Takala J. Determinants of systemic venous return and the impact of positive pressure ventilation — Annals of Translational Medicine (2018)
- Henderson WR, et al. Clinical review: Guyton – the role of mean circulatory filling pressure and right atrial pressure in controlling cardiac output — Critical Care (2010)
- Beard DA, Feigl EO. Understanding Guyton's venous return curves — Am J Physiol Heart Circ Physiol (2011)
- Brengelmann GL. Is venous return controlled by central venous pressure? — University of Washington
- Jellinek H, et al. Influence of positive airway pressure on the pressure gradient for venous return in humans — J Appl Physiol (2000)
- Berger D, et al. Effect of PEEP, blood volume, and inspiratory hold maneuvers on venous return — Am J Physiol Heart Circ Physiol (2016)
- Schipke JD, et al. Static filling pressure in patients during induced ventricular fibrillation — Am J Physiol Heart Circ Physiol (2003)
- Maas JJ, et al. Assessment of venous return curve and mean systemic filling pressure in postoperative cardiac surgery patients — Crit Care Med (2009)
- Repessé X, et al. Value and determinants of the mean systemic filling pressure in critically ill patients — Am J Physiol Heart Circ Physiol (2015)
- Physiology, Frank Starling Law — StatPearls, NCBI Bookshelf (2023)
- High-Output Cardiac Failure — StatPearls, NCBI Bookshelf (2023)
- Physiology, Central Venous Pressure — StatPearls, NCBI Bookshelf (2023)
- Nitroglycerin — StatPearls, NCBI Bookshelf (2023)
- Phenylephrine — StatPearls, NCBI Bookshelf (2023)
- Dobutamine — StatPearls, NCBI Bookshelf (2024)
- Propranolol — StatPearls, NCBI Bookshelf (2026)
- Hydralazine — StatPearls, NCBI Bookshelf (2023)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
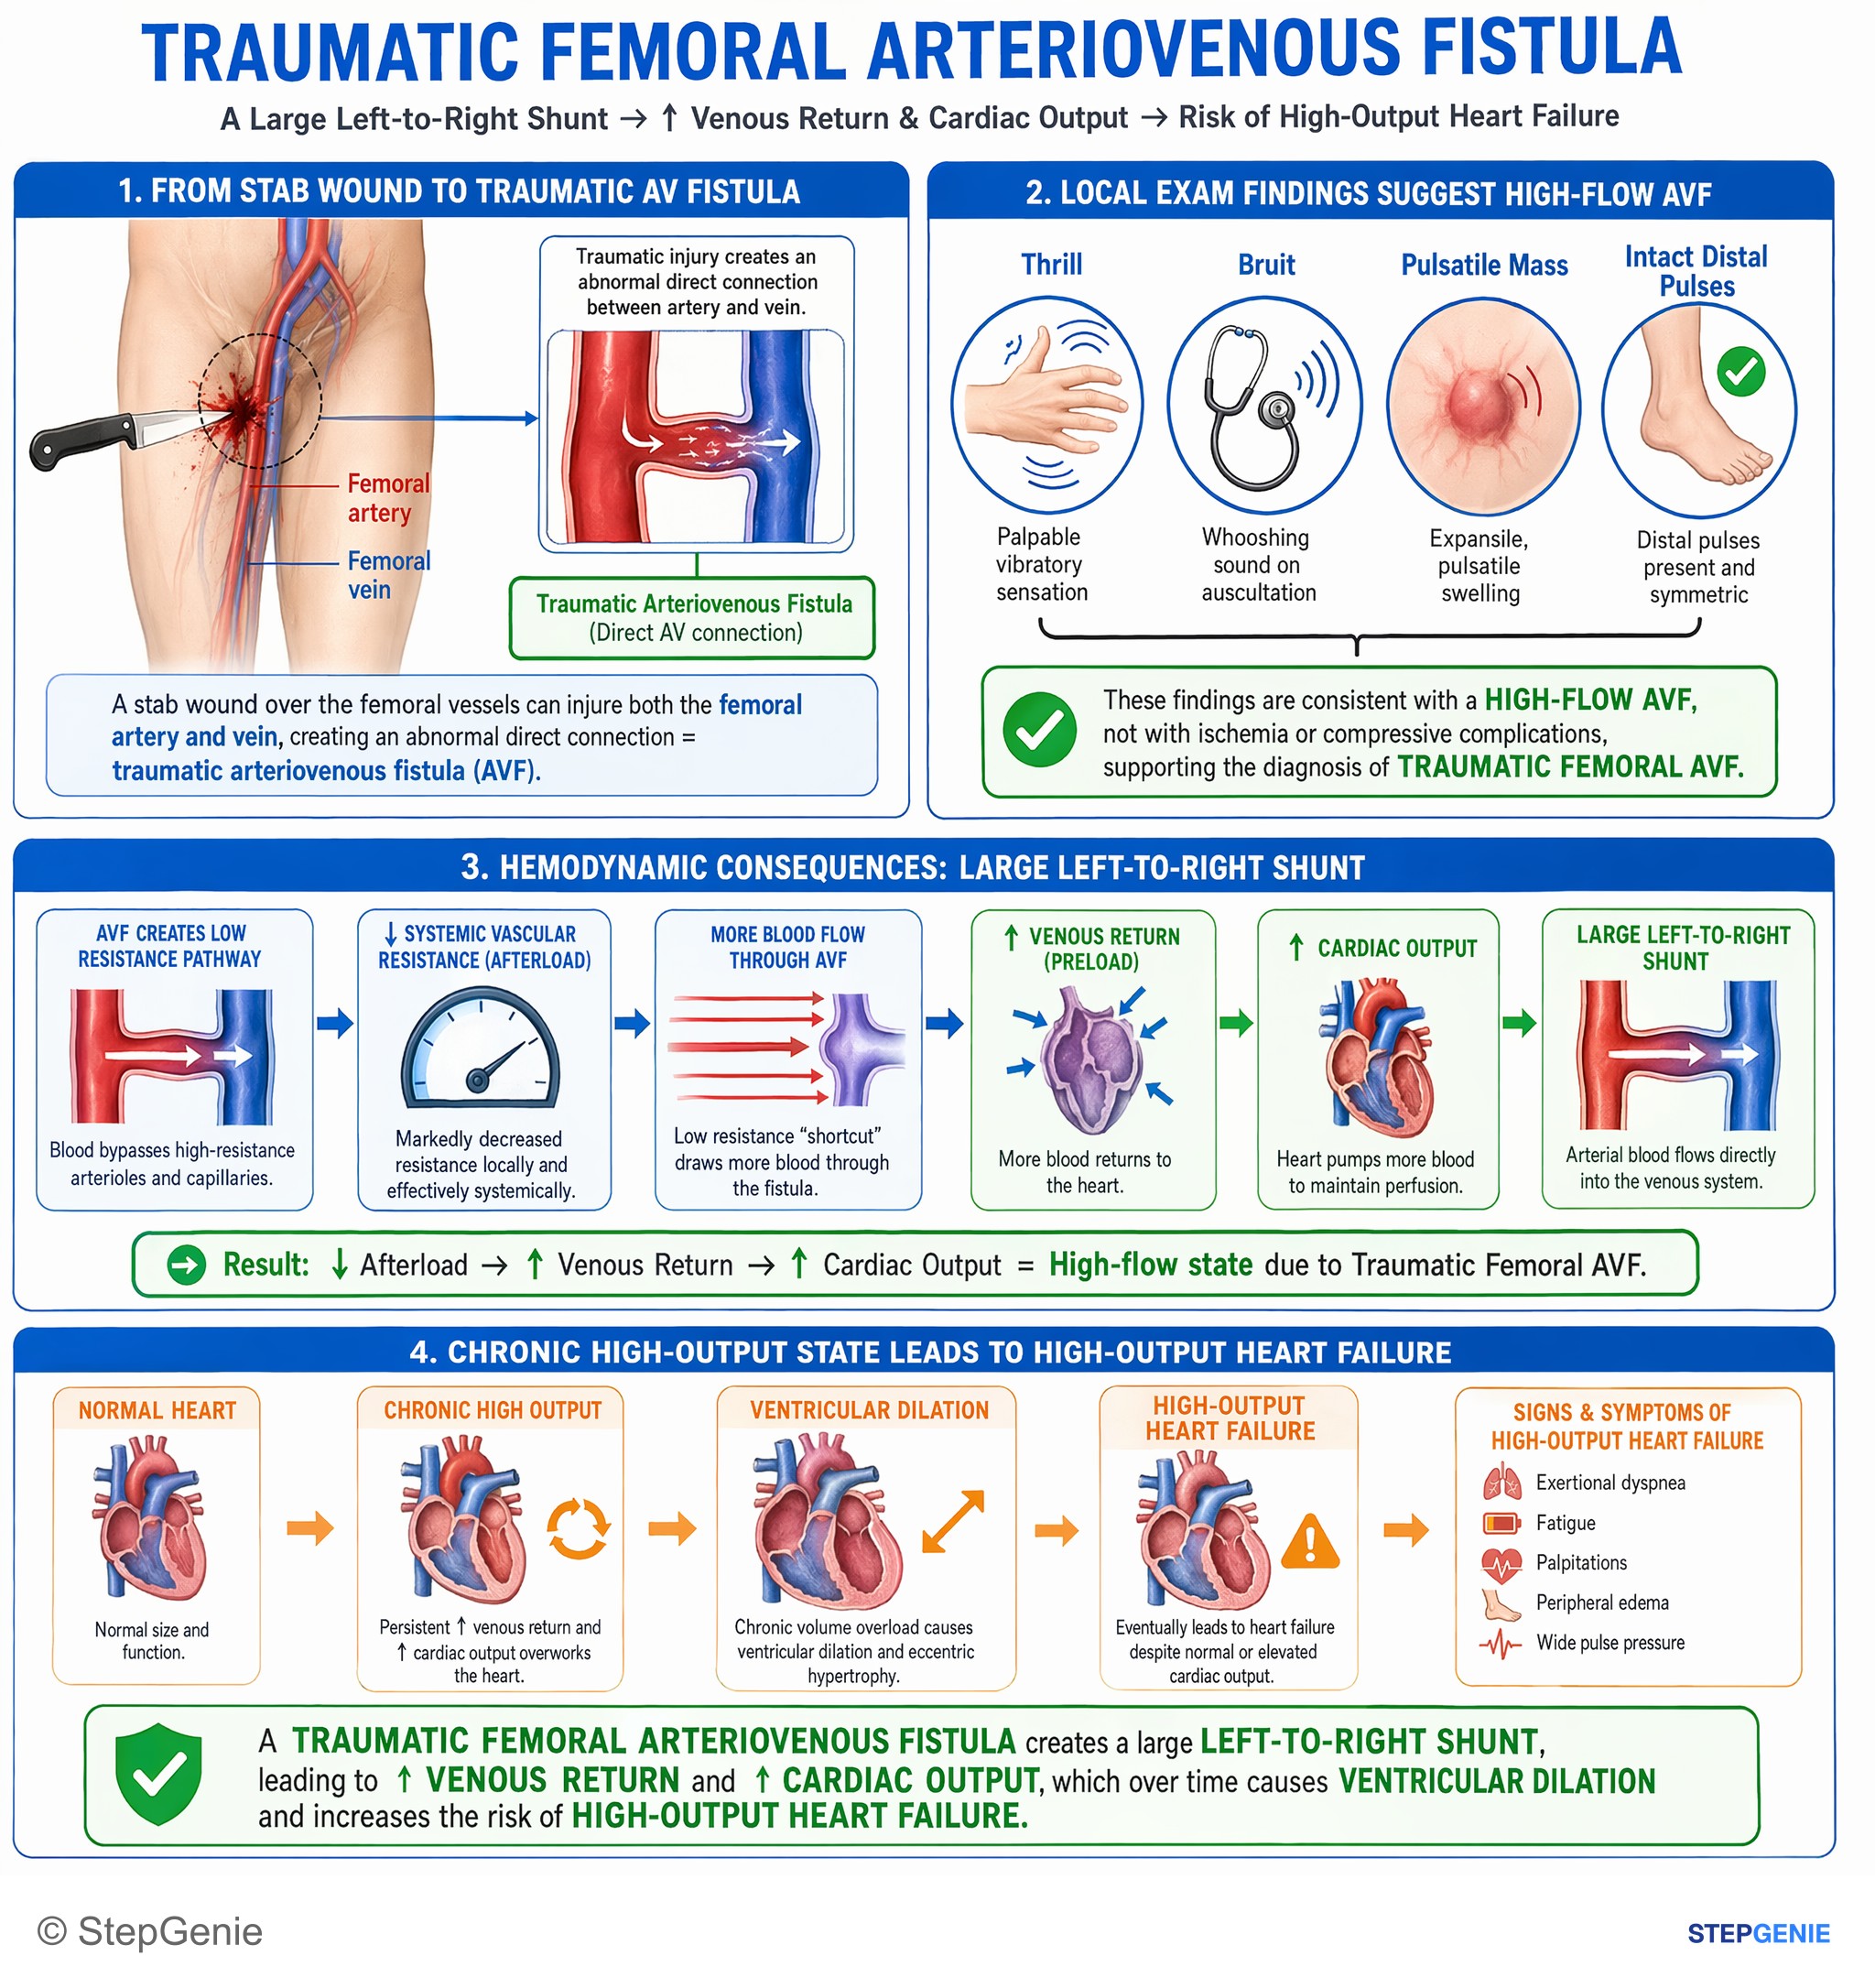
Traumatic femoral arteriovenous fistula → large left-to-right shunt → ↑ venous return and cardiac output → eventual high-output heart…
USMLE Step 2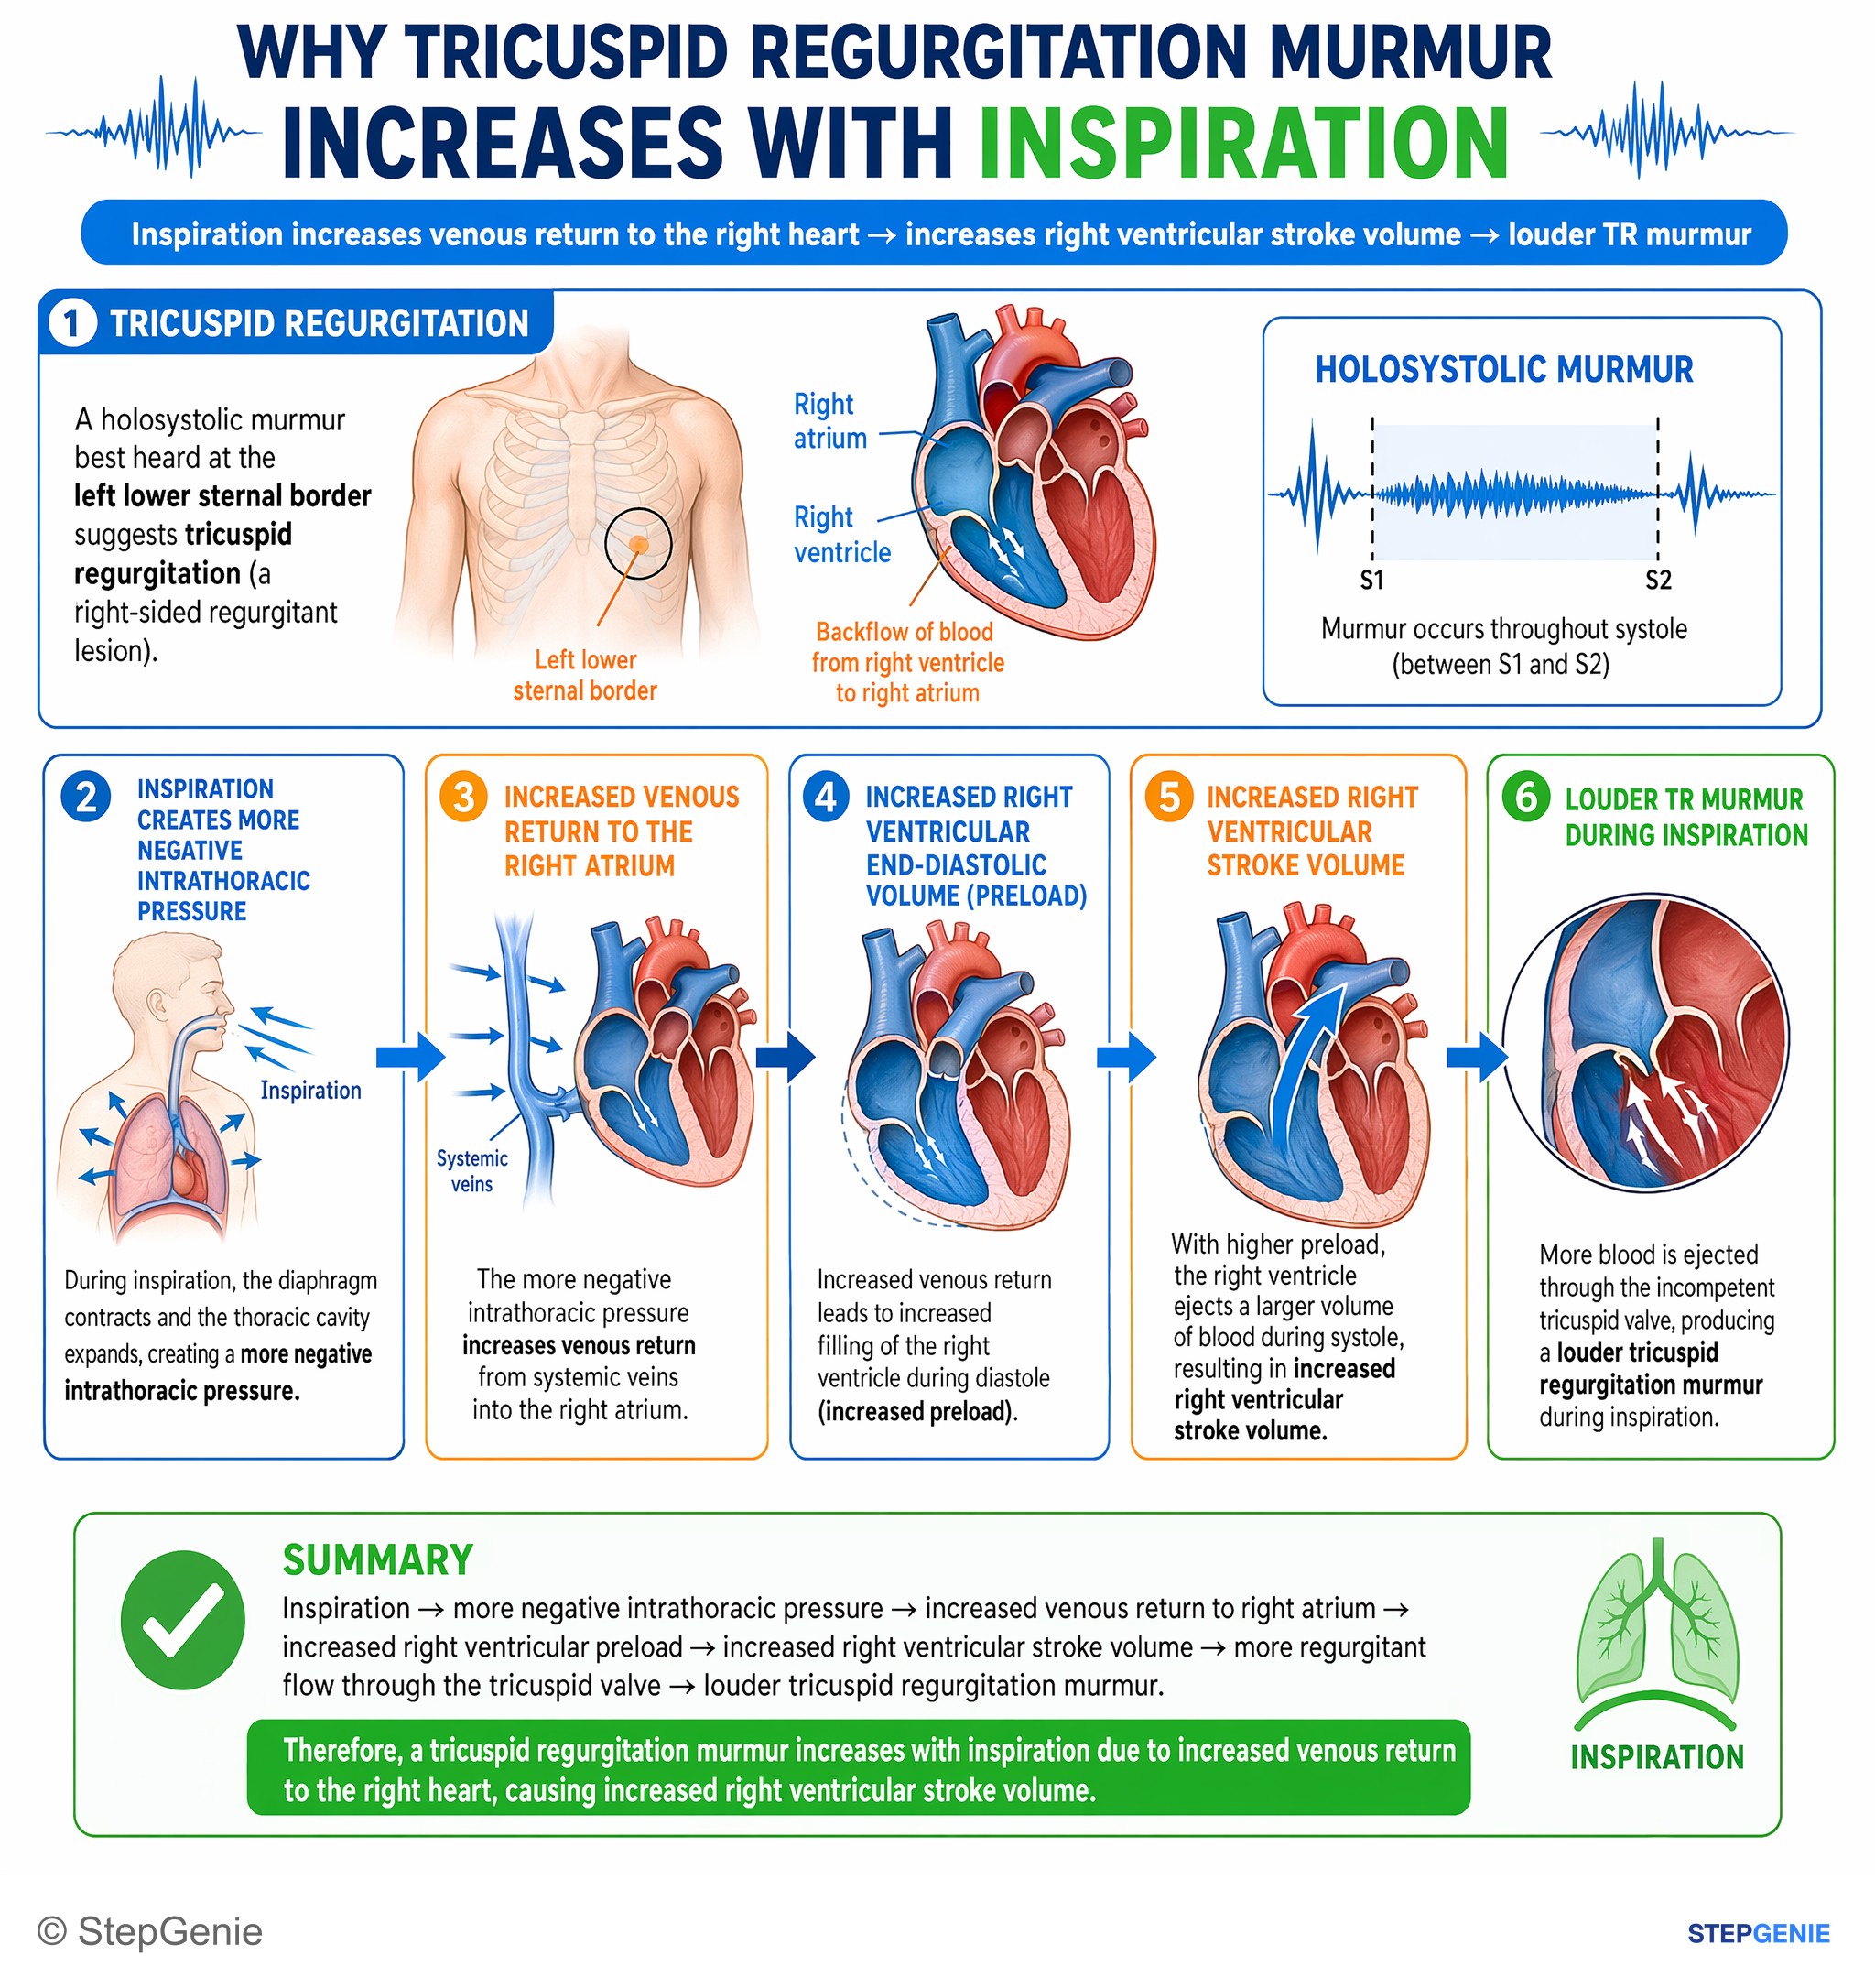
Tricuspid regurgitation murmur increases with inspiration due to increased venous return to the right heart, causing increased right…
USMLE Step 1Frequently Asked Questions
What does a venous return curve show?
A venous return curve, also called the vascular function curve, plots venous return against right atrial pressure. Flow falls as right atrial pressure rises and reaches zero at the mean systemic filling pressure, the x-intercept. The slope reflects resistance to venous return, and the curve levels off below about 0 mmHg because the great veins collapse. Where it crosses the cardiac function curve gives the steady-state cardiac output and right atrial pressure.
What is mean systemic filling pressure?
It is the pressure throughout the systemic circulation when flow stops and pressures equalize: about 7 mmHg in Guyton's dogs with reflexes blocked and about 8 mmHg in Klabunde's textbook account. Patient estimates run higher, about 13 mmHg one minute after death in ICU patients and 15 to 33 mmHg in cardiac surgery and septic shock patients. It rises with blood volume and venous tone and is the x-intercept of the venous return curve.
How does total peripheral resistance affect the venous return curve?
Arteriolar constriction flattens the venous return curve and arteriolar dilation steepens it, while mean systemic filling pressure barely changes because total vascular compliance is mostly venous. TPR is also afterload, so a higher TPR also lowers the cardiac function curve and a lower TPR raises it. The net result is that cardiac output moves opposite to TPR and right atrial pressure changes little. In Guyton's analysis, arterial resistance changes affect venous return far less than venous resistance changes.
Why does the venous return curve plateau at negative right atrial pressures?
When right atrial pressure falls below the pressure around the great veins, they collapse, so lowering it further adds no flow. With the chest closed, the curve bends between about -2 and -4 mmHg and is flat below -4 mmHg. This is why a stronger heart alone raises cardiac output only modestly: it pulls right atrial pressure toward the plateau. Large increases need the venous return curve to shift right or become steeper.
What happens to cardiac output and right atrial pressure with a positive inotrope?
Cardiac output rises and right atrial pressure falls. A positive inotrope such as dobutamine shifts the cardiac function curve up, and with the venous return curve unchanged the operating point slides up and to the left along it. The gain is modest in a normal circulation because venous collapse limits flow as right atrial pressure falls. Systolic heart failure does the opposite: output falls and right atrial pressure rises.
How does hemorrhage change the venous return curve?
Blood loss lowers the stressed volume and the mean systemic filling pressure, so the venous return curve shifts left in parallel and the new crossing point has lower cardiac output and lower right atrial pressure. Reflex venoconstriction then recruits unstressed volume and moves the curve partly back to the right, while arteriolar constriction and a faster, stronger heartbeat support blood pressure. Replacing lost volume restores mean systemic filling pressure directly.