The Starling equation is net filtration (Jv) = Kf × [(Pc − Pi) − σ(πc − πi)]. Capillary hydrostatic pressure (Pc) and interstitial oncotic pressure (πi) move fluid out of the capillary, interstitial hydrostatic pressure (Pi) and plasma oncotic pressure (πc, mostly albumin) hold it in, Kf (the filtration coefficient) scales the flow, and σ (the reflection coefficient, 0 to 1) says how well the wall holds back protein. A positive result means filtration into the tissue and a negative one means absorption; in the textbook capillary, Pc falls from about 35 to 18 mm Hg against a plasma oncotic pressure of about 25 mm Hg. Edema forms when filtration outruns lymph drainage, in four ways: raised capillary hydrostatic pressure (heart failure, venous obstruction), low plasma oncotic pressure (nephrotic syndrome, cirrhosis), leaky capillaries (burns, sepsis, ARDS) and blocked lymphatics (lymph node dissection, filariasis).
The Starling equation at a glance
| Term | What it is | Effect on filtration | Typical value | What changes it |
|---|---|---|---|---|
| Pc | Capillary hydrostatic pressure | Pushes fluid out | About 35 mm Hg at the arteriolar end, 18 mm Hg at the venular end | ↑ with venous pressure (heart failure, DVT) and arteriolar dilation (dihydropyridine CCBs) |
| Pi (also Pif, Pt) | Interstitial hydrostatic pressure | Opposes filtration when positive; a negative value adds to filtration | Near zero; about −1.4 mm Hg in human subcutaneous tissue at heart level | Rises as fluid accumulates; more negative in the lung |
| πc (also πp) | Plasma oncotic (colloid osmotic) pressure | Holds fluid in | 25–30 mm Hg; albumin supplies roughly 65–70% | ↓ in nephrotic syndrome, cirrhosis, malnutrition |
| πi | Interstitial oncotic pressure | Pulls fluid out | Low; estimates range from about 5 mm Hg to 30–60% of plasma oncotic pressure | ↑ when protein leaks out or lymph can't clear it |
| Kf | Filtration coefficient: water permeability × surface area | Scales the whole flow | Higher in fenestrated capillaries (glomerulus) than continuous ones | ↑ in inflammation, burns, sepsis |
| σ | Reflection coefficient for protein (1 = impermeable, 0 = freely permeable) | Scales the oncotic term | 0.9 or more for macromolecules in most capillaries; near 0 in liver sinusoids | ↓ when capillaries leak protein |
Sign convention. The bracketed term is the net filtration pressure (NFP) in mm Hg: positive means filtration out of the capillary, negative means absorption into it, and Kf turns it into a flow (mL/min per mm Hg). Remember that hydrostatic pressure pushes, oncotic pressure pulls, and each interstitial term works against its capillary partner, so a more negative Pi and a higher πi both increase filtration. Watch the double negative: Pc − (−2) = Pc + 2.
Venous pressure dominates Pc. Precapillary (arteriolar) resistance is normally about five times postcapillary resistance, so a rise in venous pressure raises Pc about five times as much as the same rise in arterial pressure. Venous congestion therefore causes edema while arterial pressure is buffered, and arteriolar dilators such as amlodipine let more of it through to the capillary.
Worked Starling calculations
1. The classic textbook capillary. OpenStax treats the interstitial forces as negligible, so NFP is simply Pc − πc:
- Arteriolar end: NFP = 35 − 25 = +10 mm Hg, so fluid filters out.
- Venular end: NFP = 18 − 25 = −7 mm Hg, so fluid is reabsorbed.
In that model about 24 L/day is filtered and 20.4 L reabsorbed, leaving 3.6 L/day for the lymphatics; the revised principle below explains what this picture gets wrong.
2. One capillary, four routes to edema. Exam stems often give all four pressures. With illustrative values of Pc 30, Pi −2, πc 25 and πi 5 mm Hg and σ = 1, the baseline is NFP = (30 − (−2)) − (25 − 5) = 32 − 20 = +12 mm Hg. Now change one term at a time:
| Change | Mechanism | Arithmetic | NFP (mm Hg) |
|---|---|---|---|
| Pc 30 → 45 | Venous congestion (right heart failure) | (45 + 2) − 20 = 47 − 20 | +27 |
| πc 25 → 10 | Albumin loss (nephrotic syndrome) | 32 − (10 − 5) = 32 − 5 | +27 |
| σ 1 → 0.25 | Leaky capillaries (burn) | 32 − 0.25 × 20 = 32 − 5 | +27 |
| πi 5 → 20 | Protein trapped behind blocked lymphatics | 32 − (25 − 20) = 32 − 5 | +27 |
Each change adds 15 mm Hg, about the rise that may be needed before edema becomes clinically apparent (see safety factors below). Real disease rarely moves just one term: a burn also raises Kf, so the same pressure moves more fluid.
3. The glomerulus. With OpenStax values (glomerular capillary pressure 55, Bowman's space pressure 15, average glomerular oncotic pressure 30, Bowman's space oncotic pressure about 0 mm Hg): NFP = (55 − 15) − (30 − 0) = +10 mm Hg. A GFR of 125 mL/min then implies Kf = 125 ÷ 10 = 12.5 mL/min per mm Hg. If bladder outlet obstruction raised Bowman's space pressure to 20 mm Hg in both kidneys, NFP = (55 − 20) − 30 = +5 mm Hg, and with nothing else changing GFR would fall to about 12.5 × 5 ≈ 63 mL/min. With only 10 mm Hg driving filtration, small pressure changes move GFR a lot.
Classic vs revised Starling principle
The classic picture of filtration at the arteriolar end and reabsorption at the venular end has no reproducible experimental support in most tissues. The revised Starling principle changes four things:
| Question | Classic model (still used for exam math) | Revised Starling principle |
|---|---|---|
| Which oncotic gradient counts? | Plasma vs interstitial fluid (πc − πi) | Plasma vs the thin fluid layer just beneath the endothelial glycocalyx, which is lower in protein than the interstitium |
| What happens at the venular end? | Most of the filtrate is reabsorbed | Absorption is only transient (after a hemorrhage, "autotransfusion" tops out around 500 mL); in the steady state, continuous capillaries filter slightly along their length |
| How does filtrate get back? | Mostly by capillary reabsorption, the rest as lymph | Mainly as lymph, about 8 L/day, roughly half of it absorbed into blood inside lymph nodes |
| Where is absorption sustained? | Venular end of every capillary | Only where protein-poor fluid keeps arriving: kidney peritubular capillaries, intestinal mucosa absorbing a meal, lymph nodes |
- The endothelial glycocalyx is the real protein filter. It lines continuous and fenestrated capillaries and keeps most protein out of the space beneath it. When filtration slows, protein in that space rises and the absorbing gradient fades, so reabsorption can't last. Protein still crosses slowly (σ is 0.9 or more, not 1), and lymph carries it back.
- Filtration follows a hockey-stick curve. Below a capillary pressure just under plasma oncotic pressure, filtration is near zero rather than turning into lasting absorption; above it, filtration climbs steeply with Pc.
- For the exam, do calculations with the classic four-force equation exactly as written above. For concept questions, the defensible answer is that lymphatics, not venules, return steady-state filtrate.
The four mechanisms of edema
| Mechanism | Starling change | Classic causes | Exam clues |
|---|---|---|---|
| 1. Raised capillary hydrostatic pressure | ↑ Pc | Heart failure, DVT, chronic venous insufficiency, cirrhosis with portal hypertension, volume expansion (kidney failure, pregnancy), dihydropyridine CCBs | Dependent pitting edema; JVD and an S3 in heart failure; acute one-leg swelling suggests DVT; venous edema improves with elevation |
| 2. Low plasma oncotic pressure | ↓ πc | Nephrotic syndrome, cirrhosis or liver failure, protein-losing enteropathy, malnutrition (kwashiorkor) | Generalized edema, often once albumin falls below about 2 g/dL; ascites and effusions; heavy proteinuria points to nephrotic syndrome |
| 3. Increased capillary permeability | ↑ Kf, ↓ σ; leaked protein raises πi | Burns, sepsis, ARDS, angioedema and allergic reactions, cellulitis, insect bites | Protein-rich fluid; hypotension in sepsis; bilateral lung infiltrates without a raised wedge pressure in ARDS |
| 4. Lymphatic obstruction | Filtrate isn't removed; trapped protein raises πi | Lymph node dissection or radiation, tumor, filariasis (Wuchereria bancrofti, the leading cause in tropical regions), congenital | Pits early, nonpitting as fibrosis develops; positive Stemmer sign; responds poorly to diuretics and elevation |
Interstitial oncotic pressure keeps edema going. A rise in πi is rarely the first event, but in permeability and lymphatic edema, protein that leaks out or can't be cleared raises πi and pulls water after it, so the fluid is protein-rich and chronic lymphedema becomes inflamed and fibrotic. Myxedema (hypothyroidism) is a special case: mucopolysaccharides and protein accumulate in the interstitium, giving nonpitting swelling of the eyelids, face and hands. Lipedema is fat, not fluid, and typically spares the feet.
The kidneys amplify most generalized edema. Low effective arterial volume activates the renin–angiotensin–aldosterone system and ADH, so the kidneys retain sodium and water and push Pc higher. In cirrhosis, portal hypertension raises splanchnic Pc, splanchnic vasodilation triggers that sodium retention, and reduced albumin synthesis lowers πc (cirrhosis and portal hypertension). Nephrotic edema has two explanations, both contributing: underfill (albuminuria lowers πc, fluid leaves the plasma and the kidneys retain sodium in response) and overfill (a primary tubular defect retains sodium, sometimes before albumin falls); see nephrotic vs nephritic syndrome.
Right vs left heart failure. Right-sided failure raises systemic venous pressure (leg edema, hepatic congestion, ascites); left-sided failure raises pulmonary venous pressure and floods the lungs. Coronary disease, hypertension and left-sided valve disease typically cause pulmonary edema before peripheral edema (left vs right-sided heart failure).
Safety factors: why edema needs a big push
Tissues resist edema through three feedback mechanisms:
- Interstitial pressure rises. As fluid accumulates, Pi climbs and opposes further filtration.
- Lymph flow rises. Lymphatic filling and contraction increase, carrying off more filtrate.
- Interstitial protein washes out. Extra protein-poor filtrate dilutes interstitial protein and lymph removes it, so πi falls and the gradient holding fluid in widens.
Together they explain why edema may become clinically apparent only after net filtration pressure has risen by about 15 mm Hg. Generalized edema typically isn't clinically apparent until interstitial volume has increased by 2.5–3 L. Lymphatic obstruction disables the second and third safety factors and permeability edema disables the third, which is why both produce protein-rich fluid.
Pulmonary edema: cardiogenic vs noncardiogenic
Lung capillaries run at a lower hydrostatic pressure than skeletal muscle capillaries but are more permeable to protein, and the lung interstitium has a more negative pressure than most tissues. Pulmonary edema comes in two Starling flavors:
| Feature | Cardiogenic (hydrostatic) | Noncardiogenic (permeability), e.g., ARDS |
|---|---|---|
| Starling change | ↑ Pc from high left atrial pressure | ↑ Kf, ↓ σ from injured endothelium and epithelium |
| Typical causes | LV systolic or diastolic dysfunction, valve disease, arrhythmia, volume overload | Sepsis, pneumonia, aspiration, trauma with shock, pancreatitis, multiple transfusions, inhalation injury |
| Wedge pressure (PCWP, PAOP) | High: above 18 mm Hg supports a cardiogenic cause | Usually not raised: the older AECC definition used an 18 mm Hg wedge cut-off; the Berlin definition dropped the wedge criterion |
| Edema fluid | Protein-poor | Protein-rich, with blood and cell debris |
| Chest x-ray | Central edema, Kerley B lines, peribronchial cuffing, effusions, cardiomegaly | Patchy peripheral opacities, air bronchograms |
| First-line treatment | Oxygen or noninvasive ventilation, IV furosemide, IV nitroglycerin if systolic BP is above 110 mm Hg | Treat the cause; ventilatory support |
A BNP below 100 pg/mL makes heart failure unlikely and one above 500 pg/mL makes it likely; values of 100–500 are common in critical illness and don't settle the question. Echocardiography assesses LV function; in ARDS, pulmonary artery catheters are generally discouraged. Current criteria and ventilation are covered in ARDS.
Starling forces at the glomerulus
The same equation, written for the kidney, is GFR = Kf × [(PGC − PBS) − (πGC − πBS)], where GC is the glomerular capillary and BS is Bowman's space.
| Feature | Systemic capillary | Glomerular capillary |
|---|---|---|
| Hydrostatic pressure inside | Falls along the capillary, about 35 → 18 mm Hg | High, about 55 mm Hg, set by afferent and efferent arteriolar tone |
| Hydrostatic pressure outside | Interstitium, near 0 | Bowman's space, about 15 mm Hg |
| Oncotic pressure inside | About 25 mm Hg | Rises along the capillary as protein-free filtrate leaves; averages about 30 mm Hg |
| Oncotic pressure outside | Interstitium, low (about 5 mm Hg) | Bowman's space, near 0 |
| Kf | Lower (continuous endothelium) | High (fenestrated endothelium) |
| Net result | Small net filtration, returned as lymph | Filtration along the whole length: about 125 mL/min (180 L/day) in men and 105 mL/min (150 L/day) in women, 99% of it reabsorbed |
- Afferent arteriolar constriction lowers PGC and GFR; efferent constriction raises PGC. The drugs and hormones that do this are covered in renal blood flow autoregulation.
- Ureteral or bladder outlet obstruction raises PBS, and high plasma protein raises πGC; both lower GFR.
- Peritubular capillaries do the opposite of the glomerulus. Their blood has just lost about a fifth of its plasma water to filtration, so its oncotic pressure is high; the efferent arteriole upstream has lowered its hydrostatic pressure; and the tubules keep supplying protein-free reabsorbate. They absorb continuously, one of the few beds where absorption is sustained.
Transudates, exudates and ascites
- Transudate: Starling pressures change across an intact wall (↑ Pc or ↓ πc), so the fluid is protein-poor: left heart failure, cirrhosis, nephrotic syndrome, hypoalbuminemia.
- Exudate: the wall itself leaks (↑ Kf, ↓ σ), so the fluid is rich in protein and LDH: pneumonia, tuberculosis, malignancy, pancreatitis, lupus, rheumatoid arthritis.
- Light's criteria call a pleural effusion an exudate if any one is met: fluid-to-serum protein ratio above 0.5, fluid-to-serum LDH ratio above 0.6, or pleural LDH above two-thirds of the upper limit of normal for serum LDH. Worked case: transudative vs exudative pleural effusion.
- Ascites: the serum–ascites albumin gradient (SAAG = serum albumin − ascitic albumin) has largely replaced the protein-based label. SAAG ≥ 1.1 g/dL indicates portal hypertension (cirrhosis, alcoholic hepatitis, Budd–Chiari syndrome, portal vein thrombosis, heart failure); below 1.1 points to peritoneal carcinomatosis, tuberculosis, pancreatitis or nephrotic syndrome.
Treatment follows the force
- Sodium retention (heart failure, kidney disease): sodium restriction and diuretics, loop diuretics being the most effective; SGLT2 inhibitors can be used in heart failure or nephrotic syndrome. Diuretics shouldn't be given only to improve how edema looks.
- Cirrhotic ascites: sodium restriction to 2,000 mg (88 mEq) a day and spironolactone with furosemide in a 100:40 mg ratio; after paracentesis of 5 L or more, give albumin, about 6–8 g per liter removed.
- Venous insufficiency: elevation and compression, after checking the ankle–brachial index, because compression is contraindicated in peripheral arterial disease.
- Lymphedema: complete decongestive therapy (manual lymphatic drainage, compression, skin care, exercise).
How USMLE tests Starling forces: traps and look-alikes
| Trap | What's actually true |
|---|---|
| "Starling forces" means the Frank–Starling mechanism | Different ideas: Starling forces move fluid across capillaries; the Frank–Starling mechanism links preload to stroke volume |
| A more negative Pi, or a higher πi, slows filtration | Both favor filtration: subtracting a negative adds, and πi pulls fluid out |
| Arterial hypertension by itself drives edema | Arterioles buffer arterial pressure, and venous pressure has about five times the effect on Pc; hypertension causes edema mainly through heart failure |
| Amlodipine edema means low albumin or a leak | Arteriolar dilation raises Pc downstream; it usually resolves within days of stopping the drug |
| ARDS means a high wedge pressure | A high wedge pressure points to cardiogenic edema; ARDS is permeability edema |
| Venules reabsorb most of the filtrate | At steady state, lymphatics return it, about 8 L/day |
| Nephrotic edema is purely oncotic | Primary renal sodium retention contributes, sometimes before albumin falls |
| The glomerulus behaves like a systemic capillary | High PGC, near-zero Bowman's space oncotic pressure, filtration along its whole length |
Angioedema is permeability edema too; for the bradykinin story behind the ACE-inhibitor kind, see ACE inhibitors vs ARBs.
Worked vignettes
Vignette 1. A 56-year-old man with alcohol-related cirrhosis has tense ascites and leg edema; serum albumin is 2.2 g/dL and ascitic albumin 0.7 g/dL. Which Starling changes explain his fluid?
Answer: SAAG = 2.2 − 0.7 = 1.5 g/dL (≥ 1.1), so portal hypertension: raised splanchnic Pc plus low πc, amplified by renal sodium retention.
Reasoning: Portal hypertension raises splanchnic Pc, and splanchnic vasodilation drives aldosterone-mediated sodium retention; low albumin synthesis lowers πc and adds to the leg edema. Treat both: sodium restriction, spironolactone with furosemide, and albumin if 5 L or more is removed at paracentesis.
Vignette 2. On day 2 of severe acute pancreatitis, a 45-year-old woman becomes hypoxemic with bilateral patchy peripheral opacities. LV function is normal on echocardiography and the wedge pressure is 10 mm Hg. Which Starling term changed?
Answer: ↑ Kf and ↓ σ: permeability edema (ARDS).
Reasoning: Normal LV function and a normal wedge pressure point away from a hydrostatic cause. Inflammatory injury lets protein-rich fluid cross the alveolar–capillary barrier, so treatment targets the cause and supports oxygenation.
Vignette 3. Two years after mastectomy with axillary node dissection and radiation, a 58-year-old woman's swollen left arm, which once pitted, is now firm and nonpitting, and the skin at the base of her second finger can't be pinched.
Answer: Secondary lymphedema from lymphatic obstruction.
Reasoning: Lymph can't clear filtrate or protein, so πi rises and chronic inflammation brings fibrosis, making the edema nonpitting; the unpinchable skin is a positive Stemmer sign. Treatment is complete decongestive therapy; diuretics help little.
Key takeaways
- Jv = Kf × [(Pc − Pi) − σ(πc − πi)]: hydrostatic pressure pushes, oncotic pressure pulls; positive = filtration.
- Classic values: Pc 35 → 18 mm Hg against πc about 25, so NFP +10 at the arteriolar end and −7 at the venular end.
- Revised principle: slight filtration along most capillaries, the glycocalyx as the protein filter, and lymph returning about 8 L/day.
- Four edema mechanisms: ↑ Pc, ↓ πc, ↑ permeability (↑ Kf, ↓ σ) and lymphatic obstruction.
- PCWP above 18 mm Hg supports cardiogenic pulmonary edema; ARDS is permeability edema.
- Glomerulus: (55 − 15) − 30 = +10 mm Hg, filtering along its whole length; peritubular capillaries absorb.
- Transudate = pressure problem, exudate = leaky wall; SAAG ≥ 1.1 g/dL = portal hypertension.
Sources
- Peripheral Edema — StatPearls, NCBI Bookshelf (2025)
- Physiology, Edema — StatPearls, NCBI Bookshelf (2023)
- Edema — Merck Manual Professional Edition (2025)
- 20.3 Capillary Exchange — OpenStax Anatomy and Physiology 2e (2022)
- 25.5 Physiology of Urine Formation — OpenStax Anatomy and Physiology 2e (2022)
- Physical Factors that Determine Capillary Fluid Exchange — CV Physiology, Klabunde (2023)
- Hydrostatic and Oncotic Pressures — CV Physiology, Klabunde (2023)
- Woodcock TE, Michel CC. Advances in the Starling Principle and Microvascular Fluid Exchange; Consequences and Implications for Fluid Therapy — Frontiers in Veterinary Science (2021)
- Pulmonary Edema — StatPearls, NCBI Bookshelf (2023)
- Acute Respiratory Distress Syndrome — StatPearls, NCBI Bookshelf (2024)
- Lymphedema — StatPearls, NCBI Bookshelf (2025)
- Nephrotic Syndrome — StatPearls, NCBI Bookshelf (2023)
- Pleural Effusion — StatPearls, NCBI Bookshelf (2024)
- Ascites — StatPearls, NCBI Bookshelf (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
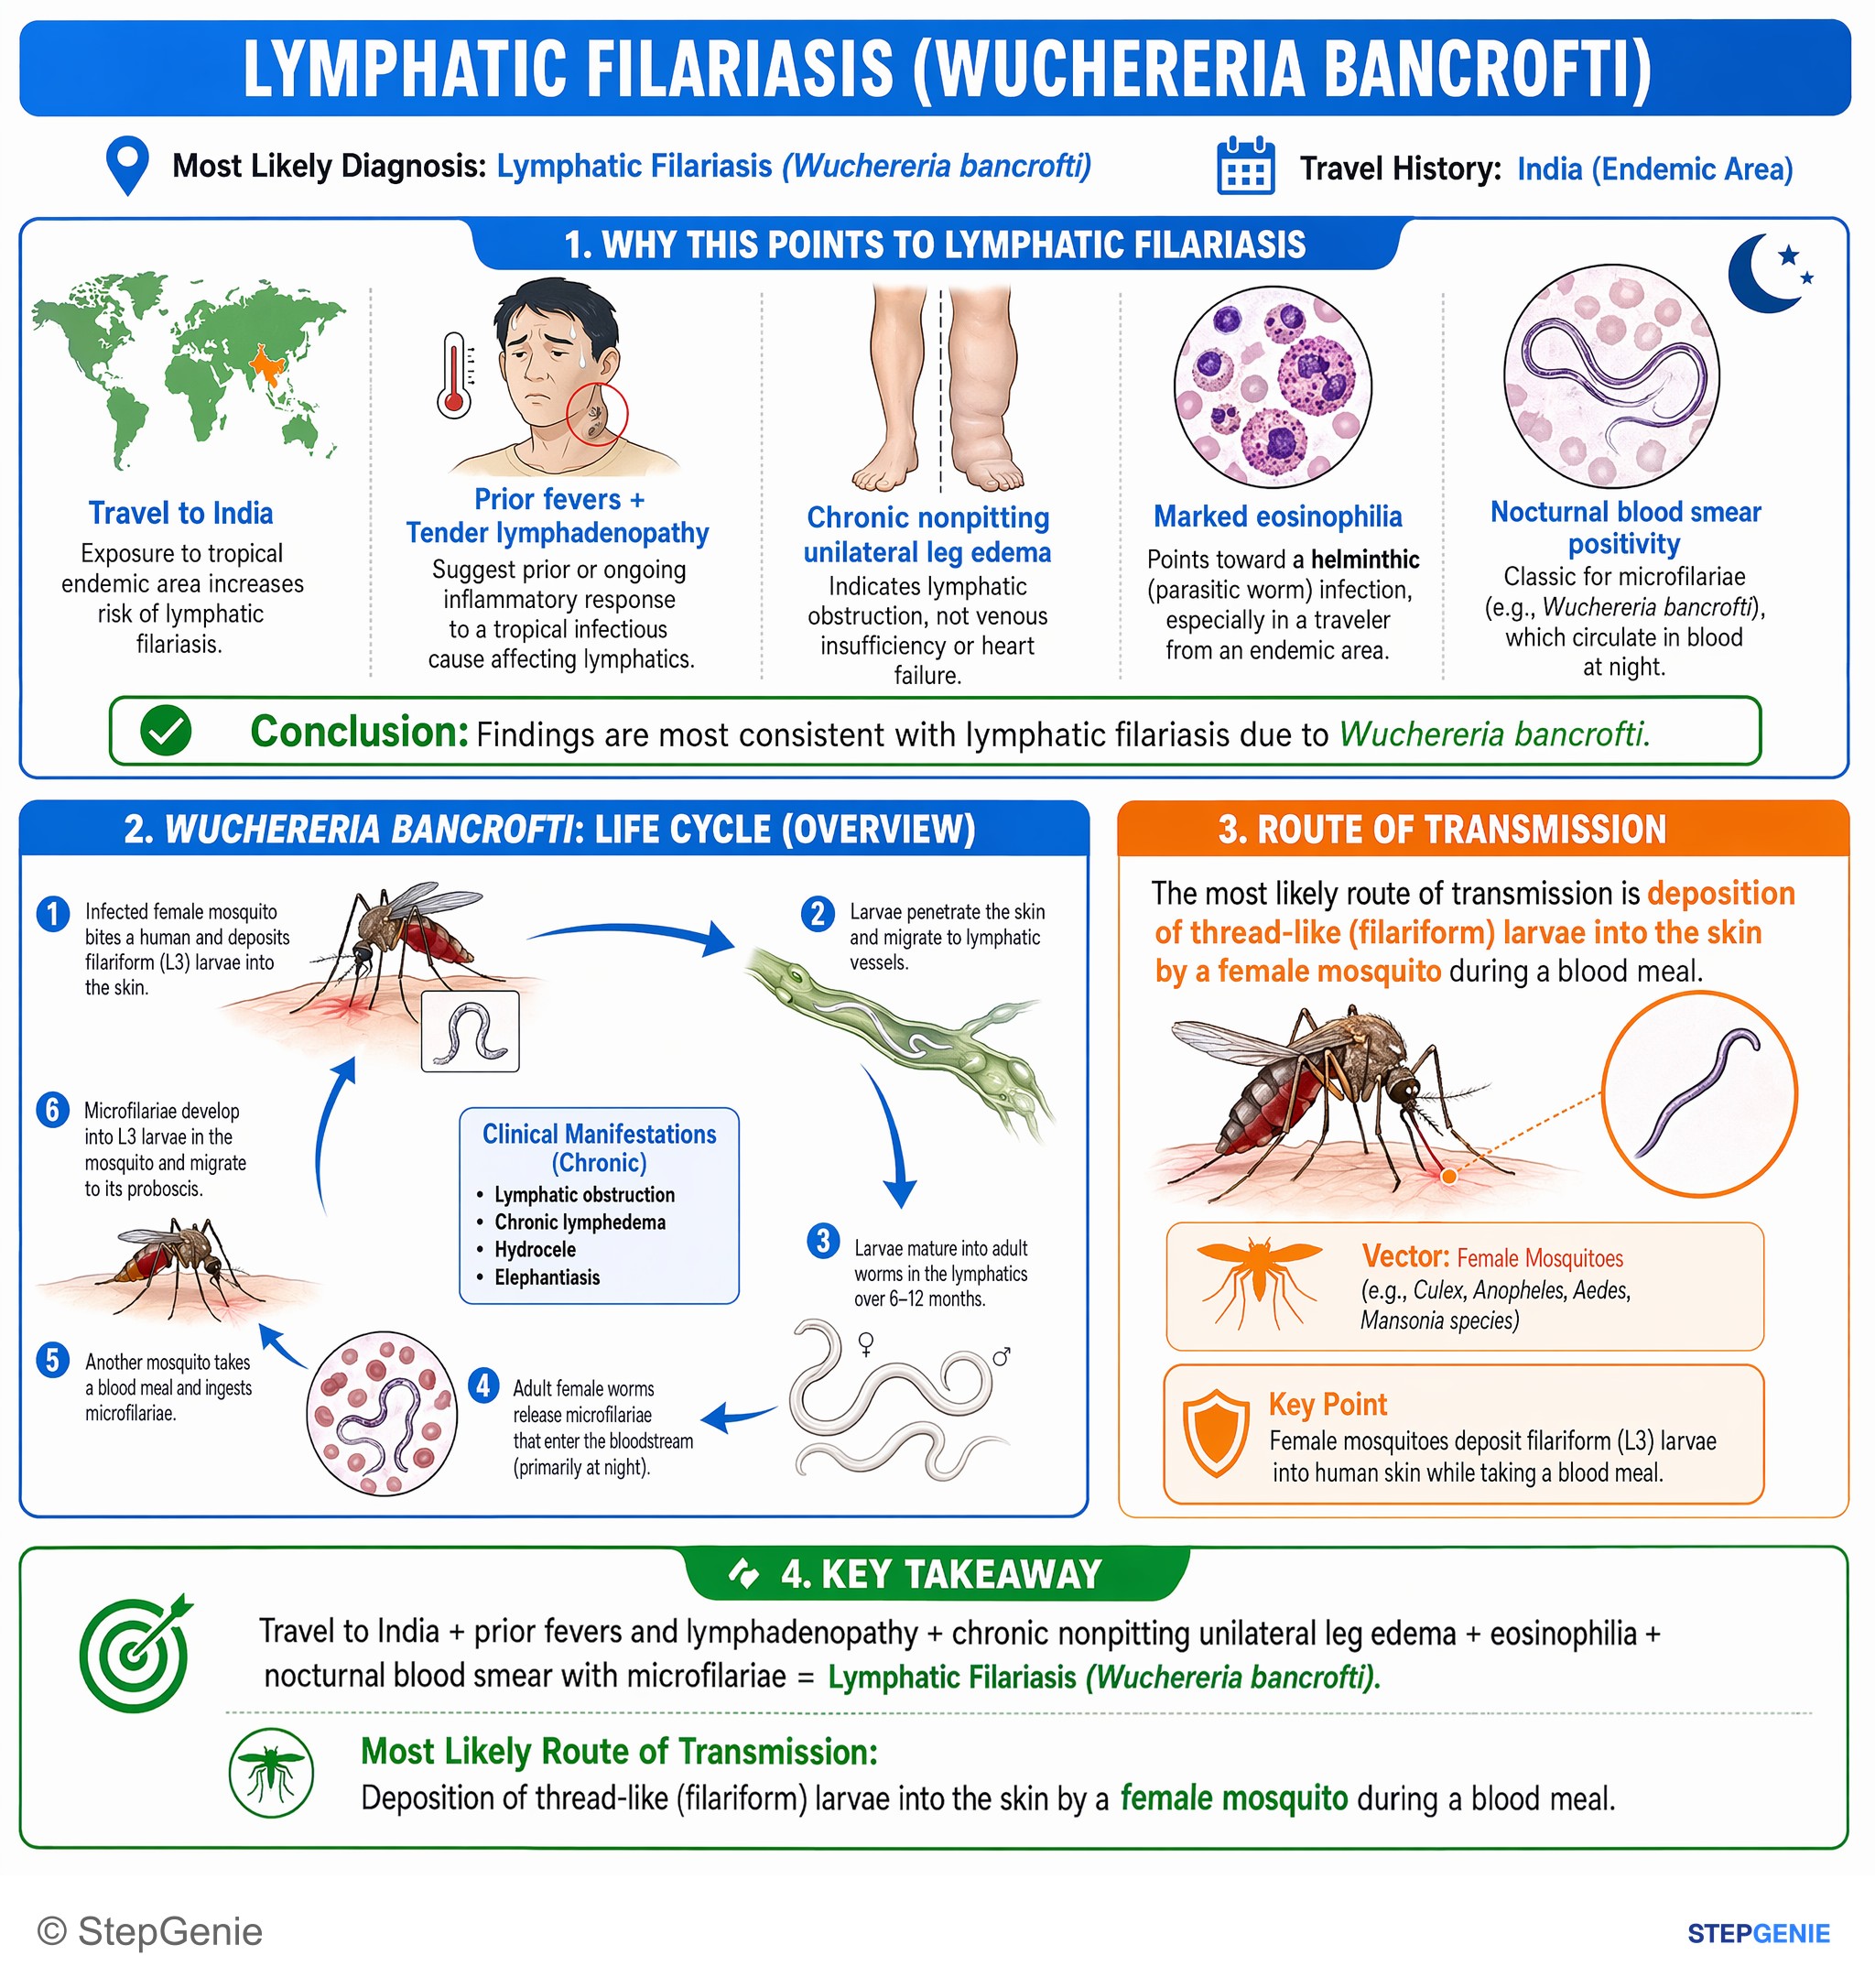
Wuchereria bancrofti filariasis causes chronic lymphedema/elephantiasis; transmitted by female mosquitoes depositing filariform larvae…
USMLE Step 1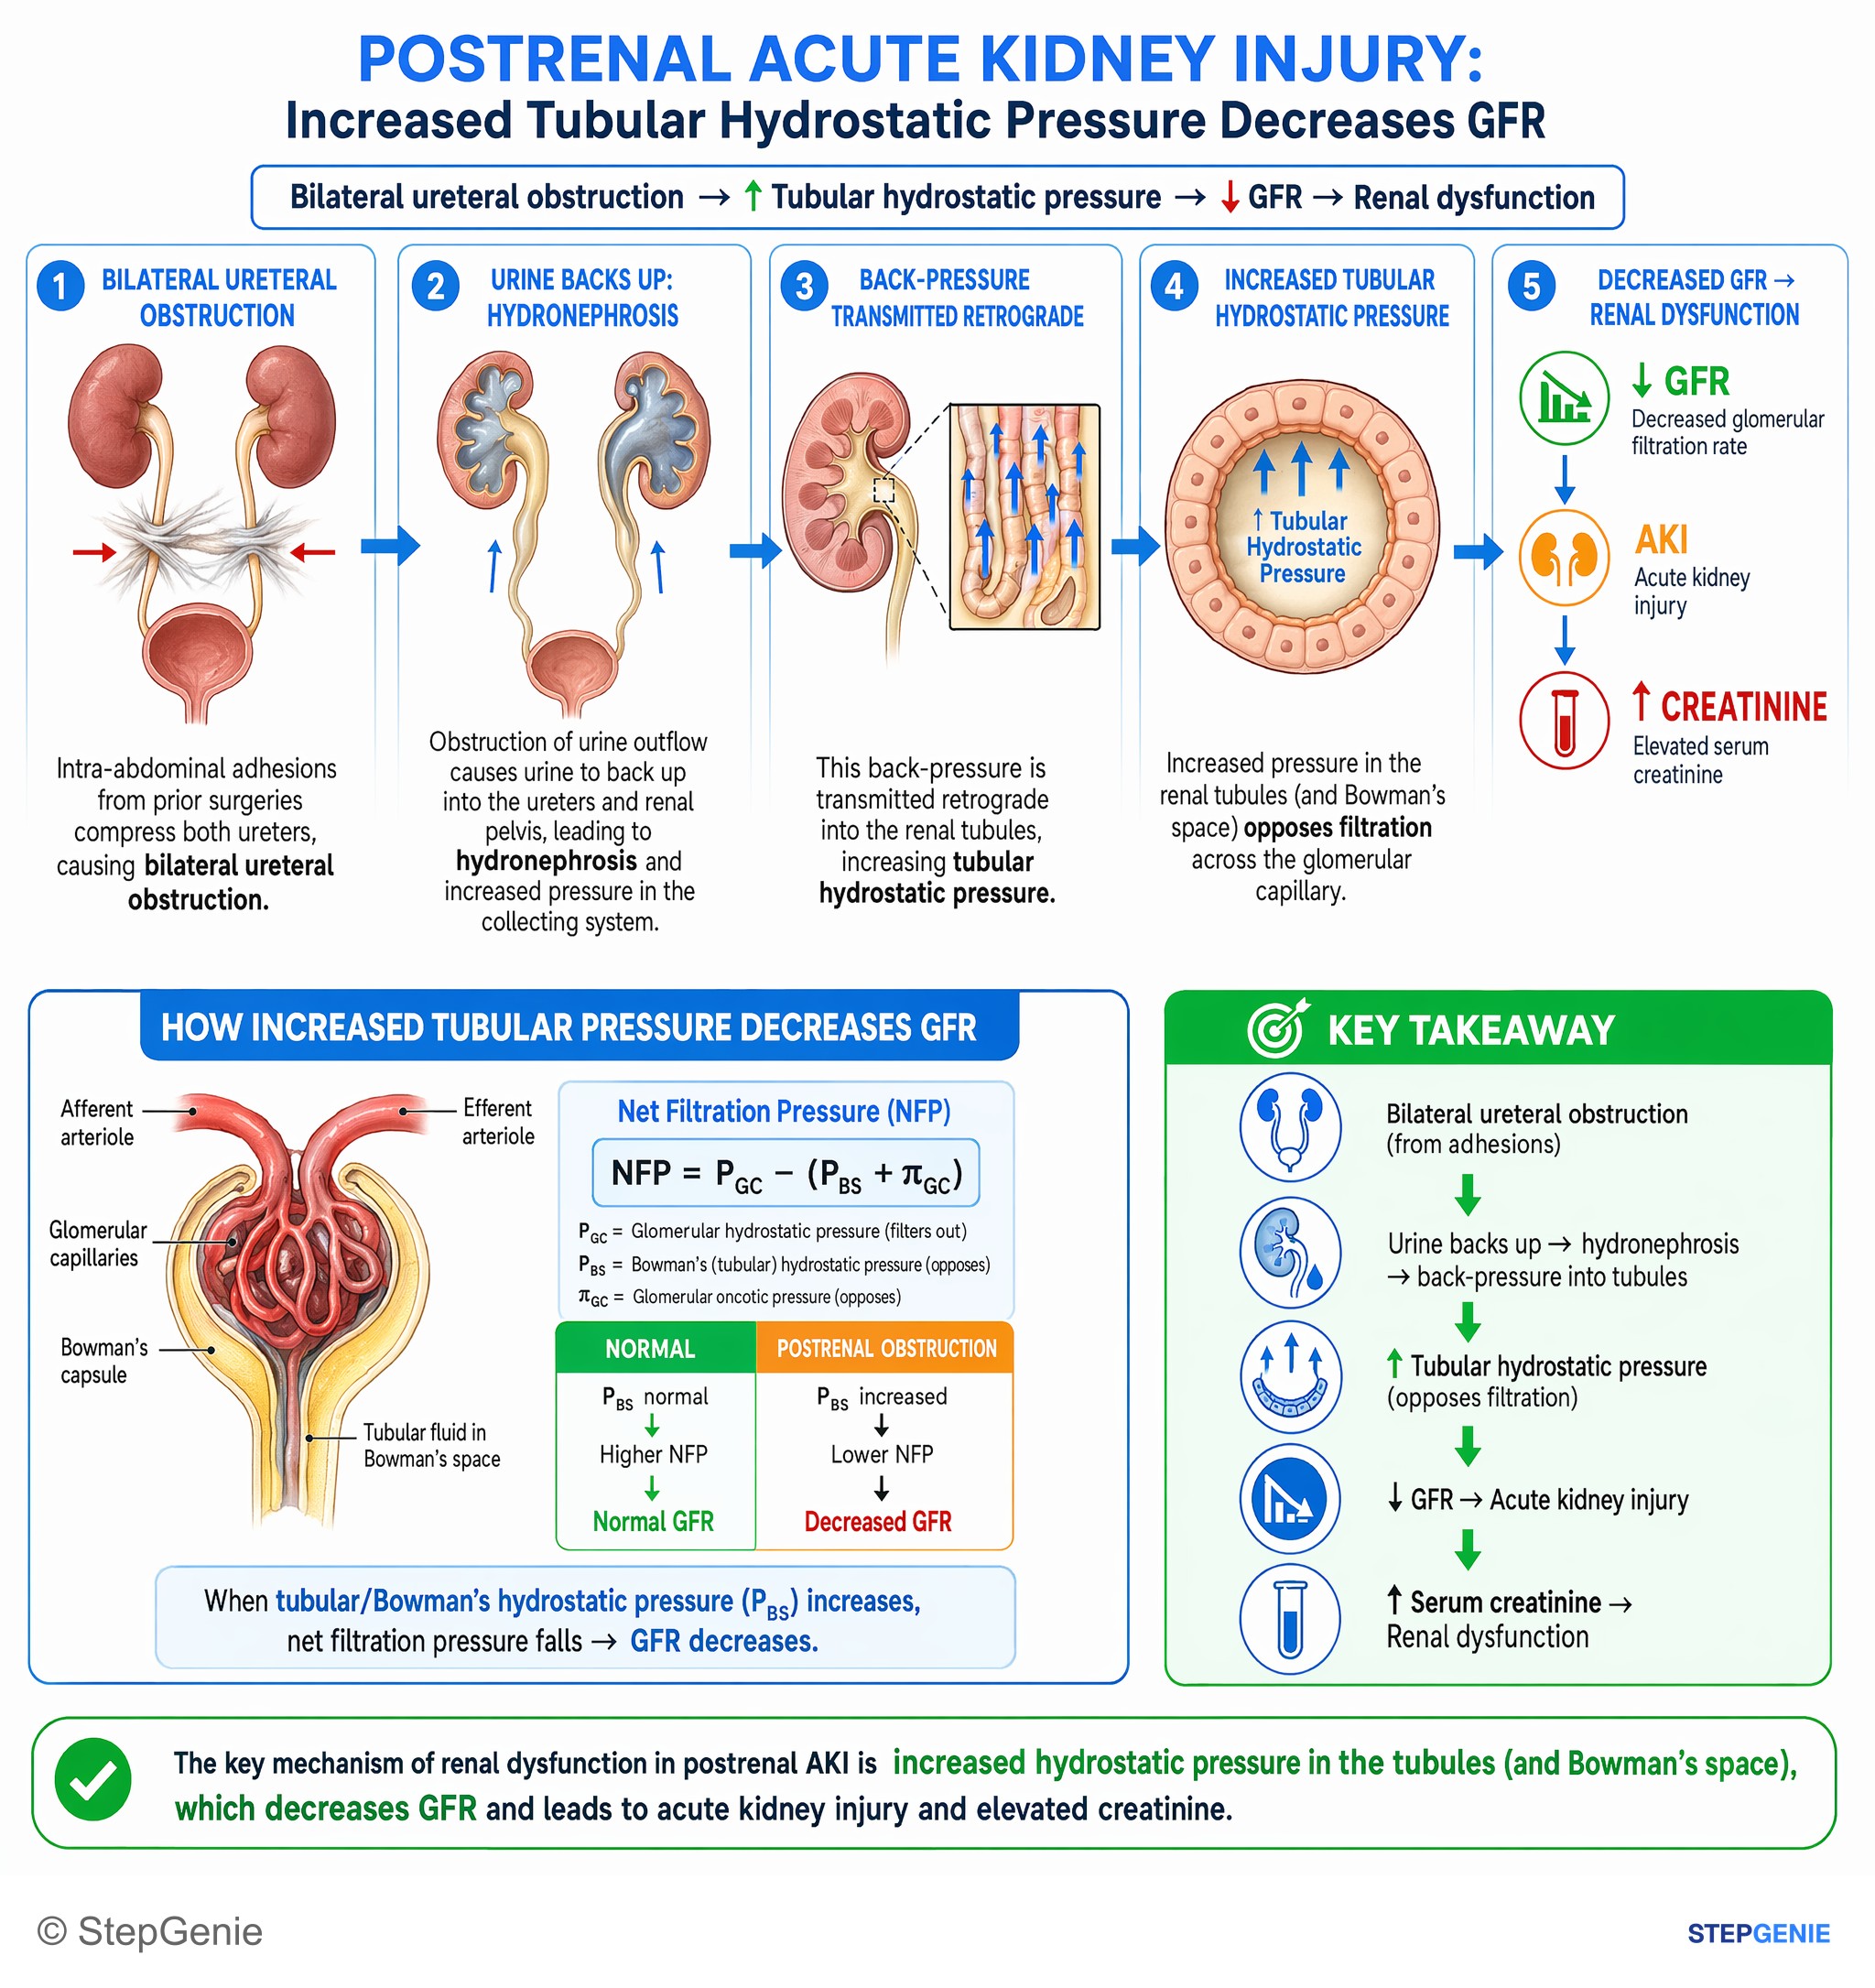
Postrenal acute kidney injury from bilateral ureteral obstruction causes increased tubular hydrostatic pressure, decreasing GFR and…
USMLE Step 1Frequently Asked Questions
What is the Starling equation?
The Starling equation describes fluid movement across a capillary wall: net filtration (Jv) = Kf × [(Pc − Pi) − σ(πc − πi)]. Pc is capillary hydrostatic pressure, Pi interstitial hydrostatic pressure, πc plasma oncotic pressure, πi interstitial oncotic pressure, Kf the filtration coefficient and σ the reflection coefficient for protein. A positive result means filtration out of the capillary and a negative result means absorption. In the classic textbook capillary, the net pressure is about +10 mm Hg at the arteriolar end and −7 mm Hg at the venular end.
What are the four mechanisms of edema?
Edema forms when capillary filtration outruns lymphatic drainage. The four Starling mechanisms are raised capillary hydrostatic pressure (heart failure, venous obstruction, volume overload), low plasma oncotic pressure (nephrotic syndrome, cirrhosis, malnutrition), increased capillary permeability (burns, sepsis, ARDS, angioedema) and lymphatic obstruction (lymph node dissection, radiation, tumor, filariasis). The first two produce protein-poor fluid; leaky capillaries and blocked lymphatics leave protein in the interstitium, which raises interstitial oncotic pressure. Renal sodium retention amplifies most generalized edema.
Do capillaries reabsorb fluid at the venous end?
Only transiently. The classic picture of filtration at the arteriolar end and reabsorption at the venular end is still used for exam calculations, but under the revised Starling principle most capillaries filter slightly along their whole length in the steady state. Absorption happens briefly, for example after a hemorrhage, and stops as protein builds up again just beneath the endothelial glycocalyx. About 8 liters a day returns as lymph instead. Sustained absorption occurs in the kidney's peritubular capillaries, the absorbing intestinal mucosa and lymph nodes.
How does low albumin cause edema?
Albumin supplies roughly 65–70% of plasma oncotic pressure, the main force holding fluid inside capillaries. When albumin falls, as in nephrotic syndrome, cirrhosis, protein-losing enteropathy or malnutrition, net filtration rises. Safety factors such as increased lymph flow and washout of interstitial protein buffer the change, so edema often appears only once serum albumin falls below about 2 g/dL. In nephrotic syndrome, primary renal sodium retention also contributes and can begin before albumin falls.
How do you tell cardiogenic pulmonary edema from ARDS?
Cardiogenic pulmonary edema is a hydrostatic problem: high left atrial pressure raises pulmonary capillary pressure, so the wedge pressure is high, and a value above 18 mm Hg supports a cardiogenic cause. ARDS is a permeability problem: injured endothelium and epithelium leak protein-rich fluid while the wedge pressure is usually normal. The older AECC definition used a wedge-pressure cut-off of 18 mm Hg; the Berlin definition dropped that criterion. Echocardiography and BNP help, and a BNP under 100 pg/mL makes heart failure unlikely.
What is the difference between a transudate and an exudate?
A transudate forms when Starling pressures change across an intact capillary wall, through high hydrostatic pressure or low oncotic pressure, so the fluid is protein-poor; causes include heart failure, cirrhosis and nephrotic syndrome. An exudate forms when the wall itself leaks because of infection, inflammation or cancer, so the fluid is rich in protein and LDH. For pleural fluid, Light's criteria call it an exudate if the protein ratio exceeds 0.5, the LDH ratio exceeds 0.6, or pleural LDH exceeds two-thirds of the serum upper limit of normal.