ST elevation questions are the closest thing Step exams have to a reaction-time sport: you either recognize the pattern in 5 seconds or you start negotiating with yourself about “maybe it’s pericarditis.” This post is a quick-hit, shareable set of STEMI localization patterns + culprit arteries + key ECG clues, with a simple mental “map” you can pull up fast.
The “5‑Second Rule” for ST Elevation: Look, Localize, Link
In 5 seconds, do these three moves:
- Look: Is there ST elevation in contiguous leads (same anatomic region)?
- Localize: Infer the wall (inferior, anterior, lateral, posterior, right ventricle).
- Link: Match to the likely culprit artery (and the classic “gotchas”).
USMLE rule of thumb: ST elevation in ≥2 contiguous leads suggests acute transmural injury (STEMI) until proven otherwise (clinical context matters).
Visual/Mnemonic Device: “Smile, Frown, Mirror”
A fast mental picture that works on test day:
- Smile = Inferior (II, III, aVF look like a “smile” along the bottom of the 12‑lead layout)
- Frown = Anterior (V1–V4 arch across the front like a “frown”)
- Mirror = Posterior (posterior MI is a mirror image on V1–V3: ST depression + tall R)
One-liner: Inferior smiles, anterior frowns, posterior hides in the mirror.
STEMI Patterns at a Glance (High-Yield Table)
| Territory | ST Elevation Leads | Reciprocal Changes (common) | Culprit Artery (most likely) | One-liner |
|---|---|---|---|---|
| Inferior | II, III, aVF | ST ↓ in I, aVL | RCA (most), sometimes LCX | “Bottom leads light up; look for lateral reciprocals.” |
| Lateral (high lateral) | I, aVL | ST ↓ in III, aVF | LCX or diagonal of LAD | “High lateral = I/aVL; inferior reciprocals help.” |
| Lateral (low lateral) | V5–V6 | Variable | LCX | “V5–V6 are your lateral chest leads.” |
| Anterior / Septal | V1–V4 (V1–V2 septal, V3–V4 anterior) | ST ↓ in inferior leads | LAD | “Front of the heart = LAD until proven otherwise.” |
| Extensive anterior | V1–V6 + I + aVL | Often ST ↓ inferior | Proximal LAD (big deal) | “Widespread precordial elevation = proximal LAD = high risk.” |
| Posterior | ST ↓ in V1–V3, tall R in V1–V3, upright T | (True ST ↑ in V7–V9 if placed) | RCA or LCX | “Posterior MI shows up as anterior ST depression with a big R.” |
| Right ventricular (RV) infarct | ST ↑ in V4R (right-sided), often with inferior MI | — | Proximal RCA | “Inferior MI + hypotension? Check V4R and avoid preload killers.” |
The 5-Second “Localization Script” (What to Say in Your Head)
1) Inferior STEMI (II, III, aVF)
Pattern: ST ↑ in II, III, aVF
Quick artery clue: If III > II, think RCA.
One-liner: “Inferior elevation—check I/aVL for reciprocals, suspect RCA if III > II.”
USMLE add-ons
- RCA also supplies AV node → may see bradycardia or AV block.
- Inferior MI + hypotension + clear lungs → suspect RV infarct.
2) Anterior/Septal STEMI (V1–V4)
Pattern: ST ↑ in V1–V4
Culprit: LAD
One-liner: “V1–V4 is LAD—big territory, high risk of pump failure.”
USMLE add-ons
- LAD infarcts can lead to acute LV failure, cardiogenic shock, and malignant ventricular arrhythmias.
- V1–V2 elevation can be septal (LAD septal perforators) and is also where some “mimics” show up—use clinical context.
3) Lateral STEMI (I, aVL, V5–V6)
Pattern: ST ↑ in I, aVL, V5–V6
Culprit: LCX (often), sometimes diagonal branch of LAD
One-liner: “Lateral elevation—think LCX (or diagonal LAD) and look for inferior reciprocals.”
4) Posterior MI (the “Mirror MI”)
Pattern on standard 12‑lead:
- ST depression in V1–V3
- Tall R waves in V1–V3 (mirror of Q waves)
- Often upright T waves
Confirm (if they mention extra leads): ST ↑ in V7–V9
One-liner: “Posterior MI hides as anterior ST depression with tall R—flip the tracing in your head.”
5) Right Ventricular MI (Don’t Miss This One)
When to suspect: Inferior STEMI + hypotension + clear lungs ± JVD
Key lead: V4R (right-sided ECG)
One-liner: “Inferior MI with shock? Get right-sided leads—RV infarct needs preload.”
USMLE management pearl
- Avoid nitrates and aggressive diuresis in RV infarct (they drop preload and can worsen hypotension).
- Treat with IV fluids (carefully) + reperfusion.
“Reciprocal Changes” = Free Points
Reciprocal ST depression strongly supports true STEMI (vs benign early repolarization or pericarditis).
Common pairings:
- Inferior STEMI (II, III, aVF) ↔ reciprocal ST ↓ in I, aVL
- High lateral STEMI (I, aVL) ↔ reciprocal ST ↓ in III, aVF
- Posterior MI: reciprocal idea in reverse—posterior ST ↑ becomes anterior ST ↓ (V1–V3)
STEMI Mimics (How Not to Get Tricked)
You don’t need to diagnose every mimic—just know the most testable differentiators.
| Mimic | ECG Hint | Clinical Hint |
|---|---|---|
| Acute pericarditis | Diffuse concave ST ↑ + PR depression; no true reciprocal changes except aVR/V1 | Pleuritic chest pain, better leaning forward |
| Early repolarization | Concave ST ↑, prominent T waves, stable over time | Young, healthy, asymptomatic |
| LVH / LBBB | ST-T “discordance” (repolarization abnormalities) | Hx HTN, wide QRS (LBBB) |
| Hyperkalemia | Peaked T waves → QRS widening → sine wave | Weakness, renal failure, meds |
USMLE shortcut: Regional, contiguous ST elevation + reciprocal depression + ischemic symptoms = STEMI until proven otherwise.
Ultra-High-Yield “Culprit Artery” Hooks
- LAD: anterior wall, septum (V1–V4) → pump failure
- RCA: inferior wall (II, III, aVF) + AV node → brady/heart block
- LCX: lateral wall (I, aVL, V5–V6) (and can do posterior)
5-Second Practice Drill (Do This Every Time)
When you see ST elevation, force this checklist:
- Which contiguous leads are up? (Inferior vs anterior vs lateral)
- Are there reciprocal changes?
- Could this be posterior? (V1–V3 ST depression + tall R)
- Inferior MI present? If yes, consider RV infarct → check V4R
Mini Summary (Screenshot-Friendly)
- II, III, aVF = Inferior (usually RCA; III > II favors RCA)
- V1–V4 = Anterior/Septal (LAD)
- I, aVL, V5–V6 = Lateral (LCX/diagonal)
- V1–V3 ST ↓ + tall R = Posterior (confirm with V7–V9)
- Inferior MI + hypotension + clear lungs = RV infarct (get V4R, avoid nitrates)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
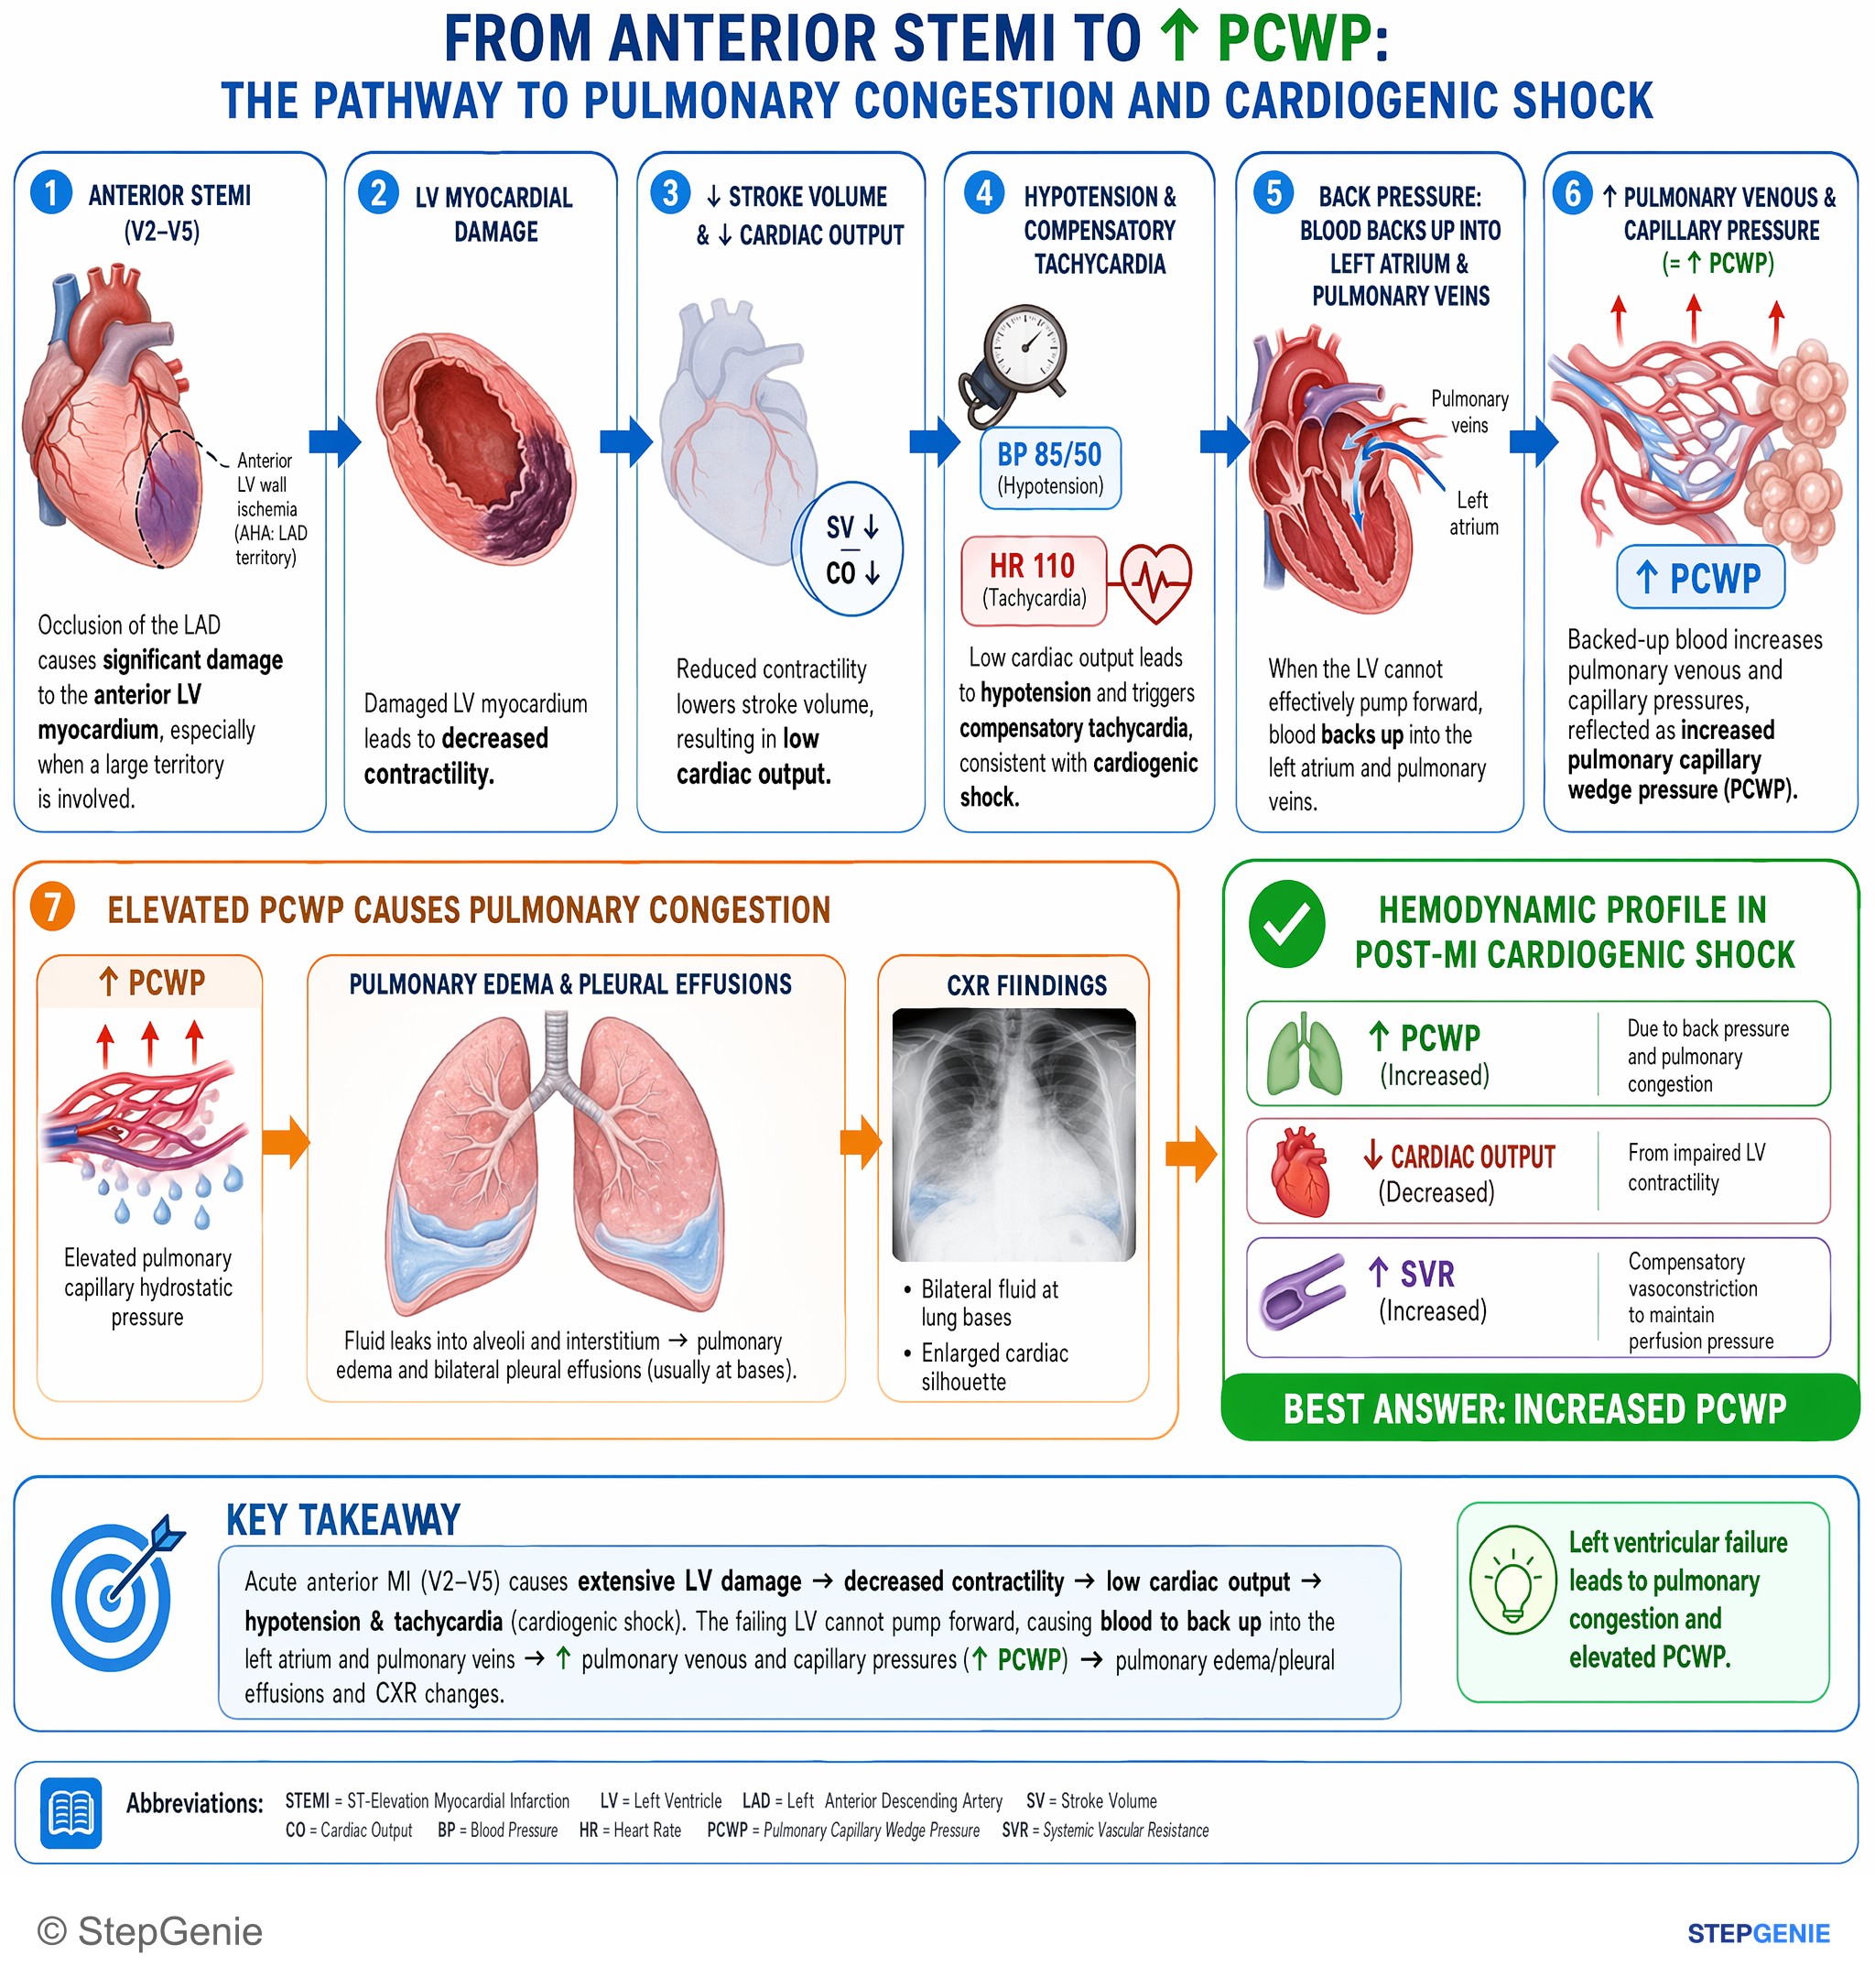
Acute anterior MI with cardiogenic shock → left ventricular failure → blood backs into lungs → elevated pulmonary capillary wedge pressure…
USMLE Step 1Frequently Asked Questions
How do you localize a STEMI in 5 seconds on an ECG?
Use a quick look-localize-link approach. First, look for ST elevation in at least 2 contiguous leads, which suggests acute transmural injury in the right clinical setting. Next, localize the involved wall such as inferior, anterior, lateral, posterior, or right ventricle. Then link that territory to the most likely culprit artery and check for classic reciprocal changes or special clues like posterior mirror findings.
What ECG pattern points to an inferior STEMI and which artery is usually involved?
Inferior STEMI shows ST elevation in leads II, III, and aVF, and the most likely culprit artery is the RCA. A helpful clue is reciprocal ST depression in leads I and aVL. If lead III has more ST elevation than lead II, that further supports RCA involvement. Because the RCA often supplies the AV node, bradycardia or AV block can also appear.
How do you recognize a posterior MI on a standard 12-lead ECG?
Posterior MI usually appears as ST depression in V1 to V3 with tall R waves in those same leads, often with upright T waves. This is the mirror-image pattern of posterior ST elevation, so it can be missed if you only think of ST elevation. If posterior leads are mentioned, true ST elevation in V7 to V9 supports the diagnosis. The usual culprit is the RCA or LCX.
How do you tell STEMI from pericarditis or early repolarization on an ECG?
True STEMI is suggested by regional ST elevation in contiguous leads with reciprocal ST depression and ischemic symptoms. Acute pericarditis more often causes diffuse concave ST elevation with PR depression and usually lacks true reciprocal changes except in aVR or V1. Early repolarization also tends to have concave ST elevation, but it is stable over time and is classically seen in a young, healthy, asymptomatic patient.
When should you suspect a right ventricular infarct and what treatment mistake should you avoid?
Suspect a right ventricular infarct when an inferior STEMI is accompanied by hypotension and clear lungs, sometimes with JVD. The key confirming lead is V4R on a right-sided ECG, and a proximal RCA lesion is most likely. The major management pitfall is giving nitrates or aggressive diuresis, because RV infarction is preload-dependent and those treatments can worsen hypotension. Careful IV fluids plus reperfusion are preferred.