You’re cruising through a parasitology Q-bank block when a vignette drops a classic: “ring-enhancing lesions” + “cat exposure” + “HIV.” You pick Toxoplasma gondii and move on… but the real score boost comes from understanding why every other option is wrong. That’s how you start predicting questions instead of reacting to them.
Tag: Microbiology > Mycology & Parasitology
The Clinical Vignette (Classic USMLE Style)
A 36-year-old man with HIV (CD4 count 45/µL) presents with 1 week of headache, confusion, and fever. Neuro exam shows mild right-sided weakness. MRI reveals multiple ring-enhancing lesions in the basal ganglia with surrounding edema. He recently adopted a cat and occasionally cleans the litter box.
Question: What is the most likely cause?
Correct Answer: Toxoplasma gondii
Why it fits
This is the prototypical setup for toxoplasmic encephalitis in advanced HIV/AIDS:
- Risk factor: CD4 < 100/µL (especially < 50)
- Presentation: headache, fever, focal neurologic deficits, seizures, altered mental status
- Imaging: multiple ring-enhancing lesions, classically in basal ganglia
- Exposure: cat feces (oocysts) and undercooked meat (tissue cysts)
High-yield microbiology + pathogenesis
- Definitive host: cat (sexual reproduction occurs in feline GI tract)
- Infectious forms:
- Oocysts from cat feces (soil/litter box exposure)
- Tissue cysts (bradyzoites) in undercooked meat (often pork/lamb)
- In immunocompromised patients, disease often represents reactivation of latent tissue cysts.
Diagnosis (what they’ll test)
- In AIDS with compatible imaging: often presumptive diagnosis
- Supporting tests:
- Toxo IgG (past exposure; many AIDS patients are IgG+)
- PCR of CSF can help (variable sensitivity)
- Definitive diagnosis: brain biopsy (rarely first-line)
Treatment (Step 2 favorite)
- Pyrimethamine + sulfadiazine + leucovorin (folinic acid)
- Leucovorin prevents pyrimethamine-induced bone marrow suppression
- Alternative: pyrimethamine + clindamycin (if sulfa allergy)
- TMP-SMX prophylaxis helps prevent toxo reactivation in HIV (also covers Pneumocystis)
Distractor Breakdown: Why the Other Choices Matter
Below are common answer choices that show up in the same clinical neighborhood (HIV + brain lesions + neurologic symptoms). The key is learning the “one detail” that flips you to the right diagnosis.
1) Primary CNS Lymphoma (EBV-associated)
Why they’ll tempt you: Also causes ring-enhancing lesions in AIDS.
How to tell it apart
- Often solitary lesion (though can be multiple)
- Strong association with EBV
- More likely when CD4 < 50/µL
- May have B symptoms or subacute progression
High-yield diagnostic clue
- Thallium-201 SPECT: typically high uptake in lymphoma (toxoplasma tends to be low)
- EBV DNA in CSF supports lymphoma
Rule of thumb:
- Multiple lesions + basal ganglia + cat/meat exposure → Toxo
- Solitary lesion + EBV markers → Primary CNS lymphoma
2) Neurocysticercosis (Taenia solium)
Why they’ll tempt you: Ring-enhancing brain lesions are classic here too.
How to tell it apart
- More often presents with seizures as the dominant symptom
- Epidemiology: travel or immigration from areas with poor sanitation (Latin America, sub-Saharan Africa, parts of Asia)
- Source: ingestion of eggs shed in human feces (fecal–oral), not pork ingestion per se (pork → intestinal tapeworm; eggs → cysticercosis)
High-yield imaging clue
- Calcified lesions in later stages
- Sometimes a “hole-with-dot” sign (scolex)
USMLE trap: “Undercooked pork” alone doesn’t guarantee neurocysticercosis—eggs cause CNS disease.
3) Cryptococcus neoformans
Why they’ll tempt you: Very common in AIDS; neuro symptoms.
How to tell it apart
- Typically causes meningitis/meningoencephalitis, not focal ring-enhancing mass lesions
- Symptoms: headache, fever, photophobia; can have altered mental status
- Often elevated intracranial pressure (ICP) is a major issue
High-yield diagnostic clues
- CSF: ↑ opening pressure, ↓ glucose, ↑ protein, lymphocytic predominance
- India ink (encapsulated yeast) or cryptococcal antigen in CSF/serum
- Exposure association: pigeon droppings
Treatment
- Induction: amphotericin B + flucytosine
- Consolidation/maintenance: fluconazole
- Repeated lumbar punctures to manage ICP can be lifesaving
4) Histoplasma capsulatum
Why they’ll tempt you: Another opportunistic infection; endemic fungus; can disseminate in AIDS.
How to tell it apart
- Primarily a pulmonary infection; disseminated disease can occur, but classic CNS ring lesions aren’t the go-to presentation
- Geography/exposure: Ohio & Mississippi River valleys, bat/bird droppings, caves
High-yield testable pearls
- Yeast inside macrophages
- Diagnosis: urine antigen (especially in disseminated disease)
Treatment
- Itraconazole for mild/moderate
- Amphotericin B for severe disseminated disease
5) JC Virus (Progressive Multifocal Leukoencephalopathy, PML)
Why they’ll tempt you: HIV + neuro deficits.
How to tell it apart
- PML causes demyelination, not mass lesions
- Symptoms: progressive focal neuro deficits (weakness, vision changes, cognitive decline)
Imaging clue
- MRI: non-enhancing white matter lesions (classically no ring enhancement, no mass effect)
High-yield diagnosis
- JC virus PCR in CSF
Treatment concept
- Immune reconstitution with ART is key
6) Amebic Brain Abscess (Entamoeba histolytica / Naegleria / Acanthamoeba)
They pop up as distractors because “brain + infection” feels plausible.
Entamoeba histolytica
- More tied to liver abscess (“anchovy paste”) than brain lesions.
Naegleria fowleri
- Rapidly fatal primary amebic meningoencephalitis
- Warm freshwater + diving/swimming, travels up cribriform plate
- Not a “multiple ring-enhancing lesions in basal ganglia” story.
Acanthamoeba
- Causes granulomatous amebic encephalitis in immunocompromised, but much less common and not the classic board answer compared with toxo/lymphoma/crypto.
The High-Yield Comparison Table (Memorize This Pattern)
| Condition | Typical Setting | Imaging | Key Clues | Best Next Diagnostic Clue |
|---|---|---|---|---|
| Toxoplasma gondii | AIDS, CD4 < 100 | Multiple ring-enhancing, often basal ganglia | Cat feces, undercooked meat; reactivation | Empiric tx response; Toxo IgG supportive |
| Primary CNS lymphoma (EBV) | AIDS, CD4 < 50 | Often solitary ring-enhancing | EBV association | Thallium uptake; EBV DNA in CSF |
| Cryptococcus | AIDS | Usually no focal ring lesions; meningitis picture | High ICP; pigeon droppings | Cryptococcal Ag; India ink |
| Neurocysticercosis | Travel/endemic regions | Ring-enhancing ± calcifications | Seizures; “dot” scolex | Imaging + serology |
| PML (JC virus) | AIDS | Non-enhancing white matter lesions | Progressive deficits, no mass effect | JC PCR in CSF |
USMLE “Answer Choice” Pitfalls You Can Avoid
- Ring-enhancing lesions are not automatically toxo—always compare with:
- EBV lymphoma (often solitary; thallium uptake)
- Neurocysticercosis (seizures, calcifications, endemic travel)
- Cryptococcus is the “headache + high opening pressure” opportunist, not the “basal ganglia ring lesions” one.
- PML is demyelination: think non-enhancing white matter, not rings.
Rapid-Fire Recall (What to Say in 10 Seconds on Test Day)
- HIV + CD4 < 100 + multiple ring-enhancing brain lesions (basal ganglia) → Toxoplasma gondii
- Treat: pyrimethamine + sulfadiazine + leucovorin
- Biggest look-alike: primary CNS lymphoma (EBV) → often solitary, thallium uptake, EBV DNA in CSF
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
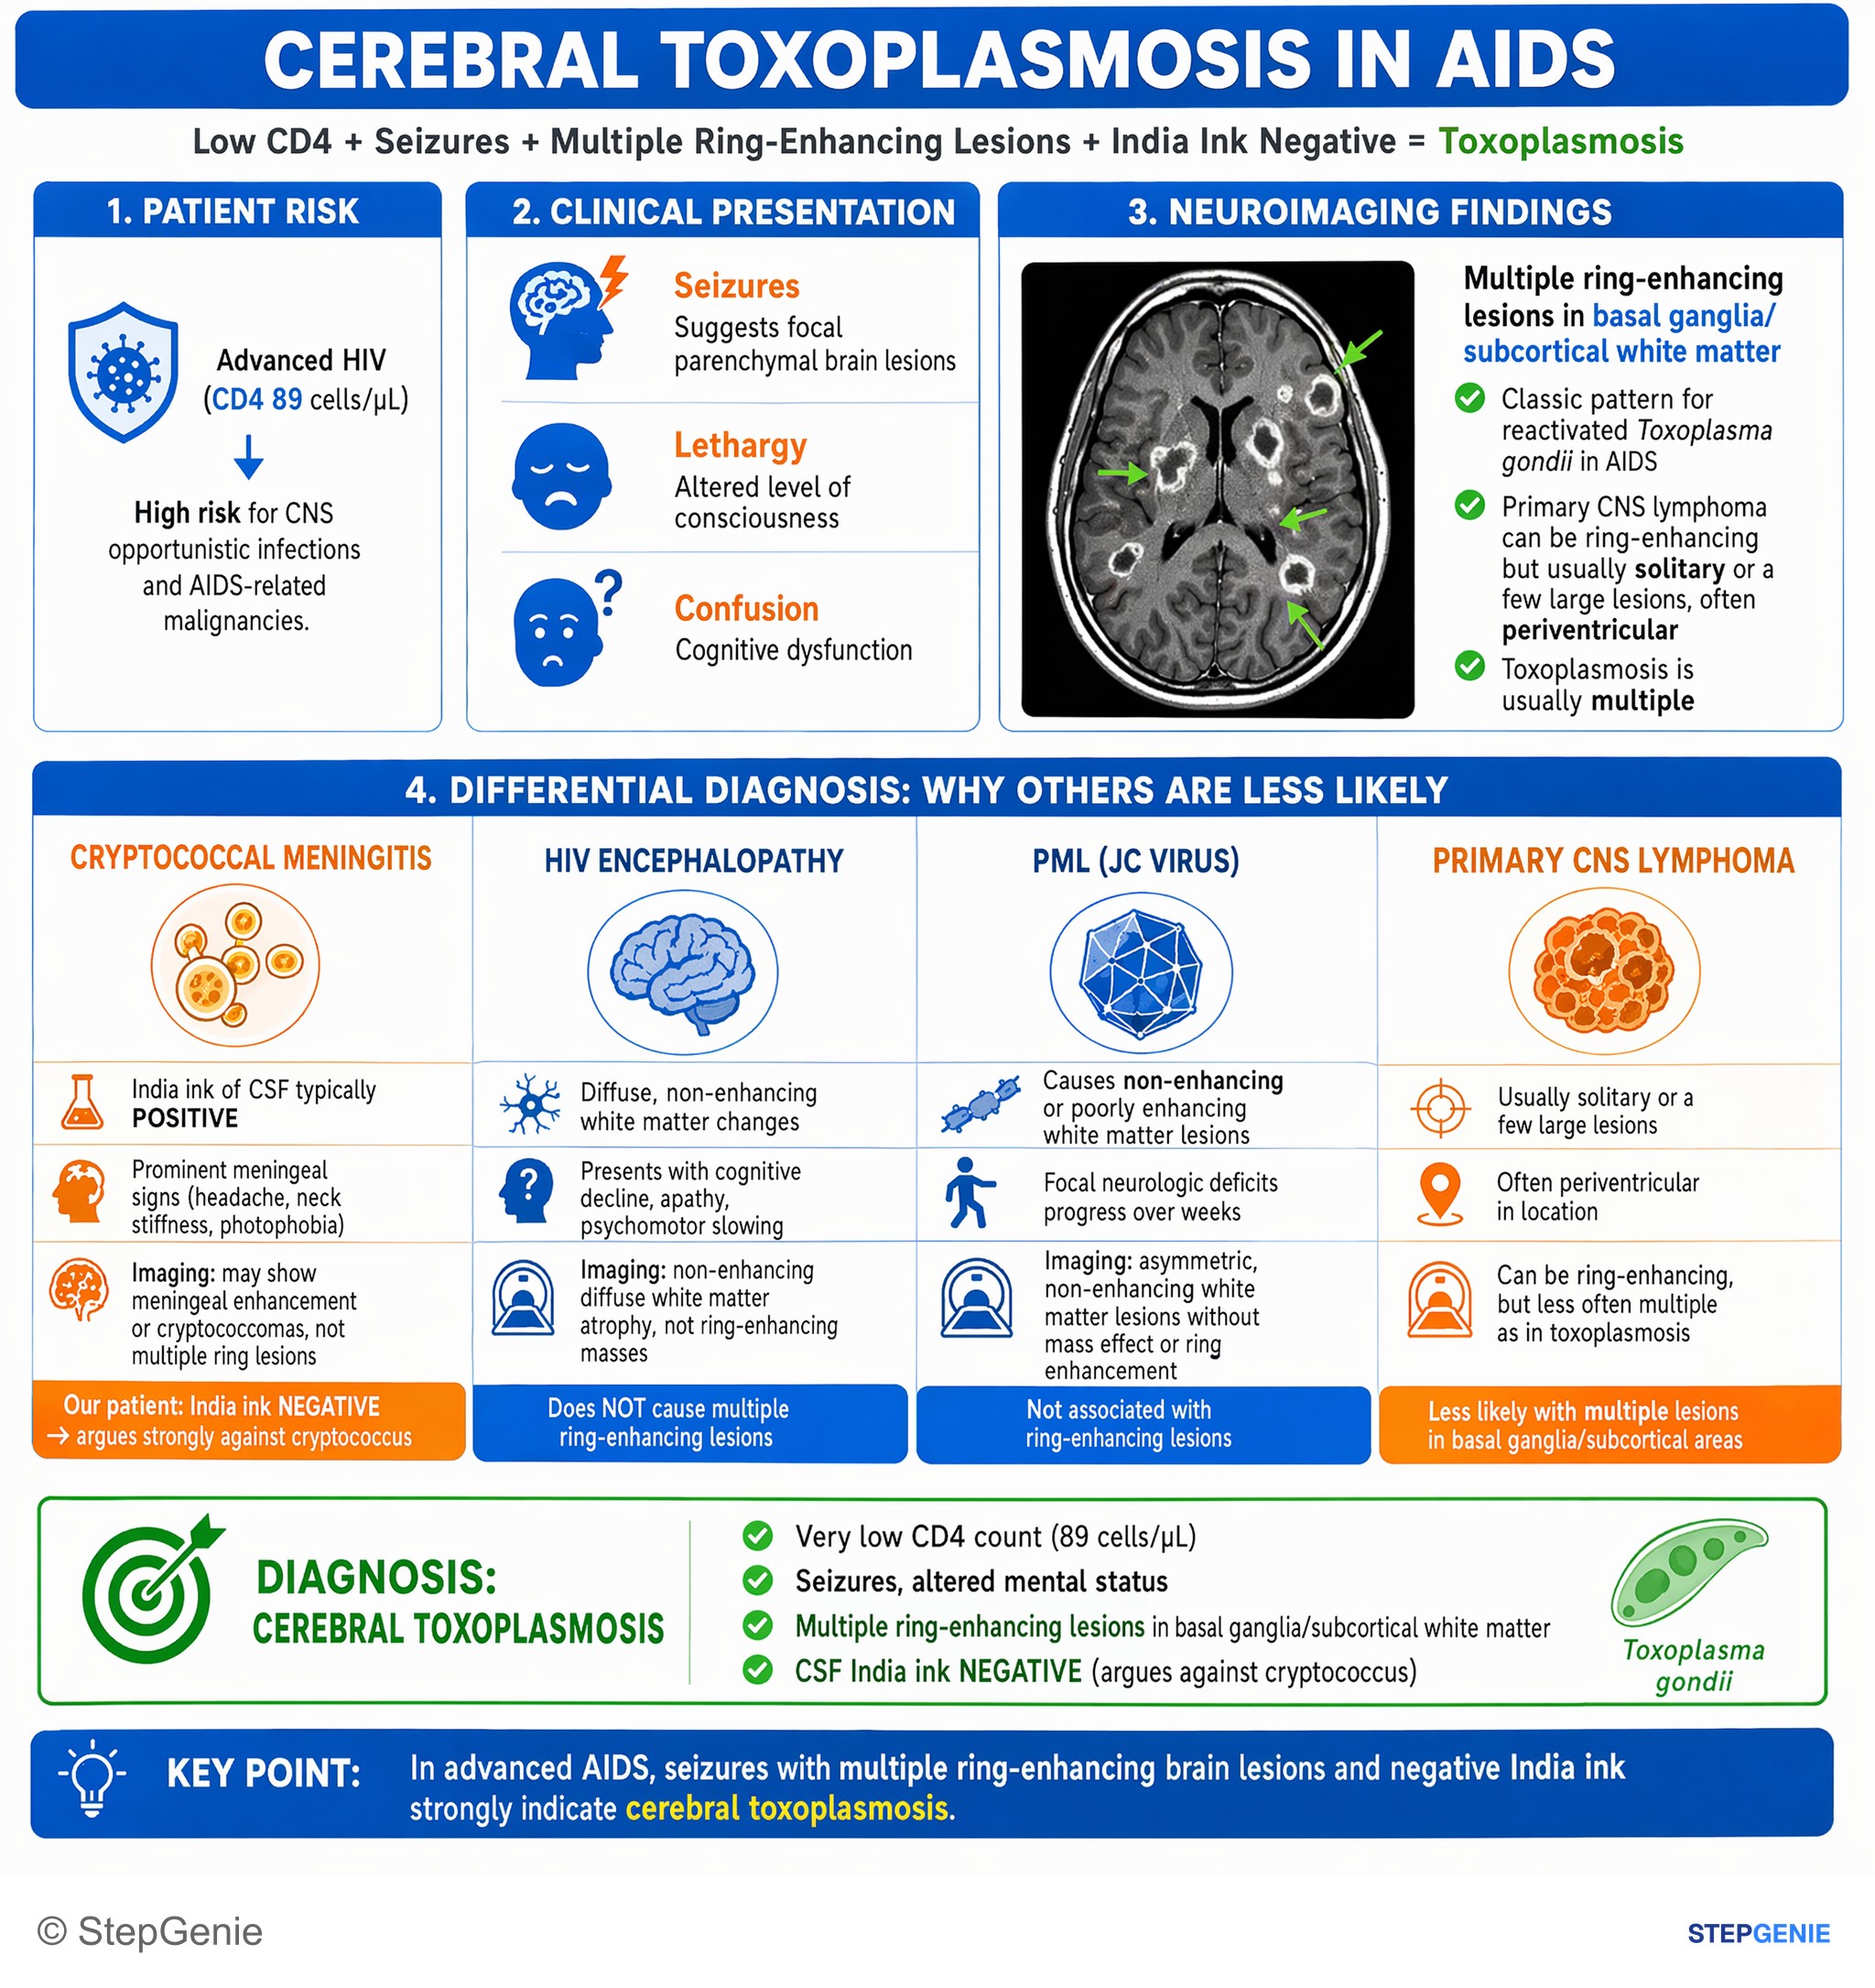
Cerebral toxoplasmosis in AIDS: very low CD4, seizures/AMS, multiple ring-enhancing lesions in basal ganglia; CSF India ink negative…
USMLE Step 2Frequently Asked Questions
How do you tell toxoplasmic encephalitis from primary CNS lymphoma in HIV with ring-enhancing lesions?
Toxoplasmic encephalitis is more likely when an HIV patient has multiple ring-enhancing lesions in the basal ganglia plus cat or undercooked meat exposure. Primary CNS lymphoma is often solitary, has a strong EBV association, and is supported by EBV DNA in CSF. Thallium-201 SPECT can also help because lymphoma typically shows high uptake, whereas toxoplasma tends to show low uptake.
Why does Toxoplasma gondii cause brain lesions in advanced HIV?
In advanced HIV, Toxoplasma gondii brain disease usually results from reactivation of latent tissue cysts. Immunocompromised patients often reactivate prior infection rather than acquire a brand-new one. This leads to toxoplasmic encephalitis, which classically presents with headache, fever, focal neurologic deficits, seizures, altered mental status, and multiple ring-enhancing lesions in the basal ganglia.
What is the first-line treatment for toxoplasmic encephalitis?
The first-line treatment is pyrimethamine plus sulfadiazine plus leucovorin. This is the classic regimen for toxoplasmic encephalitis in HIV patients. Leucovorin is added specifically to prevent pyrimethamine-induced bone marrow suppression. If the patient has a sulfa allergy, pyrimethamine plus clindamycin is an alternative, and TMP-SMX prophylaxis helps prevent toxoplasma reactivation in HIV.
How do you differentiate toxoplasmosis from cryptococcal infection in AIDS patients?
Toxoplasmosis usually causes focal brain mass lesions, while cryptococcal disease more often causes meningitis or meningoencephalitis. Toxoplasmosis produces multiple ring-enhancing lesions, often in the basal ganglia, with focal deficits. Cryptococcus is associated with headache, fever, photophobia, altered mental status, and especially elevated intracranial pressure, with CSF findings such as high opening pressure and cryptococcal antigen positivity.
Why is undercooked pork not enough to diagnose neurocysticercosis?
Undercooked pork alone does not diagnose neurocysticercosis because CNS disease comes from ingesting Taenia solium eggs, not from eating pork itself. Pork is linked to intestinal tapeworm infection, whereas fecal-oral ingestion of eggs causes cysticercosis. Neurocysticercosis also more often presents with seizures and may show calcified lesions or a hole-with-dot scolex sign on imaging.