You’re doing a Q-bank set, you see bloody diarrhea, maybe a liver abscess, and you think: “Okay, Entamoeba histolytica.” Then the question hits you with five answer choices that all sound vaguely GI-ish, and suddenly you’re second-guessing everything. This post is built to fix that: one tight clinical vignette, the correct answer, and then a systematic teardown of the distractors—because on Step, why the others are wrong is where the points live.
Tag: Microbiology > Mycology & Parasitology
The Vignette (Classic Board Style)
A 32-year-old man returns from a trip to India. He has 1 week of abdominal cramping and bloody diarrhea. He is afebrile. Exam shows mild diffuse abdominal tenderness. Stool studies show fecal leukocytes. Ova and parasite exam demonstrates cysts with multiple nuclei, and microscopy reveals trophozoites containing ingested red blood cells.
Which organism is the most likely cause?
A. Giardia lamblia
B. Entamoeba histolytica
C. Cryptosporidium parvum
D. Balantidium coli
E. Ascaris lumbricoides
The Correct Answer: B. Entamoeba histolytica
Why it’s correct (the “slam dunk” clues)
The two highest-yield clues in this stem are:
- Bloody diarrhea after travel to an endemic area (fecal–oral transmission)
- Trophozoites with ingested RBCs → this is the classic distinguishing feature of E. histolytica (pathogenic) vs nonpathogenic Entamoeba species
High-yield microbiology + pathogenesis
- Organism type: Protozoan amoeba
- Transmission: Fecal–oral ingestion of cysts (often via contaminated food/water)
- Infective form: Cyst
- Diagnostic forms:
- Cysts (typically 1–4 nuclei; classically mature cysts have 4 nuclei)
- Trophozoites in stool or tissue; RBC ingestion is highly suggestive/diagnostic
- Mechanism of disease: Flask-shaped ulcers in the colonic mucosa due to invasion
- Clinical syndromes:
- Amebic dysentery (bloody diarrhea, abdominal pain)
- Amebic liver abscess (RUQ pain, fever, “anchovy paste” aspirate)
High-yield treatment (Step-ready)
- Invasive disease (dysentery, liver abscess):
- Metronidazole (or tinidazole) PLUS a luminal agent to clear cysts
- Luminal eradication options:
- Paromomycin (often tested), iodoquinol, or diloxanide (less commonly used in US)
Test-taking pearl: Metronidazole treats the trophozoites in tissue, but you still need a luminal agent to prevent relapse and transmission.
“Why Every Answer Choice Matters”: The Distractor Breakdown
A. Giardia lamblia — Wrong because it causes non-bloody, malabsorptive diarrhea
How it tries to trick you: Travel + diarrhea + parasites.
Key distinguishing features
- Watery, greasy, foul-smelling diarrhea (steatorrhea), bloating, flatulence
- No blood (noninvasive; does not cause dysentery)
- Often from streams/daycare (“beaver fever”)
- Pear-shaped trophozoites with 2 nuclei (“old man with glasses”); cysts in stool
Treatment: Metronidazole (or tinidazole); nitazoxanide is another option.
Board tip: If they emphasize fat malabsorption or scum on the toilet water, think Giardia, not Entamoeba.
C. Cryptosporidium parvum — Wrong because it’s watery diarrhea + acid-fast oocysts
How it tries to trick you: Parasite + diarrhea after travel/water exposure.
Key distinguishing features
- Watery (not bloody) diarrhea
- Can be severe/chronic in AIDS (especially CD4 < 100)
- Acid-fast oocysts in stool; associated with contaminated water (including pools)
Treatment: Supportive in immunocompetent; nitazoxanide can be used. In AIDS, optimize ART.
Board tip: If the question says “acid-fast oocysts,” it’s usually Cryptosporidium, Cyclospora, or Cystoisospora—not Entamoeba.
D. Balantidium coli — Wrong on probability and classic association (pigs)
How it tries to trick you: It can cause dysentery, so it’s a believable distractor.
Key distinguishing features
- Ciliated protozoan (the big unique hook)
- Classically linked to pigs (pig farmers, exposure to pig feces)
- Can cause colitis and dysentery, but it’s much less common than E. histolytica
- Identifying feature: large trophozoites with cilia (and a prominent macronucleus)
Treatment: Tetracycline is often cited; metronidazole can also be used.
Board tip: If there’s no pig exposure and they hand you “RBCs inside trophozoites,” the test writer is begging for E. histolytica.
E. Ascaris lumbricoides — Wrong because it causes obstruction and lung migration, not dysentery
How it tries to trick you: Helminths are common worldwide; travel history makes it tempting.
Key distinguishing features
- Large roundworm; transmission via ingestion of eggs (fecal–oral)
- Clinical:
- Often asymptomatic
- Intestinal obstruction (esp kids)
- Löffler syndrome: transient pneumonitis, eosinophilia due to larval lung migration
Diagnosis: Eggs in stool; sometimes worms seen.
Treatment: Albendazole or mebendazole.
Board tip: If they emphasize eosinophilia + pulmonary symptoms + later GI issues, think Ascaris (or other helminths), not amoebic dysentery.
Quick Comparison Table (Use This for Rapid Elimination)
| Organism | Type | Stool Pattern | Classic Clue | Key Diagnostic Finding | First-line Treatment |
|---|---|---|---|---|---|
| Entamoeba histolytica | Amoeba (protozoan) | Bloody diarrhea, flask-shaped ulcers; +/- liver abscess | Trophozoites with ingested RBCs | O&P; trophs with RBCs; antigen/PCR | Metronidazole + paromomycin |
| Giardia lamblia | Flagellated protozoan | Non-bloody, greasy diarrhea | Stream/daycare, malabsorption | Cysts/trophs; stool antigen | Metronidazole |
| Cryptosporidium parvum | Protozoan | Watery diarrhea | AIDS, pool water | Acid-fast oocysts | Nitazoxanide (supportive/ART) |
| Balantidium coli | Ciliated protozoan | Can be bloody | Pig exposure, cilia | Large ciliated trophozoites | Tetracycline (often) |
| Ascaris lumbricoides | Helminth | Not dysentery | Obstruction; lung migration | Eggs in stool; eosinophilia | Albendazole |
Extra High-Yield Nuggets USMLE Loves
1) E. histolytica vs inflammatory bacterial diarrhea
Both can cause bloody diarrhea and fecal leukocytes. The parasite clues include:
- Travel + cysts/trophozoites on O&P
- RBC ingestion by trophozoites (highly suggestive)
2) Liver abscess: what’s “classic” vs what’s “actually tested”
- Classic description: “anchovy paste” aspirate
- High-yield nuance: aspirate is often sterile for bacteria (it’s protozoal), but serology can help
- Symptoms: RUQ pain, fever, tender hepatomegaly; diarrhea may be absent
3) Treatment strategy is two-step for a reason
- Metronidazole hits invasive trophozoites
- Luminal agent clears cysts in the gut → prevents relapse and limits transmission
Takeaway (What to Remember on Test Day)
If you see bloody diarrhea plus trophozoites with ingested RBCs, don’t overthink it: it’s Entamoeba histolytica, treated with metronidazole + luminal therapy (paromomycin). Then use the distractors to your advantage: greasy = Giardia, acid-fast watery = Crypto, pigs/cilia = Balantidium, obstruction/lung migration = Ascaris.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
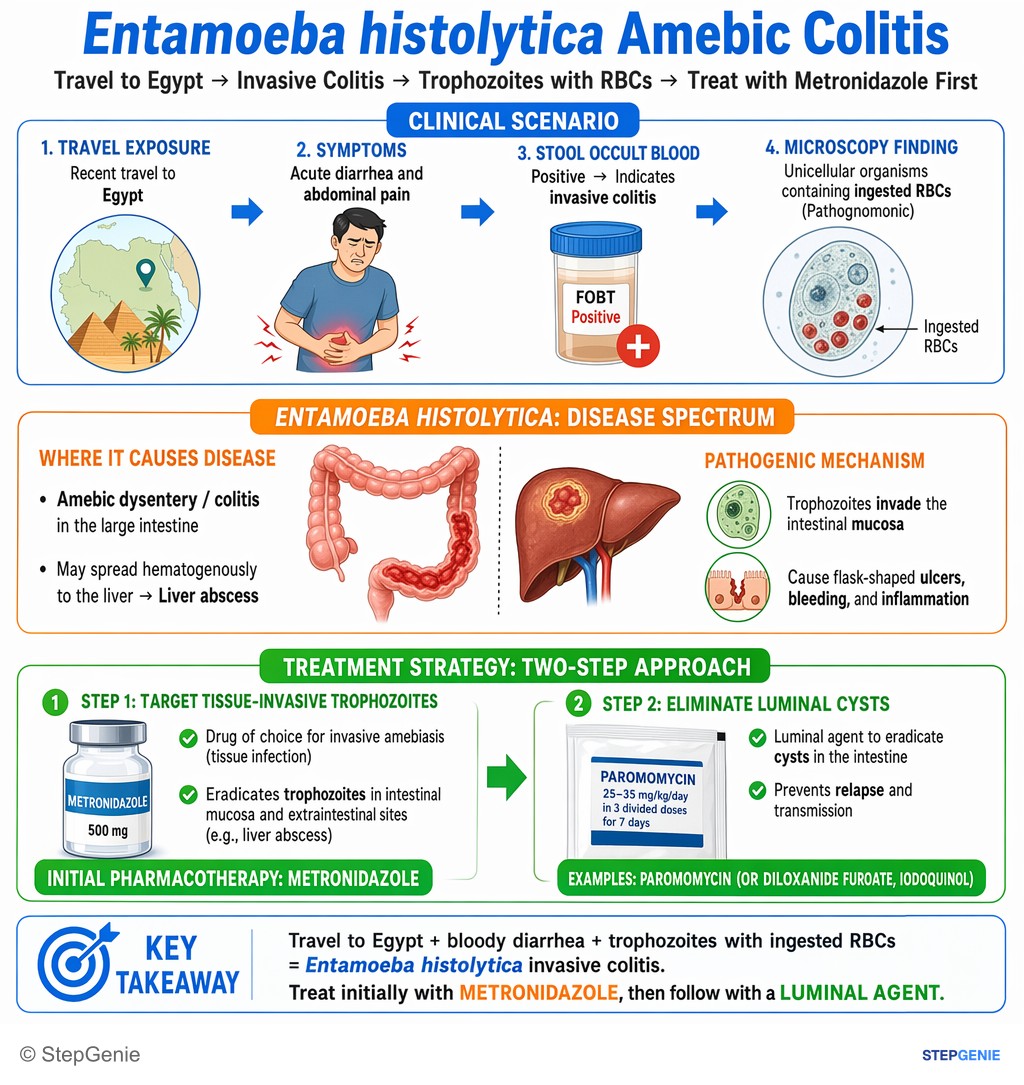
Entamoeba histolytica amebic colitis after travel; trophozoites with ingested RBCs → treat initially with metronidazole, then a luminal…
USMLE Step 2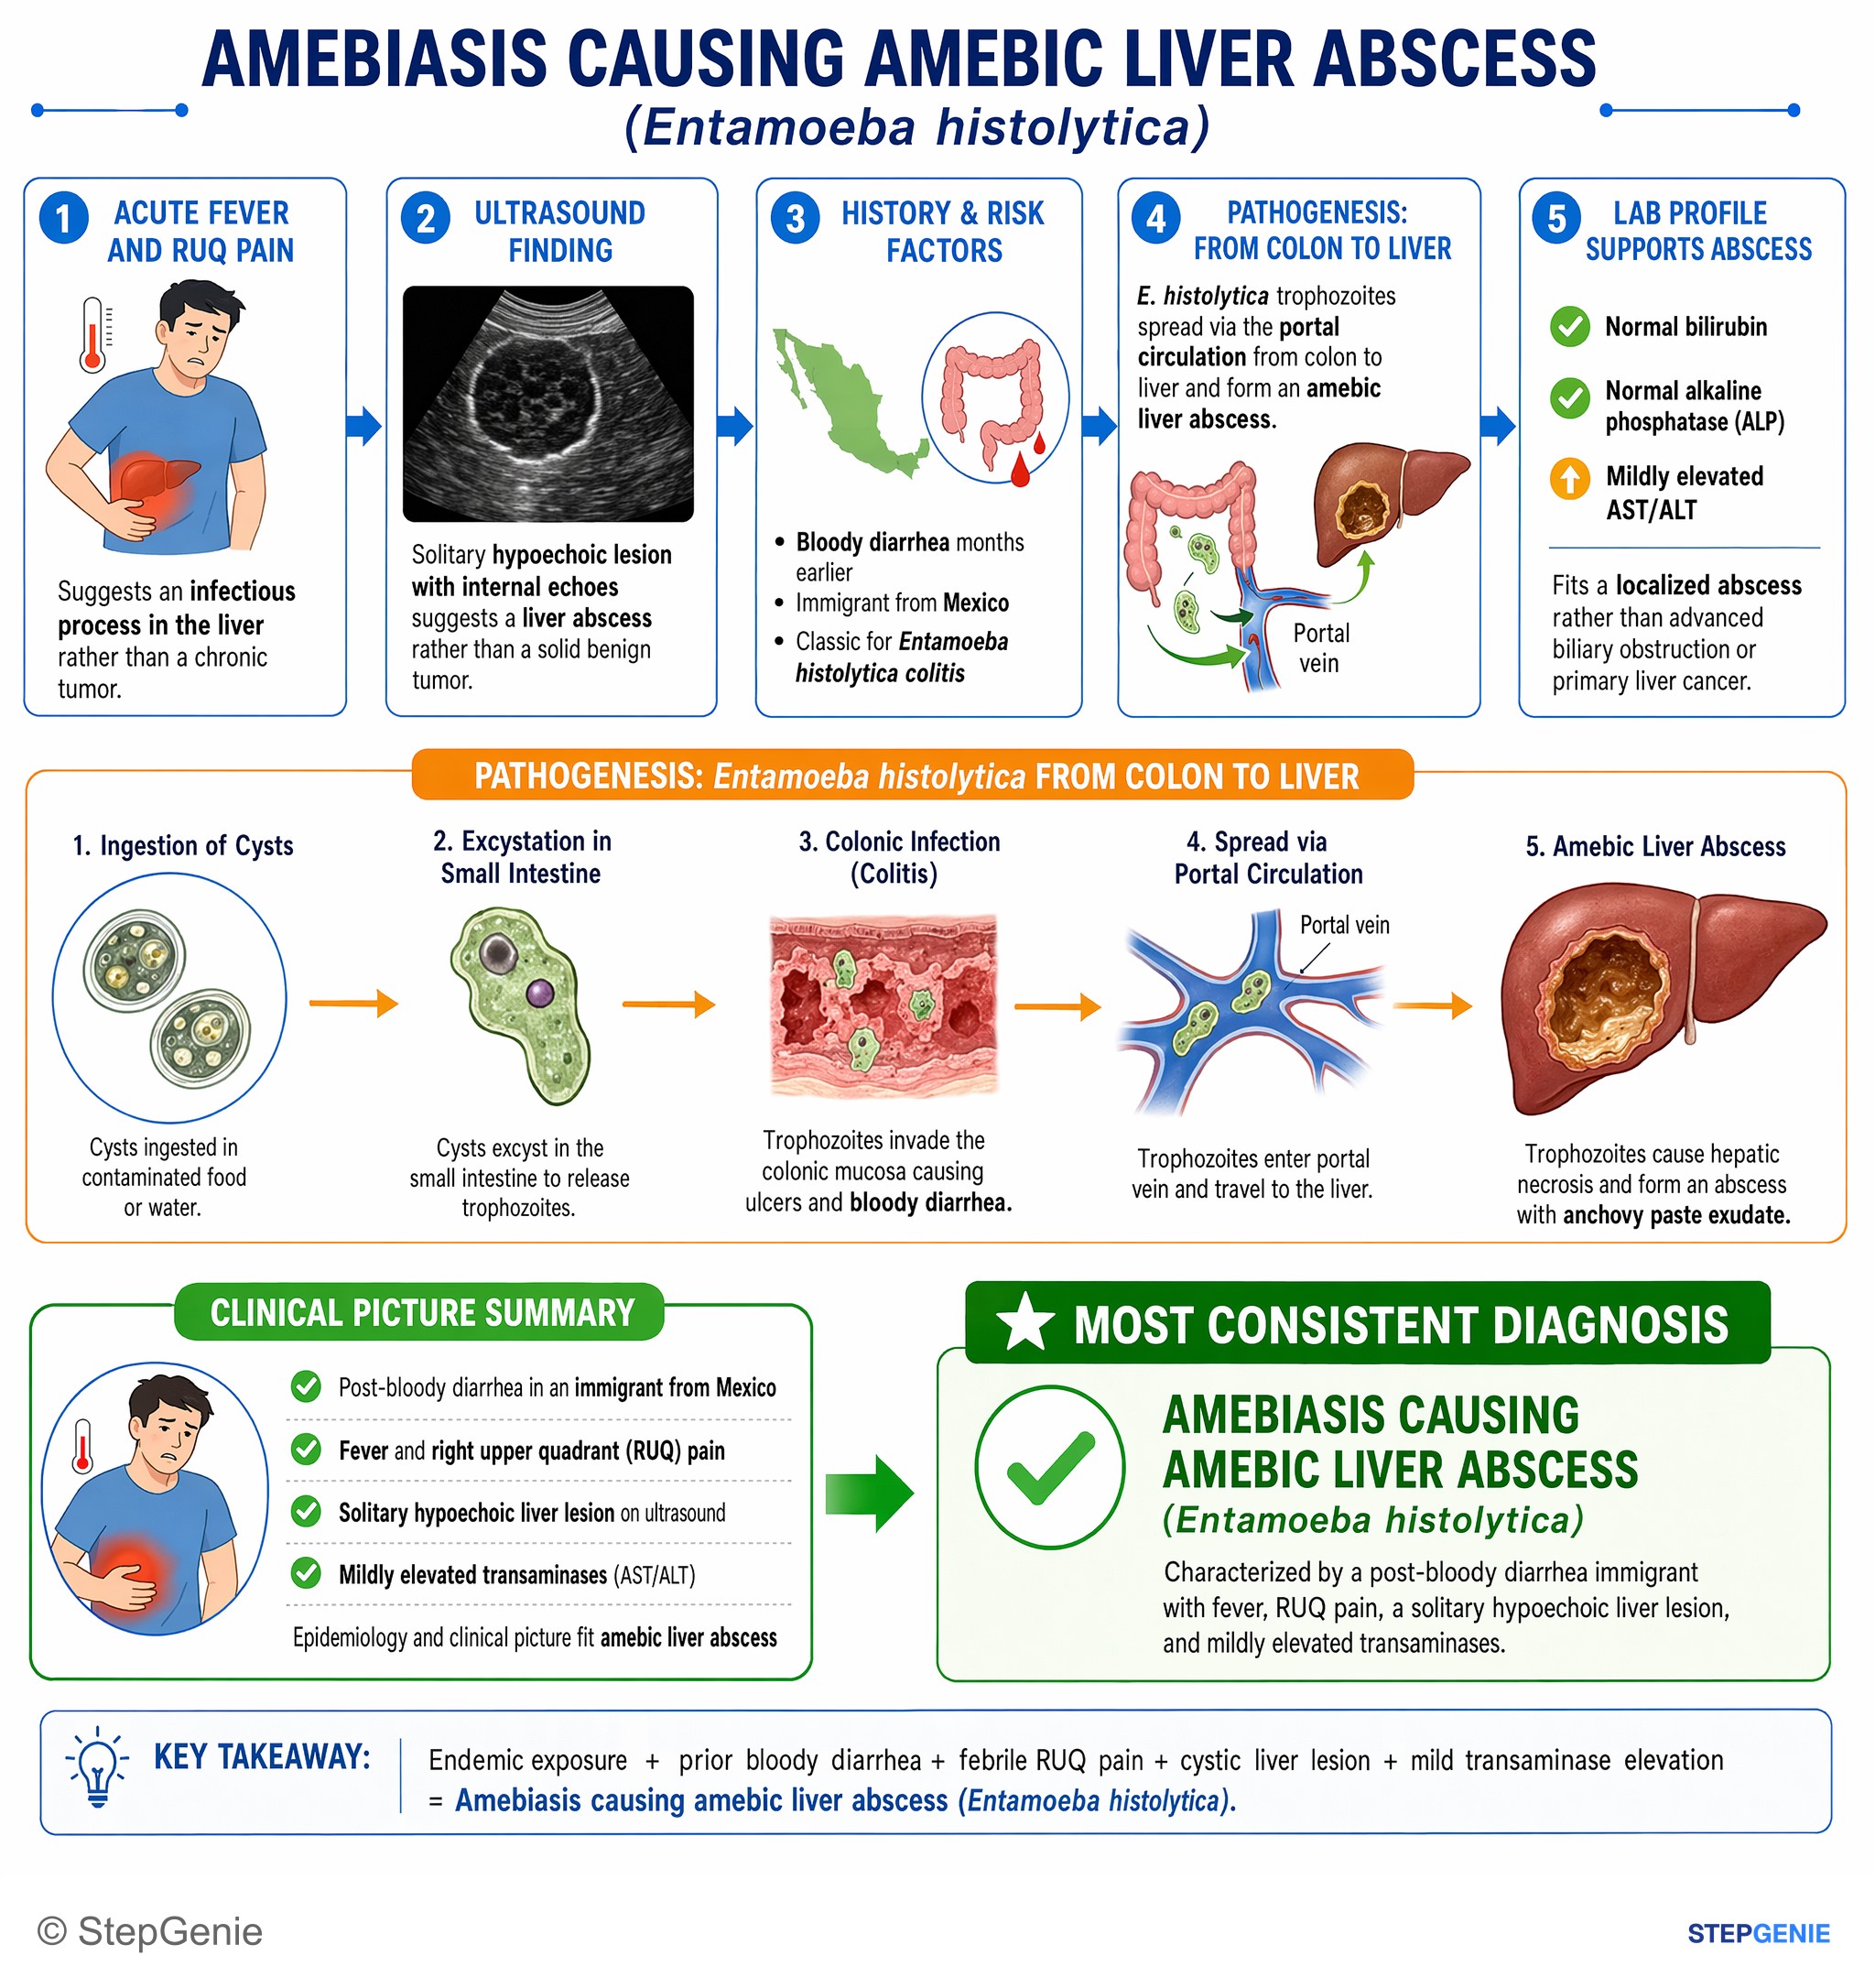
Amebic liver abscess (Entamoeba histolytica): post-bloody diarrhea immigrant with fever, RUQ pain, solitary hypoechoic liver lesion and…
USMLE Step 2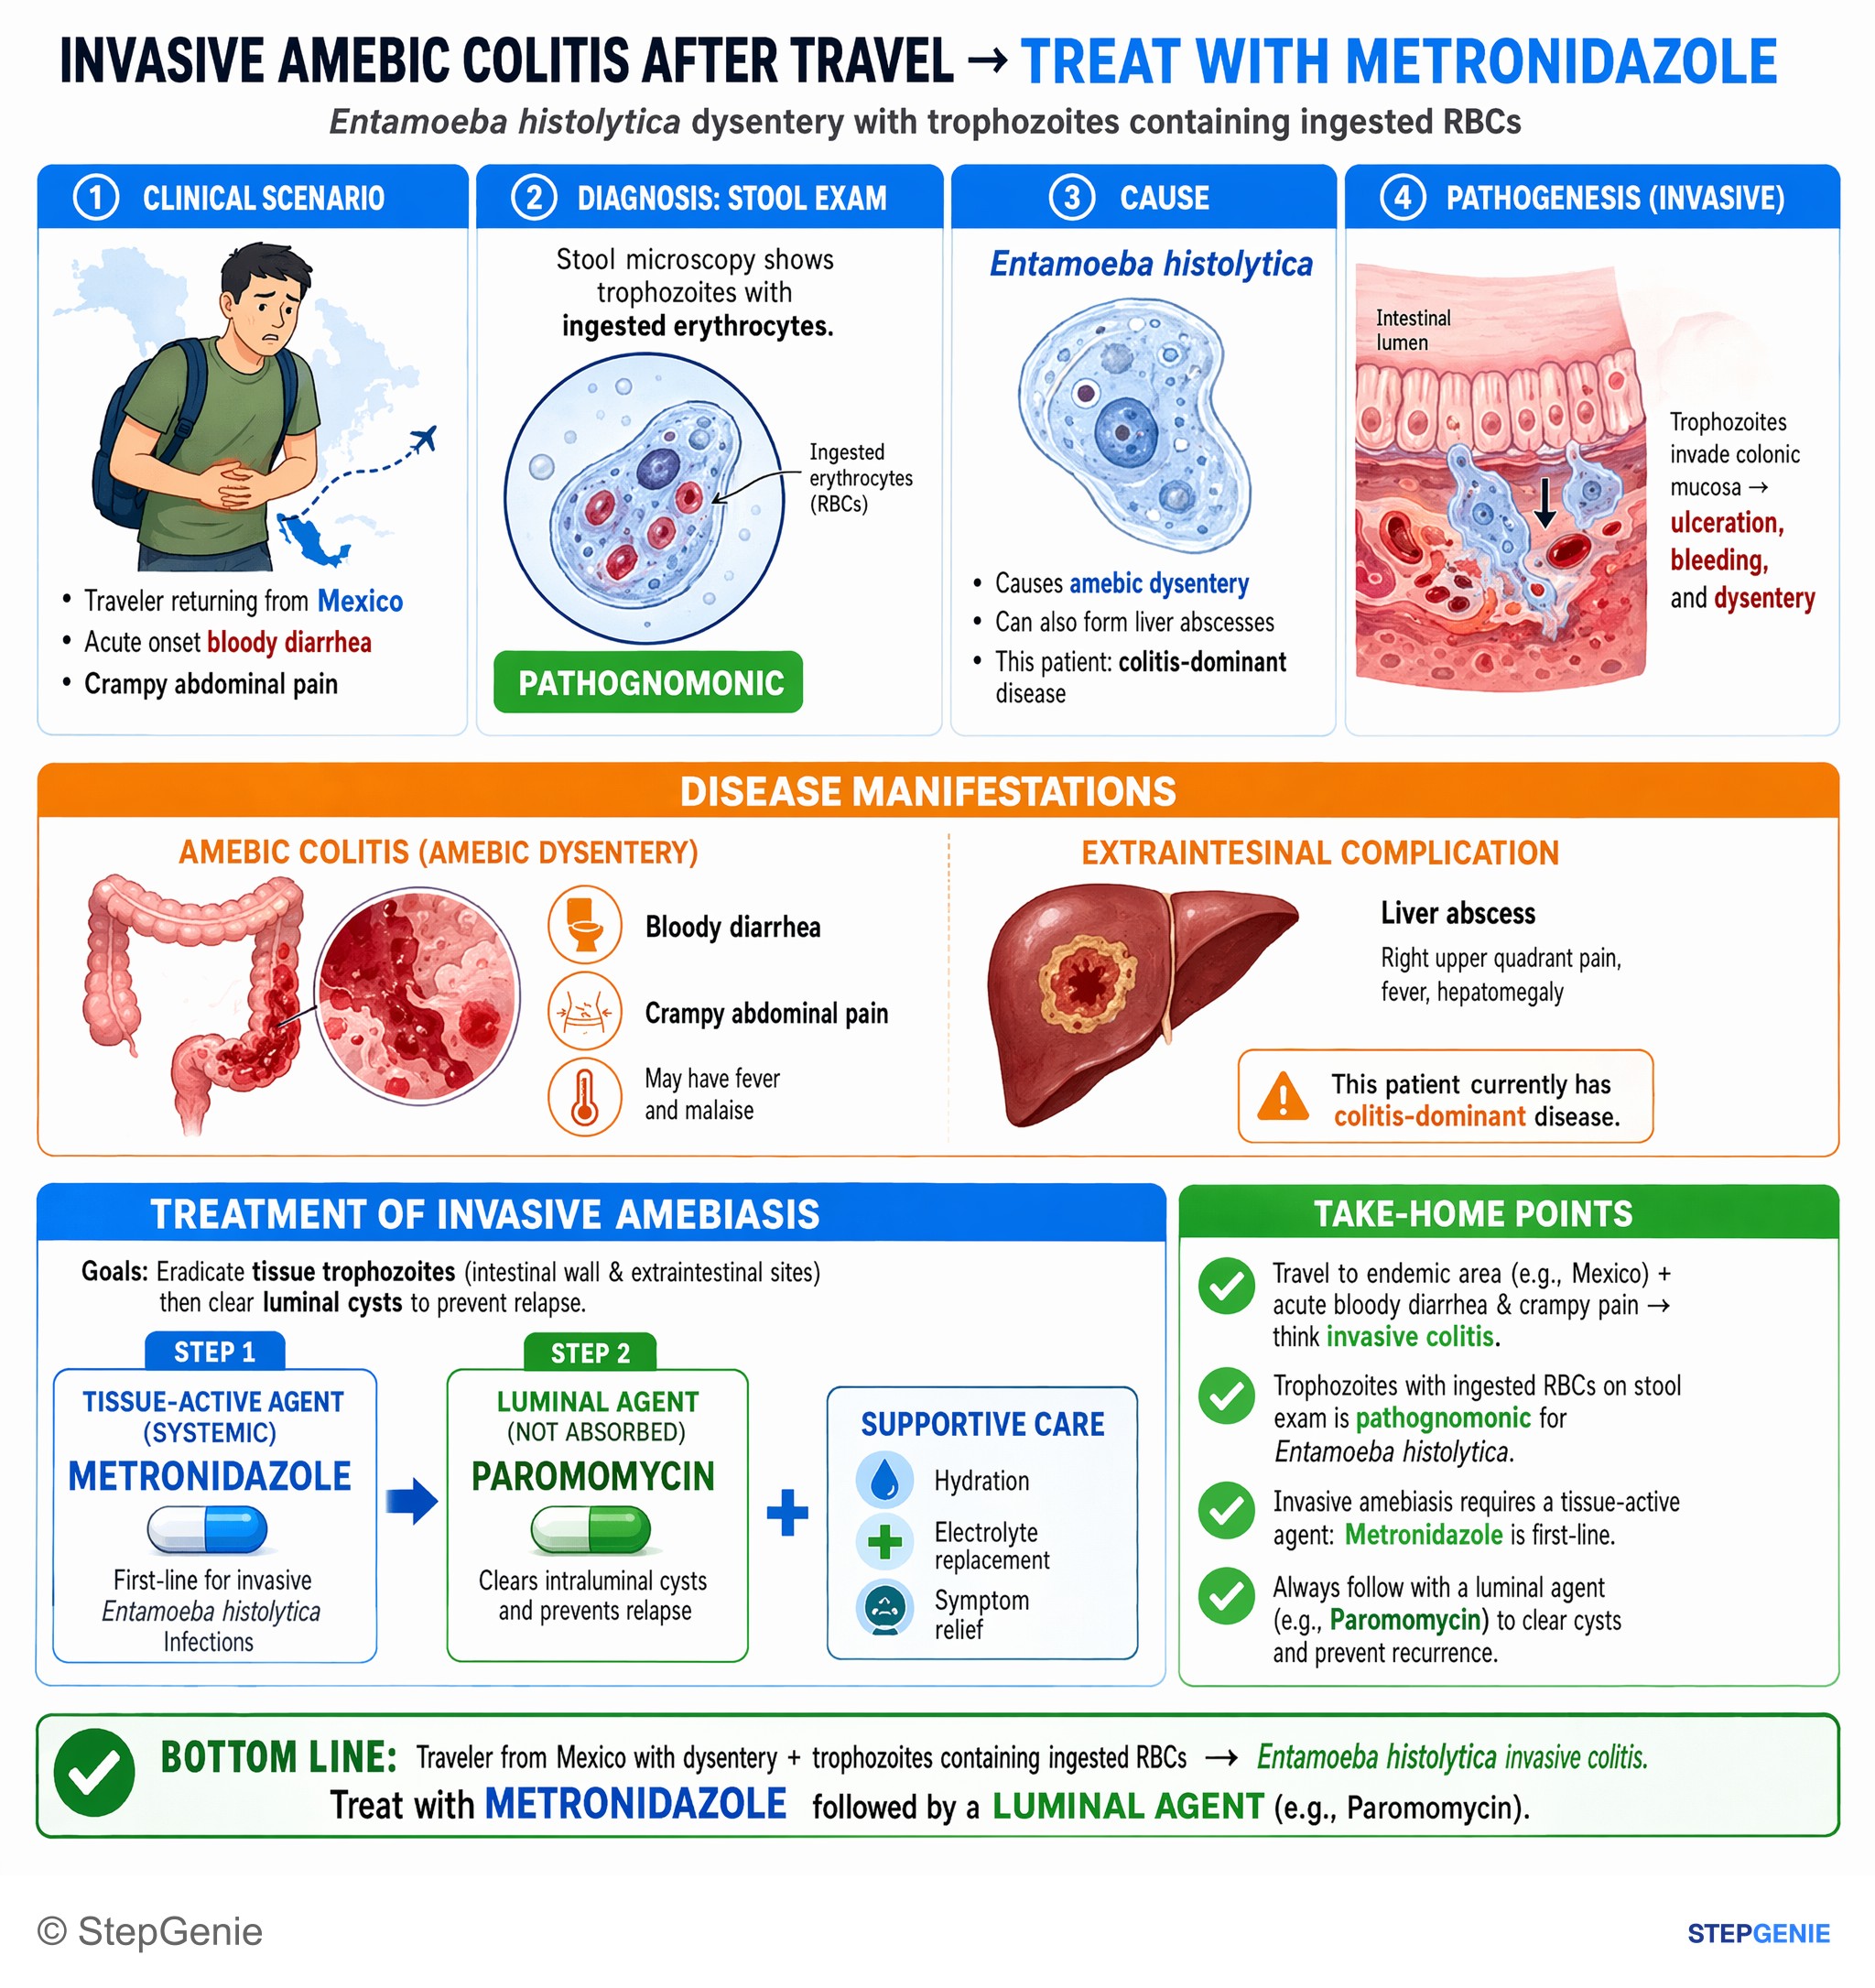
Entamoeba histolytica dysentery after travel with trophozoites containing ingested RBCs → treat with metronidazole followed by a luminal…
USMLE Step 2Frequently Asked Questions
What finding is most diagnostic for Entamoeba histolytica on stool microscopy?
Trophozoites containing ingested red blood cells are the classic diagnostic clue for Entamoeba histolytica. That finding helps distinguish pathogenic E. histolytica from nonpathogenic Entamoeba species. In the right clinical setting, such as bloody diarrhea after travel and cysts seen on ova and parasite testing, RBC ingestion inside trophozoites is the slam-dunk feature pointing to amebic dysentery.
How do you tell Entamoeba histolytica from Giardia lamblia on a question stem?
Entamoeba histolytica causes bloody diarrhea and invasive colitis, whereas Giardia lamblia causes non-bloody, greasy, malabsorptive diarrhea. Giardia is associated with bloating, flatulence, and exposures like streams or daycare, and its trophozoites are pear-shaped with 2 nuclei. Entamoeba histolytica is favored when the stem emphasizes dysentery and trophozoites with ingested red blood cells.
What is the first-line treatment for invasive Entamoeba histolytica infection?
Invasive Entamoeba histolytica infection is treated with metronidazole or tinidazole plus a luminal agent. Metronidazole treats the trophozoites in tissue, but it does not fully clear luminal cysts. A second drug such as paromomycin, iodoquinol, or diloxanide is needed to eradicate cysts, reduce relapse risk, and limit ongoing transmission.
Why does Entamoeba histolytica cause bloody diarrhea?
Entamoeba histolytica causes bloody diarrhea because it invades the colonic mucosa and produces flask-shaped ulcers. This tissue invasion leads to dysentery with abdominal pain and blood in the stool rather than the noninvasive watery diarrhea seen with some other protozoa. The organism is acquired by fecal-oral ingestion of cysts, often through contaminated food or water.
How do you distinguish Entamoeba histolytica from Cryptosporidium parvum on Step-style questions?
Entamoeba histolytica is associated with bloody diarrhea and trophozoites containing ingested red blood cells, while Cryptosporidium parvum causes watery diarrhea and is identified by acid-fast oocysts in stool. Cryptosporidium is especially associated with contaminated water and can be severe or chronic in patients with AIDS, whereas E. histolytica is the classic cause of amebic dysentery and liver abscess.