Cryptosporidium (mainly C. hominis and C. parvum) is a chlorine-resistant protozoan that infects small-bowel epithelial cells and causes profuse, non-bloody watery diarrhea after someone swallows its oocysts, classically in a pool, waterpark, daycare or around calves. Healthy people clear it on their own in 1-3 weeks; with advanced HIV (CD4 count below 100 cells/mm³) it can cause chronic, voluminous diarrhea and spread to the biliary tree. Stool shows small (about 4-5 µm) oocysts that stain red with a modified acid-fast stain, although antigen tests and PCR are more sensitive. Nitazoxanide is FDA-approved for immunocompetent patients aged 1 year and older; in AIDS, the treatment that matters is antiretroviral therapy (ART) to restore immunity.
The vignette
A 34-year-old man with HIV has had profuse watery diarrhea for 3 weeks, with cramps and a 5-kg weight loss. There is no blood in the stool. He stopped antiretroviral therapy a year ago. A month ago he swam several times at a community pool where, he heard, several children later had "stomach flu." He is afebrile and mildly dehydrated. His CD4 count is 45 cells/mm³. A modified acid-fast stain of stool shows small, round oocysts about 5 µm across that stain bright red. Which organism is most likely responsible?
A. Cryptosporidium species B. Cyclospora cayetanensis C. Cystoisospora belli D. Giardia lamblia (G. duodenalis) E. Entamoeba histolytica F. Microsporidia G. Strongyloides stercoralis
Answer: A. Cryptosporidium
Four clues settle it:
- Watery, non-bloody diarrhea that has become chronic in a patient with a CD4 count below 100 cells/mm³, the level at which the NIH opportunistic infection guidelines place the greatest risk of severe or extraintestinal disease.
- A pool with an outbreak. Oocysts can survive more than 7 days in properly chlorinated water and resist chlorine at the levels used in public water supplies, which makes Crypto the classic recreational-water parasite. CDC calls cryptosporidiosis "the leading cause of waterborne disease in the US."
- Acid-fast oocysts. On USMLE this narrows the field to the three intestinal coccidia: Cryptosporidium, Cyclospora and Cystoisospora.
- Size. At 4-5 µm these are Crypto-sized. Cyclospora oocysts are about twice as big, and Cystoisospora oocysts are about five times bigger.
Cryptosporidium at a glance
| Feature | What to know |
|---|---|
| Organism | Apicomplexan (coccidian) protozoan; C. hominis and C. parvum cause most human disease, and cattle are a common zoonotic source |
| Infective form | Thick-walled oocyst, already sporulated and infectious the moment it is passed, so person-to-person spread is easy; thin-walled oocysts cause autoinfection inside the host |
| Dose and incubation | Very few oocysts (fewer than 100) can cause disease; symptoms start 2-10 days (average 7) after infection |
| Site | Small-bowel epithelial cells (obligate intracellular parasite) |
| Spread | Fecal-oral: swallowed pool, lake or drinking water, daycare and household contact, sexual contact, calves and other farm animals |
| Immunocompetent host | Watery diarrhea and cramps, less often nausea, fever or malaise; self-limited, usually 1-3 weeks, and oocyst shedding continues for weeks afterward |
| Advanced HIV | Onset may be more gradual; severe, persistent diarrhea (losses above 5-10 L/day have been reported) and wasting; sclerosing cholangitis and pancreatitis from papillary stenosis with prolonged disease |
| Diagnosis | Modified acid-fast (Kinyoun) stain: red oocysts on a blue-green background; DFA, antigen EIA and PCR are more sensitive; send several samples |
| Treatment | Fluids for everyone; nitazoxanide for immunocompetent patients who need it; ART in HIV |
| Prevention | Soap and water (alcohol hand sanitizer does not work), don't swallow pool water, boil suspect water for 1 minute, no swimming until 2 weeks after diarrhea stops |
A famous example of how far it spreads: Merck notes that a 1993 waterborne outbreak in Milwaukee affected more than 400,000 people.
Why every other answer is wrong
| Organism | Stool finding | Classic clue | Treatment |
|---|---|---|---|
| Cryptosporidium | Acid-fast oocysts, 4-5 µm | Pool, daycare, calves; chronic when CD4 is below 100 | Nitazoxanide (immunocompetent); ART in AIDS |
| Cyclospora | Variably acid-fast oocysts, 7.5-10 µm, autofluorescent | Imported fresh produce (raspberries, basil, lettuce, snow peas) | TMP-SMX |
| Cystoisospora | Acid-fast ellipsoidal oocysts, 25-30 µm, autofluorescent | HIV, tropics; eosinophilia, Charcot-Leyden crystals | TMP-SMX, then suppression in HIV |
| Giardia | Trophozoites or cysts; stool antigen preferred | Streams, daycare; foul-smelling diarrhea, flatulence, no blood | Tinidazole, nitazoxanide or metronidazole |
| E. histolytica | Trophozoites or 4-nucleated cysts; antigen, PCR | Bloody diarrhea, flask-shaped ulcers, liver abscess | Metronidazole or tinidazole, then paromomycin |
| Microsporidia | Tiny spores; chromotrope stain, PCR | Advanced HIV: chronic diarrhea, cholangitis, keratoconjunctivitis | ART; albendazole for Encephalitozoon intestinalis |
| Strongyloides | Rhabditiform larvae | Steroids, HTLV-1, transplant: hyperinfection, gram-negative sepsis | Ivermectin |
B. Cyclospora cayetanensis. The closest look-alike: watery diarrhea, fatigue and acid-fast oocysts. But its oocysts are about twice as large (7.5-10 µm), stain unevenly (some look like unstained "ghosts") and autofluoresce under UV light. They are not sporulated when passed and need 1-2 weeks outside the body to become infectious, so Cyclospora spreads through contaminated food and water rather than person to person; US outbreaks follow imported fresh produce. Illness can last weeks and relapse. Treatment is TMP-SMX for 7-10 days (ciprofloxacin or nitazoxanide if sulfa-intolerant), with longer treatment and suppressive therapy in advanced HIV.
C. Cystoisospora (formerly Isospora) belli. Another acid-fast coccidian that causes severe, intractable watery diarrhea and weight loss in HIV, most often in tropical and subtropical regions. Its oocysts are large (25-30 µm) and ellipsoidal, and unlike most protozoa it can cause peripheral eosinophilia, sometimes with Charcot-Leyden crystals in stool. This stem gives small round oocysts and no eosinophilia. Treatment is TMP-SMX for 7-10 days; people with HIV may need higher doses or a longer course, followed by long-term suppressive therapy (alternatives: pyrimethamine, or ciprofloxacin, which is less effective).
D. Giardia lamblia. A pool or stream does not separate it from Crypto, because Giardia cysts also resist routine chlorination. Giardia trophozoites cling to the duodenum and proximal jejunum without invading, causing foul-smelling watery diarrhea, cramps and flatulence with no blood or white cells; chronic infection brings malabsorption and weight loss. It does not make acid-fast oocysts, and a stool antigen EIA (or PCR) is the preferred test. Treatment: tinidazole (single dose), nitazoxanide (3 days) or metronidazole (5-7 days). See the Giardia question breakdown.
E. Entamoeba histolytica. Amebae invade the colon, so the classic stem is bloody diarrhea with mucus (dysentery), flask-shaped ulcers or a liver abscess, not watery diarrhea. Stool shows trophozoites (classically with ingested red cells, though CDC notes this does not reliably separate it from E. dispar) or 4-nucleated cysts; antigen tests, PCR and serology are used. Treatment: metronidazole or tinidazole, then a luminal agent such as paromomycin to clear cysts. More in the Entamoeba question breakdown.
F. Microsporidia. These obligate intracellular, spore-forming organisms (now considered fungi or close relatives) cause chronic diarrhea, malabsorption, wasting and cholangitis in advanced HIV, so the host fits. But they produce tiny spores, not oocysts, which need special stains such as the chromotrope (modified trichrome) stain, or PCR. Treatment is ART; albendazole works for Encephalitozoon intestinalis but barely for Enterocytozoon bieneusi, the most common cause of microsporidial diarrhea.
G. Strongyloides stercoralis. Its larvae penetrate skin, and autoinfection lets it persist for decades. The USMLE trigger is corticosteroids (or HTLV-1 or transplant immunosuppression) leading to hyperinfection: severe GI symptoms, dyspnea or hemoptysis, and gram-negative bacteremia or meningitis from gut bacteria carried by migrating larvae. Stool shows rhabditiform larvae, not oocysts, and eosinophilia is common but can be suppressed by steroids. Hyperinfection is less common in advanced HIV than you might predict. Treatment: ivermectin. See the Strongyloides visual hack.
Diagnosis and treatment: the follow-up questions
Diagnosis. Merck warns that a routine "stool for ova and parasites" exam is unreliable for Crypto, so labs use a modified acid-fast stain, direct immunofluorescence (DFA), antigen EIA or PCR. CDC's DPDx rates immunofluorescence highest for sensitivity and specificity, followed closely by EIA, and PCR can identify the species. Multiplex GI PCR panels find more cases than microscopy. Oocysts are shed intermittently, so more than one specimen may be needed.
| Patient | Management |
|---|---|
| Immunocompetent | Oral or IV fluids; most recover without drugs. Nitazoxanide for 3 days if needed: 500 mg every 12 hours with food from age 12; oral suspension 100 mg (ages 1-3) or 200 mg (ages 4-11) every 12 hours |
| HIV with a low CD4 count | Start ART to restore the CD4 count above 100 cells/mm³ (an A-II recommendation in the NIH guidelines), plus aggressive oral or IV rehydration, electrolyte replacement and antimotility agents. Nitazoxanide (at least 14 days) or paromomycin may be added, but only alongside ART |
| Prevention in HIV | No chemoprophylaxis; avoid exposures and boil water during outbreaks |
Nitazoxanide (active metabolite tizoxanide) interferes with pyruvate:ferredoxin oxidoreductase (PFOR)-dependent electron transfer. Its label covers diarrhea caused by Giardia or C. parvum, but states it has not been shown effective for Crypto diarrhea in HIV-infected or immunodeficient patients. In immunocompetent patients, CDC cites clinical cure rates of 72-88%. TMP-SMX is the answer for Cyclospora and Cystoisospora, not Crypto.
How USMLE tests it
- Pool + outbreak + watery diarrhea = Crypto; raspberries or basil = Cyclospora; eosinophilia + big oval oocysts = Cystoisospora.
- Size ladder, "5-10-25": Crypto (4-5 µm) < Cyclospora (7.5-10 µm) < Cystoisospora (25-30 µm).
- Chlorine resistance is shared with Giardia. Let the stool test decide: acid-fast oocysts vs Giardia antigen, cysts or trophozoites.
- Acid-fast oocysts are not acid-fast bacilli. Round oocysts in stool mean coccidia; acid-fast rods mean mycobacteria such as M. avium complex.
- Watery vs bloody: Crypto, Cyclospora, Cystoisospora, Giardia and microsporidia cause watery diarrhea; E. histolytica causes bloody diarrhea.
- Best treatment in AIDS = ART, not nitazoxanide alone. Review the thresholds in CD4 counts and opportunistic infections and the drug classes in HIV antiretroviral drugs by life cycle.
- Person-to-person spread: Crypto oocysts are infectious when passed (daycare, households); Cyclospora oocysts are not, so a daycare outbreak points away from Cyclospora.
Key takeaways
- Cryptosporidium = chlorine-resistant, acid-fast oocysts of about 4-5 µm, non-bloody watery diarrhea; CDC calls it the leading cause of waterborne disease in the US.
- Oocysts are infectious as soon as they are passed, and fewer than 100 can cause disease: pools, daycare, households and calves.
- Immunocompetent: self-limited in 1-3 weeks. CD4 below 100: chronic, voluminous diarrhea, sclerosing cholangitis and pancreatitis.
- Diagnosis: modified acid-fast stain; DFA, antigen EIA and PCR are more sensitive than routine ova-and-parasite exams.
- Treatment: fluids; nitazoxanide (FDA-approved from age 1) for immunocompetent patients; ART is the key therapy in AIDS.
- Look-alikes: Cyclospora (produce, 7.5-10 µm, TMP-SMX), Cystoisospora (25-30 µm, eosinophilia, TMP-SMX), microsporidia (spores, chromotrope stain), Giardia (antigen test, no acid-fast oocysts).
- Patients should not swim until 2 weeks after diarrhea stops, and alcohol gels do not kill oocysts.
Sources
- Cryptosporidiosis — Merck Manual Professional Edition (2026)
- Cryptosporidiosis: Adult and Adolescent Opportunistic Infection Guidelines — NIH ClinicalInfo.HIV.gov (2023, reviewed 2026)
- Clinical Care of Crypto — CDC (2025)
- About Crypto Infections — CDC (2025)
- DPDx: Cryptosporidiosis — CDC (2024)
- Nitazoxanide Tablets Prescribing Information — DailyMed (2025)
- DPDx: Cyclosporiasis — CDC
- Cyclosporiasis — Merck Manual Professional Edition (2024)
- DPDx: Cystoisosporiasis — CDC (2024)
- Microsporidiosis — Merck Manual Professional Edition (2024)
- Giardiasis — Merck Manual Professional Edition (2026)
- Preventing Swimming-related Illnesses — CDC Healthy Swimming (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
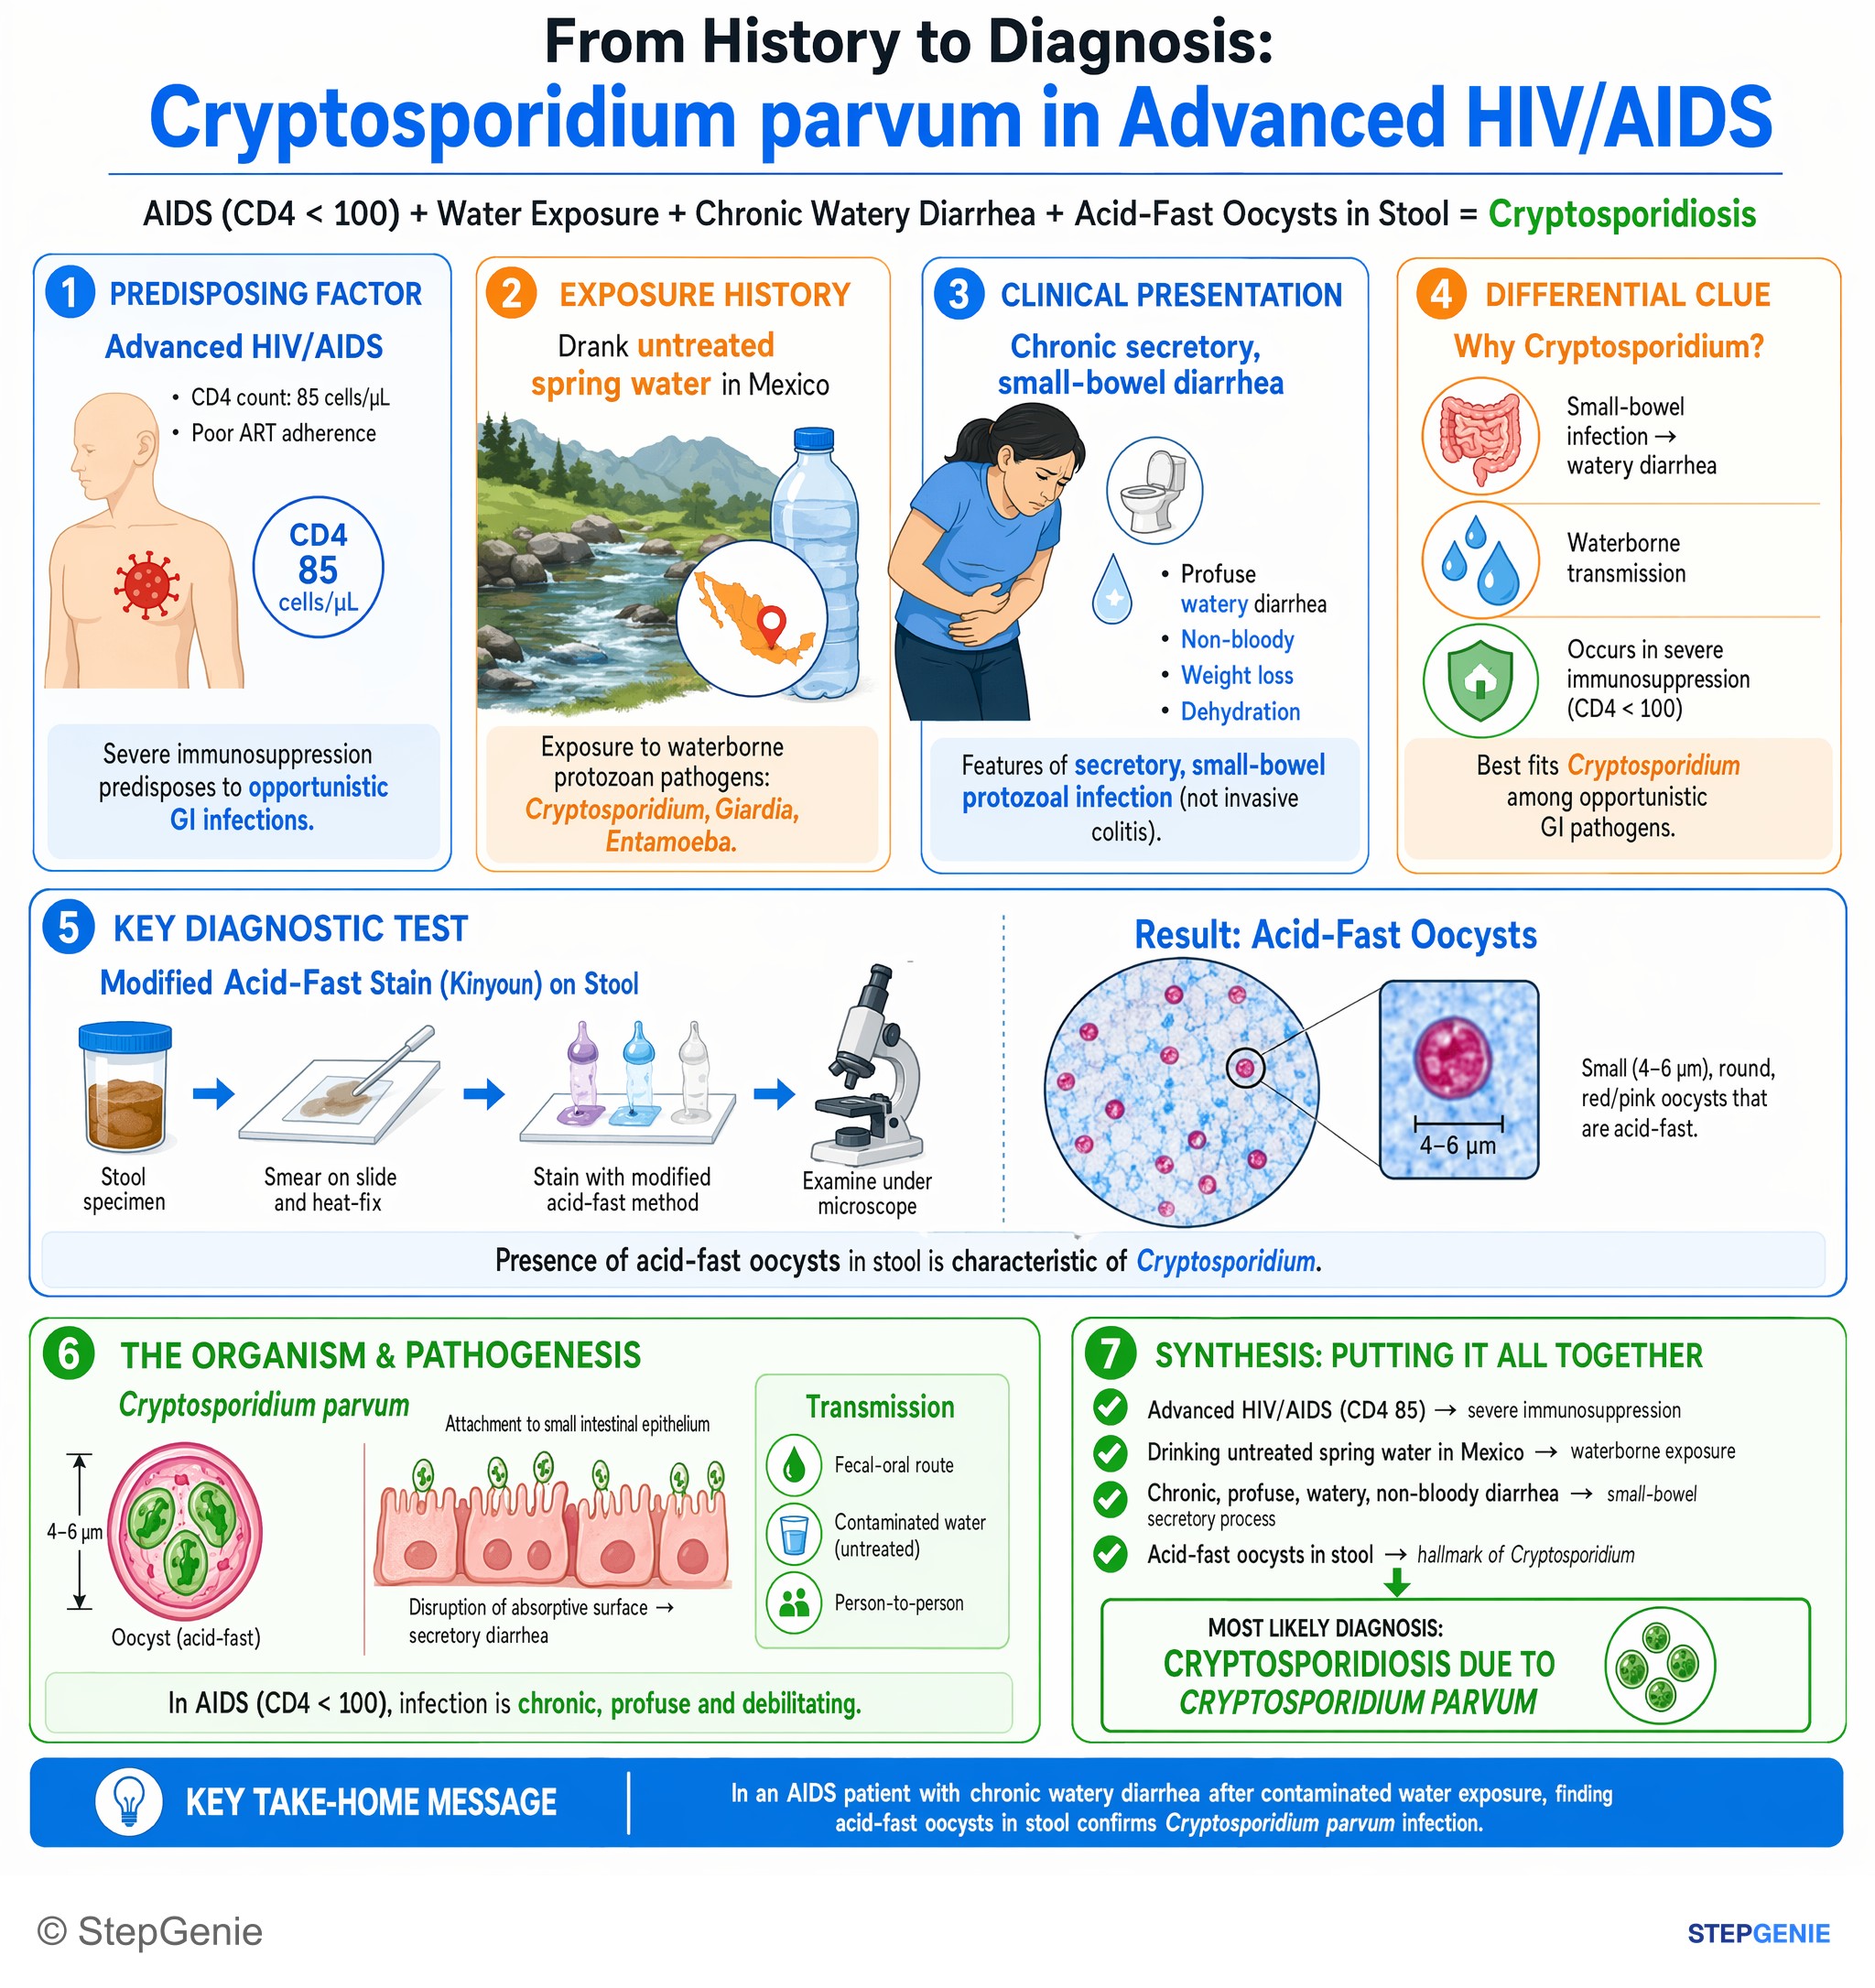
Cryptosporidiosis in AIDS: chronic profuse watery diarrhea after contaminated water exposure; acid-fast oocysts in stool confirm…
USMLE Step 1Frequently Asked Questions
What are the classic USMLE clues for Cryptosporidium?
Look for profuse, non-bloody watery diarrhea after swimming in a pool or waterpark, daycare exposure or contact with calves, plus small oocysts (about 4-5 µm) that stain red on a modified acid-fast stain. In a healthy person the illness is self-limited, usually lasting 1-3 weeks. In a patient with HIV and a CD4 count below 100 cells/mm³, the same infection is much more likely to become chronic, voluminous diarrhea with wasting, and it can involve the bile ducts.
Why is Cryptosporidium linked to swimming pools?
Its oocysts can survive for more than 7 days in properly chlorinated water, and they are infectious as soon as they are passed in stool. Very few oocysts, fewer than 100, can cause infection, so one person with diarrhea can contaminate a pool for many swimmers. CDC calls cryptosporidiosis the leading cause of waterborne disease in the US and advises no swimming until 2 weeks after diarrhea stops.
How do you tell Cryptosporidium, Cyclospora and Cystoisospora apart?
All three make acid-fast oocysts and cause watery diarrhea, so use size and exposure. Cryptosporidium oocysts are about 4-5 µm and come from pools, daycare and animals. Cyclospora oocysts are 7.5-10 µm, stain variably, autofluoresce and come from imported fresh produce such as raspberries and basil. Cystoisospora oocysts are large (25-30 µm) and oval, and the infection can cause eosinophilia. Cyclospora and Cystoisospora are treated with TMP-SMX; Cryptosporidium is not.
What is the treatment for Cryptosporidium in a patient with AIDS?
The key treatment is antiretroviral therapy, which restores immunity; NIH guidelines aim to bring the CD4 count above 100 cells/mm³. Patients also need aggressive oral or IV rehydration, electrolyte replacement and often antimotility drugs. Nitazoxanide or paromomycin can be tried alongside ART but never instead of it, because no drug aimed at Cryptosporidium has been consistently effective without immune restoration. No drug is recommended to prevent it.
Is nitazoxanide effective for cryptosporidiosis?
In immunocompetent patients, yes. Nitazoxanide is FDA-approved for diarrhea caused by Cryptosporidium parvum or Giardia in patients aged 1 year and older, given every 12 hours with food for 3 days (500 mg per dose from age 12). CDC cites clinical cure rates of 72-88%. Its label states it has not been shown effective in HIV-infected or immunodeficient patients, so in AIDS the priority is antiretroviral therapy.
How is Cryptosporidium diagnosed?
A routine ova-and-parasite stool exam is unreliable, so laboratories use a modified acid-fast stain, which shows small red oocysts on a blue-green background, or more sensitive tests: direct immunofluorescence, a stool antigen enzyme immunoassay or PCR, including multiplex GI panels. Because oocysts are shed intermittently, more than one stool sample may be needed. In patients with HIV, intestinal biopsy can also confirm the diagnosis.