Pneumocystis jirovecii is one of those Step 1 organisms that shows up everywhere: immunodeficiency questions, chest imaging vignettes, “foamy” sputum descriptions, and prophylaxis pharmacology. The key is recognizing that it behaves like a fungus but doesn’t read like your typical yeast or mold—so the exam writers love it.
Big Picture Definition (What is Pneumocystis jirovecii?)
Pneumocystis jirovecii is an opportunistic fungal pathogen that causes Pneumocystis pneumonia (PCP)—classically in patients with impaired cell-mediated immunity, especially HIV/AIDS with low CD4 counts.
High-yield identity points
- Fungus (not a protozoan), but it has quirky features:
- Does not grow on standard fungal media
- Lacks ergosterol in its cell membrane → influences antifungal choice
- Causes diffuse interstitial pneumonia with severe hypoxemia
- Classic in AIDS but also in other immunosuppressed states (transplant, steroids, chemo)
First Aid cross-reference (typical placement)
- First Aid Step 1 → Microbiology → Fungi → Opportunistic mycoses: Pneumocystis jirovecii
- Also shows up under Immunology (AIDS opportunistic infections) and Pharm (TMP-SMX, pentamidine)
Epidemiology & Risk Factors (Who gets PCP?)
Highest-yield risk factor
- HIV/AIDS with CD4 < 200 cells/mm³
Other classic risk groups
- Solid organ or bone marrow transplant
- Chronic glucocorticoid therapy
- Hematologic malignancy
- TNF-α inhibitors and other potent immunosuppressants
Transmission pearl
- Generally thought to spread via inhalation; many people are exposed early in life.
- Disease is usually due to reactivation or new infection when immunity drops.
Pathophysiology (What it does in the lungs)
PCP primarily targets the alveoli, producing a diffuse, interstitial pattern rather than lobar consolidation.
Core mechanism
- Organism fills alveoli with a proteinaceous, foamy (“cotton candy”) exudate
- Causes V/Q mismatch and diffusion impairment → hypoxemia
- Inflammation is often interstitial, explaining the imaging and exam findings
Why hypoxemia is so dramatic
A hallmark is desaturation that is out of proportion to auscultatory findings—patients can be extremely hypoxic with relatively “quiet” lungs.
Step-style concept: impaired oxygenation due to diffusion limitation → increased A–a gradient.
Clinical Presentation (How it shows up on USMLE)
Classic symptom cluster (high yield)
- Fever
- Nonproductive cough
- Progressive dyspnea (subacute onset over days to weeks)
- Pleuritic chest pain can occur but is less classic than in bacterial pneumonias
Physical exam
- May be deceptively mild:
- Tachypnea, tachycardia
- Diffuse crackles can be present, but exam may be relatively normal compared to hypoxemia
Imaging patterns you should recognize
| Modality | Typical finding | Step clue |
|---|---|---|
| CXR | Diffuse bilateral interstitial infiltrates | “Ground-glass”/reticular appearance |
| CT | Ground-glass opacities | Often more sensitive early |
Complications to remember
- Pneumothorax (especially in AIDS) can be a testable twist
- Respiratory failure if untreated
Diagnosis (How you prove it)
Step 1 “classic” diagnostic clues
- Silver stain of cysts (e.g., Gomori methenamine silver, GMS)
- Bronchoalveolar lavage (BAL) often used in practice
Commonly tested lab/imaging adjuncts
- Elevated LDH: not specific, but a classic association in PCP vignettes
- β-D-glucan may be elevated (fungal cell wall component) — supportive, not definitive
What you’ll see under the microscope (high yield)
- Cup-shaped cysts on silver stain is a frequent description
Treatment (Acute management)
First-line therapy
- TMP-SMX (trimethoprim-sulfamethoxazole)
When to add steroids (major NBME/Step concept)
Add adjunctive corticosteroids in moderate-to-severe PCP (commonly tested criterion):
- Significant hypoxemia (e.g., PaO₂ < 70 mmHg on room air or elevated A–a gradient)
Why steroids? They blunt inflammatory worsening that can occur after killing organisms in the alveoli.
Alternatives (if sulfa allergy or intolerance)
| Drug | When it’s used | Classic Step association |
|---|---|---|
| Pentamidine | Alternative therapy/prophylaxis | Can cause nephrotoxicity, hypotension, pancreatitis, hypoglycemia |
| Atovaquone | Mild-moderate disease alternative | Also used for some protozoal infections |
| Clindamycin + primaquine | Alternative regimen | Think “backup regimen” in tough questions |
First Aid cross-reference
- First Aid Step 1 → Pharmacology (antimicrobials): TMP-SMX adverse effects and pentamidine toxicities
Prophylaxis (Preventing PCP)
Who gets prophylaxis?
Most testable threshold:
- CD4 < 200 cells/mm³ (HIV)
Also consider prophylaxis in certain transplant or chronic immunosuppression regimens.
What do you give?
- TMP-SMX is first-line prophylaxis.
When can you stop prophylaxis (HIV)
Common concept:
- After immune reconstitution on ART with CD4 > 200 for a sustained period (guidelines vary, but Step usually tests the CD4 threshold concept rather than timing nuances).
High-Yield “Buzz Phrases” & Associations (Memorize these)
Buzz phrases
- “AIDS patient with CD4 <200”
- “Nonproductive cough + fever + progressive dyspnea”
- “Diffuse bilateral interstitial infiltrates / ground-glass opacities”
- “Elevated LDH”
- “Silver stain shows cysts (cup-shaped)”
- “Treat with TMP-SMX; consider steroids if hypoxemic”
- “Prophylaxis with TMP-SMX”
Classic differentials they’ll try to bait you with
| Condition | Key differentiator vs PCP |
|---|---|
| Typical bacterial pneumonia | More productive cough, lobar consolidation, higher WBC, abrupt onset |
| TB | Apical disease, night sweats, weight loss, cavitation |
| Histoplasma | Ohio/Mississippi River valleys; intracellular yeast in macrophages; mediastinal LAD |
| CMV pneumonitis | Transplant/AIDS; systemic symptoms; “owl eye” inclusions (path) |
| CHF/pulmonary edema | Kerley B lines, cardiomegaly, response to diuretics |
Step 1 Micro/Pharm Integration: TMP-SMX & Pentamidine Pearls
TMP-SMX (very testable adverse effects)
- Hypersensitivity reactions
- Photosensitivity
- Hyperkalemia
- Nephrotoxicity (interstitial nephritis)
- Hemolysis in G6PD deficiency (more classically with sulfas; still fair game)
Pentamidine toxicities (Step-favorite)
- Nephrotoxicity
- Hypoglycemia (and sometimes hyperglycemia later due to pancreatic toxicity)
- Hypotension
- Pancreatitis
Rapid Review (What you should be able to say in 15 seconds)
- Pneumocystis jirovecii is an opportunistic fungus causing PCP in AIDS (CD4 < 200) and other immunosuppressed patients.
- Presents with fever, nonproductive cough, progressive dyspnea, diffuse bilateral interstitial/ground-glass infiltrates, and hypoxemia (often with elevated LDH).
- Diagnose with silver stain (GMS) on induced sputum/BAL showing cysts.
- Treat with TMP-SMX; add steroids if significant hypoxemia.
- Prophylaxis: TMP-SMX when CD4 < 200.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
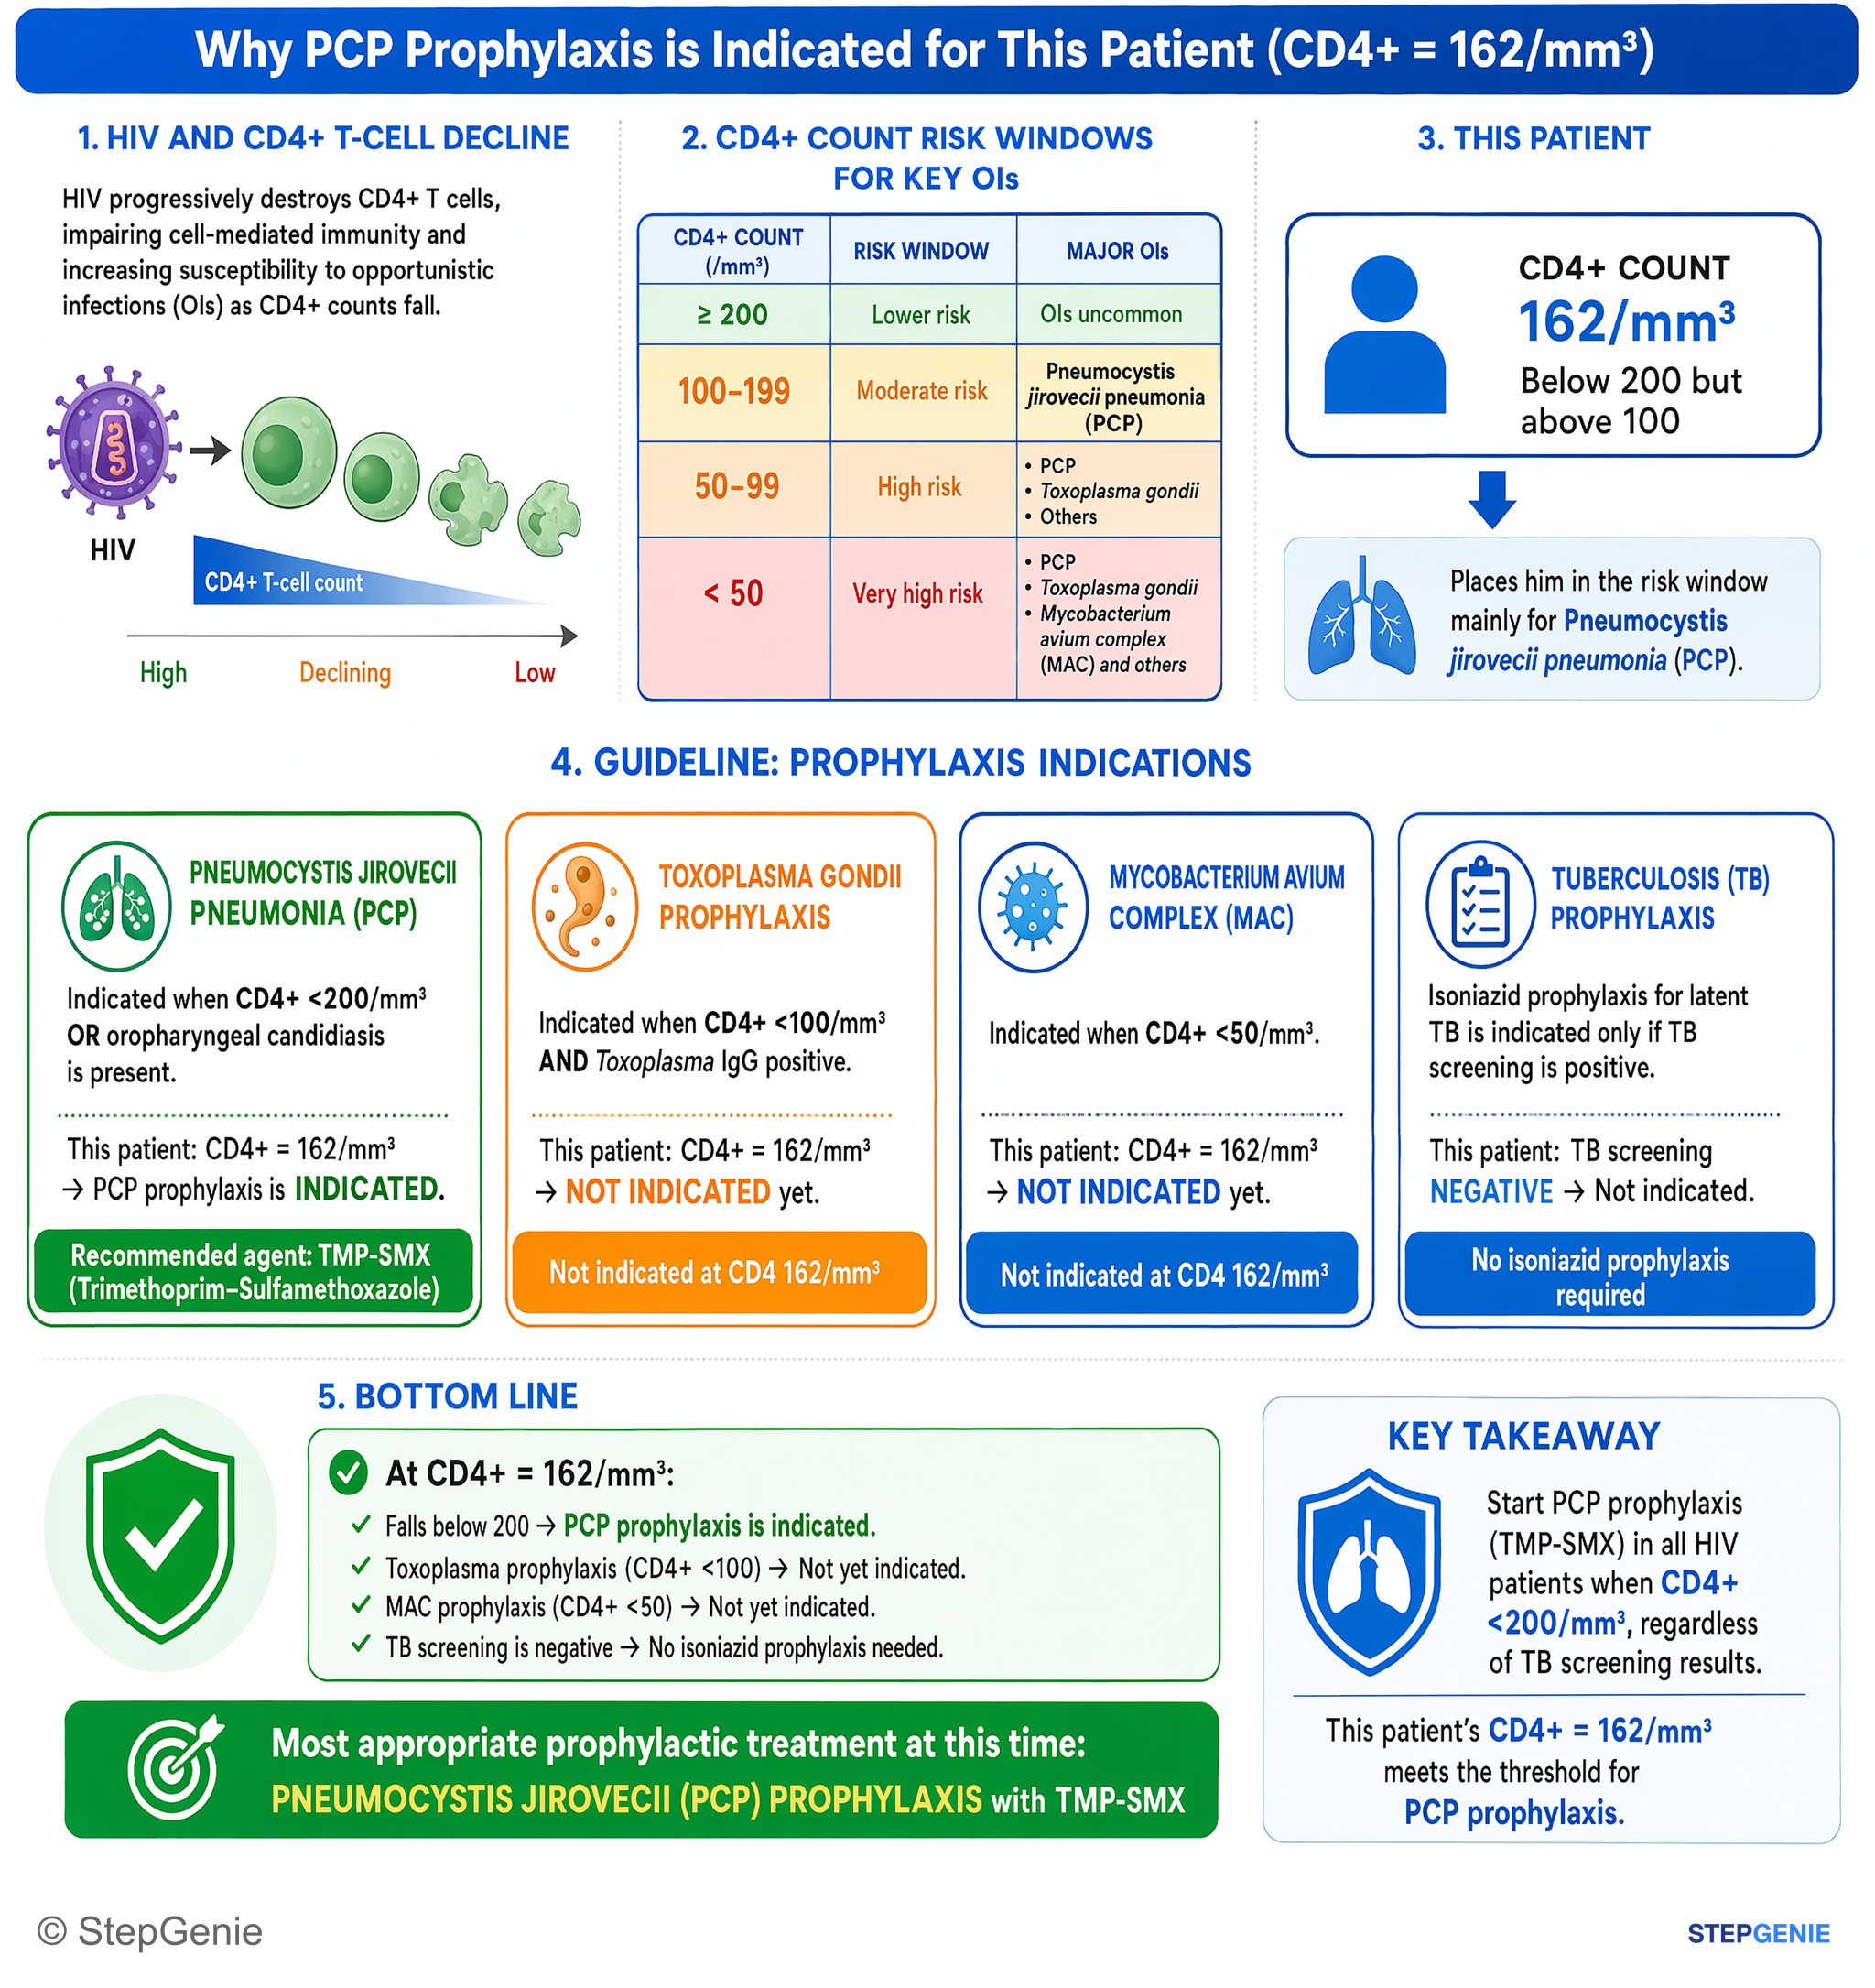
Pneumocystis jirovecii pneumonia prophylaxis (TMP-SMX) is indicated in HIV when CD4+ <200/mm³, regardless of TB screening results.
USMLE Step 2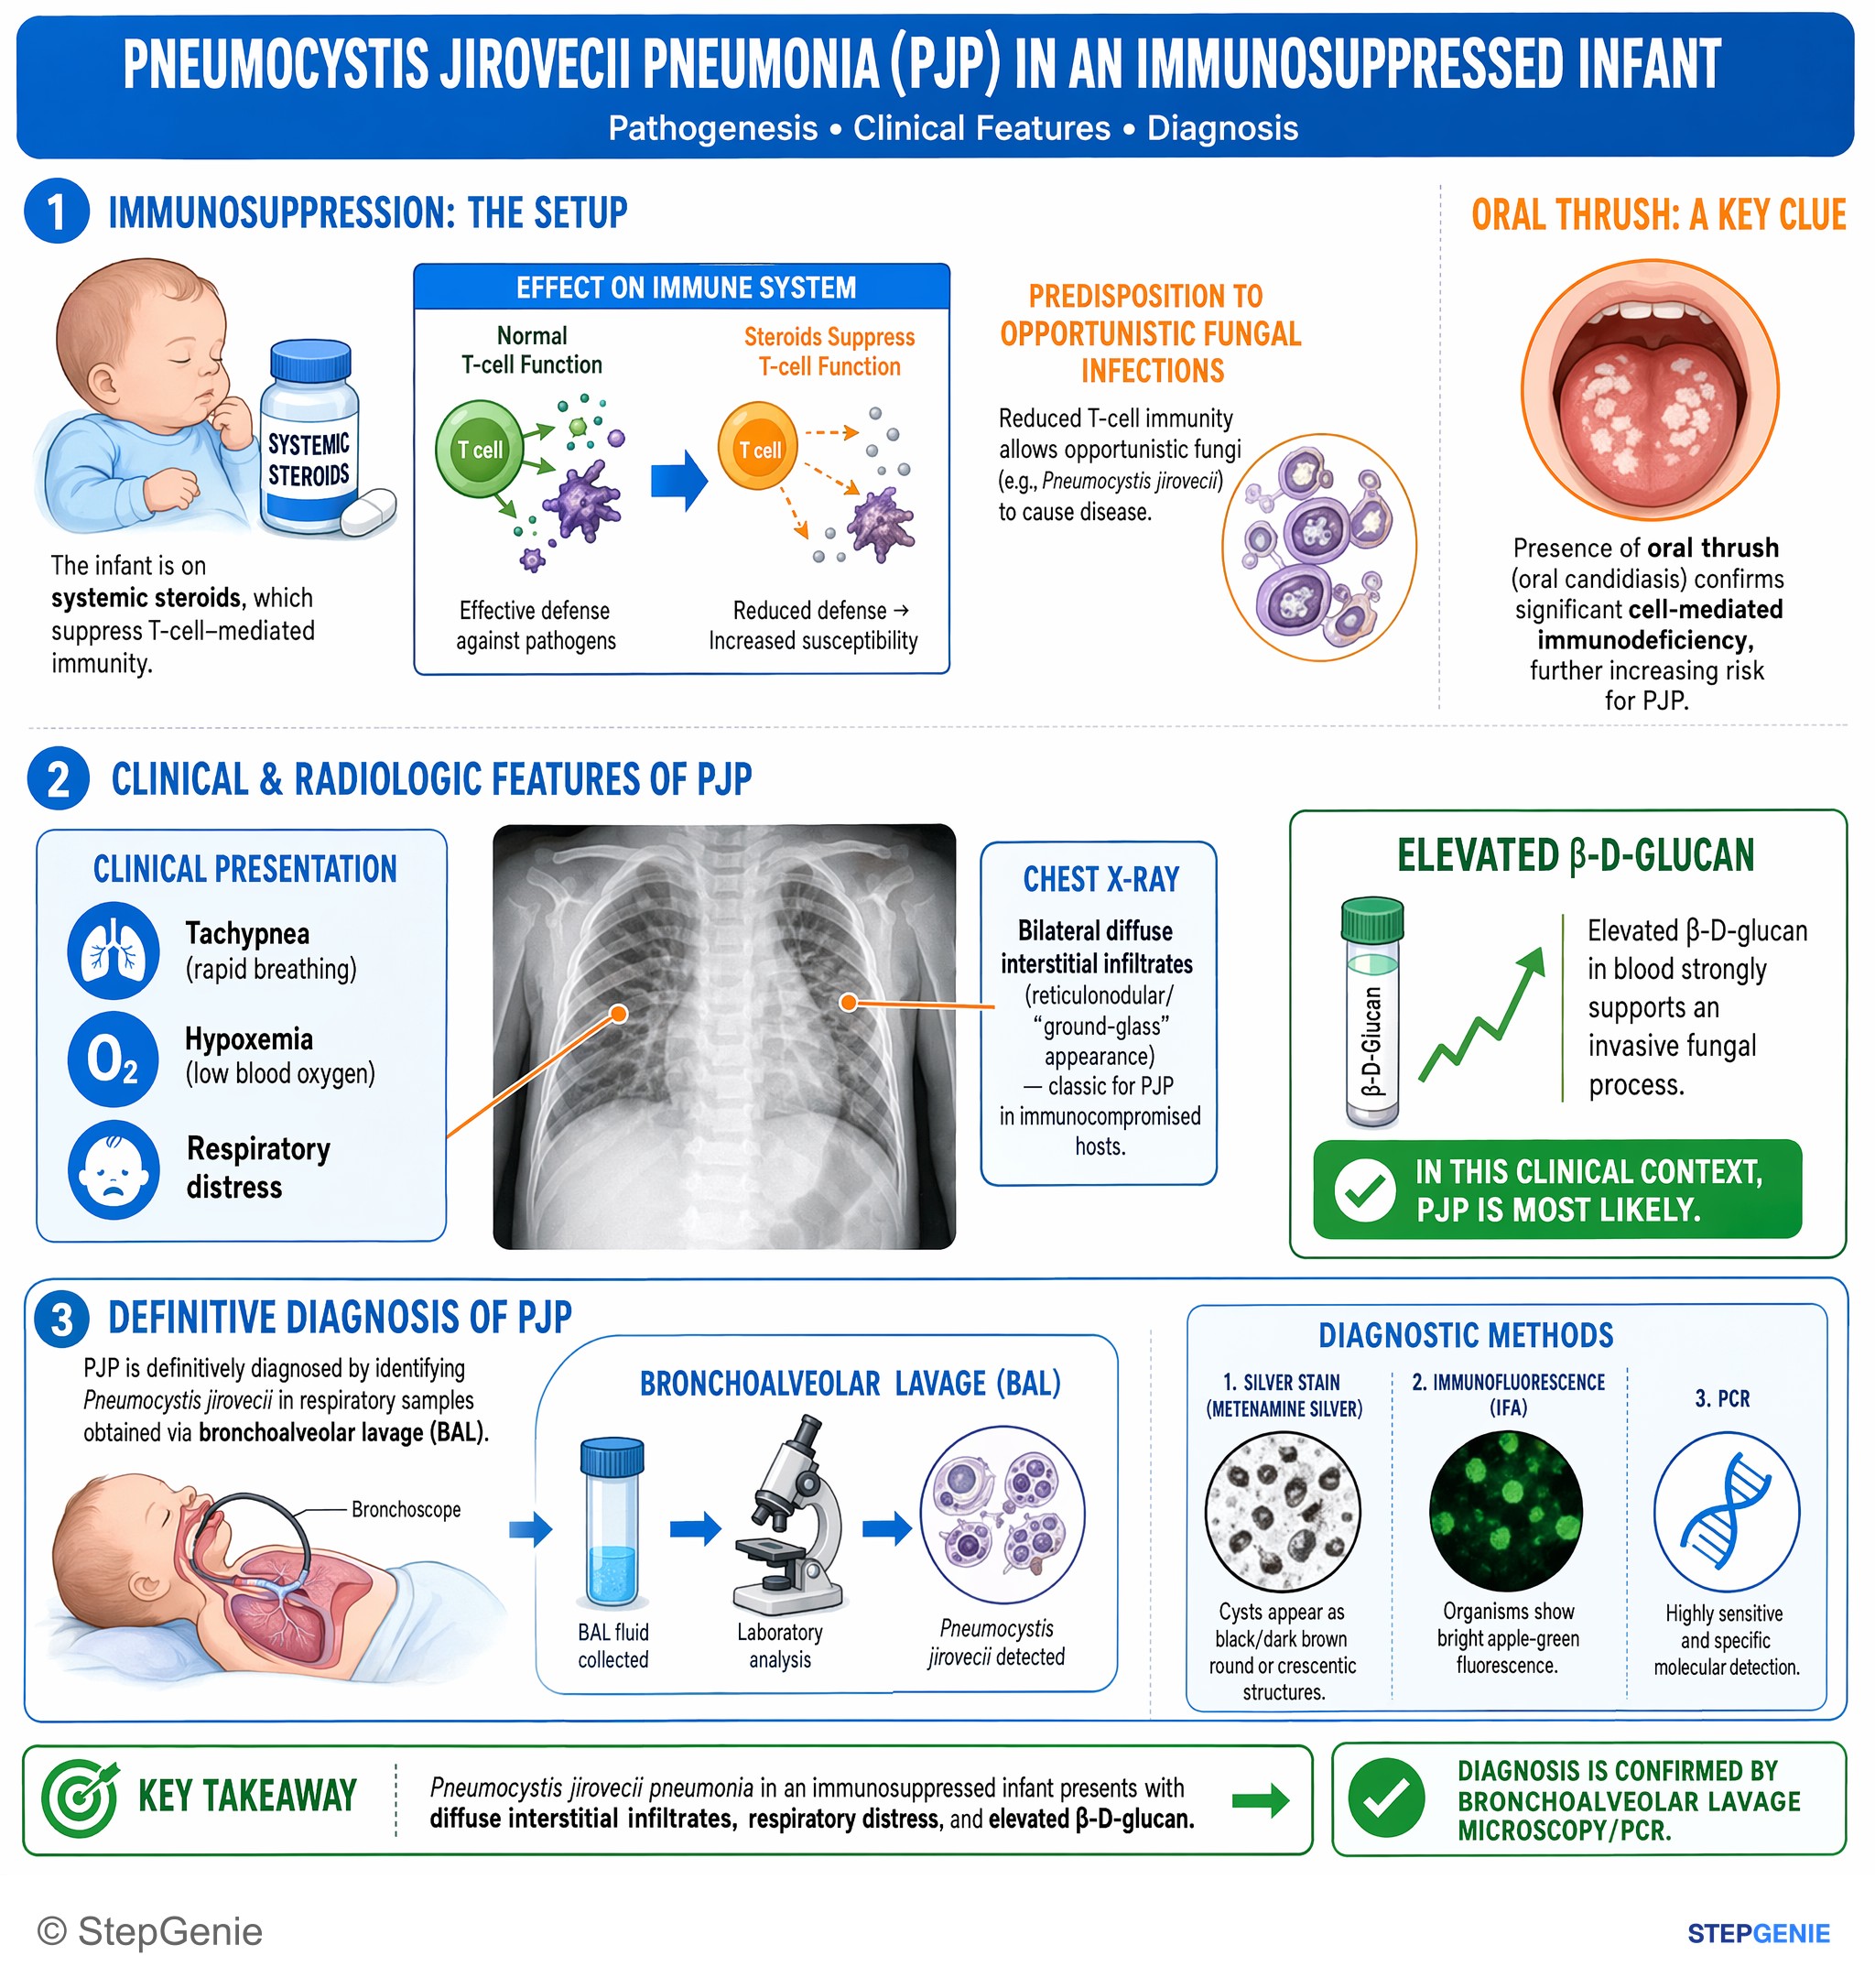
Pneumocystis jirovecii pneumonia in an immunosuppressed infant presents with diffuse interstitial infiltrates and elevated β-D-glucan…
USMLE Step 2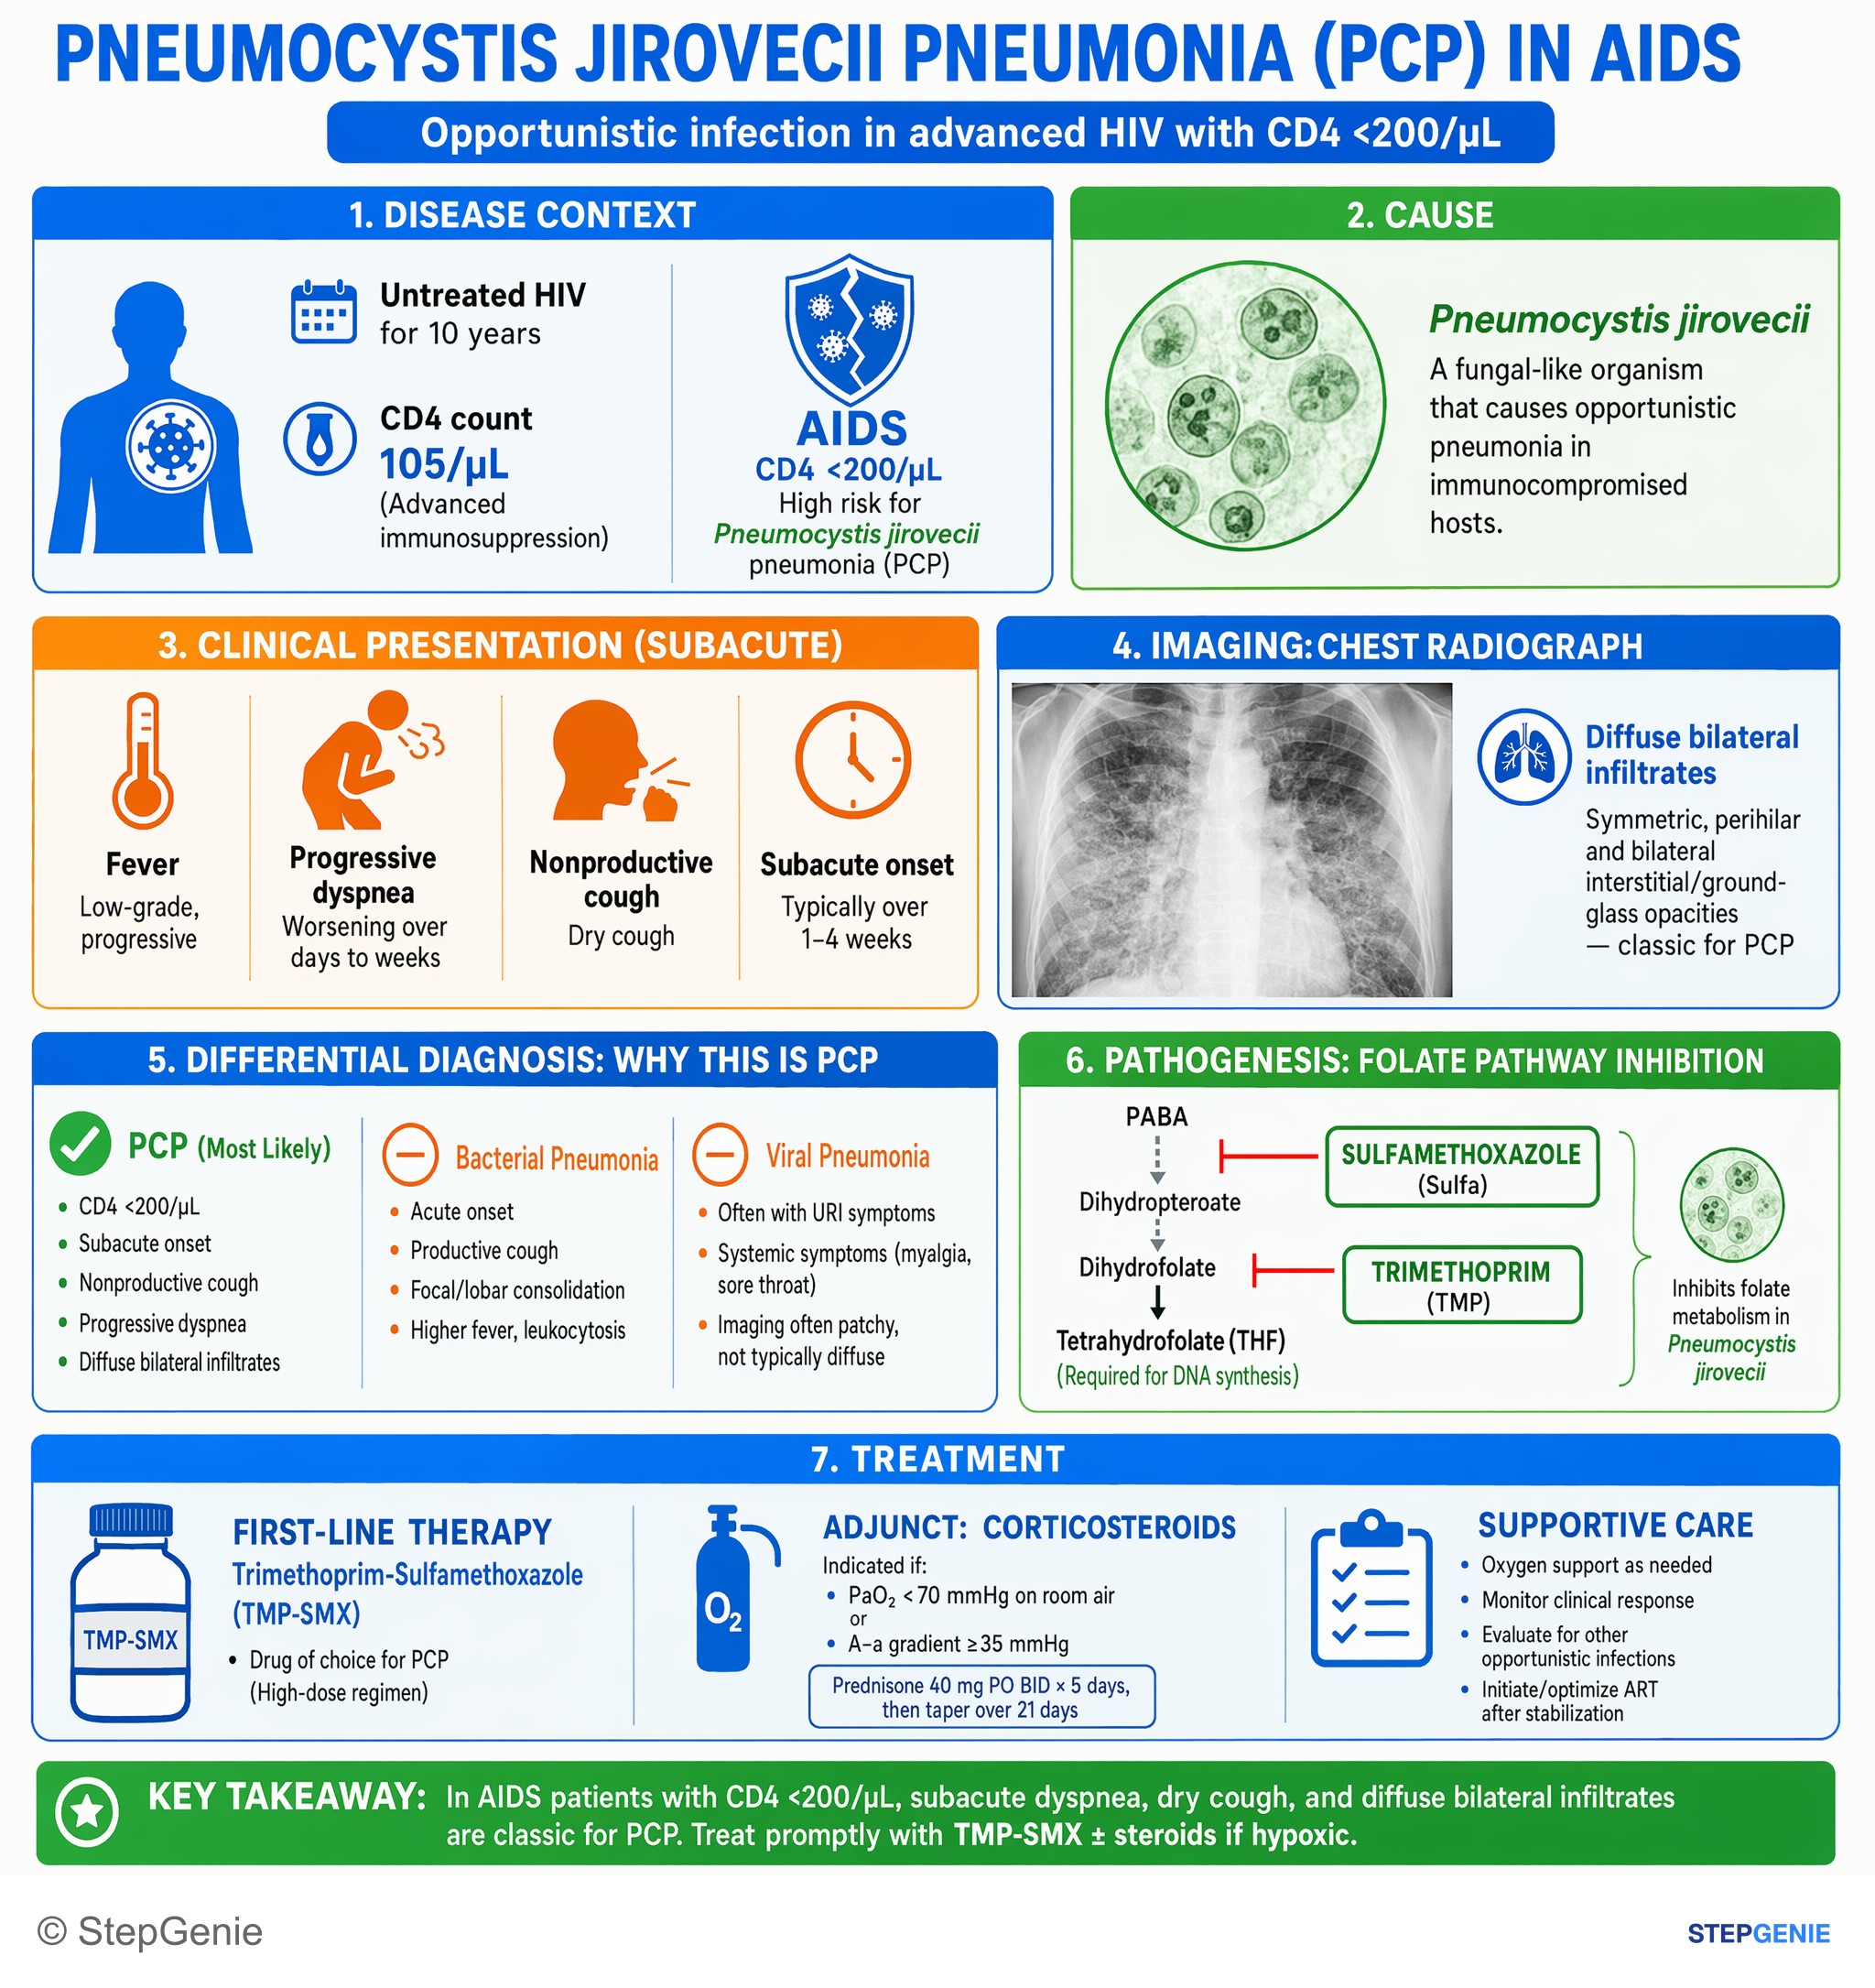
Pneumocystis jirovecii pneumonia in AIDS (CD4 <200) causes subacute dyspnea, dry cough, diffuse infiltrates; treat with TMP-SMX (±…
USMLE Step 2Frequently Asked Questions
Why does Pneumocystis jirovecii cause severe hypoxemia even when the lung exam seems mild?
Pneumocystis jirovecii causes severe hypoxemia because it fills the alveoli with a proteinaceous, foamy exudate that impairs gas exchange. This produces V/Q mismatch and diffusion impairment, so oxygenation drops even when auscultatory findings are not dramatic. That is why patients can have relatively quiet lungs but still be markedly hypoxic with an increased A–a gradient.
How do you tell Pneumocystis pneumonia from typical bacterial pneumonia on Step 1?
Pneumocystis pneumonia is suggested by a subacute illness with fever, nonproductive cough, progressive dyspnea, and diffuse bilateral interstitial or ground-glass infiltrates rather than lobar consolidation. Typical bacterial pneumonia more often causes abrupt onset, productive cough, higher white blood cell counts, and lobar findings. PCP is especially associated with impaired cell-mediated immunity, particularly HIV/AIDS with CD4 counts below 200 cells/mm3.
What is the first-line treatment for Pneumocystis jirovecii pneumonia, and when do you add steroids?
The first-line treatment for Pneumocystis jirovecii pneumonia is TMP-SMX, and adjunctive corticosteroids are added in moderate-to-severe disease with significant hypoxemia. A commonly tested threshold is PaO2 below 70 mmHg on room air or an elevated A–a gradient. Steroids are used because inflammatory worsening can occur after organisms are killed in the alveoli.
How is Pneumocystis jirovecii diagnosed in a vignette?
Pneumocystis jirovecii is classically diagnosed by identifying cysts on silver stain, especially Gomori methenamine silver stain, often using bronchoalveolar lavage samples. A frequent microscopic description is cup-shaped cysts. Elevated LDH and beta-D-glucan can support the diagnosis, but they are not definitive, so the silver stain finding is the classic Step-style clue.
Who needs Pneumocystis jirovecii prophylaxis, and what drug is used?
Patients with HIV and CD4 counts below 200 cells/mm3 are the classic group who need Pneumocystis jirovecii prophylaxis, and TMP-SMX is the first-line drug. Prophylaxis is also considered in certain transplant patients and others on chronic immunosuppression. In HIV, a common test concept is that prophylaxis can be stopped after immune reconstitution on ART when the CD4 count rises above 200.