Coccidioides immitis and its near-identical sister species C. posadasii are dimorphic soil fungi of the southwestern United States that cause coccidioidomycosis ("Valley fever") when someone inhales arthroconidia from disturbed dust. In tissue they form large spherules filled with endospores, not budding yeast. Most infections are silent or a self-limited pneumonia, often with erythema nodosum; about 1% disseminate to skin, bone, joints or meninges, mainly with impaired cell-mediated immunity, pregnancy, diabetes, or African or Filipino ancestry. Diagnose with serology (EIA, immunodiffusion, complement fixation). IDSA 2016 treats primary pneumonia only in debilitated or high-risk patients (oral fluconazole), gives fluconazole for life in meningitis, and uses amphotericin B for severe disease and in the first trimester of pregnancy.
Coccidioides at a glance
| Feature | High-yield fact | Exam clue |
|---|---|---|
| Species | C. immitis (typically California) and C. posadasii (typically outside California) | Same disease; either name can appear |
| Where | Arizona, California's Central (San Joaquin) Valley, Nevada, New Mexico, Utah, Texas west of El Paso, south-central Washington; parts of Mexico, Central and South America | Recent move to, or trip through, the desert Southwest |
| Environmental form | Mold in soil; barrel-shaped arthroconidia alternating with empty cells | Construction, farming, digging, dust blown downwind |
| Tissue form | Spherules (10–80 µm) packed with endospores (2–5 µm) | "Spherules with endospores" on biopsy |
| Spread | Inhalation; not person to person, not from animals | Sick contacts are not the source |
| Burden | About 20,000 US cases reported a year (21,037 provisional in 2023: 10,990 in Arizona, 9,060 in California); CDC estimates the true burden is 10–18 times higher | CDC: 15–30% of community-acquired pneumonia in Phoenix and Tucson |
Life cycle: why biopsies show spherules
- Soil: the fungus grows as a mold after heavy rain. When conditions turn hot and dry, it disperses into the air as arthroconidia carried in dust.
- Alveolus: at body temperature, an inhaled arthroconidium converts into a spherule.
- Rupture: the spherule enlarges and bursts, releasing thousands of endospores, each of which can form a new spherule.
- Host response: granulomatous inflammation. Containment depends on cell-mediated immunity (the Th1 arm), which is why HIV, transplant immunosuppression, TNF-α inhibitors and high-dose steroids let the infection spread.
Two traps. "Mold in the cold, yeast in the heat" fits the other endemic dimorphic fungi such as Histoplasma and Blastomyces, but the tissue form of Coccidioides is a spherule, not a yeast. And the culture plate is the dangerous form: the mold releases highly infectious arthroconidia, so culture needs a biosafety level 3 laboratory, and the lab must be warned when coccidioidomycosis is suspected.
Clinical spectrum
| Presentation | Share of infections (CDC) | What it looks like |
|---|---|---|
| No symptoms | Most infections (only about 40% are symptomatic) | Nothing to find |
| Primary pneumonia ("Valley fever") | About 40%, beginning 1–3 weeks after exposure | Fatigue, cough, fever, dyspnea, headache, night sweats, myalgias, joint pain, rash |
| Lung complications | About 5–10% | Nodules, thin-walled cavities (hemoptysis, rupture into the pleural space), chronic pneumonia |
| Dissemination | About 1% | Skin and soft tissue, bone, joints, meninges |
- It masquerades as bacterial pneumonia. CDC advises testing for Valley fever when community-acquired pneumonia in an endemic area does not improve on empiric antibiotics.
- Fatigue may be the last complaint to resolve, with weeks to months of convalescence (IDSA).
- Imaging: segmental or lobar consolidation, sometimes hilar or mediastinal adenopathy; effusion in about 5–15%.
- Peripheral eosinophilia can be an important clue.
Erythema nodosum: the reassuring rash
- Tender, red subcutaneous nodules, usually on the shins, appearing 1–3 weeks after the respiratory symptoms. It is the most frequent reactive skin eruption in coccidioidomycosis; erythema multiforme also occurs.
- Joint pain is typically symmetric arthralgia of the ankles, knees, hips and elbows, and the illness is also called "desert rheumatism."
- Erythema nodosum or multiforme is a favorable prognostic sign: it reflects a robust immune response, not dissemination. The nodules are a reaction, whereas skin lesions of disseminated disease are infected tissue.
- Erythema nodosum has many other triggers, compared in the erythema nodosum Q-bank breakdown.
Who disseminates, and where
| Risk group | Specifics |
|---|---|
| Impaired cell-mediated immunity | HIV (especially CD4 < 250/µL), solid organ or stem cell transplant, TNF-α inhibitors, high-dose corticosteroids (IDSA cites ≥20 mg prednisone daily for ≥2 weeks) |
| Pregnancy | Second or third trimester and postpartum; highest risk in the third trimester |
| Ancestry | Filipino and African ancestry are the classic pair; Merck ranks Filipino, Black, American Indian, Hispanic and Asian people in decreasing order of relative risk |
| Other | Diabetes, older age, cancer |
- Usual targets: skin, subcutaneous tissue, bone (osteomyelitis), joints and meninges. IDSA recommends surgical consultation for every patient with vertebral disease.
- Meningitis: headache, blurry vision, photophobia, meningismus, cognitive decline or focal deficits. CSF shows a lymphocytic or mixed pleocytosis, very high protein and low glucose; complement-fixing antibody in CSF is diagnostic.
- Meningitis complications: hydrocephalus (often needing a ventricular shunt), vasculitis and strokes. Untreated, it is uniformly fatal, and 78% relapsed in a small series when azoles were stopped (UC Davis Center for Valley Fever), which is why therapy is lifelong.
Diagnosis
Who to test (CDC): community-acquired pneumonia, or erythema nodosum after recent respiratory symptoms, in someone who lives in or has traveled to a highly endemic area (south-central Arizona or the San Joaquin Valley) or had outbreak exposure; and pneumonia in an endemic area that has not improved on antibiotics.
| Test | What it tells you |
|---|---|
| EIA (IgM and IgG) | Sensitive first-line screen; IgM without IgG is the least convincing result (IDSA) |
| Immunodiffusion | Detects IgM (positive early) or IgG; confirms a positive EIA |
| Complement fixation (IgG) | Titer tracks severity: IDSA lists titers above 1:16 among markers of more severe illness, and Merck notes titers of 1:32 or higher signal a greater likelihood of dissemination |
| CSF complement fixation | Positive = coccidioidal meningitis |
| Histopathology or cytology | Spherules with endospores in sputum, pleural fluid, CSF, drainage or tissue |
| Culture | Grows the mold; a biosafety level 3 hazard |
| PCR | Sensitivity 56–75%, specificity 99–100% (CDC) |
- Early serology can be negative: CDC advises repeating it 2–6 weeks later if suspicion remains.
- Antibodies usually fade as the infection resolves, so a positive result points to recent or active infection.
- IDSA advises lumbar puncture only for unusual, worsening or persistent headache, altered mental status, unexplained nausea or vomiting, or a new focal deficit.
Treatment (IDSA 2016)
| Situation | Management |
|---|---|
| Mild pneumonia, no risk factors | No antifungal: education, close follow-up and physical reconditioning |
| Debilitating illness, extensive lung involvement, diabetes or frailty (some experts add African or Filipino ancestry) | Oral azole such as fluconazole ≥400 mg daily for 3–6 months or longer |
| Asymptomatic nodule or cavity | No antifungal |
| Symptomatic chronic cavitary pneumonia | Fluconazole or itraconazole for at least 1 year |
| Disseminated soft tissue, bone or joint | Fluconazole or itraconazole; amphotericin B first for extensive or limb-threatening bone disease or imminent cord compromise, then an azole |
| Meningitis | Fluconazole 400–1,200 mg daily for life; if it fails, a higher dose, another azole or intrathecal amphotericin B |
| Pregnancy, first trimester | IV amphotericin B (high-dose fluconazole in the first trimester has been linked to birth defects); an azole can be considered after the first trimester |
| HIV with active infection and CD4 < 250/µL | Treat all, and continue while CD4 stays below 250/µL (no primary prophylaxis) |
- Azoles (fluconazole, itraconazole) inhibit fungal cytochrome P450 14α-demethylase, blocking ergosterol synthesis. They also inhibit human drug metabolism, so check interactions. Fluconazole reaches CSF at 70% or more of serum levels, which makes it the meningitis drug.
- Amphotericin B binds ergosterol and opens pores in the fungal membrane. Its toxicities are nephrotoxicity, hypokalemia, hypomagnesemia and infusion reactions; lipid formulations are less toxic and preferred for severe disease.
Dimorphic fungi and look-alikes
| Fungus | Where | Tissue form | Classic clue |
|---|---|---|---|
| Coccidioides | Desert Southwest, Mexico, Central and South America | Spherules with endospores | Dust exposure, erythema nodosum, eosinophilia |
| Histoplasma | Ohio and Mississippi River valleys | Small oval yeasts inside macrophages | Bird or bat droppings, caves; urine antigen |
| Blastomyces | Ohio and Mississippi River valleys, Great Lakes region, southern Canada | Large yeasts with broad-based buds | Spread to skin, bone and prostate |
| Cryptococcus (opportunistic yeast) | Soil with pigeon droppings | Encapsulated yeast with narrow-based buds | Meningitis in advanced HIV; India ink halo; antigen test |
The capsule-and-pigeon picture is decoded in the Cryptococcus neoformans mnemonic.
Practice question
A 26-year-old man moves from Ohio to Phoenix, Arizona, to work on a highway construction crew. Three weeks later he develops fever, dry cough, pleuritic chest pain and fatigue. A 5-day course of azithromycin does not help, and he then notices painful red nodules on both shins. Chest radiograph shows a patchy right lower lobe infiltrate, and his eosinophil count is mildly elevated. Which finding would most likely be seen on biopsy of the lung lesion?
- A. Large yeasts with broad-based buds
- B. Small oval yeasts within macrophages
- C. Thick-walled spherules containing endospores
- D. Encapsulated yeasts with narrow-based buds
- E. Septate hyphae branching at acute angles
Answer: C. Construction dust in Phoenix, pneumonia 3 weeks later that ignores a macrolide, erythema nodosum and eosinophilia add up to primary coccidioidomycosis, and Coccidioides forms spherules packed with endospores in tissue.
- A (Blastomyces): endemic to the Ohio and Mississippi River valleys, the Great Lakes region and southern Canada, not the desert, and it classically spreads to skin and bone.
- B (Histoplasma): the Ohio background is the bait, but his exposure (desert construction dust) and timing (symptoms within the 1–3 week incubation after arriving in Arizona) point to Coccidioides; histoplasmosis follows bird or bat droppings.
- D (Cryptococcus): mainly meningitis in advanced HIV, with a capsule seen on India ink.
- E (Aspergillus): invasive disease in neutropenic or transplant patients, or a fungus ball in an old cavity; not a healthy construction worker.
Next step? With no risk factors and a nondebilitating illness, IDSA 2016 favors education, close follow-up and reconditioning without antifungals; his erythema nodosum is reassuring. Fluconazole would be indicated for diabetes, extensive infiltrates, debilitating or prolonged symptoms, or (for some experts) African or Filipino ancestry.
Key takeaways
- Inhaled arthroconidia become spherules with endospores in tissue; not a yeast, and not spread person to person.
- Desert Southwest exposure plus pneumonia that fails antibiotics means test for Valley fever.
- Erythema nodosum and symmetric arthralgias are hypersensitivity signs with a good prognosis; eosinophilia is a clue.
- About 1% disseminate (skin, bone, joints, meninges): impaired cell-mediated immunity, pregnancy (third trimester), Filipino or African ancestry, diabetes.
- Serology first: EIA, confirmed by immunodiffusion or complement fixation; CF titer tracks severity; CF antibody in CSF means meningitis; warn the lab before culture.
- Treat by risk (IDSA 2016): observe mild disease; fluconazole ≥400 mg/day for debilitated or high-risk patients; lifelong fluconazole for meningitis; amphotericin B for severe disease and the first trimester.
Sources
- IDSA 2016 Clinical Practice Guideline for the Treatment of Coccidioidomycosis — Infectious Diseases Society of America (2016)
- Clinical Overview of Valley Fever — CDC
- Testing Algorithm for Coccidioidomycosis — CDC
- Reported Cases of Valley Fever — CDC
- About Valley Fever — CDC
- Coccidioidomycosis — Merck Manual Professional Edition
- Primary Pulmonary Infection — UC Davis Health Center for Valley Fever
- Coccidioidal Meningitis — UC Davis Health Center for Valley Fever
- Coccidioides Species — Doctor Fungus
- Guide to Coccidioidomycosis (2023) — Arizona Department of Health Services
- Antifungal Medications — Merck Manual Professional Edition
- Diflucan (Fluconazole) Prescribing Information — DailyMed, National Library of Medicine
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
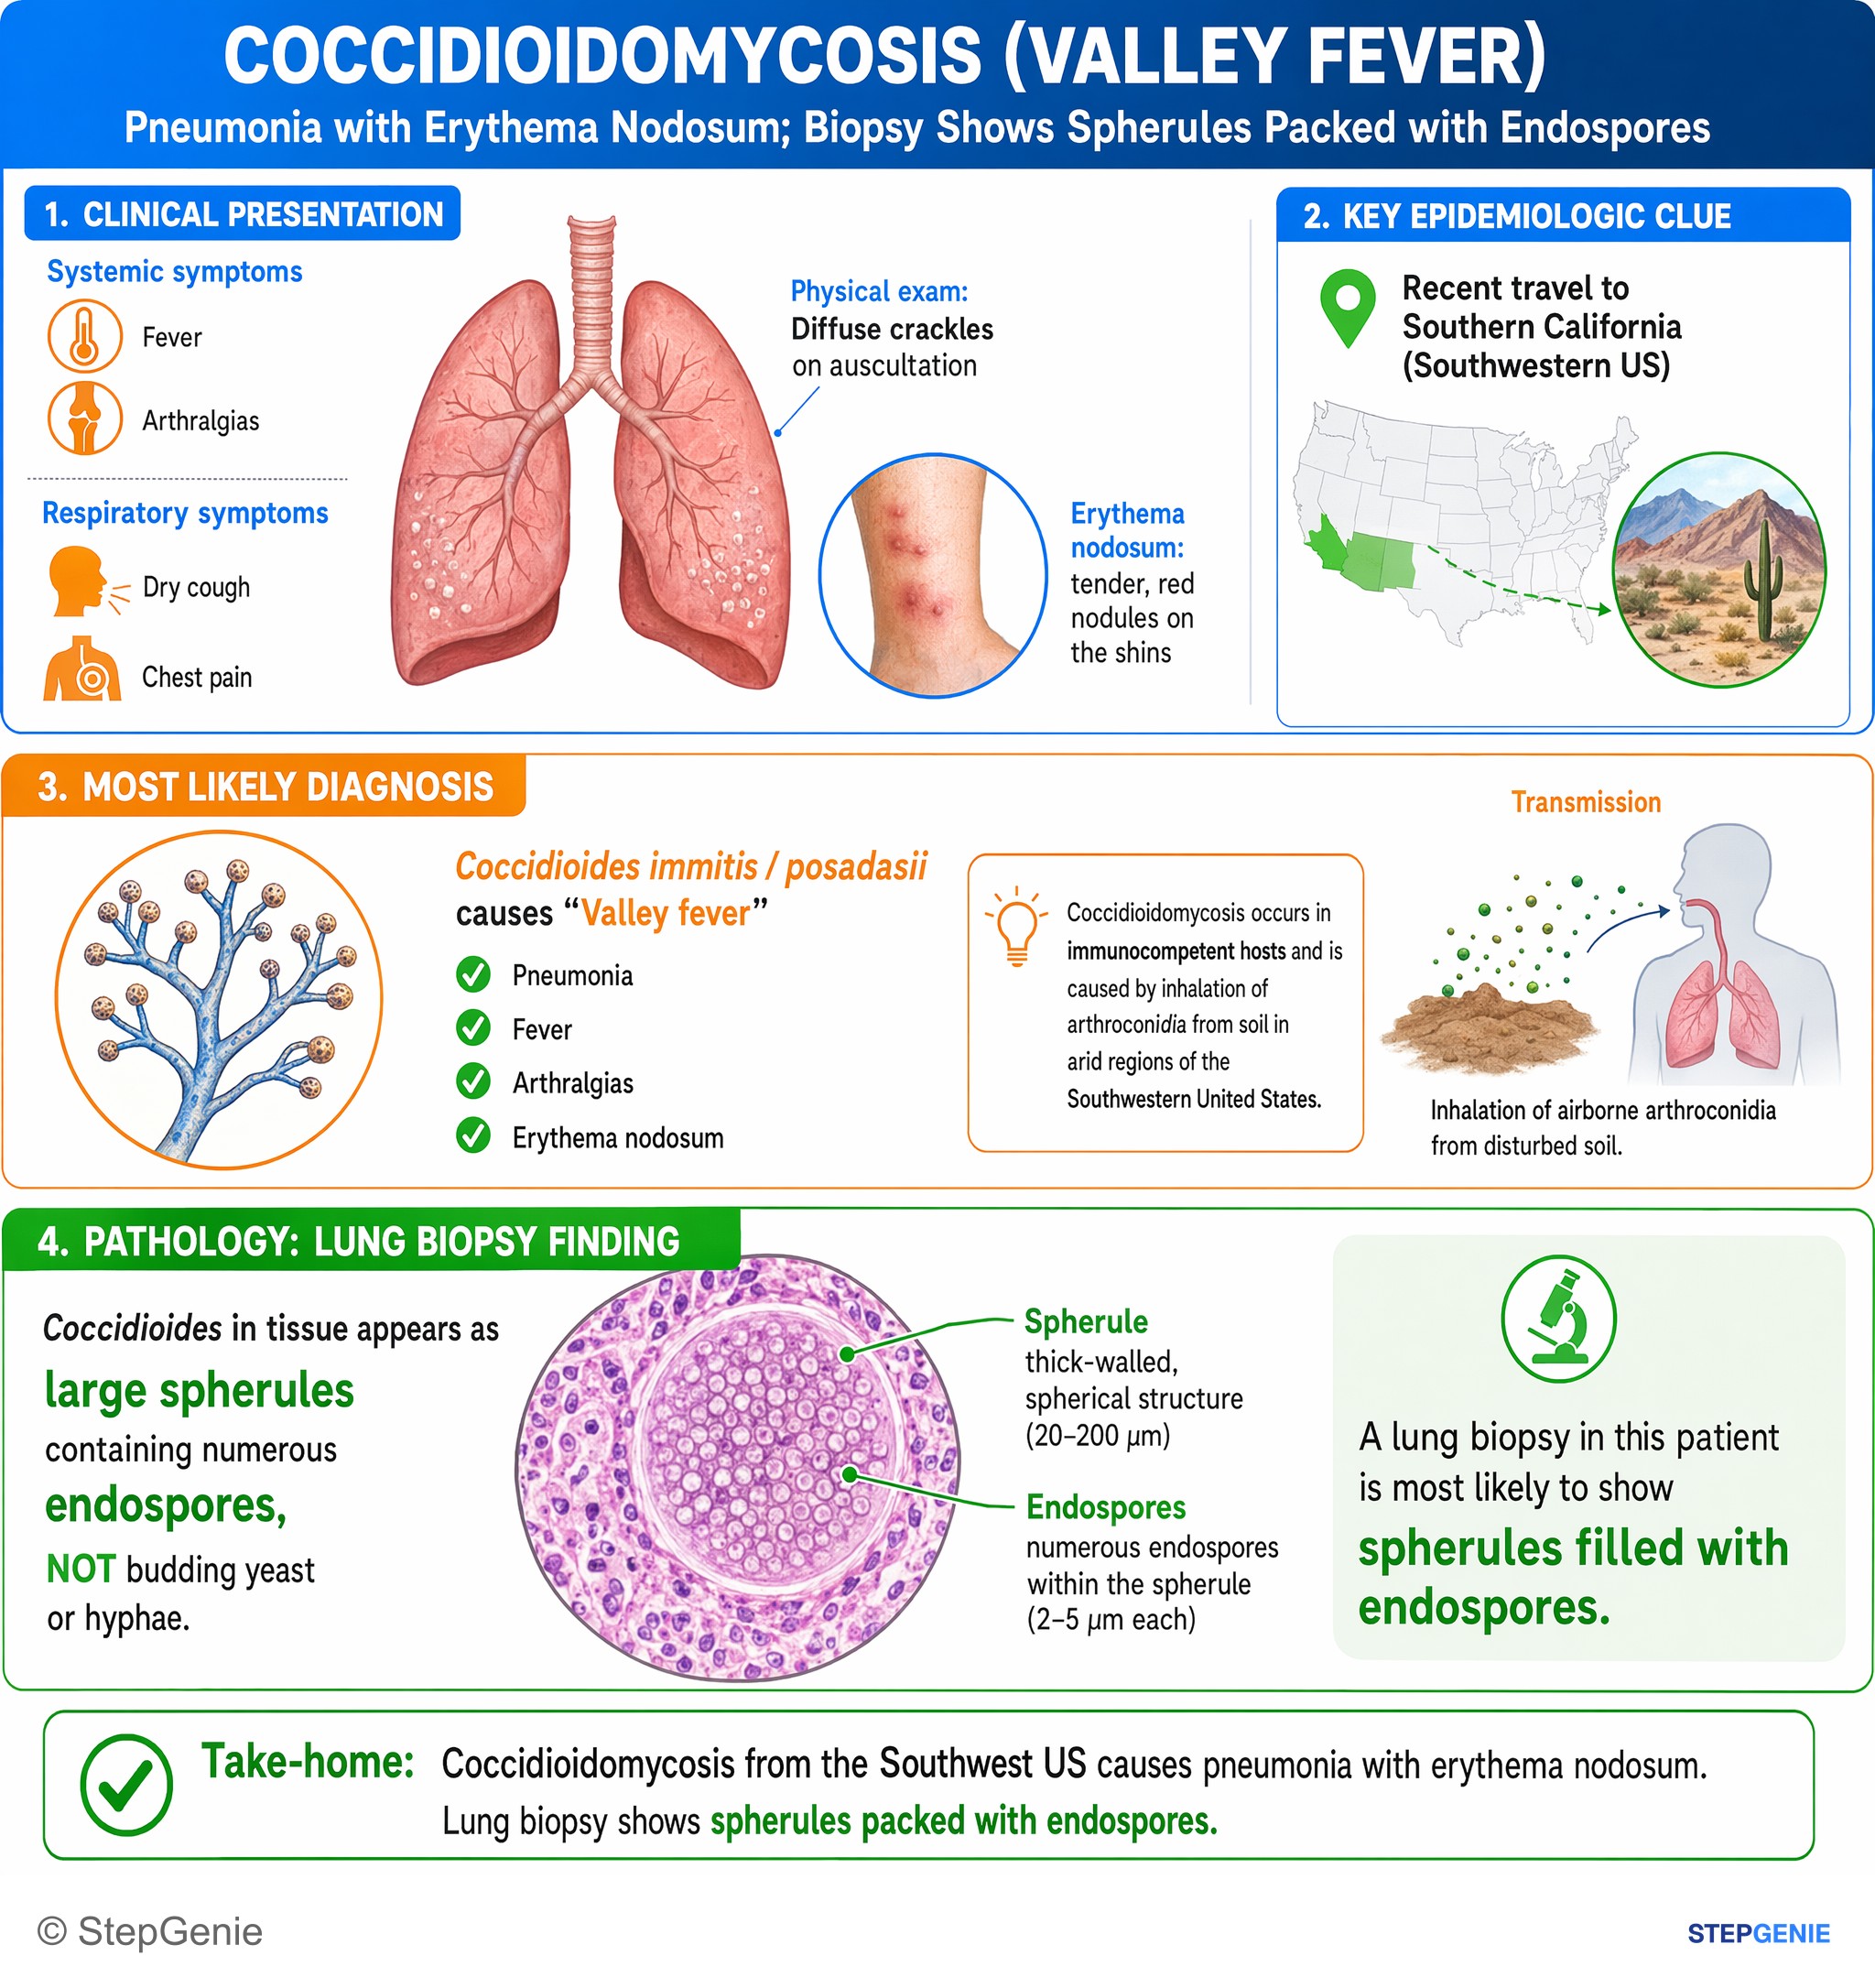
Coccidioidomycosis from Southwest US causes pneumonia with erythema nodosum; lung biopsy shows spherules packed with endospores.
USMLE Step 1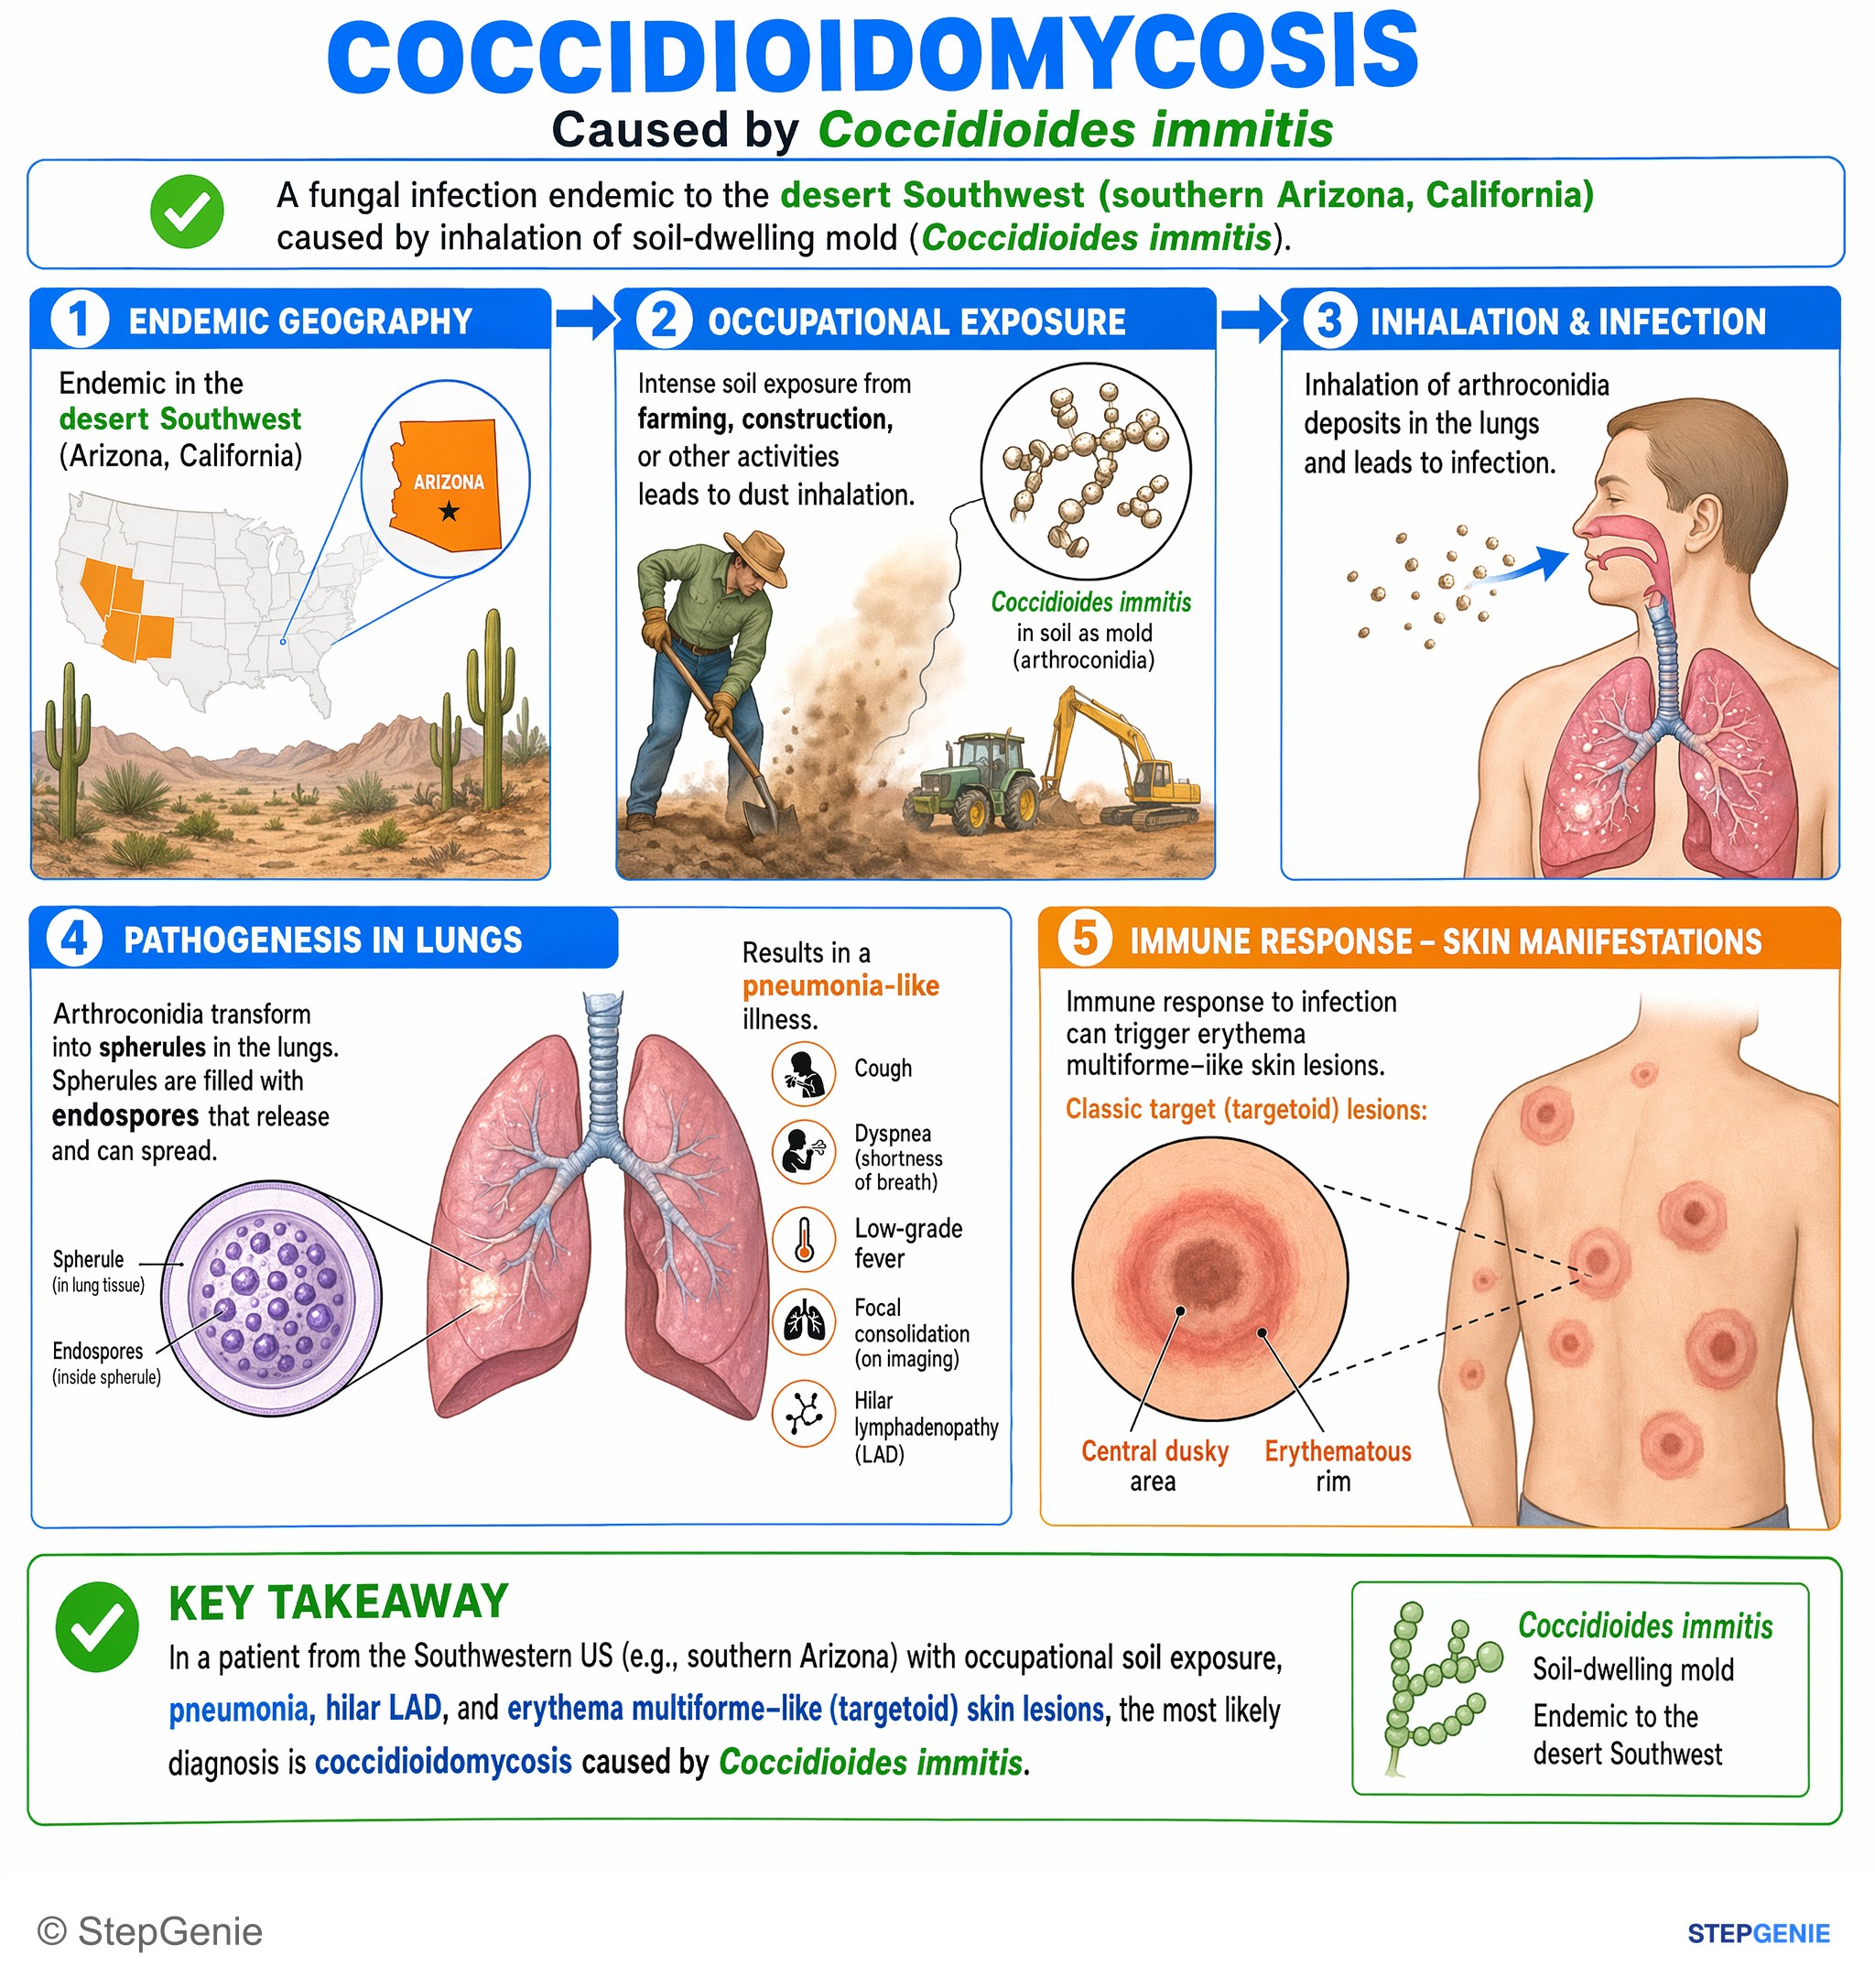
Coccidioidomycosis from Coccidioides immitis causes pneumonia plus erythema multiforme–like skin lesions in patients from the southwestern…
USMLE Step 1Frequently Asked Questions
What is Coccidioides immitis?
Coccidioides immitis is a dimorphic soil fungus of the southwestern United States that causes coccidioidomycosis, also called Valley fever. It grows as a mold in soil, and its arthroconidia are inhaled in dust and turn into spherules filled with endospores in the lung. Its sister species, Coccidioides posadasii, causes the same disease and is found mainly outside California.
What does Coccidioides look like in tissue?
In tissue, Coccidioides forms large, thick-walled spherules, about 10 to 80 micrometers across, packed with small endospores. When a spherule ruptures, the released endospores can each form a new spherule. Unlike Histoplasma and Blastomyces, it does not appear as a budding yeast in tissue.
Why does Valley fever cause erythema nodosum?
Erythema nodosum in coccidioidomycosis is a reactive, hypersensitivity-type eruption, not spread of the fungus to the skin. The tender red nodules usually appear on the shins 1 to 3 weeks after the respiratory symptoms. It reflects a robust immune response and is considered a favorable prognostic sign.
Who is at risk for disseminated coccidioidomycosis?
The CDC estimates that about 1% of infections disseminate beyond the lungs. Risk is higher with impaired cell-mediated immunity (HIV, organ transplant, TNF-alpha inhibitors, high-dose corticosteroids), pregnancy (especially the third trimester), African or Filipino ancestry, and diabetes. The usual targets are skin, bone, joints and the meninges.
How is Valley fever diagnosed?
Serology is the main test: an enzyme immunoassay for IgM and IgG, confirmed with immunodiffusion or complement fixation; the complement-fixation titer tracks severity. Spherules can be seen in tissue or body fluids, and PCR and culture are available, but the culture is a laboratory biohazard, so the lab must be warned. If early serology is negative and suspicion remains, the CDC suggests repeating it 2 to 6 weeks later.
What is the treatment for coccidioidomycosis?
Most mild infections in otherwise healthy people resolve without antifungals, and the IDSA 2016 guideline recommends education, close follow-up and reconditioning for them. Fluconazole at 400 mg a day or more is used for debilitating illness, extensive lung involvement or risk factors such as diabetes. Coccidioidal meningitis needs fluconazole for life, and amphotericin B is used for severe disease and in the first trimester of pregnancy.