You’re cruising through your Q-bank and hit a stem: wheezing infant, wintertime, hypoxemia, maybe some crackles. You know it’s RSV… but the question isn’t really asking “What’s the diagnosis?” It’s asking whether you can prove it by eliminating everything else. That’s the Step mindset: the correct answer matters, but the distractors are where the test writers hide the points.
Tag: Microbiology > Virology
The Clinical Vignette (RSV Classic)
A 4-month-old infant is brought in during January for 2 days of runny nose and cough, now with increasing work of breathing. Parents report poor feeding. Vitals: T 37.8°C, RR 60, O2 sat 90% on room air. Exam: nasal flaring, intercostal retractions, and diffuse wheezing with crackles. CXR shows hyperinflation and peribronchial thickening.
Question: Which pathogen is the most likely cause?
Correct Answer: Respiratory Syncytial Virus (RSV)
Why RSV fits best
RSV is the most common cause of bronchiolitis and pneumonia in infants. The vignette screams:
- Age < 2 years (especially < 6 months)
- Winter season
- Upper respiratory prodrome lower respiratory symptoms
- Bronchiolitis picture: wheeze + crackles + hyperinflation
- Hypoxemia + increased work of breathing
High-yield microbiology
RSV basics (Step-ready):
- Family: Paramyxoviridae (sometimes taught as Pneumoviridae in updated taxonomy; exams often still lump with paramyxo-like features)
- Genome: (-) single-stranded RNA, enveloped
- Key proteins:
- F (fusion) protein syncytia (multinucleated giant cells)
- G protein attachment to respiratory epithelium
Pathogenesis you can visualize
RSV infects bronchiolar epithelium inflammation + necrosis + sloughed cells + mucus plugging air trapping and hyperinflation (especially in tiny infant airways).
Diagnosis & management (high-yield clinical)
- Diagnosis: often clinical; PCR panels common in real life
- Treatment: Supportive (oxygen, hydration, suctioning)
- Prevention in high-risk infants: palivizumab (monoclonal Ab against F protein)
- Think: prematurity, chronic lung disease, significant congenital heart disease
Why Every Other Answer Choice Is Wrong (and What They’re Trying to Test)
Below is a systematic distractor breakdown—exactly how you should train your brain on review.
Distractor 1: Influenza virus
Why they want you to pick it: winter respiratory illness + sick kid.
Why it’s wrong here:
- Influenza typically causes abrupt onset high fever, myalgias, headache, and systemic toxicity.
- Wheezing can happen, but classic presentation is “hit by a truck” and fever is usually prominent.
High-yield differentiator
- Influenza: segmented (-)RNA orthomyxovirus; antigenic shift/drift
- RSV: bronchiolitis in infants; syncytia via F protein
Clinical pearl: In a young infant, wheezing + crackles + hyperinflation points more toward RSV bronchiolitis than primary influenza.
Distractor 2: Parainfluenza virus
Why they want you to pick it: also a paramyxovirus and affects kids.
Why it’s wrong here:
- Parainfluenza classically causes croup (laryngotracheobronchitis):
- Barking cough
- Inspiratory stridor
- Hoarseness
- Imaging clue (if given): steeple sign (subglottic narrowing)
High-yield differentiator
- Parainfluenza: upper airway obstruction phenotype (stridor)
- RSV: lower airway small bronchiole disease (wheezing, crackles)
Distractor 3: Adenovirus
Why they want you to pick it: pediatric respiratory virus; can cause pneumonia.
Why it’s wrong here: Adenovirus often comes with extra clues beyond bronchiolitis:
- Pharyngitis
- Conjunctivitis (think: “pharyngoconjunctival fever”)
- Can cause hemorrhagic cystitis (important board association)
- Can cause outbreaks in military recruits, daycare settings
High-yield micro
- Nonenveloped dsDNA virus
- Can cause severe pneumonia, but the classic bronchiolitis infant winter wheeze still favors RSV.
Distractor 4: Rhinovirus
Why they want you to pick it: most common cause of “common cold”; kids wheeze.
Why it’s wrong here:
- Rhinovirus is usually mild URI, afebrile or low-grade fever.
- It can trigger asthma exacerbations, but it’s less likely to cause classic bronchiolitis with hypoxemia in a 4-month-old.
High-yield micro
- Picornavirus, (+)ssRNA, nonenveloped
- Prefers cooler temps (nasal mucosa); classically upper airway.
Rule of thumb: If the question is really pushing lower respiratory distress in an infant, RSV > rhinovirus.
Distractor 5: Human metapneumovirus
Why they want you to pick it: it can look exactly like RSV (and test writers know that).
Why it’s wrong here (test logic):
- Metapneumovirus causes bronchiolitis/pneumonia similar to RSV, often in young children and winter/spring.
- Many USMLE-style questions still expect RSV as the prototypical bronchiolitis virus, unless they give a specific clue (e.g., outbreak patterns or older child with similar syndrome but RSV already ruled out).
How to handle it on exams:
If the vignette is a straight-down-the-middle bronchiolitis case, pick RSV unless they deliberately steer you away.
Distractor 6: Bordetella pertussis (bacterial distractor)
Why they want you to pick it: infant respiratory illness; can be severe.
Why it’s wrong here: Pertussis is about paroxysmal cough:
- Staccato coughing fits
- Inspiratory whoop
- Post-tussive emesis
- Often minimal fever
- Lymphocytosis may be mentioned
RSV bronchiolitis is about wheezing, increased work of breathing, and hypoxemia, not classic whooping cough episodes.
The “One Table” You Should Remember
| Pathogen | Typical Syndrome | Key Clues | High-Yield Buzzwords |
|---|---|---|---|
| RSV | Bronchiolitis, pneumonia (infants) | Winter, wheeze + crackles, hyperinflation | F protein, syncytia, palivizumab |
| Parainfluenza | Croup | Stridor, barking cough | Steeple sign |
| Influenza | Febrile respiratory illness | Abrupt onset, myalgias | Drift/shift, neuraminidase |
| Adenovirus | URI/LRI + systemic | Conjunctivitis, pharyngitis | Hemorrhagic cystitis |
| Rhinovirus | Common cold | Mild URI, triggers asthma | Picornavirus, nonenveloped |
| Pertussis | Paroxysmal cough | Whoop, post-tussive emesis | Lymphocytosis, toxin-mediated |
USMLE High-Yield RSV Takeaways (What They Love to Ask)
- Most common cause of bronchiolitis in infants and young children
- (-)ssRNA, enveloped, classically taught with paramyxovirus-like features
- F protein fusion of infected cells syncytia
- Bronchiolitis path: mucus plugging + airway edema wheeze, crackles, hyperinflation
- Management is supportive
- Palivizumab prophylaxis targets F protein (high-risk infants)
How to Review This Question Like a Pro
After you pick RSV, force yourself to do a 10-second check:
- Upper vs lower airway? (stridor = croup; wheeze = bronchiolitis/asthma)
- Age + season? (infant + winter = RSV)
- Systemic toxicity? (high fever/myalgias = influenza)
- Extra organs involved? (conjunctivitis/cystitis = adenovirus)
That habit is what turns “I recognized the vignette” into “I can’t be tricked.”
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
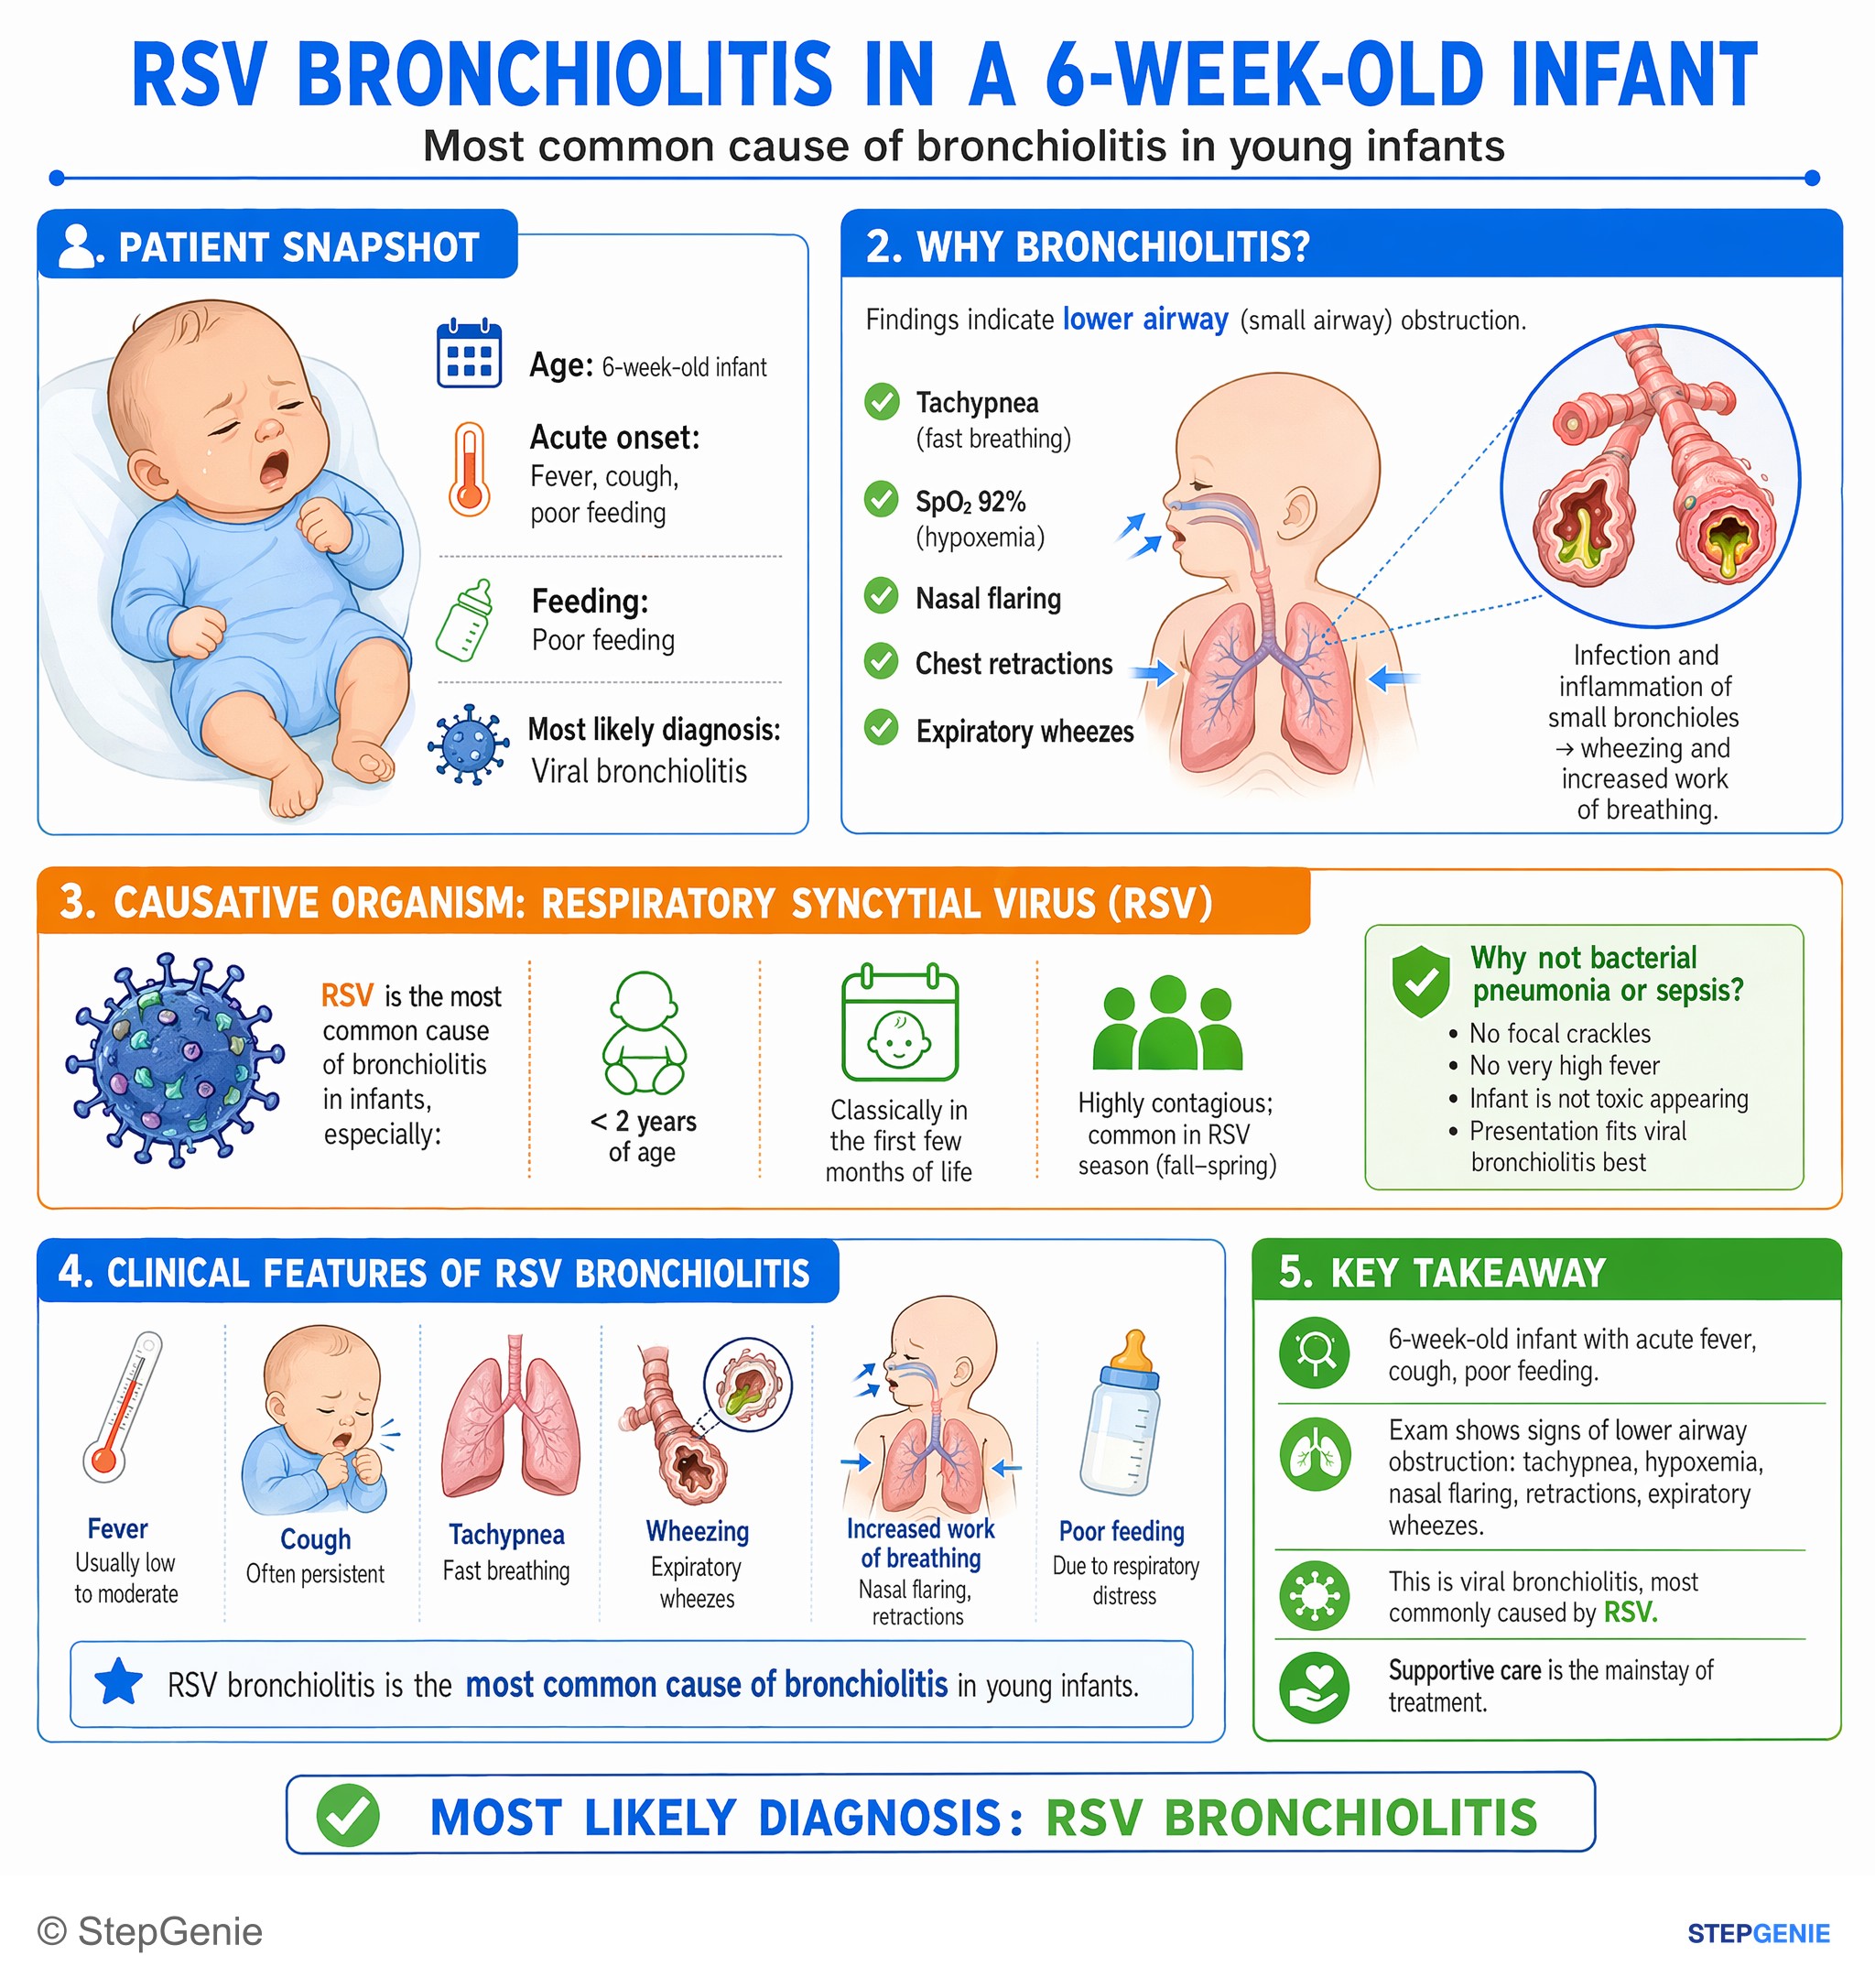
RSV bronchiolitis in young infants causes fever, cough, tachypnea, wheezing, and increased work of breathing; it is the most common cause…
USMLE Step 1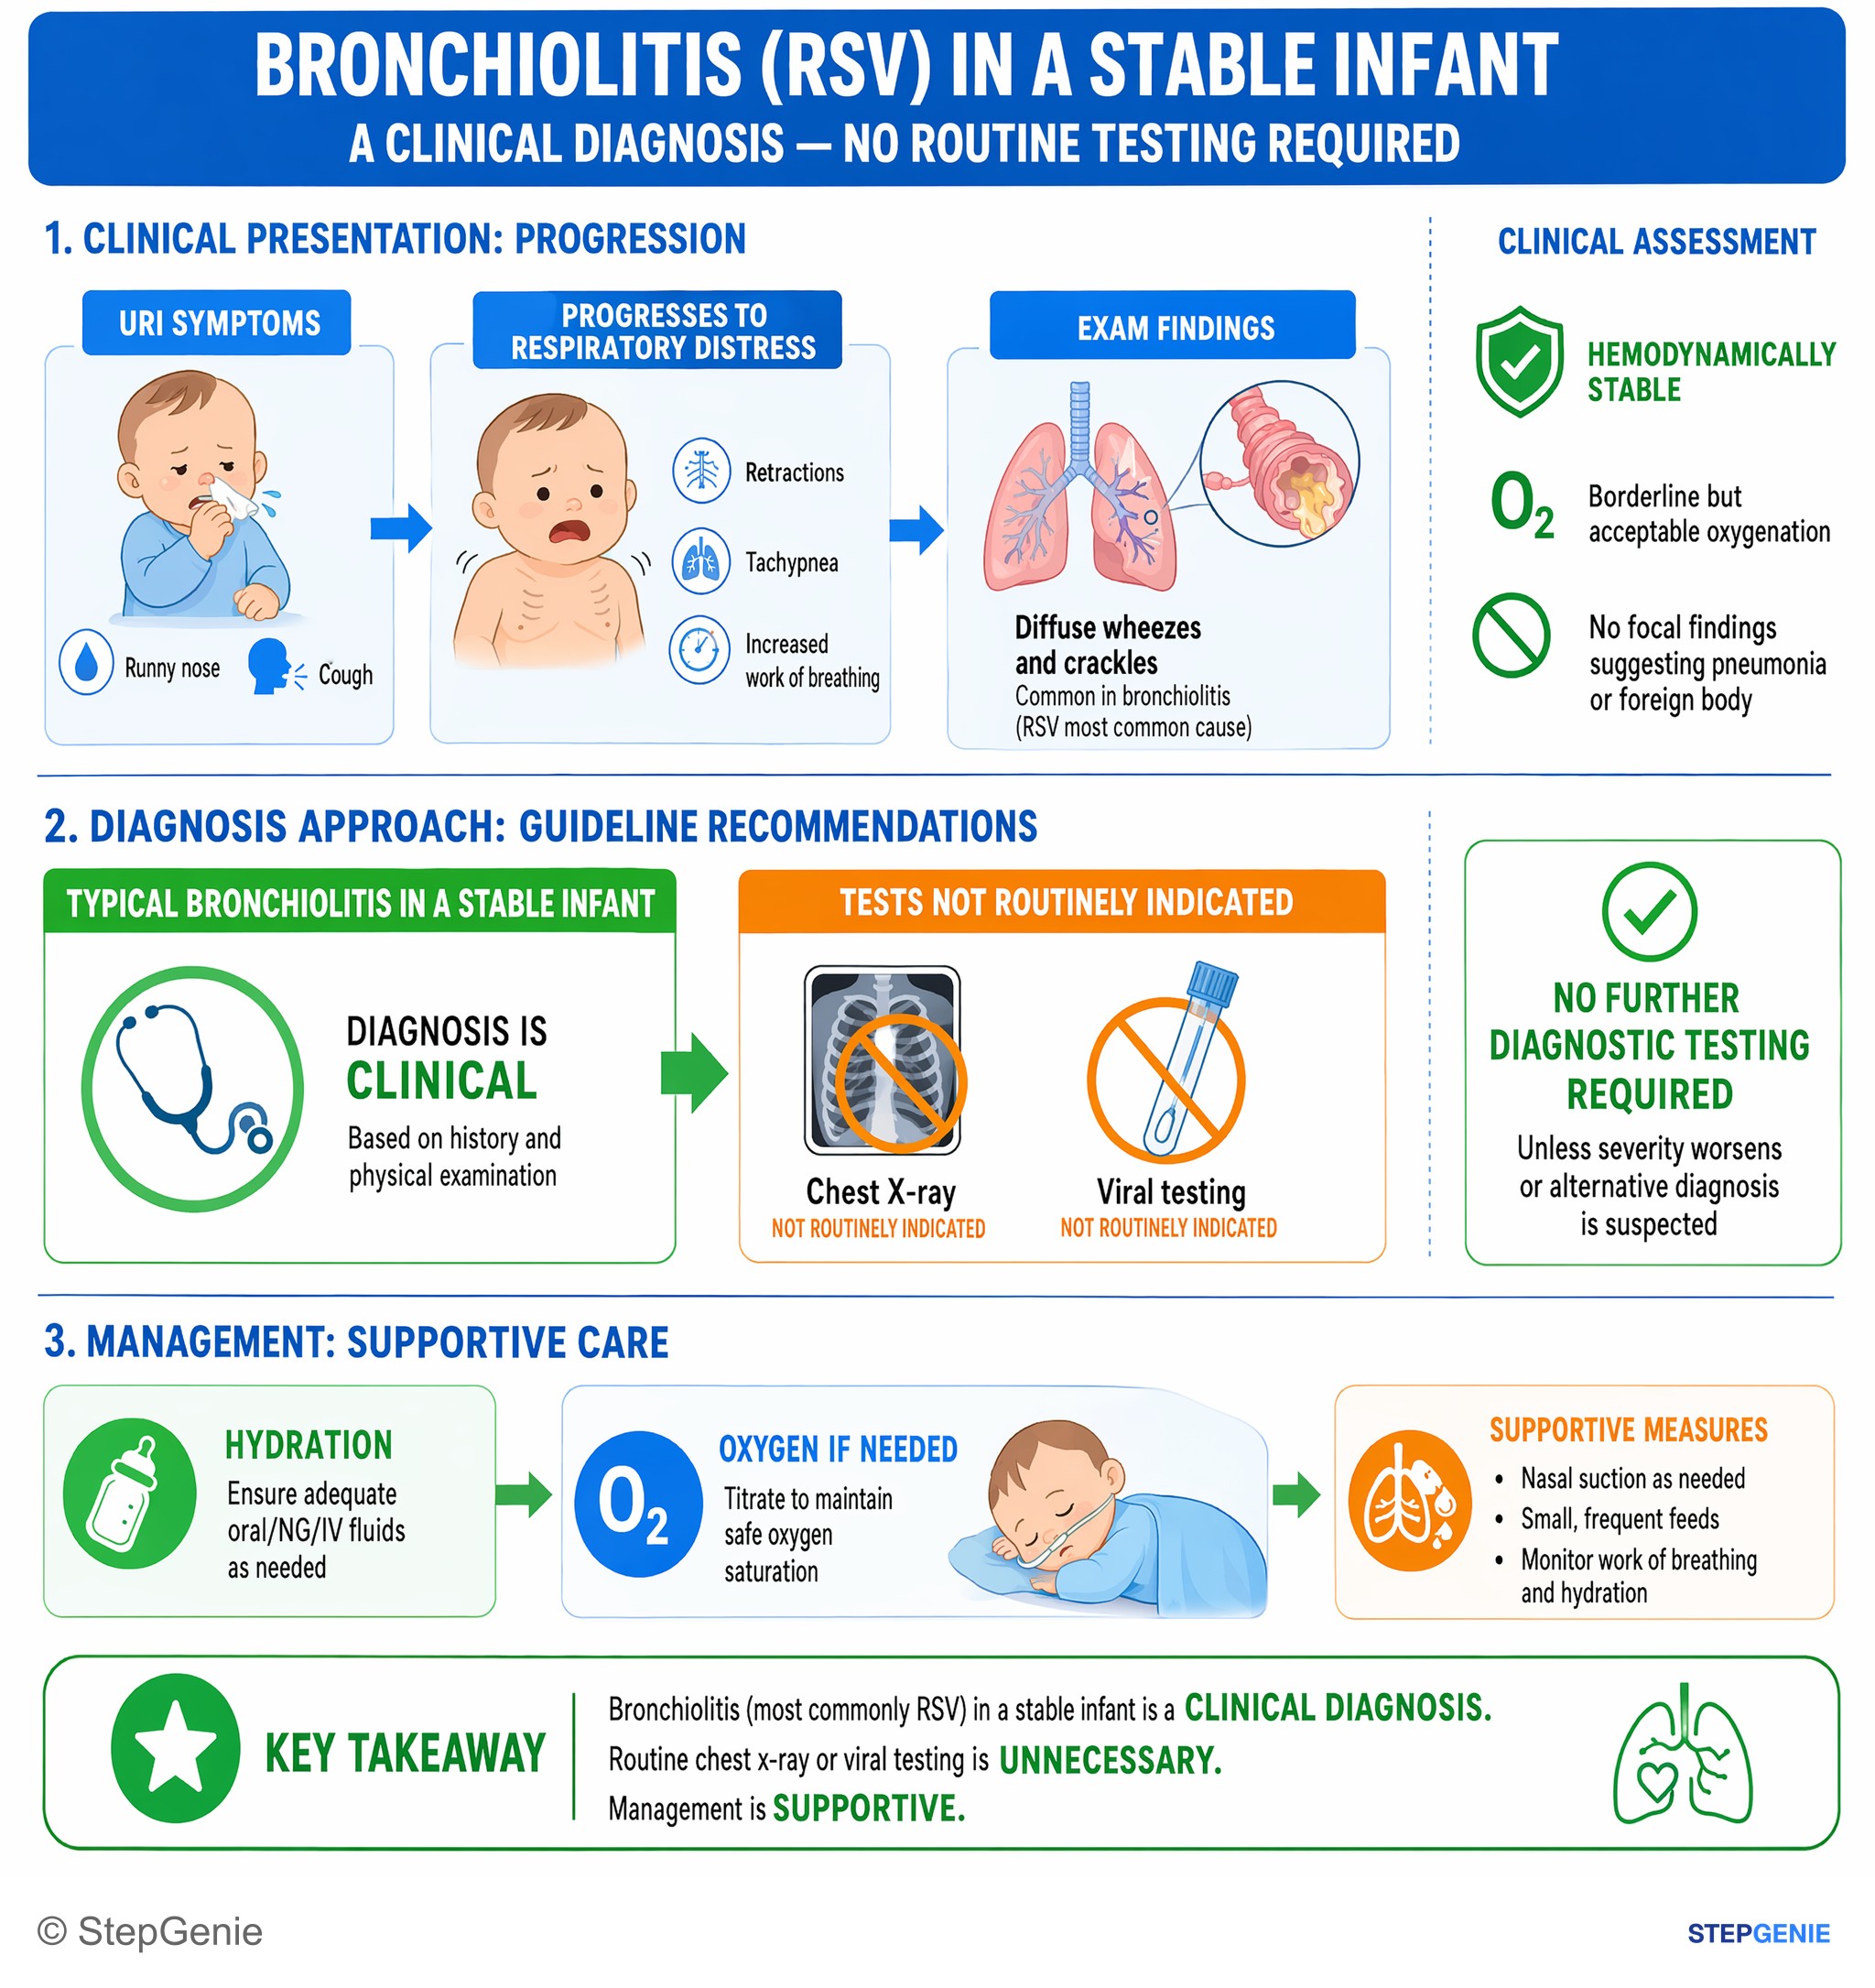
Bronchiolitis (RSV) in a stable infant is a clinical diagnosis; routine imaging or viral testing is unnecessary unless severity or…
USMLE Step 2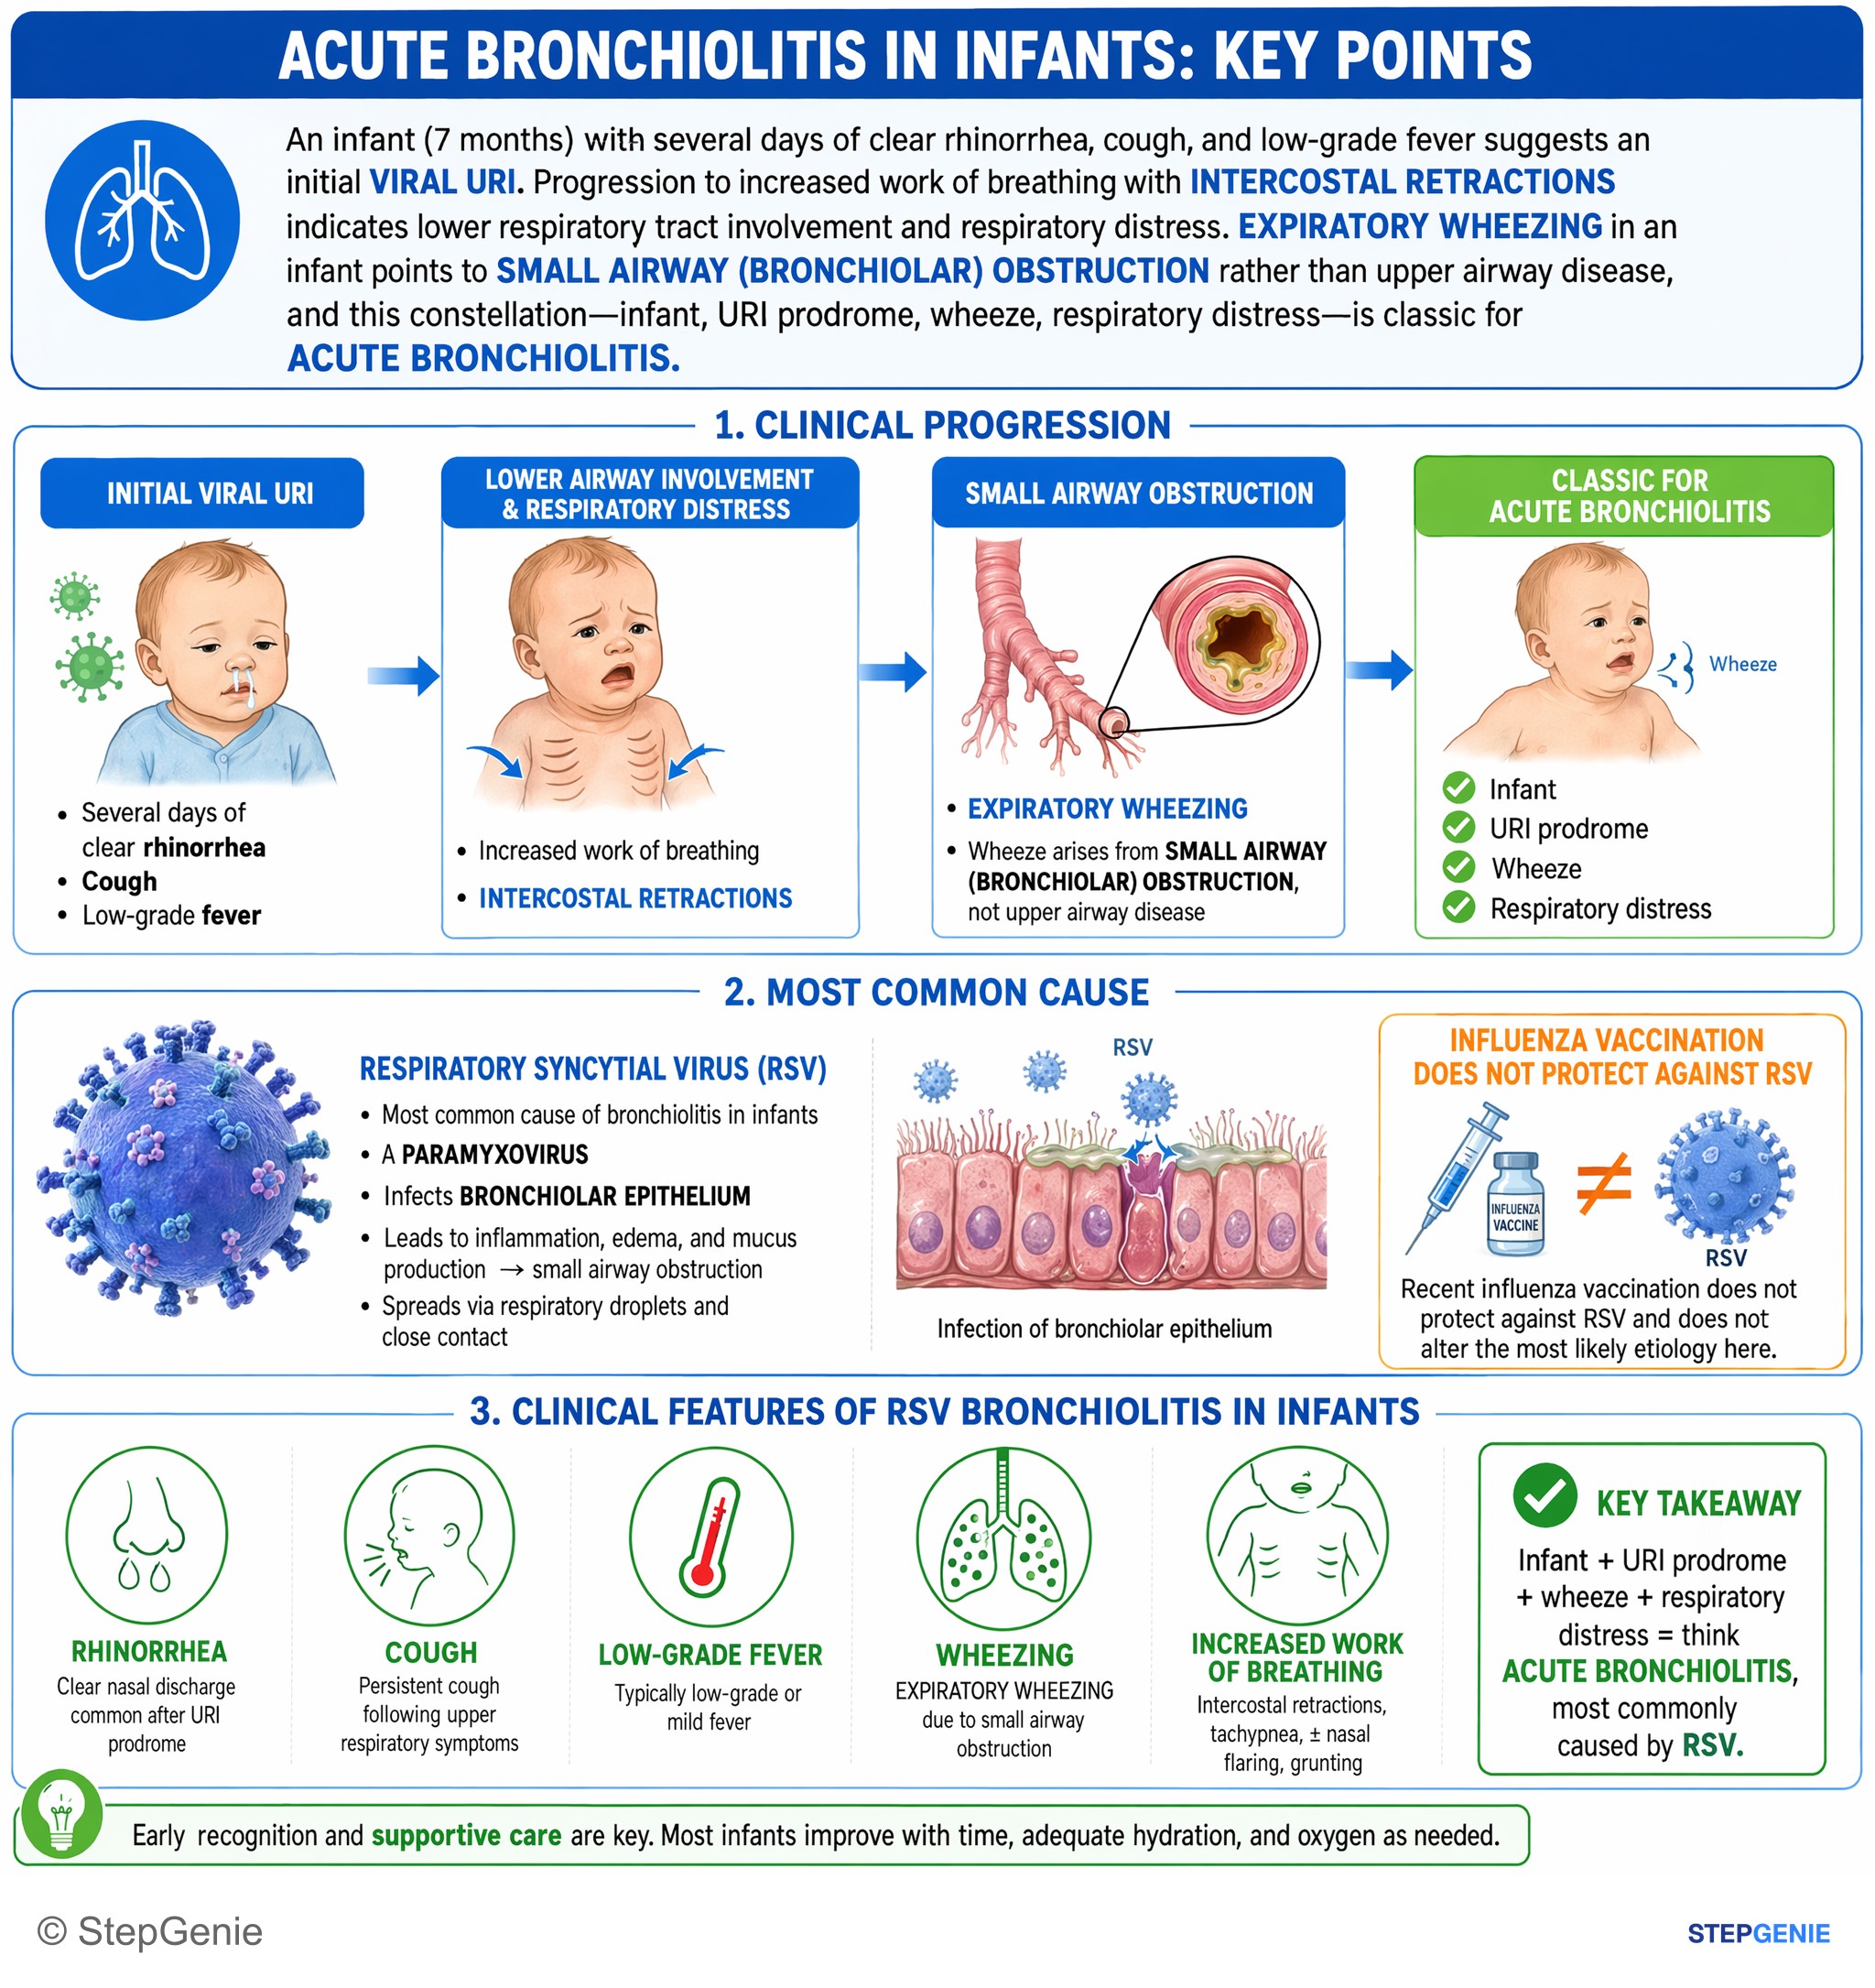
RSV bronchiolitis in infants causes rhinorrhea, cough, low-grade fever, wheezing, and increased work of breathing following an upper…
USMLE Step 1Frequently Asked Questions
Why is RSV the best answer for a wheezing infant in winter with crackles and hyperinflation?
RSV is the best answer because it is the most common cause of bronchiolitis and pneumonia in infants and matches the classic bronchiolitis pattern. The key clues are age under 2 years, especially under 6 months, winter season, an upper respiratory prodrome followed by lower respiratory symptoms, wheezing with crackles, hyperinflation on chest imaging, hypoxemia, and increased work of breathing.
How do you tell RSV bronchiolitis from influenza in a USMLE-style vignette?
RSV bronchiolitis is favored when a young infant has wheezing, crackles, and hyperinflation rather than a toxic systemic illness. Influenza usually presents with abrupt high fever, myalgias, headache, and a "hit by a truck" feeling, with fever being prominent. In contrast, RSV classically causes bronchiolitis in infants and is associated with syncytia formation through its F protein.
How do you distinguish RSV from parainfluenza on exam questions?
RSV causes lower airway bronchiolar disease, while parainfluenza classically causes croup with upper airway obstruction. RSV points include wheezing, crackles, hypoxemia, and hyperinflation in an infant. Parainfluenza is suggested by barking cough, inspiratory stridor, hoarseness, and sometimes a steeple sign showing subglottic narrowing, which fit croup rather than bronchiolitis.
What is the mechanism behind wheezing and hyperinflation in RSV bronchiolitis?
RSV causes wheezing and hyperinflation by infecting the bronchiolar epithelium and triggering inflammation. This leads to necrosis, sloughed cells, and mucus plugging, which trap air in the small airways. Because infant bronchioles are tiny, this air trapping produces the bronchiolitis picture of wheezing, crackles, increased work of breathing, and hyperinflation on chest imaging.
What are the high-yield diagnosis, treatment, and prevention facts for RSV?
RSV is often diagnosed clinically, though PCR panels are commonly used in real practice. Treatment is supportive, including oxygen, hydration, and suctioning. Prevention for high-risk infants is palivizumab, a monoclonal antibody against the RSV F protein. High-risk groups highlighted include infants with prematurity, chronic lung disease, or significant congenital heart disease.