A great microbiology Q-bank question doesn’t just test whether you “know rabies”—it tests whether you can separate rabies from other neurotropic viruses and encephalitides when the vignette is trying to trick you. The fastest way to level up is to treat every answer choice like it’s trying to teach you something.
Tag: Microbiology > Virology
The Clinical Vignette (USMLE-Style)
A 28-year-old man comes to the ED with fever, malaise, anxiety, and difficulty swallowing. He has episodes of involuntary inspiratory spasms when offered water and becomes extremely agitated. Two weeks ago, he was bitten on the hand by a stray dog while traveling. He did not seek medical care. Physical exam shows hypersalivation and intermittent confusion. CSF shows a mild lymphocytic pleocytosis.
Question: Which of the following best explains the pathogenesis of his illness?
Correct Answer: Rabies virus — Retrograde axonal transport to CNS (Negri bodies)
Why it’s correct
This vignette is classic for rabies encephalitis, especially:
- Hydrophobia (painful pharyngeal spasms triggered by swallowing water)
- Hypersalivation
- Agitation / autonomic instability
- History of animal bite (dog in many global settings; bats in the US are key too)
- Incubation that can be weeks to months (shorter when bite is closer to CNS, e.g., face; longer for distal extremities)
Core pathogenesis (Step 1 + Step 2 high-yield)
- Virus: Rabies (Rhabdoviridae)
- Genome: (-)ssRNA, enveloped
- Shape: Bullet-shaped
- Entry & spread:
- Replicates locally in muscle
- Binds nicotinic acetylcholine receptors at the neuromuscular junction
- Travels via retrograde axonal transport up peripheral nerves to the CNS
- Disseminates centrifugally to tissues (e.g., salivary glands) → transmission
Classic histology/diagnostics
- Negri bodies: eosinophilic cytoplasmic inclusions in neurons (especially hippocampus, Purkinje cells)
- Diagnosis (practical boards angle):
- Direct fluorescent antibody testing on skin biopsy (nuchal skin), corneal impression, saliva/CSF PCR in some settings
- But clinically: once symptomatic, diagnosis is often confirmed while prognosis is discussed
The “don’t miss” management pearl
- Once symptomatic, rabies is nearly universally fatal.
- Post-exposure prophylaxis (PEP) prevents disease if given before symptoms:
- Rabies immune globulin (RIG) infiltrated around wound + remainder IM
- Rabies vaccine series (days 0, 3, 7, 14; immunocompromised get an extra dose)
- If previously vaccinated: no RIG, vaccine boosters only
Distractor Breakdown: Why Every Wrong Choice Is Wrong (and What It’s Really Describing)
Below are common “trap” answer choices you’ll see paired with rabies vignettes—each is a real disease mechanism, just not this one.
Distractor 1: HSV-1 encephalitis — Temporal lobe hemorrhagic necrosis
Why it’s tempting: HSV is a common cause of encephalitis with fever and altered mental status.
Why it’s wrong here:
- HSV-1 encephalitis classically features:
- Personality changes, confusion
- Seizures
- Focal neurologic deficits
- Rabies has the signature hydrophobia + aerophobia (air-triggered spasms) + hypersalivation and a bite exposure.
High-yield HSV-1 facts
- DNA virus, enveloped
- Temporal lobe involvement → memory, behavior, aphasia
- CSF: lymphocytes, ↑RBCs (hemorrhagic)
- Treat: acyclovir
Distractor 2: Poliovirus — Destruction of anterior horn cells (flaccid paralysis)
Why it’s tempting: Neurotropic virus affecting motor neurons.
Why it’s wrong here:
- Poliomyelitis causes asymmetric flaccid paralysis with decreased reflexes, not hydrophobia/spasms.
- Transmission is fecal–oral, not via animal bite.
- Rabies often produces encephalitic behavior changes and autonomic findings early.
High-yield polio facts
- (+)ssRNA, nonenveloped (Picornavirus)
- Can cause aseptic meningitis or paralytic polio
- Vaccine detail: IPV (Salk) is inactivated; OPV (Sabin) is live-attenuated and can rarely revert
Distractor 3: Tetanus toxin — Blocks inhibitory neurotransmitters (spastic paralysis)
Why it’s tempting: Spasms + a “wound” history might make you think tetanus.
Why it’s wrong here:
- Tetanus is bacterial (Clostridium tetani), not viral.
- Tetanus causes:
- Trismus (lockjaw)
- Risus sardonicus
- Opisthotonos
- Rabies causes painful swallowing triggers (hydrophobia) and encephalitis features (agitation, delirium).
High-yield tetanus facts
- Tetanospasmin cleaves SNARE → ↓GABA/glycine release
- Treat: wound care + metronidazole, TIG, and vaccination
Distractor 4: Guillain–Barré syndrome — Demyelination with ascending weakness
Why it’s tempting: Post-infectious neuro problem; sometimes shows up near “viral” questions.
Why it’s wrong here:
- GBS presents with:
- Ascending weakness
- Areflexia
- Often after Campylobacter, CMV, EBV, etc.
- It does not cause hydrophobia, pharyngeal spasms triggered by water, or hypersalivation.
High-yield GBS facts
- CSF: albuminocytologic dissociation (↑protein, normal WBC)
- Treat: IVIG or plasmapheresis
Distractor 5: West Nile virus — Flaccid paralysis + meningitis/encephalitis after mosquito exposure
Why it’s tempting: Another viral encephalitis that can cause weakness.
Why it’s wrong here:
- West Nile is associated with:
- Mosquito exposure
- Older adults with encephalitis
- Can cause acute flaccid paralysis (anterior horn involvement)
- The vignette’s standout clues—dog bite, hydrophobia, hypersalivation—scream rabies.
High-yield West Nile facts
- (+)ssRNA, enveloped (Flavivirus)
- Think: summer/fall, outdoors, mosquito-borne
- Supportive care (no specific antiviral routinely used)
Rapid Side-by-Side: Rabies vs Key Look-Alikes
| Condition | Exposure clue | Key clinical hallmark | Pathogenesis/Location | Treatment |
|---|---|---|---|---|
| Rabies | Animal bite (dog/bat/raccoon) | Hydrophobia, hypersalivation, agitation | Retrograde axonal transport; Negri bodies | PEP (vaccine + RIG) before symptoms |
| HSV-1 encephalitis | Reactivation; not bite-related | Temporal lobe signs, seizures | Hemorrhagic temporal lobe necrosis | Acyclovir |
| Polio | Fecal–oral | Asymmetric flaccid paralysis | Anterior horn cells | Supportive; prevention via vaccine |
| Tetanus | Contaminated wound | Trismus, opisthotonos | Blocks GABA/glycine release | TIG + antibiotics + vaccine |
| West Nile | Mosquito | Encephalitis ± flaccid paralysis | Neuroinvasive disease | Supportive |
USMLE High-Yield Rabies Checklist
Virology essentials
- Rhabdoviridae, bullet-shaped
- Enveloped (-)ssRNA
- Replicates in cytoplasm
- Negri bodies in neurons
Clinical essentials
- Incubation: weeks to months
- Symptoms: fever → agitation, hydrophobia, autonomic instability → coma
- Fatal once symptomatic (boards love this line)
Prevention & PEP essentials
- Immediate wound cleaning is not “fluff”—it’s testable:
- Irrigate thoroughly (soap/water; virucidal agents if available)
- RIG + vaccine unless previously vaccinated
- Don’t forget the US nuance:
- In the US, many cases come from bats; “no known bite” can still count if exposure is plausible (sleeping in a room with a bat, etc.)
How to Answer the Next Rabies Question in 10 Seconds
When you see:
- Animal bite + agitation + hydrophobia/hypersalivation
Your brain should immediately autocomplete:
- Rabies
- Retrograde axonal transport
- Negri bodies
- PEP prevents it; symptoms = near-certain death
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
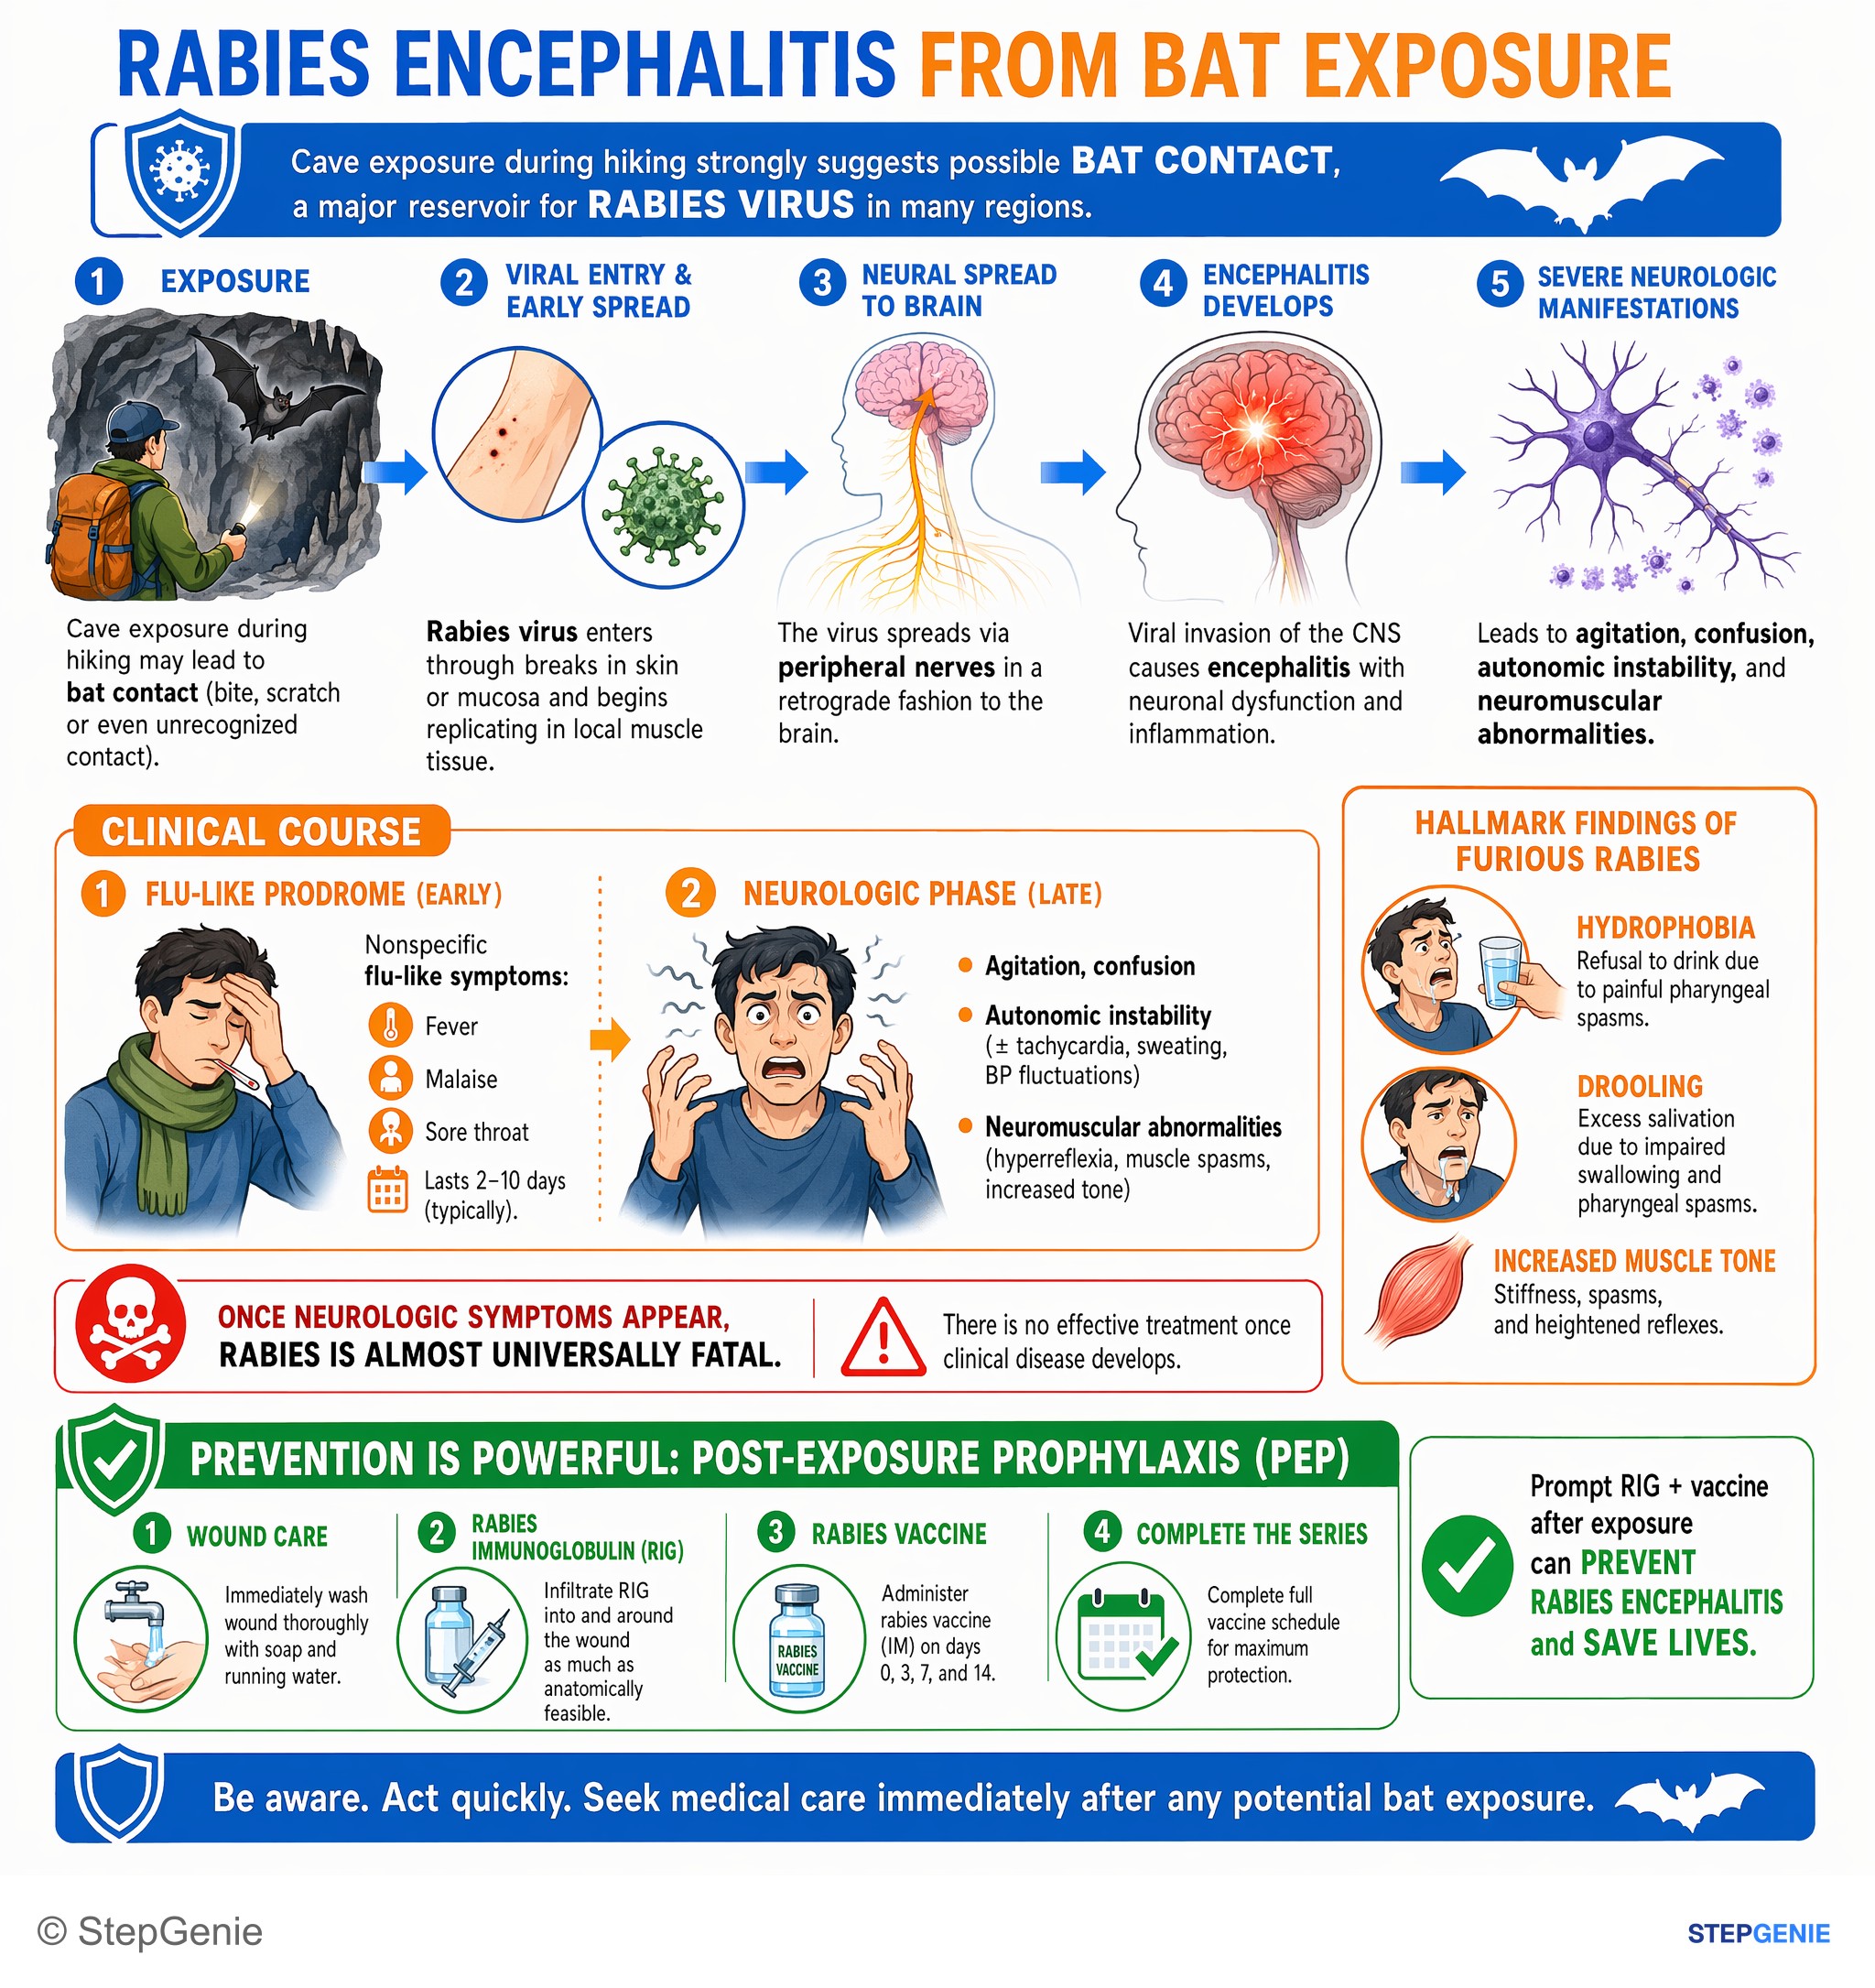
Rabies encephalitis from bat exposure causes hydrophobia, agitation, autonomic dysfunction; prevented by prompt rabies immunoglobulin plus…
USMLE Step 2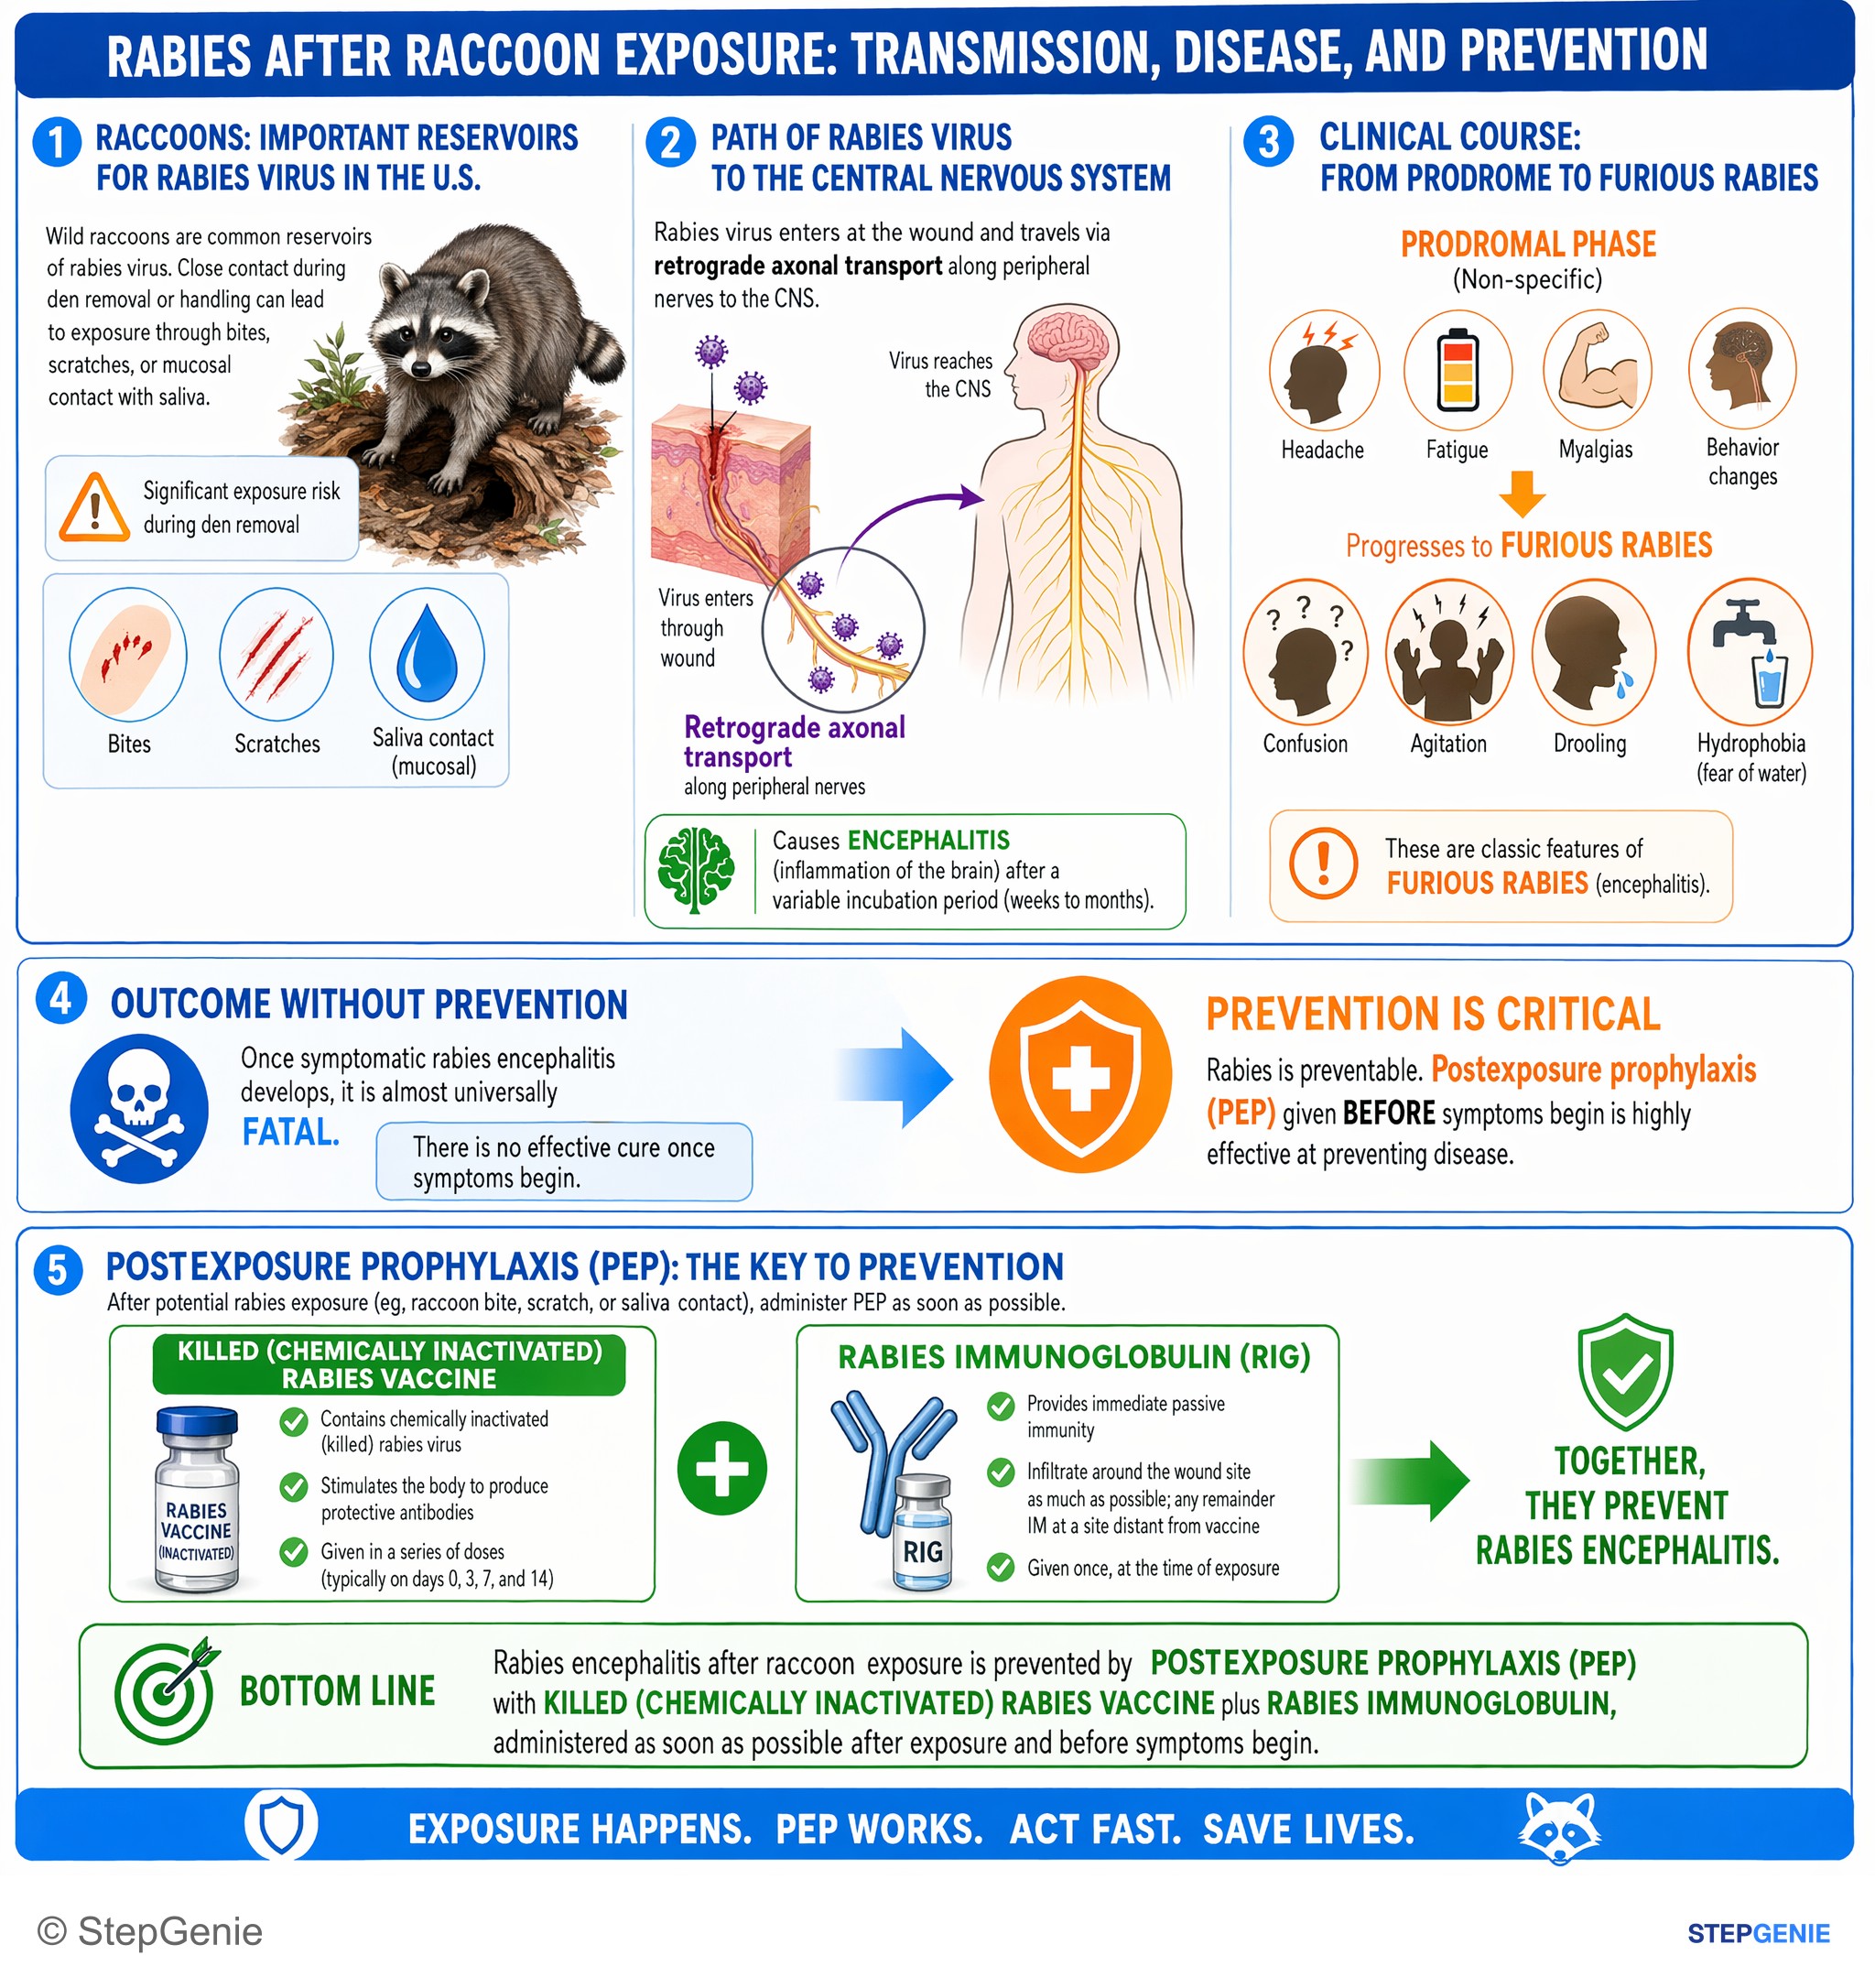
Rabies encephalitis after raccoon exposure is prevented by postexposure prophylaxis with killed (chemically inactivated) rabies vaccine…
USMLE Step 2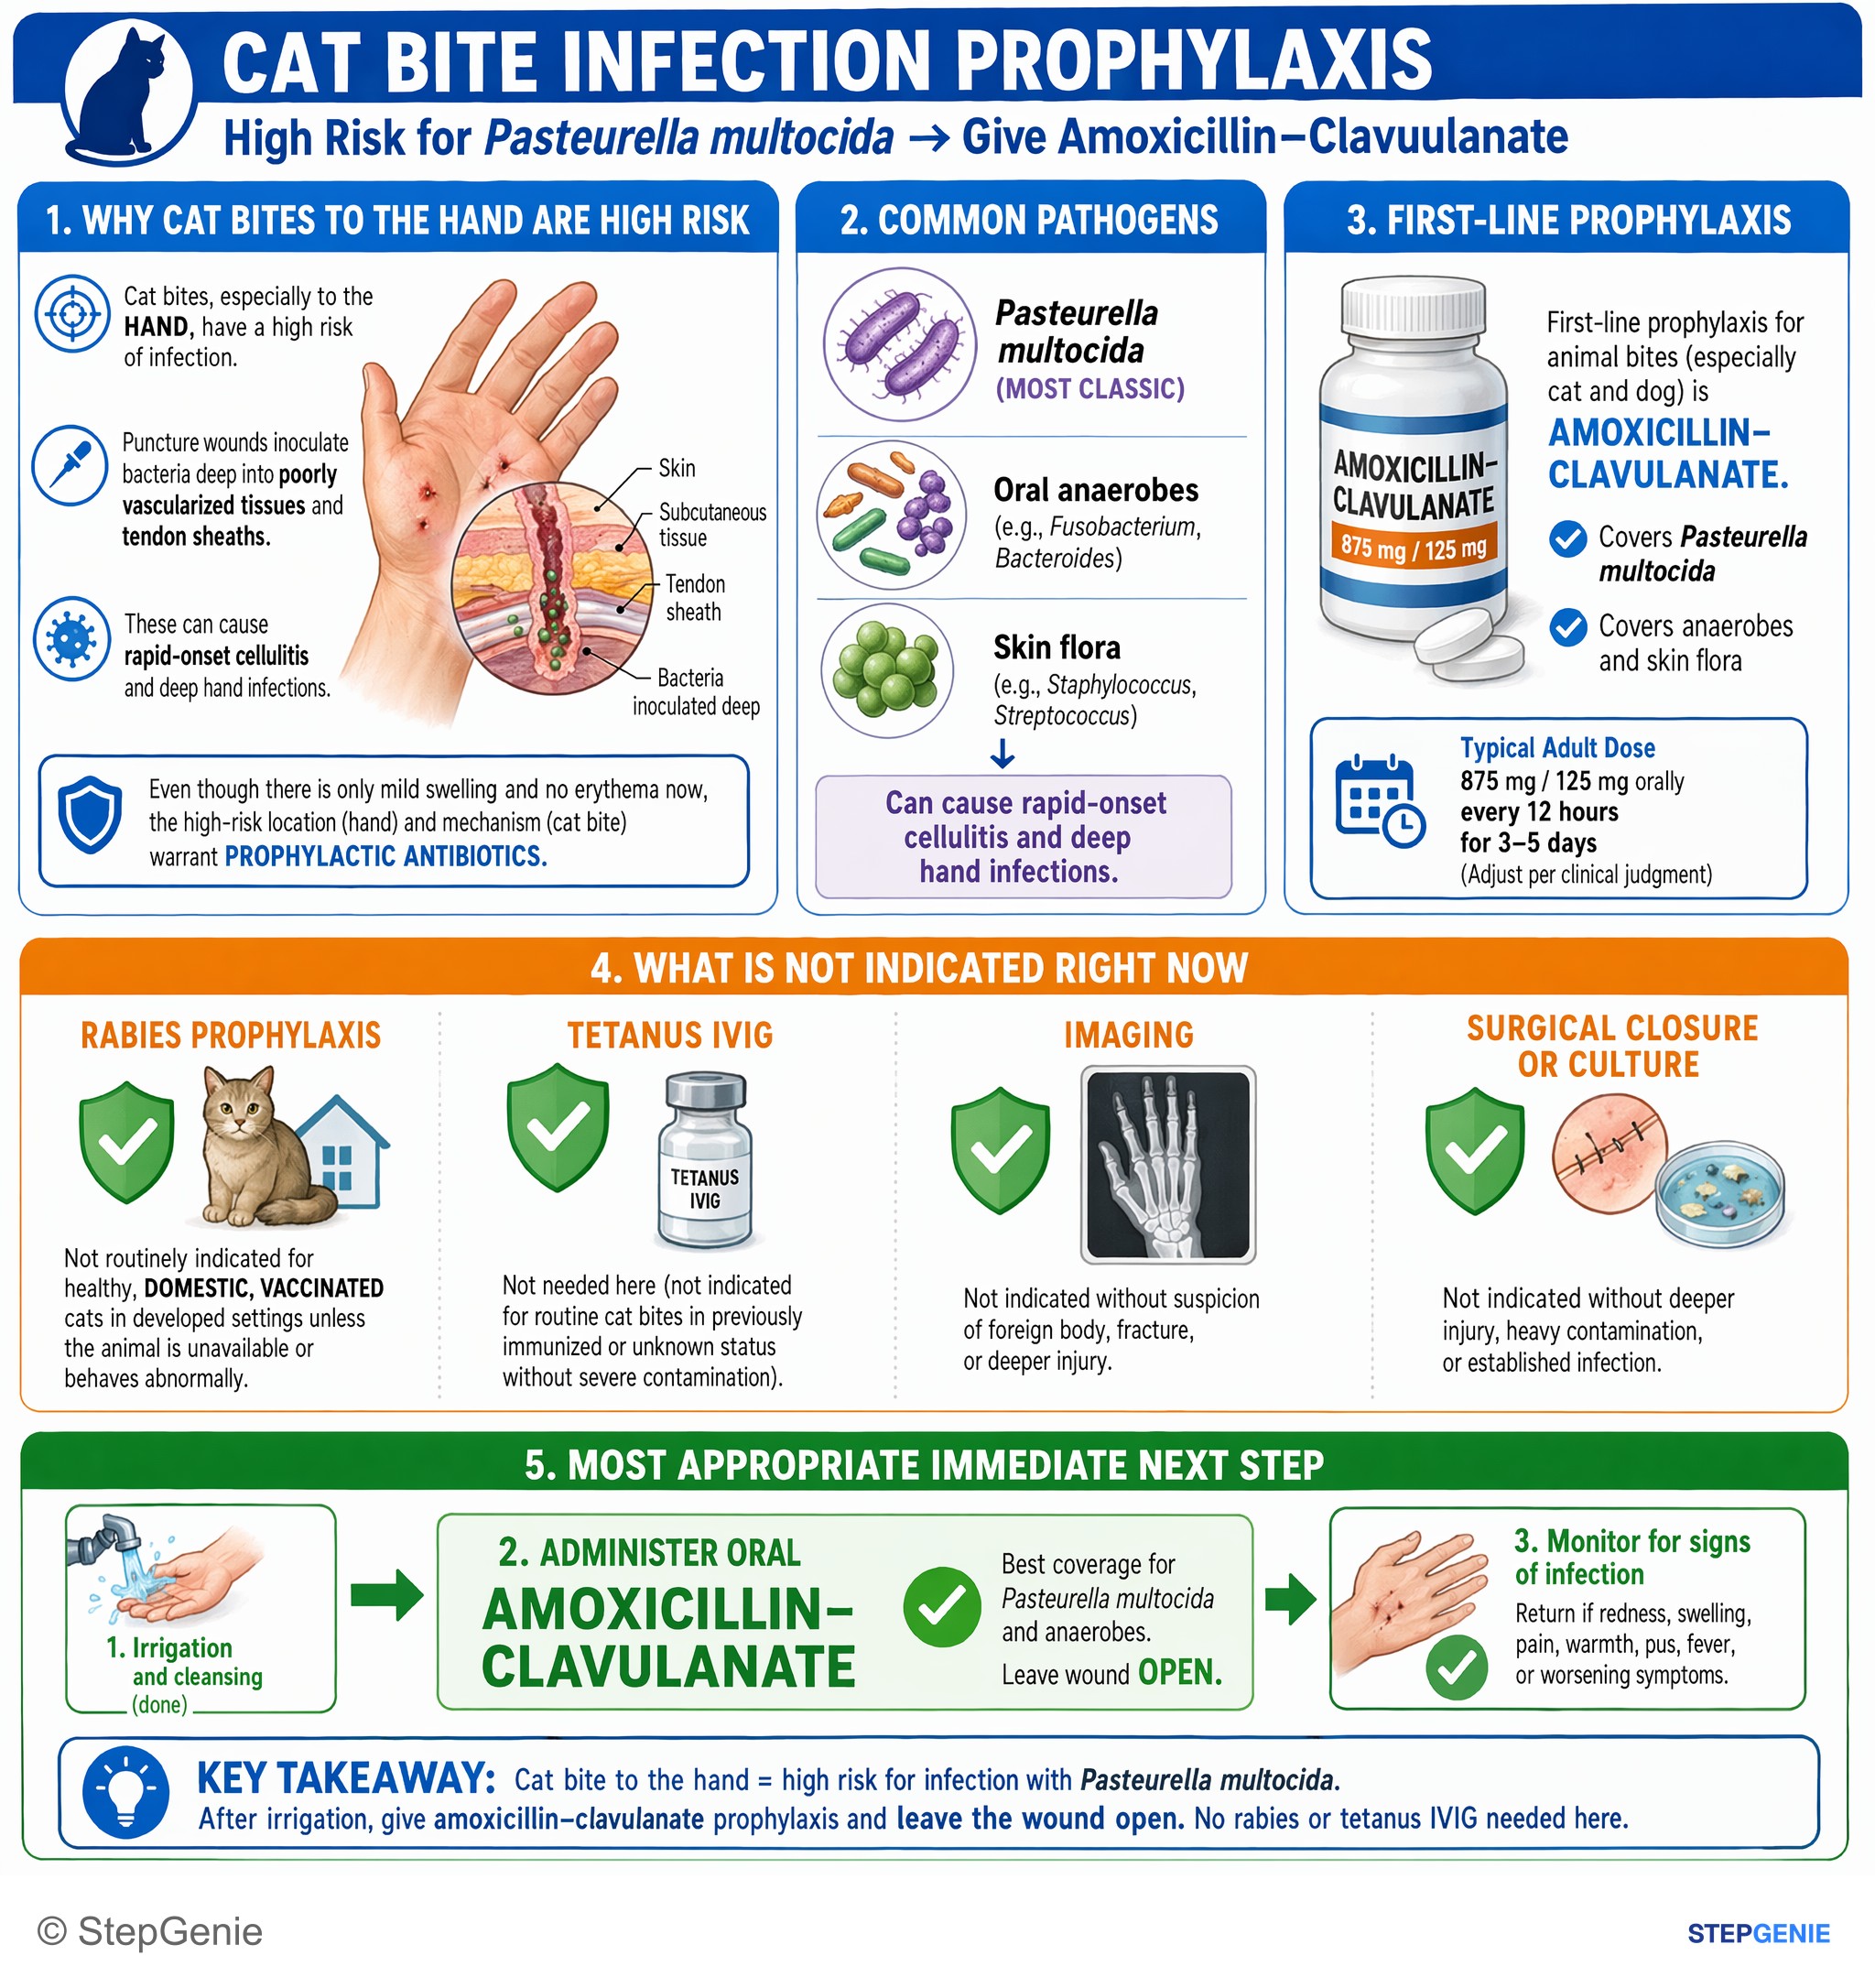
Cat bite infection prophylaxis: high risk for Pasteurella multocida → give amoxicillin-clavulanate and leave wound open; no rabies or…
USMLE Step 2Frequently Asked Questions
Why does rabies cause hydrophobia and painful spasms when trying to drink water?
Rabies causes hydrophobia because it produces painful pharyngeal spasms triggered by swallowing, which makes water intake provoke involuntary inspiratory spasms and agitation. In a classic presentation, these spasms occur along with hypersalivation, anxiety, confusion, and autonomic instability after an animal bite, reflecting rabies encephalitis rather than a simple local wound problem.
How does rabies get from an animal bite to the brain?
Rabies reaches the brain by retrograde axonal transport after first replicating locally in muscle. The virus binds nicotinic acetylcholine receptors at the neuromuscular junction, then travels up peripheral nerves to the CNS. It later disseminates centrifugally to tissues such as the salivary glands, which helps explain how infected saliva transmits the virus.
How do you tell rabies encephalitis from HSV-1 encephalitis on a vignette?
Rabies is suggested by an animal bite plus hydrophobia, hypersalivation, agitation, and air- or water-triggered spasms, whereas HSV-1 encephalitis classically causes fever, altered mental status, personality changes, seizures, and focal neurologic deficits. HSV-1 is associated with temporal lobe hemorrhagic necrosis and can show lymphocytes with increased RBCs in the CSF, while rabies has the distinctive bite exposure and hydrophobia clues.
What are the classic pathology and diagnostic clues for rabies?
The classic pathology clue in rabies is Negri bodies, which are eosinophilic cytoplasmic inclusions in neurons, especially in the hippocampus and Purkinje cells. Practical diagnostic approaches include direct fluorescent antibody testing on nuchal skin biopsy or corneal impression, and PCR testing of saliva or CSF in some settings. Clinically, diagnosis is often confirmed after symptoms appear while prognosis is being discussed.
What is the key treatment pearl for rabies exposure?
The key management pearl is that post-exposure prophylaxis can prevent rabies if given before symptoms, but once symptomatic, rabies is nearly universally fatal. Recommended prophylaxis is rabies immune globulin infiltrated around the wound with the remainder given intramuscularly, plus a rabies vaccine series. If the patient was previously vaccinated, rabies immune globulin is not given and only vaccine boosters are needed.