Adenovirus is a nonenveloped, icosahedral, linear double-stranded DNA virus, and its signature USMLE presentation is pharyngoconjunctival fever: fever, sore throat and red, watery eyes, often in a school, camp or swimming-pool outbreak. It also causes epidemic keratoconjunctivitis, pneumonia (classically in military recruits, who get a live oral vaccine against types 4 and 7), hemorrhagic cystitis, gastroenteritis (types 40 and 41) and severe, disseminated disease in transplant recipients, and it is linked to intussusception. Care is supportive: no antiviral is FDA-approved, but cidofovir is used off-label for severe disease in immunocompromised patients. Because it has no envelope it resists many disinfectants, and alcohol is unreliable against it.
The Q-bank vignette
A 6-year-old boy is brought to the clinic with 4 days of fever, sore throat, runny nose and red, watery eyes. Several classmates have had the same illness. His temperature is 39°C (102.2°F). He has pharyngeal erythema with exudates, tender anterior cervical lymph nodes and bilateral conjunctival injection without purulent discharge. A rapid streptococcal antigen test is negative.
Which virus is the most likely cause?
- A. Adenovirus
- B. Coxsackievirus A
- C. Epstein-Barr virus
- D. Herpes simplex virus type 1
- E. Influenza virus
- F. Parainfluenza virus
- G. Respiratory syncytial virus
- H. Rhinovirus
Answer: A. Adenovirus.
Why it's adenovirus
- The triad: fever + pharyngitis + conjunctivitis is pharyngoconjunctival fever, classically caused by types 3, 4 and 7 (Merck).
- The setting: it mostly affects children and spreads in schools, daycare and summer camps, notably where pools or lakes are inadequately chlorinated. Adenovirus spreads by droplets, close contact, contaminated objects, stool and water.
- The exudate is the trap: adenovirus causes exudative pharyngitis that mimics strep throat and mono. Conjunctivitis and a runny nose point to a virus, and the rapid strep test is negative. Strep throat itself is covered in the S. pyogenes 5-second rule.
- A hardy virus: with no envelope, it survives on surfaces, which fuels outbreaks.
Why every other answer choice is wrong
| Choice | Genome | Pick it when the stem shows | Why not here |
|---|---|---|---|
| B. Coxsackievirus A | Nonenveloped (+)ssRNA (enterovirus) | Herpangina (vesicles on the soft palate and posterior pharynx) or hand-foot-and-mouth disease, in summer and fall | No vesicles, ulcers or rash |
| C. Epstein-Barr virus | Enveloped dsDNA (herpesvirus) | Teen or young adult with exudative pharyngitis, posterior cervical nodes, splenomegaly and fatigue; positive heterophile (Monospot) test; rash after amoxicillin | Conjunctivitis isn't a classic mono feature; no posterior nodes or splenomegaly; a school outbreak doesn't fit |
| D. Herpes simplex virus type 1 | Enveloped dsDNA (herpesvirus) | Gingivostomatitis: painful vesicles and ulcers on the gums, lips and tongue, drooling, refusal to eat | No vesicles; conjunctivitis plus exudative pharyngitis isn't the classic HSV picture |
| E. Influenza virus | Enveloped, segmented (−)ssRNA | Abrupt fever, myalgias, headache and dry cough in a winter epidemic | Conjunctivitis with exudative pharyngitis favors adenovirus; no prominent myalgias |
| F. Parainfluenza virus | Enveloped (−)ssRNA (paramyxovirus) | Croup: barking cough, inspiratory stridor, steeple sign, age 6 months to 3 years | No barking cough or stridor |
| G. Respiratory syncytial virus | Enveloped (−)ssRNA | Bronchiolitis in infants: wheeze, tachypnea, retractions; its F protein forms syncytia | Wrong age and wrong syndrome |
| H. Rhinovirus | Nonenveloped (+)ssRNA (picornavirus) | Mild, usually afebrile common cold; binds ICAM-1; grows best in the cool nose | High fever, exudates and conjunctivitis aren't rhinovirus |
Influenza's segmented genome and antigenic shift are on the influenza cheat sheet, EBV and HSV are compared in the herpesvirus guide, and bronchiolitis is broken down in the RSV question.
Adenovirus at a glance
| Feature | Fact | Why it matters |
|---|---|---|
| Genome | Linear dsDNA, like herpesviruses and poxviruses | Papilloma-, polyoma- and hepadnaviruses are the circular DNA viruses |
| Capsid | Nonenveloped icosahedron with fiber projections from its 12 vertices | Stable in the environment |
| Diversity | 7 species (A-G) and more than 100 genotypes | Specific types map to specific syndromes |
| Spread | Droplets, close contact, objects such as towels and eye instruments, stool (diaper changes), poorly chlorinated pools and lakes | Outbreaks in schools, camps, barracks and eye clinics |
| Season | Any time of year | No winter-only pattern |
| Persistence | Can shed for weeks or longer; latent infection of lymphoid tissue | Prolonged outbreaks; danger in immunosuppression |
| Disinfection | Resists many common disinfectants; alcohol is unreliable; stays infectious on surfaces for hours | Use disinfectants that work against norovirus (EPA List G) |
Syndromes by type
| Syndrome | Classic types | Who and where | Key clues |
|---|---|---|---|
| Pharyngoconjunctival fever | 3, 4, 7 | Children; schools, camps, pools | Fever, exudative pharyngitis, nonpurulent conjunctivitis, tender neck nodes |
| Epidemic keratoconjunctivitis (EKC) | 8, 19, 37 (also 53, 54) | Any age; eye clinics | Gritty, watery, red, light-sensitive eyes; corneal subepithelial infiltrates that can last months; spread by tonometers, slit lamps, eye drops and hands |
| Acute respiratory disease and pneumonia | 4, 7 (also 14) | Military recruits and other crowded settings | Febrile respiratory outbreaks; types 4 and 7 are prevented by the oral vaccine |
| Infant pneumonia, pertussis-like illness | Various | Infants and young children | Pneumonia is more severe in infants; paroxysmal cough |
| Gastroenteritis | 40, 41 | Infants and toddlers in daycare | Fever and watery diarrhea for 1-2 weeks; compare rotavirus and norovirus |
| Intussusception (association) | Non-enteric types | Infants and toddlers | Enlarged Peyer patches are the classic proposed lead point, but whether they cause it or result from it is unclear; colicky pain, vomiting, currant-jelly stool |
| Acute hemorrhagic cystitis | 11 and other species B types | Children 5-15 years; transplant recipients | Gross hematuria and dysuria; self-limited (about 3 days) in healthy children |
| Disseminated disease | Many | Stem cell and solid-organ transplant recipients | Pneumonitis, hepatitis, nephritis, colitis, encephalitis; high mortality |
Adenovirus is often found in children with intussusception; the full workup is in the intussusception breakdown.
Adenovirus in transplant recipients
- Highest risk: allogeneic hematopoietic stem cell transplant (HSCT), especially with T-cell depletion (for example, alemtuzumab), lymphopenia, graft-versus-host disease or young age. In solid-organ recipients, the transplanted organ itself can be infected.
- What it causes: pneumonitis, hepatitis and liver failure, hemorrhagic cystitis and nephritis, gastroenteritis and disseminated disease, mostly early after HSCT, before engraftment. Disseminated adenovirus carries a high mortality.
- Hematuria after HSCT: think of three causes: cyclophosphamide (its metabolite acrolein; mesna prevents it), BK polyomavirus and adenovirus.
Diagnosis and treatment
- Diagnosis: usually clinical in healthy children. PCR (often on multiplex respiratory panels) or antigen detection confirms it when it matters, as in outbreaks or immunocompromised patients (CDC).
- Treatment: supportive; there is no FDA-approved antiviral for adenovirus (CDC).
- Severe disease in immunocompromised patients: no antiviral is proven effective, but Merck notes that cidofovir (off-label) may offer the highest likelihood of antiviral effect. Recovery of T-cell immunity appears vital to clearing severe infection, and some centers add IVIG or donor-derived, virus-specific T cells (Medscape).
- Cidofovir pearls: a nucleotide analog that does not need a viral kinase to be activated. Its boxed warnings include nephrotoxicity (so every dose is given with IV saline prehydration and probenecid) and neutropenia. Its only labeled use is CMV retinitis in AIDS.
Prevention and infection control
- Vaccine: a live oral vaccine against types 4 and 7, given as two enteric-coated tablets swallowed whole, so the virus is not released in the upper airway. It is licensed only for military populations aged 17-50. It is not given in pregnancy (women should avoid pregnancy for 6 weeks afterward), and vaccine virus is shed in stool, with none detected by 28 days after vaccination. There is no adenovirus vaccine for the general public.
- Eye clinics: hand hygiene, gloves and disinfection of instruments after every use. CDC warns that 70% isopropyl alcohol should not be relied on for ophthalmic instruments, because it has been linked to EKC outbreaks; staff with EKC should stay off work.
- Everyday control: hand hygiene, cleaning with disinfectants that are effective against norovirus, and adequate chlorination of pools.
How USMLE tests adenovirus
- Pink eye + sore throat + fever, with an outbreak or a pool = adenovirus.
- Nonenveloped = tough: fecal-oral and fomite spread; resists many disinfectants (alcohol is unreliable) and survives for hours on surfaces.
- Linear dsDNA, like herpes- and poxviruses.
- Military recruits with febrile respiratory illness = types 4 and 7, prevented by a live oral, enteric-coated vaccine.
- Hemorrhagic cystitis: adenovirus in a child; in an HSCT recipient, also consider BK virus and cyclophosphamide.
- Intussusception after a viral illness: adenovirus is the classic association, with Peyer patch hyperplasia as the proposed lead point (exam framing; cause versus effect is unproven).
- Cidofovir = nephrotoxicity, so give probenecid and saline.
Key takeaways
- Adenovirus: nonenveloped, icosahedral, linear dsDNA; spreads by droplets, hands, fomites, stool and water, any time of year.
- Pharyngoconjunctival fever (types 3, 4, 7) is the classic stem: fever, exudative pharyngitis and conjunctivitis in a school or camp outbreak.
- EKC (types 8, 19, 37) spreads through eye clinics; alcohol wipes don't reliably kill it.
- Also: military pneumonia (types 4, 7; oral vaccine), gastroenteritis (types 40, 41), hemorrhagic cystitis and a link to intussusception.
- Transplant recipients get pneumonitis, hepatitis, cystitis or disseminated disease; severe disease may be treated off-label with cidofovir (nephrotoxic, so give probenecid).
- Healthy patients need supportive care only.
Sources
- Clinical Overview of Adenovirus — CDC (2025)
- About Adenovirus — CDC (2025)
- Guidelines for Outbreaks: Adenovirus — CDC (2025)
- Adenovirus-Associated Epidemic Keratoconjunctivitis Outbreaks — Four States, 2008–2010 — MMWR, CDC (2013)
- Adenovirus Infections — Merck Manual Professional Edition (2026)
- Family: Adenoviridae — ICTV Report, International Committee on Taxonomy of Viruses (2026)
- Adenovirus Type 4 and Type 7 Vaccine, Live, Oral: Package Insert — FDA (2019)
- Adenoviruses — Medscape Reference (2021)
- Adenoviruses: Clinical Presentation — Medscape Reference (2021)
- Adenoviruses: Treatment & Management — Medscape Reference (2017)
- Cidofovir Injection: Prescribing Information — DailyMed (2021)
- Intussusception — Medscape Reference (2016)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
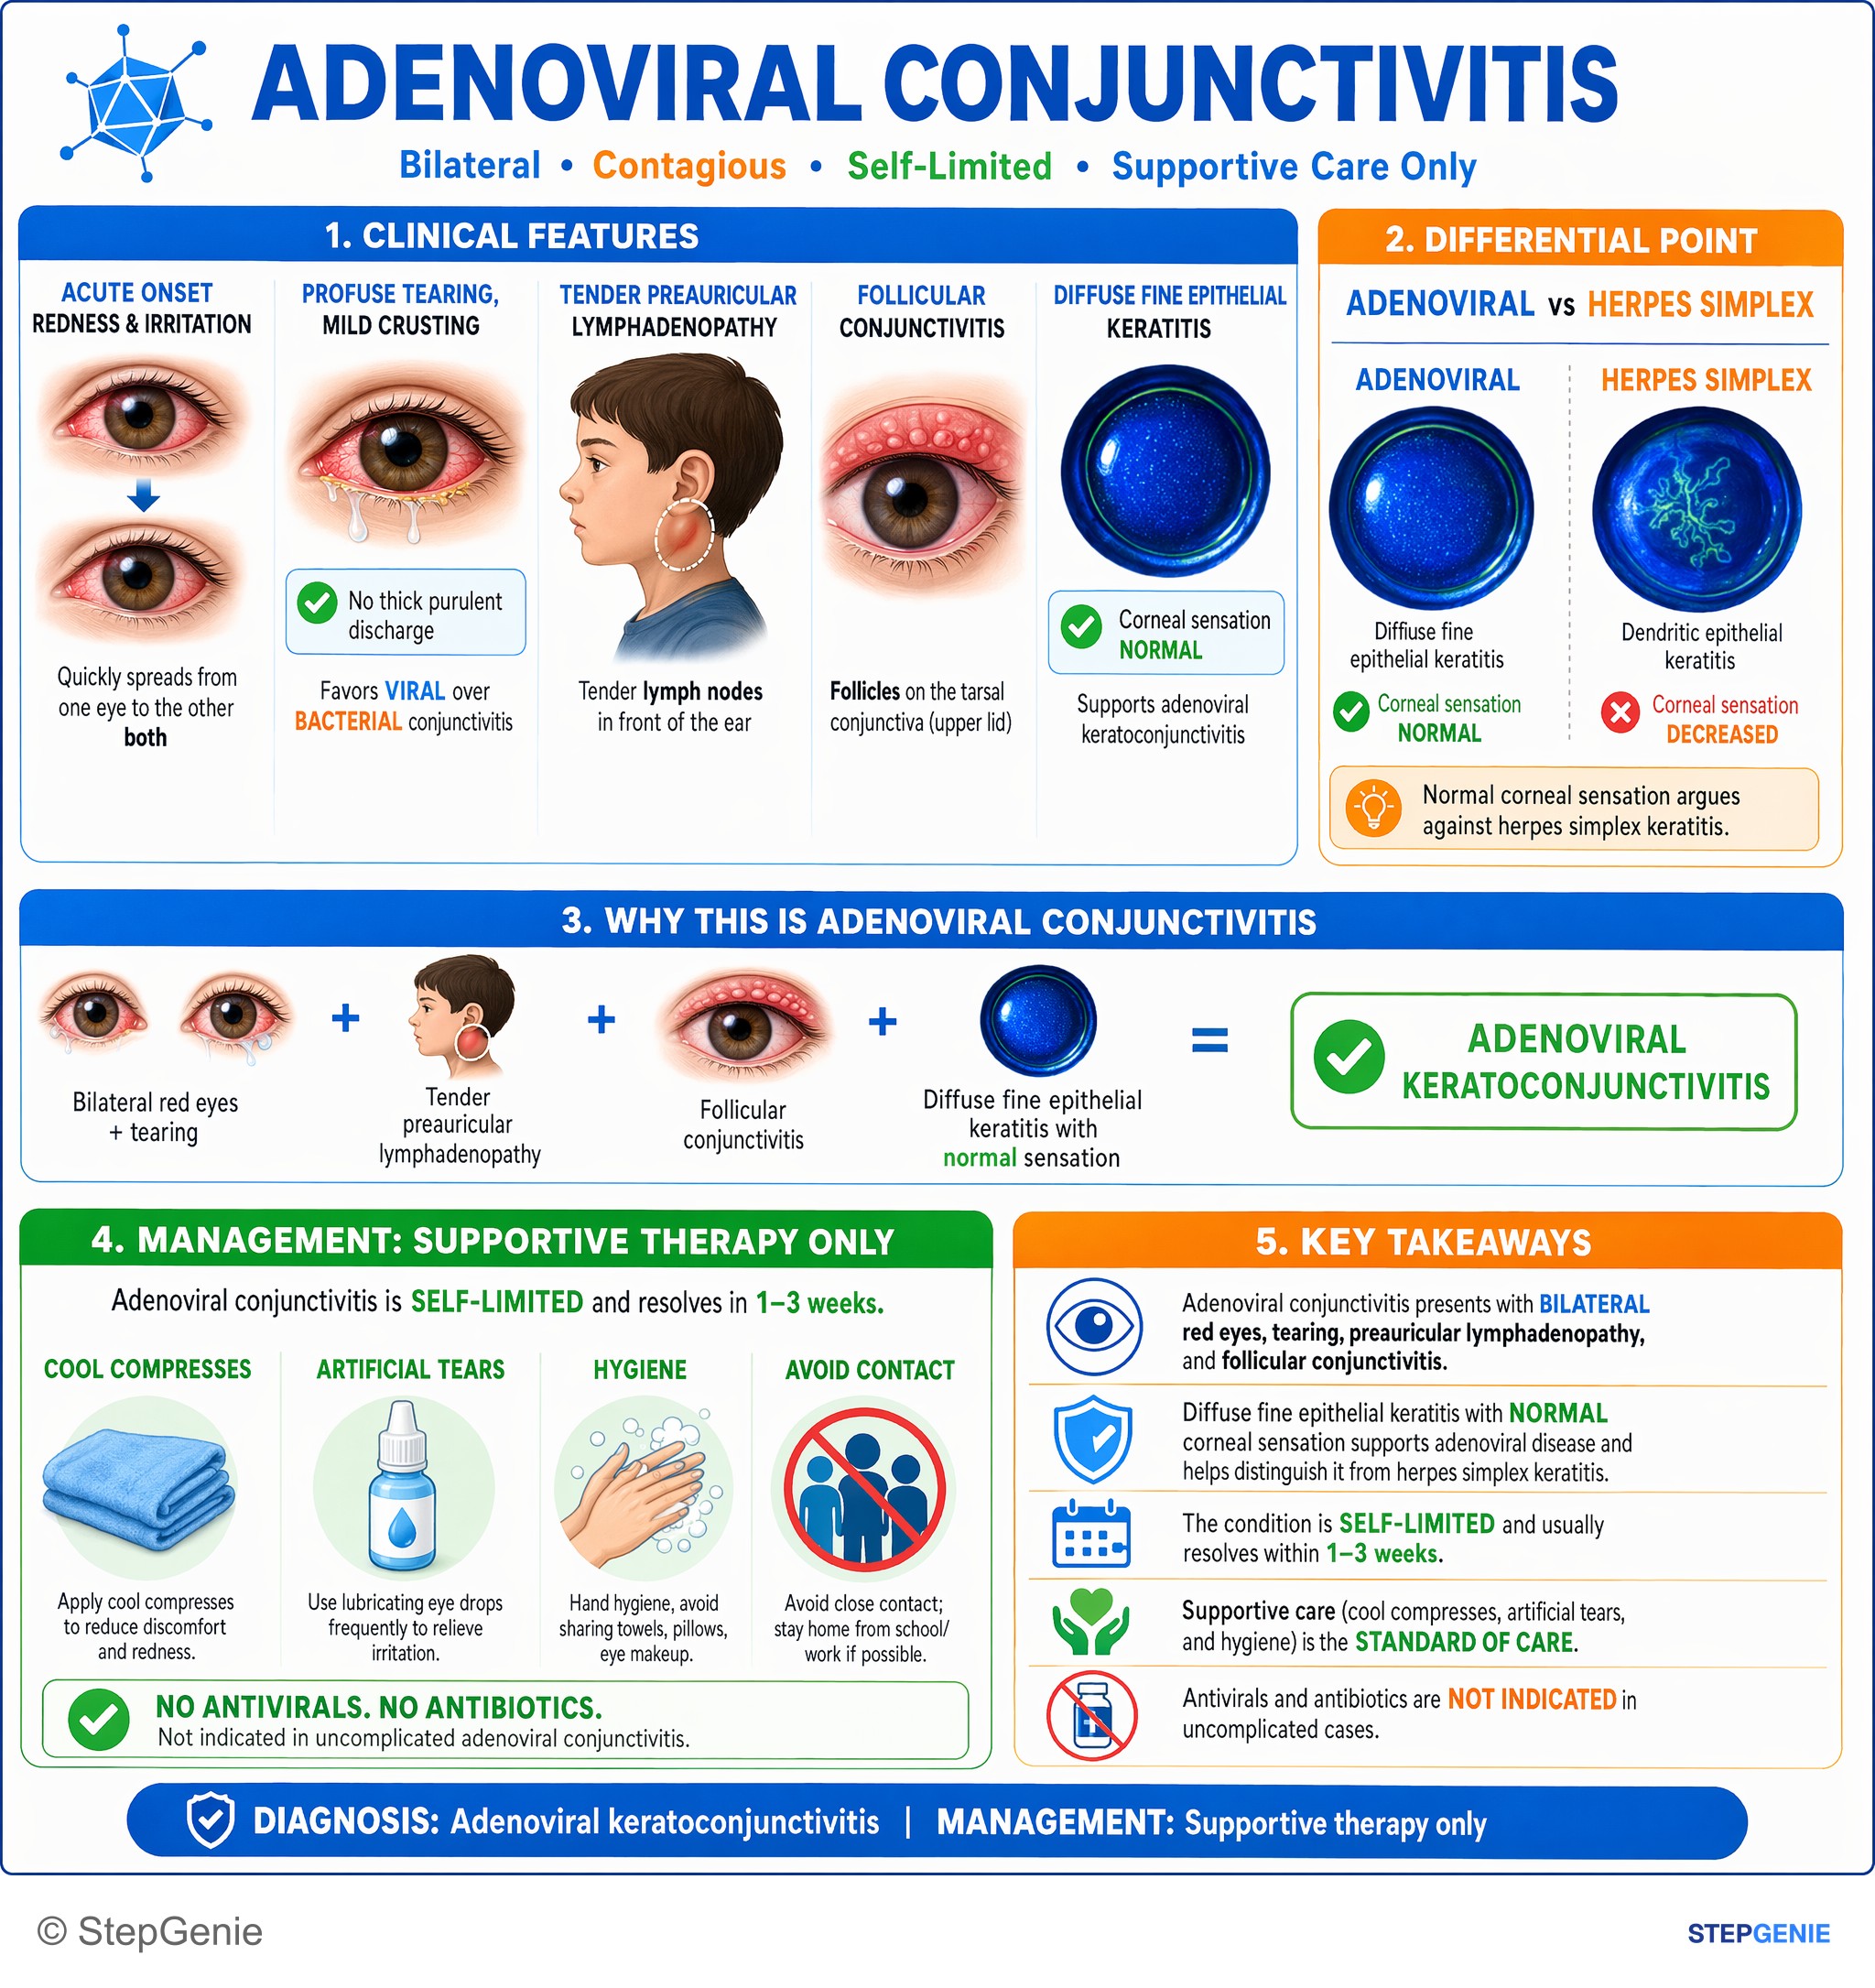
Adenoviral conjunctivitis causes bilateral red eyes, tearing, preauricular lymphadenopathy, follicular conjunctivitis; treat with…
USMLE Step 2Frequently Asked Questions
What is pharyngoconjunctival fever?
Pharyngoconjunctival fever is the classic adenovirus syndrome: fever, sore throat (often with exudates) and conjunctivitis with red, watery eyes, usually with tender neck lymph nodes. It mostly affects children and spreads in outbreaks at schools, summer camps and inadequately chlorinated swimming pools. Types 3, 4 and 7 are the usual causes. It is self-limited, and care is supportive, with hand hygiene to limit spread.
Why is adenovirus resistant to alcohol and disinfectants?
Adenovirus has no lipid envelope; its DNA sits inside a tough protein capsid. Alcohol and detergents readily destroy enveloped viruses by disrupting their lipid membrane, but nonenveloped viruses like adenovirus resist many common disinfectants and can stay infectious on surfaces for hours. CDC warns that isopropyl alcohol should not be relied on to disinfect eye instruments, because it has been linked to outbreaks of epidemic keratoconjunctivitis. Disinfectants effective against norovirus also work against adenovirus.
Can adenovirus cause blood in the urine?
Yes. Adenovirus causes acute hemorrhagic cystitis, with gross hematuria and painful urination. In otherwise healthy children, usually aged 5 to 15 years, it is self-limited and settles within a few days. In stem cell or solid-organ transplant recipients, adenovirus can cause severe hemorrhagic cystitis and nephritis, and the differential includes BK polyomavirus and cyclophosphamide toxicity. Severe disease in immunocompromised patients may be treated with cidofovir.
What is the treatment for adenovirus infection?
Most adenovirus infections are self-limited and need only supportive care, such as fluids, rest and fever control. There is no FDA-approved antiviral for adenovirus. For severe or disseminated disease in immunocompromised patients, such as transplant recipients, cidofovir is used off-label: no antiviral is proven effective, but cidofovir may offer the highest likelihood of an antiviral effect. Cidofovir is nephrotoxic, so it is given with IV saline prehydration and probenecid, and blood counts are watched for neutropenia.
Is there a vaccine for adenovirus?
Yes, but only for the US military. The adenovirus type 4 and type 7 vaccine is a live oral vaccine given as two enteric-coated tablets that must be swallowed whole, so the virus is not released in the upper airway. It is licensed for military populations aged 17 to 50 to prevent febrile acute respiratory disease from those two types. It is contraindicated in pregnancy, and vaccine virus is shed in stool, with none detected by 28 days after vaccination.
How do you tell adenovirus from strep throat or mono?
All three can cause fever with an exudative sore throat. Adenovirus is favored by conjunctivitis, a runny nose and an outbreak in a school or camp, with a negative rapid strep test. Strep throat usually lacks cough, runny nose and conjunctivitis and is confirmed with a rapid antigen test or throat culture. Mono, from Epstein-Barr virus, is suggested by posterior cervical nodes, splenomegaly and marked fatigue in a teen or young adult, with a positive heterophile test.