Cryptococcus neoformans is an encapsulated, round yeast from soil contaminated with pigeon droppings that causes subacute meningitis in people with T-cell deficiency, above all advanced HIV: about 90% of cryptococcal cases in people with HIV occur at CD4 counts below 100/mm³. The capsule gives the India ink halo, cryptococcal antigen (CrAg) in serum or CSF makes the diagnosis, and the opening pressure is high. Treat meningitis with amphotericin B plus flucytosine for 2 weeks, then fluconazole, and lower the pressure with repeated lumbar punctures, not steroids.
The mnemonic: CRYPTO
Picture a pigeon perched in a crypt. A round yeast walks past wearing a thick capsule cloak; shine India ink on it and the cloak shows up as a clear halo. Then the yeast slips into the brain, and the pressure inside the skull climbs.
| Letter | Stands for | What to know |
|---|---|---|
| C | Capsule | Polysaccharide capsule, the key virulence factor: clear halo on India ink, stains with mucicarmine, and is the antigen that CrAg tests detect |
| R | Round budding yeast | Encapsulated yeast with narrow-based buds |
| Y | Year of fluconazole | In HIV, fluconazole maintenance continues until at least 1 year after antifungal therapy began |
| P | Pigeon droppings | C. neoformans lives in soil contaminated with bird droppings, especially pigeons; infection starts when spores are inhaled |
| T | T-cell deficiency (and other immune suppression) | Advanced HIV (CD4 <100/mm³), organ transplant, long-term glucocorticoids; also lymphoma, sarcoidosis and cirrhosis |
| O | Opening pressure ↑ | ≥25 cm H₂O in 60–80% of patients with HIV; drain it with therapeutic lumbar punctures |
One-liner: encapsulated yeast from pigeon droppings + low CD4 + subacute headache + high opening pressure = cryptococcal meningitis.
How it presents
- Meningitis or meningoencephalitis (the classic test item): fever, malaise and headache that build slowly over weeks (median about 2 weeks in people with HIV). Neck stiffness and other classic meningeal signs appear in only a quarter to a third of patients, so their absence does not rule it out. Rising pressure and cerebral edema drive many symptoms; vision loss can occur.
- Lungs: the portal of entry. Many infections are asymptomatic; others cause cough, fever, chest pain and weight loss. Mild to moderate pulmonary disease is treated with fluconazole alone.
- Skin: lesions can resemble acne, molluscum contagiosum or basal cell carcinoma.
- Who gets it: advanced HIV, solid organ transplant recipients, long-term glucocorticoid users and people with lymphoma, sarcoidosis or cirrhosis. Immunocompetent people can be infected, but less often.
The other species: C. neoformans is found worldwide in soil, decaying wood and bird droppings. C. gattii lives in decayed tree hollows (more than 50 tree species, especially eucalyptus in Australia) and is found mostly in tropical and subtropical areas, plus British Columbia, Vancouver Island, the US Pacific Northwest and California.
Diagnosis: what each test shows
| Test | Finding | Pearl |
|---|---|---|
| Opening pressure | ≥25 cm H₂O in 60–80% of patients with HIV | Always measure it; it guides therapeutic taps |
| CSF profile | Mildly high protein, low-to-normal glucose, variable lymphocytic pleocytosis | Cell counts can be low in advanced AIDS |
| CrAg, lateral flow assay (serum or CSF) | Detects capsular antigen | Becoming the preferred test worldwide; sensitivity and specificity above 99% |
| India ink (CSF) | Encapsulated yeast with a clear halo | Positive in only 60–80%; a negative smear does not exclude it |
| CSF culture | Grows the yeast | Gold standard; positive in 90–94% |
| Tissue stains | Mucicarmine or Masson-Fontana positive | Confirms the yeast in biopsy material |
Screening: current US guidelines recommend serum CrAg testing in people with newly diagnosed HIV and CD4 counts ≤200/mm³ (particularly ≤50/mm³) who have no signs of meningitis. A positive serum CrAg generally calls for a lumbar puncture to rule out CNS disease; only lower-risk patients with a low titer (below 1:80 by lateral flow assay) can skip it, and early meningitis can show a positive blood CrAg with negative CSF studies.
For how Cryptococcus fits among the other CD4-based infections, see this CD4 count and opportunistic infections table; for the CSF contrasts with bacterial and viral meningitis, see this meningitis comparison.
Treatment: induction, consolidation, maintenance
The regimen below follows the US adult HIV opportunistic infection guidelines (updated 2024).
| Phase | Regimen | Duration |
|---|---|---|
| Induction | Liposomal amphotericin B 3–4 mg/kg IV daily + flucytosine 25 mg/kg orally four times daily | At least 2 weeks |
| Induction, resource-limited settings (WHO regimen) | A single 10 mg/kg dose of liposomal amphotericin B + flucytosine + fluconazole 1,200 mg/day | 2 weeks |
| Consolidation | Fluconazole 800 mg daily | At least 8 weeks |
| Maintenance | Fluconazole 200 mg daily | Until at least 1 year after antifungal therapy began; then stop if asymptomatic with CD4 ≥100/mm³ and a suppressed viral load on ART |
- Without HIV (per the Merck Manual): induction with liposomal amphotericin B plus flucytosine for 2–4 weeks, fluconazole consolidation for 8 weeks, then fluconazole maintenance for 6–12 months.
- High intracranial pressure: complications are more likely once opening pressure is ≥25 cm H₂O. Therapeutic LPs have a survival benefit; in patients with ongoing symptoms, repeat them at least daily until symptoms improve and the pressure normalizes to <20 cm H₂O. Corticosteroids, mannitol and acetazolamide are not recommended.
- Timing of antiretroviral therapy: defer ART for 4–6 weeks after antifungals start. About 10–30% of people with HIV and cryptococcal meningitis develop immune reconstitution inflammatory syndrome (IRIS) after ART starts; continue both ART and antifungals and treat raised pressure if it occurs.
Drug pearls (Step 1 pharmacology):
| Drug | Mechanism | High-yield toxicity and pearls |
|---|---|---|
| Amphotericin B | Binds ergosterol in the fungal membrane and forms ion channels; cations leak out and the cell dies | Infusion reactions (fever, chills, headache, hypotension), nephrotoxicity, hypokalemia, hypomagnesemia, anemia; lipid formulations and saline loading reduce kidney injury |
| Flucytosine | Nucleic acid analog | Resistance develops readily, so it is almost always combined with another antifungal; bone marrow suppression, hepatotoxicity |
| Fluconazole | Inhibits lanosterol 14-alpha-demethylase, blocking ergosterol synthesis | Reaches CSF levels of at least 70% of serum levels, which is why it works for consolidation and maintenance |
Exam traps
- "No neck stiffness" does not argue against cryptococcal meningitis in AIDS.
- A negative India ink does not rule it out; CrAg and culture are more sensitive.
- Steroids, acetazolamide or mannitol for high pressure: wrong. Drain CSF with repeated LPs.
- Starting ART the same day as antifungals: wrong for CNS cryptococcosis; wait 4–6 weeks.
- Fluconazole alone as induction for meningitis: not the preferred answer. Induction is amphotericin B plus flucytosine; fluconazole alone is for mild to moderate lung disease, and fluconazole follows induction as consolidation and maintenance.
- Flucytosine alone: wrong, because resistance emerges; it is almost always given with another antifungal.
Worked example
Vignette. A 34-year-old man with untreated HIV (CD4 count 42/mm³) has 2 weeks of headache, fever and malaise. He has no neck stiffness. Lumbar puncture shows an opening pressure of 34 cm H₂O, 8 white cells/µL (mostly lymphocytes), mildly elevated protein and low-normal glucose. India ink shows encapsulated budding yeast, and CSF CrAg is positive. He starts liposomal amphotericin B and flucytosine. On day 3 his headache worsens, and a repeat lumbar puncture shows an opening pressure of 30 cm H₂O. What is the best next step?
Answer: Continue induction therapy and repeat therapeutic lumbar punctures at least daily until symptoms improve and the opening pressure normalizes.
Why the tempting distractors are wrong:
- Dexamethasone: corticosteroids are not recommended for raised pressure in cryptococcal meningitis.
- Acetazolamide or mannitol: also not recommended for pressure control.
- Start antiretroviral therapy now: ART is deferred for 4–6 weeks after antifungal therapy begins because of the IRIS risk.
- Switch to fluconazole 800 mg daily: that is consolidation, which starts only after at least 2 weeks of induction.
Key takeaways
- CRYPTO: Capsule, Round budding yeast, Year of fluconazole, Pigeon droppings, T-cell deficiency, Opening pressure ↑.
- About 90% of cryptococcal disease in people with HIV occurs at CD4 <100/mm³.
- CrAg (lateral flow) is the key test; India ink is positive in only 60–80%; culture is the gold standard.
- Treatment: amphotericin B + flucytosine for at least 2 weeks → fluconazole 800 mg for at least 8 weeks → fluconazole 200 mg until at least 1 year from the start of therapy.
- Pressure: therapeutic LPs, at least daily while symptomatic, not steroids, mannitol or acetazolamide. ART: wait 4–6 weeks.
Sources
- Cryptococcosis — NIH/CDC/IDSA Guidelines for the Prevention and Treatment of Opportunistic Infections in Adults and Adolescents With HIV (Clinicalinfo.HIV.gov)
- Clinical Overview of Cryptococcosis — CDC
- Cryptococcosis — Merck Manual Professional Edition
- Antifungal Medications — Merck Manual Professional Edition
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
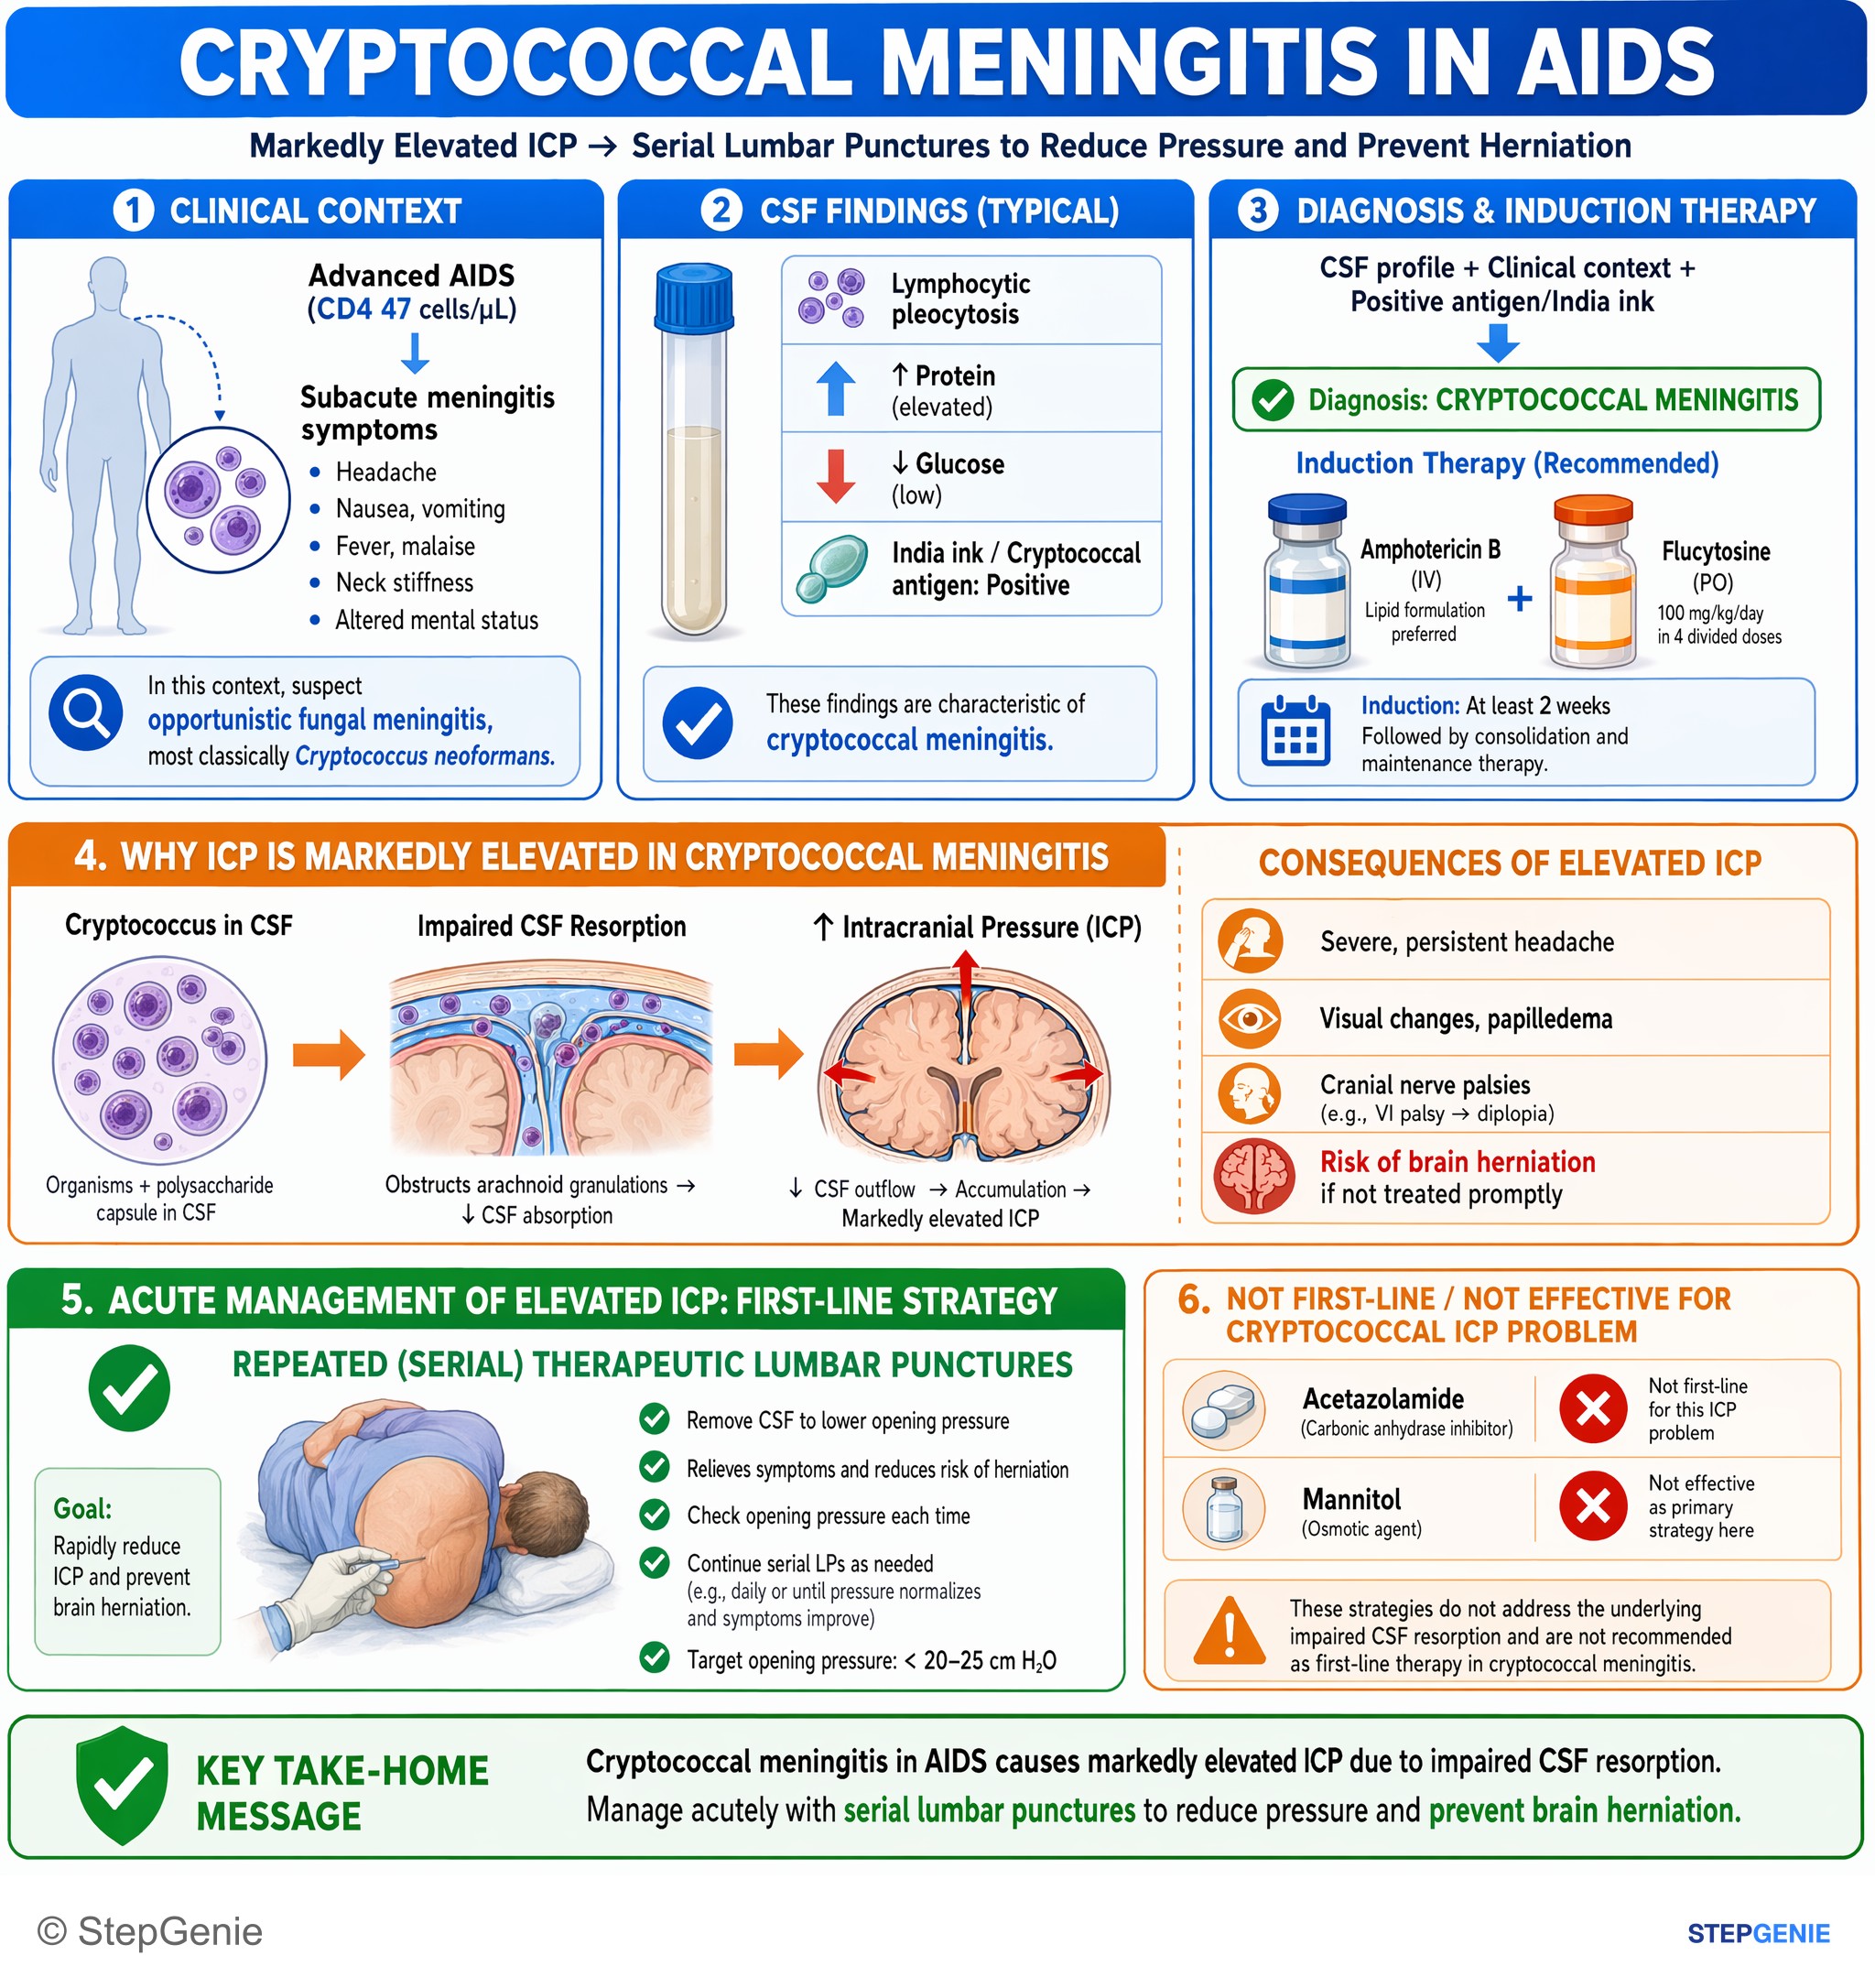
Cryptococcal meningitis in AIDS causes markedly elevated ICP; manage acutely with serial lumbar punctures to reduce pressure and prevent…
USMLE Step 2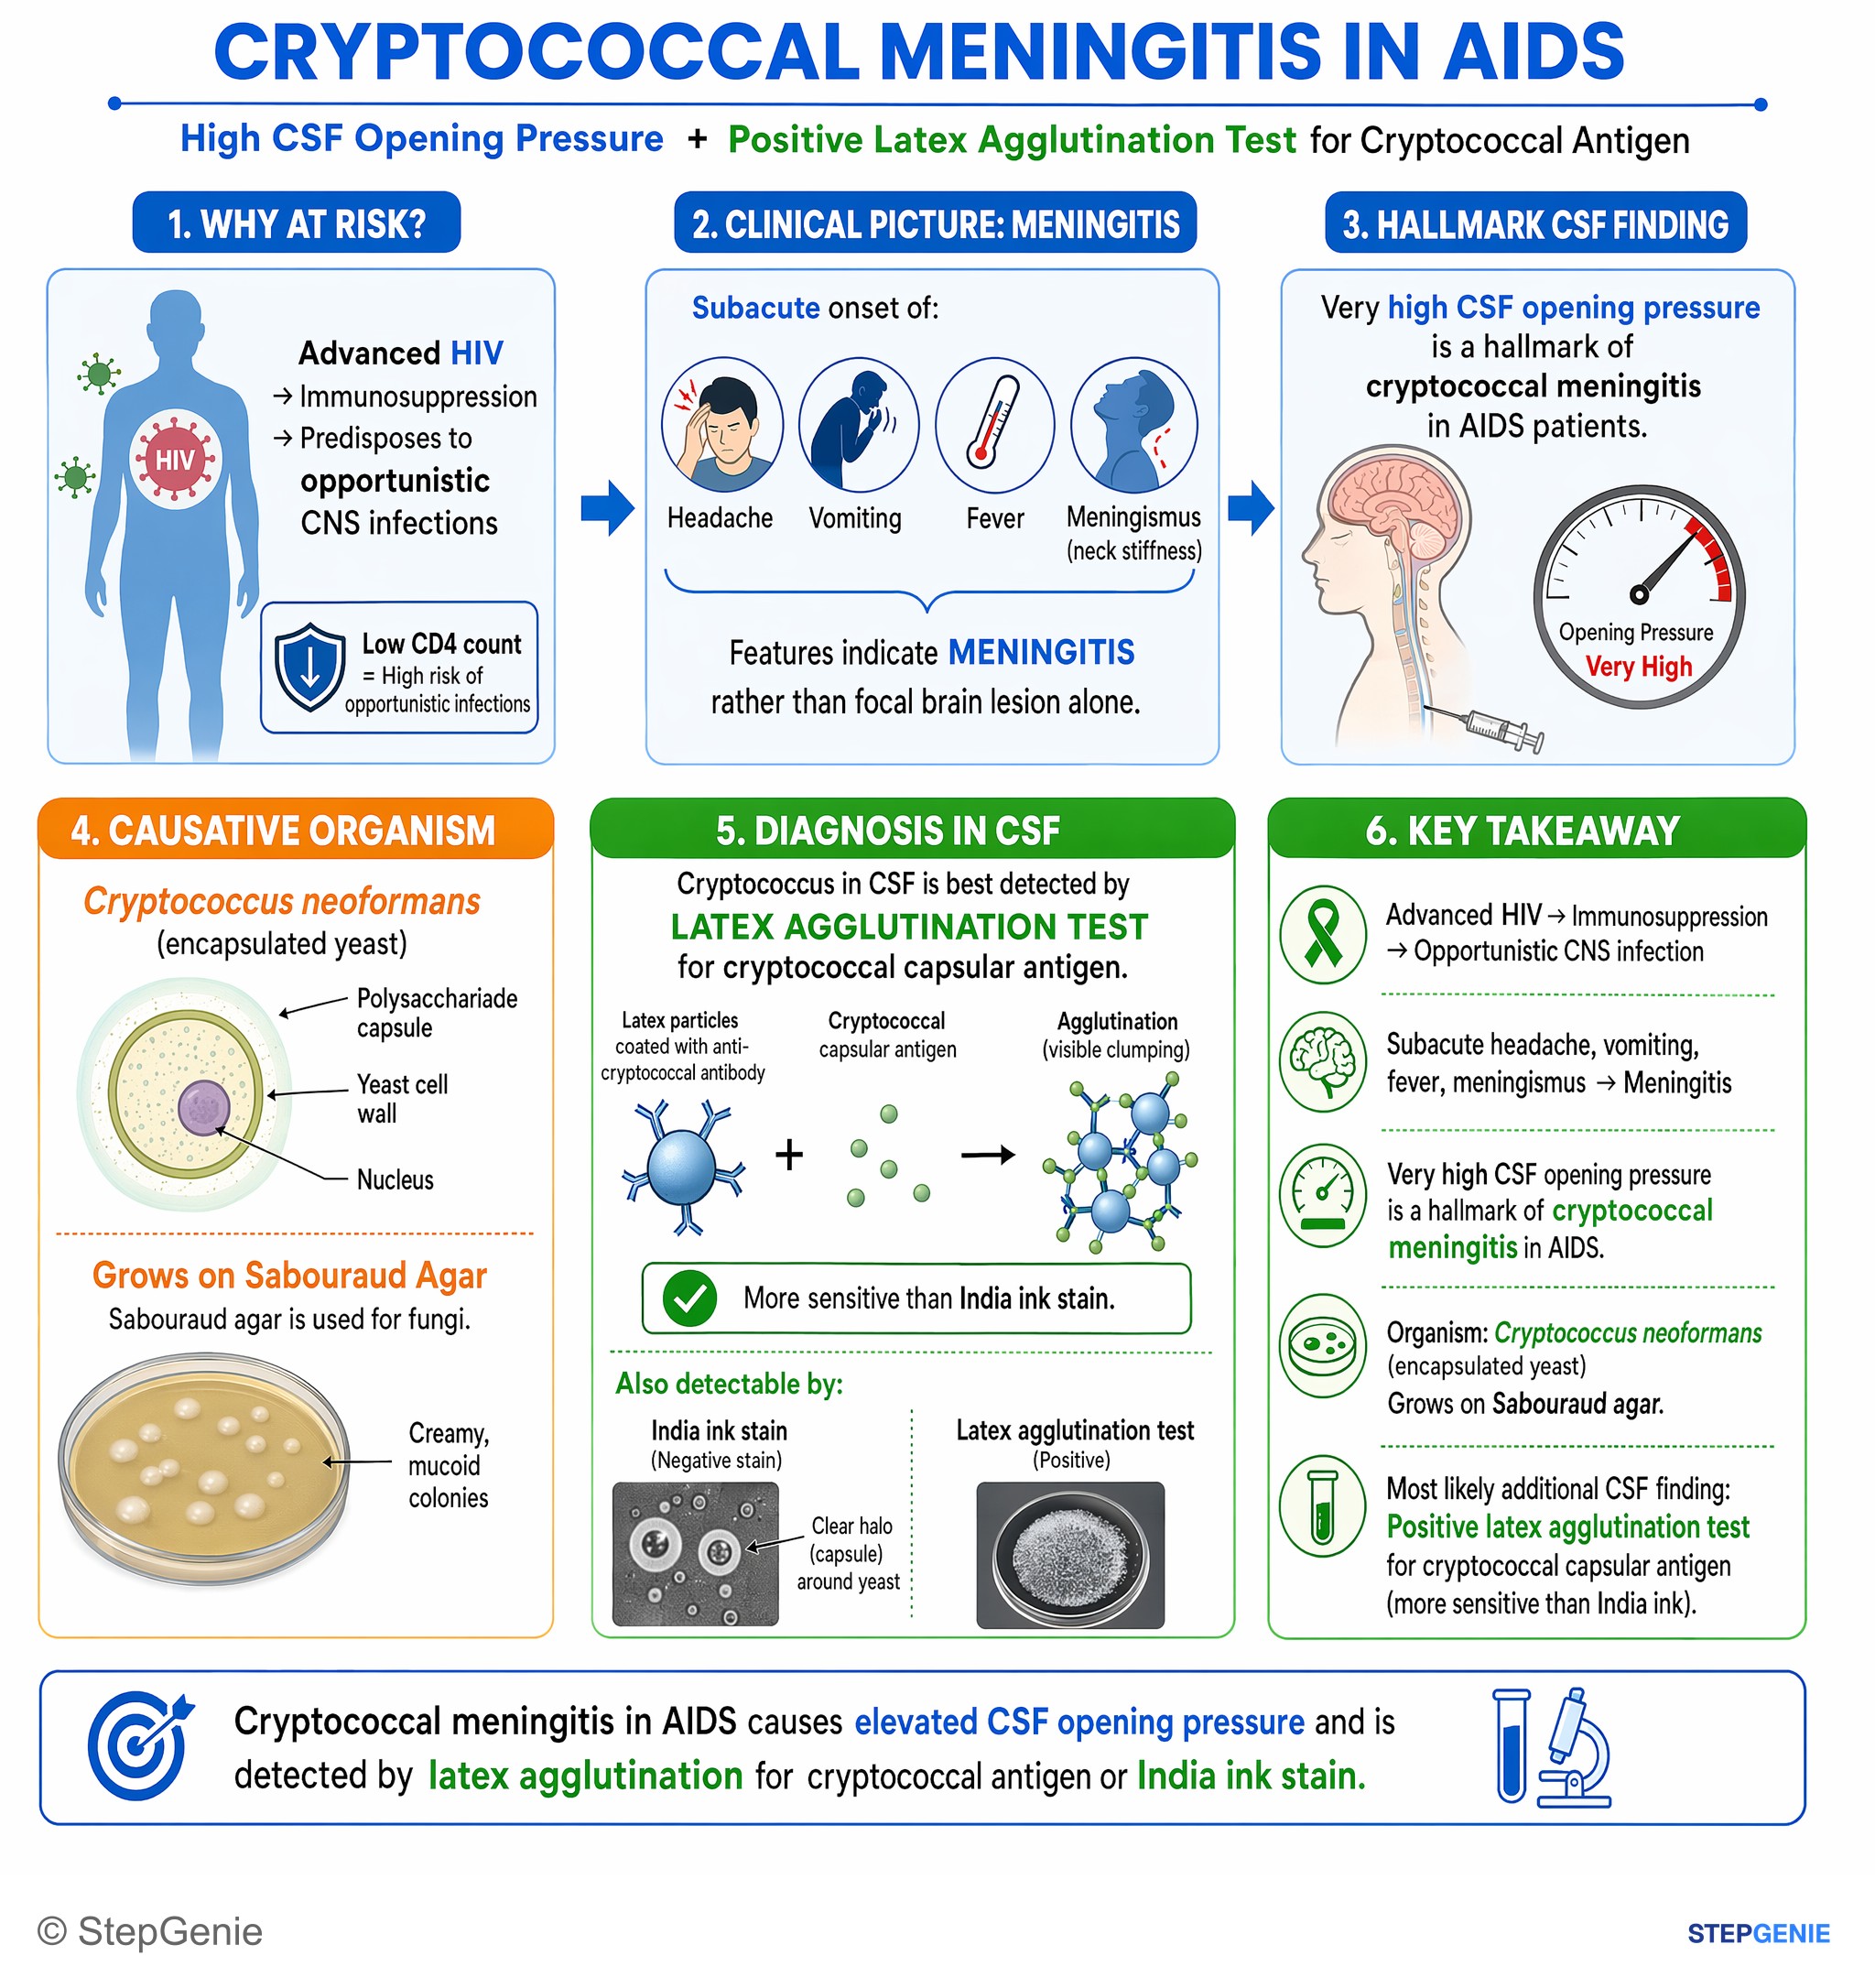
Cryptococcal meningitis in AIDS causes elevated CSF opening pressure and is detected by latex agglutination for cryptococcal antigen or…
USMLE Step 1Frequently Asked Questions
Why does India ink show a clear halo around Cryptococcus?
India ink is a negative stain: it darkens the background, and the thick polysaccharide capsule keeps the ink particles away from the yeast, leaving a clear halo around a round budding cell. The smear is quick but positive in only 60% to 80% of cases in people with HIV, so a negative India ink does not rule out cryptococcal meningitis. The cryptococcal antigen test, which detects the same capsule, is far more sensitive.
At what CD4 count does cryptococcal meningitis occur?
About 90% of cryptococcal cases in people with HIV occur when the CD4 count is below 100 cells/mm³. Current US guidelines recommend screening serum cryptococcal antigen in people newly diagnosed with HIV whose CD4 count is 200 cells/mm³ or less, particularly 50 or less, even without symptoms. Transplant recipients and people on long-term glucocorticoids are also at risk regardless of HIV status.
What is the treatment for cryptococcal meningitis?
In people with HIV, induction is liposomal amphotericin B 3 to 4 mg/kg IV daily plus flucytosine 25 mg/kg orally four times daily for at least 2 weeks. Consolidation is fluconazole 800 mg daily for at least 8 weeks, then maintenance fluconazole 200 mg daily until at least 1 year after treatment began, stopping only if the CD4 count is at least 100 with a suppressed viral load. For resource-limited settings, the guideline cites the WHO regimen: a single high dose of liposomal amphotericin B with flucytosine and fluconazole.
Why are serial lumbar punctures used instead of steroids in cryptococcal meningitis?
Opening pressure is 25 cm H₂O or higher in 60% to 80% of people with HIV and cryptococcal meningitis, and raised pressure causes much of the headache, confusion and vision loss. Removing CSF by repeated lumbar punctures lowers the pressure and has a survival benefit, so in patients with ongoing symptoms it is repeated at least daily until symptoms improve and the pressure normalizes. Corticosteroids, mannitol and acetazolamide are not recommended for controlling the pressure.
When should antiretroviral therapy start in cryptococcal meningitis?
US guidelines advise deferring antiretroviral therapy for 4 to 6 weeks after antifungal treatment begins for CNS cryptococcosis. Starting too early raises the risk of immune reconstitution inflammatory syndrome, which affects roughly 10% to 30% of people with HIV and cryptococcal meningitis after ART starts. If IRIS occurs, ART and antifungals are continued and raised intracranial pressure is treated.