Aspergillus fumigatus is one of those “looks simple, tests deep” fungi: a classic microscope appearance, a classic patient profile, and a handful of board-favorite clinical syndromes that differ mainly by host immune status. If you can draw it once, you can usually recall it under pressure.
Draw-it-out method (the 20-second sketch)
Grab a scrap of paper and draw this:
- A long airway tube (a bronchus)
- Inside it, draw a fuzzy “fungus ball” (a scribbly circle)
- Off to the side, draw a Y-shaped branch at a 45° angle
- Add a neutrophil with a sad face (neutropenia) next to blood vessels with little “leaks” (hemorrhage)
What each doodle encodes
- Y-shaped branch @ ~45° → Aspergillus morphology
- Fuzzy ball in a cavity → aspergilloma (fungus ball)
- Sad neutrophil + vessel invasion/leaks → angioinvasive disease in immunocompromised → hemorrhage/infarction
- Airway tube → allergic/airway-centered disease (ABPA) in asthma/CF
One-liner (memorize this)
Aspergillus fumigatus = septate hyphae with acute-angle (~45°) branching → causes ABPA, aspergilloma (hemoptysis), and angioinvasive pneumonia in neutropenic/transplant patients.
High-yield ID: what Step expects you to recognize
Microscopy & morphology
- Septate hyphae
- Acute-angle branching (~45°)
- Often described as dichotomous branching (symmetrical “Y”)
Where it lives / how you get it
- Ubiquitous mold found in soil/decaying vegetation
- Infection via inhalation of conidia (spores)
The “3 clinical buckets” (based on host status)
| Syndrome | Typical patient | Pathogenesis | Hallmark clues | Board-favorite associations |
|---|---|---|---|---|
| Allergic bronchopulmonary aspergillosis (ABPA) | Asthma or cystic fibrosis | Type I (IgE) ± Type III hypersensitivity to Aspergillus in airways | Wheezing, cough, brownish mucus plugs, fleeting infiltrates, eosinophilia, ↑IgE | Think “asthma/CF + eosinophils + IgE” |
| Aspergilloma (“fungus ball”) | Prior lung cavity (e.g., TB, sarcoid, old abscess) | Colonization—not invasion—of a pre-existing cavity | Hemoptysis, mobile intracavitary mass; “air crescent” concept | “Fungus ball in a cavity → bleeds” |
| Invasive (angioinvasive) aspergillosis | Neutropenia, chemo, transplant, chronic granulomatous disease, high-dose steroids | Hyphae invade blood vessels → thrombosis, infarction, hemorrhage | Fever, cough, pleuritic pain, hemoptysis; can disseminate (brain, skin) | “Neutropenic + hemoptysis = suspect angioinvasion” |
ABPA: the quick-hit checklist
Think asthma/CF + allergy features.
High-yield findings:
- ↑ IgE
- Eosinophilia
- Central bronchiectasis (classically emphasized)
- Recurrent wheezing + transient (“fleeting”) pulmonary infiltrates
Treatment vibe (Step-level):
- Steroids to control hypersensitivity (often front-line)
- Add an azole (e.g., itraconazole/voriconazole) in many regimens to reduce fungal burden (depends on case framing)
Aspergilloma: why hemoptysis?
An aspergilloma grows as a tangled ball of hyphae sitting in a preformed cavity. It can erode nearby vessels or mechanically irritate → hemoptysis (can be massive).
Key setup stem:
- History of TB (or other cavitary disease)
- Imaging suggests a mass within a cavity (often with an “air crescent” surrounding it)
Invasive aspergillosis: the testable mechanism
Angioinvasion is the money word.
What angioinvasion causes:
- Thrombosis → tissue ischemia/infarction
- Hemorrhage → hemoptysis, hemorrhagic lesions
- Dissemination hematogenously (CNS involvement can show ring-enhancing lesions in some contexts)
High-risk patients:
- Neutropenic (especially prolonged)
- Hematopoietic stem cell transplant or solid organ transplant
- Chronic granulomatous disease (impaired oxidative burst → catalase+ organisms, including Aspergillus)
Classic pharmacology tie-ins (Step-friendly)
- Voriconazole is commonly the go-to for invasive aspergillosis in exam questions.
- Amphotericin B is a broad, classic option often mentioned for severe systemic mycoses (toxicity matters, but Step loves the association).
Micro “either-or” you must not mix up
Aspergillus vs Mucor (most common trap)
| Feature | Aspergillus | Mucor/Rhizopus |
|---|---|---|
| Hyphae | Septate | Nonseptate (pauciseptate) |
| Branching angle | Acute (~45°) | Right angle (~90°) |
| Classic patient | Neutropenia/transplant, CGD | DKA, neutropenia, deferoxamine |
| Big buzzword | Angioinvasive | Angioinvasive (also!) with rhinocerebral disease |
Mnemonic:
- Aspergillus = Acute angle
- Mucor = Massive 90° turns
Rapid recall (what to say in 10 seconds)
- ID: septate hyphae, acute-angle branching
- ABPA: asthma/CF + ↑IgE + eosinophils
- Aspergilloma: fungus ball in old cavity → hemoptysis
- Invasive: neutropenia/transplant → angioinvasion → hemorrhage/infarction
- Tx (classic): voriconazole for invasive disease
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
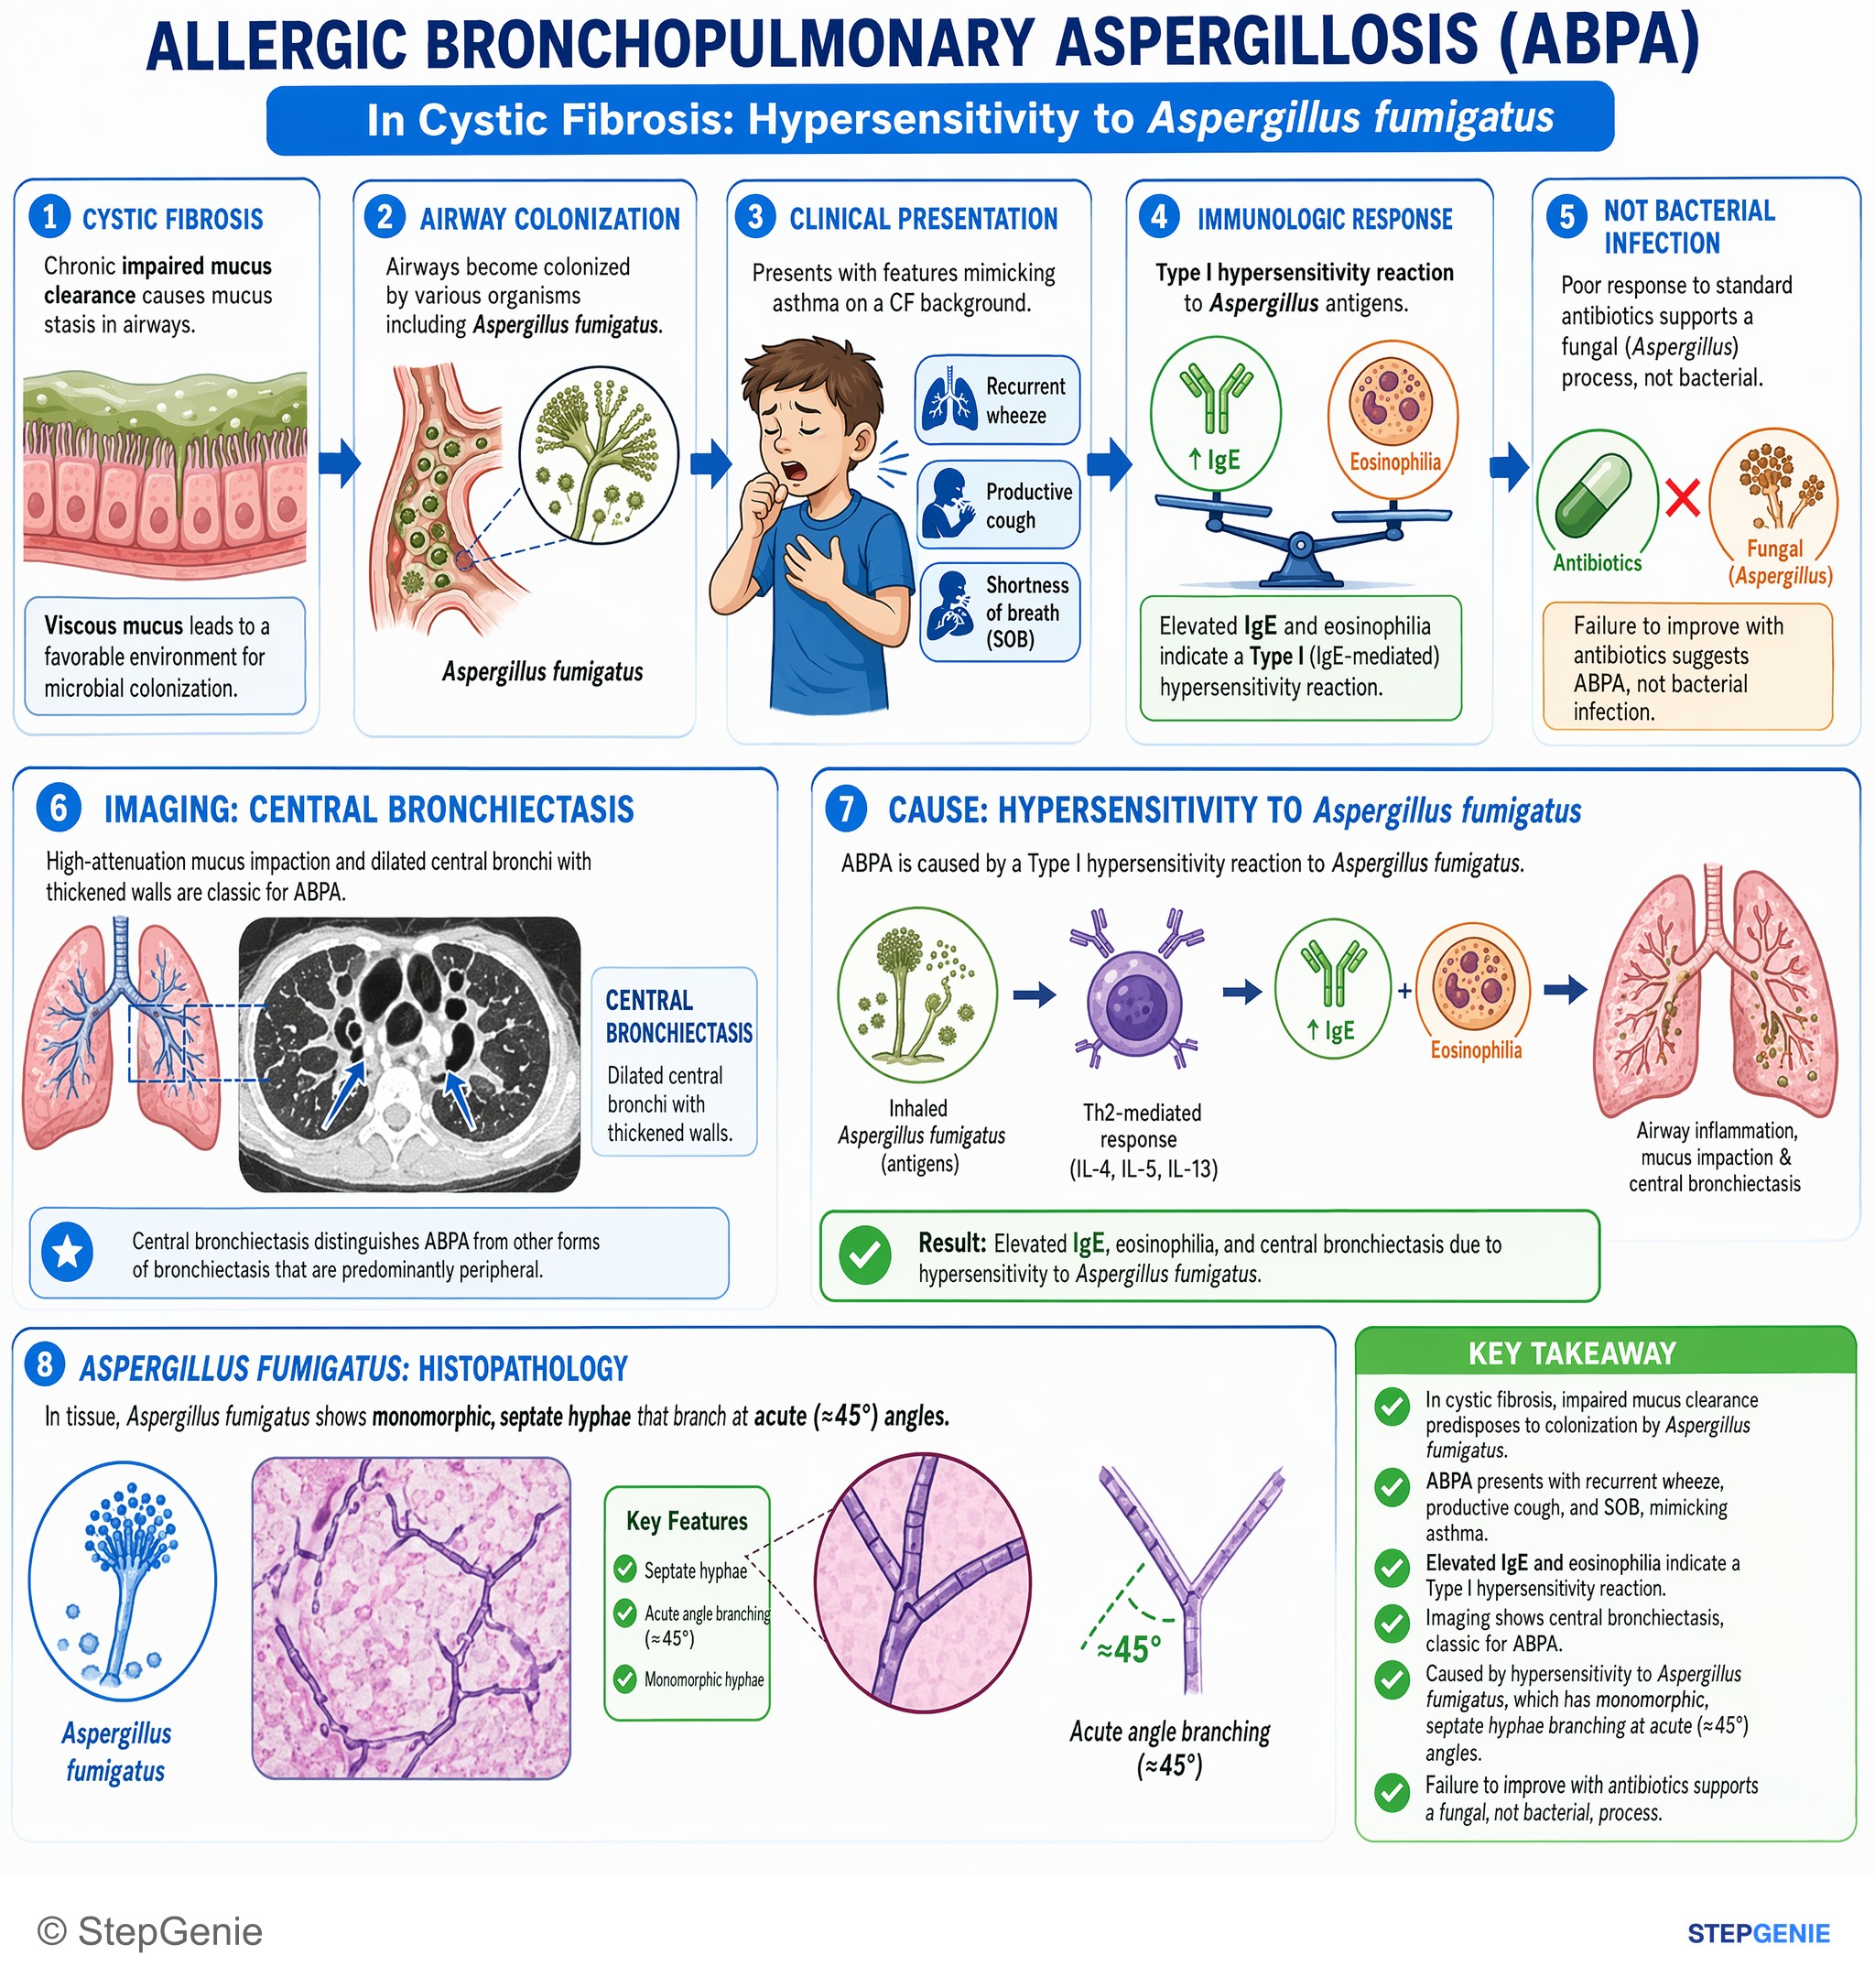
Allergic bronchopulmonary aspergillosis in cystic fibrosis: hypersensitivity to Aspergillus fumigatus → elevated IgE, eosinophilia…
USMLE Step 1Frequently Asked Questions
How do you tell Aspergillus from Mucor on microscopy?
Aspergillus is identified by septate hyphae with acute-angle branching around 45 degrees, often forming a symmetrical Y shape. Mucor or Rhizopus instead shows nonseptate or pauciseptate hyphae with branching closer to 90 degrees. This distinction is a classic test trap, so the branching angle and presence or absence of septations are the key clues.
Why does an aspergilloma cause hemoptysis?
An aspergilloma causes hemoptysis because a tangled ball of hyphae sits inside a preexisting lung cavity and can erode nearby blood vessels or mechanically irritate the cavity. The usual setup is a patient with prior cavitary lung disease such as tuberculosis, sarcoid, or an old abscess, plus imaging that shows a mobile intracavitary mass or an air crescent.
What clinical clues point to ABPA from Aspergillus?
ABPA is suggested by asthma or cystic fibrosis plus allergic features such as wheezing, cough, brownish mucus plugs, eosinophilia, and elevated IgE. It is an airway-centered hypersensitivity reaction to Aspergillus, described as type I IgE with or without type III involvement. Recurrent symptoms with fleeting pulmonary infiltrates and central bronchiectasis are especially high-yield clues.
Why is Aspergillus especially dangerous in neutropenic or transplant patients?
Aspergillus is especially dangerous in neutropenic or transplant patients because it can become angioinvasive. The hyphae invade blood vessels, leading to thrombosis, tissue infarction, and hemorrhage, which can cause fever, cough, pleuritic pain, and hemoptysis. In severe cases it can disseminate through the bloodstream to sites such as the brain or skin, making immune status the major clinical separator.
What is the go-to treatment for invasive aspergillosis on exams?
Voriconazole is the commonly tested go-to treatment for invasive aspergillosis. This association is especially important in exam questions describing neutropenia or transplant status with angioinvasive disease, hemoptysis, and septate hyphae branching at acute angles. Amphotericin B is also a classic broad antifungal mentioned for severe systemic mycoses, but voriconazole is the key board-style answer for invasive Aspergillus.