Candida albicans is one of those organisms you’ll see everywhere on USMLE—because it’s both a normal flora yeast and a classic opportunistic pathogen. The trick is being able to recognize it in 5 seconds from a vignette, a smear, or a culture description.
The “5-Second Rule” for Candida albicans
If you can say these 5 things fast, you’ll rarely miss it:
- Yeast that forms pseudohyphae
- Budding yeast on microscopy
- Germ tubes at 37°C (classic lab clue)
- Thrush + vaginitis + diaper rash (mucocutaneous)
- Opportunistic in immunosuppressed / diabetics / after antibiotics
One-liner: Candida albicans is a normal flora yeast that becomes opportunistic, causing mucocutaneous disease and bloodstream infection, and is identified by budding yeast, pseudohyphae, and germ tubes.
Visual/Mnemonic Device: “CANDI-DA”
Think of CANDI-DA like a piece of candy that stretches into strings (pseudohyphae), and melts into the bloodstream when defenses drop.
CANDI-DA mnemonic
- C: Creamy white plaques (thrush) that scrape off
- A: Antibiotics predispose (kills competing flora)
- N: Neutropenia → invasive disease risk
- D: Diabetes predisposes (esp. vulvovaginal infections)
- I: Indwelling lines → candidemia
- D: Dimorphic-ish look on smear (yeast + pseudohyphae; not true dimorphism like Histoplasma)
- A: Albicans = germ tubes (at 37°C)
Memory image: A “candy cane” (Candida) that’s normally on the table (normal flora), but when the bouncer leaves (immunosuppression/antibiotics), it grows long stretchy “strings” (pseudohyphae) and spills into the punch bowl (bloodstream).
Instant ID: What to Recognize on Questions
On microscopy / pathology
- Budding yeast + pseudohyphae
- Can form true hyphae in tissue as well
- Germ tube test positive (high-yield for C. albicans)
On culture
- Often described as creamy colonies (yeast-like)
High-Yield Clinical Syndromes (the “Greatest Hits”)
1) Oral thrush (oropharyngeal candidiasis)
- White plaques that scrape off → erythematous base
- Risks: HIV/AIDS, inhaled steroids, extremes of age
2) Esophagitis
- Odynophagia/dysphagia in immunocompromised
- Endoscopy: white plaques
- Classic association: AIDS (often with low CD4)
3) Vulvovaginal candidiasis
- Pruritus, erythema, dyspareunia
- Thick, white “cottage cheese” discharge (typically minimal odor)
- Risks: pregnancy, diabetes, antibiotics
4) Candidemia / disseminated Candida
- Think: ICU patient, TPN, neutropenia, central venous catheter, broad-spectrum antibiotics
- Can seed organs (e.g., eye → endophthalmitis)
5) Diaper rash / intertrigo
- Beefy red rash with satellite lesions
- Loves warm, moist areas
USMLE “Clue → Diagnosis” Speed Table
| Vignette clue | Snap diagnosis move |
|---|---|
| White plaques in mouth that scrape off | Thrush (Candida) |
| Odynophagia in AIDS + esophageal plaques | Candida esophagitis |
| Thick white discharge + itching, risk factors like diabetes | Vulvovaginal Candida |
| Neutropenic patient + fever + central line | Candidemia |
| Budding yeast + pseudohyphae | Candida species (esp. albicans) |
| Germ tubes at 37°C | Candida albicans |
Pathogenesis in One Breath (Why It Happens)
- Normal flora (mouth, GI, vagina)
- Disruption of barriers or microbiome (antibiotics, mucosal damage) or immune deficits (neutropenia, HIV, steroids) → overgrowth and invasion
Treatment: What USMLE Usually Wants You to Say
This is a “pattern recognition” zone—match severity and location:
- Mucocutaneous (thrush, vaginitis): often azole therapy (e.g., fluconazole), topical options depending on site/severity
- Invasive candidemia: echinocandin is commonly first-line in sick patients; remove/replace infected lines when relevant
(Exact regimen can vary by setting and resistance risk—on exams, the big idea is: azoles for uncomplicated mucosal disease; echinocandin for invasive/critically ill.)
5-Second Recap (Say It Out Loud)
“Candida albicans: budding yeast that forms pseudohyphae and germ tubes; causes thrush, vaginitis, and opportunistic candidemia—especially after antibiotics, in diabetes, neutropenia, or with indwelling lines.”
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
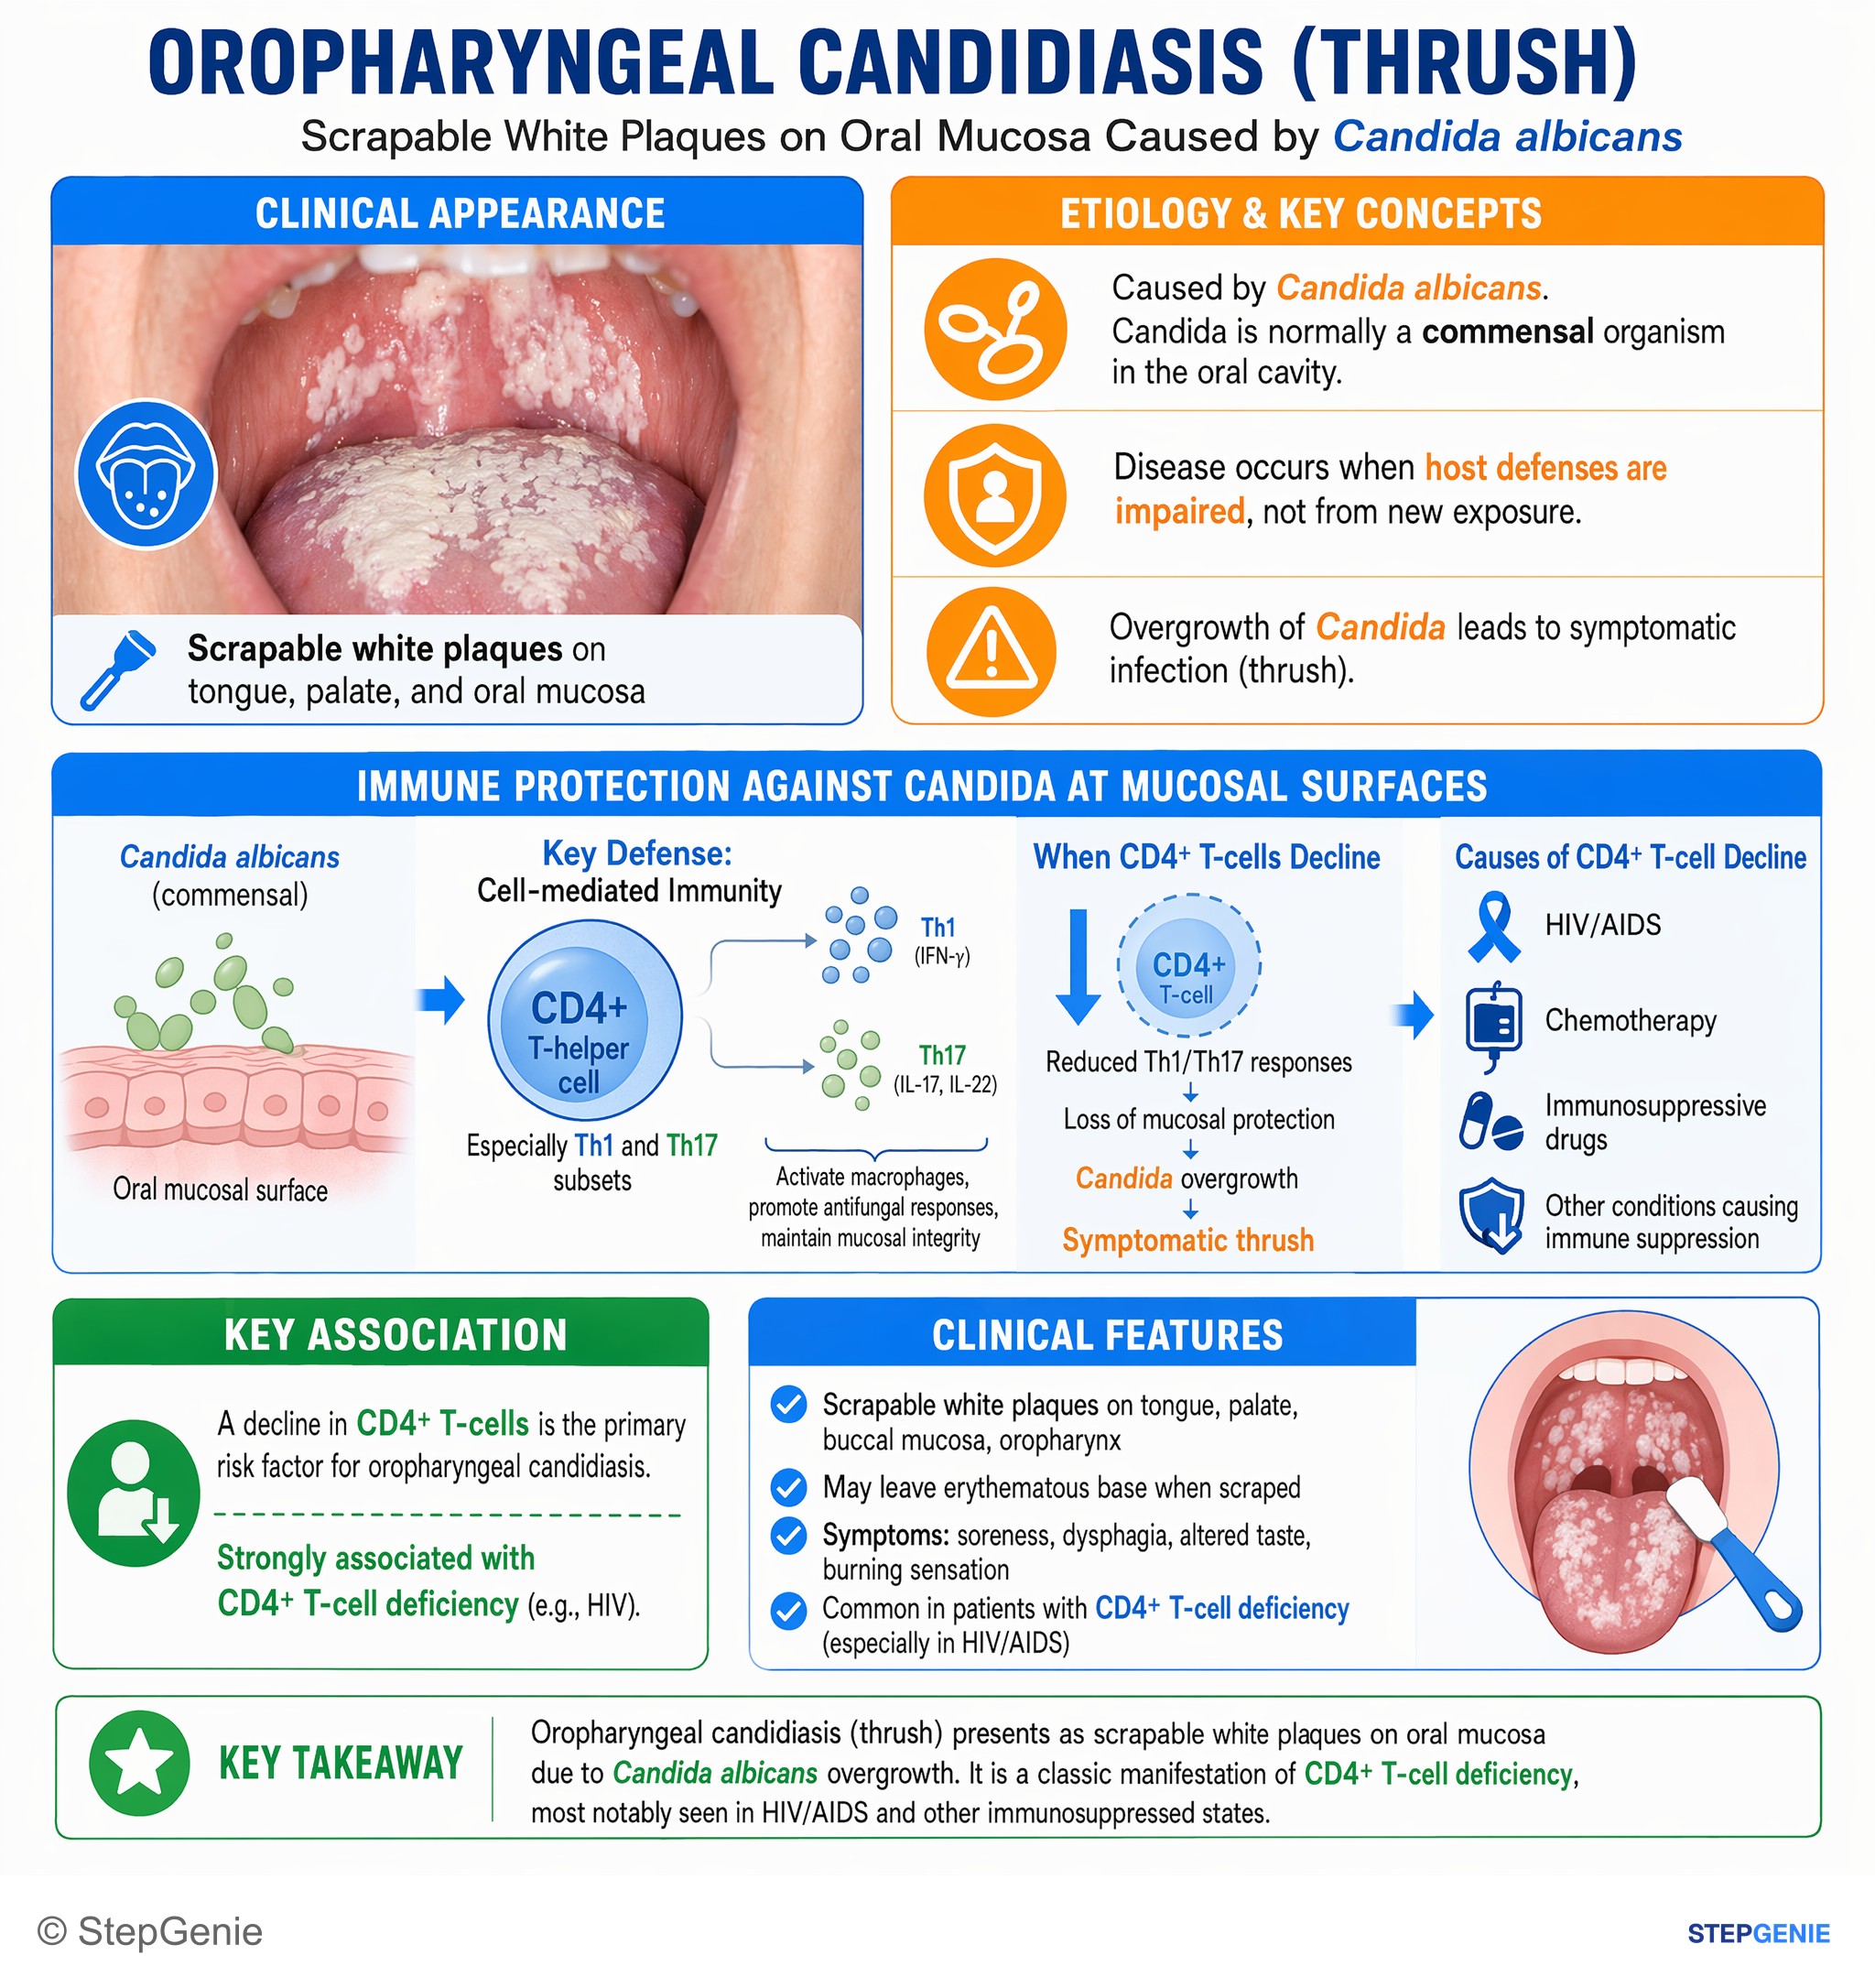
Oropharyngeal candidiasis (thrush) presents as scrapable white plaques on tongue/palate and is strongly associated with CD4+ T-cell…
USMLE Step 1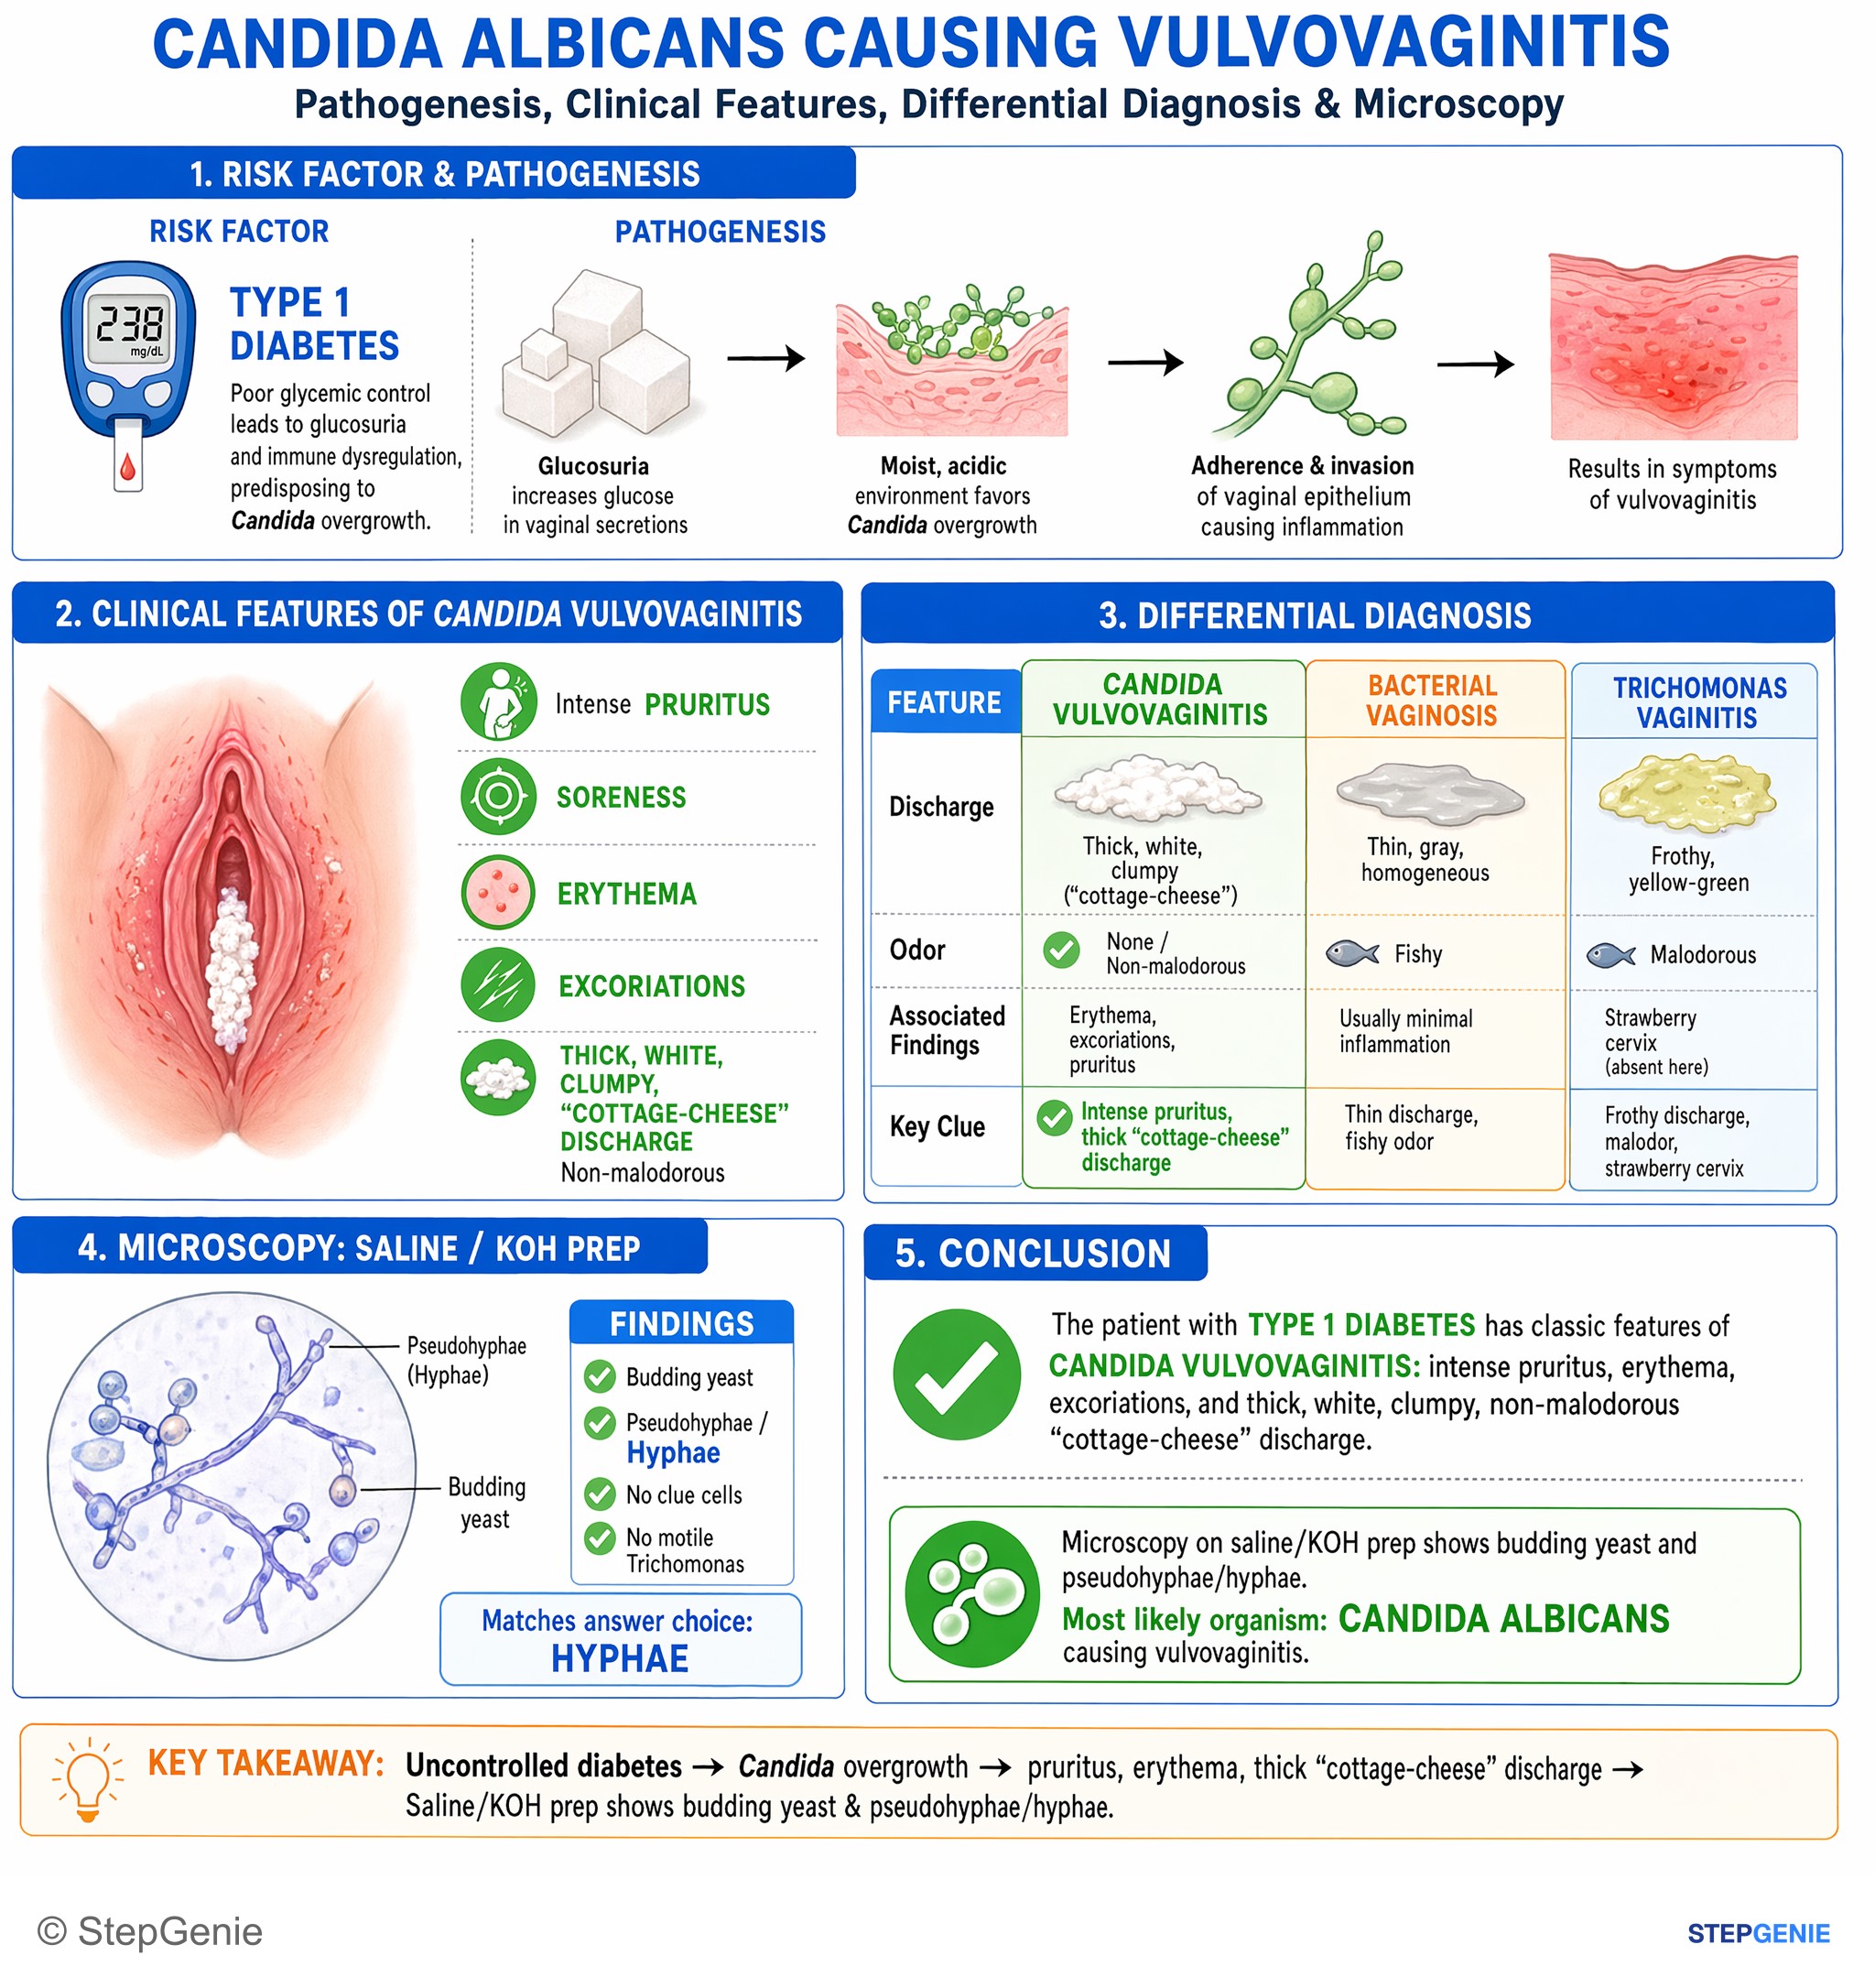
Candida vulvovaginitis from uncontrolled diabetes: pruritus, erythema, thick “cottage-cheese” discharge; saline or KOH prep shows budding…
USMLE Step 1Frequently Asked Questions
How do you recognize Candida albicans quickly on microscopy or lab testing?
Candida albicans is recognized by budding yeast, pseudohyphae, and a positive germ tube test at 37°C. On microscopy, questions often describe budding yeast with pseudohyphae, and the organism can also form true hyphae in tissue. A classic lab clue is germ tube formation, and culture may be described as creamy, reflecting its yeast-like colonies.
Why do antibiotics, diabetes, and immunosuppression predispose to Candida albicans infections?
They predispose because Candida albicans is normal flora that overgrows when host defenses or the normal microbiome are disrupted. Antibiotics kill competing flora, while immune deficits such as neutropenia, HIV, or steroid use reduce control of the organism. Diabetes is also a classic risk factor, especially for vulvovaginal infections, allowing this usually harmless yeast to become opportunistic and invasive.
How do you tell oral thrush from other white mouth lesions in a vignette?
Oral thrush is suggested by creamy white plaques that scrape off and leave an erythematous base. That scraping clue is one of the fastest ways to identify Candida in oral lesions. Thrush is especially associated with HIV/AIDS, inhaled steroid use, and extremes of age, so those risk factors in the vignette make Candida even more likely.
What are the classic clinical syndromes caused by Candida albicans?
The classic syndromes are thrush, esophagitis, vulvovaginal candidiasis, diaper rash or intertrigo, and candidemia. Thrush causes white plaques that scrape off, esophagitis causes odynophagia or dysphagia in immunocompromised patients, vulvovaginal disease causes pruritus with thick white discharge, and diaper rash produces a beefy red rash with satellite lesions. Invasive disease can occur in ICU patients or those with neutropenia or central lines.
What is the usual treatment approach for Candida albicans on exams?
The usual exam approach is azoles for uncomplicated mucocutaneous disease and an echinocandin for invasive candidemia in sick patients. Thrush and vaginitis are often treated with azole therapy such as fluconazole, with topical options depending on site and severity. For invasive bloodstream infection, questions often expect echinocandin as first-line, along with removing or replacing infected indwelling lines when relevant.