Chlamydia trachomatis is the “can’t-miss” Step bug because it shows up everywhere: urethritis/cervicitis, PID, neonatal disease, reactive arthritis, and even blindness. The trick isn’t memorizing a list—it’s running a fast mental flowchart that tells you what syndrome you’re looking at, how to diagnose it, and what to treat with.
The 10-second ID: what makes Chlamydia unique?
Obligate intracellular, energy parasite: it cannot make enough ATP and relies on host cells → must live inside them.
Classic one-liner:
“Chlamydia = obligate intracellular organism with a biphasic life cycle (EB → RB) that causes GU infection, neonatal pneumonia/conjunctivitis, reactive arthritis, and trachoma.”
Visual mnemonic: “EB enters, RB replicates”
Think of a cell as a nightclub:
- Elementary body (EB) = the infectious form
- E = Entry / Extracellular / Enfectious (infectious)
- Reticulate body (RB) = the replicative form
- R = Replication / Retained inside (intracellular)
Cycle: EB is endocytosed → converts to RB → replicates in cytoplasmic inclusions → converts back to EB → released to infect new cells.
Step-by-step flowchart (high-yield, test-day ready)
Step 1 — What syndrome is the stem pointing to?
A) Sexually transmitted GU infection
Clues:
- Dysuria + no nitrites, sterile pyuria
- Cervicitis (friable cervix) or urethritis
- NAAT-positive partner / high-risk sex
Think: Chlamydia (D–K)
B) PID / infertility / ectopic pregnancy risk
Clues:
- Cervical motion tenderness, fever, adnexal tenderness
- Post-coital bleeding, dyspareunia
- Long-term: infertility, ectopic pregnancy
Think: Chlamydia (D–K) is a major cause (often with gonorrhea)
C) Neonatal infection (timing is key)
- Conjunctivitis: 5–14 days after birth (not at birth)
- Pneumonia: 1–3 months, staccato cough, tachypnea, often afebrile, eosinophilia
Think: Chlamydia (D–K) acquired during vaginal delivery
D) Reactive arthritis pattern
Clues:
- Arthritis + conjunctivitis/uveitis + urethritis/cervicitis
- Often HLA-B27 association
Think: Chlamydia (D–K) is a classic trigger
E) Trachoma (blinding disease)
Clues:
- Chronic follicular conjunctivitis
- Scarring/entropion/trichiasis
- Endemic areas, poor sanitation
Think: Chlamydia (A–C)
F) Lymphogranuloma venereum (LGV)
Clues:
- Painful genital ulcer may be subtle
- Then painful inguinal lymphadenopathy (“buboes”), proctocolitis risk (esp. MSM)
Think: Chlamydia (L1–L3)
Step 2 — Choose the diagnostic test (what will they ask?)
| Clinical situation | Best test | Key exam wording |
|---|---|---|
| Urethritis/cervicitis/PID suspicion | NAAT (PCR) on urine or swab | “Most sensitive,” “screening,” “first-line test” |
| Inclusion conjunctivitis (adult or neonatal) | NAAT from conjunctival swab | Purulent discharge + timing 5–14 days neonate |
| Suspected intracellular inclusions | Giemsa may show basophilic cytoplasmic inclusions (historical) | “Intracytoplasmic inclusions” |
| Culture | Not routine for Step purposes | Obligate intracellular → special culture |
High-yield pearl: If the stem emphasizes “intracellular” + “cannot be grown on artificial media”, they’re pointing you to Chlamydia (or other obligate intracellular organisms). For Chlamydia specifically, NAAT is the modern answer.
Step 3 — Treat + cover partners (and often cover gonorrhea)
Uncomplicated cervicitis/urethritis
- Doxycycline (common Step answer), or azithromycin in pregnancy or adherence concerns
- Treat sexual partners and advise abstinence until therapy complete
PID (outpatient classic)
- Must cover Chlamydia + gonorrhea + anaerobes
(You’ll often see a combo regimen; the principle is broad coverage)
Neonatal disease
- Neonatal conjunctivitis/pneumonia: macrolide (e.g., erythromycin/azithromycin)
(And treat the parent(s) to prevent reinfection)
Trachoma mass treatment
- Azithromycin used in public health strategies + sanitation measures
High-yield “differentials” you’ll get pimped on (and tested on)
Chlamydia vs Gonorrhea (classic Step comparison)
| Feature | Chlamydia trachomatis | Neisseria gonorrhoeae |
|---|---|---|
| Gram stain | No peptidoglycan → doesn’t Gram stain well | Gram-negative intracellular diplococci may be seen |
| Culture | Obligate intracellular → not on standard media | Can grow on Thayer-Martin |
| Common clue | Sterile pyuria, NAAT+ | Purulent discharge, Gram stain supportive in symptomatic men |
| Coinfection | Common → treat for both in many scenarios | Common |
Neonatal conjunctivitis timing (exam favorite)
- Gonococcal: 2–5 days (earlier, more severe)
- Chlamydial: 5–14 days
- Chemical (silver nitrate): within 24 hours (much less common now)
The “flowchart in one box” (shareable quick-hit)
If you see… → think… → test… → treat…
- Urethritis/cervicitis + sterile pyuria → Chlamydia (D–K) → NAAT → doxycycline (or azithro) + partner tx
- PID or infertility risk → Chlamydia (D–K) (often with GC) → NAAT → broad PID regimen covering Chlamydia/GC/anaerobes
- Neonate 5–14d conjunctivitis OR 1–3mo staccato cough → Chlamydia (D–K) → NAAT → macrolide
- Arthritis + conjunctivitis + urethritis → reactive arthritis trigger → NAAT for Chlamydia → treat infection + supportive arthritis care
- Trachoma blindness → Chlamydia (A–C) → clinical/NAAT → azithromycin + sanitation
- Buboes/proctocolitis (LGV) → Chlamydia (L1–L3) → NAAT → doxycycline (longer course)
Micro details that score easy points
- No muramic acid / minimal peptidoglycan → poor Gram stain visibility
- Cytoplasmic inclusions are a classic descriptor
- Intracellular life cycle (EB infectious, RB replicative) is the mechanism behind many question stems
- Screening matters: many infections are asymptomatic but lead to PID/infertility—Step questions often emphasize silent disease + big consequences
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
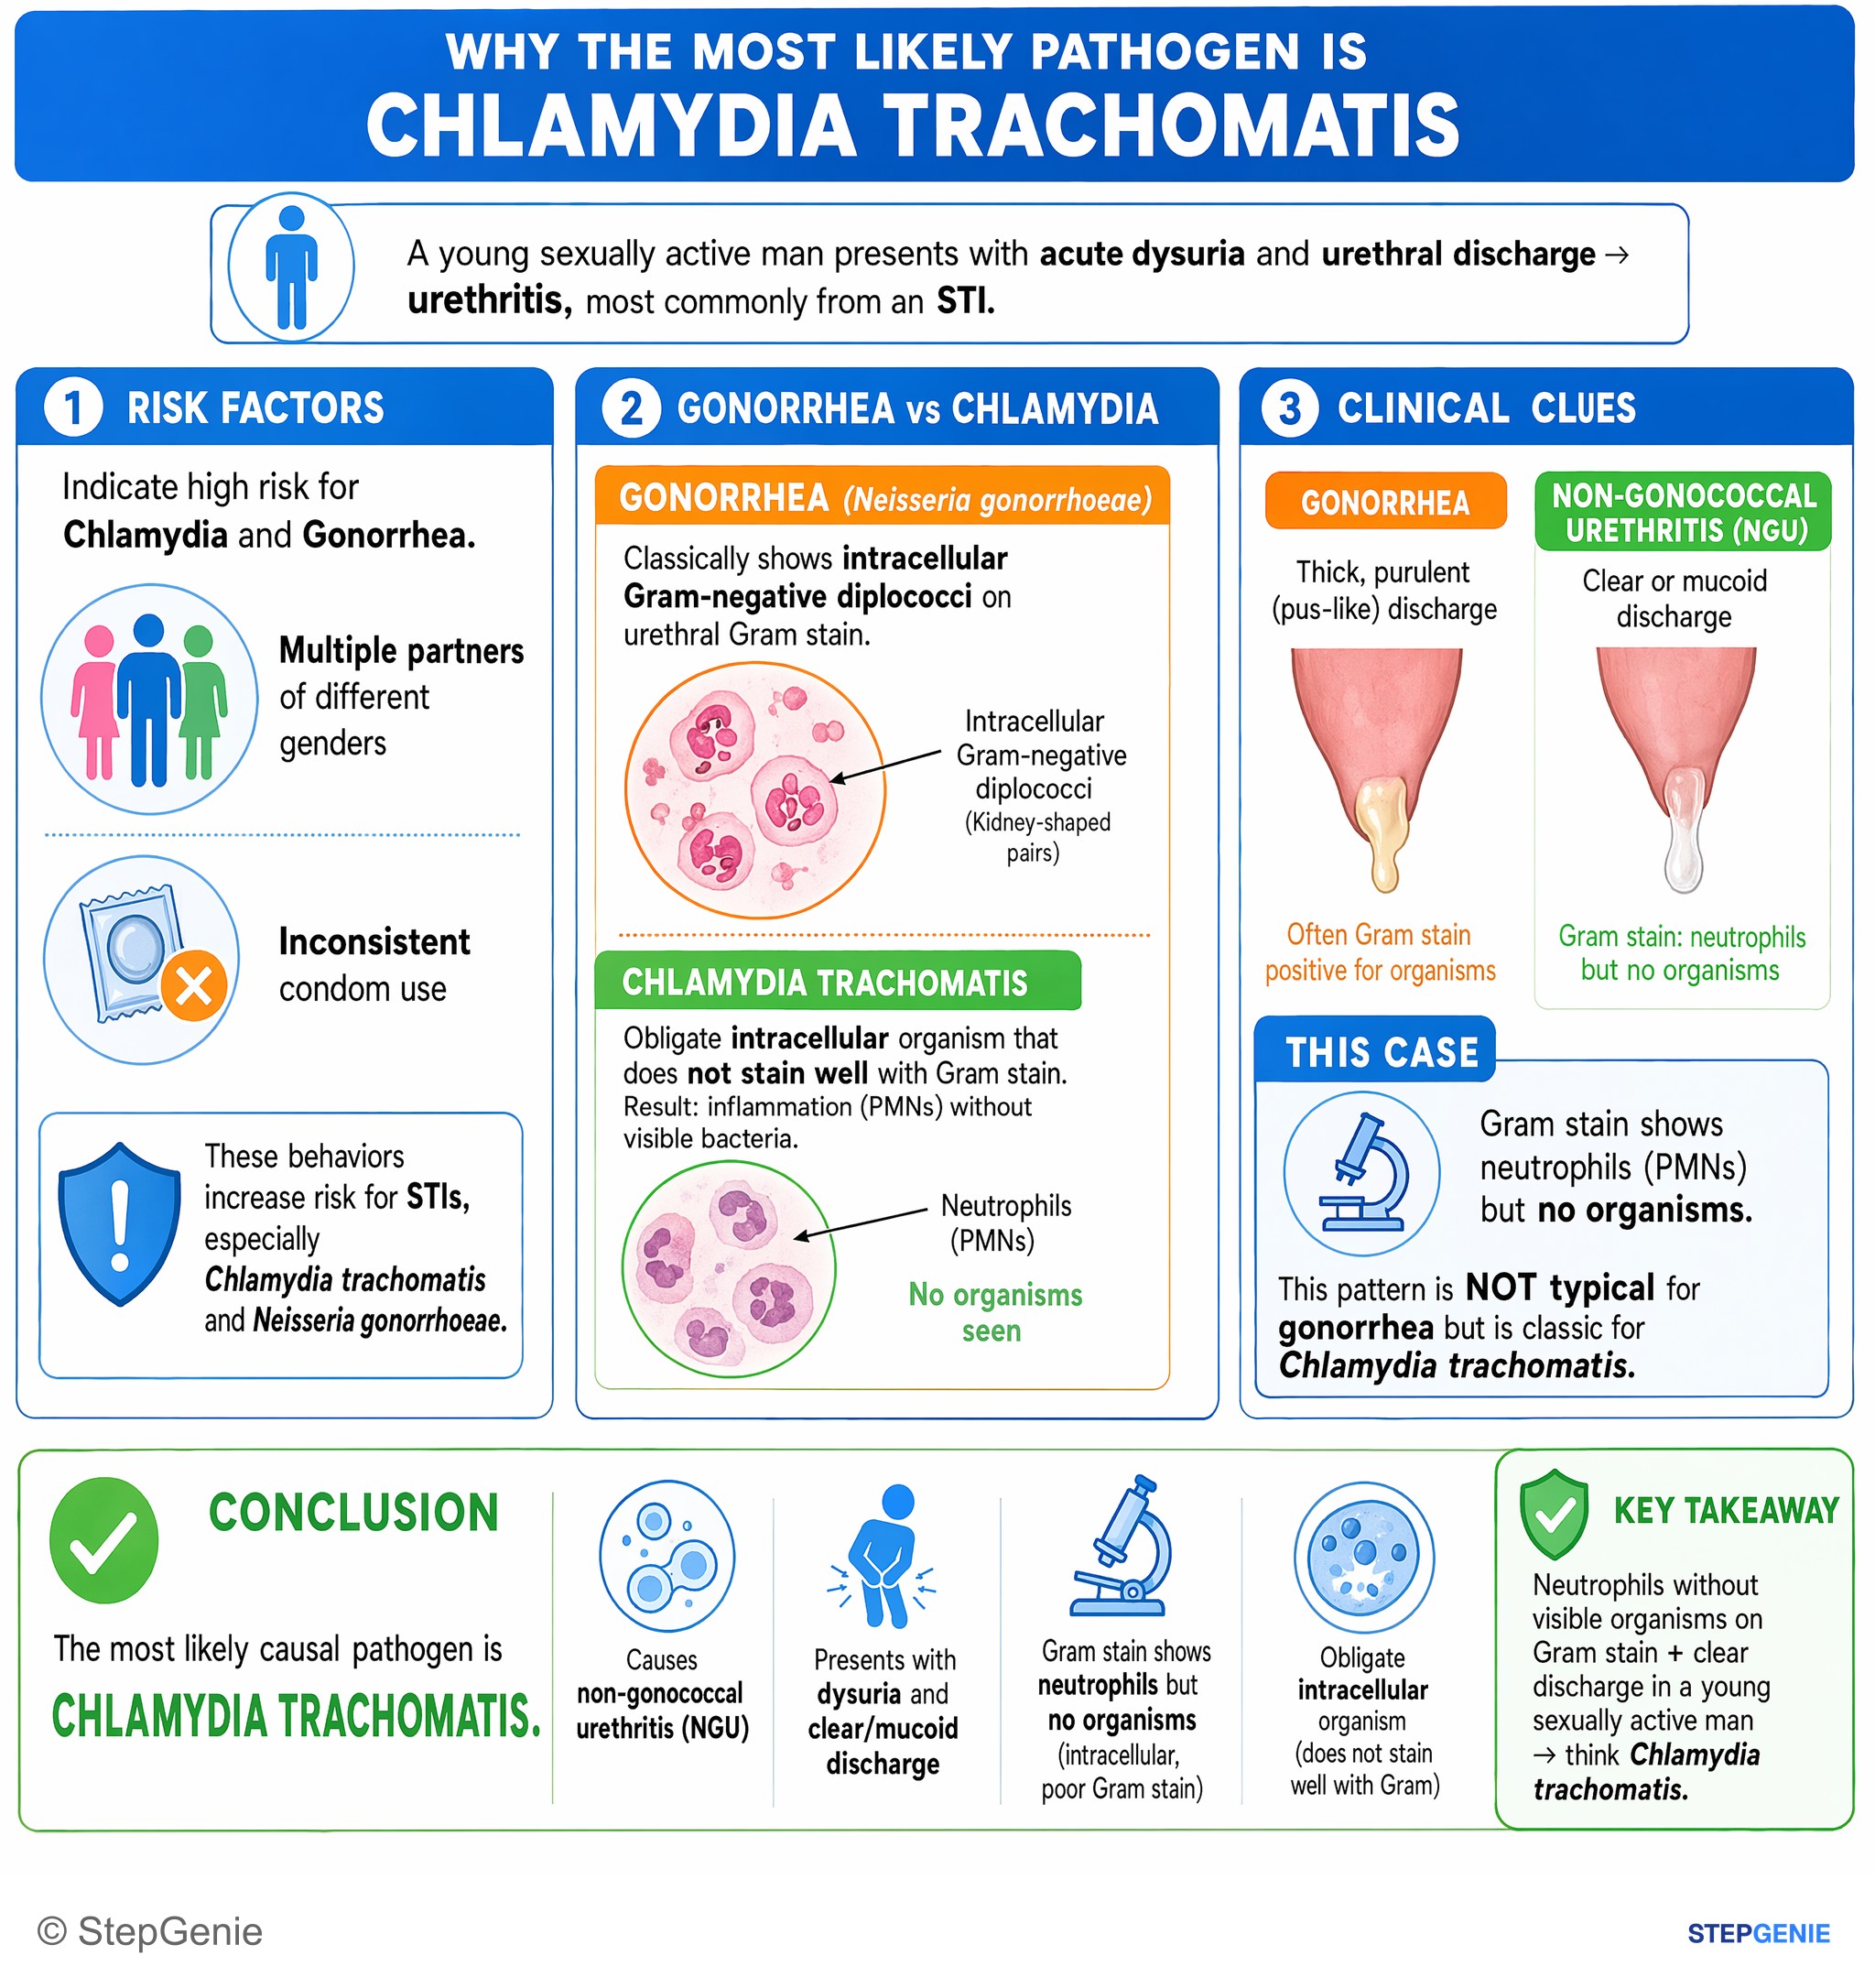
Chlamydia trachomatis causes non-gonococcal urethritis with dysuria and clear discharge; Gram stain shows neutrophils but no organisms…
USMLE Step 1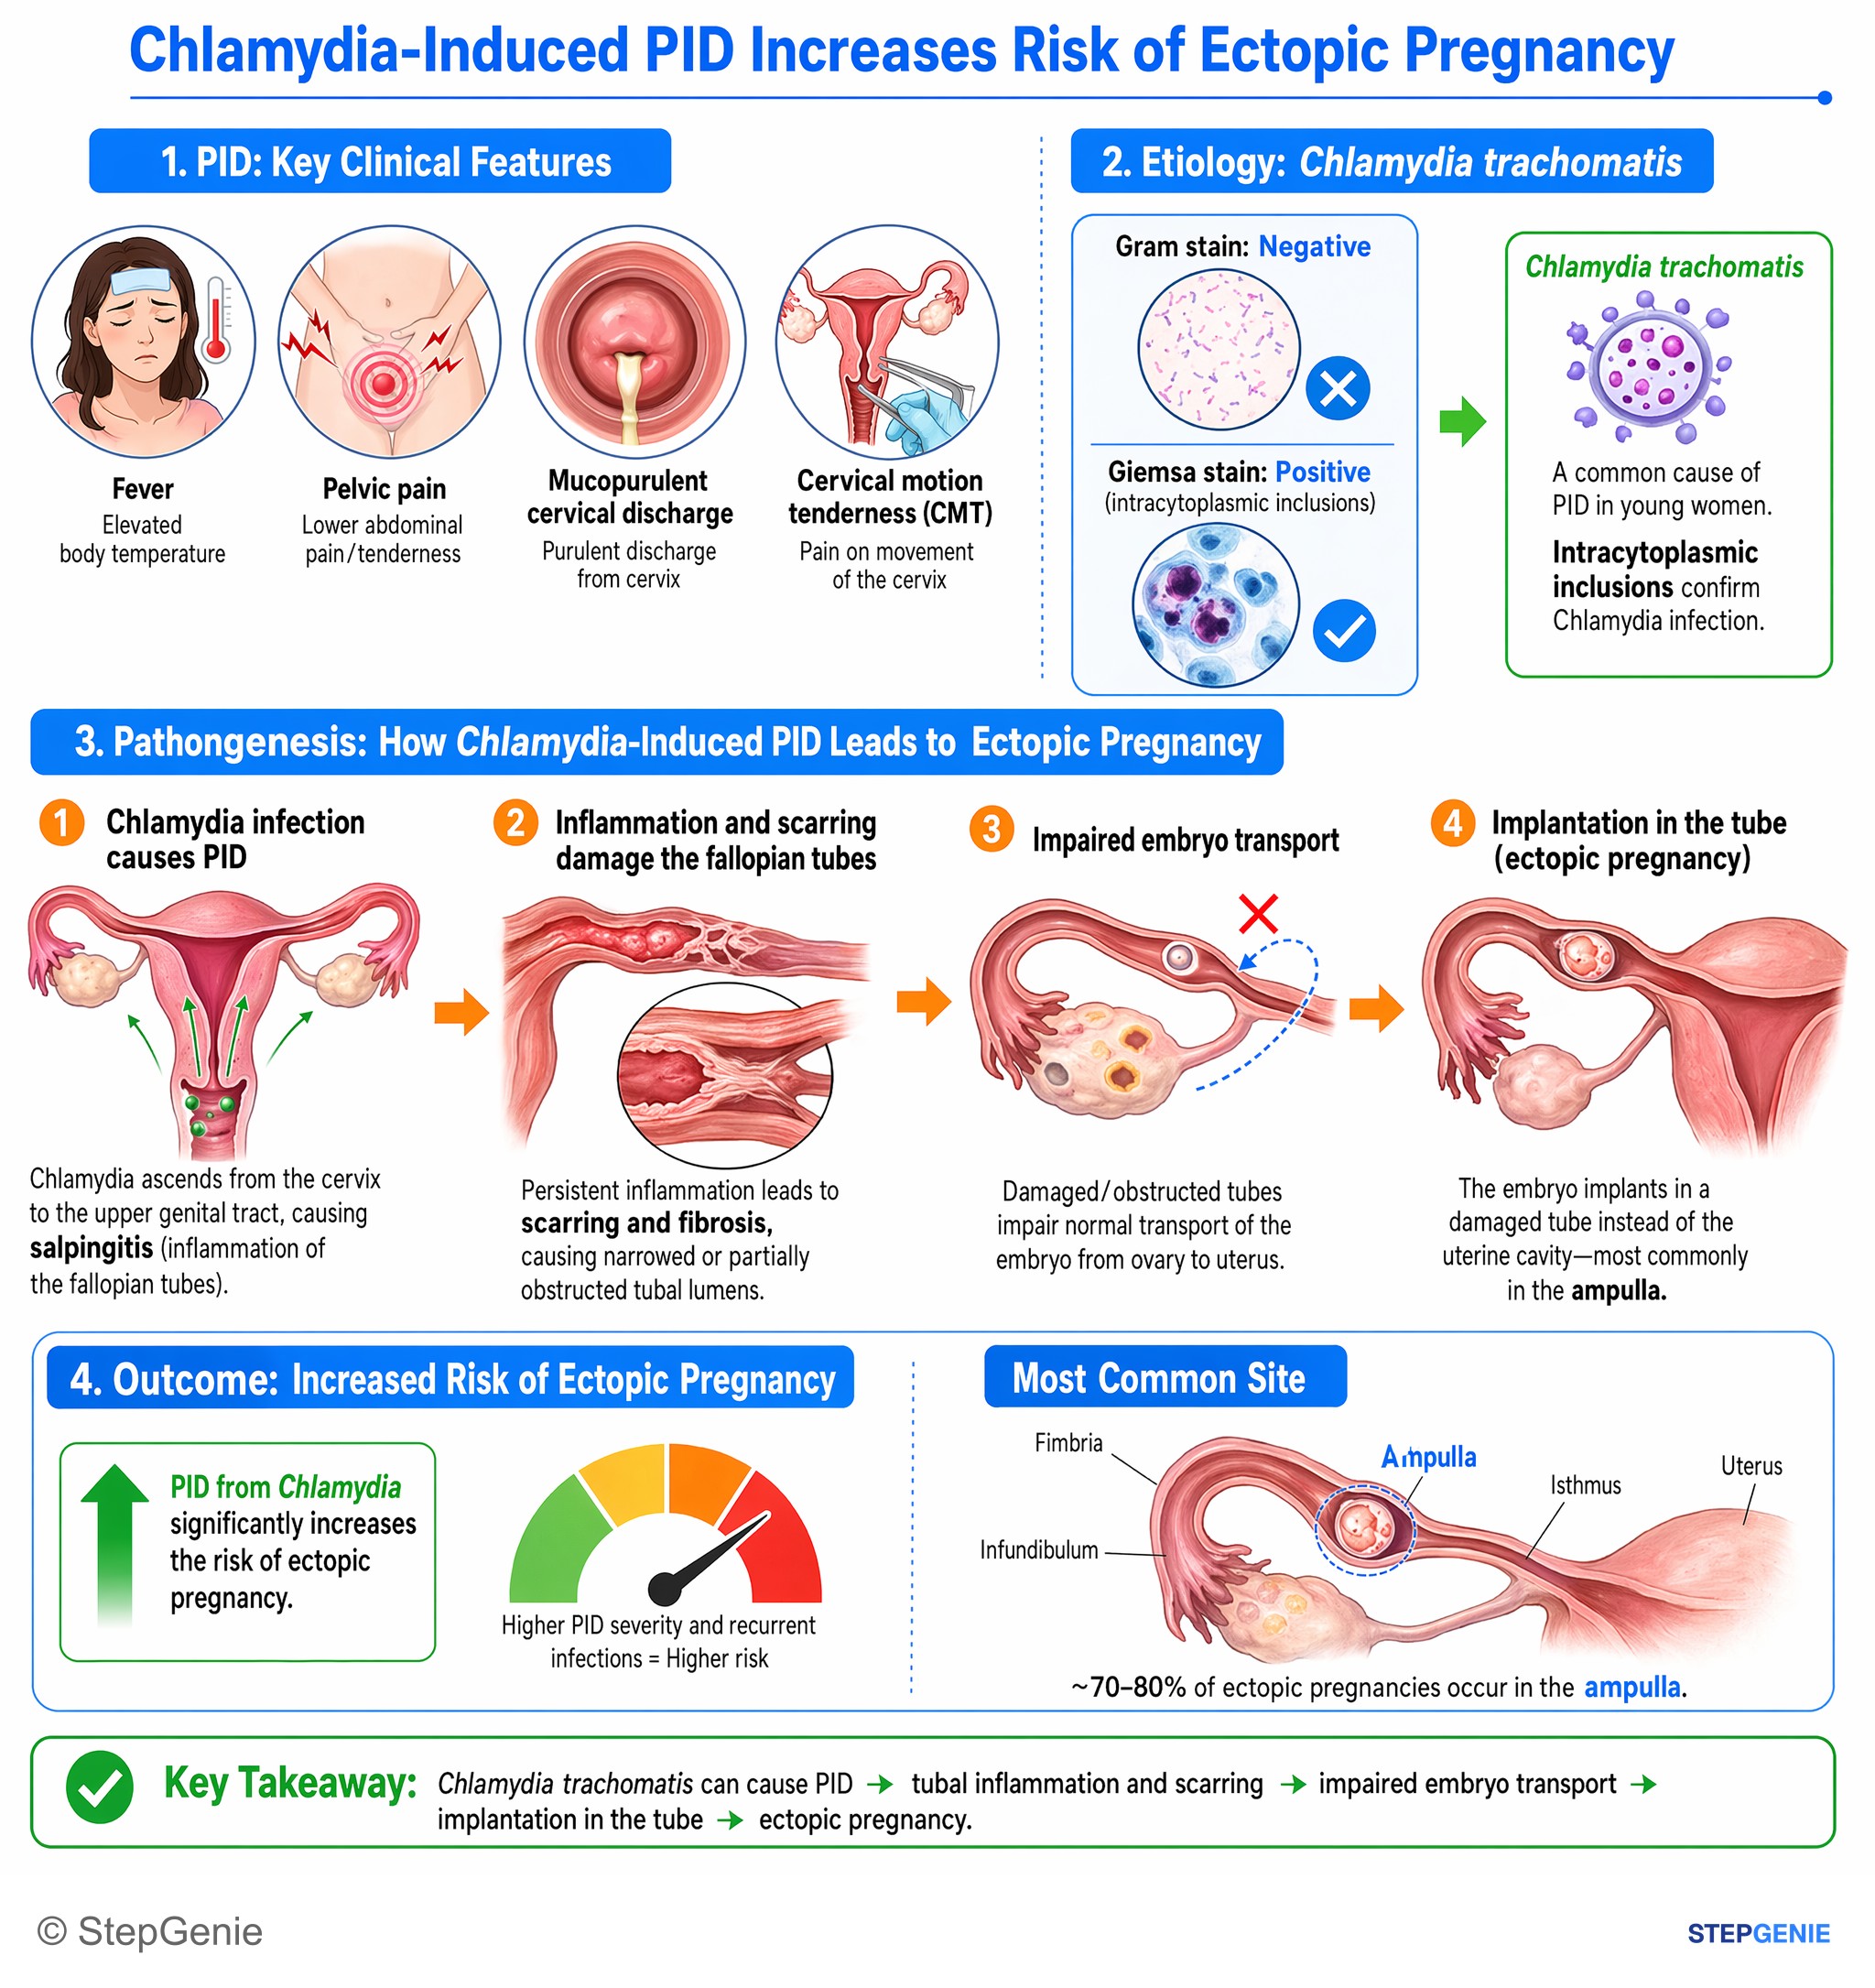
Pelvic inflammatory disease from Chlamydia trachomatis (mucopurulent cervicitis, CMT, intracytoplasmic inclusions) damages tubes → ↑ risk…
USMLE Step 1Frequently Asked Questions
Why is Chlamydia trachomatis an obligate intracellular organism?
Chlamydia trachomatis is obligate intracellular because it cannot make enough ATP and depends on host cells for energy. That energy-parasite biology explains why it must live inside cells and why question stems often emphasize an intracellular organism that cannot be grown on artificial media. Its biphasic life cycle also reflects this intracellular strategy: the elementary body enters cells, then the reticulate body replicates within cytoplasmic inclusions.
How do you tell chlamydial neonatal conjunctivitis from gonococcal conjunctivitis on an exam?
The key distinction is timing after birth. Chlamydial conjunctivitis typically appears 5 to 14 days after delivery, whereas gonococcal conjunctivitis presents earlier, around 2 to 5 days, and chemical conjunctivitis occurs within 24 hours. If the stem also mentions vaginal delivery, purulent conjunctival discharge, or associated neonatal pneumonia later in infancy, that further supports Chlamydia trachomatis.
What is the best test for Chlamydia trachomatis urethritis or cervicitis?
NAAT, often described as PCR, is the best and most sensitive test for chlamydial urethritis or cervicitis. It can be performed on urine or a swab and is the first-line diagnostic answer in typical exam scenarios. Older clues like basophilic cytoplasmic inclusions on Giemsa may appear in stems, but NAAT is the modern test you should pick.
What clinical clues suggest chlamydia in a patient with dysuria?
Dysuria with no nitrites and sterile pyuria is a classic clue for chlamydial infection. Additional findings such as urethritis, cervicitis with a friable cervix, high-risk sexual exposure, or a NAAT-positive partner strengthen the suspicion. On exams, this pattern points to Chlamydia trachomatis serovars D through K as a common cause of sexually transmitted genitourinary infection.
What is the first-line treatment for Chlamydia trachomatis, and do partners need treatment?
For uncomplicated chlamydial cervicitis or urethritis, doxycycline is the common first-line treatment, with azithromycin used in pregnancy or when adherence is a concern. Sexual partners should also be treated, and patients should abstain from sex until therapy is complete. In PID, treatment must also cover gonorrhea and anaerobes, and neonatal disease is treated with a macrolide such as erythromycin or azithromycin.