Legionella questions love to “hide the ball”: the patient looks like they have a routine pneumonia… until the stem drops a clue like hyponatremia, GI symptoms, or recent hotel/cruise exposure. The trick is not just knowing the right answer—it’s knowing why every other option is wrong for this vignette. That’s how you stop missing points on test day.
Microbiology > Gram-Negative Bacteria: The Vignette
A 62-year-old man presents with 4 days of fever, dry cough, and shortness of breath. He also reports watery diarrhea and confusion. He returned last week from a convention where he stayed at a large hotel. Vitals show C, HR 112, RR 26. Exam: diffuse crackles. CXR shows patchy unilateral infiltrates. Labs reveal Na 128 mEq/L and mildly elevated AST/ALT. Sputum Gram stain shows many neutrophils but no organisms.
Question: Which organism is the most likely cause?
The Correct Answer: Legionella pneumophila
Why Legionella fits this stem
This vignette is classic for Legionnaires’ disease (atypical pneumonia) due to Legionella pneumophila:
- Epidemiology/exposure: aerosolized water from hotels, hospitals, cruise ships, air conditioning systems, hot tubs
- Clinical pattern (high-yield triad-ish):
- Atypical pneumonia (fever, dry cough, patchy infiltrates)
- GI symptoms (especially diarrhea)
- Neurologic symptoms (confusion)
- Lab associations: hyponatremia (often from SIADH), elevated LFTs
- Gram stain clue: “many PMNs but no organisms” → suggests an organism that doesn’t stain well on Gram stain (and/or is intracellular)
Micro pearls you’re expected to know
Legionella pneumophila
- Gram-negative bacillus (but poorly visualized on routine Gram stain)
- Facultative intracellular pathogen that replicates in macrophages
- Culture: requires BCYE agar (buffered charcoal yeast extract) with iron and cysteine
- Diagnosis (commonly tested):
- Urinary antigen (classically detects L. pneumophila serogroup 1)
- PCR/NAAT (in many real-world settings)
- Treatment:
- Azithromycin or a respiratory fluoroquinolone (e.g., levofloxacin)
- (Doxycycline is sometimes used, but macrolide/fluoroquinolone are the go-to board answers.)
Why the Distractors Are Wrong (and How They Try to Trick You)
Below are common answer choices tested against this exact clinical pattern.
Distractor 1: Streptococcus pneumoniae
Why students pick it: Most common cause of community-acquired pneumonia; fever + infiltrate.
Why it’s wrong here:
- Typically productive cough with rust-colored sputum
- No strong association with diarrhea, hyponatremia, or confusion as “signature” clues
- Gram stain usually shows Gram-positive lancet-shaped diplococci, not “no organisms”
- Risk clue differences: asplenia, sickle cell, elderly, alcoholism—none as specific as hotel water exposure
Board takeaway: If the stem screams atypical + GI + hyponatremia, stop defaulting to pneumococcus.
Distractor 2: Mycoplasma pneumoniae
Why students pick it: Atypical pneumonia with minimal sputum; “walking pneumonia.”
Why it’s wrong here:
- Classic population: teens/young adults, close quarters (dorms, military barracks)
- Hallmarks: bullous myringitis, cold agglutinins → hemolytic anemia
- Doesn’t classically cause hyponatremia or prominent diarrhea
- CXR can show diffuse interstitial pattern, but the stem’s water exposure + hyponatremia is more Legionella-coded
Board takeaway: Mycoplasma is atypical, but Legionella is atypical + systemic (GI/Na/LFTs).
Distractor 3: Klebsiella pneumoniae
Why students pick it: Severe pneumonia in older patients; high fever; looks sick.
Why it’s wrong here:
- Strong association with alcohol use disorder, aspiration risk, diabetes
- Currant jelly sputum and upper lobe necrotizing pneumonia are classic clues
- Gram stain would show Gram-negative rods
- Not linked to hotel AC/water systems or hyponatremia-diarrhea combo
Board takeaway: Think Klebsiella when you see aspiration risk + currant jelly + upper lobe.
Distractor 4: Pseudomonas aeruginosa
Why students pick it: Gram-negative pathogen associated with water.
Why it’s wrong here:
- Pneumonia typically in:
- Cystic fibrosis
- Ventilated patients
- Burn patients
- Neutropenia
- Would be seen on Gram stain as Gram-negative rods
- “Water” clue for Pseudomonas is often hot tubs (folliculitis), contact lens keratitis, or hospital equipment—less “hotel outbreak pneumonia + hyponatremia”
Board takeaway: Pseudomonas pneumonia is usually healthcare-associated or structural lung disease, not convention-hotel atypical pneumonia.
Distractor 5: Haemophilus influenzae
Why students pick it: Common respiratory pathogen, especially in COPD.
Why it’s wrong here:
- More typical in COPD exacerbations, otitis media, sinusitis
- Gram stain: small pleomorphic Gram-negative coccobacilli
- No classic association with diarrhea + hyponatremia
- Exposure clue doesn’t match
Board takeaway: In pneumonia stems, H. influenzae often pairs with COPD/smoking and purulent sputum.
Distractor 6: Chlamydia pneumoniae
Why students pick it: Another atypical pneumonia cause.
Why it’s wrong here:
- Often mild, prolonged course; can include hoarseness or pharyngitis
- No classic hyponatremia or prominent diarrhea
- “Many PMNs but no organisms” is less emphasized than for Legionella (and exposure history is not water-system linked)
Board takeaway: For atypical pneumonias, history is the differentiator—Legionella loves water systems.
High-Yield “Legionella vs Others” Cheat Table
| Feature | Legionella pneumophila | Mycoplasma pneumoniae | Strep pneumoniae | Klebsiella pneumoniae |
|---|---|---|---|---|
| Pneumonia type | Atypical | Atypical (“walking”) | Typical CAP | Typical, severe |
| Key clues | Diarrhea, confusion, hyponatremia, ↑LFTs; hotel/cruise/hospital water | Cold agglutinins, bullous myringitis; young adults | Rust sputum, lobar consolidation | Currant jelly sputum; alcoholism/aspiration |
| Gram stain | PMNs, no organisms (poor staining) | No cell wall (won’t Gram stain) | G+ diplococci | G− rods |
| Culture | BCYE (iron, cysteine) | Eaton agar (rarely tested) | Standard media | Standard media |
| Treatment | Azithro or levofloxacin | Azithro/doxy | Ceftriaxone/amoxicillin (depending) | Ceftriaxone; broader if severe/ESBL risk |
Test-Day Pattern Recognition (What to Circle Mentally)
When you see pneumonia + systemic findings, ask:
1) Any exposure to aerosolized water?
- Hotel, cruise ship, hospital, air-conditioning cooling towers, humidifiers → Legionella
2) Any “extra-pulmonary” clues?
- Diarrhea
- Confusion
- Hyponatremia (SIADH)
- Elevated LFTs
If yes → Legionella until proven otherwise
3) Gram stain: “lots of neutrophils, no organisms”
- Think atypical organisms; Legionella is a top-tier pick when paired with the right history/labs.
Rapid-Fire USMLE Facts You Can Use Immediately
- Legionella = Gram-negative, facultative intracellular, macrophages, BCYE, urine antigen
- “Pontiac fever” = milder, flu-like illness without pneumonia (still Legionella exposure)
- Treat with macrolide or fluoroquinolone (good intracellular penetration)
- Don’t get baited by “water” alone: match setting + symptoms + labs
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.

Legionella pneumophila causes severe pneumonia with GI symptoms, confusion, and hyponatremia; it is isolated on charcoal yeast extract…
USMLE Step 1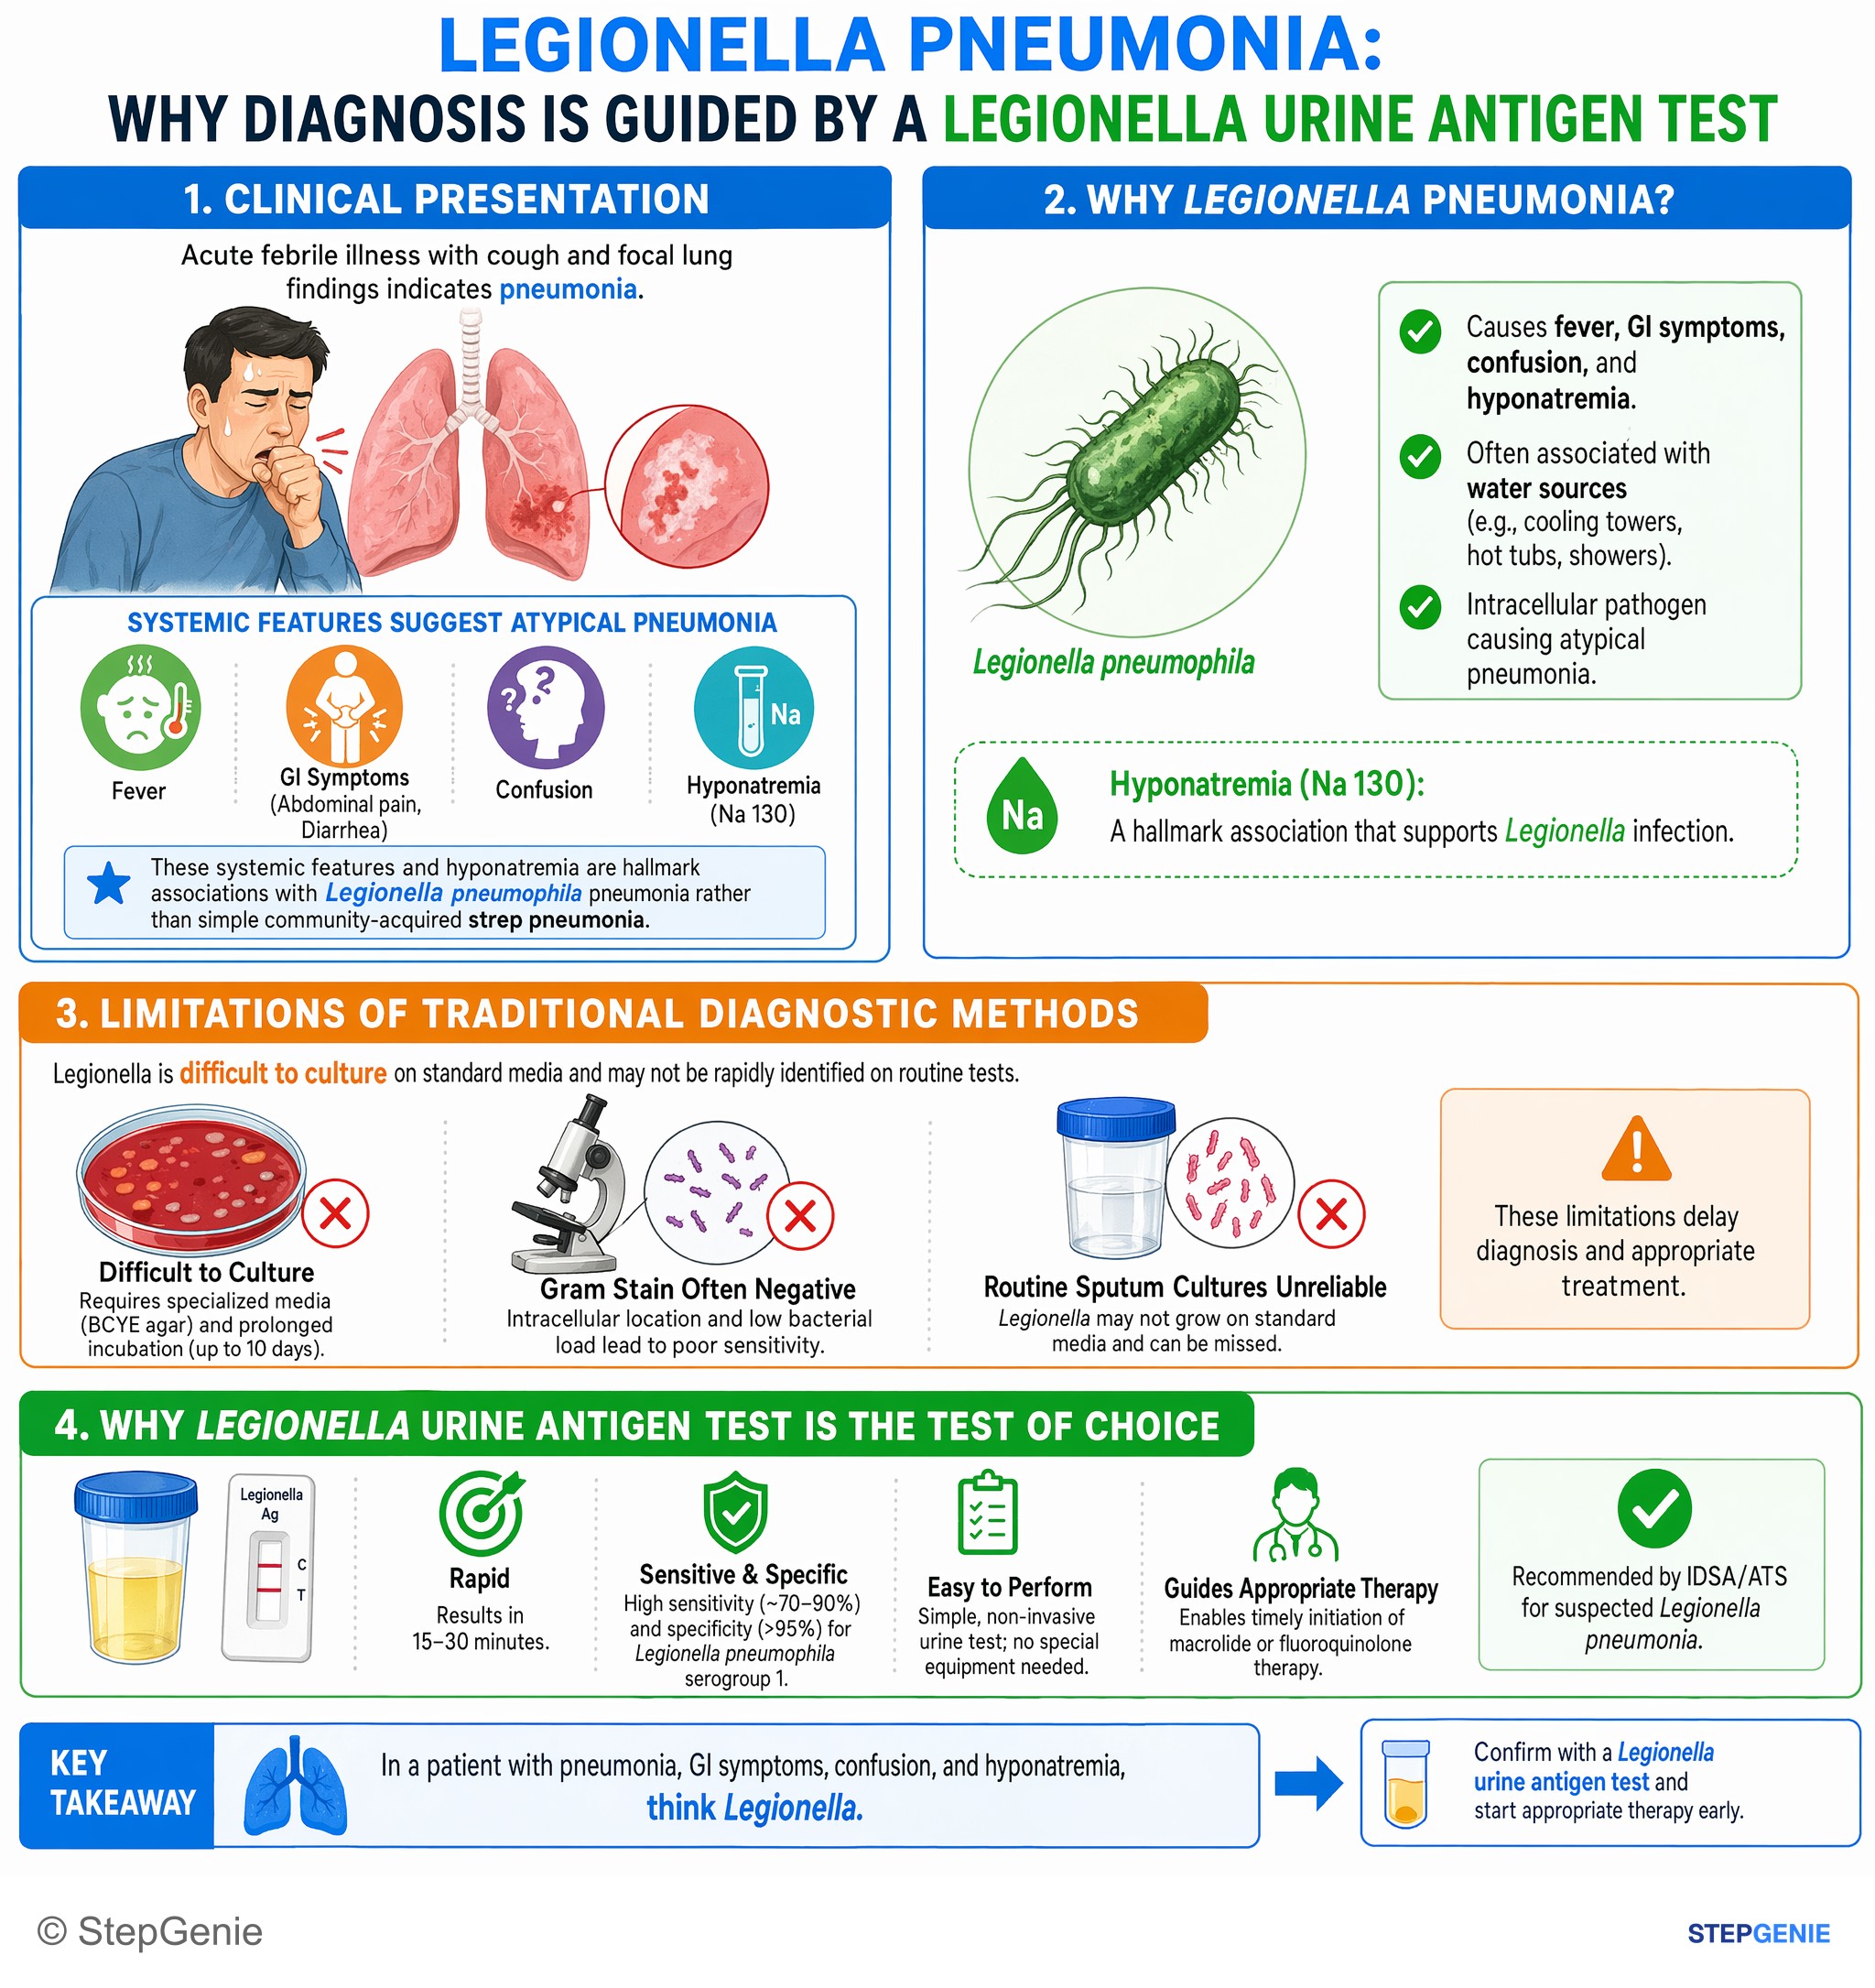
Legionella pneumonia causes fever, GI symptoms, confusion, and hyponatremia; diagnosis is guided by a Legionella urine antigen test.
USMLE Step 2Frequently Asked Questions
What clues in a pneumonia question point to Legionella pneumophila instead of routine community-acquired pneumonia?
Legionella pneumophila is suggested by atypical pneumonia plus systemic clues like watery diarrhea, confusion, hyponatremia, mildly elevated liver enzymes, and recent exposure to aerosolized water from places such as hotels, hospitals, cruise ships, air conditioning systems, or hot tubs. A dry cough with patchy infiltrates and a sputum Gram stain showing many neutrophils but no organisms also supports Legionella over a more routine bacterial pneumonia.
Why does Legionella show many neutrophils but no organisms on Gram stain?
The key reason is that Legionella is poorly visualized on routine Gram stain. It is a gram-negative bacillus, but the organism often does not show up well despite an inflammatory response, so the sputum can have many neutrophils without visible bacteria. This pattern also fits an organism that does not stain well and may be intracellular.
How do you tell Legionella pneumonia from Mycoplasma pneumoniae on a vignette?
Legionella is favored when atypical pneumonia comes with water-system exposure, hyponatremia, diarrhea, confusion, and elevated liver enzymes. Mycoplasma pneumoniae is more typical in teens or young adults living in close quarters and is associated with bullous myringitis and cold agglutinins causing hemolytic anemia. Both can cause atypical pneumonia, but Legionella is the one linked to more prominent systemic findings.
What is the best test and treatment for Legionella pneumophila?
A commonly tested diagnostic test is the urinary antigen, which classically detects Legionella pneumophila serogroup 1. PCR or other nucleic acid testing may also be used in practice. The go-to treatments are azithromycin or a respiratory fluoroquinolone such as levofloxacin. The organism can also be cultured on BCYE agar, which requires iron and cysteine.
How do you distinguish Legionella from Streptococcus pneumoniae in a pneumonia stem?
Legionella is more likely when the stem emphasizes atypical pneumonia with diarrhea, hyponatremia, confusion, and hotel or water exposure. Streptococcus pneumoniae more often causes productive cough with rust-colored sputum and would usually appear on Gram stain as gram-positive lancet-shaped diplococci. If the question says many neutrophils but no organisms and adds systemic clues, Legionella is the better fit.