Lyme disease is infection with the spirochete Borrelia burgdorferi, spread by Ixodes (blacklegged) ticks in the Northeast, mid-Atlantic and upper Midwest, and in smaller areas of the Pacific coast; tiny nymphs, active from April through July, pose the highest risk. Its classic first sign is erythema migrans (EM): an expanding red rash at the bite site 3-30 days later (about 7 days on average) in 70-80% of infected people, diagnosed clinically without serology. Untreated, it can disseminate to cause multiple EM lesions, facial palsy (sometimes bilateral), lymphocytic meningitis, radiculoneuritis and fluctuating AV block, and later knee arthritis. EM is treated with doxycycline for 10 days (amoxicillin or cefuroxime for 14 days are alternatives) under the 2020 IDSA/AAN/ACR guideline, and no Lyme vaccine is licensed for people in the US as of October 2026.
The vignette
A 28-year-old woman comes to the clinic in July with 4 days of fatigue, headache, muscle aches and low-grade fever. Ten days ago she hiked and camped in Connecticut, and she later found and removed a tiny tick from her leg. On her posterior thigh is an 11-cm, oval, red patch with partial central clearing that has enlarged over several days; it is warm but neither itchy nor painful. Temperature is 37.9°C (100.2°F); other vital signs are normal. There are no mucosal lesions, and the palms and soles are spared. CBC and liver enzymes are normal.
Which organism is the most likely cause?
A. Anaplasma phagocytophilum B. Babesia microti C. Borrelia burgdorferi D. Leptospira interrogans E. Rickettsia rickettsii F. Treponema pallidum
Answer: C. Borrelia burgdorferi.
| Clue in the stem | What it tells you |
|---|---|
| July, hiking in Connecticut, tiny tick | Ixodes scapularis territory; poppy-seed-sized nymphs are active April through July |
| Expanding red patch at the bite site, 10 days later | Erythema migrans: begins 3-30 days after the bite and expands over days; warm, rarely itchy or painful |
| Partial central clearing | Some EM lesions develop a bull's-eye, but many have no central clearing |
| Fever, fatigue, headache, myalgia | Early localized Lyme disease |
| Normal CBC and liver enzymes; palms, soles and mucosa spared | Argues against anaplasmosis, ehrlichiosis, RMSF and secondary syphilis |
Why every answer choice matters
A. Anaplasma phagocytophilum (anaplasmosis)
- Why it tempts: the same Ixodes ticks spread it in the same regions, and it causes fever, chills, headache and myalgia.
- Why it is wrong: rash is rare, and the labs give it away: leukopenia, thrombocytopenia and raised liver enzymes, with morulae in neutrophils. Its cousin Ehrlichia chaffeensis comes from the lone star tick in the southeastern and south-central US, infects monocytes and sometimes causes a rash. Both are treated with doxycycline at all ages, and coinfection with Lyme disease is possible.
B. Babesia microti (babesiosis)
- Why it tempts: same tick, same places (the islands and mainland around Nantucket Sound, eastern Long Island, coastal Connecticut, and foci in Wisconsin and Minnesota, among others), and a classic Lyme coinfection.
- Why it is wrong: Babesia is a red-cell protozoan. It causes prolonged fever with hemolytic anemia (jaundice and dark urine when severe), not EM. The smear shows intraerythrocytic parasites, sometimes as tetrads ("Maltese cross"), with no pigment. Disease is worse in asplenic patients, older adults and people with advanced HIV, and it can spread by transfusion. Treat with atovaquone plus azithromycin (quinine plus clindamycin is the alternative); exchange transfusion has been used in severe illness with high-grade (more than 10%) parasitemia. Compare the smear with Plasmodium species.
C. Borrelia burgdorferi (correct)
- EM at a tick-bite site after a summer exposure in an endemic state is diagnostic of early Lyme disease. Ticks pick up the spirochete from rodents; deer feed adult ticks but are not infected. In most cases the tick must stay attached for more than 24 hours to transmit it.
D. Leptospira interrogans (leptospirosis)
- Why it tempts: another spirochete, with fever, headache and myalgia after outdoor exposure.
- Why it is wrong: it comes from contact with infected animal urine, directly or through contaminated water or soil, not from ticks. Look for conjunctival suffusion on day 3-4, a biphasic illness, and in severe cases Weil syndrome (jaundice, kidney injury, bleeding). Mild disease gets doxycycline; severe disease, IV penicillin G or ceftriaxone. More in the Leptospira breakdown.
E. Rickettsia rickettsii (Rocky Mountain spotted fever)
- Why it tempts: a summer tick-borne illness with fever, headache and rash.
- Why it is wrong: the main vectors are Dermacentor ticks (the dog tick in the east, center and south; the wood tick in the west), the brown dog tick also spreads it in some areas, and more than 60% of US cases are reported from North Carolina, Oklahoma, Arkansas, Tennessee and Missouri. The rash typically starts on the wrists, ankles, palms, soles and forearms, spreads centrally and turns petechial; about 90% of patients have it by the sixth day of fever, so a missing rash early on does not rule out RMSF. Doxycycline is first-line for all patients, including children and pregnant patients.
F. Treponema pallidum (syphilis)
- Why it tempts: a spirochete that causes rash and systemic symptoms.
- Why it is wrong: it is sexually transmitted. Primary syphilis is a painless, firm-based chancre 3-4 weeks after exposure; secondary syphilis, 6-12 weeks after the chancre, brings a symmetric rash most marked on the palms and soles, plus condylomata lata. Screen with RPR or VDRL and confirm with a treponemal test; treat with benzathine penicillin G and warn about the Jarisch-Herxheimer reaction (fever, rigors, headache within 6-12 hours, settling within 24 hours). Review the syphilis stages.
Follow-up: what should you do for her?
Her urine pregnancy test is negative. Which is the most appropriate next step? A. Oral doxycycline for 10 days. B. Two-tier Lyme serology, treating only if positive. C. IV ceftriaxone for 14 days. D. A single 200-mg dose of doxycycline. E. Oral azithromycin for 7 days.
Answer: A. Typical EM in an endemic area is a clinical diagnosis: treat now.
- B: antibodies take weeks to develop, so early serology is often negative; CDC advises treating likely EM promptly whether or not a test is sent.
- C: IV ceftriaxone is for patients hospitalized with severe carditis and for some neurologic disease, not uncomplicated EM.
- D: one 200-mg dose is prophylaxis after a high-risk bite (identified Ixodes tick, highly endemic area, attached at least 36 hours, given within 72 hours of removal), not treatment of an established infection.
- E: azithromycin is second-line because it is less effective; patients who take it need close follow-up.
Lyme disease by stage
| Stage | Findings | Treatment (IDSA/AAN/ACR 2020; CDC) |
|---|---|---|
| Early localized (3-30 days) | EM, sometimes with fever, chills, headache, fatigue, myalgia, arthralgia, lymphadenopathy | Doxycycline 10 days; amoxicillin or cefuroxime 14 days; azithromycin is second-line |
| Early disseminated (days to months) | Multiple EM; facial palsy, which can be bilateral; lymphocytic meningitis; radiculoneuritis; carditis with fluctuating AV block | Facial palsy: oral doxycycline 14-21 days. Meningitis or radiculoneuritis: oral doxycycline or IV ceftriaxone, 14-21 days. Carditis: oral if mild (PR under 300 ms); admit for monitoring and IV ceftriaxone if PR is 300 ms or longer, symptoms are present or block is second or third degree, then finish 14-21 days orally; temporary pacing, not a permanent pacemaker |
| Late (1 to a few months, occasionally up to 2 years) | Arthritis of one or a few large joints, usually the knee, much more swollen than painful; positive IgG serology (antibody tests are highly sensitive at this stage) | Oral doxycycline, amoxicillin or cefuroxime for 28 days; little or no response, IV ceftriaxone for 2-4 weeks; still active after antibiotics, rheumatology for DMARDs or synovectomy |
- How often: of every 100 cases reported to CDC, 9 have facial palsy, 4 radiculopathy and 3 meningitis or encephalitis; carditis occurs in about 1 in 100. Heart block can worsen fast, so check an ECG when cardiac symptoms appear, and see the AV block cheat sheet.
- Neurologic Lyme disease is one of the lymphocytic meningitides in the bacterial vs viral meningitis guide.
- Lyme arthritis vs septic arthritis: a big, relatively painless knee effusion with positive Lyme IgG serology points to Lyme; a hot, exquisitely painful joint needs aspiration for septic arthritis. PCR of synovial fluid is often positive in Lyme arthritis.
Testing, prevention and vaccine status
- Two-tier serology is for disseminated or late disease, not typical EM. Standard: enzyme immunoassay (EIA) then Western blot. Modified: two different EIAs. Disregard a positive IgM result if the patient has been ill for more than 30 days, and do not use titers as a test of cure, because antibodies persist for months to years. For CNS disease, test CSF and serum together for an antibody index rather than CSF alone.
- Post-treatment Lyme disease syndrome: fatigue, aches or cognitive complaints can persist after appropriate treatment; without objective evidence of active infection, IDSA recommends against more antibiotics.
- Burden: more than 80,000 cases are reported to CDC each year, and an insurance-claims estimate suggests about 476,000 people are treated each year (CDC notes this may be an overestimate).
- Vaccine (as of October 2026): no Lyme vaccine is licensed for people in the US. Pfizer and Valneva's 6-valent OspA vaccine, PF-07307405, reported about 73-75% efficacy (with wide confidence intervals; the first of two prespecified analyses missed its statistical success criterion) in people aged 5 and older in the phase 3 VALOR trial in March 2026, and the European Medicines Agency validated its marketing application in August 2026.
How USMLE tests it
- A bull's-eye is not required: many EM lesions are uniformly red.
- Never wait for serology to treat EM.
- Bilateral facial palsy in summer in an endemic area suggests Lyme disease.
- A young adult with fluctuating AV block after a tick season: Lyme carditis; treat with antibiotics and use temporary pacing if needed, not a permanent pacemaker.
- EM-like rash after a lone star tick bite in the South: STARI (southern tick-associated rash illness). Its cause is unknown, and studies show it is not caused by B. burgdorferi.
- Lyme plus hemolytic anemia or plus cytopenias and high liver enzymes: think Babesia or Anaplasma coinfection.
- Children and pregnancy: IDSA (2020) notes a growing consensus that doxycycline courses of up to 14 days are safe in young children, and CDC lists pediatric doxycycline doses with no age cutoff, whereas Merck still avoids doxycycline under age 8; amoxicillin or cefuroxime sidestep the issue. In pregnancy, IDSA individualizes the choice and Merck uses amoxicillin.
Key takeaways
- Ixodes tick + Northeast, mid-Atlantic or upper Midwest + expanding rash = erythema migrans = Borrelia burgdorferi; treat on sight.
- Early disseminated: multiple EM, facial palsy (can be bilateral), lymphocytic meningitis, radiculoneuritis, fluctuating AV block. Late: knee arthritis.
- Doxycycline 10 days for EM; amoxicillin or cefuroxime 14 days; IV ceftriaxone for hospitalized carditis and selected neurologic disease; oral doxycycline also works for meningitis and facial palsy.
- Mimics: Anaplasma (cytopenias, high liver enzymes, neutrophil morulae), Babesia (hemolysis, Maltese cross), RMSF (Dermacentor, wrists and ankles to palms and soles), Leptospira (animal urine, conjunctival suffusion), syphilis (sexual, painless chancre, palm and sole rash).
- Prophylaxis: one 200-mg doxycycline dose within 72 hours only after a high-risk Ixodes bite.
- No licensed Lyme vaccine for people in the US (October 2026); PF-07307405 is under EU review.
Sources
- AAN/ACR/IDSA 2020 Guidelines for the Prevention, Diagnosis and Treatment of Lyme Disease — Infectious Diseases Society of America (2020)
- Lyme Disease Signs and Symptoms — CDC (2024)
- How Lyme Disease Spreads — CDC (2024)
- Clinical Testing and Diagnosis for Lyme Disease — CDC (2024)
- Clinical Treatment of Erythema Migrans Rash — CDC (2026)
- Clinical Care and Treatment of Lyme Carditis — CDC (2026)
- Neurologic Lyme Disease — CDC (2025)
- Lyme Arthritis — CDC (2024)
- Lyme Disease — Merck Manual Professional Edition (2026)
- Vaccines Licensed for Use in the United States — U.S. Food and Drug Administration (2026)
- Rocky Mountain Spotted Fever — Merck Manual Professional Edition (2026)
- Lyme Disease Vaccine Program (VLA15/PF-07307405) — Valneva (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
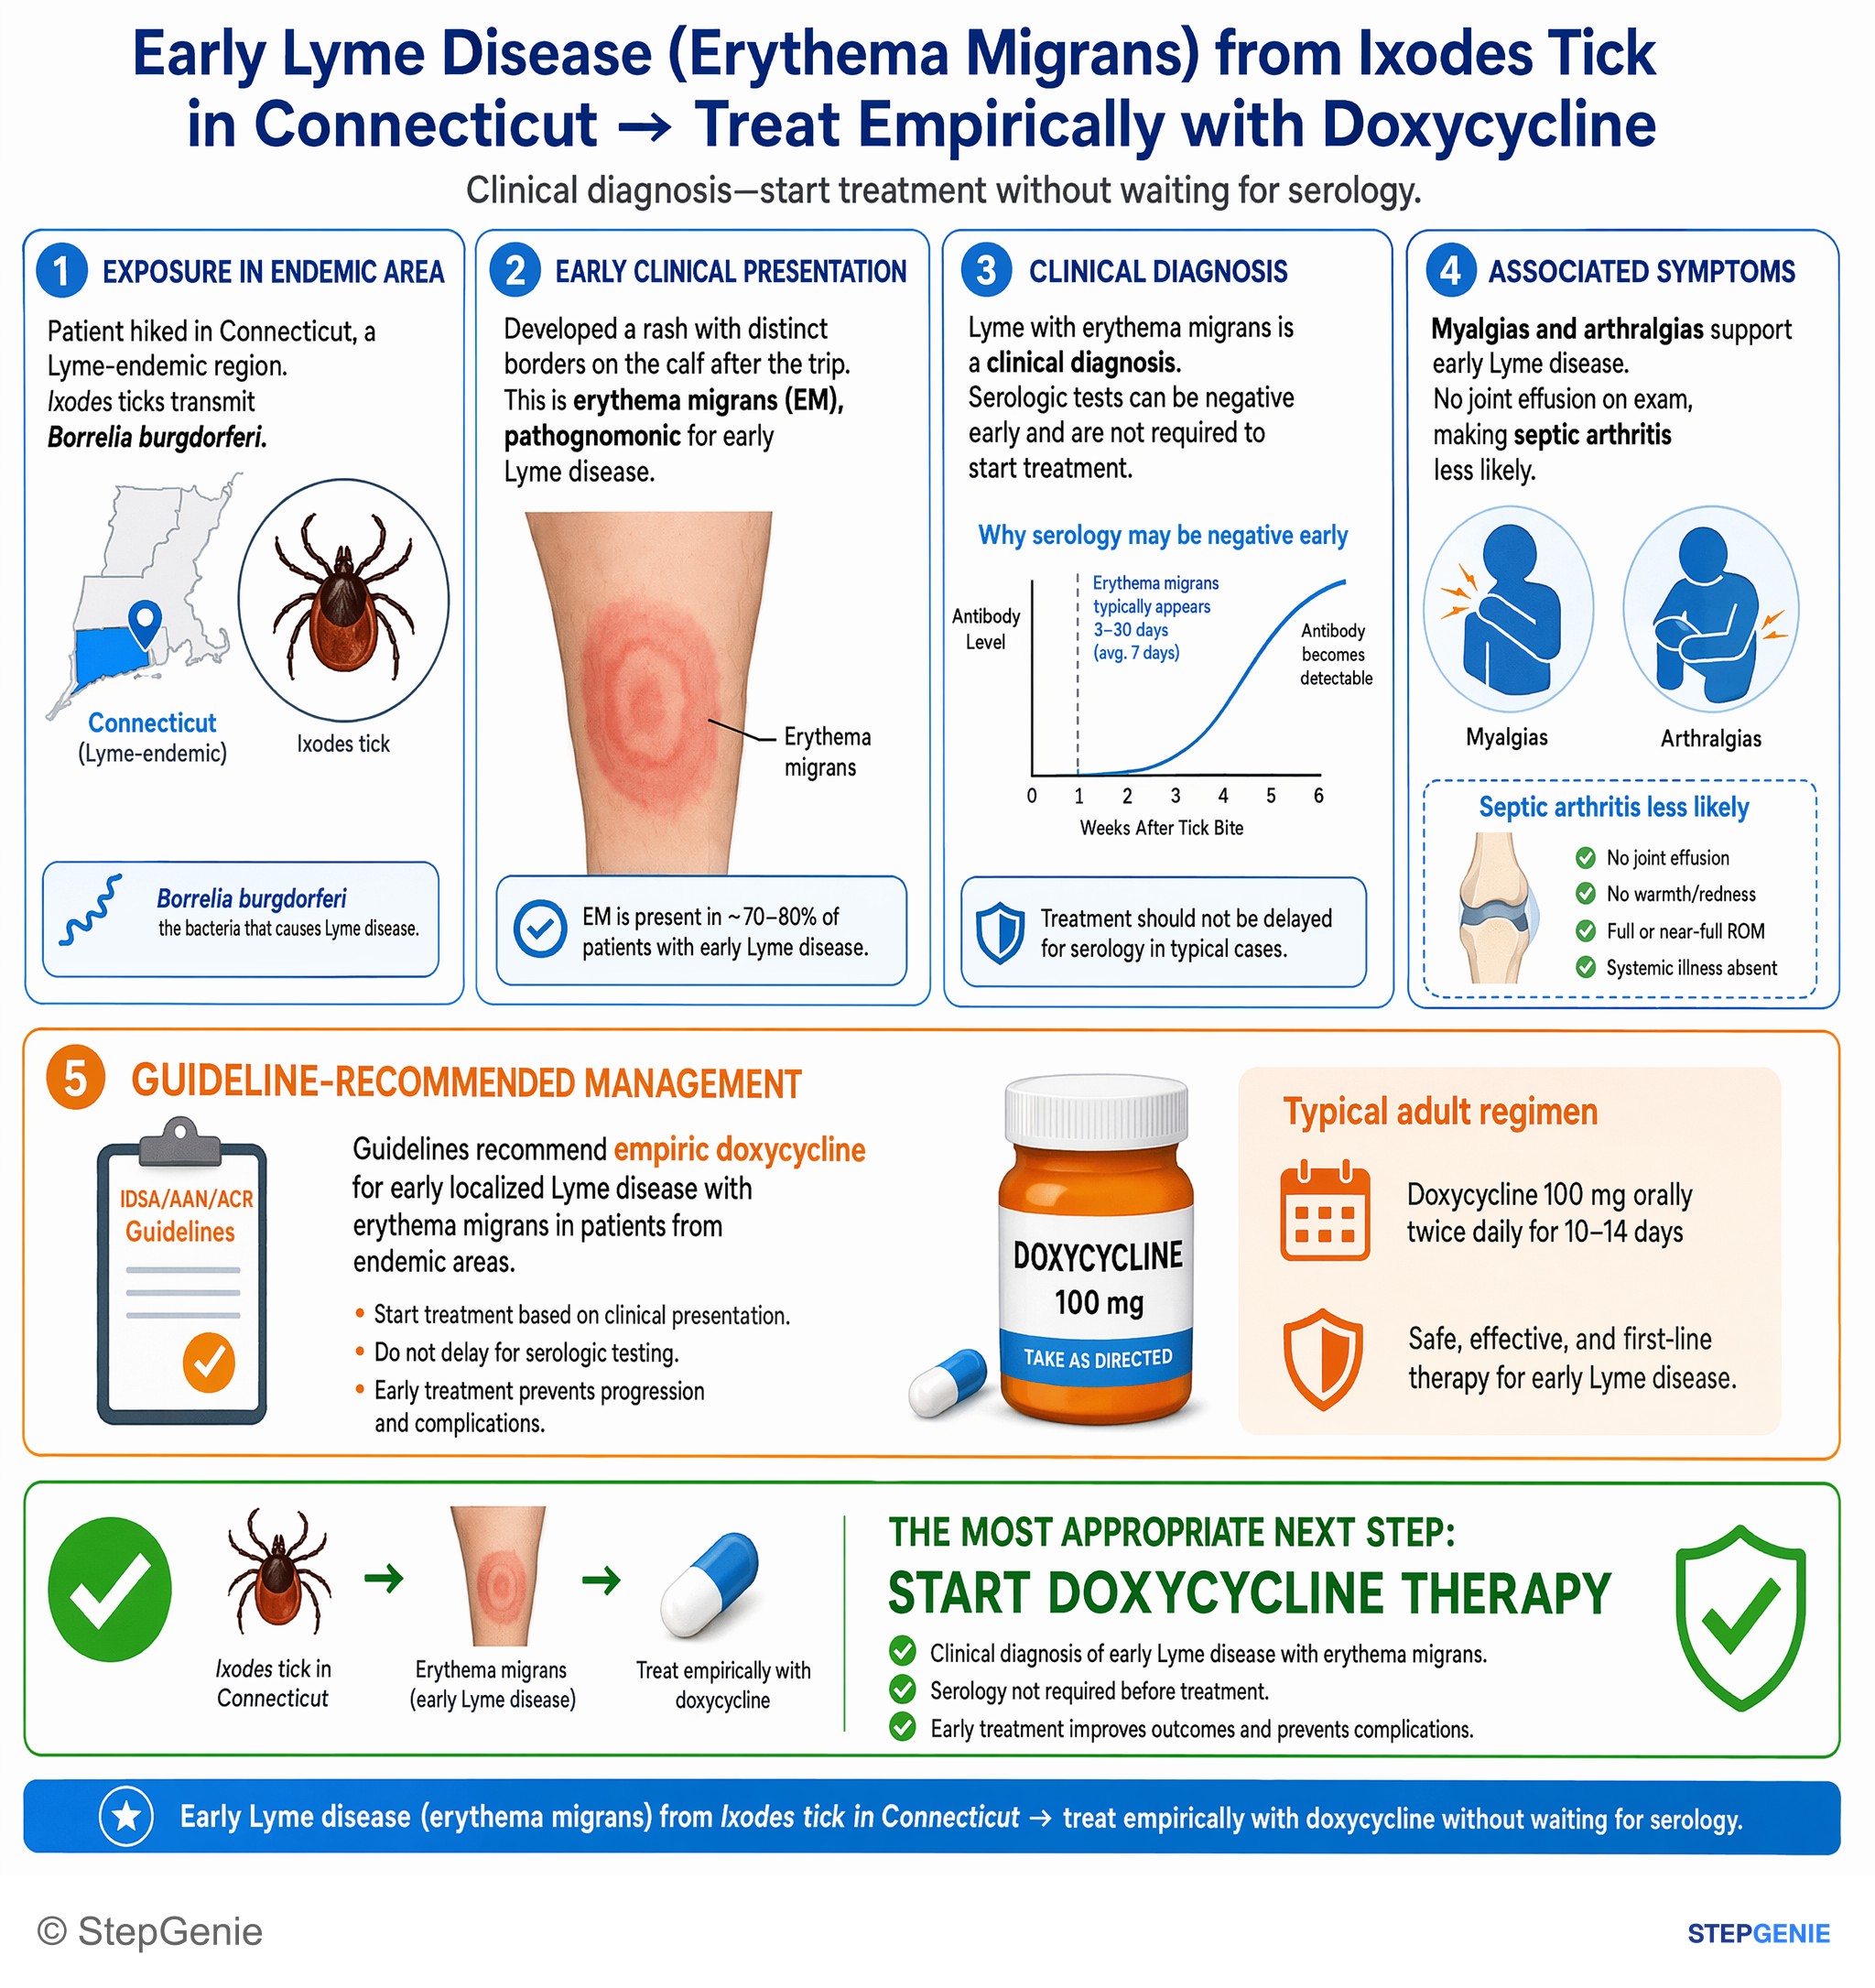
Early Lyme disease (erythema migrans) from Ixodes tick in Connecticut → treat empirically with doxycycline without waiting for serology.
USMLE Step 2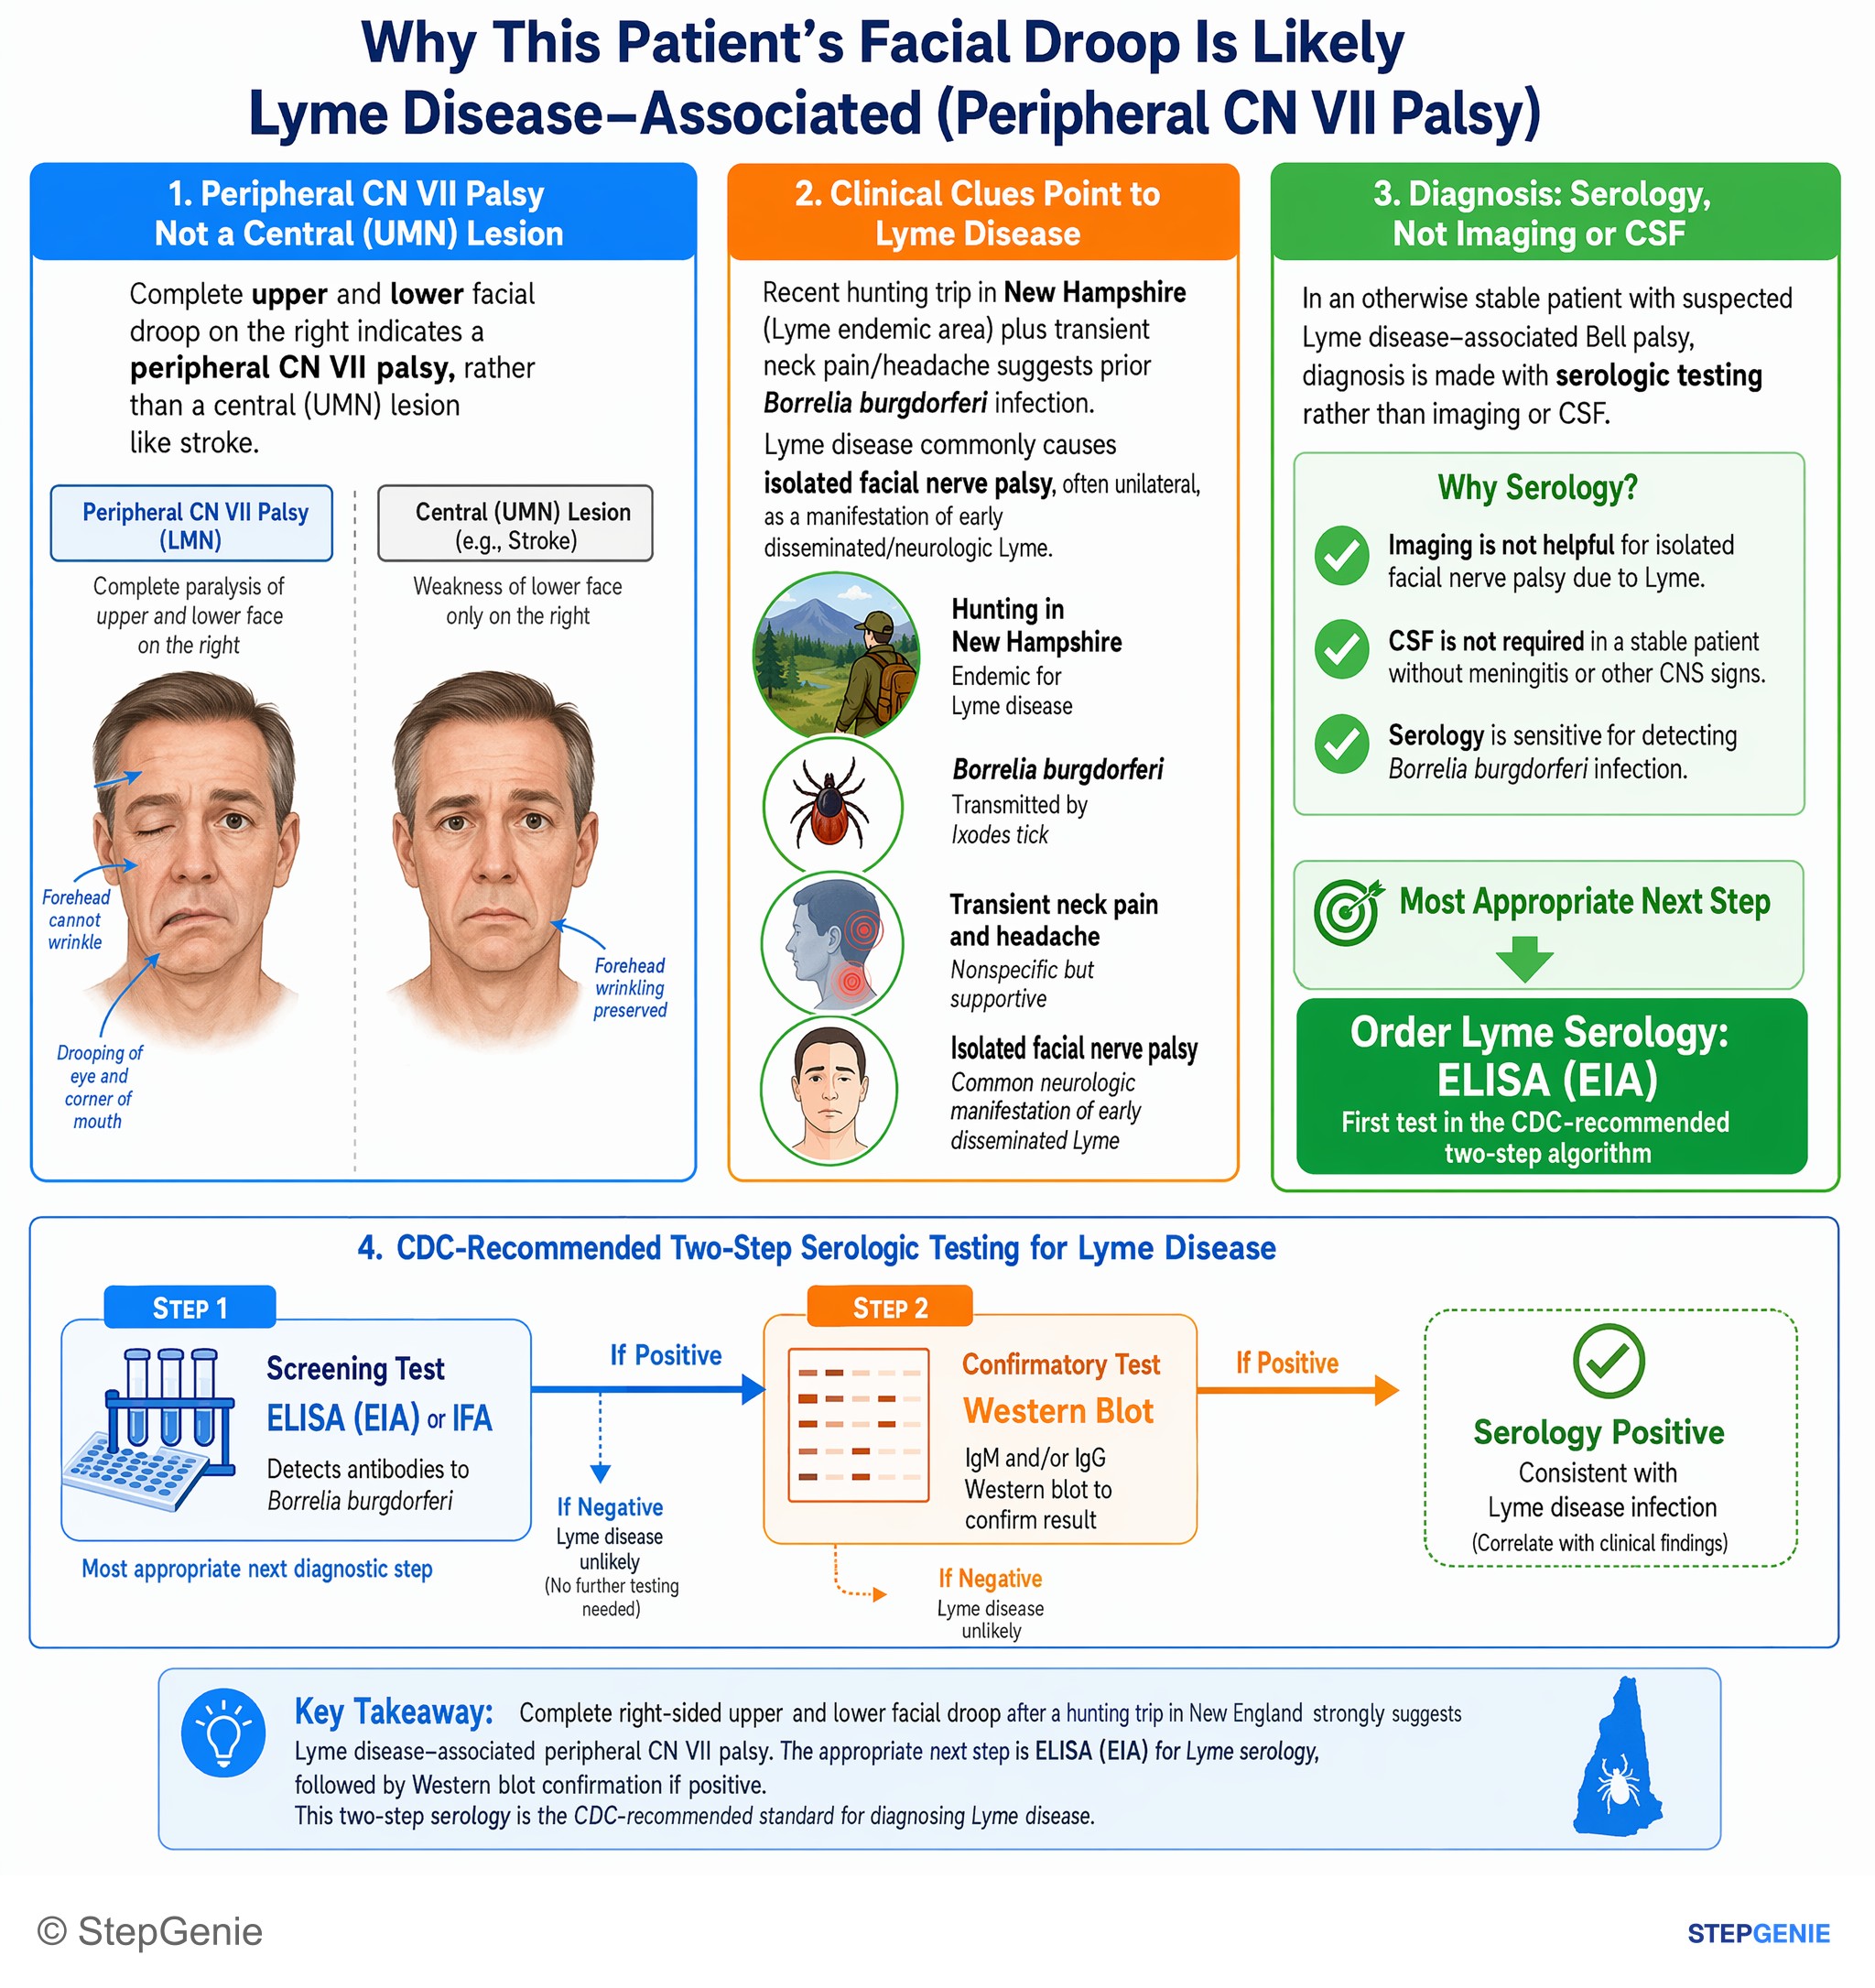
Lyme disease–associated Bell palsy after New England outdoor exposure → diagnose with two-step serology: ELISA first, then Western blot…
USMLE Step 2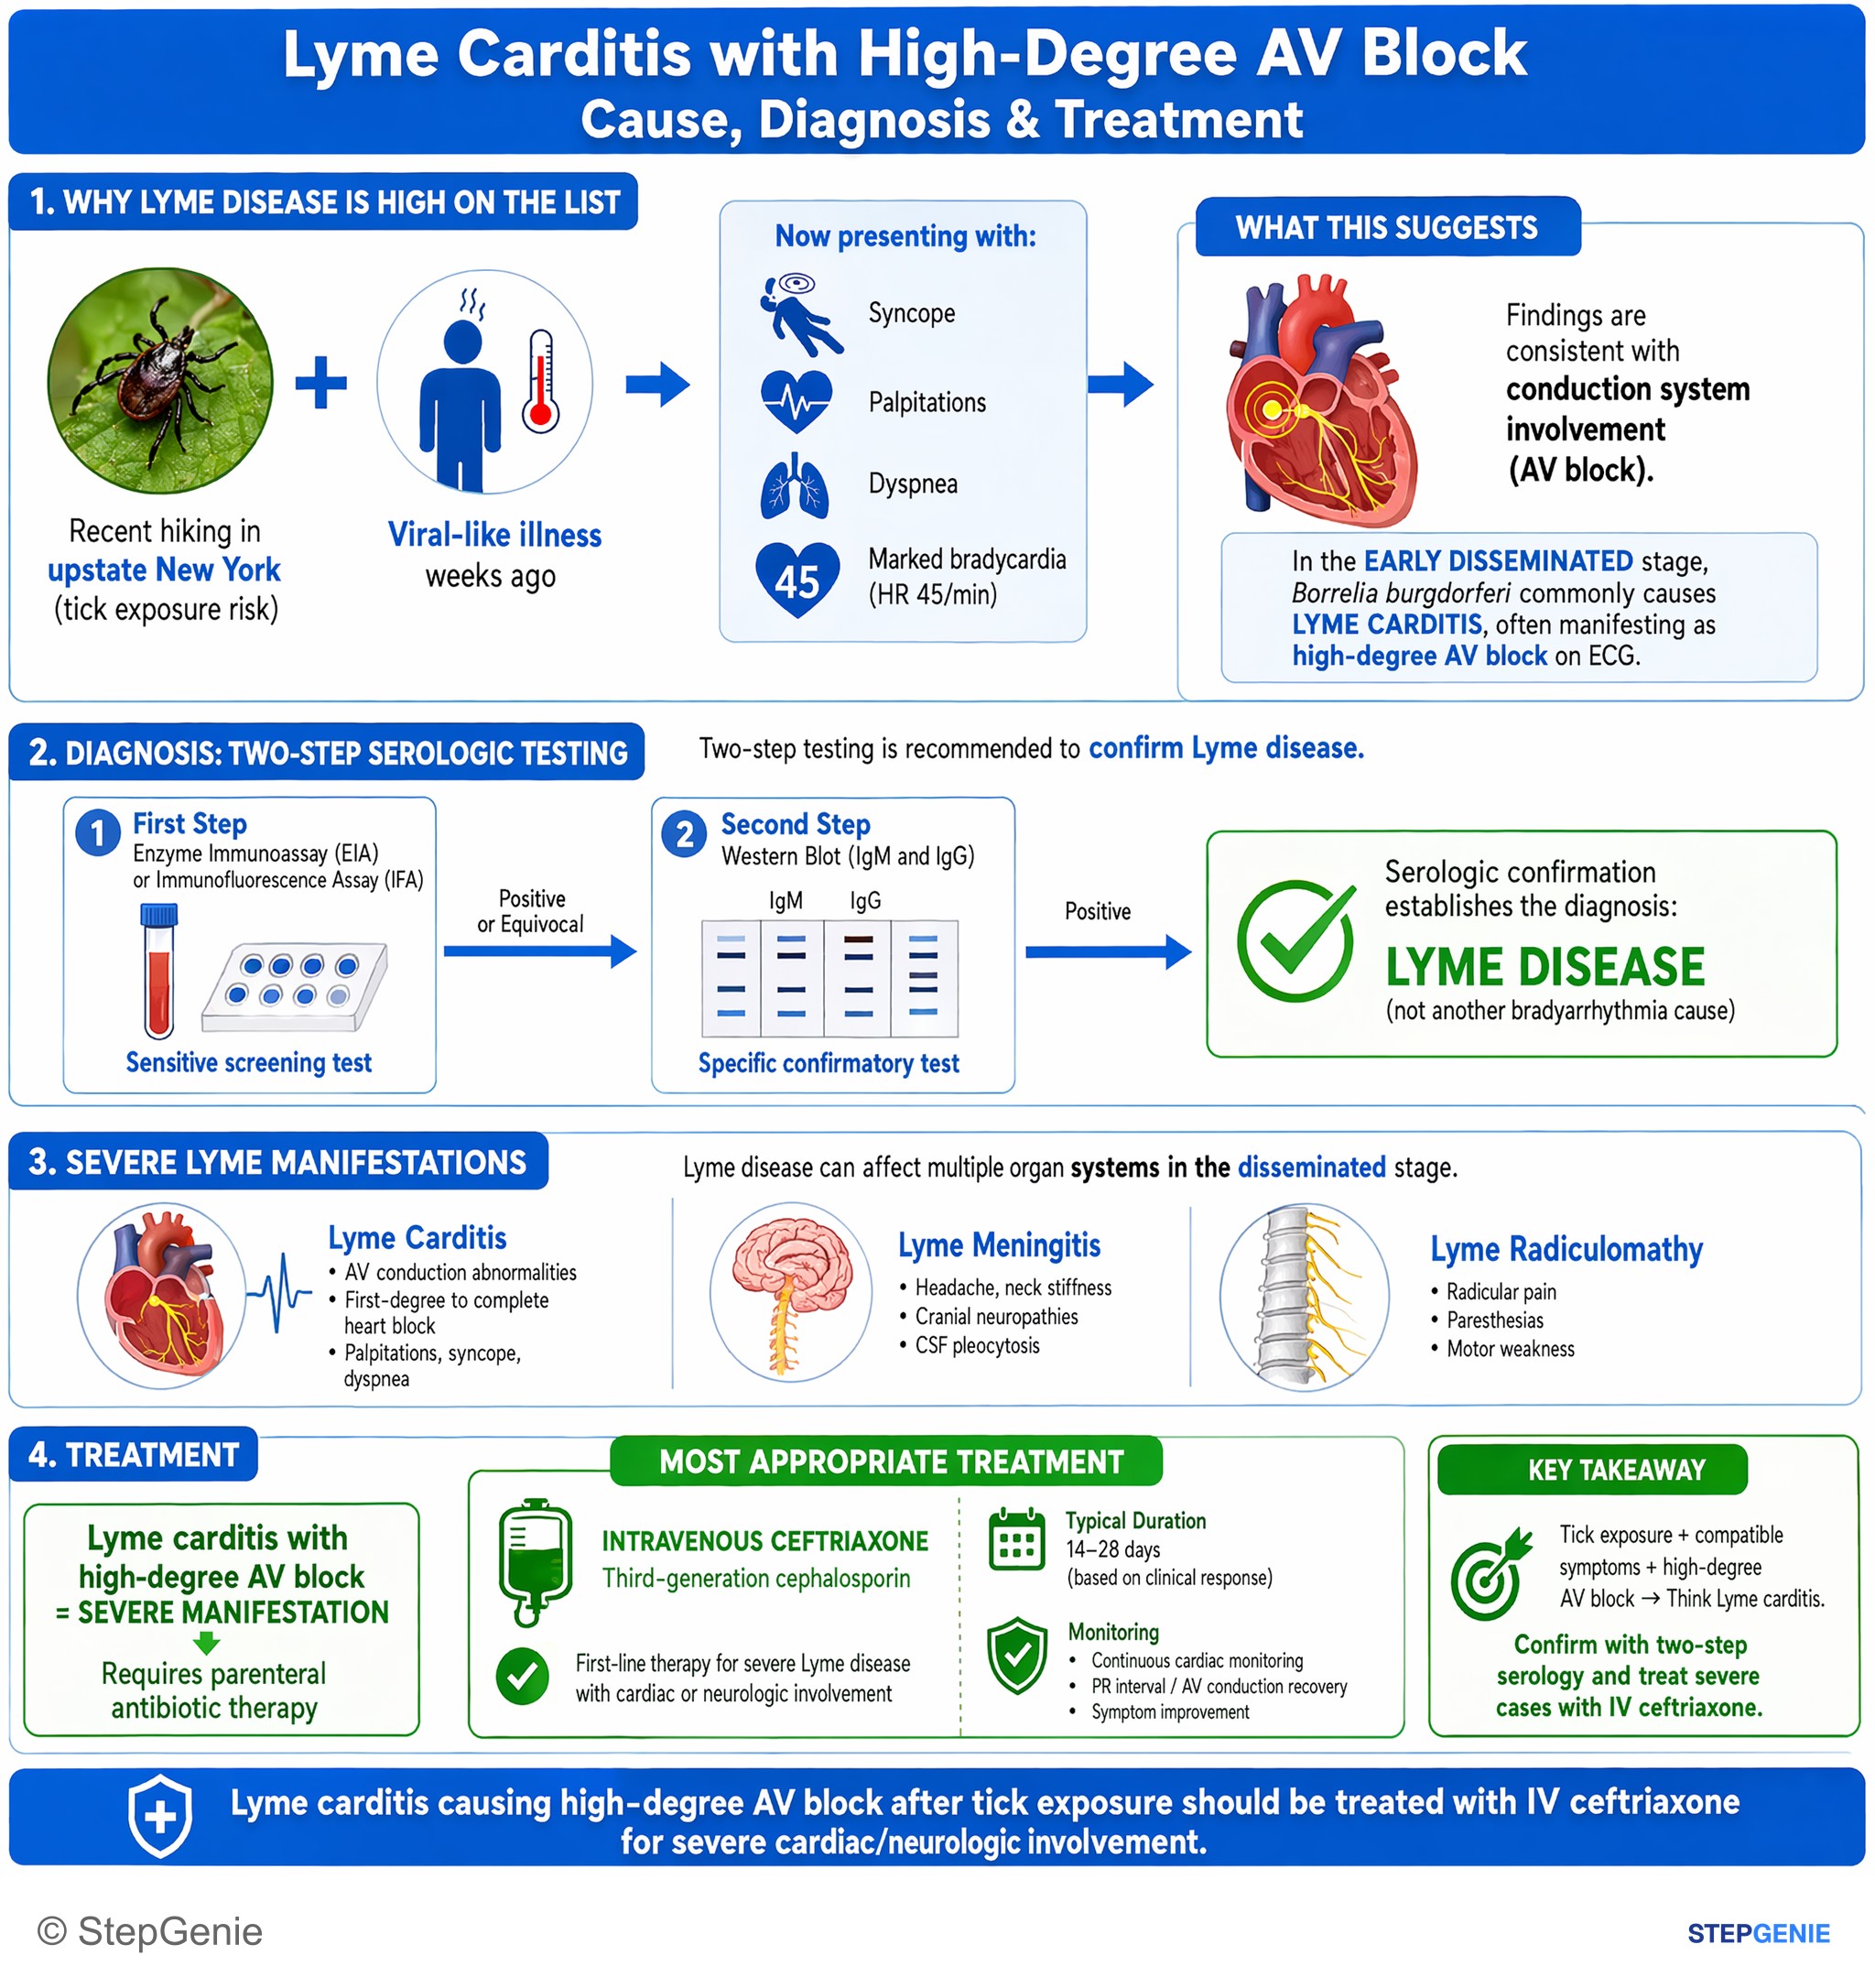
Lyme carditis causing high-degree AV block after tick exposure → treat with IV ceftriaxone for severe cardiac/neurologic involvement.
USMLE Step 2Frequently Asked Questions
What are the stages of Lyme disease?
Early localized Lyme disease is erythema migrans, an expanding red rash at the tick-bite site 3 to 30 days after the bite, often with fever, fatigue, headache and aches. Early disseminated disease, days to months later, brings multiple erythema migrans lesions, facial palsy that can be bilateral, lymphocytic meningitis, radiculoneuritis and carditis with fluctuating AV block. Late disease, one to a few months or more after infection, is arthritis of one or a few large joints, usually the knee.
Should you order Lyme serology for erythema migrans?
No. A typical erythema migrans rash in someone with possible tick exposure in an endemic area is a clinical diagnosis, and treatment should start right away. Antibodies take several weeks to develop, so serology is often negative in early disease. Two-tier testing, either an enzyme immunoassay followed by a Western blot or two different enzyme immunoassays, is used for suspected disseminated or late Lyme disease such as facial palsy, carditis or arthritis.
What is the treatment for Lyme disease?
Under the 2020 IDSA/AAN/ACR guideline, erythema migrans is treated with oral doxycycline for 10 days, or amoxicillin or cefuroxime for 14 days; azithromycin is second-line. Facial palsy gets oral doxycycline for 14 to 21 days, and meningitis or radiculoneuritis can be treated with oral doxycycline or IV ceftriaxone. Hospitalized carditis starts with IV ceftriaxone, and Lyme arthritis gets 28 days of an oral agent, with IV ceftriaxone if it does not respond.
How do you tell Lyme disease from Rocky Mountain spotted fever?
Lyme disease comes from Ixodes ticks in the Northeast, mid-Atlantic and upper Midwest and starts as a single expanding erythema migrans rash at the bite site. Rocky Mountain spotted fever comes mainly from Dermacentor ticks, with more than 60% of US cases reported from North Carolina, Oklahoma, Arkansas, Tennessee and Missouri, and causes a rash on the wrists, ankles, palms, soles and forearms that spreads to the trunk and turns petechial. Doxycycline treats both.
Is there a vaccine for Lyme disease?
As of October 2026, no Lyme disease vaccine is licensed for people in the United States. Pfizer and Valneva's six-valent OspA-based vaccine, PF-07307405, reported about 73 to 75 percent efficacy, with wide confidence intervals, in people aged 5 years and older in the phase 3 VALOR trial announced in March 2026; the first of two prespecified analyses missed its statistical success criterion. The European Medicines Agency validated its marketing application in August 2026. Prevention still relies on avoiding ticks and removing them promptly.
When is a single dose of doxycycline given after a tick bite?
The 2020 IDSA/AAN/ACR guideline supports one oral dose of doxycycline (200 mg for adults, 4.4 mg/kg up to 200 mg for children) only after a high-risk bite: the tick is identified as an Ixodes species, the bite happened in a highly endemic area, the tick was attached for at least 36 hours, and the dose can be given within 72 hours of removal. It is prophylaxis, not treatment; anyone with erythema migrans needs a full course.