A good Q-bank question doesn’t just test whether you can name the bug—it tests whether you can defend your pick against every distractor. Atypical mycobacteria (especially Mycobacterium avium complex, MAC) show up over and over on Step because the clinical presentation overlaps with TB, fungal disease, malignancy, and other opportunists. Let’s walk through a classic vignette and then dismantle every answer choice like you’re doing it out loud on rounds.
The Vignette (Classic Q-Bank Style)
A 39-year-old man with advanced HIV presents with several weeks of fever, night sweats, fatigue, watery diarrhea, and weight loss. He has diffuse abdominal tenderness and hepatosplenomegaly. Labs show anemia and elevated alkaline phosphatase. His CD4 count is 28 cells/mm³. Blood cultures grow acid-fast bacilli after several days.
Which organism is the most likely cause?
Correct Answer: Mycobacterium avium complex (MAC)
Why MAC fits best
This is the textbook setup for disseminated MAC in AIDS:
- Risk: typically CD4 < 50
- Symptoms: fever, night sweats, weight loss, profound malaise
- GI involvement: watery diarrhea, abdominal pain
- Reticuloendothelial involvement: hepatosplenomegaly, lymphadenopathy
- Labs: can see anemia, elevated alkaline phosphatase (hepatic involvement)
- Micro: acid-fast bacilli, often from blood cultures (disseminated disease)
High-yield microbiology and treatment pearls
Organism
- Mycobacterium avium + Mycobacterium intracellulare (MAC)
- Acid-fast, aerobic
- Environmental reservoir: soil and water (not usually person-to-person)
Prophylaxis (Step favorite)
- If CD4 < 50: azithromycin (or clarithromycin)
Treatment
- Typically a macrolide (azithro/clarithro) + ethambutol
- Often add rifabutin (especially disseminated/severe disease or to reduce resistance)
Step framing: MAC is the late-stage AIDS systemic AFB that loves the bloodstream and GI tract.
Distractor Autopsy: Why Every Other Option Is Wrong (and What It Would Look Like)
Below are common answer choices that appear in the same question family.
1) Mycobacterium tuberculosis (TB)
Why it tempts you: acid-fast bacilli + constitutional symptoms.
Why it’s wrong here:
- TB classically presents with pulmonary symptoms (cough, hemoptysis) ± constitutional symptoms.
- Disseminated TB can occur, but the vignette screams CD4 < 50 systemic bacteremia + diarrhea, which is much more MAC-coded.
- TB is often associated with upper lobe cavitary disease (reactivation) or miliary pattern (disseminated).
What would point to TB instead
- Chronic cough, hemoptysis, apical cavitation, caseating granulomas
- Risk factors: incarceration, homelessness, travel, close contacts
- Testing: AFB smear/culture, NAAT; PPD/IGRA for exposure
Treatment hook
- RIPE therapy: rifampin, isoniazid (+B6), pyrazinamide, ethambutol
2) Mycobacterium kansasii
Why it tempts you: atypical mycobacterium that causes TB-like lung disease.
Why it’s wrong here:
- M. kansasii most often causes chronic pulmonary infection resembling TB, not classic disseminated diarrhea + bloodstream infection.
- Dissemination can happen but is less “Step-classic” than MAC for CD4 < 50 with systemic/GI symptoms.
What would point to M. kansasii
- Smoker/COPD, chronic cough, cavitary lung lesions
- Classically associated with tap water exposure in some settings
- Often treated with rifampin + ethambutol + isoniazid (varies by susceptibility)
3) Mycobacterium marinum
Why it tempts you: atypical mycobacterium tested often.
Why it’s wrong here:
- M. marinum causes skin/soft tissue infection after exposure to aquariums/fish tanks or saltwater.
- Think localized papules/nodules and sporotrichoid spread (linear nodules along lymphatics), not bacteremia/diarrhea in AIDS.
What would point to M. marinum
- “Fish tank granuloma”
- Lesions on hands/forearms after aquatic exposure
- Grows best at cooler temperatures (skin)
4) Mycobacterium leprae
Why it tempts you: acid-fast mycobacterium with immune-dependent manifestations.
Why it’s wrong here:
- Leprosy causes skin lesions + peripheral neuropathy and is not a classic bloodstream/GI opportunist in AIDS the way MAC is.
- Incubation is long; presentation is chronic, not “weeks of systemic illness with diarrhea.”
What would point to leprosy
- Hypopigmented anesthetic skin patches
- Thickened peripheral nerves
- Lepromatous form: diffuse skin lesions, nodules, leonine facies
- Tx: dapsone + rifampin (± clofazimine)
5) Nocardia asteroides
Why it tempts you: partially acid-fast + opportunistic.
Why it’s wrong here:
- Nocardia is weakly acid-fast and causes pneumonia with possible CNS dissemination (brain abscesses)—more common in transplant patients, chronic steroids, and advanced HIV too.
- But this vignette emphasizes GI symptoms + bacteremia rather than lung-to-brain spread.
What would point to Nocardia
- Cavitary pneumonia + neurologic deficits
- Branching, filamentous, gram-positive rods
- Treatment: TMP-SMX (often prolonged)
6) Histoplasma capsulatum
Why it tempts you: disseminated disease in AIDS with systemic symptoms.
Why it’s wrong here:
- Disseminated histoplasmosis can mimic MAC (fever, weight loss, hepatosplenomegaly), but:
- It’s a fungus, not AFB.
- You’d expect clues like Ohio/Mississippi River valley exposure or bat/bird droppings, and diagnostics like urine antigen or intracellular yeasts in macrophages.
What would point to histo
- Immunosuppressed + systemic symptoms
- Pancytopenia, mucosal ulcers (can occur)
- Yeast inside macrophages on smear
- Treatment: itraconazole (mild/moderate) vs amphotericin B (severe)
7) Treponema pallidum (syphilis) or other spirochetes
Why it tempts you: “Atypicals, Spirochetes, Mycobacteria” mixed topic sets love to cross-wire you.
Why it’s wrong here:
- Spirochetes are not acid-fast bacilli and don’t present as AFB-positive blood cultures.
- Syphilis is about staged mucocutaneous disease, neuro/vascular complications—not this.
What would point to syphilis
- Painless chancre (primary), rash on palms/soles (secondary), tabes dorsalis/aortitis (tertiary)
- Testing: RPR/VDRL then confirm with treponemal test
- Treatment: penicillin G
Rapid Comparison Table (High-Yield)
| Organism | Stain / Morphology | Classic Setting | Typical Presentation | High-Yield Treatment/Prevention |
|---|---|---|---|---|
| MAC (M. avium-intracellulare) | Acid-fast bacillus | AIDS, CD4 < 50 | Disseminated: fever, wt loss, diarrhea, hepatosplenomegaly, anemia; blood cultures | Prophylaxis: azithro; Tx: macrolide + ethambutol ± rifabutin |
| M. tuberculosis | Acid-fast bacillus | Crowding, exposure, immunosuppression | Chronic cough, hemoptysis, night sweats; apical cavitation or miliary | RIPE |
| M. kansasii | Acid-fast bacillus | COPD/smokers; water exposure | TB-like pulmonary disease | Rifampin-based regimen |
| M. marinum | Acid-fast bacillus | Fish tank/aquatic exposure | Localized skin nodules, sporotrichoid spread | Macrolide, doxycycline, etc. |
| M. leprae | Acid-fast bacillus | Travel/endemic; armadillos | Skin lesions + peripheral neuropathy | Dapsone + rifampin (± clofazimine) |
| Nocardia | Weakly acid-fast, branching G+ rods | Transplant, steroids, AIDS | Pneumonia ± brain abscess | TMP-SMX |
| Histoplasma | Fungus (intracellular yeasts) | Ohio/Mississippi River valleys | Pneumonia; disseminated in AIDS | Itraconazole or amphotericin B |
Exam-Day Pattern Recognition (What to Lock In)
If you see CD4 < 50 + systemic symptoms…
Think MAC prophylaxis = azithromycin.
If you see CD4 < 50 + fever/weight loss + diarrhea + AFB in blood
Think disseminated MAC.
If you see AFB + pulmonary cavitation and classic TB risks
Think TB (RIPE).
If you see weakly acid-fast + branching filaments + brain abscess
Think Nocardia (TMP-SMX).
Take-Home Q-Bank Skill: “Defend the Diagnosis”
When the stem says AIDS, don’t stop at “opportunistic infection.” Force yourself to answer:
- What CD4 range is implied?
- Is this pulmonary, GI, CNS, skin, or systemic bacteremia?
- Which organisms are most classic for that organ pattern at that CD4?
That’s how you turn a memorized list into consistent points.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
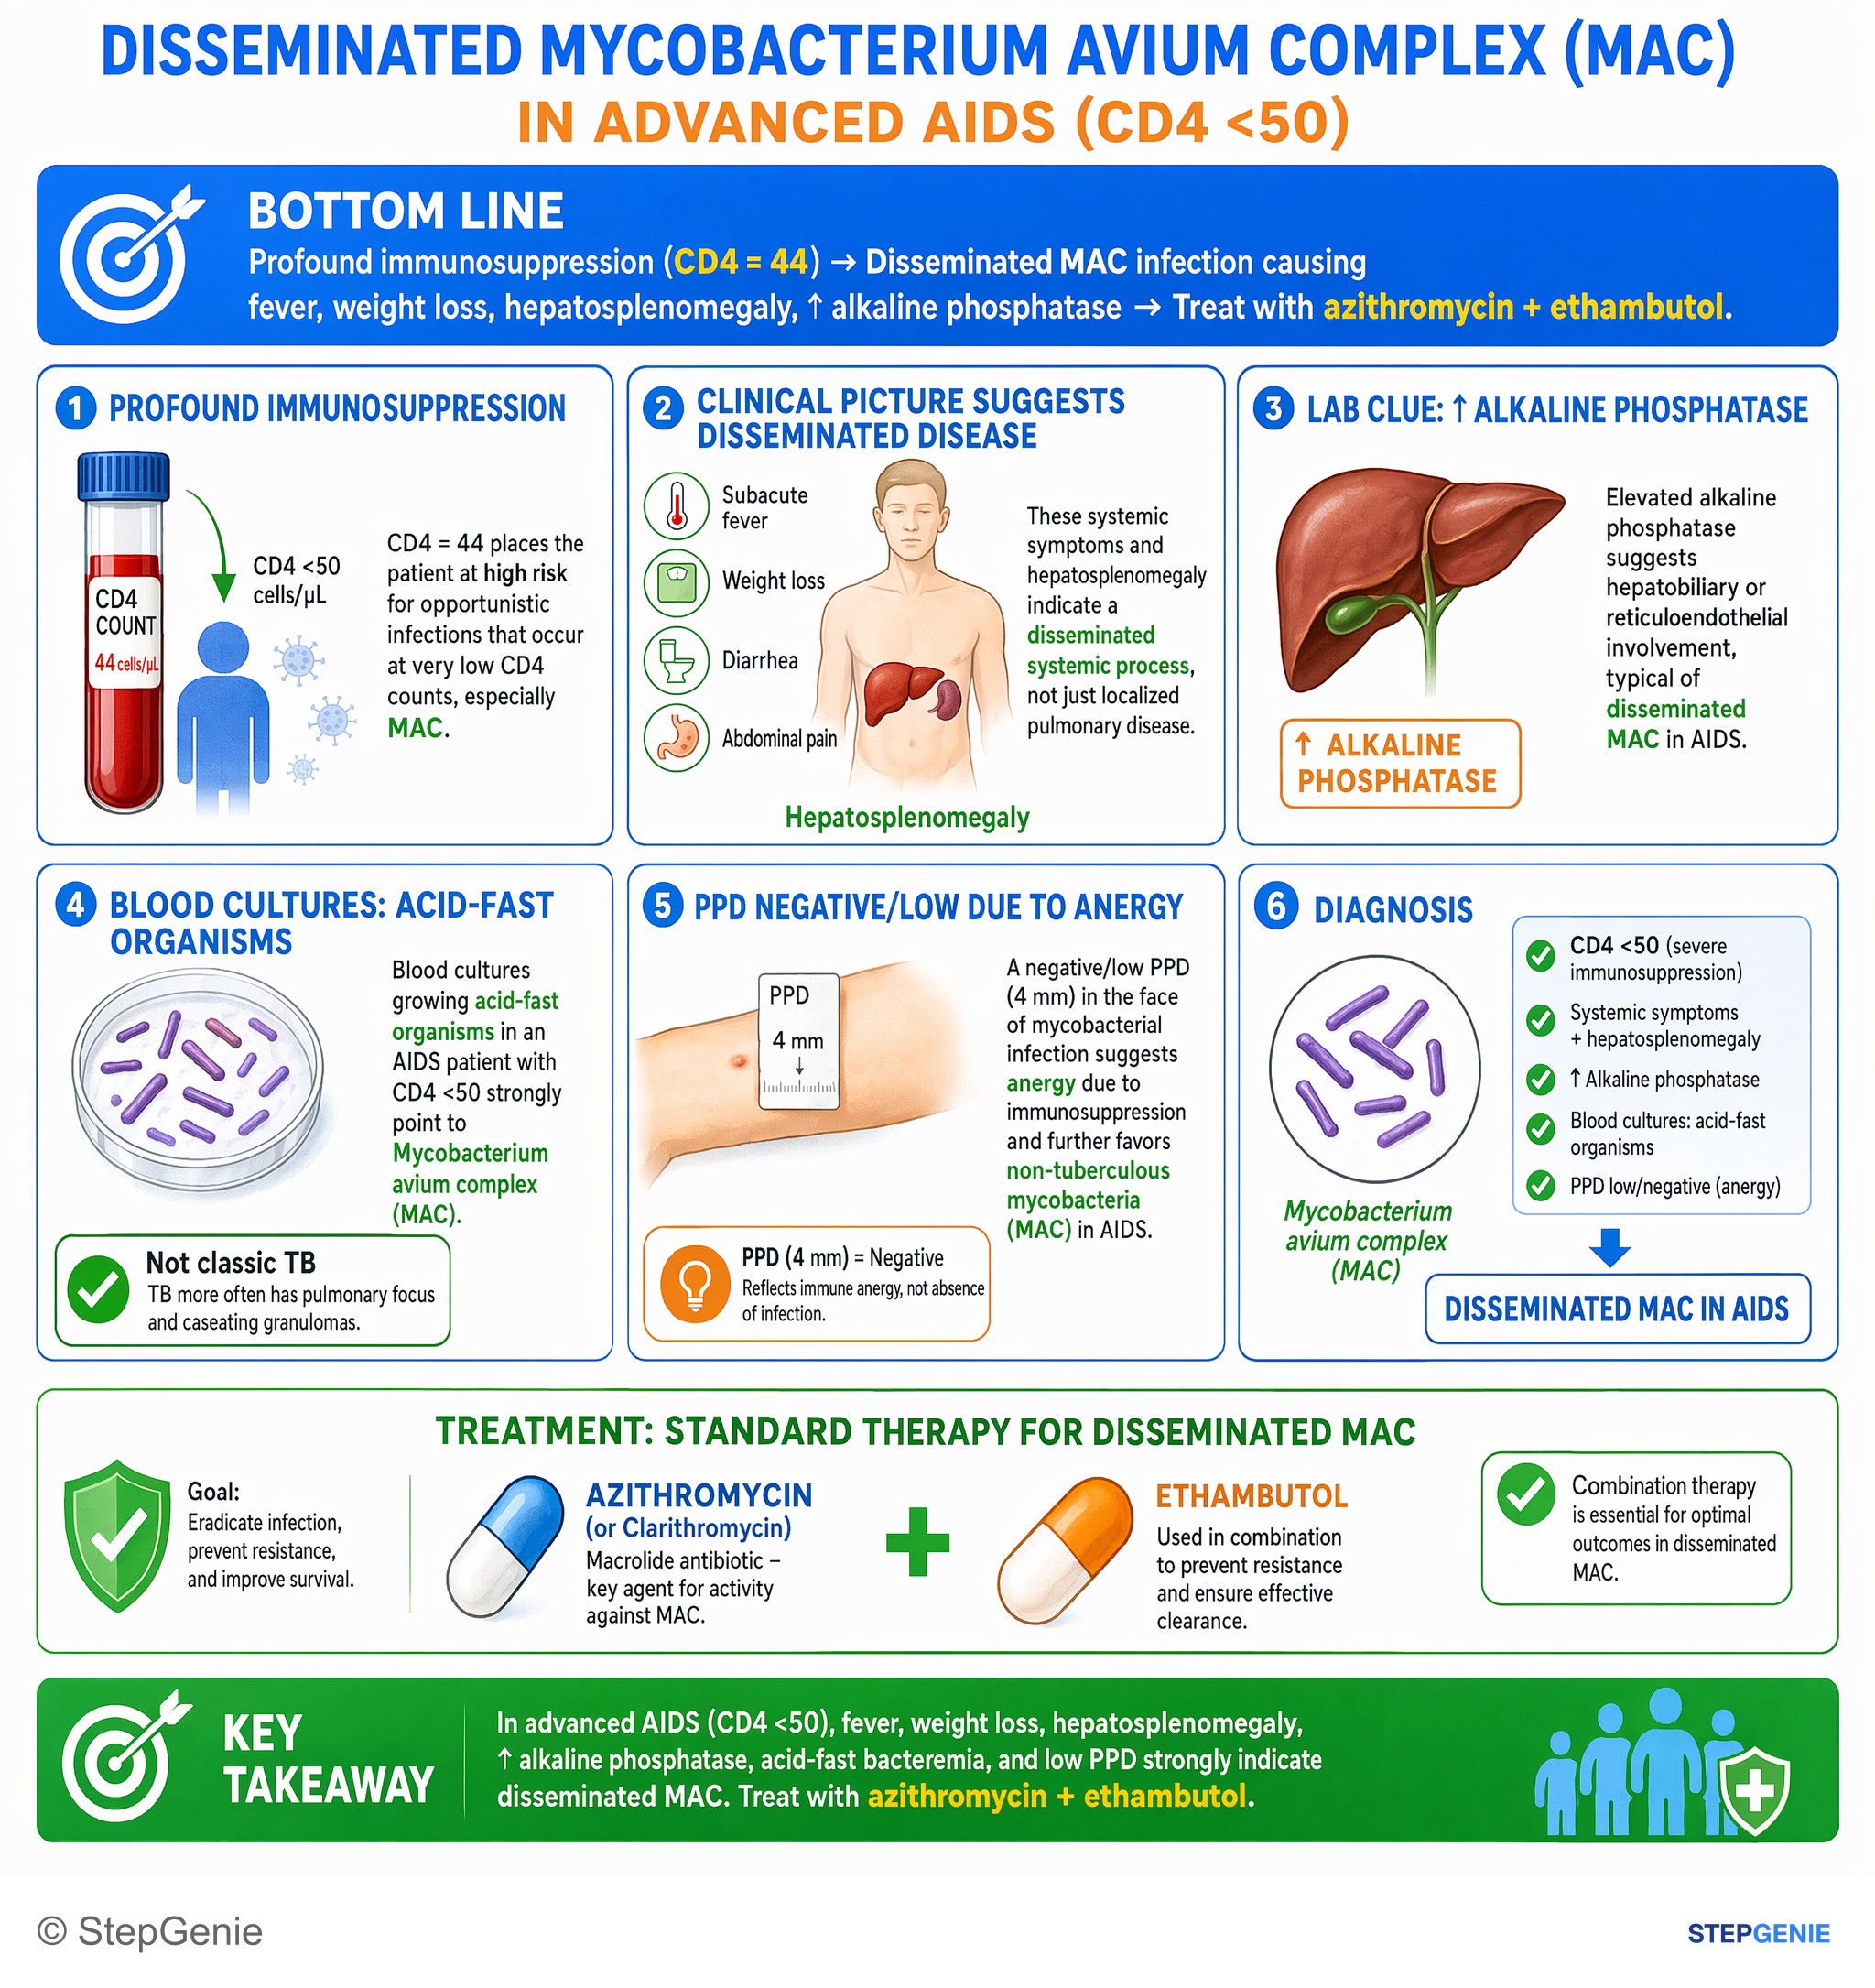
Disseminated Mycobacterium avium complex (MAC) in advanced AIDS (CD4 <50) causing fever, weight loss, hepatosplenomegaly, ↑alk phos →…
USMLE Step 2Frequently Asked Questions
What clues make disseminated MAC the best diagnosis in an AIDS patient with acid-fast bacilli?
Disseminated MAC is most likely when advanced HIV is paired with CD4 below 50, systemic symptoms, GI symptoms, and acid-fast bacilli in blood cultures. The classic pattern is fever, night sweats, weight loss, profound fatigue, watery diarrhea, abdominal pain, hepatosplenomegaly, anemia, and elevated alkaline phosphatase, which together point to late-stage AIDS MAC involving the bloodstream and reticuloendothelial system.
How do you tell disseminated MAC from tuberculosis on a vignette?
Disseminated MAC is favored when the patient has CD4 below 50 with bacteremia and prominent GI symptoms like watery diarrhea. Tuberculosis can also cause acid-fast disease and constitutional symptoms, but it classically points more toward pulmonary findings such as chronic cough, hemoptysis, apical cavitation, or caseating granulomas, with possible upper lobe cavitary disease or a miliary pattern rather than the classic MAC bloodstream and GI presentation.
What is the prophylaxis and treatment for MAC in advanced HIV?
MAC prophylaxis is azithromycin or clarithromycin when the CD4 count is below 50. Treatment is typically a macrolide such as azithromycin or clarithromycin plus ethambutol, and rifabutin is often added in disseminated or severe disease or to reduce resistance. This regimen matches the classic Step pattern of disseminated MAC as a late-stage AIDS opportunistic infection.
How do you distinguish MAC from Nocardia in an immunocompromised patient?
MAC is more likely when the vignette emphasizes watery diarrhea, hepatosplenomegaly, anemia, elevated alkaline phosphatase, and acid-fast bacilli from blood cultures. Nocardia is only weakly acid-fast and more classically causes pneumonia with possible CNS spread, especially brain abscesses. Clues for Nocardia include cavitary pneumonia, neurologic deficits, and branching filamentous gram-positive rods rather than a bloodstream and GI syndrome.
Why is Histoplasma not the best answer when disseminated disease in AIDS looks similar to MAC?
Histoplasma is less likely because it is a fungus, not an acid-fast bacillus. Although disseminated histoplasmosis can also cause fever, weight loss, and hepatosplenomegaly in immunosuppressed patients, the expected clues are different, such as Ohio or Mississippi River valley exposure, bat or bird droppings, urine antigen testing, or intracellular yeasts within macrophages rather than AFB growing from blood cultures.