Vibrio cholerae is a curved (comma-shaped), flagellated, oxidase-positive gram-negative rod that causes cholera: abrupt, painless, high-volume "rice-water" diarrhea, often with vomiting, that can kill by hypovolemic shock. Its AB5 cholera toxin binds GM1 ganglioside and ADP-ribosylates the Gsα protein, locking adenylate cyclase on; the cAMP surge opens CFTR chloride channels and blocks sodium chloride absorption, so water pours into the small-bowel lumen without any mucosal invasion. Rehydration is the treatment: oral rehydration solution (ORS) for most patients and isotonic IV fluid for severe dehydration, with a single dose of doxycycline as an adjunct (azithromycin or ciprofloxacin if doxycycline resistance is documented). Untreated cholera kills more than half of patients; with timely rehydration, deaths fall to about 1%.
The organism at a glance
| Feature | V. cholerae | Exam hook |
|---|---|---|
| Shape and motility | Curved (comma) gram-negative rod; motile and flagellated | Darting "shooting star" motility on dark-field microscopy |
| Oxidase | Positive | Classic lab clue for vibrios |
| Growth | Thrives in alkaline conditions | Enrich in alkaline peptone water (pH 8.5), then TCBS agar: yellow (sucrose-fermenting) colonies |
| Epidemic serogroups | O1 (classical and El Tor biotypes; El Tor now predominates) and O139 | Only toxin-producing O1 and O139 count as cholera; other Vibrio illness is "vibriosis" |
| Spread | Water or food contaminated with feces; raw shellfish | Outbreaks follow failures of water and sanitation, such as after natural disasters |
| Host risk | Killed by stomach acid, so a large inoculum is needed; low gastric acid (achlorhydria, acid-suppressing drugs such as PPIs and H2 blockers) and blood group O raise risk | Stomach acid is the first defense |
| Virulence genes | Cholera toxin genes are carried by a prophage (CTXΦ) | The toxin gene arrives by lysogenic conversion |
Cholera toxin: the mechanism step by step
- Bind: the five B subunits, arranged in a ring, bind GM1 ganglioside on small-intestinal epithelial cells.
- Enter: the toxin is carried backward through the Golgi to the endoplasmic reticulum, and the A1 fragment slips into the cytosol.
- Lock Gs on: A1 ADP-ribosylates Gsα, blocking its GTP hydrolysis, so adenylate cyclase never switches off.
- cAMP surge: cAMP activates protein kinase A, which phosphorylates and opens the CFTR chloride channel; cAMP also inhibits electroneutral NaCl absorption.
- Flood: chloride secretion with sodium and water following produces isotonic fluid loss; stool output in adults can exceed 1 L per hour, although it is usually much less.
- The loophole: sodium-glucose cotransport still works, which is why ORS, with glucose and sodium together, rehydrates patients.
One-liner: ADP-ribosylates Gs → ↑ cAMP → CFTR opens → Cl⁻, Na⁺ and water into the lumen → rice-water stool.
| Toxin | Target | Result |
|---|---|---|
| Cholera toxin (AB5) | ADP-ribosylates Gsα | ↑ cAMP, secretory diarrhea |
| ETEC heat-labile toxin (LT) | Highly homologous to cholera toxin (about 80% amino acid identity); one A and five B subunits | ↑ cAMP, watery travelers' diarrhea |
| ETEC heat-stable toxin (ST) | Small peptide that stimulates guanylate cyclase | ↑ cGMP, watery diarrhea |
| Diphtheria toxin (AB) | ADP-ribosylates elongation factor 2 | Protein synthesis stops, cells die |
The same ADP-ribosylation trick hits a different target in Corynebacterium diphtheriae; the E. coli toxins are broken down in the ETEC, EHEC, EPEC, EIEC and EAEC breakdown.
Clinical picture
- Incubation: usually 1-3 days.
- Spectrum: many infections are subclinical or mild, especially with the El Tor biotype; about 1 in 10 infected people develop severe symptoms.
- Severe cholera: abrupt, painless, watery diarrhea and vomiting; rice-water stool; intense thirst, muscle (leg) cramps, weakness and marked loss of tissue turgor, with sunken eyes and wrinkled skin.
- Noninflammatory: the vibrios colonize the gut lining but do not invade the intestinal wall, so stool is watery and nonbloody with few or no white blood cells.
- Complications: hypovolemic shock, metabolic acidosis, hypokalemia, and oliguria that can progress to acute tubular necrosis. On exams, diarrhea is a classic cause of normal anion gap (hyperchloremic) acidosis from bicarbonate loss; lactic acidosis from shock and kidney failure add an anion gap. Review the anion gap approach and hypokalemia.
- Survival: untreated cholera kills more than 50%; timely rehydration brings deaths to about 1%.
Diagnosis
- Start rehydration on clinical grounds; do not wait for the lab.
- Stool culture confirms the diagnosis: enrichment in alkaline peptone water, plating on TCBS (yellow colonies), a positive oxidase test, then serogrouping with O1 and O139 antisera. PCR is also used.
- Rapid dipstick tests help where labs are scarce, but their specificity is suboptimal, so culture remains the confirmatory test.
- Definition: illness caused by toxin-producing V. cholerae O1 or O139 is cholera; infections with other Vibrio species and strains are called vibriosis.
Treatment: fluids first
| Step | What to do | Details |
|---|---|---|
| 1. Rehydrate | ORS for mild to moderate dehydration; isotonic IV fluid for hypovolemic or severely dehydrated patients, then ORS | WHO reduced-osmolarity ORS contains sodium 75 mmol/L and glucose 75 mmol/L (total osmolarity 245). Sports drinks, sodas and juices carry too little sodium and too much sugar |
| 2. Antibiotics (adjunct) | Early effective treatment eradicates vibrios, cuts stool volume by about 50% and usually stops diarrhea within 48 hours | Single-dose doxycycline for adults, including pregnant patients, and for children (weight-based dose); single-dose azithromycin or ciprofloxacin if doxycycline resistance is documented |
| 3. Zinc | Children | Has reduced the severity and duration of cholera in children in low-resource areas |
| 4. Feed early | Infants resume breast milk or formula; children restart an age-appropriate diet once rehydrated and no longer vomiting | Supports recovery |
- Exam rule: antibiotics never replace fluids. The patient in shock gets IV isotonic fluid first.
Prevention, vaccines and epidemiology
- Safe water, sanitation and food hygiene prevent cholera.
- US vaccine: Vaxchora (CVD 103-HgR) is a live attenuated, single-dose oral vaccine and the FDA-licensed cholera vaccine in the US, labeled for people aged 2-64 traveling to cholera-affected areas; ACIP recommends it for travelers aged 2-64 going to areas of active toxigenic V. cholerae O1 transmission. Give it at least 10 days before potential exposure. In a challenge study of adults aged 18-45, it reduced moderate to severe diarrhea by about 90% at 10 days and 80% at 3 months; protection beyond the trial period is unknown, and there is no US booster recommendation. It targets serogroup O1 and has not been shown to protect against O139.
- Vaxchora interactions: do not give it within 14 days after oral or parenteral antibiotics, and give it at least 10 days before starting chloroquine. The vaccine strain is shed in stool for at least 7 days, so recipients should wash their hands carefully.
- Supply: production was halted in December 2020 and the vaccine was reported unavailable in the US in 2023, so check current availability before travel.
- Elsewhere: killed whole-cell oral vaccines (Dukoral and bivalent vaccines such as Euvichol) are used internationally but are not available in the US.
- Burden: an estimated 1.3-4 million cases and 21,000-143,000 deaths worldwide each year. US residents can acquire cholera while traveling abroad and fall ill after returning home.
How USMLE tests it
| Organism | Classic stem | Discriminator |
|---|---|---|
| V. cholerae | Outbreak, flood or travel; liters of rice-water stool; shock | Oxidase-positive comma rod; yellow colonies on TCBS; Gs → ↑ cAMP |
| ETEC | Traveler with watery diarrhea | The number one cause of travelers' diarrhea (20-60%); LT (cAMP) and ST (cGMP); ranges from mild to cholera-like |
| V. vulnificus | Raw or undercooked seafood (classically oysters) or a wound exposed to coastal water, especially with liver disease | Fever, chills, hypotension, blistering skin lesions; about 1 in 5 die; ceftazidime plus doxycycline |
| V. parahaemolyticus | Gastroenteritis after raw or undercooked seafood | Watery diarrhea, abdominal cramps, nausea and fever; one of the most common causes of vibriosis in the US |
| Shigella | Stools that may contain mucus, pus and blood; fever, cramps | Invades the intestinal epithelium; see Shigella |
Traps: a stem with raw oysters plus cirrhosis and bullae is V. vulnificus, not cholera. "Painless, profuse, no blood, no fecal WBCs" means a toxin, not invasion. Vaxchora is live and oral, so recent antibiotics blunt it.
Practice question
A 34-year-old aid worker returns from a refugee camp during a cholera outbreak. Over 12 hours he has passed several liters of painless, watery, gray stool with mucus flecks and has vomited twice. He is afebrile, with a pulse of 118/min and dry mucous membranes. Stool shows no blood or leukocytes. Culture on thiosulfate-citrate-bile salts-sucrose agar grows yellow colonies of oxidase-positive, curved gram-negative rods. The toxin responsible for his diarrhea acts by which mechanism?
A. ADP-ribosylation of elongation factor 2 B. ADP-ribosylation of the Gsα protein, keeping adenylate cyclase active C. Stimulation of guanylate cyclase in intestinal cells D. Nonspecific activation of large numbers of T cells E. Invasion and destruction of the colonic mucosa
Answer: B. Rice-water diarrhea in an outbreak, with oxidase-positive curved rods forming yellow colonies on TCBS, is cholera. Cholera toxin ADP-ribosylates Gsα, blocking GTP hydrolysis; constant cAMP production opens CFTR and drives chloride and water secretion. His tachycardia and dry mucosa mean rehydration comes first, with ORS if he can drink or IV isotonic fluid if he cannot keep up or is in shock; a single dose of doxycycline is an adjunct.
- A: ADP-ribosylation of elongation factor 2 is how diphtheria toxin stops protein synthesis and kills cells.
- C: guanylate cyclase stimulation (↑ cGMP) is the action of ETEC heat-stable toxin; ETEC's heat-labile toxin resembles cholera toxin, but the TCBS and oxidase findings point to Vibrio.
- D: nonspecific T-cell activation is the superantigen mechanism of toxic shock syndrome toxins, which cause high fever, hypotension and shock, not secretory diarrhea.
- E: invasion of the intestinal mucosa, as by Shigella, causes dysentery (mucus, pus and blood in stool, fever); V. cholerae does not invade the intestinal wall.
Key takeaways
- Comma-shaped, oxidase-positive, gram-negative rod that thrives in alkaline media and grows as yellow colonies on TCBS; O1 and O139 cause epidemic cholera.
- Cholera toxin: B binds GM1; A1 ADP-ribosylates Gsα → ↑ cAMP → CFTR chloride secretion plus blocked NaCl absorption → rice-water stool.
- Noninvasive: no blood, few or no fecal leukocytes; death comes from hypovolemic shock, with metabolic acidosis and hypokalemia.
- Treatment = rehydration (ORS works because sodium-glucose cotransport is intact; IV isotonic fluid when severe); single-dose doxycycline shortens illness (azithromycin or ciprofloxacin if resistant); zinc for young children.
- Vaxchora: live, single-dose oral vaccine for travelers aged 2-64, given at least 10 days before travel and not within 14 days of antibiotics; check US availability.
- Look-alikes: ETEC (LT works like cholera toxin), V. vulnificus (seafood or seawater wounds, liver disease, bullae), Shigella (bloody, invasive).
Sources
- Cholera — Merck Manual Professional Edition (2024)
- About Cholera — CDC (2024)
- Isolation and Identification of Vibrio cholerae Serogroups O1 and O139 (Laboratory Methods for the Diagnosis of Epidemic Dysentery and Cholera, Chapter 6) — CDC
- Cholera Toxin — ScienceDirect Topics, Elsevier
- Bacterial Infections of the Gastrointestinal Tract — OpenStax Microbiology (2016)
- Virulence Factors of Bacterial and Viral Pathogens — OpenStax Microbiology (2016)
- Enterotoxigenic Escherichia coli — ScienceDirect Topics, Elsevier
- Oral Rehydration — Merck Manual Professional Edition (2025)
- Metabolic Acidosis — Merck Manual Professional Edition (2025)
- Clinical Overview of Vibriosis — CDC (2024)
- VAXCHORA (Cholera Vaccine, Live, Oral) label — DailyMed, National Library of Medicine (2025)
- Ask the Experts: Cholera — Immunize.org
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
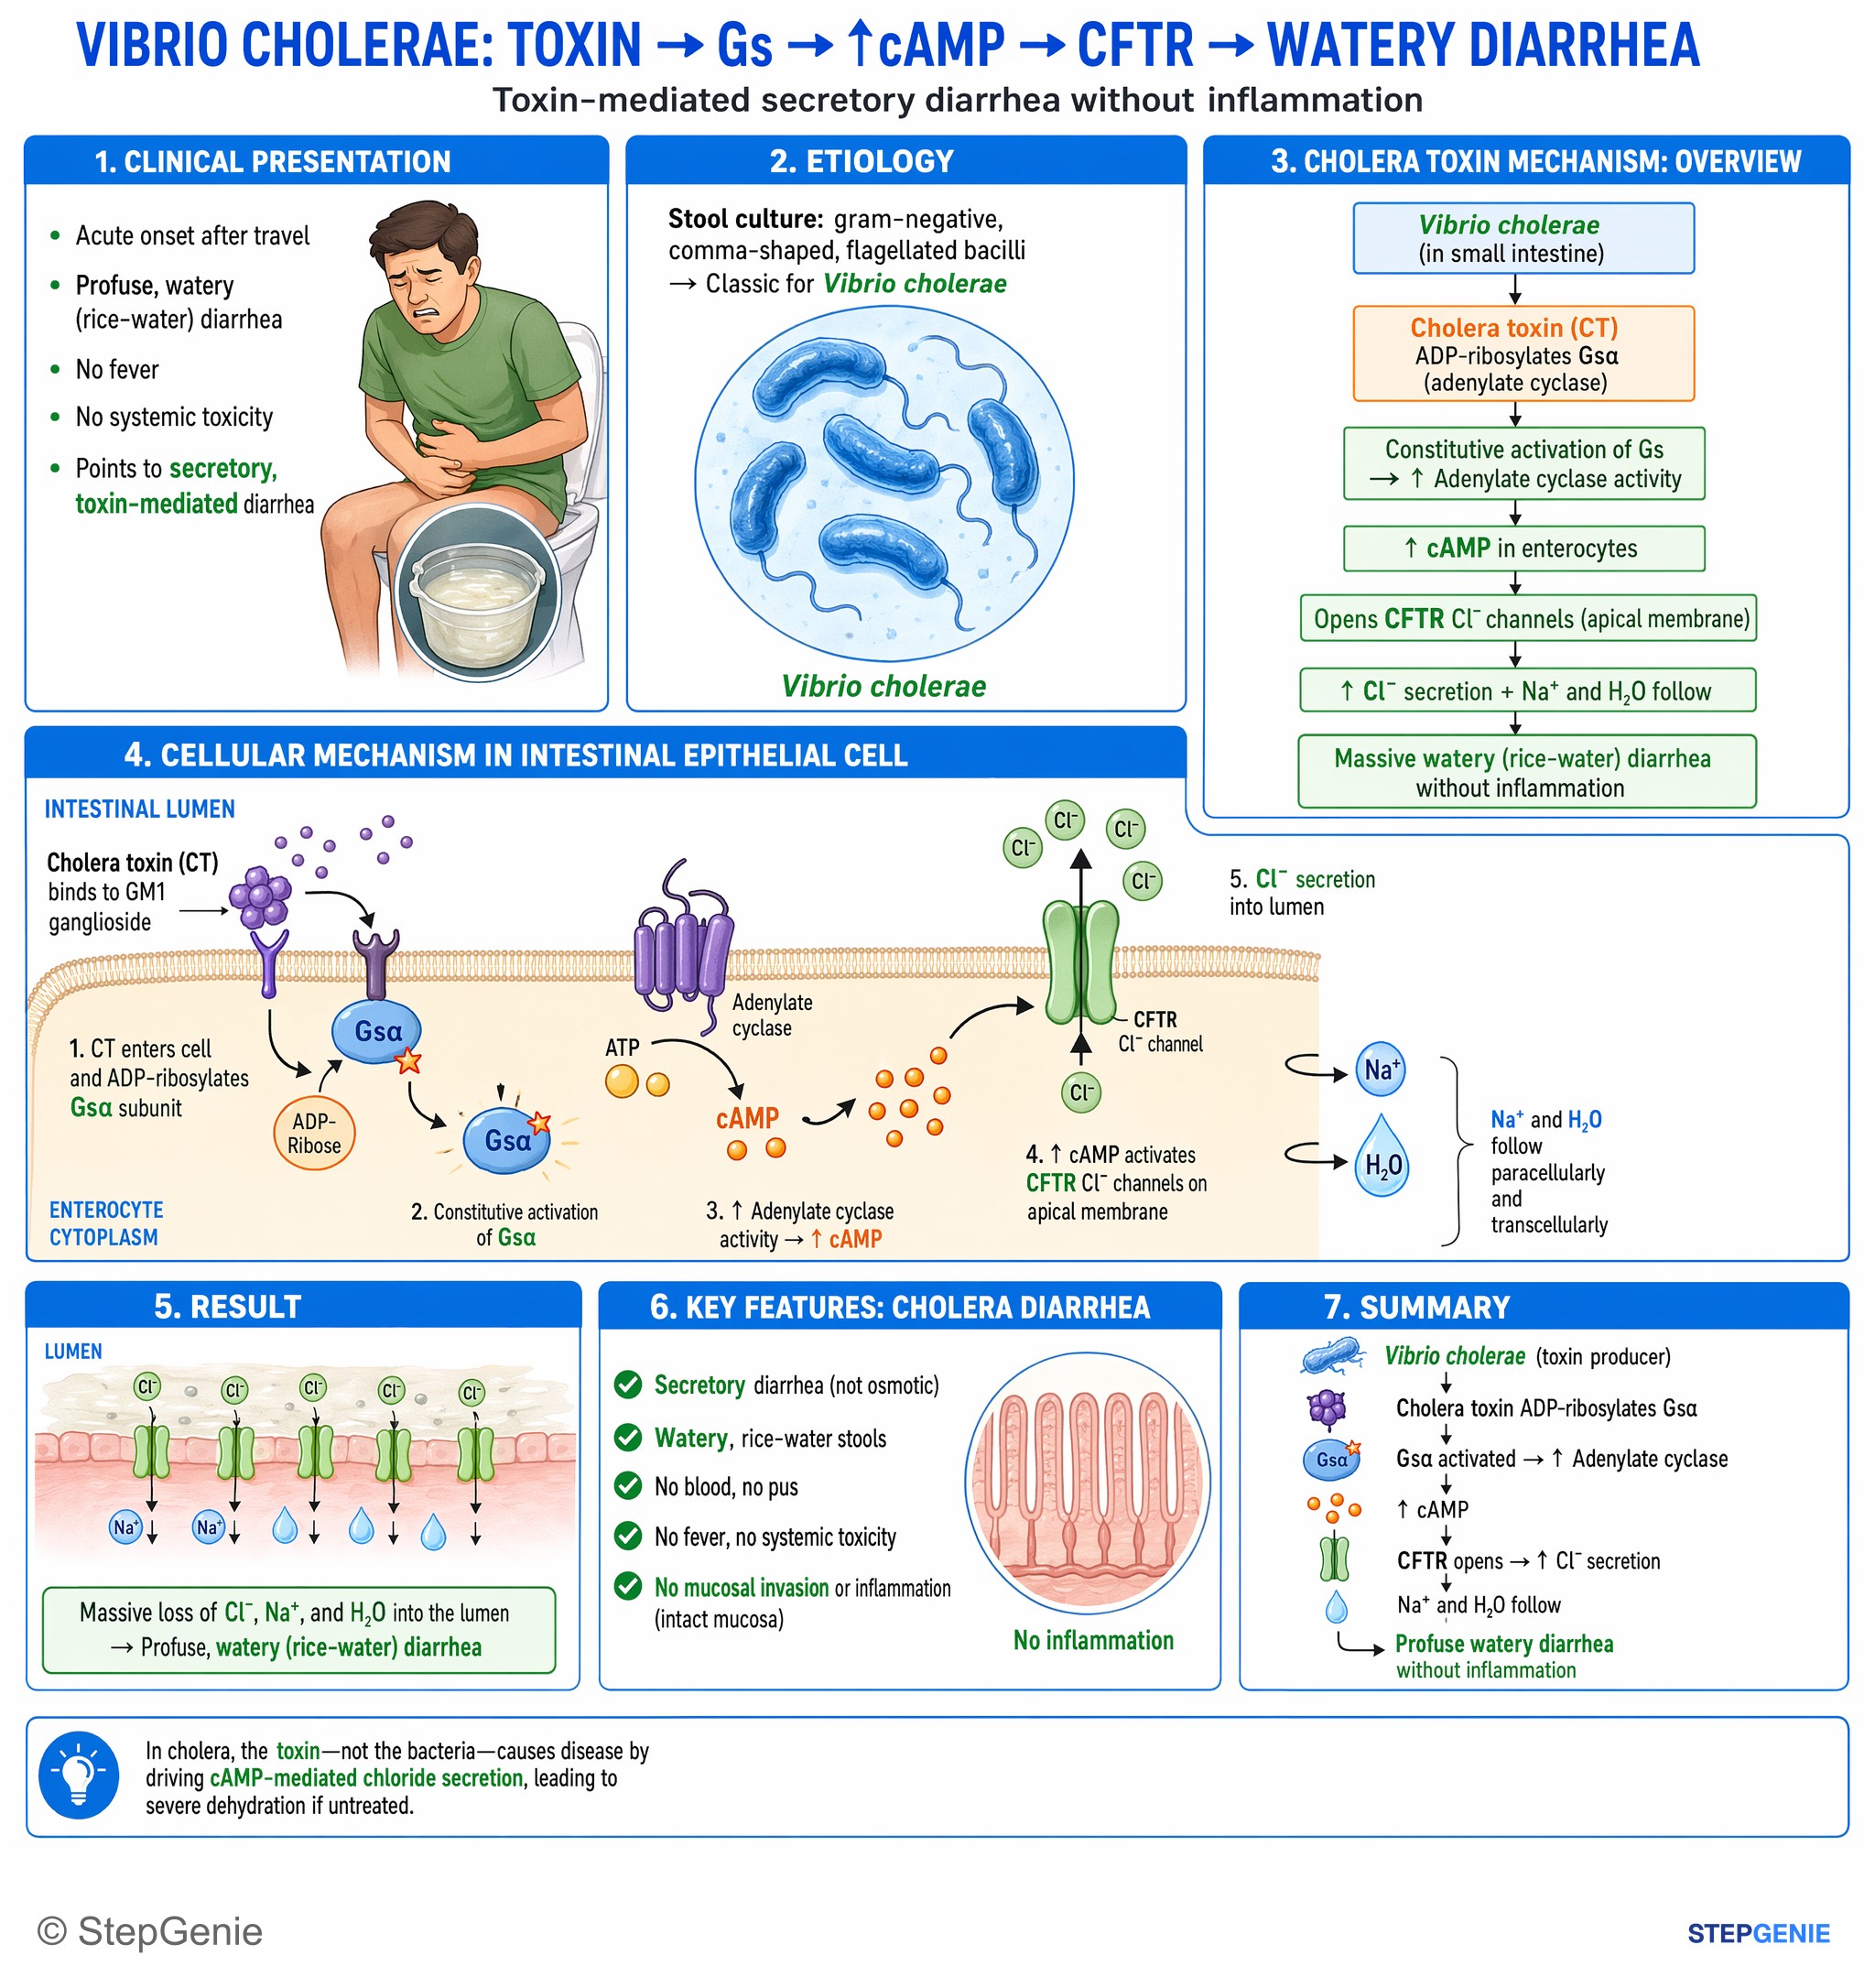
Vibrio cholerae → toxin activates Gs → ↑cAMP → opens intestinal CFTR → massive Cl⁻ and water secretion → profuse watery diarrhea without…
USMLE Step 1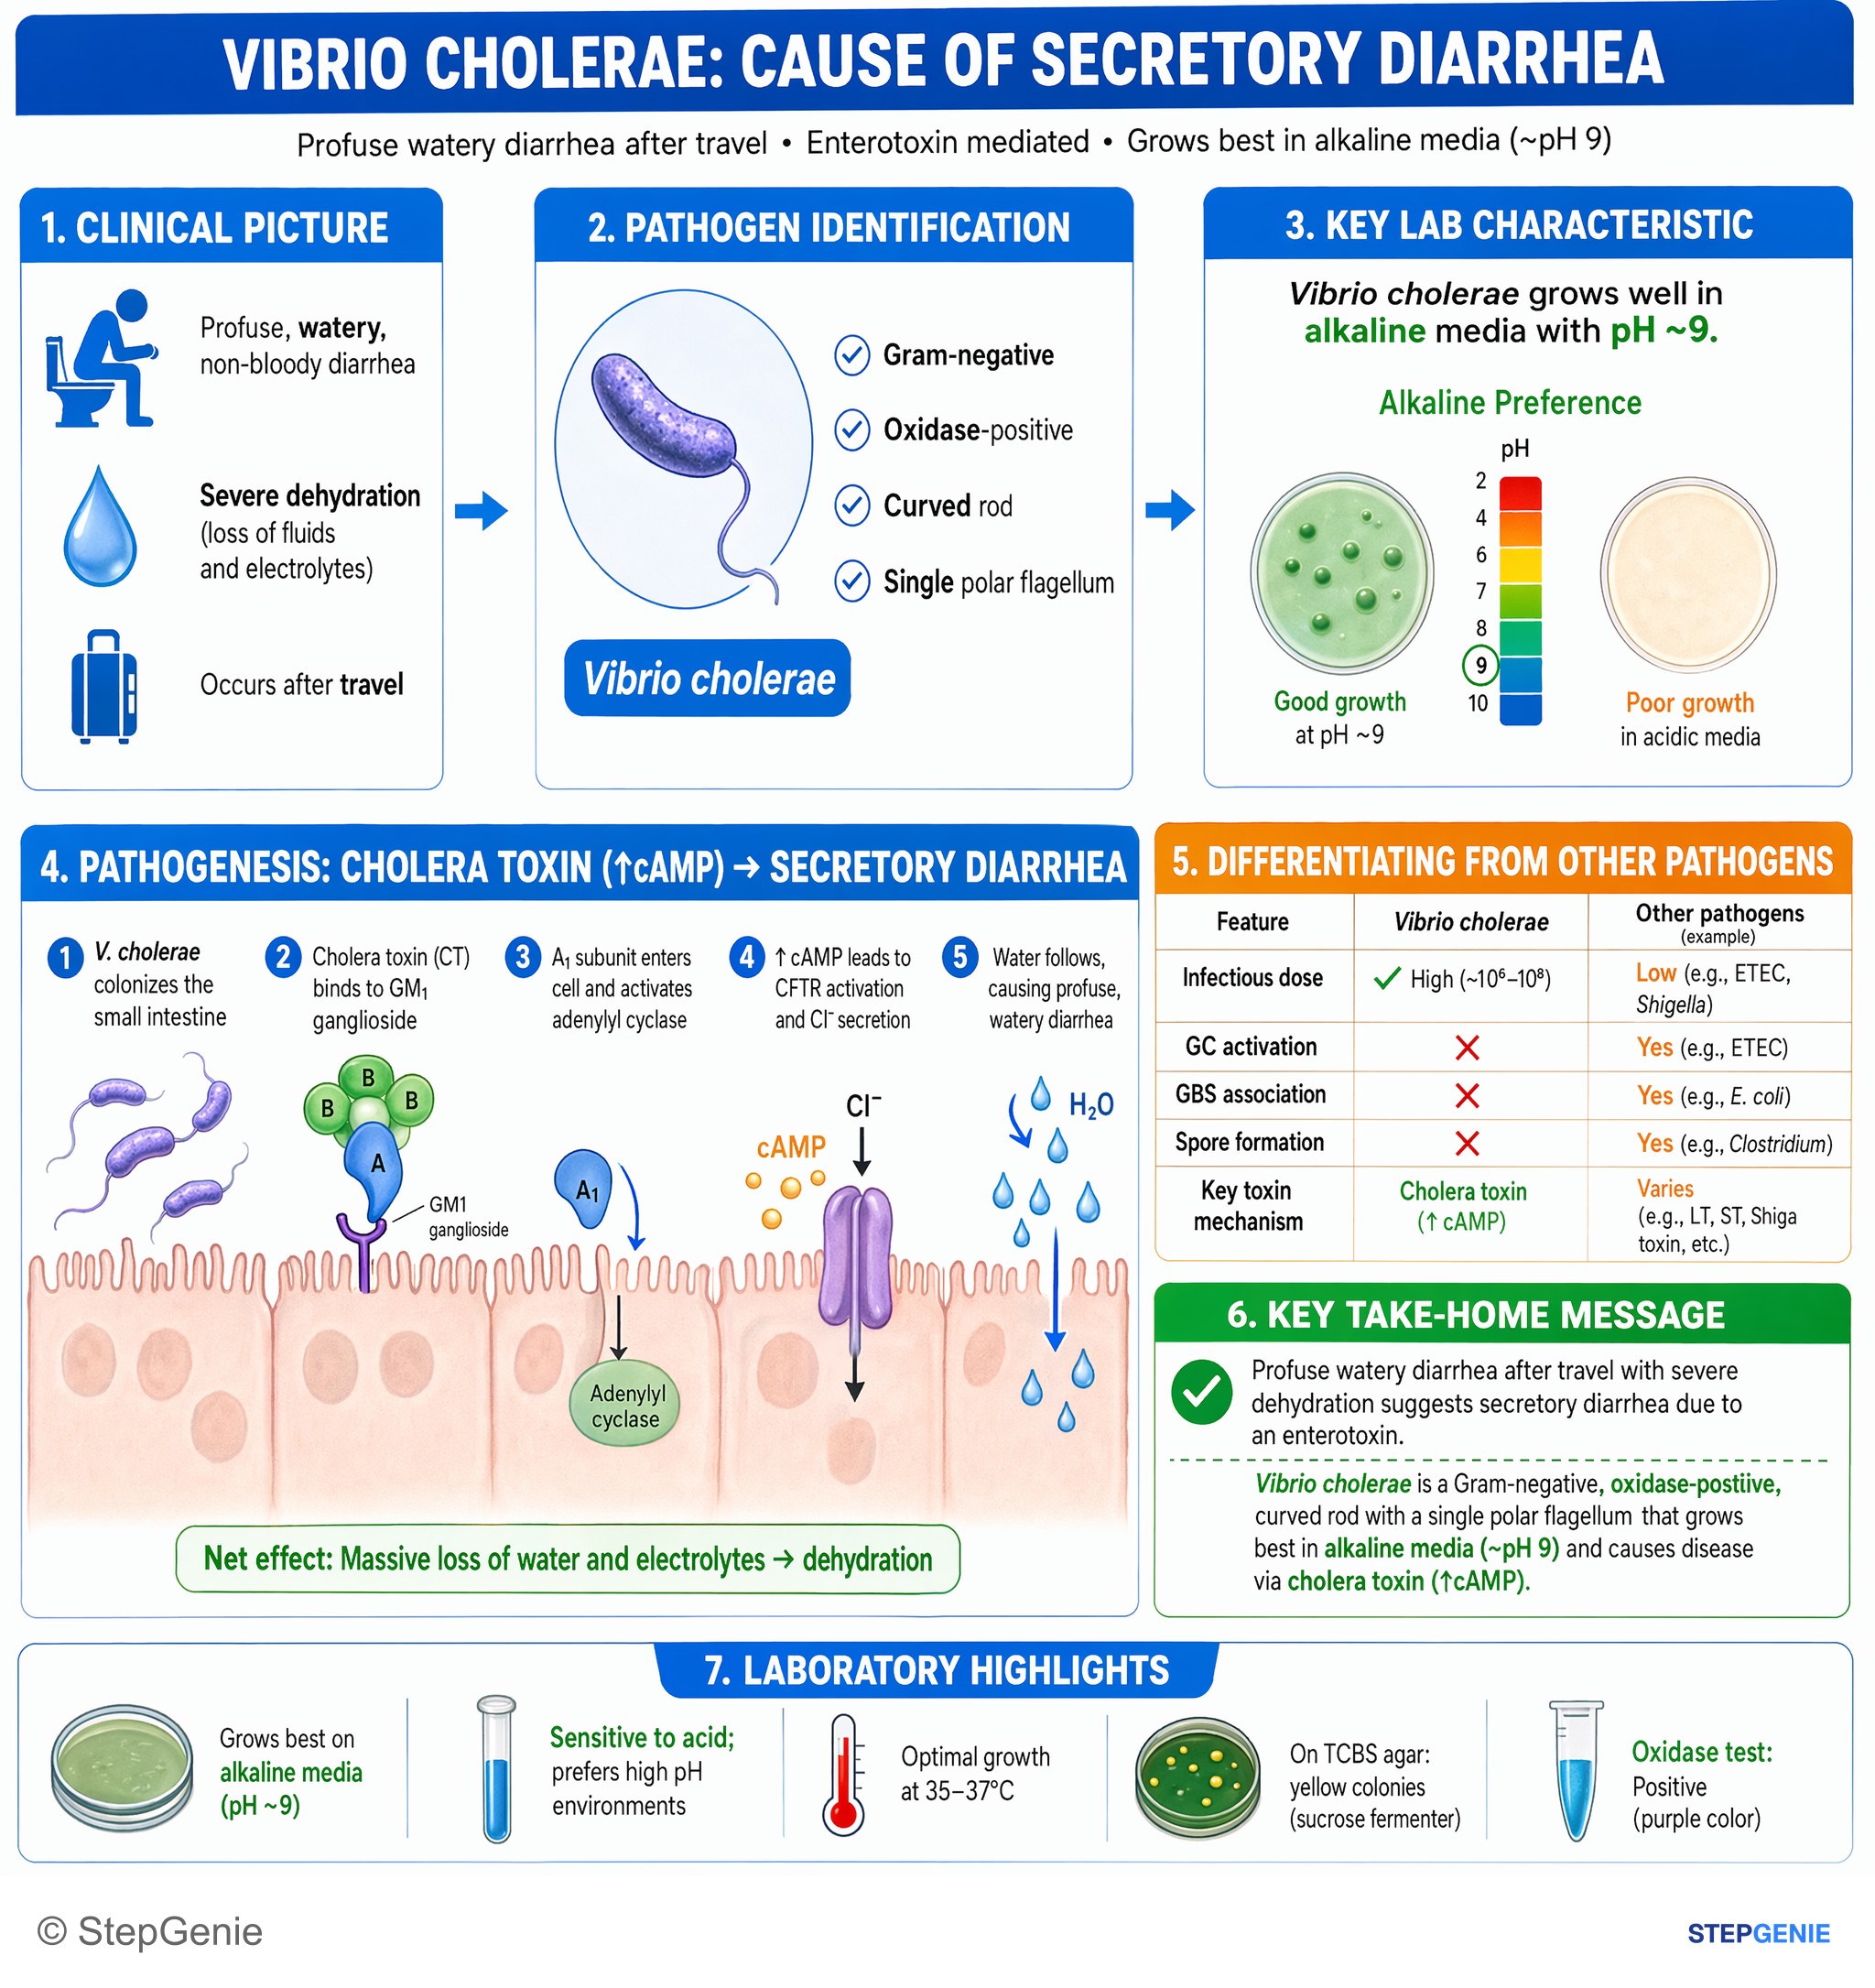
Vibrio cholerae causes profuse watery diarrhea via cholera toxin (↑cAMP) and grows best in alkaline media (around pH 9).
USMLE Step 1Frequently Asked Questions
How does cholera toxin cause diarrhea?
Cholera toxin is an AB5 toxin. Its five B subunits bind GM1 ganglioside on small-intestinal cells, and the A1 fragment ADP-ribosylates the Gs alpha protein so it cannot hydrolyze GTP. Adenylate cyclase stays on, cAMP rises, and protein kinase A opens the CFTR chloride channel while cAMP also blocks sodium chloride absorption. Chloride, sodium and water pour into the lumen, producing isotonic rice-water diarrhea without any invasion of the mucosa.
Why does cholera cause watery diarrhea without blood?
Vibrio cholerae does not invade the intestinal wall. It colonizes the small-bowel lining and releases a toxin that makes the cells secrete an isotonic salt solution, so stool is watery and nonbloody with few or no white blood cells, and in adults output can exceed 1 liter per hour. Invasive organisms such as Shigella invade the intestinal lining instead, producing stools that may contain mucus, pus and blood, along with fever and abdominal cramps.
What is the treatment for cholera?
Rehydration is the cornerstone. Oral rehydration solution works for most patients because sodium-glucose cotransport in the gut is intact, and hypovolemic or severely dehydrated patients need isotonic IV fluid, then oral solution. Untreated cholera kills more than half of patients, but with timely rehydration about 1 percent die. Antibiotics are an adjunct: a single dose of doxycycline is first-line for adults, including pregnant patients, and for children, with azithromycin or ciprofloxacin if doxycycline resistance is documented. Zinc helps young children.
How is Vibrio cholerae identified in the lab?
Vibrio cholerae is a curved, comma-shaped, flagellated gram-negative rod that is oxidase-positive and thrives in alkaline conditions. Stool is enriched in alkaline peptone water and plated on thiosulfate-citrate-bile salts-sucrose (TCBS) agar, where it forms yellow, sucrose-fermenting colonies; agglutination with O1 or O139 antisera identifies the serogroup, and PCR is also used. Dark-field microscopy shows darting shooting-star motility. Rapid dipstick tests have suboptimal specificity, so culture remains the confirmatory test.
Is there a cholera vaccine in the United States?
Vaxchora (CVD 103-HgR), a live attenuated vaccine taken as a single oral dose, is the FDA-licensed cholera vaccine in the US. It is labeled for travelers aged 2 to 64 going to cholera-affected areas, and ACIP recommends it for travelers going to areas of active transmission. Give it at least 10 days before exposure and not within 14 days after antibiotics. It reduced moderate to severe diarrhea by about 90 percent at 10 days and 80 percent at 3 months. Production was halted in late 2020, so check current availability.
How is cholera different from ETEC travelers' diarrhea?
Both cause watery, noninvasive diarrhea. ETEC's heat-labile toxin shares about 80 percent of its amino acid sequence with cholera toxin and also raises cAMP, while its heat-stable toxin, a small peptide, stimulates guanylate cyclase. ETEC is the most common cause of travelers' diarrhea and ranges from mild illness to cholera-like purging. Vibrio cholerae is a curved, oxidase-positive rod that grows as yellow colonies on TCBS agar and causes epidemics when drinking water and sanitation fail.