Helicobacter pylori is one of those Step 1 organisms that keeps showing up because it connects micro to GI pathology, immunology, and pharm in a super testable way. If you can explain how this bug survives stomach acid, causes both ulcers and cancer, and how to diagnose/treat it, you’ve basically built a mini “integrated vignette engine” for exam day.
What is Helicobacter pylori?
Definition: H. pylori is a gram-negative, curved/spiral-shaped, motile, urease-positive bacillus that colonizes the gastric antrum and causes chronic gastritis, peptic ulcer disease, and is strongly associated with gastric adenocarcinoma and MALT lymphoma.
First Aid cross-reference: Microbiology → Gram-negative bacteria (curved rods); GI pathology → chronic gastritis/peptic ulcer disease; Oncology → gastric adenocarcinoma, MALT lymphoma.
Core microbiology (high-yield ID features)
Classic “buzzwords” that should trigger H. pylori
- Gram-negative curved rod
- Urease positive
- Oxidase positive
- Motile (flagella)
- Colonizes antrum
- Causes duodenal ulcers + gastric ulcers
- Associated with gastric cancer + MALT lymphoma
Quick ID table (Step-style)
| Feature | H. pylori | Why it matters on USMLE |
|---|---|---|
| Shape | Curved/spiral gram-negative rod | Helps distinguish from enteric straight rods |
| Urease | Positive | Survives acidic stomach by making ammonia |
| Location | Gastric antrum | Increased gastrin → acid → duodenal ulcers |
| Pathology | Chronic active gastritis | Links micro → inflammation → malignancy |
| Cancer link | Gastric adenocarcinoma, MALT lymphoma | Very high-yield associations |
Pathophysiology: how it survives acid and causes disease
1) Survival mechanism: urease is the “acid shield”
H. pylori produces urease, which converts urea into ammonia (NH₃) and CO₂. Ammonia locally buffers gastric acid, creating a friendlier microenvironment.
- Reaction conceptually: urea → NH₃ (basic) + CO₂
- Clinical test tie-in: urease positivity is the basis of the urea breath test.
2) Mucosal injury and inflammation
Even though it survives acid, it injures the mucosa via:
- Inflammation (neutrophils + chronic mononuclear infiltrate)
- Disruption of mucus layer
- Virulence factors (classically tested):
- CagA (cytotoxin-associated gene A): linked to more severe inflammation and higher cancer risk
- VacA (vacuolating cytotoxin): epithelial injury
3) Why duodenal ulcers are so common (board favorite chain)
Antral-predominant infection tends to decrease somatostatin from D cells → increase gastrin → increase acid production by parietal cells → acid load spills into duodenum → duodenal ulceration.
A simple way to remember the Step logic:
- Antrum infection → ↑ gastrin → ↑ acid → duodenal ulcers
4) Cancer and lymphoma associations
Chronic infection → chronic gastritis → atrophy/metaplasia/dysplasia pathway:
- Gastric adenocarcinoma (intestinal-type classically associated with chronic gastritis)
- MALT lymphoma (extranodal marginal zone lymphoma)
Huge Step pearl: Early MALT lymphoma can regress with H. pylori eradication.
First Aid cross-reference: GI pathology (chronic gastritis → ulcers), Oncology (MALT lymphoma and gastric adenocarcinoma association).
Clinical presentation (what vignettes look like)
Common symptoms
- Epigastric pain/dyspepsia
- Nausea, bloating, early satiety
- May be asymptomatic until ulcer complications
Ulcer-pattern clues
Duodenal ulcer (classically H. pylori):
- Pain often improves with meals (then returns later)
- Can have nighttime pain
- Melena if bleeding
Gastric ulcer (can be H. pylori or NSAIDs):
- Pain may worsen with meals
- Weight loss more common (food avoidance)
Red flags (alarm features)
If the stem mentions these, think endoscopy rather than “test-and-treat”:
- GI bleeding, iron deficiency anemia
- Unintentional weight loss
- Progressive dysphagia/odynophagia
- Persistent vomiting
- Family history of gastric cancer
- Palpable mass/lymphadenopathy
Diagnosis: best tests and when to use them
Noninvasive tests (very high-yield)
1) Urea breath test
- Patient ingests labeled urea (e.g., )
- If urease present → labeled CO₂ detected in breath
- Great for initial diagnosis and test of cure
2) Stool antigen test
- Detects H. pylori antigens
- Also used for test of cure
Step tip: For confirming eradication, prefer urea breath or stool antigen, not serology.
Serology (IgG): why it’s less favored
- Can remain positive after treatment
- Not reliable for active infection vs past exposure
Endoscopy + biopsy (invasive)
Used with alarm symptoms or complicated disease. Biopsy can show:
- Organisms on special stains
- Rapid urease test on biopsy specimen
Treatment (and what Step 1 loves to test)
General principle
Treat with combination therapy to overcome resistance and ensure eradication.
Classic regimens (know the components)
Triple therapy (classic board answer):
- PPI + clarithromycin + amoxicillin
- Use metronidazole if penicillin allergy
Bismuth quadruple therapy (common in practice and testable):
- PPI + bismuth + tetracycline + metronidazole
High-yield: Clarithromycin resistance is common; many guidelines favor bismuth quadruple therapy as first-line in areas with high resistance. For Step, recognize both regimens.
Test of cure (often asked)
Confirm eradication with:
- Urea breath test or stool antigen
- Done at least 4 weeks after antibiotics and after being off PPIs for ~2 weeks (PPIs can cause false negatives)
High-yield associations & “gotcha” facts
Diseases caused/associated with H. pylori
- Chronic gastritis
- Peptic ulcer disease (especially duodenal ulcers)
- Gastric adenocarcinoma
- MALT lymphoma (may regress with eradication)
How to distinguish from NSAID ulcers (classic comparison)
| Feature | H. pylori ulcers | NSAID ulcers |
|---|---|---|
| Mechanism | Inflammation + ↑ acid (often via ↑ gastrin) | ↓ prostaglandins → ↓ mucus/bicarb, ↓ mucosal blood flow |
| Cancer association | Yes (adenocarcinoma, MALT) | Not directly |
| Treat | Eradication regimen + PPI | Stop NSAID + PPI/misoprostol |
HY vignette triggers
- “Urease positive curved gram-negative rod”
- “Duodenal ulcer in someone without NSAID use”
- “Chronic gastritis in the antrum”
- “MALT lymphoma improves after antibiotics”
- “Positive urea breath test”
First Aid-style rapid review (what to memorize)
- Gram-negative curved rod, urease+, oxidase+, motile
- Antral colonization → ↑ gastrin → ↑ acid → duodenal ulcers
- Urea breath test and stool antigen = best noninvasive tests (and for cure)
- Treat with:
- PPI + clarithromycin + amoxicillin (or metronidazole), or
- Bismuth quadruple therapy (PPI + bismuth + tetracycline + metronidazole)
- Associated with gastric adenocarcinoma and MALT lymphoma (can regress after eradication)
Mini self-check (Step 1 quick questions)
-
Why does H. pylori survive in the stomach?
Urease → ammonia buffers local acid. -
Best test to confirm eradication after treatment?
Urea breath test or stool antigen (not serology). -
Bug + malignancy pair you should never miss?
H. pylori → gastric adenocarcinoma + MALT lymphoma.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
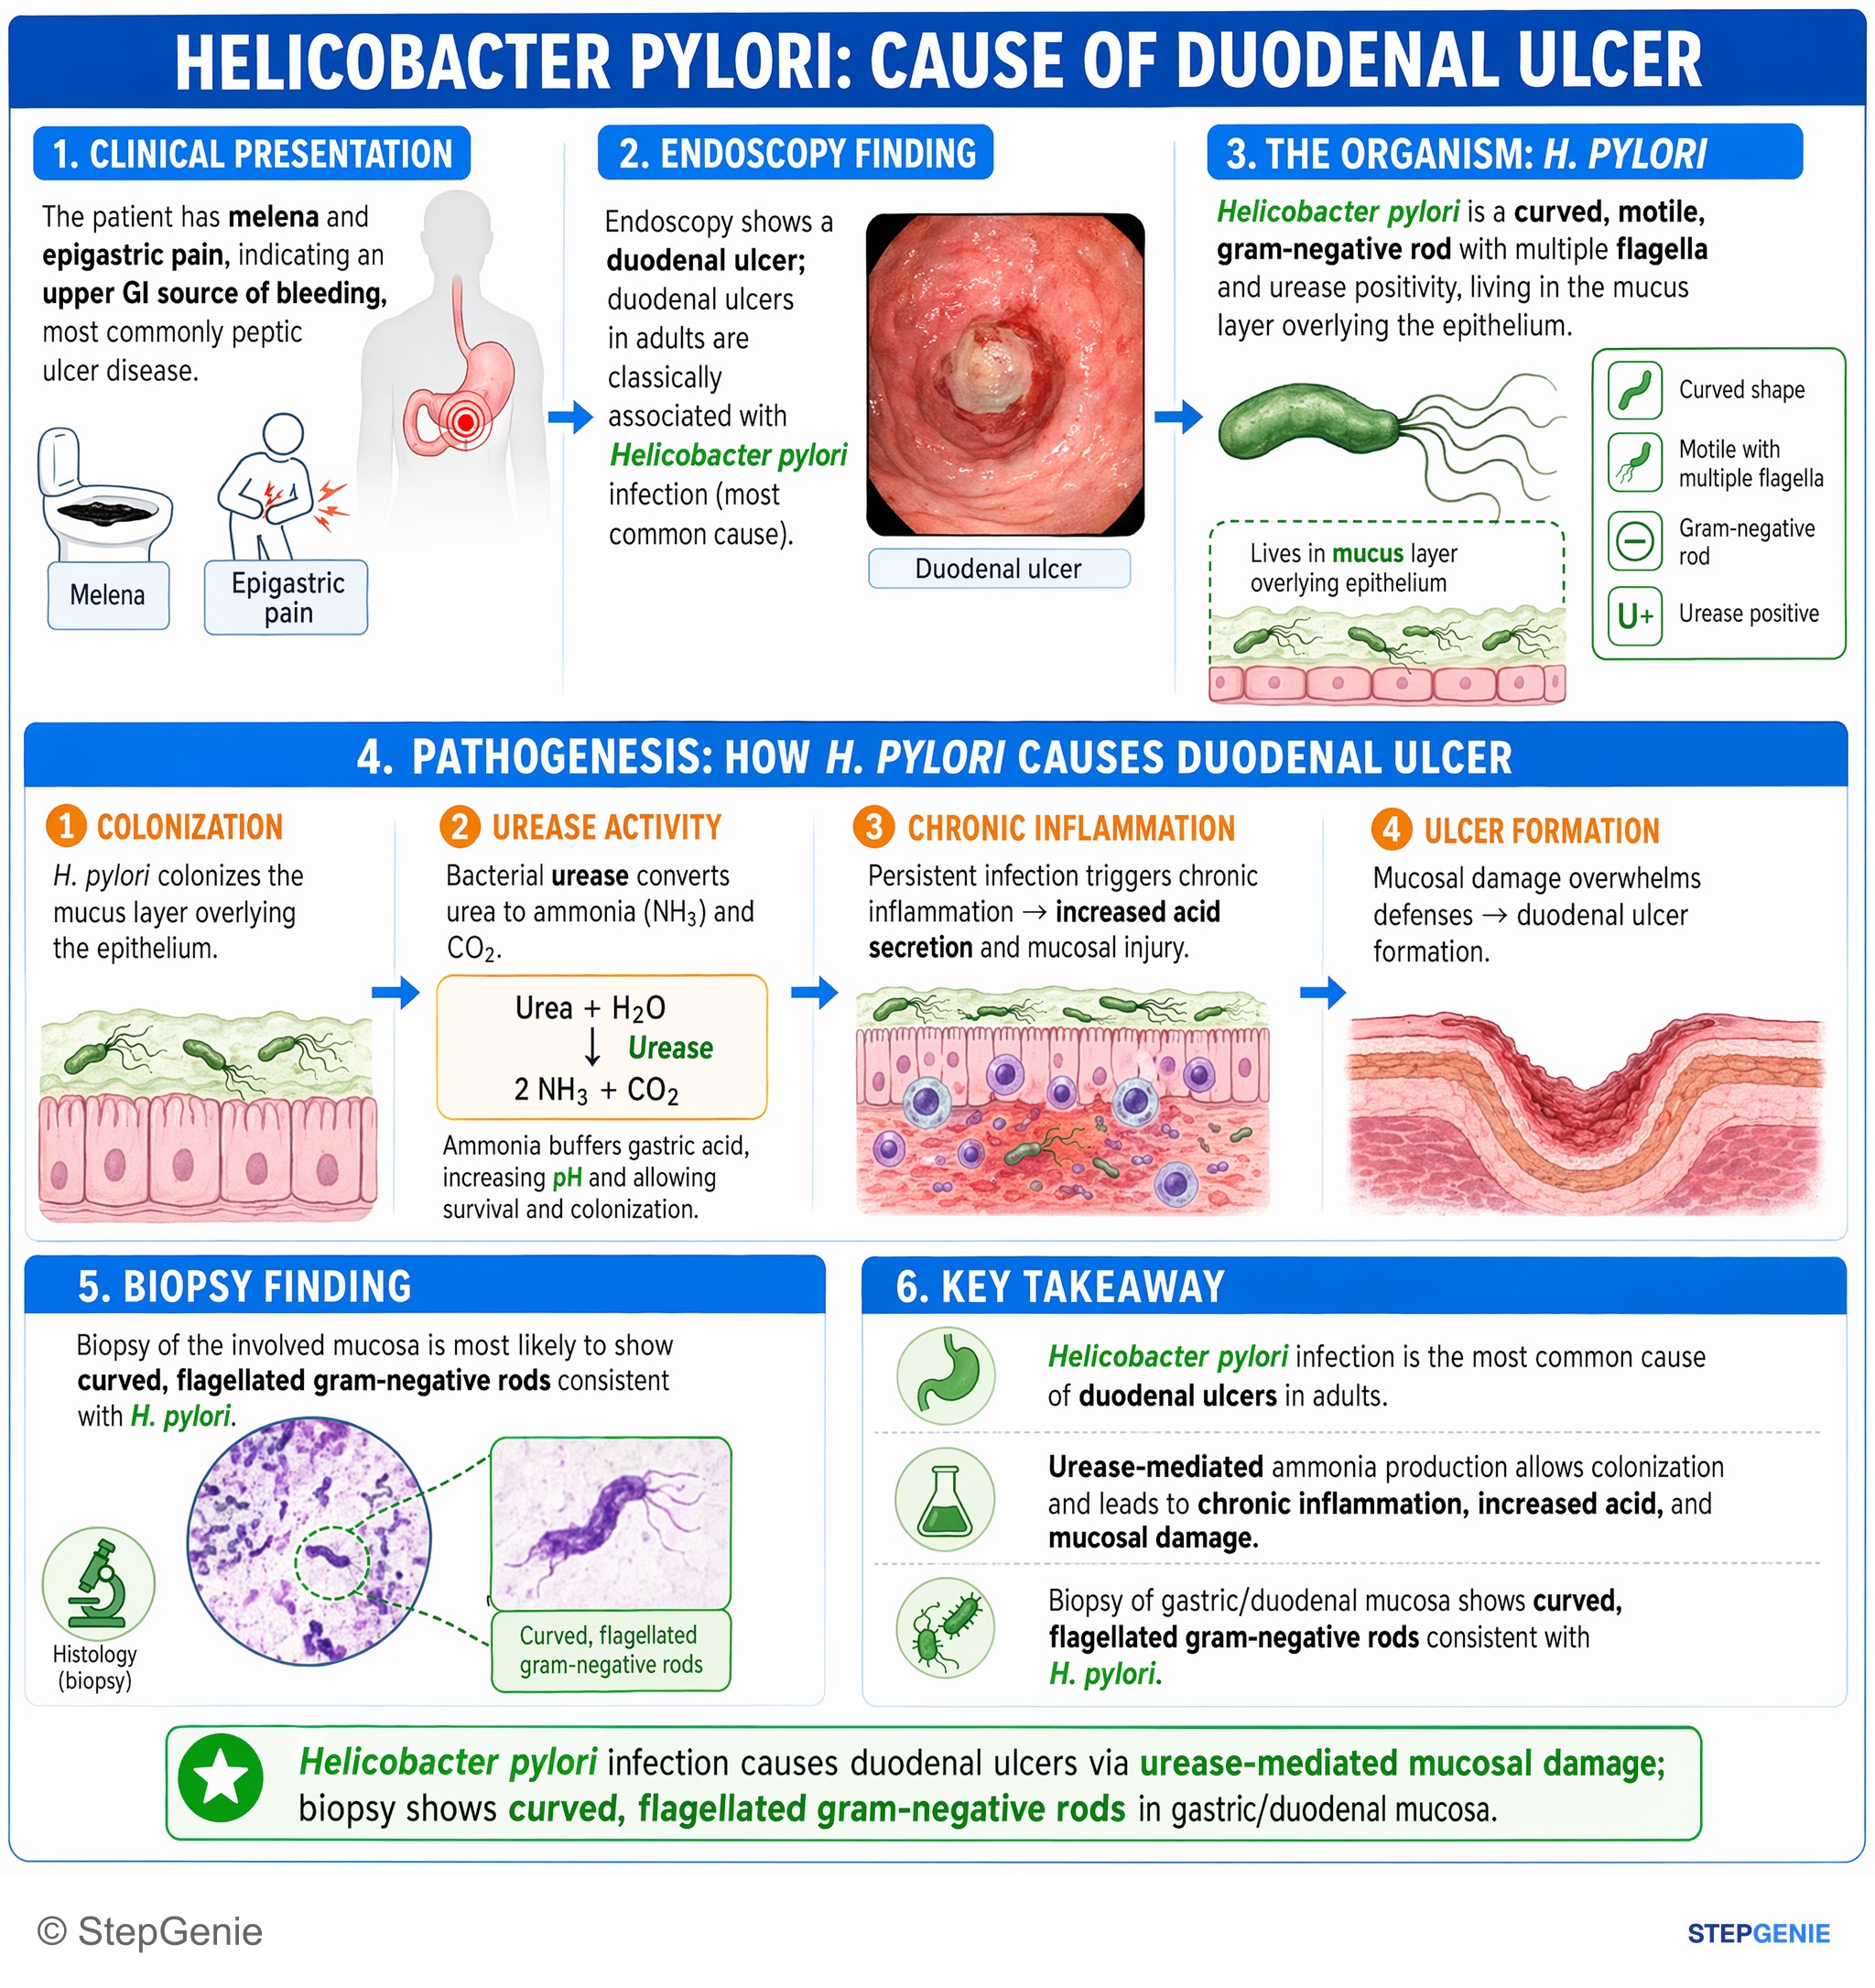
Helicobacter pylori infection causes duodenal ulcers via urease-mediated mucosal damage; biopsy shows curved, flagellated gram-negative…
USMLE Step 1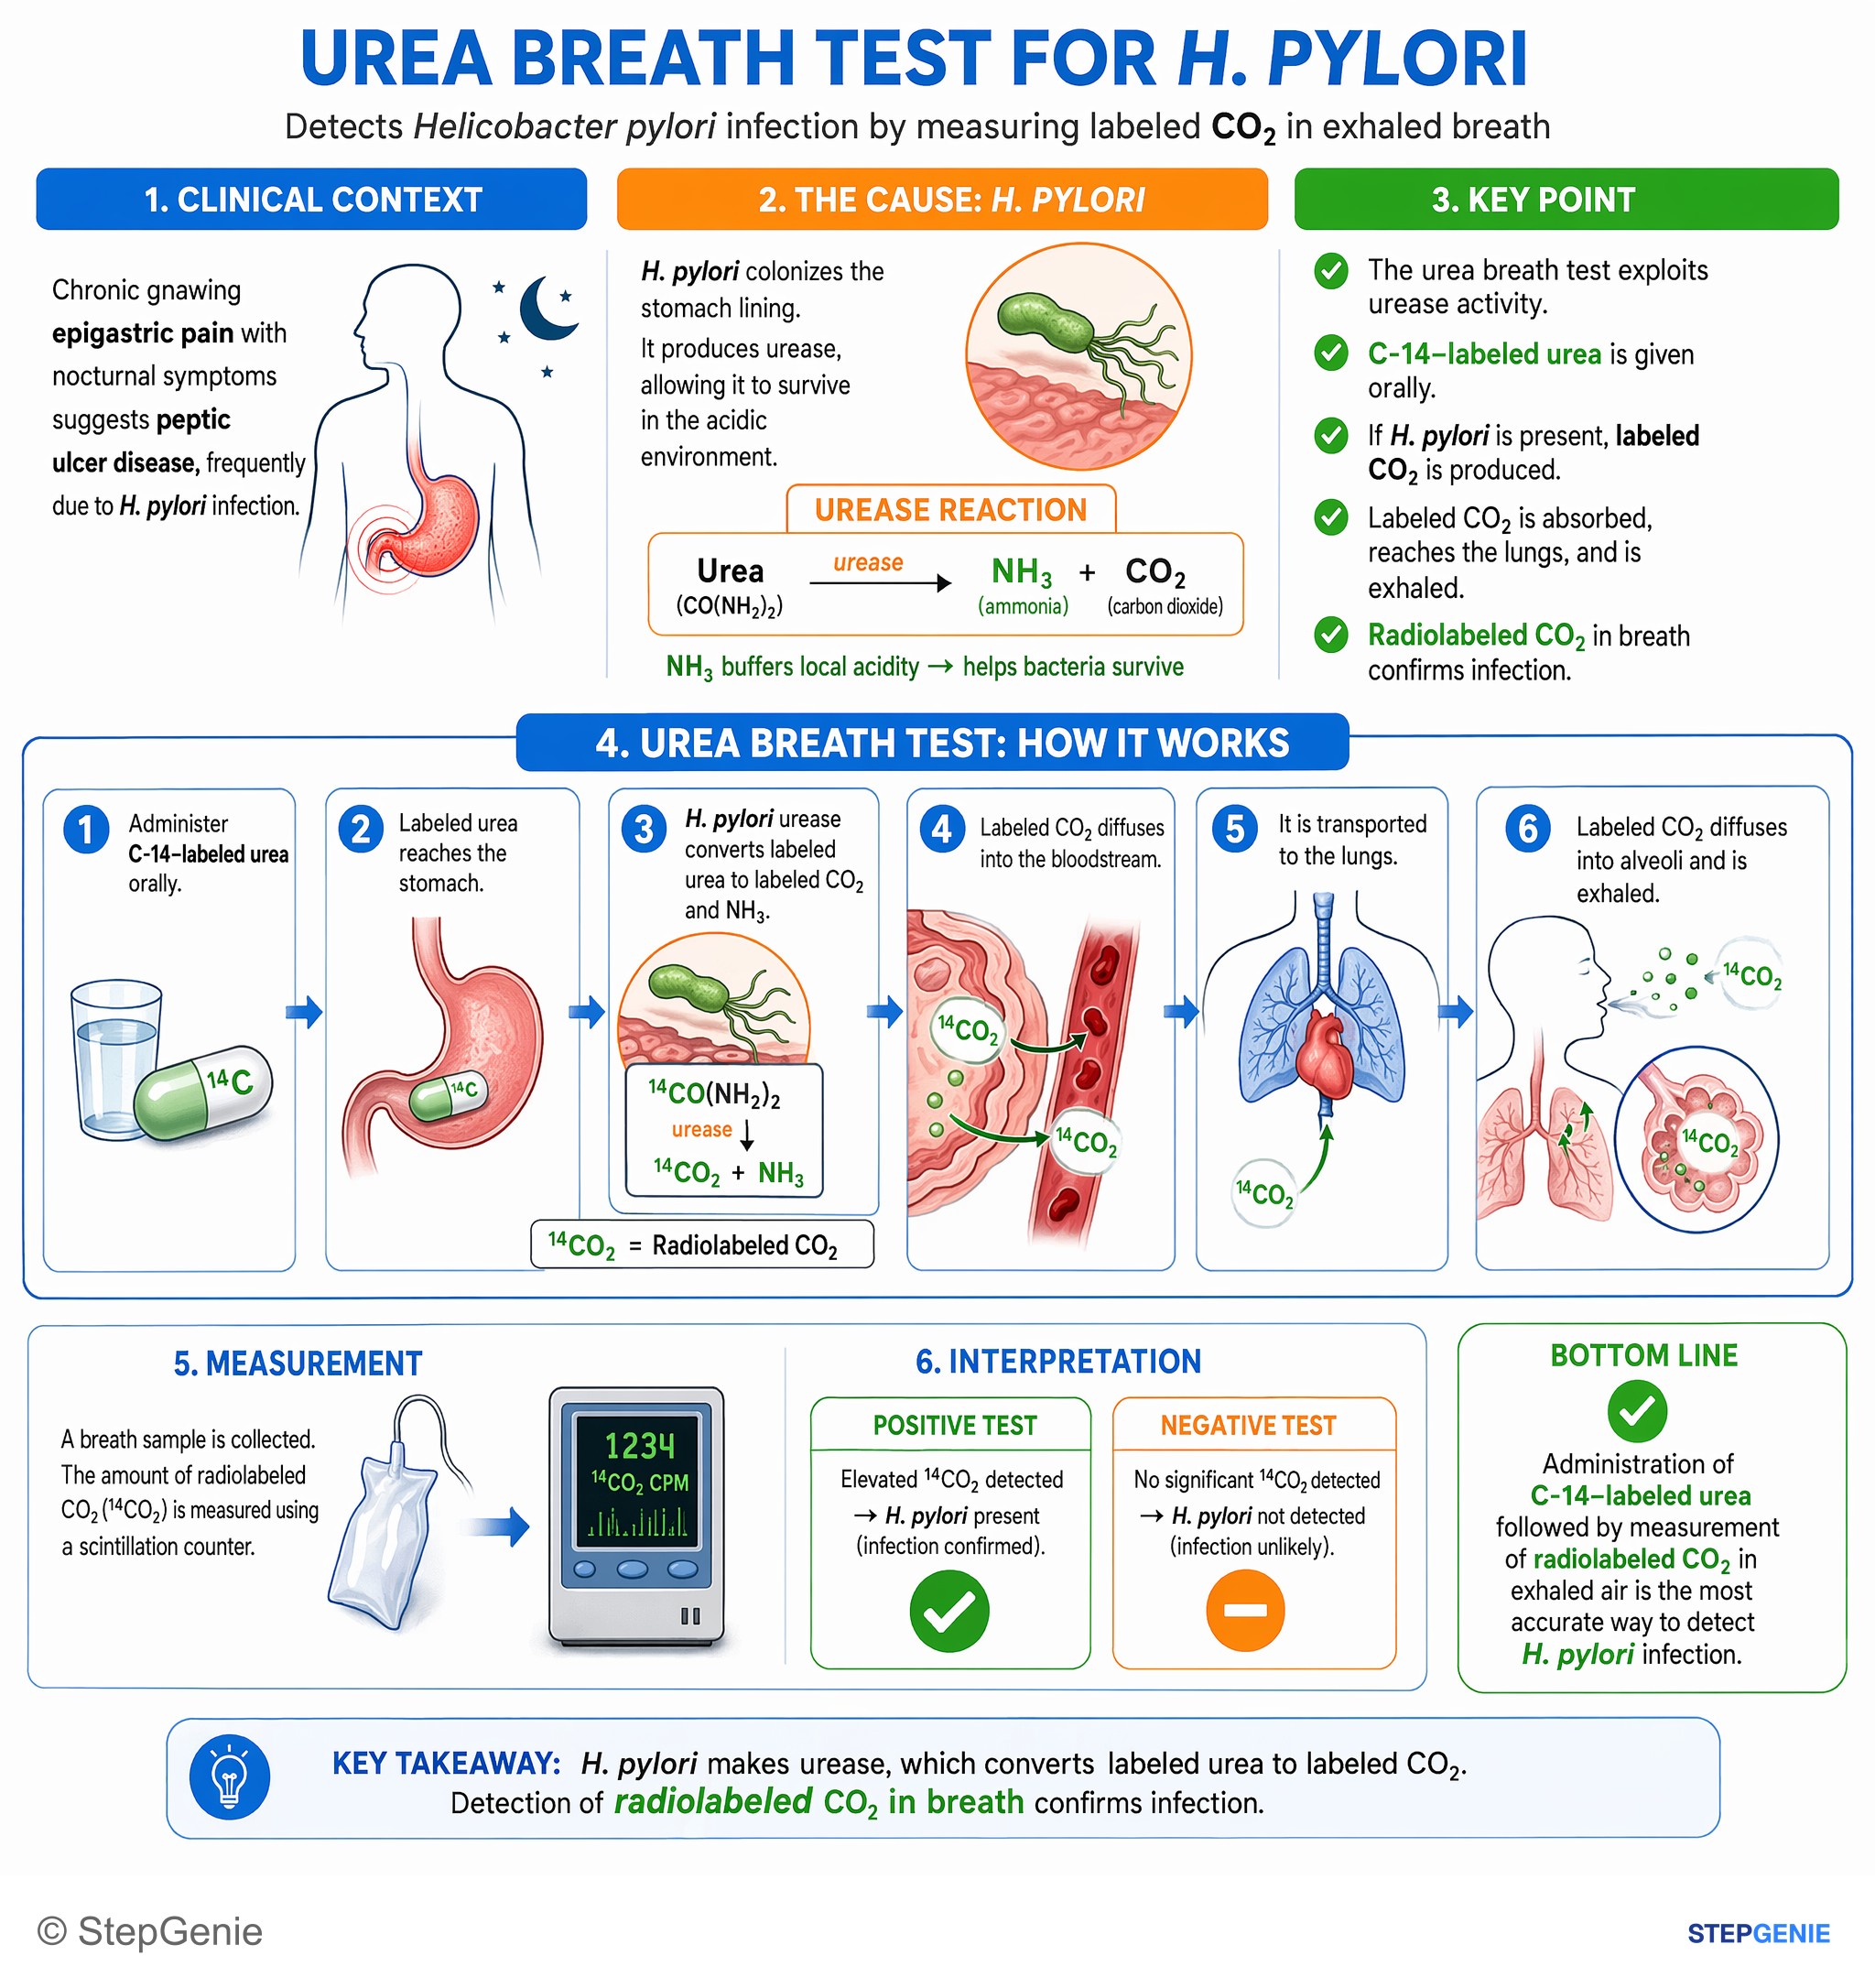
Helicobacter pylori makes urease, which converts labeled urea to labeled CO₂; detection of radiolabeled CO₂ in breath confirms infection.
USMLE Step 1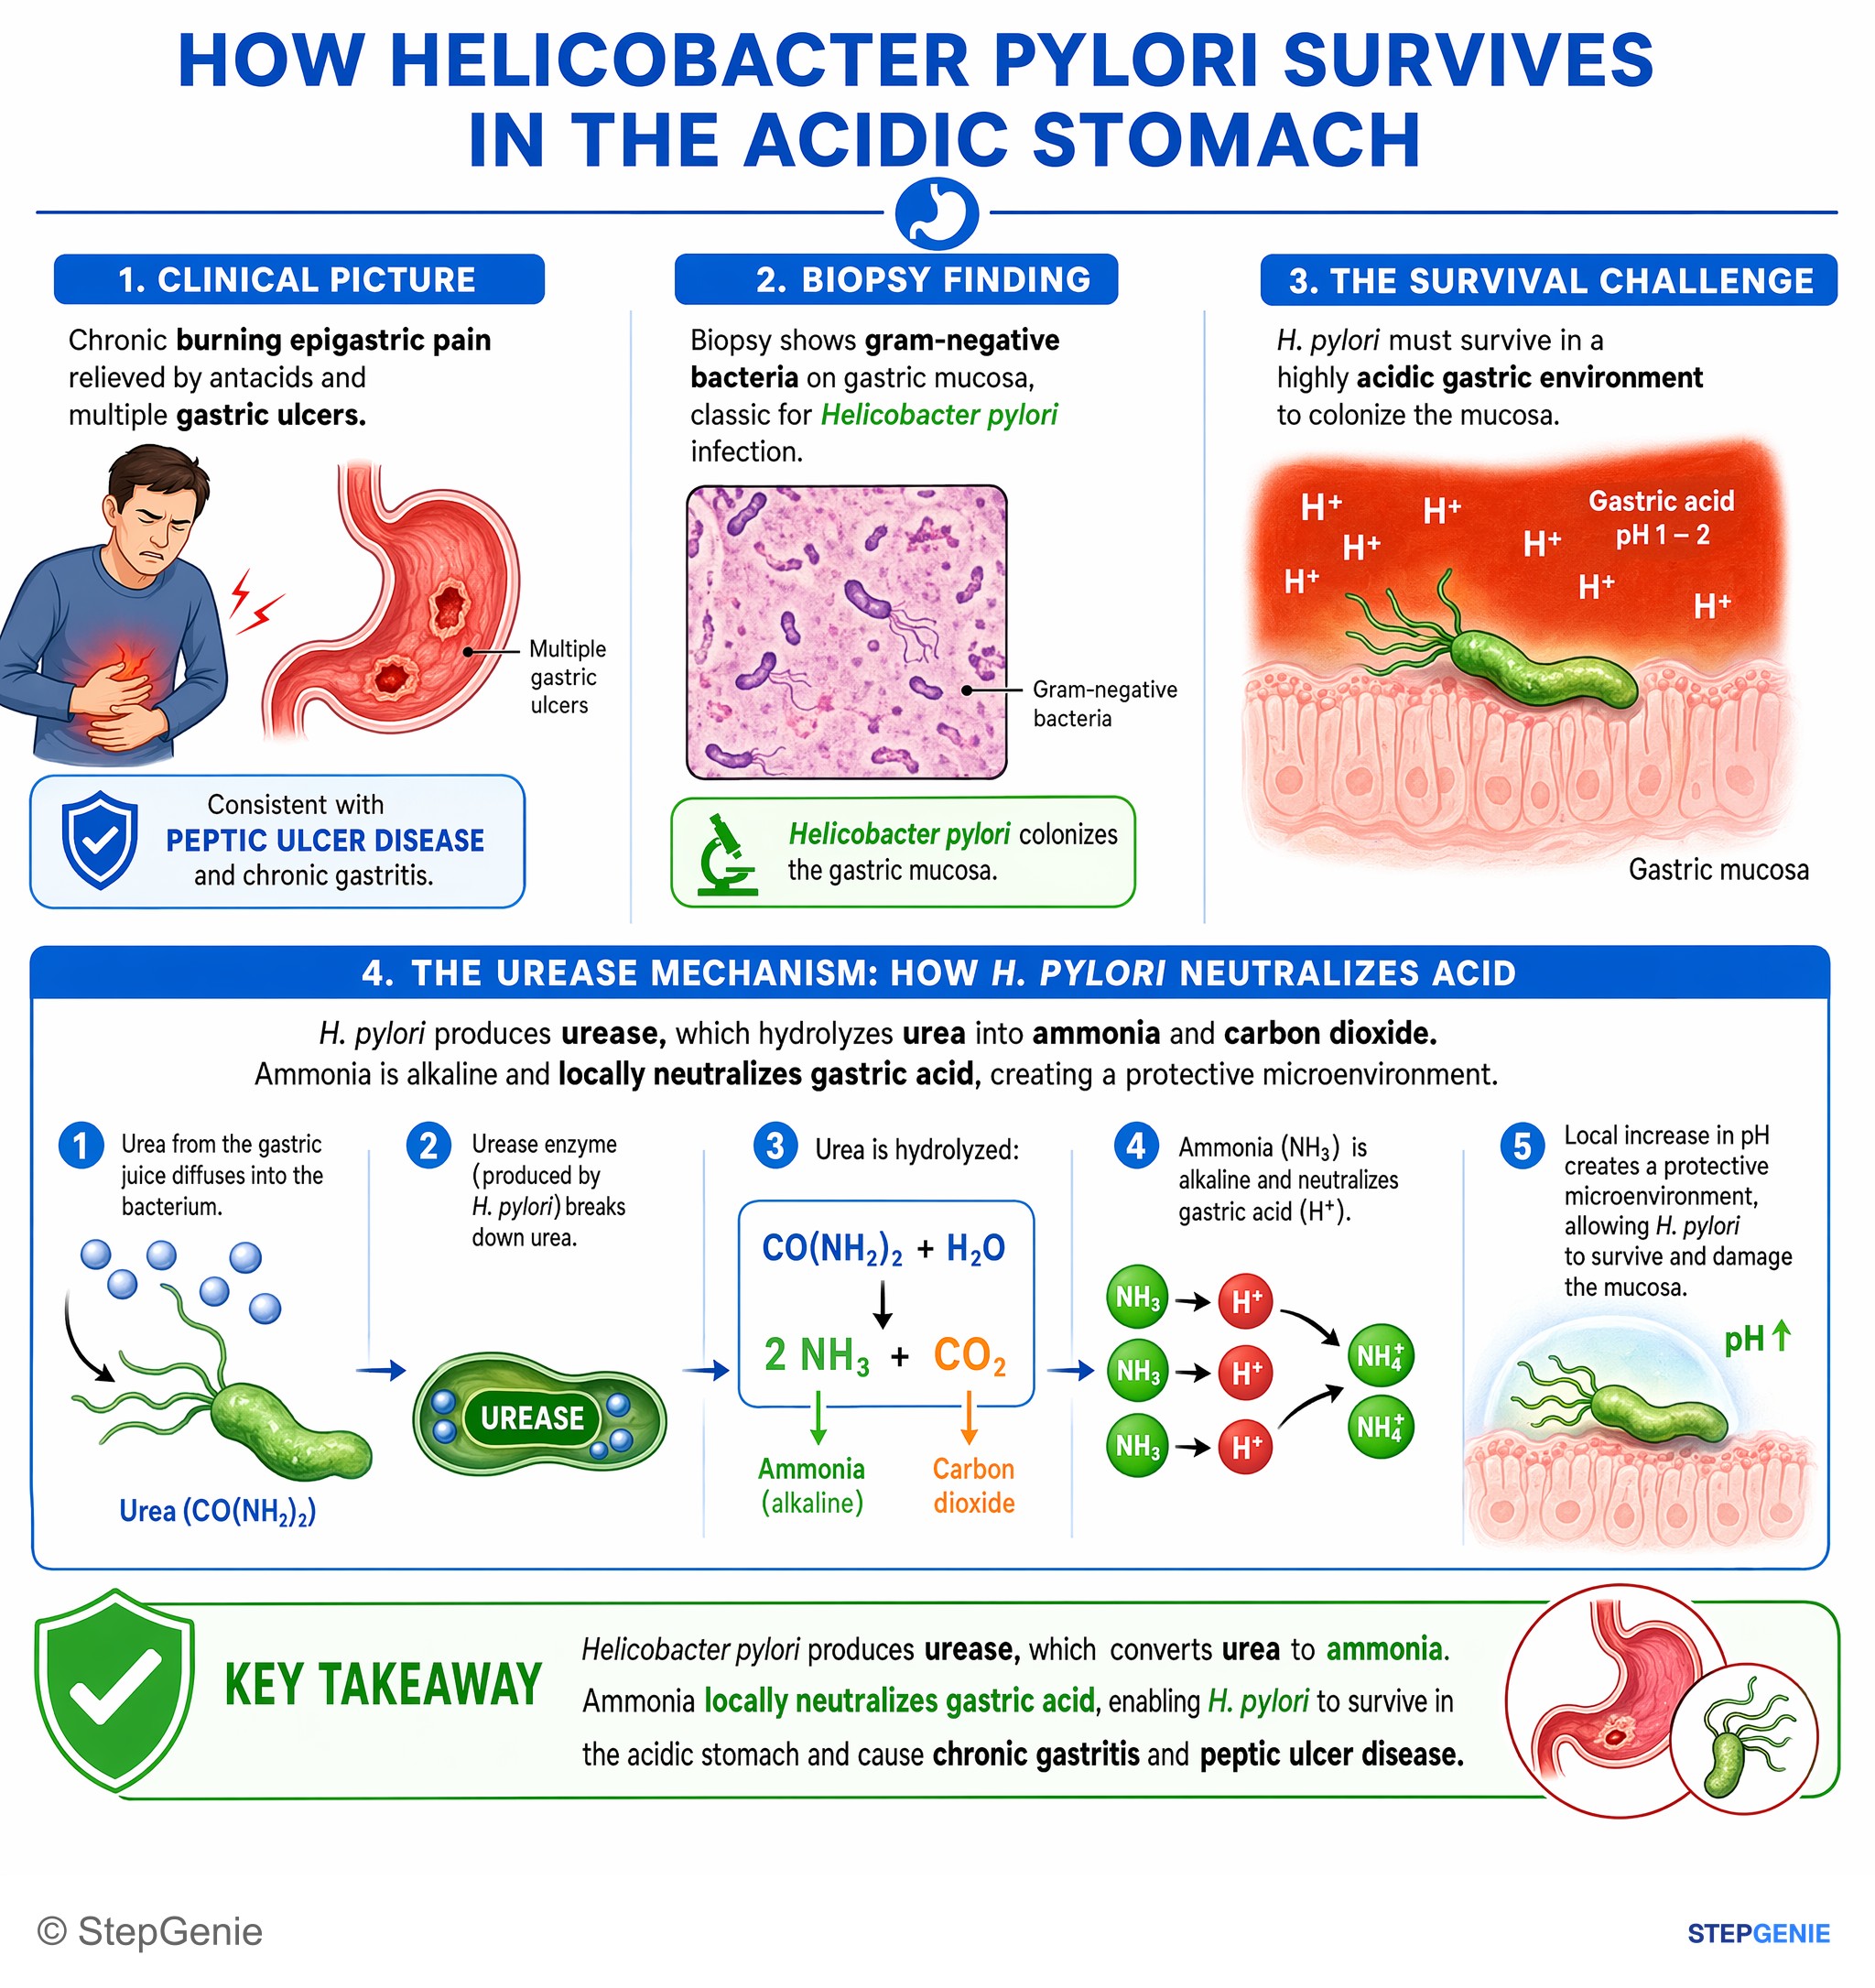
Helicobacter pylori produces urease, which converts urea to ammonia, locally neutralizing gastric acid and enabling survival in the acidic…
USMLE Step 1Frequently Asked Questions
How does Helicobacter pylori survive in the acidic stomach?
Helicobacter pylori survives stomach acid by producing urease. Urease converts urea into ammonia and carbon dioxide, and the ammonia buffers gastric acid to create a more favorable local environment. This urease-based acid shield is also why the urea breath test works, because urease activity leads to detectable labeled carbon dioxide in the patient’s breath.
Why does Helicobacter pylori commonly cause duodenal ulcers?
Helicobacter pylori commonly causes duodenal ulcers because antral infection increases acid production. Antral-predominant infection decreases somatostatin from D cells, which raises gastrin levels and stimulates parietal cells to secrete more acid. That increased acid load reaches the duodenum and promotes duodenal ulceration, making this a classic exam mechanism to know.
How do you tell a duodenal ulcer from a gastric ulcer in an H. pylori vignette?
A duodenal ulcer classically improves with meals and may cause nighttime pain, whereas a gastric ulcer may worsen with meals and is more often associated with weight loss from food avoidance. Both can be linked to Helicobacter pylori, but duodenal ulcers are the classic association. Melena can appear if bleeding occurs, which can help signal ulcer complications in a vignette.
What tests are best for diagnosing Helicobacter pylori and confirming eradication?
The best noninvasive tests are the urea breath test and stool antigen test, and both can also be used to confirm eradication. Serology is less favored because IgG can stay positive after treatment and cannot reliably distinguish active infection from past exposure. For test of cure, use a urea breath test or stool antigen after treatment rather than serology.
What is the first-line treatment for Helicobacter pylori?
Helicobacter pylori is treated with combination therapy rather than a single drug. Classic triple therapy is a proton pump inhibitor plus clarithromycin plus amoxicillin, with metronidazole substituted for penicillin allergy. Bismuth quadruple therapy includes a proton pump inhibitor, bismuth, tetracycline, and metronidazole, and is often favored when clarithromycin resistance is common.