Campylobacter jejuni is a curved ("gull-wing"), motile, oxidase-positive, microaerophilic gram-negative rod that grows best at 42°C; CDC estimates Campylobacter causes 1.87 million US illnesses and 13,000 hospitalizations a year. Infection usually follows raw or undercooked poultry and brings fever, cramping abdominal pain and often bloody diarrhea after a 2-5 day incubation, and most people recover within a week with fluids alone. It is the most common infection preceding Guillain-Barré syndrome, and when antibiotics are needed, azithromycin is the usual choice because fluoroquinolone resistance is common.
Lab ID card
| Feature | C. jejuni | Why it matters |
|---|---|---|
| Gram stain and shape | Gram-negative comma, S-shaped or gull-wing rod | One of the classic curved gram-negative rods |
| Motility | Single polar flagellum at one or both ends; darting motility in fresh stool | Flagella are needed for chemotaxis and adherence |
| Oxygen | Microaerophilic (needs reduced oxygen, about 5-10%) | Cultures need a low-oxygen atmosphere |
| Temperature | Grows best at 42°C (thermophilic; CDC gives 37-42°C) | CDC: seems well adapted to birds, which fits the poultry link |
| Oxidase | Positive | Part of the classic lab description in stems |
| Environment | Fragile outside the host; cannot tolerate drying | Spread is mainly through food (especially poultry), raw milk and water |
| Species | C. jejuni causes almost 90% of human Campylobacter illness | Others: C. coli, C. upsaliensis, C. fetus, C. lari |
The curved gram-negative rods
| Campylobacter jejuni | Vibrio cholerae | Helicobacter pylori | |
|---|---|---|---|
| Where | Jejunum, ileum and colon (invasive) | Small bowel (toxin) | Gastric mucosa |
| Lab clue | 42°C, microaerophilic | Curved, motile; selective stool media | Urease (urea breath test, stool antigen) |
| Disease | Inflammatory, often bloody diarrhea | Painless, profuse rice-water diarrhea | Gastritis, peptic ulcer, gastric adenocarcinoma, MALT lymphoma |
| Source | Poultry, raw milk, water, pets | Contaminated water, shellfish | Probably oral-oral or fecal-oral |
For the cholera side of the table, see Vibrio cholerae.
Reservoirs and transmission
- Poultry first: most infections follow eating raw or undercooked poultry, or food cross-contaminated by it; poultry accounts for 50-70% of human infections.
- Other sources: unpasteurized milk, untreated water, seafood, produce, and contact with dog or cat feces (including pet-store puppies).
- Low infectious dose: as few as about 800 organisms can cause illness.
- Person-to-person spread is uncommon, unlike Shigella.
- Who: all ages, with peak incidence at ages 1-5. People at risk of severe disease: adults 65 and older, pregnant women and the immunocompromised.
How it causes disease, and how patients look
C. jejuni uses its flagella to reach the mucosa, then invades and destroys epithelial cells of the jejunum, ileum and colon. The result is a diffuse, bloody, edematous, exudative enteritis with an infiltrate of neutrophils, eosinophils and mononuclear cells: an inflammatory diarrhea, so stool smears show white cells.
- Incubation: typically 2-5 days.
- Prodrome: 1-3 days of high fever, rigors, dizziness and body aches, often before the diarrhea starts.
- Diarrhea: often bloody, sometimes more than 10 stools a day, with nausea and sometimes vomiting.
- Pain: cramping, and it can mimic acute appendicitis (pseudoappendicitis) or ulcerative colitis; pain can last days to weeks after the diarrhea settles.
- Course: most patients recover completely within 1 week.
- C. fetus is different: it causes bacteremia and systemic infection in older, immunocompromised and pregnant patients (fetal loss up to 70%), and is the species more often behind Campylobacter endocarditis.
Complications
| Complication | How often and when | Key point |
|---|---|---|
| Guillain-Barré syndrome | 0.2-1.7 per 1,000 illnesses (CDC), usually 1-3 weeks later; Campylobacter is behind 5-41% of all GBS | Lipooligosaccharide mimics gangliosides → anti-GM1 antibodies → classically the axonal AMAN variant. Full details in Guillain-Barré syndrome |
| Reactive arthritis | About 1-5%, within about 4 weeks | Usually knees and ankles. The classic exam link is HLA-B27 (Merck), though StatPearls notes no population-level HLA-B27 association after Campylobacter; see reactive arthritis |
| Irritable bowel syndrome | After recovery | A recognized long-term consequence (CDC) |
| Bacteremia | Under 1% | More often with C. fetus and in immunocompromised hosts |
| Rare | — | Myocarditis or pericarditis, toxic megacolon, HUS, immunoproliferative small intestinal disease |
Exam timing trap: the weakness of GBS usually starts after the diarrhea has resolved, so the stem may mention "an episode of diarrhea 2 weeks ago" almost in passing. Preceding C. jejuni diarrhea also predicts a worse GBS outcome.
Diagnosis
- Stool culture on selective media at 42°C under microaerophilic conditions, or a culture-independent test (PCR panel or antigen test).
- CDC asks labs to culture CIDT-positive specimens, because only an isolate allows susceptibility testing and outbreak subtyping.
- Stool shows white cells and often blood (inflammatory diarrhea); blood cultures if systemic infection is suspected.
- The 2017 IDSA infectious diarrhea guideline advises that people with fever or bloody diarrhea be tested for pathogens that antibiotics can help, including Salmonella, Shigella and Campylobacter.
Treatment and resistance
- Fluids first. Most infections are self-limited; patients should drink extra fluids while diarrhea lasts (oral rehydration, IV if severe).
- Who gets antibiotics: CDC says people with, or at risk of, severe illness: adults 65 and older, pregnant women and immunocompromised patients. StatPearls adds patients with fever, bloody stools or severe pain.
- Which drug: CDC lists azithromycin and fluoroquinolones (e.g., ciprofloxacin) as commonly used, but fluoroquinolone resistance is common in the US, so susceptibility results should guide treatment. StatPearls calls macrolides the best choice when antibiotics are indicated, and Merck advises ciprofloxacin only when susceptibility is established, as resistance can emerge during therapy.
- Resistance numbers: CDC's 2019 threat report (2015-2017 data) found decreased susceptibility to ciprofloxacin in 28% of US Campylobacter infections versus 4% for azithromycin (29% to either drug), and decreased ciprofloxacin susceptibility had almost doubled in 20 years; it is more common in low- and middle-income countries, so returning travelers are at greater risk. StatPearls (2024) puts US macrolide resistance at about 1-3%.
- Empiric antibiotics: IDSA (2017) does not recommend them for bloody diarrhea in most immunocompetent people while tests are pending; when they are used, it advises a fluoroquinolone or azithromycin depending on local susceptibility patterns.
- Avoid antimotility drugs such as loperamide in inflammatory, bloody diarrhea; IDSA says they should not be given to children under 18 with acute diarrhea, or at any age when toxic megacolon could result. See the loperamide question.
- Prevention: cook poultry thoroughly, use separate cutting boards for raw meat, avoid raw milk and untreated water, and wash hands.
Bloody diarrhea look-alikes
| Organism | Exposure | Fever | Clincher |
|---|---|---|---|
| Campylobacter jejuni | Undercooked poultry, raw milk, puppies | Yes | Curved rod, 42°C, microaerophilic; GBS and reactive arthritis |
| Shigella | Person to person (crowding, sexual contact between men) | Yes | Only 10-100 organisms needed; tenesmus; S. dysenteriae type 1 Shiga toxin can cause HUS. See Shigella |
| Nontyphoidal Salmonella | Poultry, eggs, raw milk, pet turtles and reptiles | Yes | Blood or mucus in stool is rare; antibiotics are unwarranted in uncomplicated cases and may prolong excretion; bacteremia and osteomyelitis risk in sickle cell disease |
| EHEC (O157:H7) | Undercooked ground beef | Low-grade or none | HUS in 2-7%; not treated with antibiotics. Compare the E. coli types |
| Yersinia enterocolitica | Raw or undercooked pork, chitterlings; milk | Yes | Right-sided pain mimicking appendicitis (mesenteric adenitis); cold enrichment or CIN agar; iron overload predisposes |
How USMLE tests it: "cookout with undercooked chicken" plus fever and bloody diarrhea; a lab that names 42°C or microaerophilic growth; weakness 1-3 weeks later (GBS); knee or ankle arthritis within weeks (reactive arthritis); and the treatment question, where the right answer is fluids for most and azithromycin for severe or high-risk disease, never loperamide.
Practice question
A 22-year-old college student has 2 days of fever, crampy abdominal pain and diarrhea that has become bloody. Symptoms began 3 days after a weekend cookout where he ate undercooked chicken. Temperature is 38.6°C (101.5°F), and the abdomen is diffusely tender. Stool contains many leukocytes. Culture on selective agar incubated at 42°C in a microaerophilic atmosphere grows curved, motile, oxidase-positive gram-negative rods. Which organism is most likely?
A. Campylobacter jejuni B. Vibrio cholerae C. Shigella dysenteriae D. Enterotoxigenic E. coli (ETEC) E. Salmonella Enteritidis F. Yersinia enterocolitica
Answer: A. Undercooked poultry, a 3-day incubation, fever, bloody inflammatory diarrhea and curved oxidase-positive rods growing at 42°C under reduced oxygen are C. jejuni. Most patients need only fluids; watch for Guillain-Barré syndrome over the next few weeks.
- B: V. cholerae is curved too, but its toxin causes painless, profuse rice-water diarrhea without blood, usually from contaminated water or shellfish.
- C: Shigella also causes fever and bloody diarrhea with tenesmus, but it spreads person to person with a tiny inoculum and is not a curved, microaerophilic 42°C organism.
- D: ETEC causes watery traveler's diarrhea (and diarrhea in infants) through toxins; it is noninvasive, so stools lack blood and white cells.
- E: Salmonella also comes from poultry and eggs and causes fever, but blood or mucus in stool is rare, and the culture profile here does not fit.
- F: Yersinia is linked to pork and chitterlings, causes right-sided pain that mimics appendicitis, and is isolated with cold enrichment or CIN agar.
Key takeaways
- C. jejuni = curved (gull-wing), motile, oxidase-positive, microaerophilic gram-negative rod that grows at 42°C.
- Undercooked poultry is the main source; also raw milk, untreated water and contact with dog or cat feces; person-to-person spread is uncommon.
- Inflammatory diarrhea: 2-5 day incubation, fever, cramps that can mimic appendicitis, often bloody stools with white cells; most recover within a week.
- Complications: Guillain-Barré syndrome (1-3 weeks later; anti-GM1, AMAN), reactive arthritis (classically HLA-B27), IBS; bacteremia is rare (more often C. fetus).
- Treatment: fluids for most; azithromycin for severe or high-risk disease; fluoroquinolone resistance is common, so test susceptibility; avoid loperamide.
Sources
- Clinical Overview of Campylobacter — CDC (2026)
- Campylobacter Infections — Merck Manual Professional Edition (2026)
- Campylobacter Infection — StatPearls, NCBI Bookshelf (2024)
- Drug-Resistant Campylobacter (Antibiotic Resistance Threats Report fact sheet) — CDC (2019)
- 2017 Clinical Practice Guidelines for the Diagnosis and Management of Infectious Diarrhea — IDSA (2017)
- Campylobacter and Helicobacter — Medical Microbiology, 4th ed., NCBI Bookshelf (1996)
- Shigellosis — Merck Manual Professional Edition (2026)
- Nontyphoidal Salmonella Infections — Merck Manual Professional Edition (2024)
- Escherichia coli Infections — Merck Manual Professional Edition (2026)
- Clinical Overview of Yersiniosis — CDC (2026)
- About Yersinia Infection — CDC (2024)
- Cholera — Merck Manual Professional Edition (2024)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
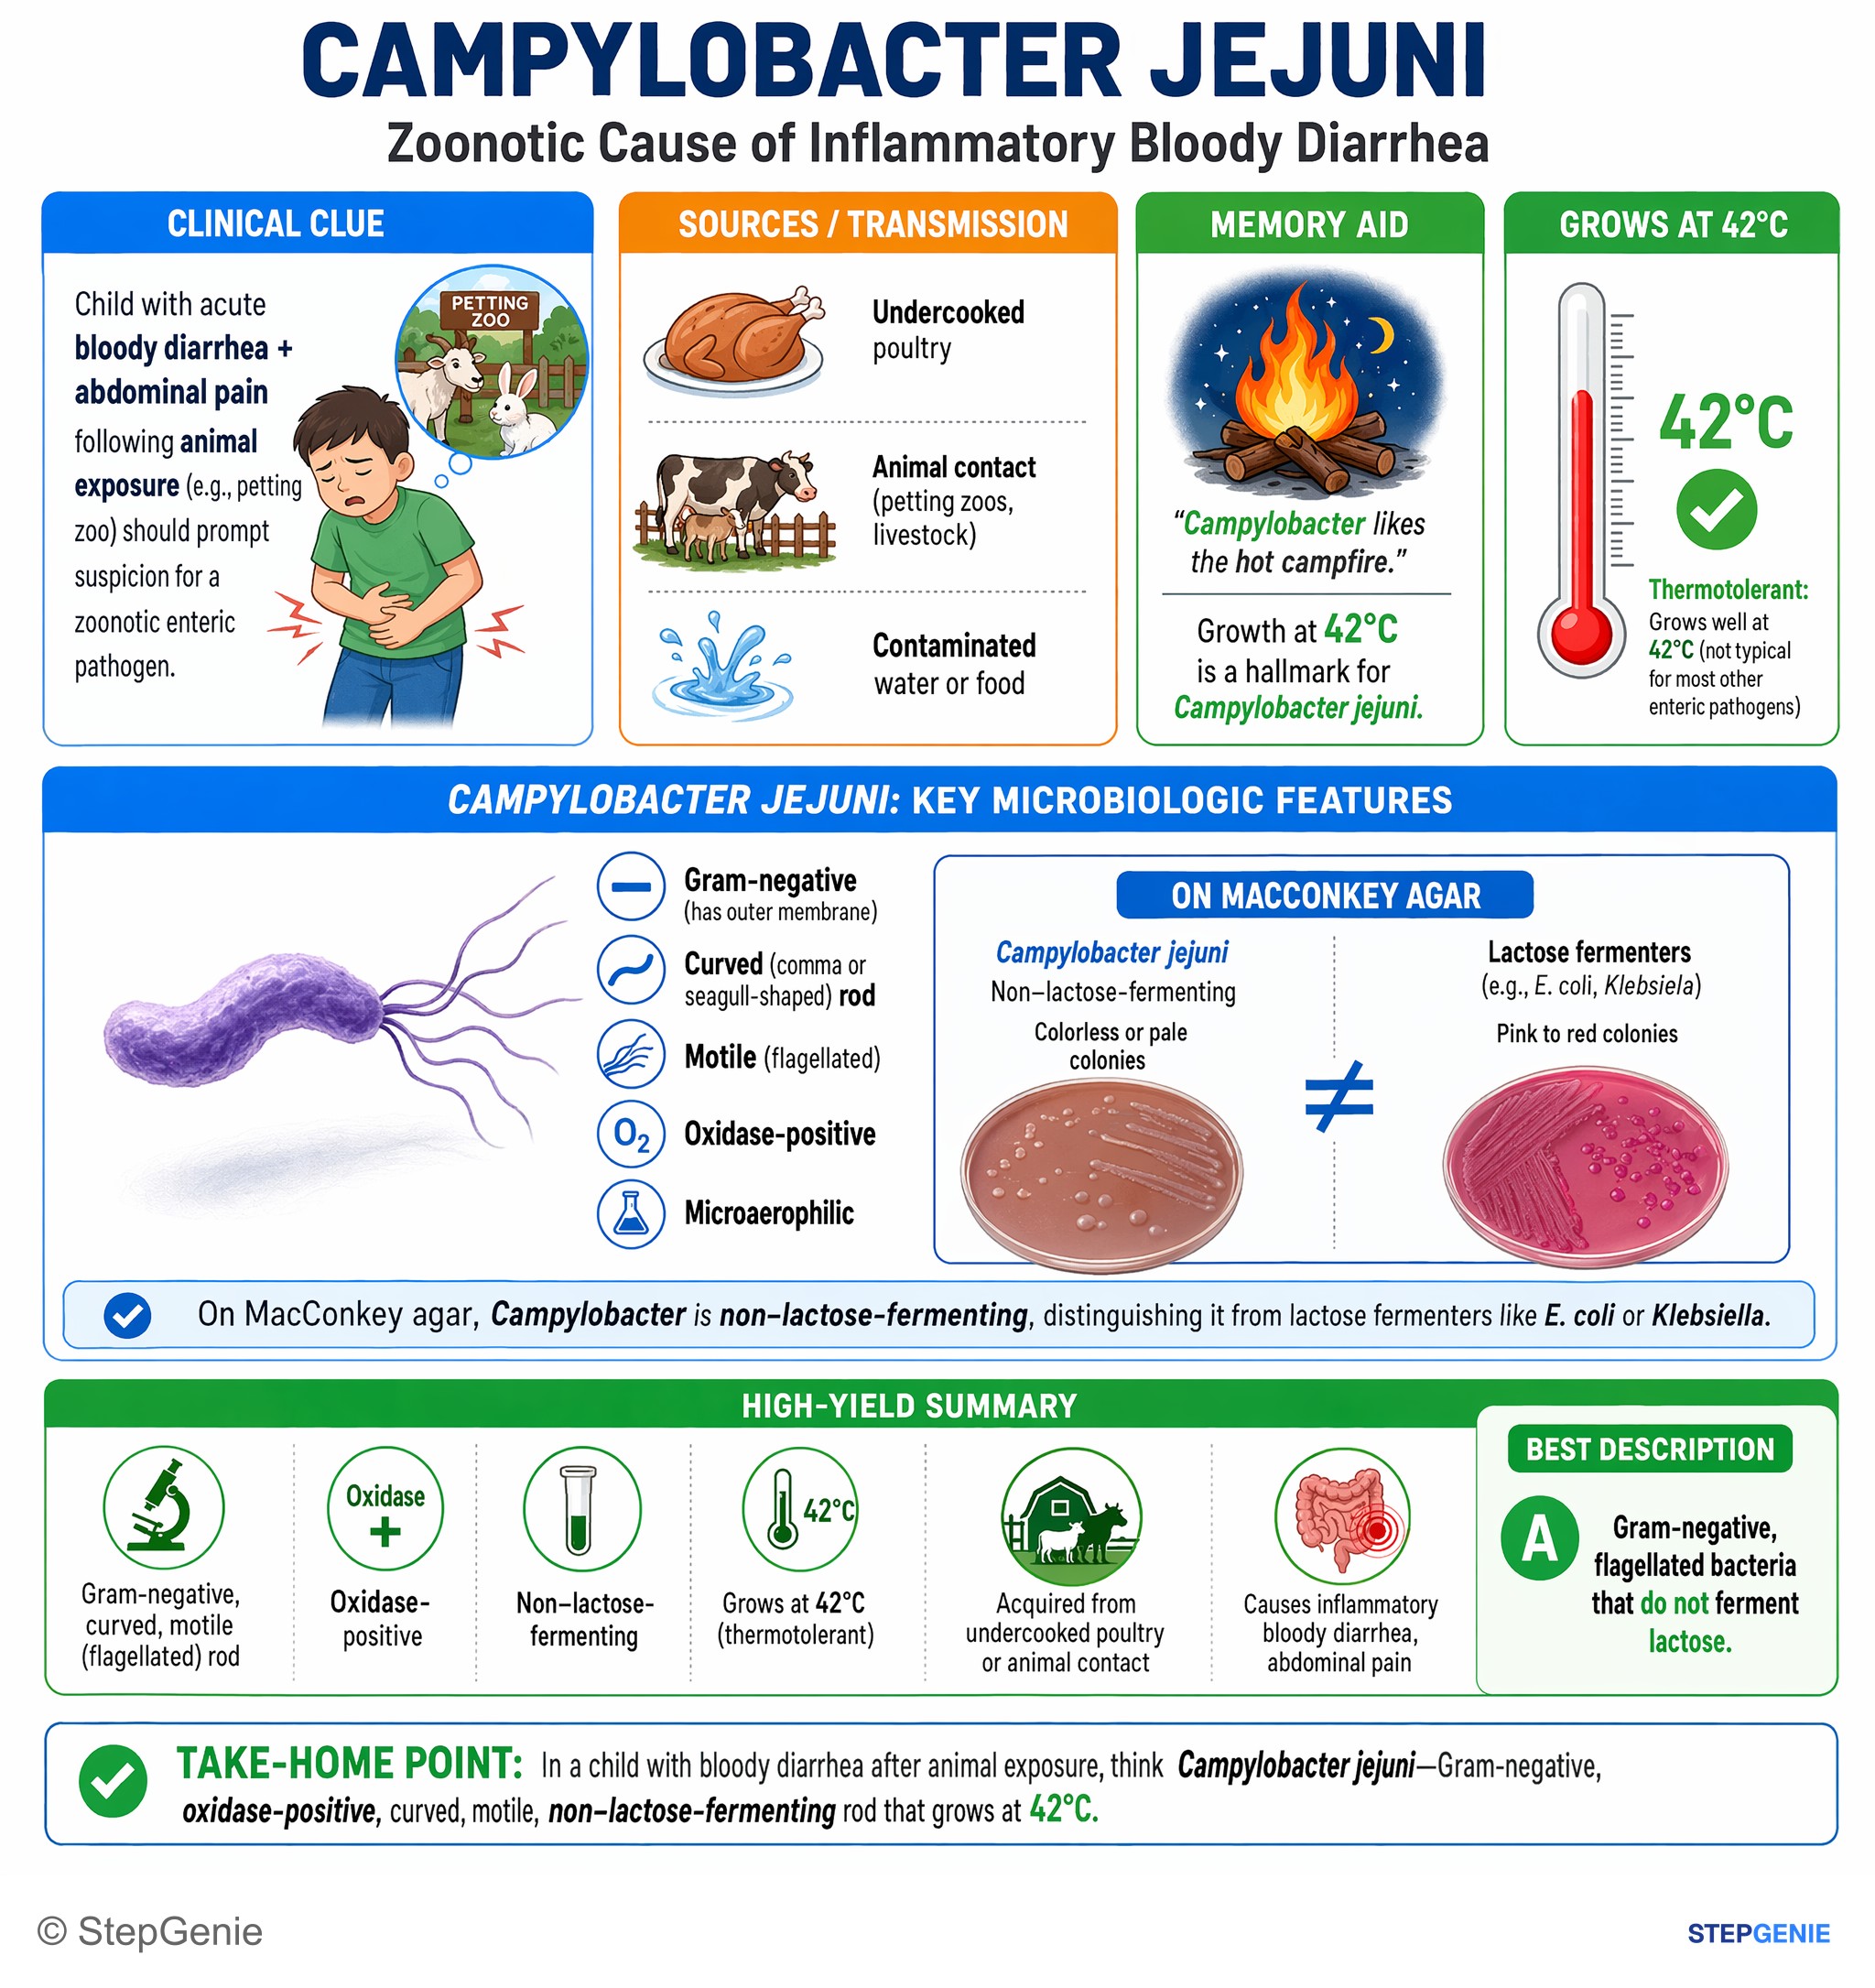
Campylobacter jejuni: Gram-negative, oxidase-positive, curved, motile, non–lactose-fermenting rod; grows at 42°C; causes inflammatory…
USMLE Step 1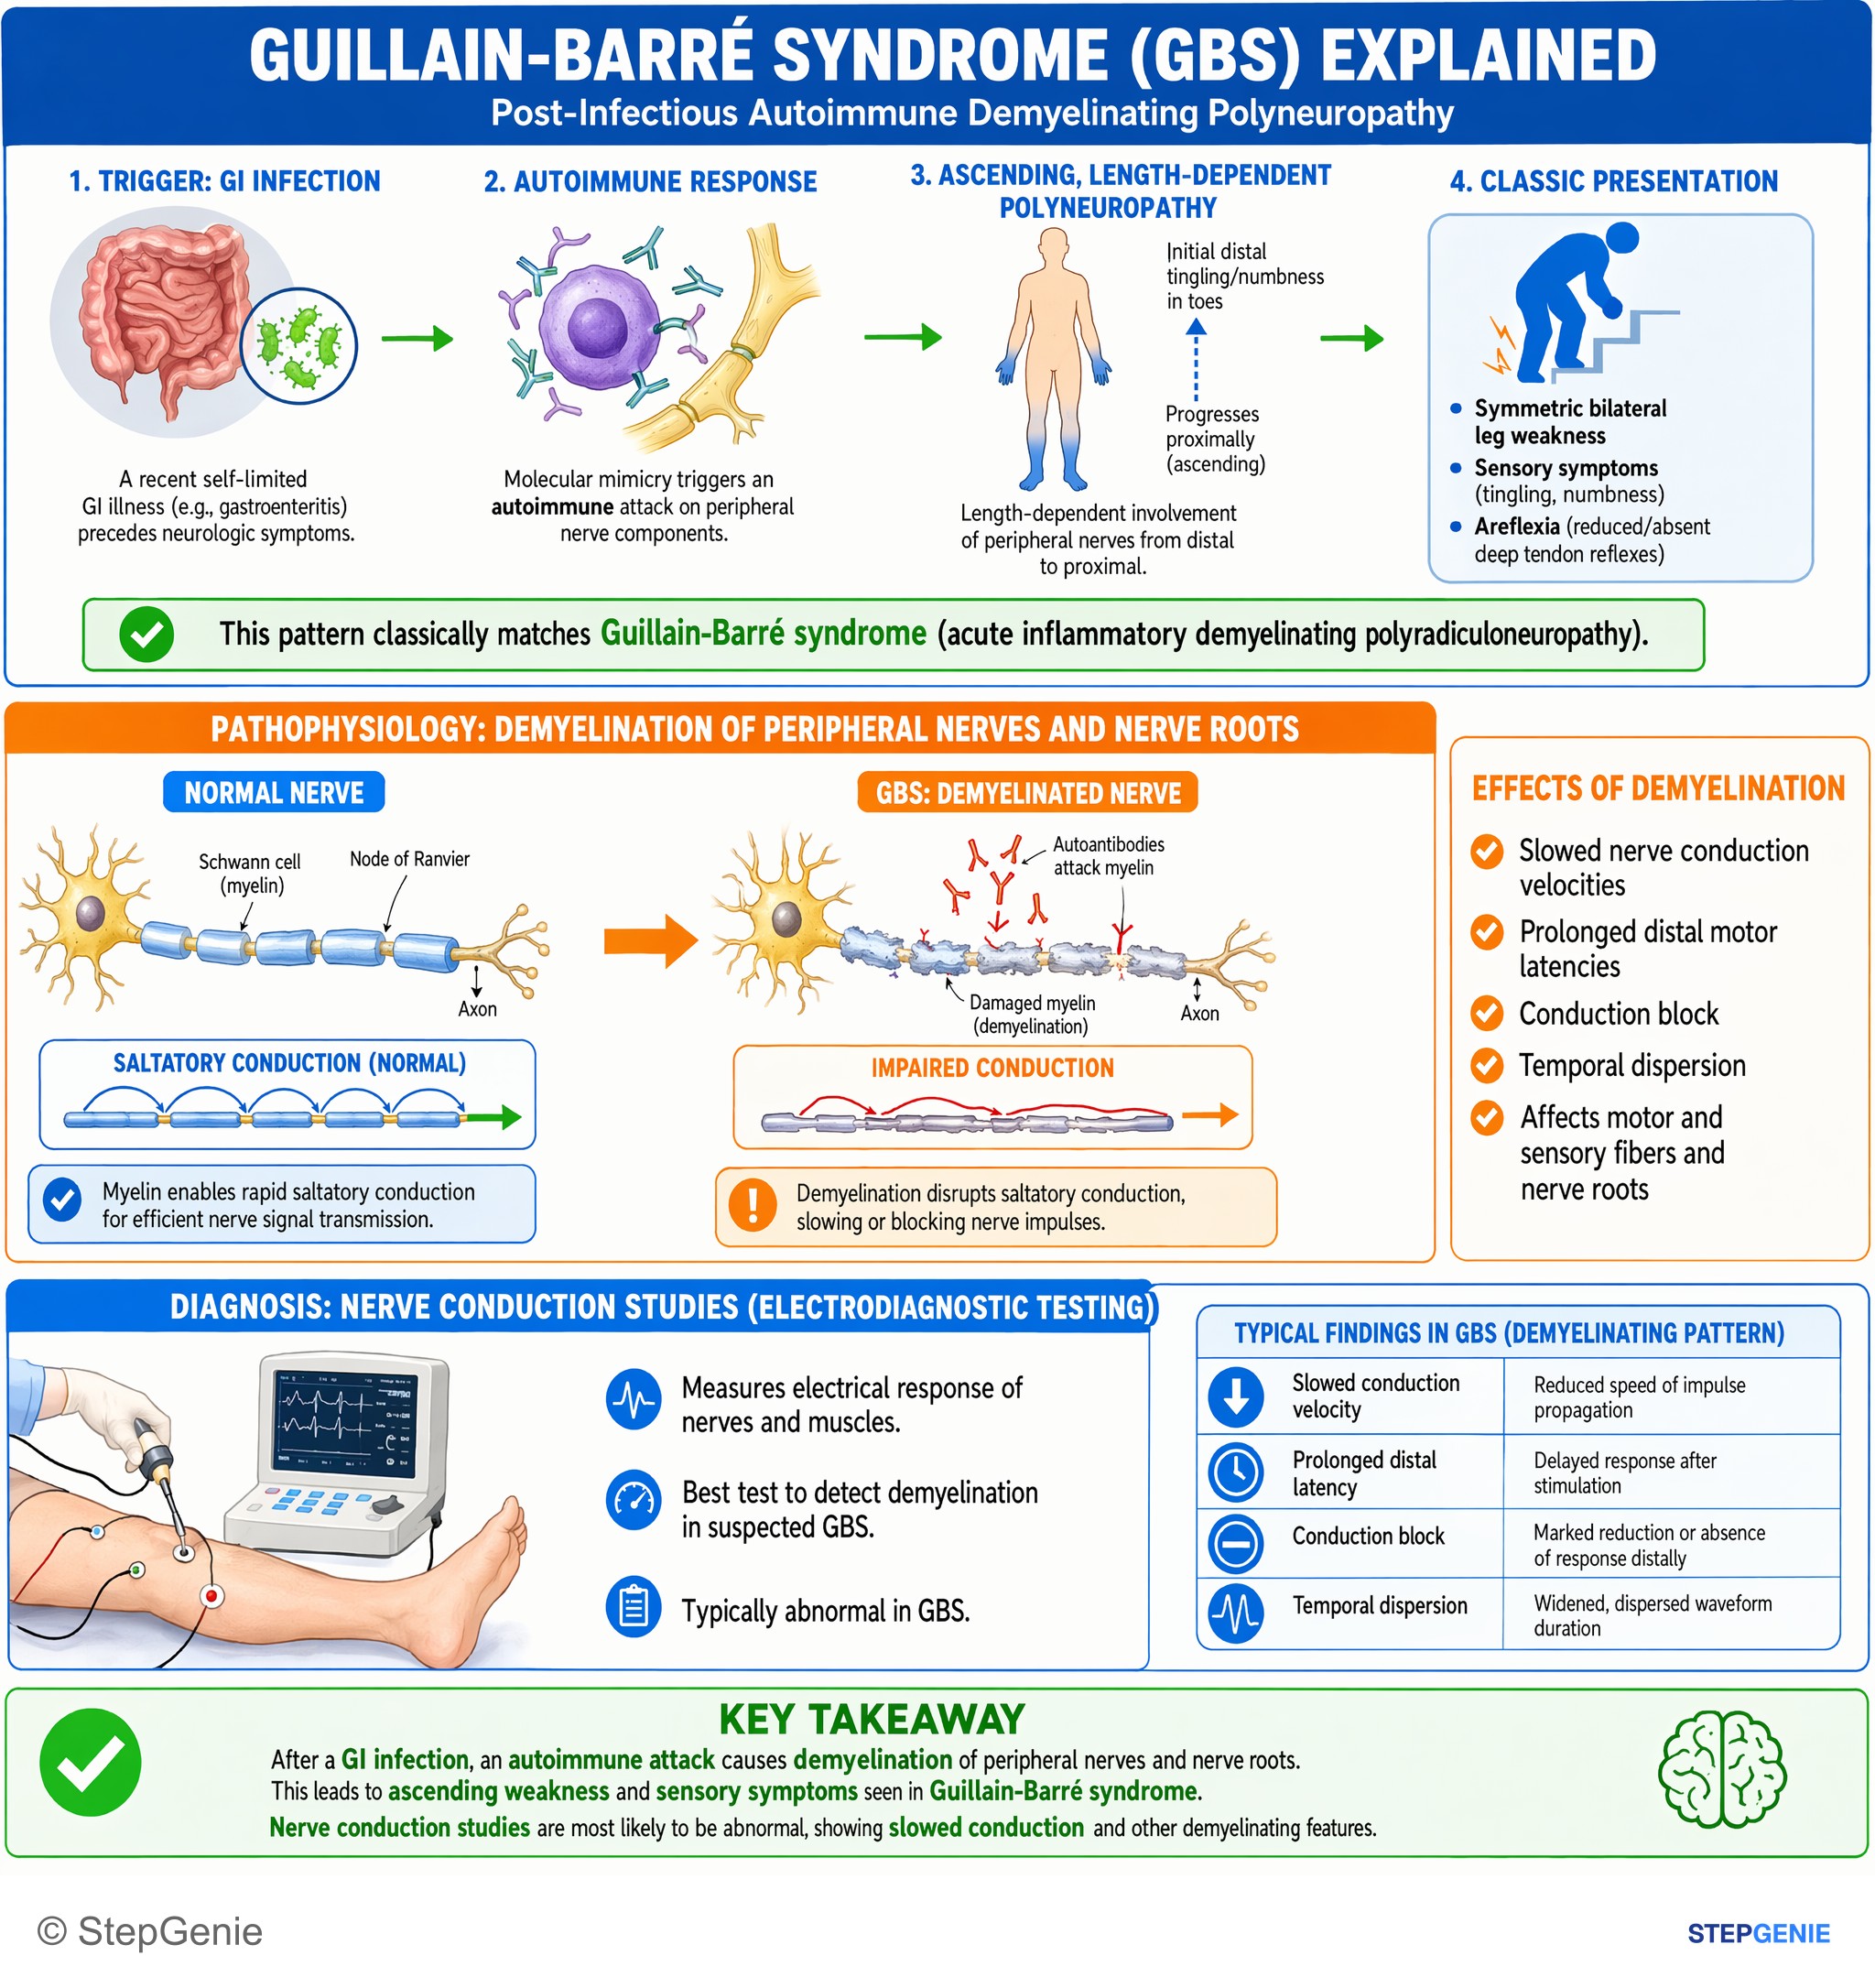
Guillain-Barré syndrome after GI infection causes demyelinating peripheral neuropathy with ascending weakness; nerve conduction studies…
USMLE Step 2Frequently Asked Questions
What lab findings identify Campylobacter jejuni?
Campylobacter jejuni is a curved, comma- or gull-wing-shaped gram-negative rod with a polar flagellum that gives darting motility. It is oxidase-positive and microaerophilic, needing about 5-10% oxygen, and grows best at 42°C, so stool is cultured on selective media at 42°C in a low-oxygen atmosphere. Many labs now use PCR or antigen tests first, and CDC asks labs to culture positive specimens so that susceptibility can be tested.
Why does Campylobacter cause bloody diarrhea?
Campylobacter jejuni invades and destroys the epithelial cells of the jejunum, ileum and colon, producing a diffuse, bloody, edematous enteritis with a neutrophil-rich inflammatory infiltrate. That makes it an inflammatory diarrhea: fever, cramping pain, white cells in the stool and often visible blood. After a 2-5 day incubation the illness usually lasts about a week, and the abdominal pain can mimic appendicitis or ulcerative colitis.
How does Campylobacter jejuni cause Guillain-Barré syndrome?
Through molecular mimicry. The lipooligosaccharide of Campylobacter jejuni contains ganglioside-like structures, so antibodies made against the bacterium cross-react with gangliosides such as GM1 on peripheral nerve axons, classically causing the acute motor axonal neuropathy (AMAN) form of GBS. CDC estimates that only 0.2-1.7 of every 1,000 Campylobacter illnesses lead to GBS, yet Campylobacter accounts for 5-41% of GBS cases. Weakness usually begins 1-3 weeks after the diarrhea.
What is the treatment for Campylobacter jejuni infection?
Most infections resolve on their own within a week, so fluids and oral rehydration are the mainstay. CDC reserves antibiotics for people with, or at risk of, severe illness, such as adults 65 and older, pregnant women and immunocompromised patients. Azithromycin is the usual choice because fluoroquinolone resistance is common in the United States, and susceptibility testing should guide therapy. Antimotility drugs such as loperamide should be avoided in bloody, inflammatory diarrhea.
Is Campylobacter resistant to ciprofloxacin?
Often, yes. CDC says fluoroquinolone resistance is common in the United States. Its 2019 threat report (2015-2017 data) found decreased susceptibility to ciprofloxacin in 28% of US Campylobacter infections versus 4% for azithromycin, and decreased ciprofloxacin susceptibility had almost doubled in 20 years. Resistance is more common in low- and middle-income countries, which matters for returning travelers. Because macrolide resistance stays low, azithromycin is preferred when treatment is needed, ideally guided by susceptibility results.
How do you tell Campylobacter from Shigella, Salmonella and EHEC?
Campylobacter follows undercooked poultry, causes fever with bloody diarrhea and grows as a curved rod at 42°C in low oxygen. Shigella spreads person to person with as few as 10-100 organisms and causes tenesmus. Nontyphoidal Salmonella comes from poultry, eggs and reptiles, and visible blood in the stool is rare. EHEC O157:H7 follows undercooked ground beef, causes bloody diarrhea with little or no fever, leads to HUS in 2-7% of cases and is not treated with antibiotics.