Mycoplasma pneumoniae is the kind of Step question that looks like “just pneumonia,” but the test writers want you to recognize a very specific pattern: walking pneumonia + cold agglutinins + no cell wall. Here’s a quick, shareable acronym trick you can recall in seconds.
The Acronym Trick: MYCOPLASMA
Use MYCOPLASMA to hit the classic boards clues:
- M = Mild “walking” pneumonia (often outpatient)
- Y = Youth (classically kids/teens/young adults; outbreaks in schools/military)
- C = Cold agglutinins (IgM) → hemolytic anemia
- O = Outbreaks (close quarters)
- P = Pneumonia that’s patchy/interstitial
- L = Lacks a cell wall → beta-lactams don’t work
- A = Atypical = dry cough, low-grade fever, diffuse symptoms
- S = Serology/PCR (not seen on Gram stain)
- M = Macrolide (or doxycycline) treatment
- A = Atypical CXR: “worse than exam” (diffuse interstitial infiltrates)
One-liner: “MYCOPLASMA = Mild Youth outbreaks + Cold agglutinins; Lacks a cell wall → treat with Macrolide/Doxy.”
Visual Mnemonic (Picture It)
Imagine a college dorm in winter:
- A student is walking to class coughing (mild symptoms)
- Holding an ice pack labeled “IgM Cold Agglutinins”
- Wearing a shirt that says “NO WALL”
- A sign outside the dorm reads “BETA-LACTAMS NOT ALLOWED”
- The campus clinic hands out azithromycin
That single “scene” captures the organism’s biggest USMLE hooks.
High-Yield Facts You’re Expected to Know
What it is (and why it’s weird)
- No peptidoglycan cell wall → not visible on Gram stain, intrinsically resistant to:
- Penicillins/cephalosporins/carbapenems
- Vancomycin
- Has a sterol-containing cell membrane (think “flexible” membrane compensation)
Clinical pattern
- Atypical pneumonia: dry cough, low-grade fever, headache, malaise
- Often “walking pneumonia”: patient looks relatively okay
- CXR: classically diffuse, patchy interstitial infiltrates that can look more impressive than the physical exam
The Step buzzword: cold agglutinins
- IgM antibodies can bind RBCs at low temperatures → hemolysis
- Clues you may see:
- Hemolytic anemia symptoms
- Elevated indirect bilirubin/LDH, low haptoglobin (general hemolysis pattern)
- Agglutination findings in cold conditions
Diagnosis and Treatment (What they’ll test)
Diagnosis (common test-day framing)
- Not seen well on Gram stain; questions lean on clinical syndrome
- Confirmatory options:
- PCR
- Serology (context-dependent)
Treatment (boards answer choices)
| Scenario | Best coverage |
|---|---|
| Suspected Mycoplasma atypical pneumonia | Macrolide (e.g., azithromycin) or doxycycline |
| Need “atypical” coverage in CAP | Add macrolide/doxy (or use a respiratory fluoroquinolone when appropriate) |
Key move: If the stem screams atypical + no cell wall clues, don’t pick a beta-lactam.
Rapid-Fire USMLE Takeaways
- No cell wall → beta-lactam resistant
- Cold agglutinins (IgM) → hemolytic anemia association
- Young/close quarters outbreaks
- Dry cough + interstitial infiltrates
- Treat with macrolide or doxycycline
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
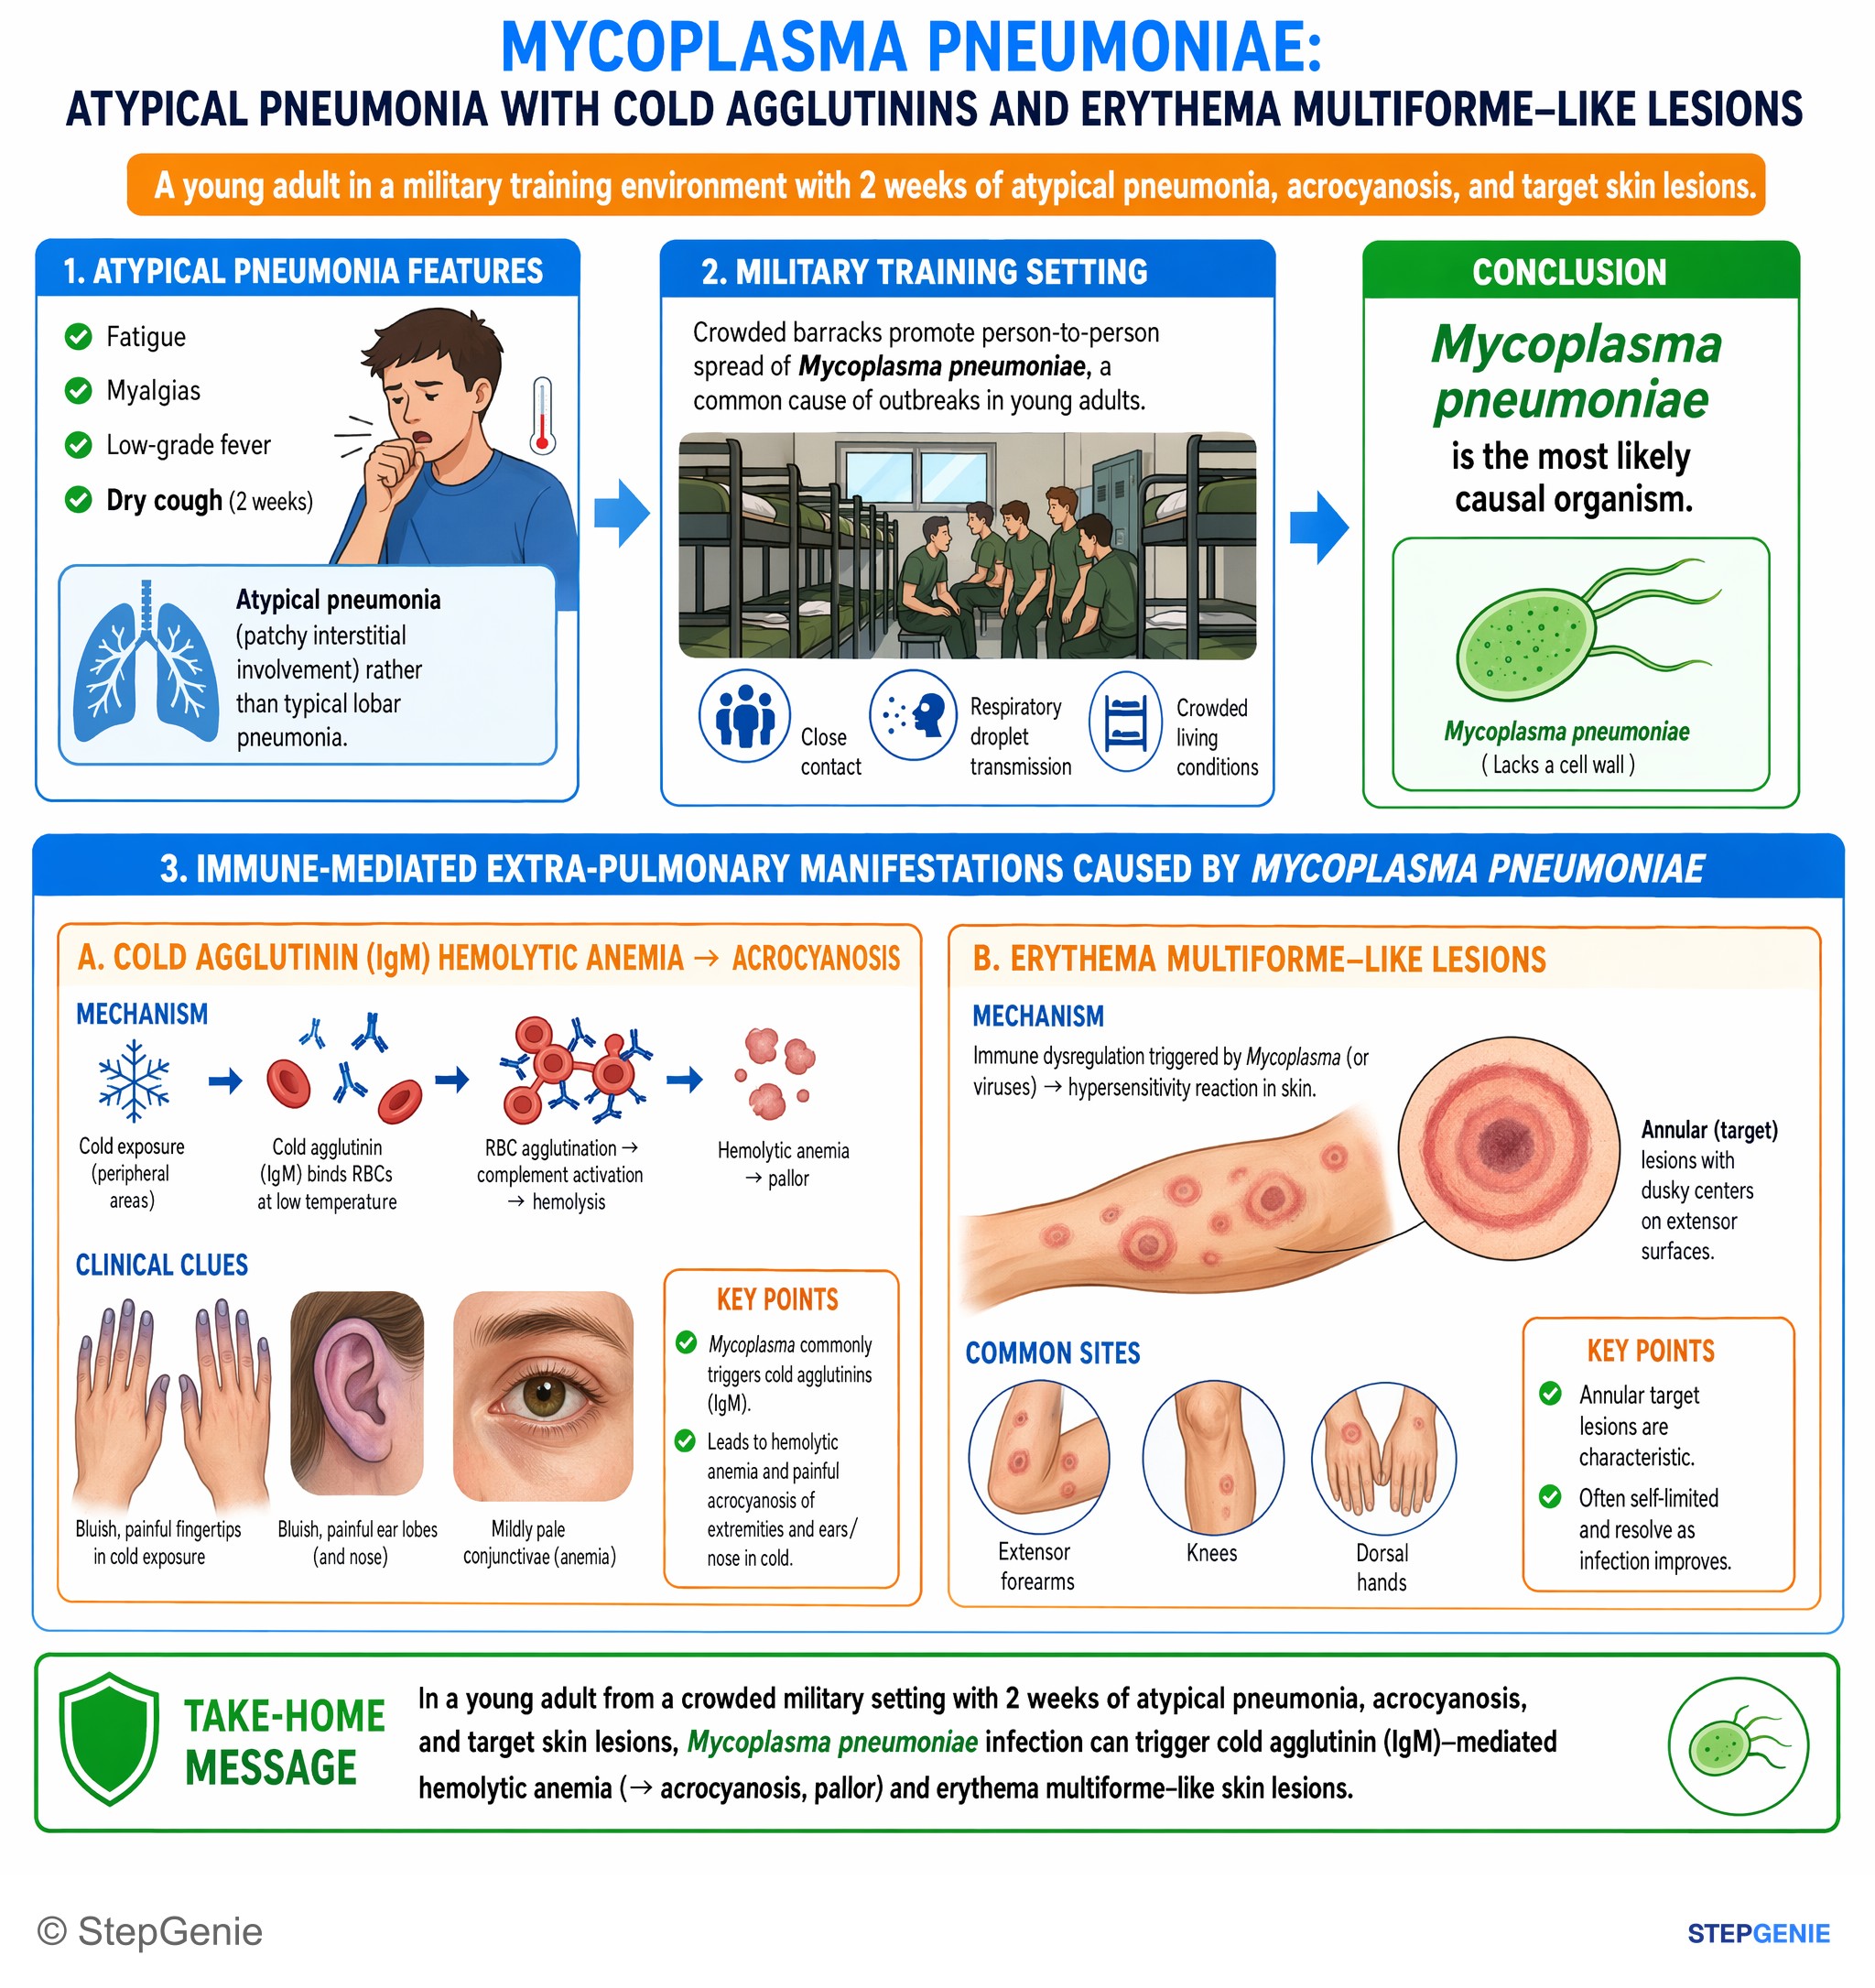
Mycoplasma pneumoniae atypical pneumonia can trigger cold agglutinins/cryoglobulins causing acrocyanosis and erythema multiforme–like…
USMLE Step 1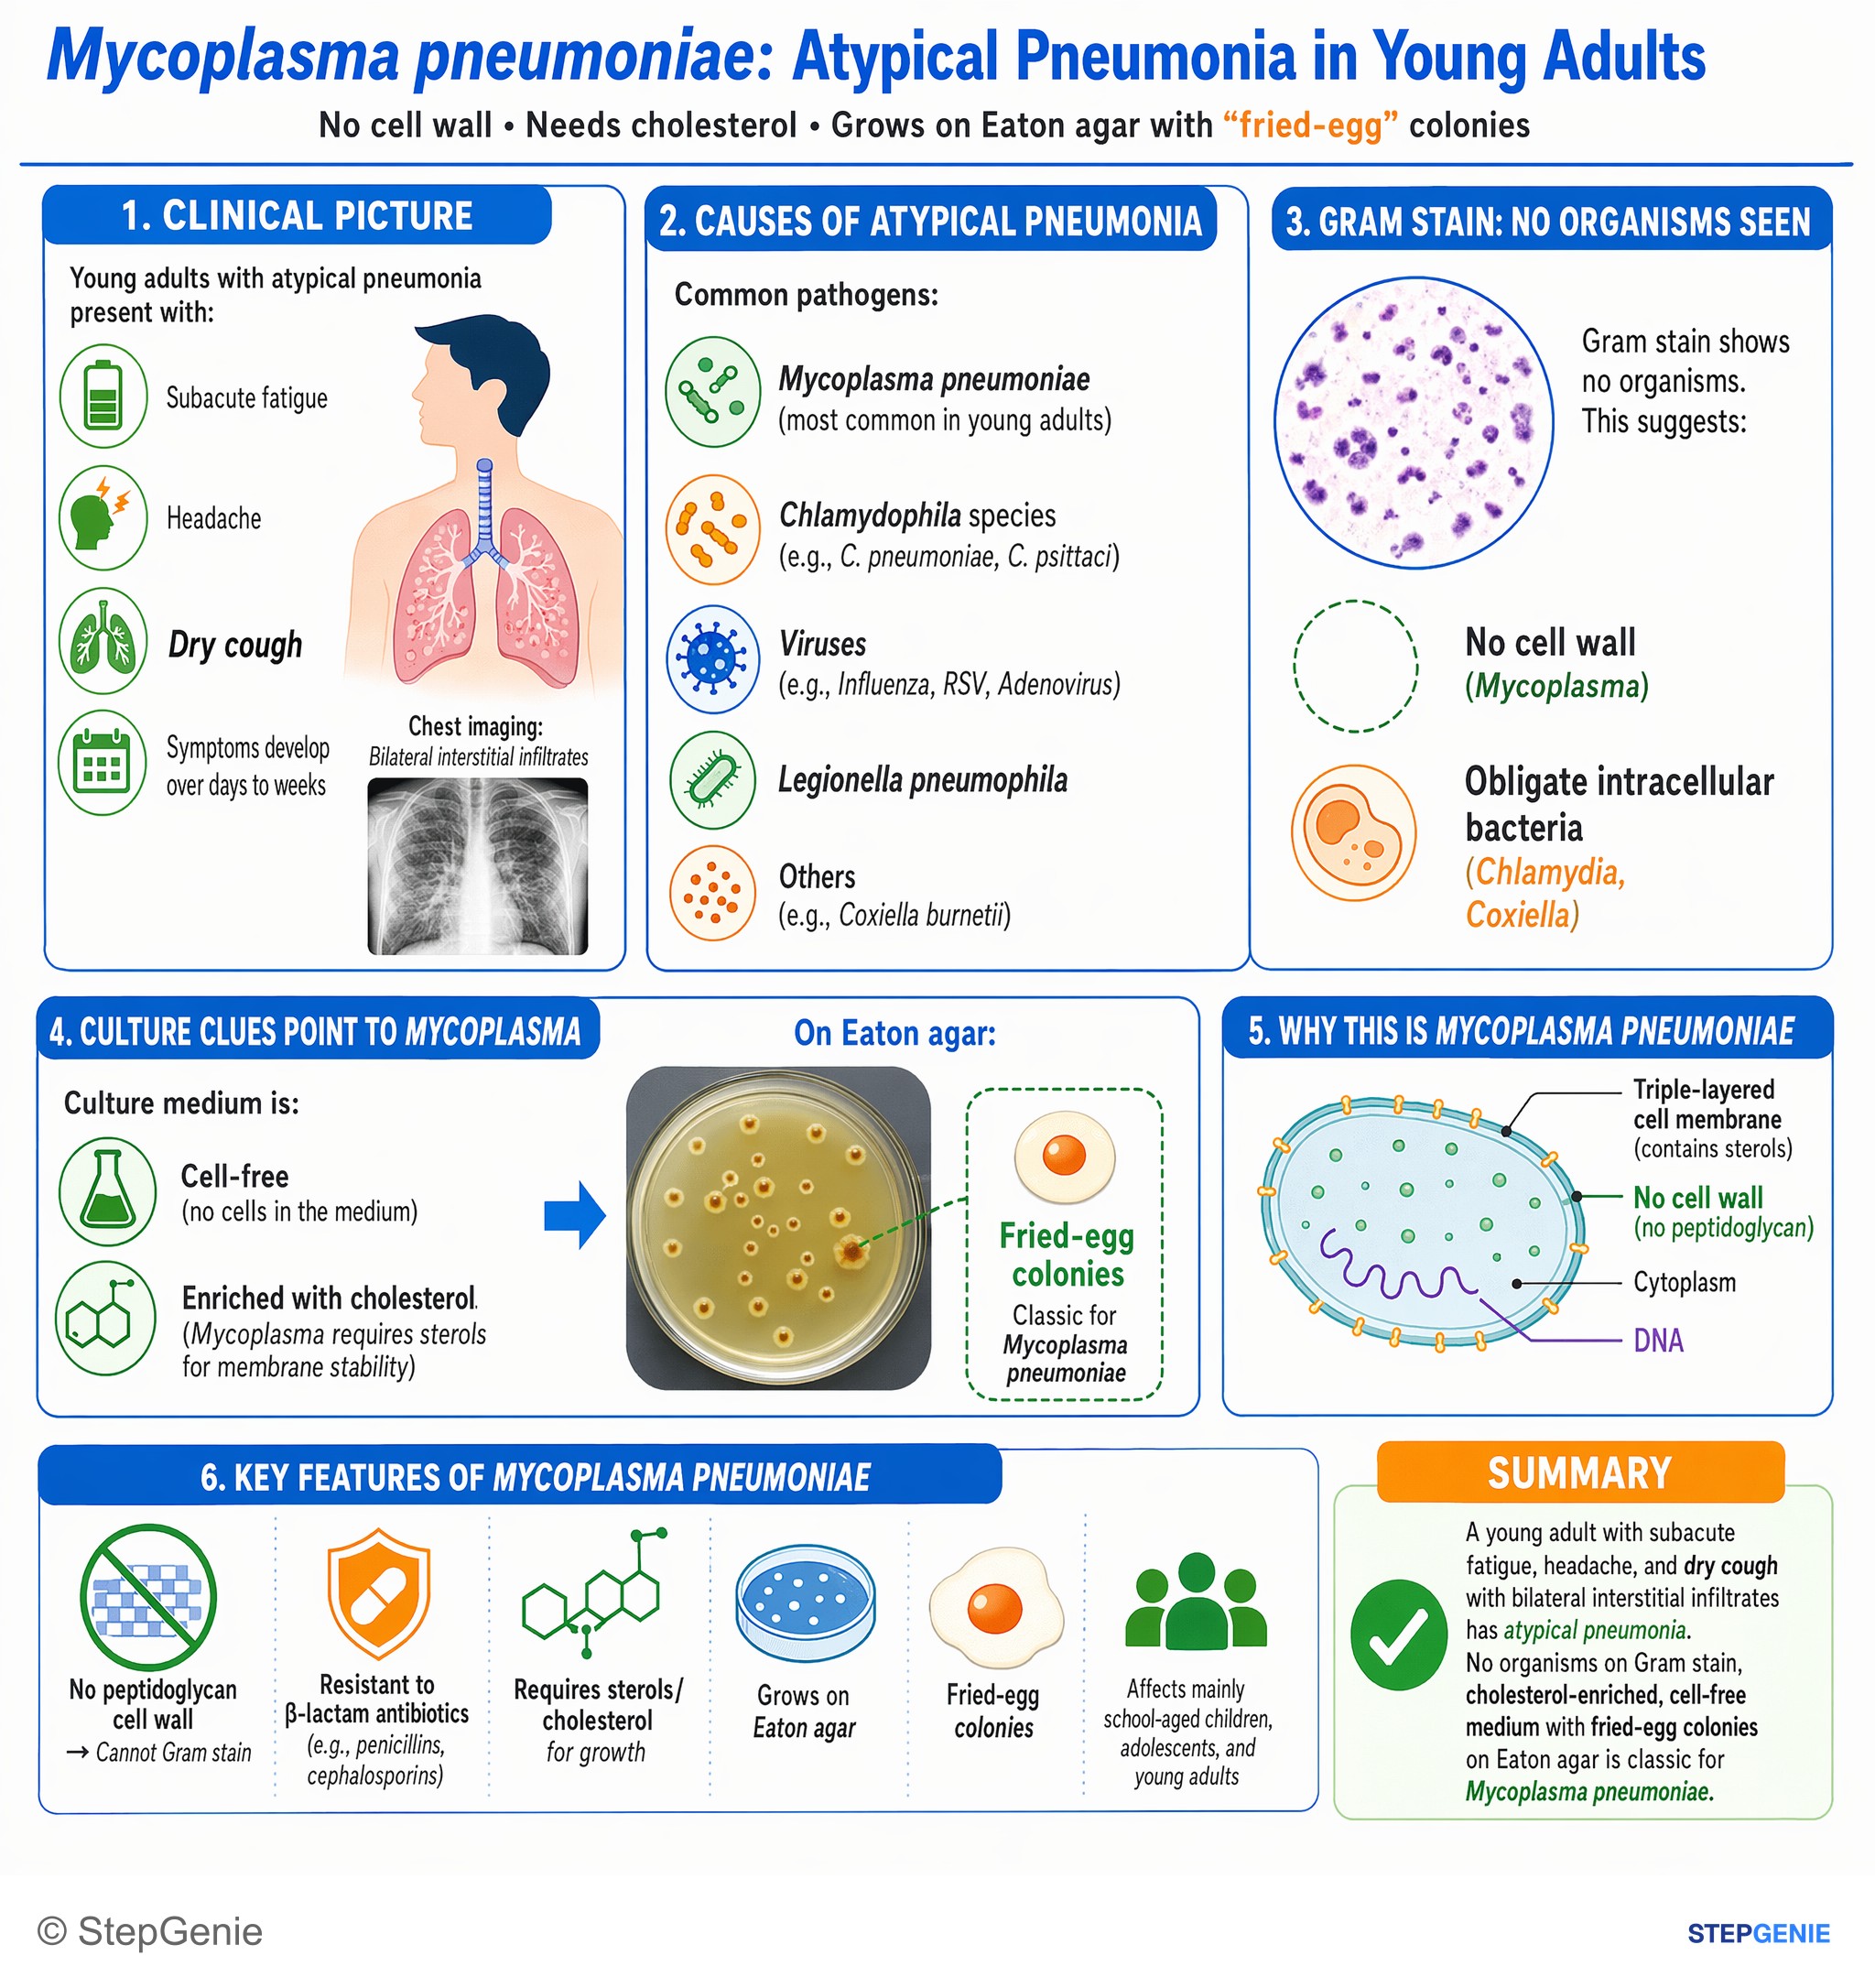
Mycoplasma pneumoniae causes atypical pneumonia in young adults; no cell wall, needs cholesterol, grows on Eaton agar with fried-egg…
USMLE Step 1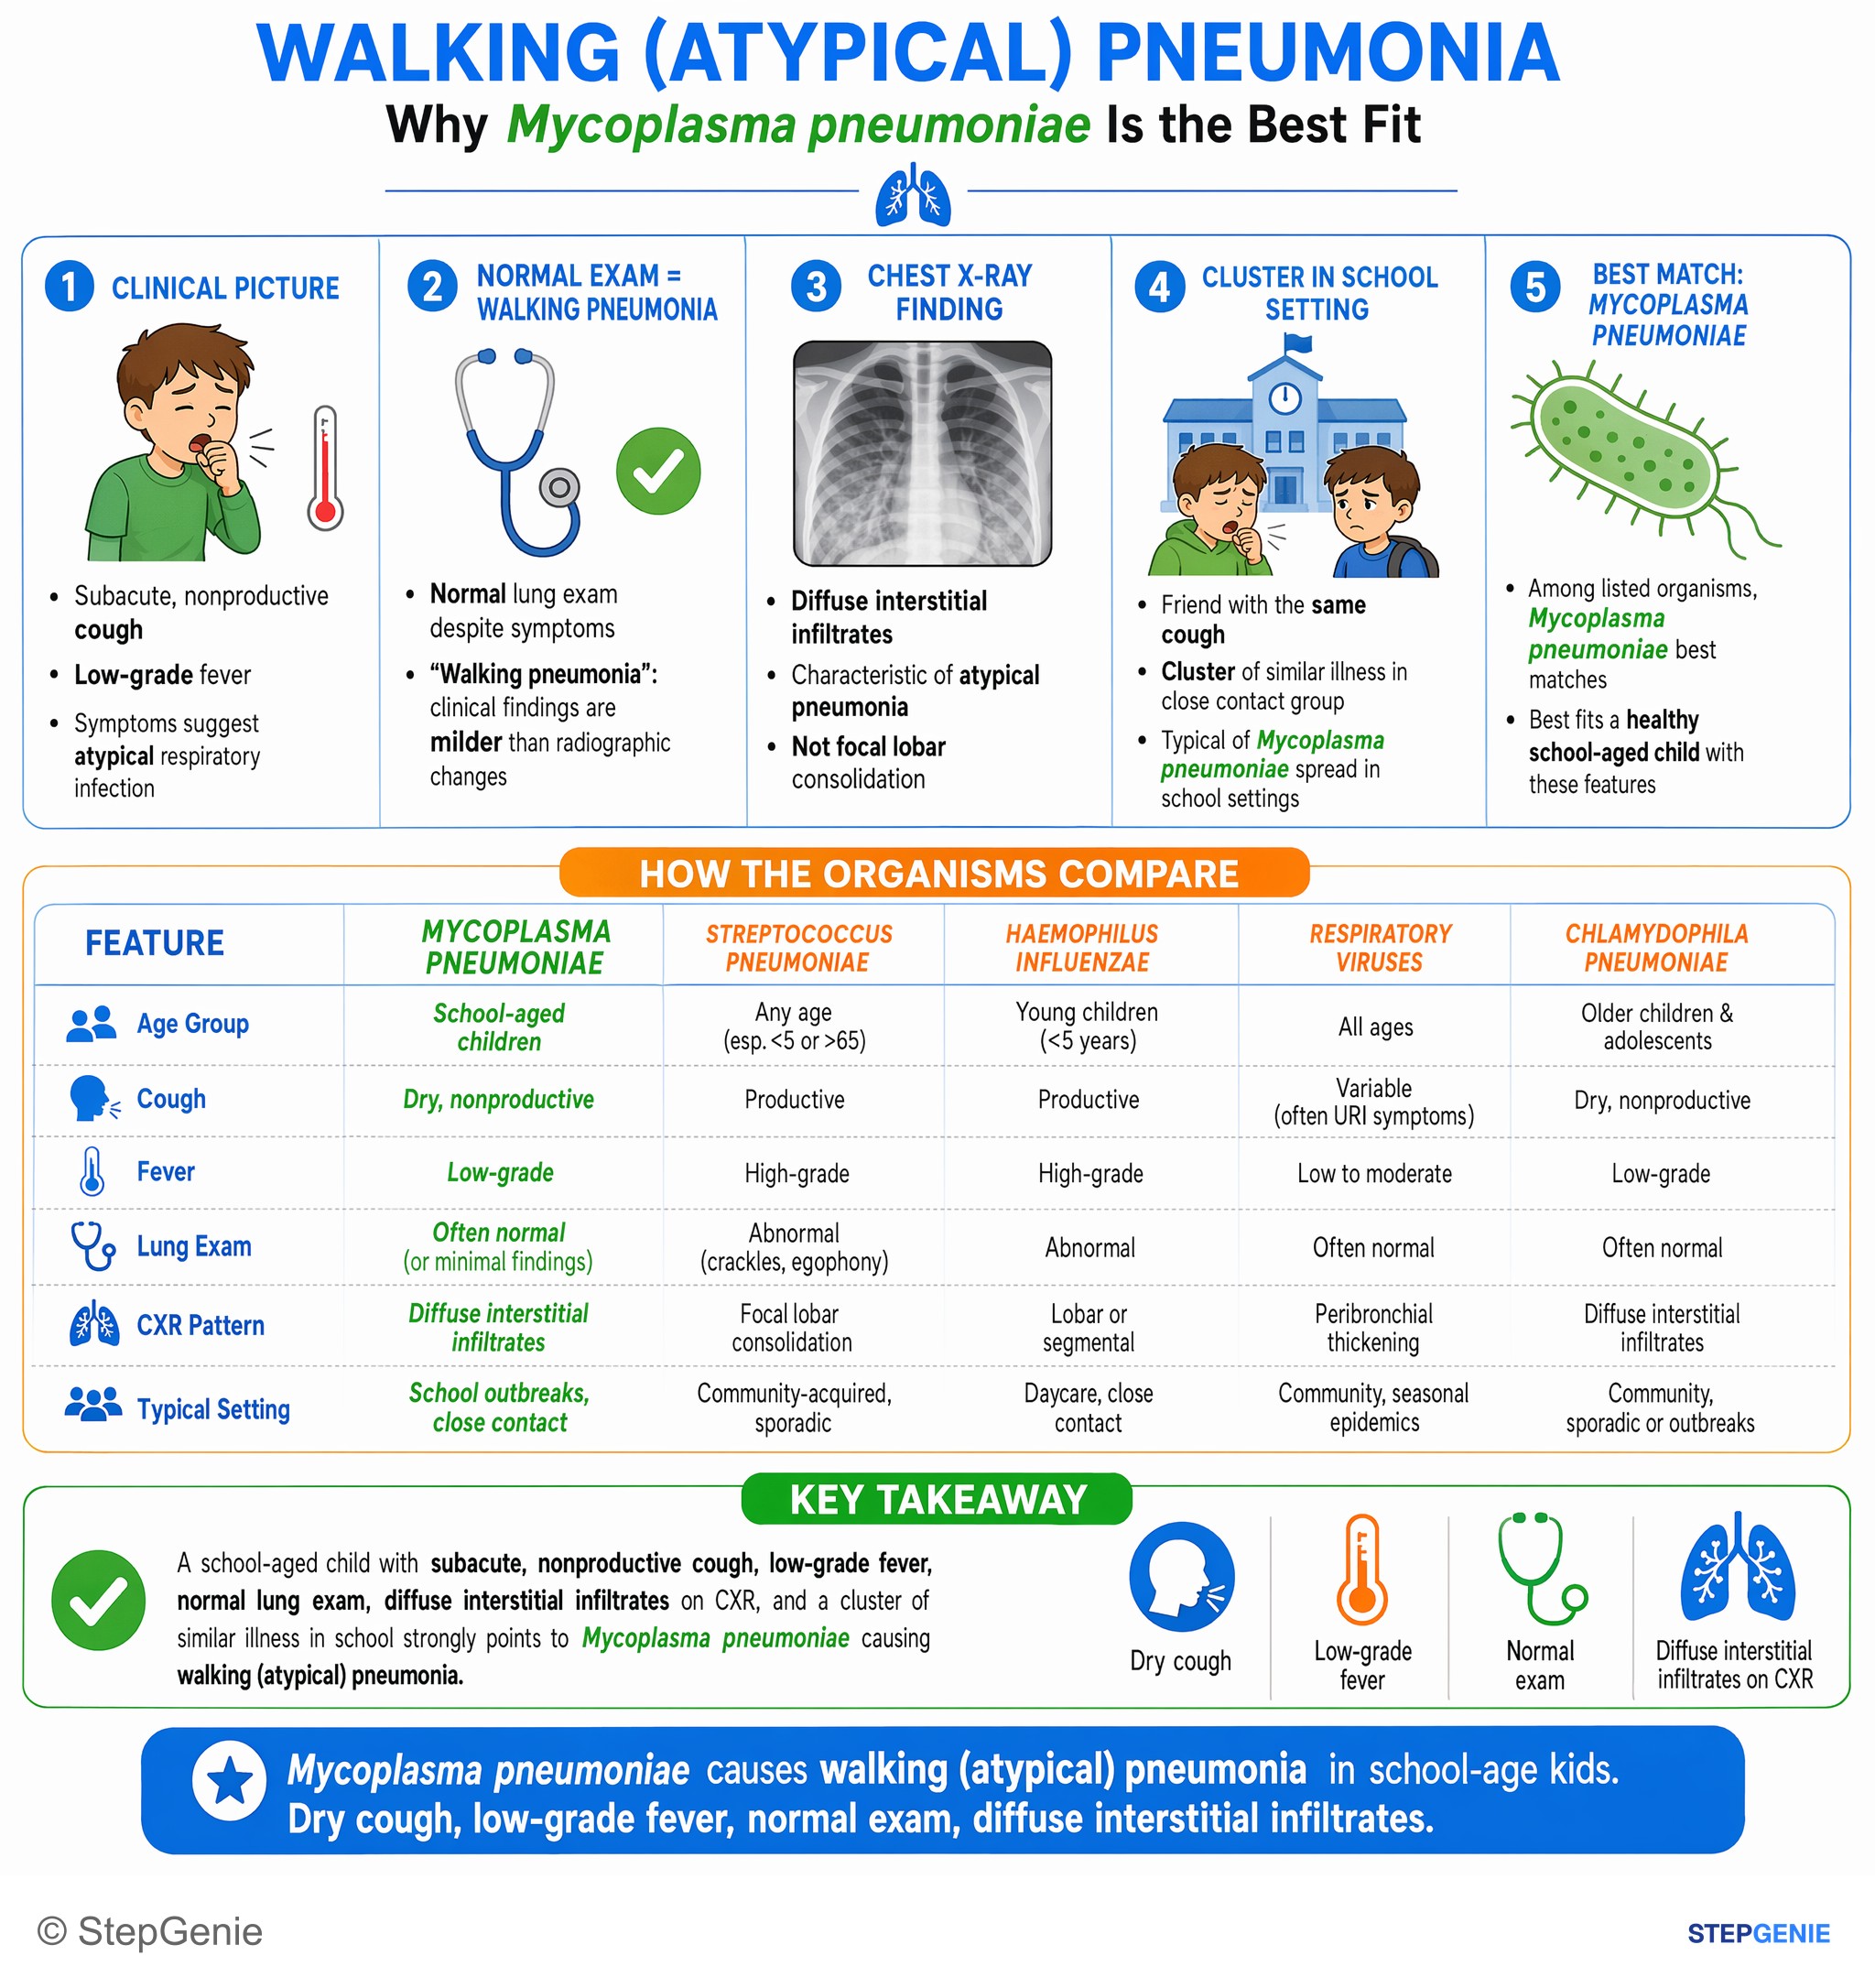
Mycoplasma pneumoniae causes walking (atypical) pneumonia in school-age kids: dry cough, low-grade fever, normal exam, diffuse…
USMLE Step 1Frequently Asked Questions
Why doesn’t Mycoplasma pneumoniae respond to beta-lactam antibiotics?
Mycoplasma pneumoniae does not respond to beta-lactams because it lacks a peptidoglycan cell wall. Beta-lactam drugs target cell wall synthesis, so this organism is intrinsically resistant to penicillins, cephalosporins, carbapenems, and even vancomycin. This is also why it is not seen well on Gram stain and why board-style questions often pair “no cell wall” with choosing a macrolide or doxycycline instead.
What are the classic clues that point to Mycoplasma pneumoniae on an exam question?
The classic clues are walking pneumonia, cold agglutinins, and no cell wall. Patients usually have an atypical pneumonia with dry cough, low-grade fever, headache, and malaise, often while looking relatively well. Test questions also like young patients in close-quarter outbreaks, patchy or diffuse interstitial infiltrates on chest x-ray, and a chest x-ray that looks worse than the physical exam.
Why does Mycoplasma pneumoniae cause cold agglutinins and hemolytic anemia?
Mycoplasma pneumoniae is associated with cold agglutinins because IgM antibodies can bind red blood cells at low temperatures, leading to hemolysis. This can produce hemolytic anemia findings, including general hemolysis clues such as elevated indirect bilirubin and LDH with low haptoglobin. On exams, the combination of atypical pneumonia plus cold agglutinins is a major hint toward Mycoplasma pneumoniae.
How is Mycoplasma pneumoniae diagnosed if it does not show up well on Gram stain?
Mycoplasma pneumoniae is often recognized clinically and can be confirmed with PCR or serology. Because it lacks a peptidoglycan cell wall, it is not seen well on Gram stain, so questions often expect you to identify it from the syndrome instead. The key pattern is atypical pneumonia with dry cough and diffuse interstitial infiltrates, especially in younger patients or close-quarter outbreaks.
What is the first-line treatment for Mycoplasma pneumoniae atypical pneumonia?
The usual treatment is a macrolide, such as azithromycin, or doxycycline. These are the right choices because Mycoplasma pneumoniae lacks a cell wall, making beta-lactams ineffective. In board-style community-acquired pneumonia questions, the key move is to recognize the atypical features and avoid picking a beta-lactam when the stem suggests Mycoplasma.