Neisseria gonorrhoeae is one of those Step bugs that shows up everywhere—OB/GYN stems, urethritis questions, septic arthritis, and “why is this newborn’s eye doing that?” If you can picture it instantly, you’ll answer faster and miss fewer easy points.
The 5-second visual hack (sticky mental image)
Mnemonic: “GONO = GO, NO capsule, NO maltose”
Picture two kidney beans (diplococci) wearing pink Gram-negative jackets, hiding inside a neutrophil, holding a sign that says:
- “GO!” (gonorrhea spreads easily)
- “NO capsule”
- “NO maltose” (glucose only)
That single image maps to the classic USMLE identifiers.
One-liner (what to say to yourself on a question)
“Neisseria gonorrhoeae is a Gram-negative, oxidase-positive intracellular diplococcus that ferments glucose (not maltose), has no capsule, and causes urethritis/cervicitis, PID, septic arthritis, and neonatal conjunctivitis.”
Identification: what the lab and the stem are really telling you
Core ID features (memorize these as a bundle)
- Gram-negative diplococci (often described as “coffee bean-shaped”)
- Oxidase positive
- Intracellular in neutrophils on smear from urethral discharge (classic)
- Ferments glucose only (key distinction from N. meningitidis)
- No capsule (again: contrast with meningococcus)
Quick comparison table (high-yield)
| Feature | N. gonorrhoeae | N. meningitidis |
|---|---|---|
| Morphology | Gram− diplococci | Gram− diplococci |
| Oxidase | + | + |
| Location on smear | Inside neutrophils (often emphasized) | Can be intra/extra |
| Sugars fermented | Glucose only | Glucose + maltose |
| Capsule | Absent | Present |
| Big diseases | Urethritis, cervicitis, PID, septic arthritis, neonatal conjunctivitis | Meningitis, meningococcemia, Waterhouse-Friderichsen |
Virulence & pathogenesis: the “why” behind the presentations
High-yield virulence factors
- Pili with antigenic variation
- Promotes adherence to mucosa
- Immune evasion → repeat infections are common
- IgA protease
- Helps colonize mucosal surfaces
- LOS (lipooligosaccharide) (not classic LPS O-antigen)
- Drives inflammation and tissue damage
Clinical “must-recognize” presentations (Step 1 + Step 2)
Urogenital
- Urethritis (often purulent discharge, dysuria)
- Cervicitis (may be asymptomatic; can cause discharge/bleeding)
- PID (pelvic inflammatory disease)
- Think: ascending infection → fever, pelvic pain, cervical motion tenderness
- Major complication: infertility, ectopic pregnancy
Disseminated gonococcal infection (DGI)
Classic board pattern:
- Migratory polyarthritis
- Tenosynovitis
- Dermatitis (small pustular/vesicular lesions)
Also very testable:
- Septic arthritis (often monoarticular—knee is a favorite)
Neonates
- Neonatal conjunctivitis (ophthalmia neonatorum)
- Typically 2–5 days after birth for gonorrhea
- Can be severe/purulent and threatens vision
- Prevention: erythromycin eye ointment prophylaxis (routine in many settings)
Diagnostics: what to order and what it means
Best test in practice questions
- NAAT (nucleic acid amplification test) on urine or swab
- Sensitive and specific; commonly paired with chlamydia testing
Classic microbiology (still fair game)
- Thayer-Martin (VPN) medium: Vancomycin, Polymyxin (or colistin), Nystatin
- Selects for Neisseria by inhibiting contaminants
- No capsule, glucose fermentation only → points to gonorrhoeae
Treatment: the USMLE-safe approach
Uncomplicated gonorrhea (common exam answer)
- Ceftriaxone
- Plus treat empirically for Chlamydia unless it’s been excluded:
- Doxycycline (often first-line), or azithromycin depending on scenario/guidelines
Step 2 “public health” add-ons
- Treat sexual partners
- Test for other STIs (HIV, syphilis, etc.)
- Counsel on reinfection risk (antigenic variation + common coinfections)
Rapid-fire high-yield bullets (what they love to test)
- Gram− diplococci inside neutrophils → think N. gonorrhoeae
- Glucose only (vs meningococcus = glucose + maltose)
- No capsule (vs meningococcus has capsule)
- Antigenic variation of pili → no lasting immunity → recurrent infections
- DGI triad: dermatitis + tenosynovitis + migratory polyarthritis
- Neonatal conjunctivitis at 2–5 days, prevented with erythromycin ointment
- Thayer-Martin (VPN) selective medium
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
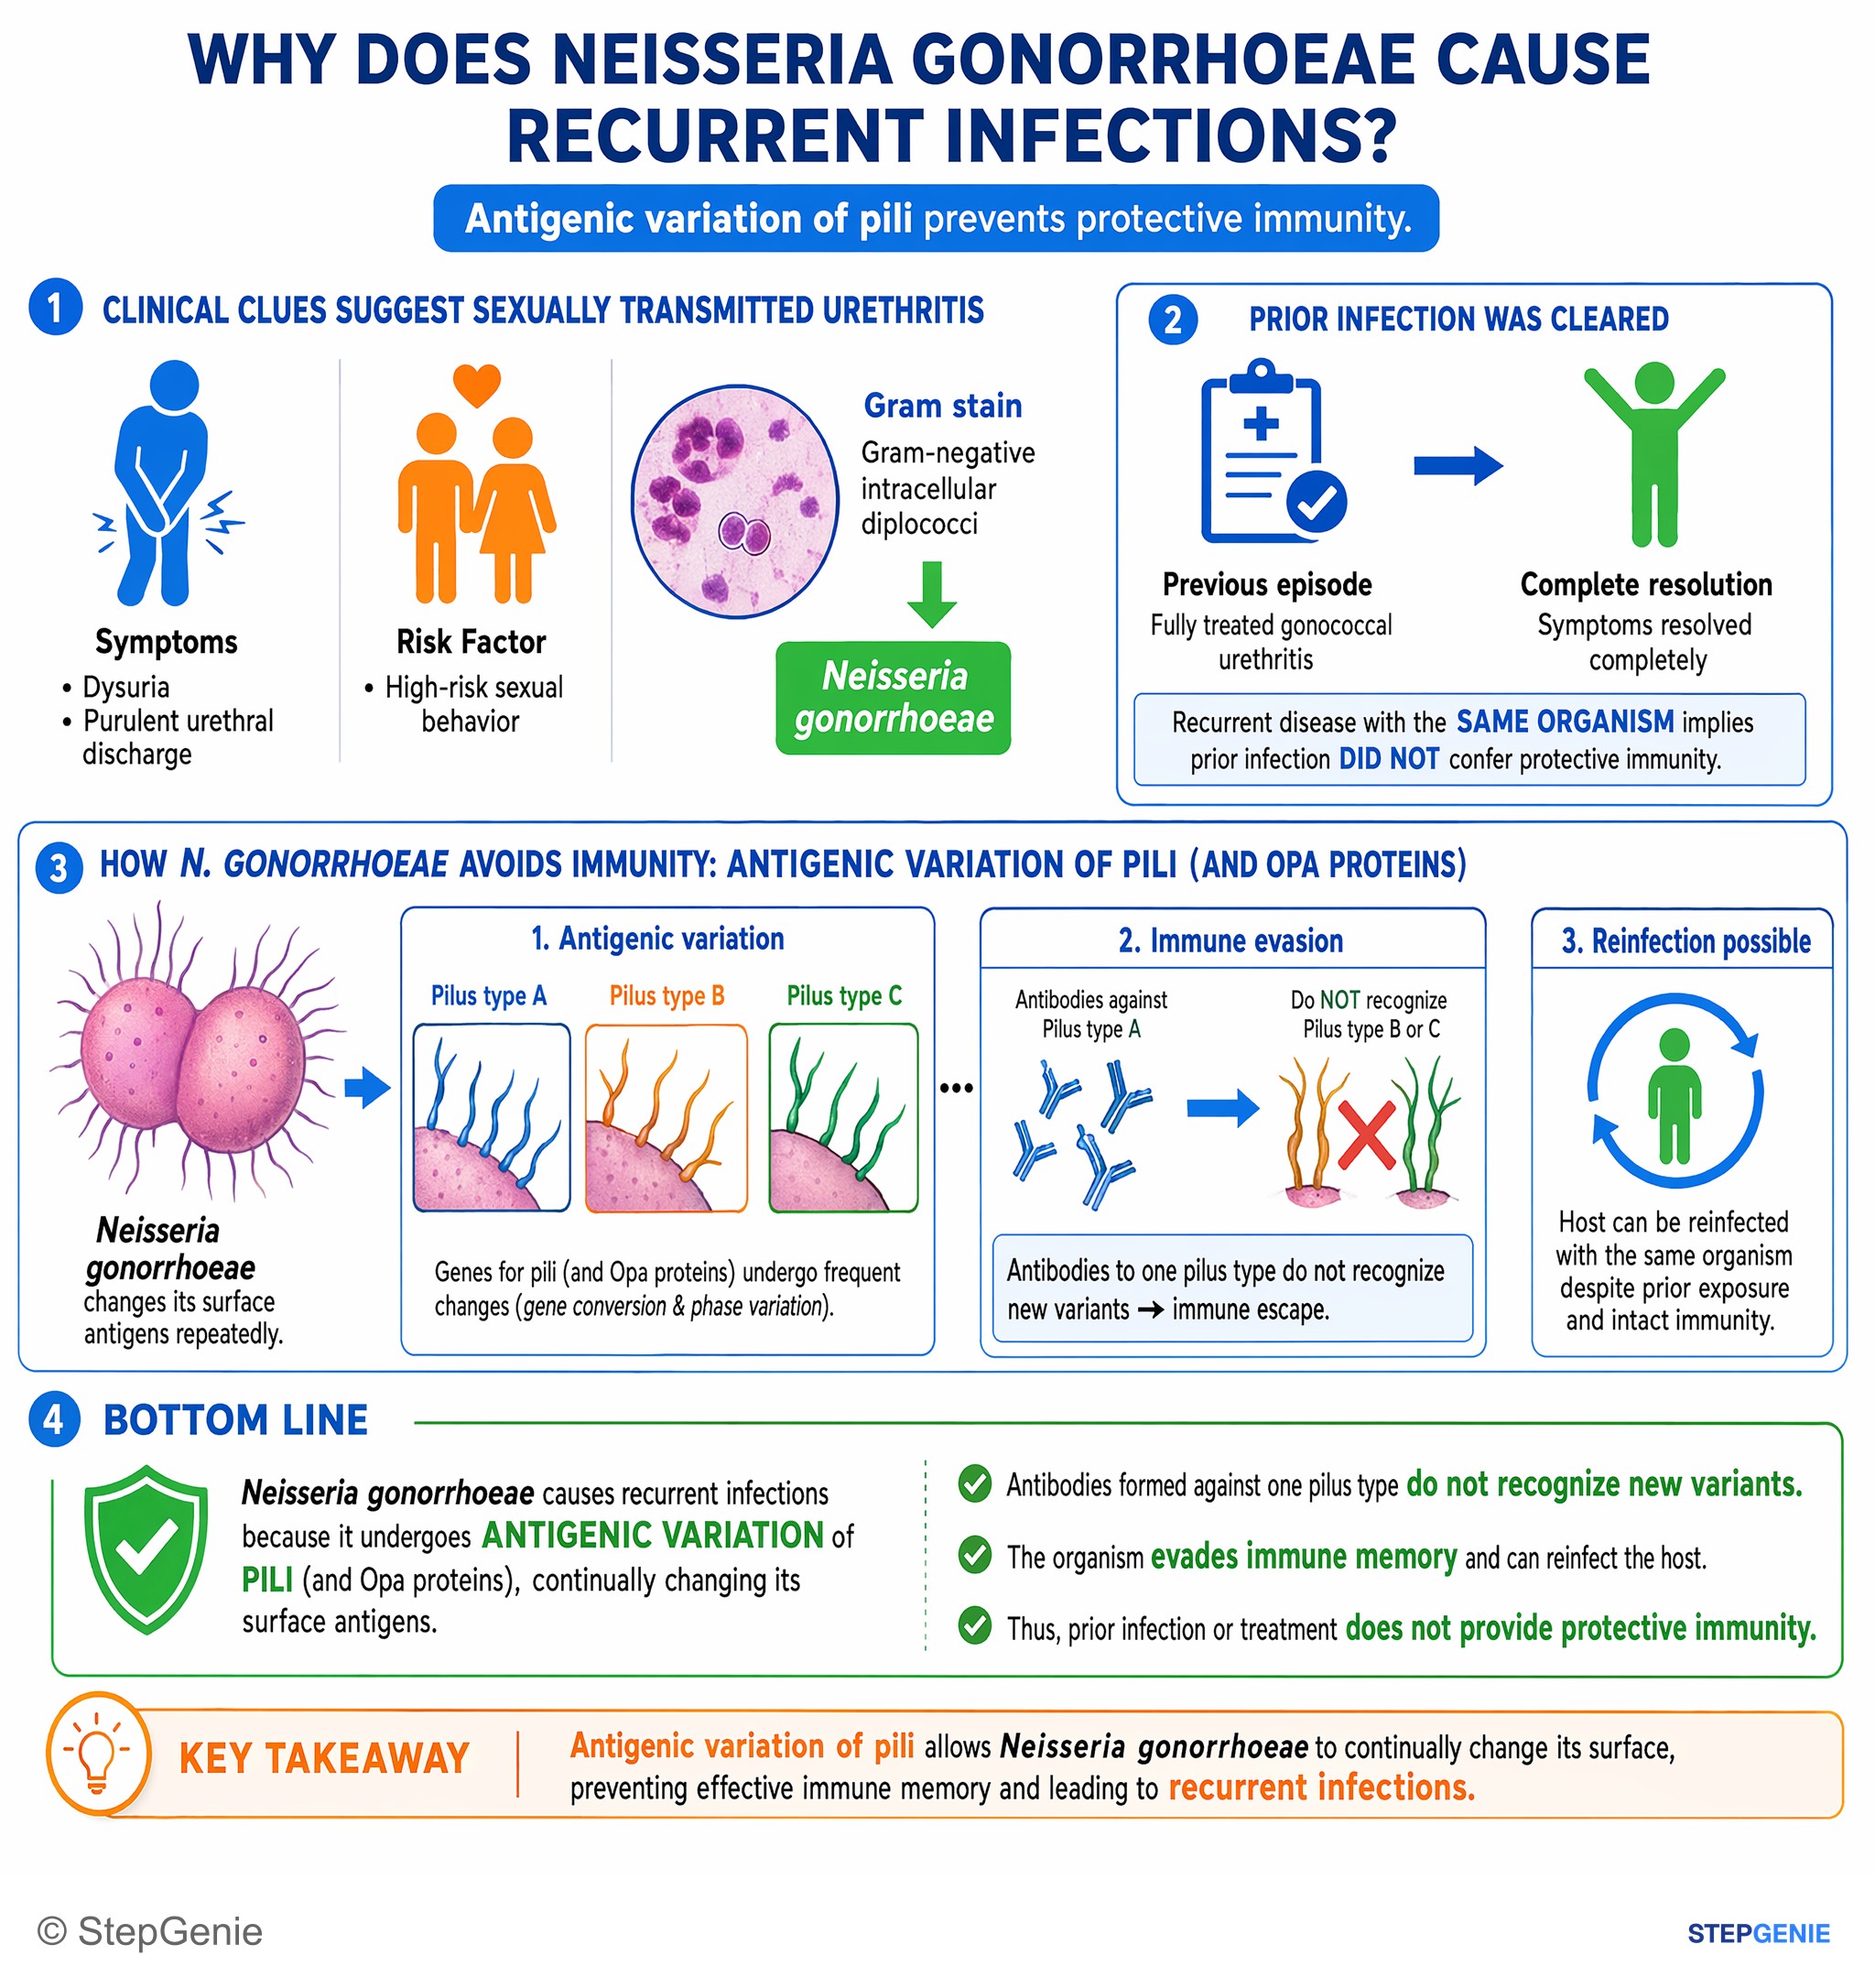
Neisseria gonorrhoeae causes recurrent infections due to antigenic variation of pili, preventing effective immune memory despite prior…
USMLE Step 1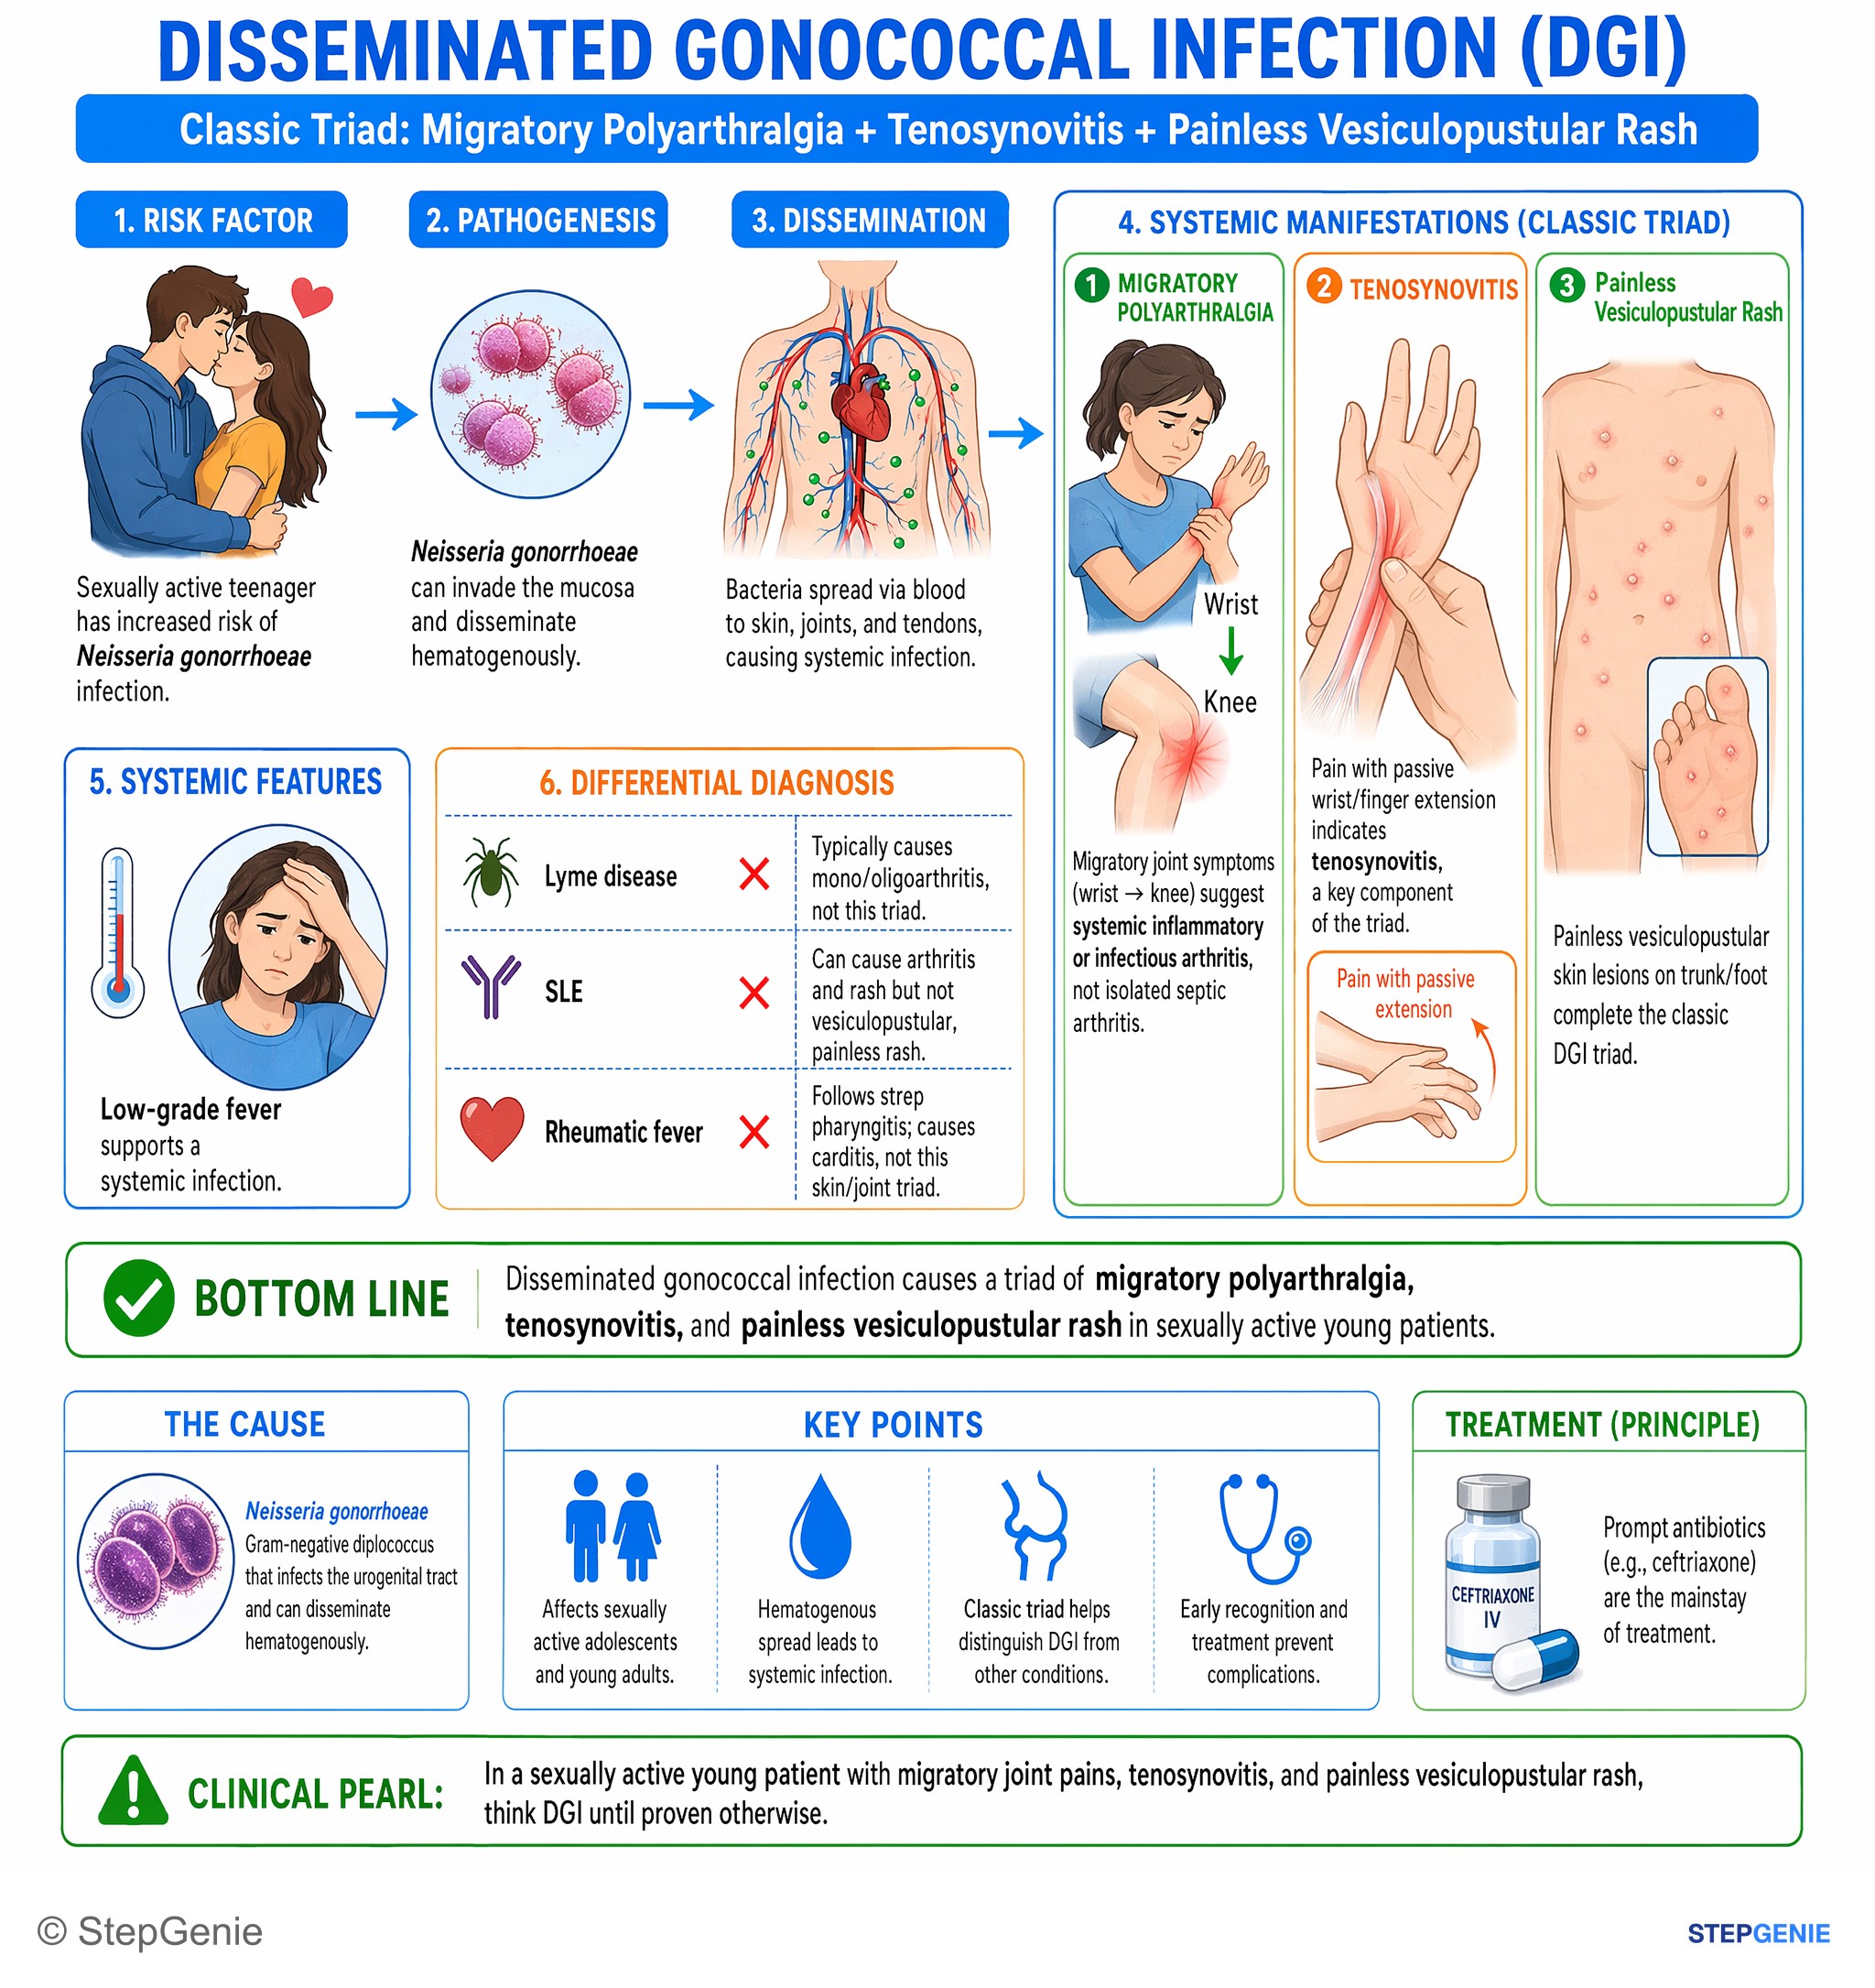
Disseminated gonococcal infection causes triad of migratory polyarthralgia, tenosynovitis, and painless vesiculopustular rash in sexually…
USMLE Step 2Frequently Asked Questions
How do you tell Neisseria gonorrhoeae from Neisseria meningitidis on a question stem?
Neisseria gonorrhoeae is distinguished by glucose-only fermentation and the absence of a capsule. Both organisms are Gram-negative, oxidase-positive diplococci, so the key differentiators are that gonorrhoeae ferments glucose but not maltose, lacks a capsule, and is often described as intracellular in neutrophils on a smear, especially from urethral discharge.
Why are repeat gonorrhea infections common?
Repeat gonorrhea infections are common because Neisseria gonorrhoeae has pili with antigenic variation. Those pili help the organism adhere to mucosal surfaces, and their antigenic variation allows immune evasion. The result is no lasting immunity, which is why reinfection is a classic high-yield clue associated with this organism.
What is the classic disseminated gonococcal infection pattern?
The classic disseminated gonococcal infection pattern is migratory polyarthritis, tenosynovitis, and dermatitis. On exams, dermatitis is often described as small pustular or vesicular skin lesions. Gonorrhea can also present as septic arthritis, often monoarticular, with the knee being a favorite board-style joint to test.
What is the first-line treatment for uncomplicated gonorrhea?
The standard exam answer for uncomplicated gonorrhea is ceftriaxone. Patients should also be treated empirically for Chlamydia unless it has been excluded, commonly with doxycycline or sometimes azithromycin depending on the scenario or guideline context. Public health management also includes treating sexual partners and testing for other sexually transmitted infections.
When does gonococcal neonatal conjunctivitis happen, and how is it prevented?
Gonococcal neonatal conjunctivitis typically appears 2 to 5 days after birth and is prevented with erythromycin eye ointment prophylaxis. It can be severe and purulent and may threaten vision, which is why this timing and prevention strategy are important clinical clues when a newborn presents with eye discharge shortly after delivery.