Klebsiella pneumoniae is a heavily encapsulated, lactose-fermenting, nonmotile, urease-positive gram-negative rod from the gut. It classically causes severe lobar pneumonia with dark red "currant jelly" sputum, lung abscess and empyema in people with alcohol use disorder or diabetes, and it also causes UTIs and hospital-acquired infections. Hypervirulent strains (hvKp) cause community-acquired liver abscesses in otherwise healthy people that can seed the eye (endophthalmitis) and the brain (meningitis). Resistance is just as testable: serious ESBL infections outside the urinary tract need a carbapenem, and carbapenemase producers such as KPC and NDM make it a carbapenem-resistant Enterobacterales (CRE).
The Q-bank vignette
A 58-year-old man is brought to the emergency department with 3 days of fever, cough and shortness of breath. He has alcohol use disorder and poorly controlled type 2 diabetes. Chest x-ray shows dense consolidation of the right upper lobe with a bulging fissure. He is coughing up thick, dark red, jelly-like sputum. Gram stain shows gram-negative rods, and culture grows pink, very mucoid colonies on MacConkey agar. The isolate is nonmotile.
Which organism is the most likely cause?
- A. Escherichia coli
- B. Haemophilus influenzae
- C. Klebsiella pneumoniae
- D. Legionella pneumophila
- E. Oral anaerobes (Bacteroides, Fusobacterium, Peptostreptococcus)
- F. Pseudomonas aeruginosa
- G. Staphylococcus aureus
- H. Streptococcus pneumoniae
Answer: C. Klebsiella pneumoniae.
Why it's Klebsiella pneumoniae
- The host: Merck names diabetes and alcohol use disorder as the classic risk groups. Heavy drinking also raises aspiration risk, and aspiration typically lands in the posterior segments of the upper lobes or the superior or lateral basal segments of the lower lobes (Merck). StatPearls describes Klebsiella pneumonia as typically a lobar infiltrate in the posterior right upper lobe, which is why stems so often show an upper-lobe consolidation.
- The sputum: thick, bloody, mucoid "currant jelly" sputum (dark red or brown). The capsule makes it mucoid, and the severe, necrotizing inflammation makes it bloody; lung abscess and empyema can follow.
- The x-ray: the bulging fissure sign is a lobar consolidation so heavy that the lobe expands and bows the fissure. It is the classic exam association with Klebsiella, but it is now rarely seen because of early antibiotic use (Radiopaedia) and is not specific to Klebsiella (StatPearls).
- The lab: a gram-negative rod that grows as pink (lactose-fermenting), very mucoid colonies and is nonmotile is Klebsiella's fingerprint.
Klebsiella microbiology at a glance
| Feature | K. pneumoniae | Why it matters |
|---|---|---|
| Gram stain | Gram-negative rod (Enterobacterales); normal gut flora | Lives in the gut; spreads person to person and on equipment |
| Capsule | Large polysaccharide capsule | Main virulence factor: antiphagocytic; makes colonies and sputum mucoid |
| MacConkey | Lactose fermenter (pink) | Separates it from Pseudomonas and other non-fermenters |
| Colonies | Very mucoid | Hypervirulent strains are often hypermucoviscous (positive string test) |
| Motility | Nonmotile | E. coli, Proteus and Pseudomonas are motile |
| Urease | Positive | Like Proteus, a cause of struvite (magnesium ammonium phosphate) stones |
Memory hook, ABCDE: Aspiration pneumonia, aBscess (lung and liver), Currant jelly sputum, Diabetes, Ethanol. Add UTIs and hospital infections.
What Klebsiella causes
| Syndrome | Typical patient | Clues |
|---|---|---|
| Community-acquired pneumonia | Alcohol use disorder, diabetes | Currant jelly sputum, dense lobar consolidation, abscess, empyema; severe |
| Hospital-acquired infections | Ventilated patients, IV catheters, long antibiotic courses | Ventilator-associated pneumonia, bloodstream infection, wound and surgical-site infection, meningitis |
| UTI | Catheterized or hospitalized patients | Urease-positive, so struvite stones |
| Liver abscess | Often a healthy adult in the community (hvKp) | Fever, right upper quadrant pain, spread to eye and brain |
CDC notes that Klebsiella spreads mainly through person-to-person contact and contaminated equipment such as ventilators and IV catheters, not through the air, so hand hygiene is the core of prevention.
Hypervirulent K. pneumoniae: the liver abscess that spreads
- Who: classic Klebsiella infects hospitalized or immunocompromised patients; hvKp can also infect healthy people in the community (WHO). It was first recognized in Asia, where it now causes more than 80% of pyogenic liver abscesses, and it is reported worldwide, including in people who never traveled to Asia (Emerging Infectious Diseases, 2018). Diabetes is a classic association, although not every cohort confirms it.
- Classic picture: fever and right upper quadrant pain from a pyogenic liver abscess without biliary disease ("cryptogenic"), often with bacteremia.
- Metastatic spread is the signature: endogenous endophthalmitis (eye pain, blurred vision), meningitis or brain abscess, and seeding of muscle or bone. Endophthalmitis needs rapid recognition and eye-directed treatment, so any visual symptom in a patient with a Klebsiella liver abscess or bacteremia calls for urgent ophthalmology review.
- Lab clues: hypermucoviscous colonies with a positive string test (a viscous string longer than 5 mm when a colony is stretched), capsule types K1 (sequence type 23) and K2, and the siderophore aerobactin. Hypermucoviscosity and hypervirulence overlap but are not the same thing.
- Treatment: drain the abscess and give antibiotics guided by susceptibility. hvKp has usually been susceptible (in a Paris series, none of 13 cryptogenic liver-abscess strains made an ESBL), but WHO warned in 2024 about ST23 hvKp carrying carbapenemase genes: hypervirulent and carbapenem-resistant.
Don't confuse it with an amebic liver abscess from Entamoeba histolytica: travel to or migration from an endemic area, "anchovy paste" pus, positive amebic serology and treatment with metronidazole plus a luminal agent.
Resistance: ESBL, KPC and CRE
| Strain | What it inactivates | What to use |
|---|---|---|
| Susceptible | No acquired beta-lactamase | By susceptibility: third-generation cephalosporins, cefepime, piperacillin-tazobactam, fluoroquinolones, aminoglycosides or carbapenems (Merck) |
| ESBL producer | Most penicillins and cephalosporins (including ceftriaxone) and aztreonam; carbapenems are spared (IDSA) | A carbapenem (ertapenem, meropenem or imipenem) for infections outside the urinary tract; IDSA (2026) advises against piperacillin-tazobactam there even when the lab reports it susceptible. ESBL cystitis: nitrofurantoin, TMP-SMX or a single aminoglycoside dose, among others |
| KPC producer (a CRE) | Nearly all beta-lactams, including carbapenems | Preferred (IDSA 2026): ceftazidime-avibactam, imipenem-relebactam or meropenem-vaborbactam; aztreonam-avibactam and cefiderocol are alternatives |
| NDM producer (a CRE; metallo-beta-lactamase) | All traditional beta-lactams, including carbapenems, except aztreonam (which co-produced ESBL and AmpC enzymes often destroy) | Preferred (IDSA 2026): aztreonam-avibactam or cefiderocol; ceftazidime-avibactam plus aztreonam if aztreonam-avibactam is unavailable. The KPC agents fail because avibactam, relebactam and vaborbactam don't inhibit NDM. CDC calls NDM-CRE "extremely hard to treat" |
- CRE are Enterobacterales resistant to at least one carbapenem or that produce a carbapenemase (CDC; IDSA). Healthy people rarely get them; they spread on hands, wounds, stool and devices in health care settings.
- KPC stands for Klebsiella pneumoniae carbapenemase, and IDSA notes it has historically been found most often in K. pneumoniae, although it is increasingly found in Enterobacter cloacae and E. coli.
- NDM-producing CRE rose 461% in the US between 2019 and 2023 (CDC).
Why every other answer choice is wrong
A. Escherichia coli. The other common lactose fermenter, but it is motile and lacks Klebsiella's very mucoid colonies. It is the top cause of UTIs and a major cause of neonatal meningitis (K1 capsule) and gram-negative sepsis, and it causes pneumonia mainly in hospitalized patients. Currant jelly sputum is Klebsiella's signature.
B. Haemophilus influenzae. A small gram-negative coccobacillus behind COPD exacerbations, otitis media and sinusitis. It needs factor X (hemin) and factor V (NAD+), so it grows on chocolate agar, not as pink colonies on MacConkey. Review it with the H. influenzae mnemonic.
D. Legionella pneumophila. Severe pneumonia with hyponatremia, diarrhea and confusion after exposure to contaminated water (cooling towers, hot tubs, plumbing). It stains poorly on Gram stain, needs buffered charcoal yeast extract (BCYE) agar with iron and cysteine, is usually diagnosed with a urine antigen test, and never grows on MacConkey. See the Legionella breakdown.
E. Oral anaerobes. Alcohol use does raise aspiration risk, and anaerobes are the classic cause of lung abscess, but the clues would be foul-smelling sputum, poor dentition and a cavity with an air-fluid level in a dependent segment. Anaerobes don't grow as pink colonies on routine MacConkey agar. Compare them in the lung abscess breakdown.
F. Pseudomonas aeruginosa. Also a gram-negative rod behind severe hospital pneumonia, but it is a non-lactose fermenter (colorless colonies on MacConkey), oxidase-positive and motile, with blue-green pigment (pyocyanin) and a grape-like odor. Think ventilators, cystic fibrosis, burns and neutropenia. See the Pseudomonas breakdown.
G. Staphylococcus aureus. Causes necrotizing, cavitating pneumonia, classically after influenza or from septic emboli in people who inject drugs, but it is a gram-positive coccus in clusters, and this Gram stain shows rods.
H. Streptococcus pneumoniae. The most common cause of lobar community-acquired pneumonia, with rust-colored sputum, but it is a gram-positive, lancet-shaped diplococcus (alpha-hemolytic, optochin-sensitive, bile-soluble). The S. pneumoniae sketch covers its lab ID.
How USMLE tests Klebsiella
- Currant jelly sputum = Klebsiella; currant jelly stools = intussusception. Same jam, different organ.
- Pink + very mucoid + nonmotile on MacConkey = Klebsiella; pink + motile = E. coli; colorless + oxidase-positive = Pseudomonas.
- Pink colonies on MacConkey mean a lactose-fermenting gram-negative rod, which excludes Legionella, Haemophilus, obligate anaerobes and the gram-positive choices (none of them grow as pink colonies on routine MacConkey agar).
- Liver abscess in a healthy adult, classically in the Asian Pacific Rim, plus eye pain = hvKp with endophthalmitis.
- Struvite stone = urease-positive organism: Proteus or Klebsiella.
- ESBL infection outside the urinary tract = carbapenem, not piperacillin-tazobactam; KPC = ceftazidime-avibactam, imipenem-relebactam or meropenem-vaborbactam; NDM = aztreonam-avibactam or cefiderocol.
Key takeaways
- K. pneumoniae is an encapsulated, lactose-fermenting, nonmotile, urease-positive gram-negative rod with very mucoid colonies; the capsule is its main virulence factor.
- Classic pneumonia: alcohol use disorder or diabetes, currant jelly sputum, dense lobar consolidation (bulging fissure), abscess and empyema.
- In hospitals it causes ventilator-associated pneumonia, bacteremia, wound infections, meningitis and UTIs (struvite stones).
- hvKp: community-acquired liver abscess in healthy adults with metastatic endophthalmitis or meningitis; hypermucoviscous (string test over 5 mm), K1/K2 capsules.
- ESBL (outside the urinary tract) = carbapenem; KPC (a CRE) = ceftazidime-avibactam, imipenem-relebactam or meropenem-vaborbactam (IDSA 2026); NDM-CRE is rising fast, is extremely hard to treat and calls for aztreonam-avibactam or cefiderocol.
Sources
- Klebsiella, Enterobacter, and Serratia Infections — Merck Manual Professional Edition (2024)
- About Klebsiella — CDC (2025)
- About Carbapenem-resistant Enterobacterales (CRE) — CDC (2025)
- IDSA 2026 Guidance on the Treatment of Antimicrobial Resistant Gram-Negative Infections — Infectious Diseases Society of America (2026)
- Antimicrobial Resistance, Hypervirulent Klebsiella pneumoniae – Global situation — World Health Organization (2024)
- Hypervirulent Klebsiella pneumoniae — Clinical Microbiology Reviews (2019)
- Hypervirulent Klebsiella pneumoniae in Cryptogenic Liver Abscesses, Paris, France — Emerging Infectious Diseases, CDC (2018)
- Klebsiella Pneumonia — StatPearls, NCBI Bookshelf (2023)
- Klebsiella Infections — Medscape Reference (2015)
- Lung Abscess — Merck Manual Professional Edition (2025)
- Urinary Calculi — Merck Manual Professional Edition (2025)
- Bulging fissure sign — Radiopaedia
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
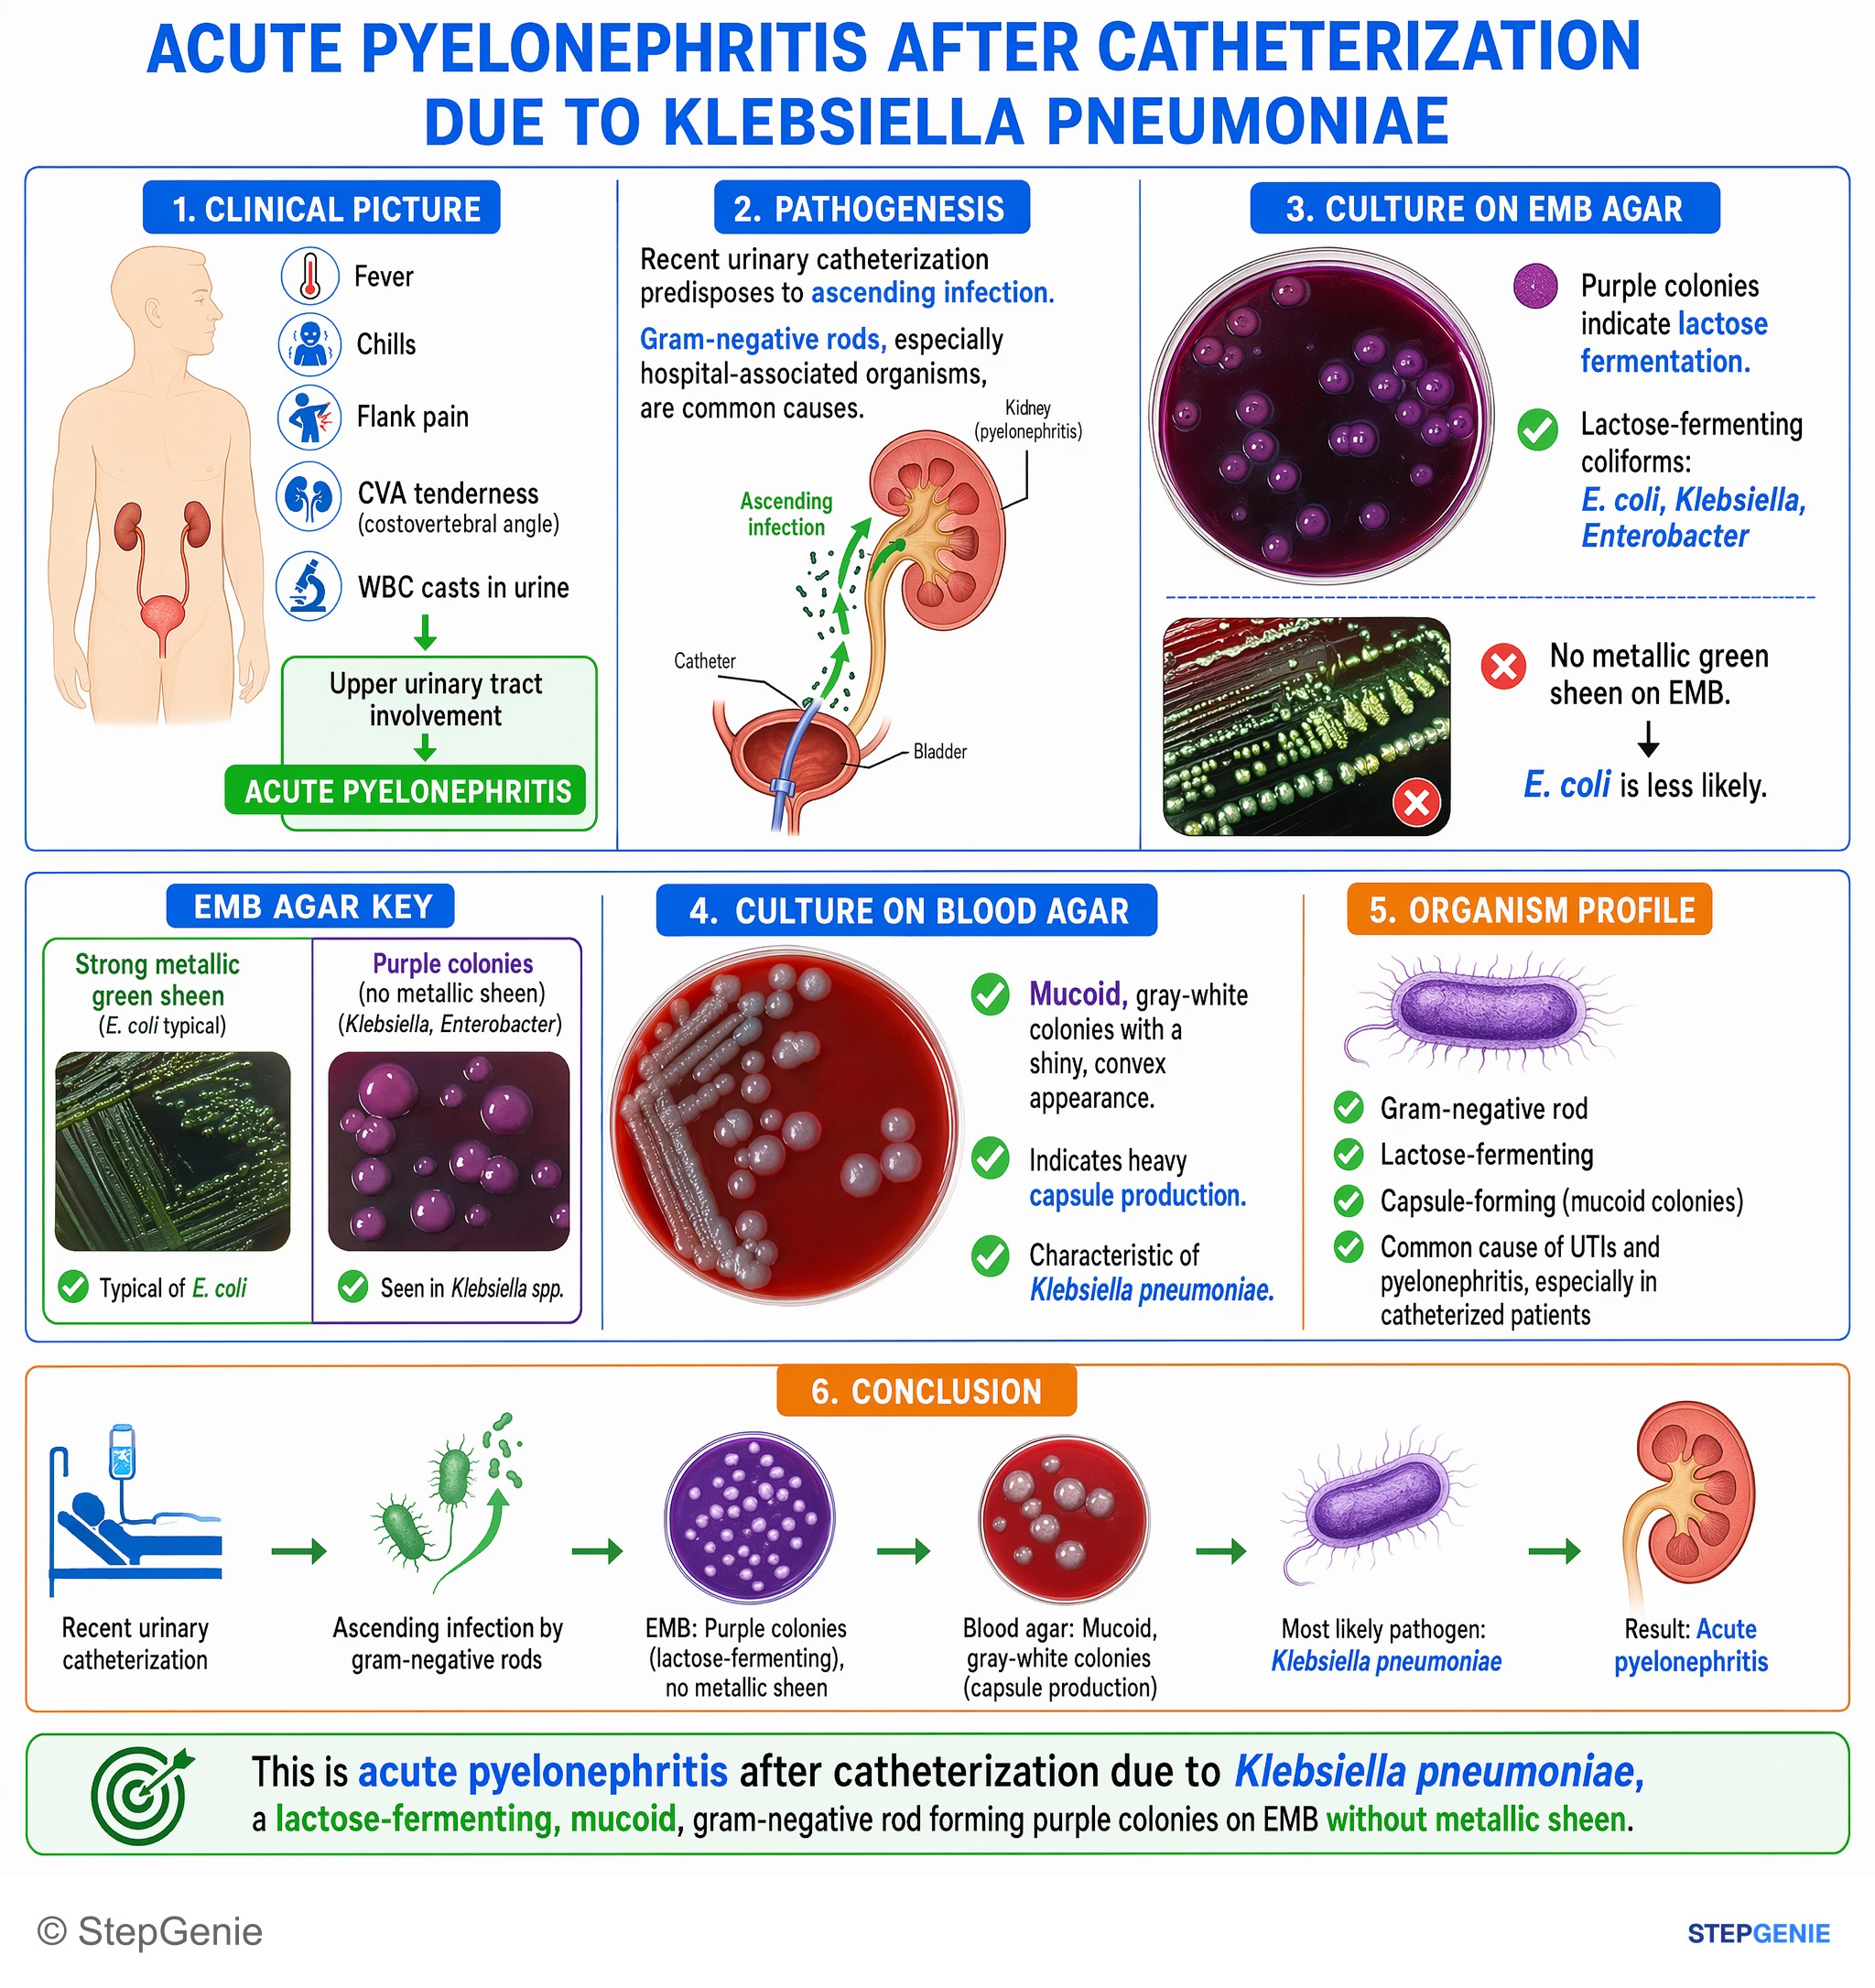
Acute pyelonephritis after catheterization due to Klebsiella, a lactose-fermenting, mucoid, gram-negative rod forming purple colonies on…
USMLE Step 1Frequently Asked Questions
What are the classic USMLE clues for Klebsiella pneumoniae pneumonia?
The classic stem is a patient with alcohol use disorder or diabetes who has severe lobar pneumonia with thick, dark red currant jelly sputum, often with a dense upper-lobe consolidation (sometimes with a bulging fissure), lung abscess or empyema. The lab clues are a gram-negative rod that grows as pink, very mucoid colonies on MacConkey agar, because it ferments lactose and has a large polysaccharide capsule, and that is nonmotile and urease-positive.
Why does Klebsiella cause currant jelly sputum?
Klebsiella makes a large polysaccharide capsule that produces thick, mucoid secretions, and its pneumonia is a severe, necrotizing infection that bleeds into the airways. The mix of mucus and blood gives the dark red or brown, jelly-like sputum. The same capsule is the organism's main virulence factor, because it resists phagocytosis, and it explains the very mucoid colonies on culture. Don't confuse it with currant jelly stools, a sign of intussusception.
Is Klebsiella pneumoniae a lactose fermenter, and how do you tell it from E. coli and Pseudomonas?
Yes. Klebsiella pneumoniae ferments lactose, so it forms pink colonies on MacConkey agar, and its capsule makes them very mucoid. E. coli also ferments lactose but is motile and less mucoid, whereas Klebsiella is nonmotile. Pseudomonas aeruginosa does not ferment lactose, so its colonies are colorless; it is also oxidase-positive and often makes a blue-green pigment with a grape-like smell.
What is hypervirulent Klebsiella pneumoniae (hvKp)?
Hypervirulent K. pneumoniae is a strain type that infects healthy people in the community rather than mainly hospitalized or immunocompromised patients. It classically causes a pyogenic liver abscess without biliary disease and spreads through the blood to the eye (endophthalmitis), the brain (meningitis or abscess), muscle or bone. It was first recognized in Asia, where it causes most pyogenic liver abscesses, and now occurs worldwide. Isolates are often hypermucoviscous, with a positive string test and K1 or K2 capsules.
How is ESBL-producing Klebsiella treated?
For serious ESBL-producing Klebsiella infections outside the urinary tract, a carbapenem such as meropenem, imipenem or ertapenem is preferred. IDSA's 2026 guidance advises against piperacillin-tazobactam for these infections even when the lab reports it as susceptible. For uncomplicated ESBL cystitis, options include nitrofurantoin or TMP-SMX when active. ESBL enzymes inactivate most penicillins and cephalosporins, including ceftriaxone, and aztreonam, but not carbapenems.
What is KPC, and how is carbapenem-resistant Klebsiella treated?
KPC stands for Klebsiella pneumoniae carbapenemase, an enzyme that destroys nearly all beta-lactams, including carbapenems, which makes the organism a carbapenem-resistant Enterobacterales (CRE). IDSA's 2026 guidance prefers ceftazidime-avibactam, imipenem-relebactam or meropenem-vaborbactam, with aztreonam-avibactam or cefiderocol as alternatives, guided by susceptibility testing. NDM, a metallo-beta-lactamase, is not blocked by those inhibitors, so IDSA prefers aztreonam-avibactam or cefiderocol; CDC reports NDM-producing CRE rose 461% in the US from 2019 to 2023.