You’re going to see “E. coli diarrhea” questions over and over in q-banks—not because the test writers lack imagination, but because the answer choices are designed to test your mechanism-level sorting. If you can explain why the correct pathotype fits and why each distractor doesn’t, you’ll stop getting trapped by buzzwords like “bloody diarrhea” or “travel.”
Tag: Microbiology > Gram-Negative Bacteria
The Clinical Vignette (Q-Bank Style)
A 24-year-old woman returns from a week-long trip to Mexico. Two days after returning, she develops profuse watery diarrhea, abdominal cramping, and nausea. She is afebrile. No blood or mucus is noted in the stool. Several friends who traveled with her have similar symptoms. Stool studies show no fecal leukocytes. Symptoms improve with oral rehydration.
Which E. coli pathotype is most likely responsible?
A. ETEC
B. EHEC
C. EPEC
D. EIEC
E. EAEC
Step 1: Pick the Correct Answer (and Prove It)
✅ Correct: A. Enterotoxigenic E. coli (ETEC)
Why it fits the vignette:
- Traveler’s diarrhea
- Watery, non-bloody diarrhea
- No fever (often mild/absent)
- No fecal leukocytes (noninflammatory)
- Multiple travelers affected (common exposure, contaminated food/water)
Core mechanism (must-know):
- Produces LT (heat-labile) and/or ST (heat-stable) enterotoxins
- Increases secretion → watery diarrhea:
- LT → activates adenylate cyclase → ↑ → ↑ Cl⁻ secretion
- ST → activates guanylate cyclase → ↑ → ↑ Cl⁻ secretion
High-yield memory hook:
ETEC = Traveler + Toxins → watery
Step 2: Systematically Destroy Each Distractor
The goal isn’t just to know the right answer—it’s to know why the other four are wrong in this stem.
B. EHEC (Enterohemorrhagic E. coli) — Why it’s wrong here
What EHEC usually looks like:
- Bloody diarrhea (often prominent)
- Severe abdominal pain
- Classically little/no fever
- Exposure clue: undercooked ground beef, unpasteurized juice, petting zoos
Key pathogenesis:
- Produces Shiga-like toxin (verotoxin)
- Inactivates 60S ribosomal subunit → inhibits protein synthesis
- Causes A/E lesions (attaching and effacing), like EPEC
High-yield complication:
- HUS (hemolytic uremic syndrome): triad
- Microangiopathic hemolytic anemia
- Thrombocytopenia
- Acute kidney injury
Why it doesn’t fit this vignette:
- Stem emphasizes watery diarrhea, no blood, and no fecal leukocytes
- Strong travel clustering points more toward ETEC than a Shiga toxin outbreak
USMLE trap to avoid:
EHEC can be afebrile, so fever doesn’t help much—blood does.
C. EPEC (Enteropathogenic E. coli) — Why it’s wrong here
What EPEC usually looks like:
- Watery diarrhea (non-bloody)
- Classically in infants/young children
- Can cause outbreaks in daycare settings
Key pathogenesis:
- Attaching and effacing (A/E) lesions
- Loss of microvilli → malabsorption → watery diarrhea
- No classic enterotoxins like ETEC
- No invasion (so typically noninflammatory)
Why it doesn’t fit this vignette:
- Patient is an adult traveler
- “Multiple travelers” + “Mexico” screams ETEC in q-bank logic
- EPEC is more “peds watery diarrhea” than “traveler’s diarrhea”
Fast sorter:
EPEC = Pediatric watery diarrhea + A/E lesions
D. EIEC (Enteroinvasive E. coli) — Why it’s wrong here
What EIEC usually looks like:
- Dysentery-like illness: fever, cramps, bloody diarrhea
- Inflammatory diarrhea → fecal leukocytes often present
Key pathogenesis:
- Invades intestinal mucosa (colon)
- Mechanistically resembles Shigella (and often presents similarly)
Why it doesn’t fit this vignette:
- Stem is afebrile, watery, and no fecal leukocytes
- That pattern argues against invasion/inflammation
USMLE pearl:
When you see fecal leukocytes, think invasive/inflammatory (EIEC, Shigella, Salmonella, Campylobacter, C. difficile, etc.).
E. EAEC (Enteroaggregative E. coli) — Why it’s wrong here (but worth knowing)
What EAEC usually looks like:
- Persistent watery diarrhea (often >14 days)
- Can be acute, but classically prolonged
- Important in:
- Children
- HIV/AIDS
- Travelers with persistent symptoms
Key pathogenesis:
- “Stacked-brick” adherence to intestinal mucosa
- Biofilm formation → persistent diarrhea (less “explosive” than ETEC in many stems)
Why it doesn’t fit this vignette:
- This is acute traveler’s diarrhea resolving with rehydration—not persistent illness
Fast sorter:
EAEC = Aggregative adherence + persistent watery diarrhea
One-Table Summary (What You Actually Need on Test Day)
| Pathotype | Typical Stool | Fever? | Mechanism | High-Yield Clues | Big Complication |
|---|---|---|---|---|---|
| ETEC | Watery | Usually no | LT → ↑, ST → ↑ | Traveler’s diarrhea, contaminated food/water | Dehydration |
| EHEC | Bloody | Often no | Shiga-like toxin → 60S inhibition; A/E lesions | Undercooked beef, unpasteurized juice | HUS |
| EPEC | Watery | Variable | A/E lesions, microvilli effacement | Infants, daycare | Dehydration |
| EIEC | Bloody, inflammatory | Yes common | Invasion of mucosa (Shigella-like) | Dysentery picture, fecal WBCs | Severe colitis |
| EAEC | Watery, persistent | Variable | Aggregative adherence, biofilm | Persistent diarrhea, kids/HIV | Chronic dehydration/weight loss |
“Answer Choice Matters” Checklist (How Q-Banks Try to Trick You)
Use these quick discriminators:
1) Watery vs Bloody
- Watery → ETEC, EPEC, EAEC
- Bloody → EHEC (toxin-mediated), EIEC (invasive)
2) Fecal leukocytes
- Present → inflammatory/invasive (think EIEC)
- Absent → secretory/toxin or adherence (think ETEC, often EHEC can be tricky—use blood + exposure)
3) Who is the patient?
- Adult traveler → ETEC
- Infant/daycare → EPEC
- Immunocompromised or persistent course → EAEC
4) Key exposure
- Undercooked beef/petting zoo → EHEC
Management Pearls (USMLE-Relevant)
- ETEC: Oral rehydration first-line; sometimes antibiotics shorten course (varies by guideline and severity).
- EHEC: Avoid antibiotics and antidiarrheals in suspected EHEC due to increased risk of HUS (classic exam teaching).
- Any severe dehydration: prioritize fluids/electrolytes.
Take-Home: The Mental Model That Stops Mistakes
If the stem screams traveler + watery + no leukocytes, your default should be ETEC unless there’s a strong competing clue (like persistent course → EAEC, infant/daycare → EPEC). If it’s bloody, ask: toxin (EHEC) or invasion (EIEC)—and use fever/fecal WBCs/exposures to decide.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
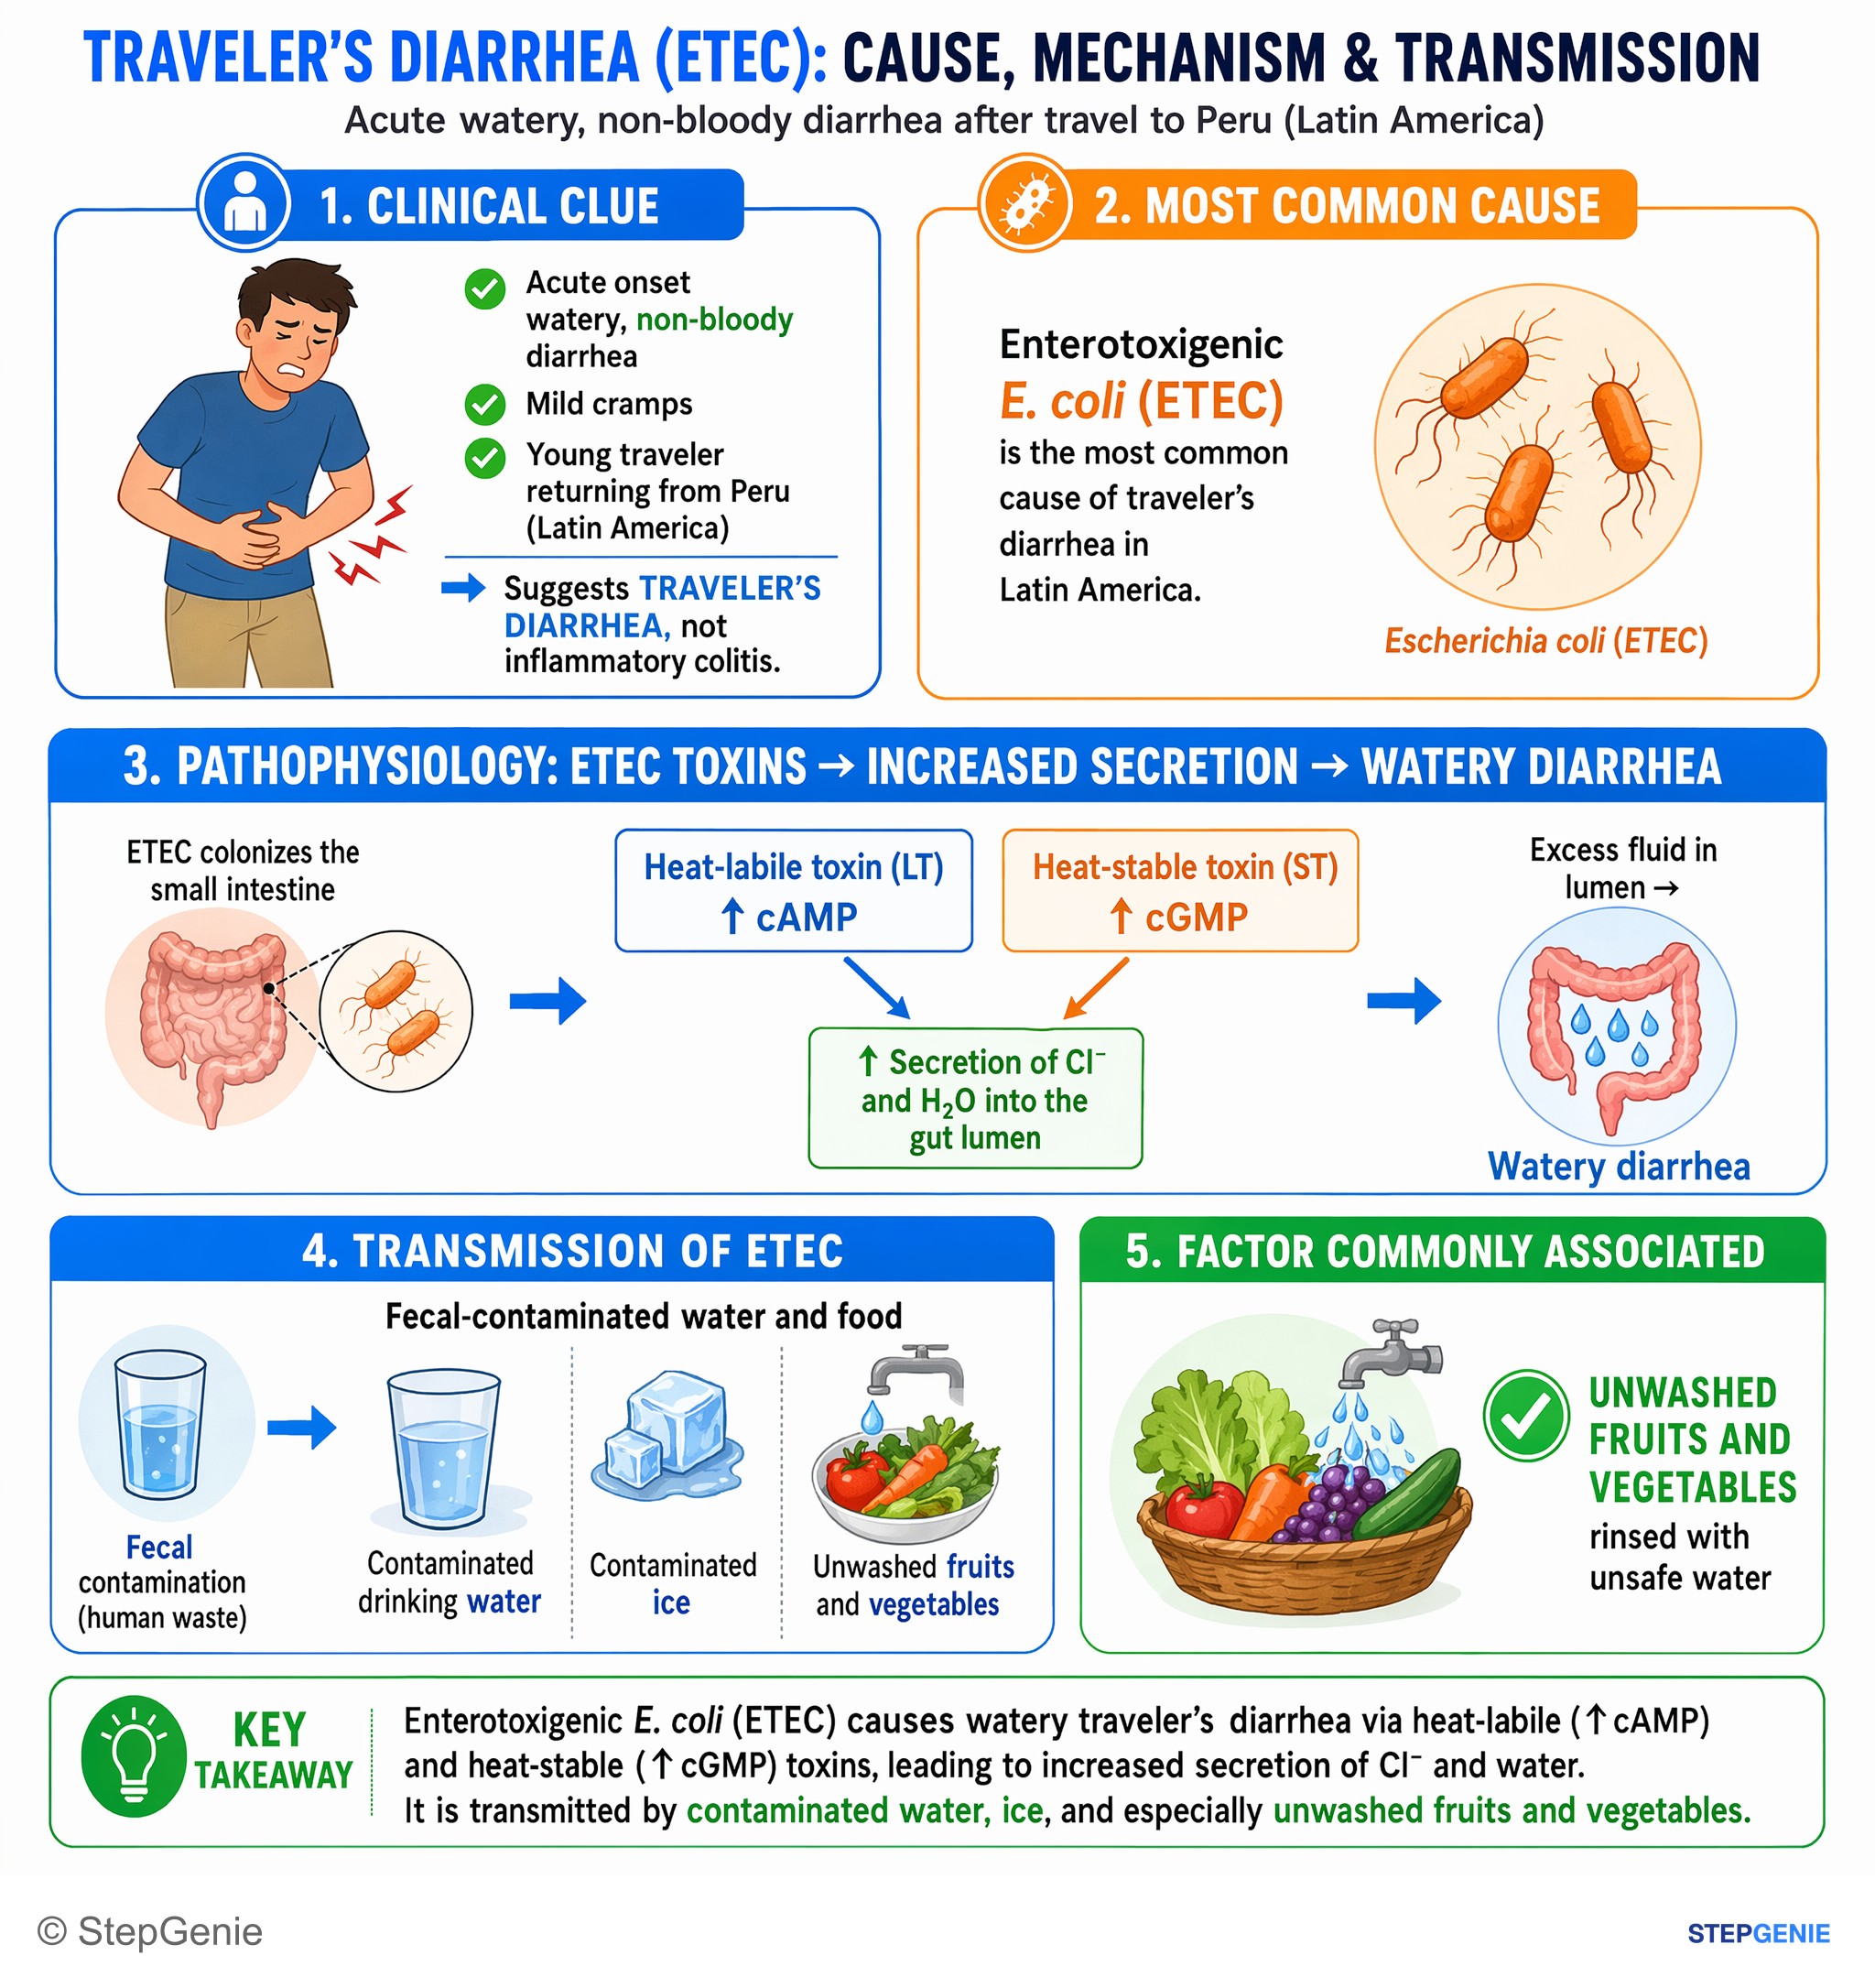
Enterotoxigenic E. coli (ETEC) causes watery traveler’s diarrhea via heat-labile/stable toxins; transmitted by contaminated water, ice…
USMLE Step 1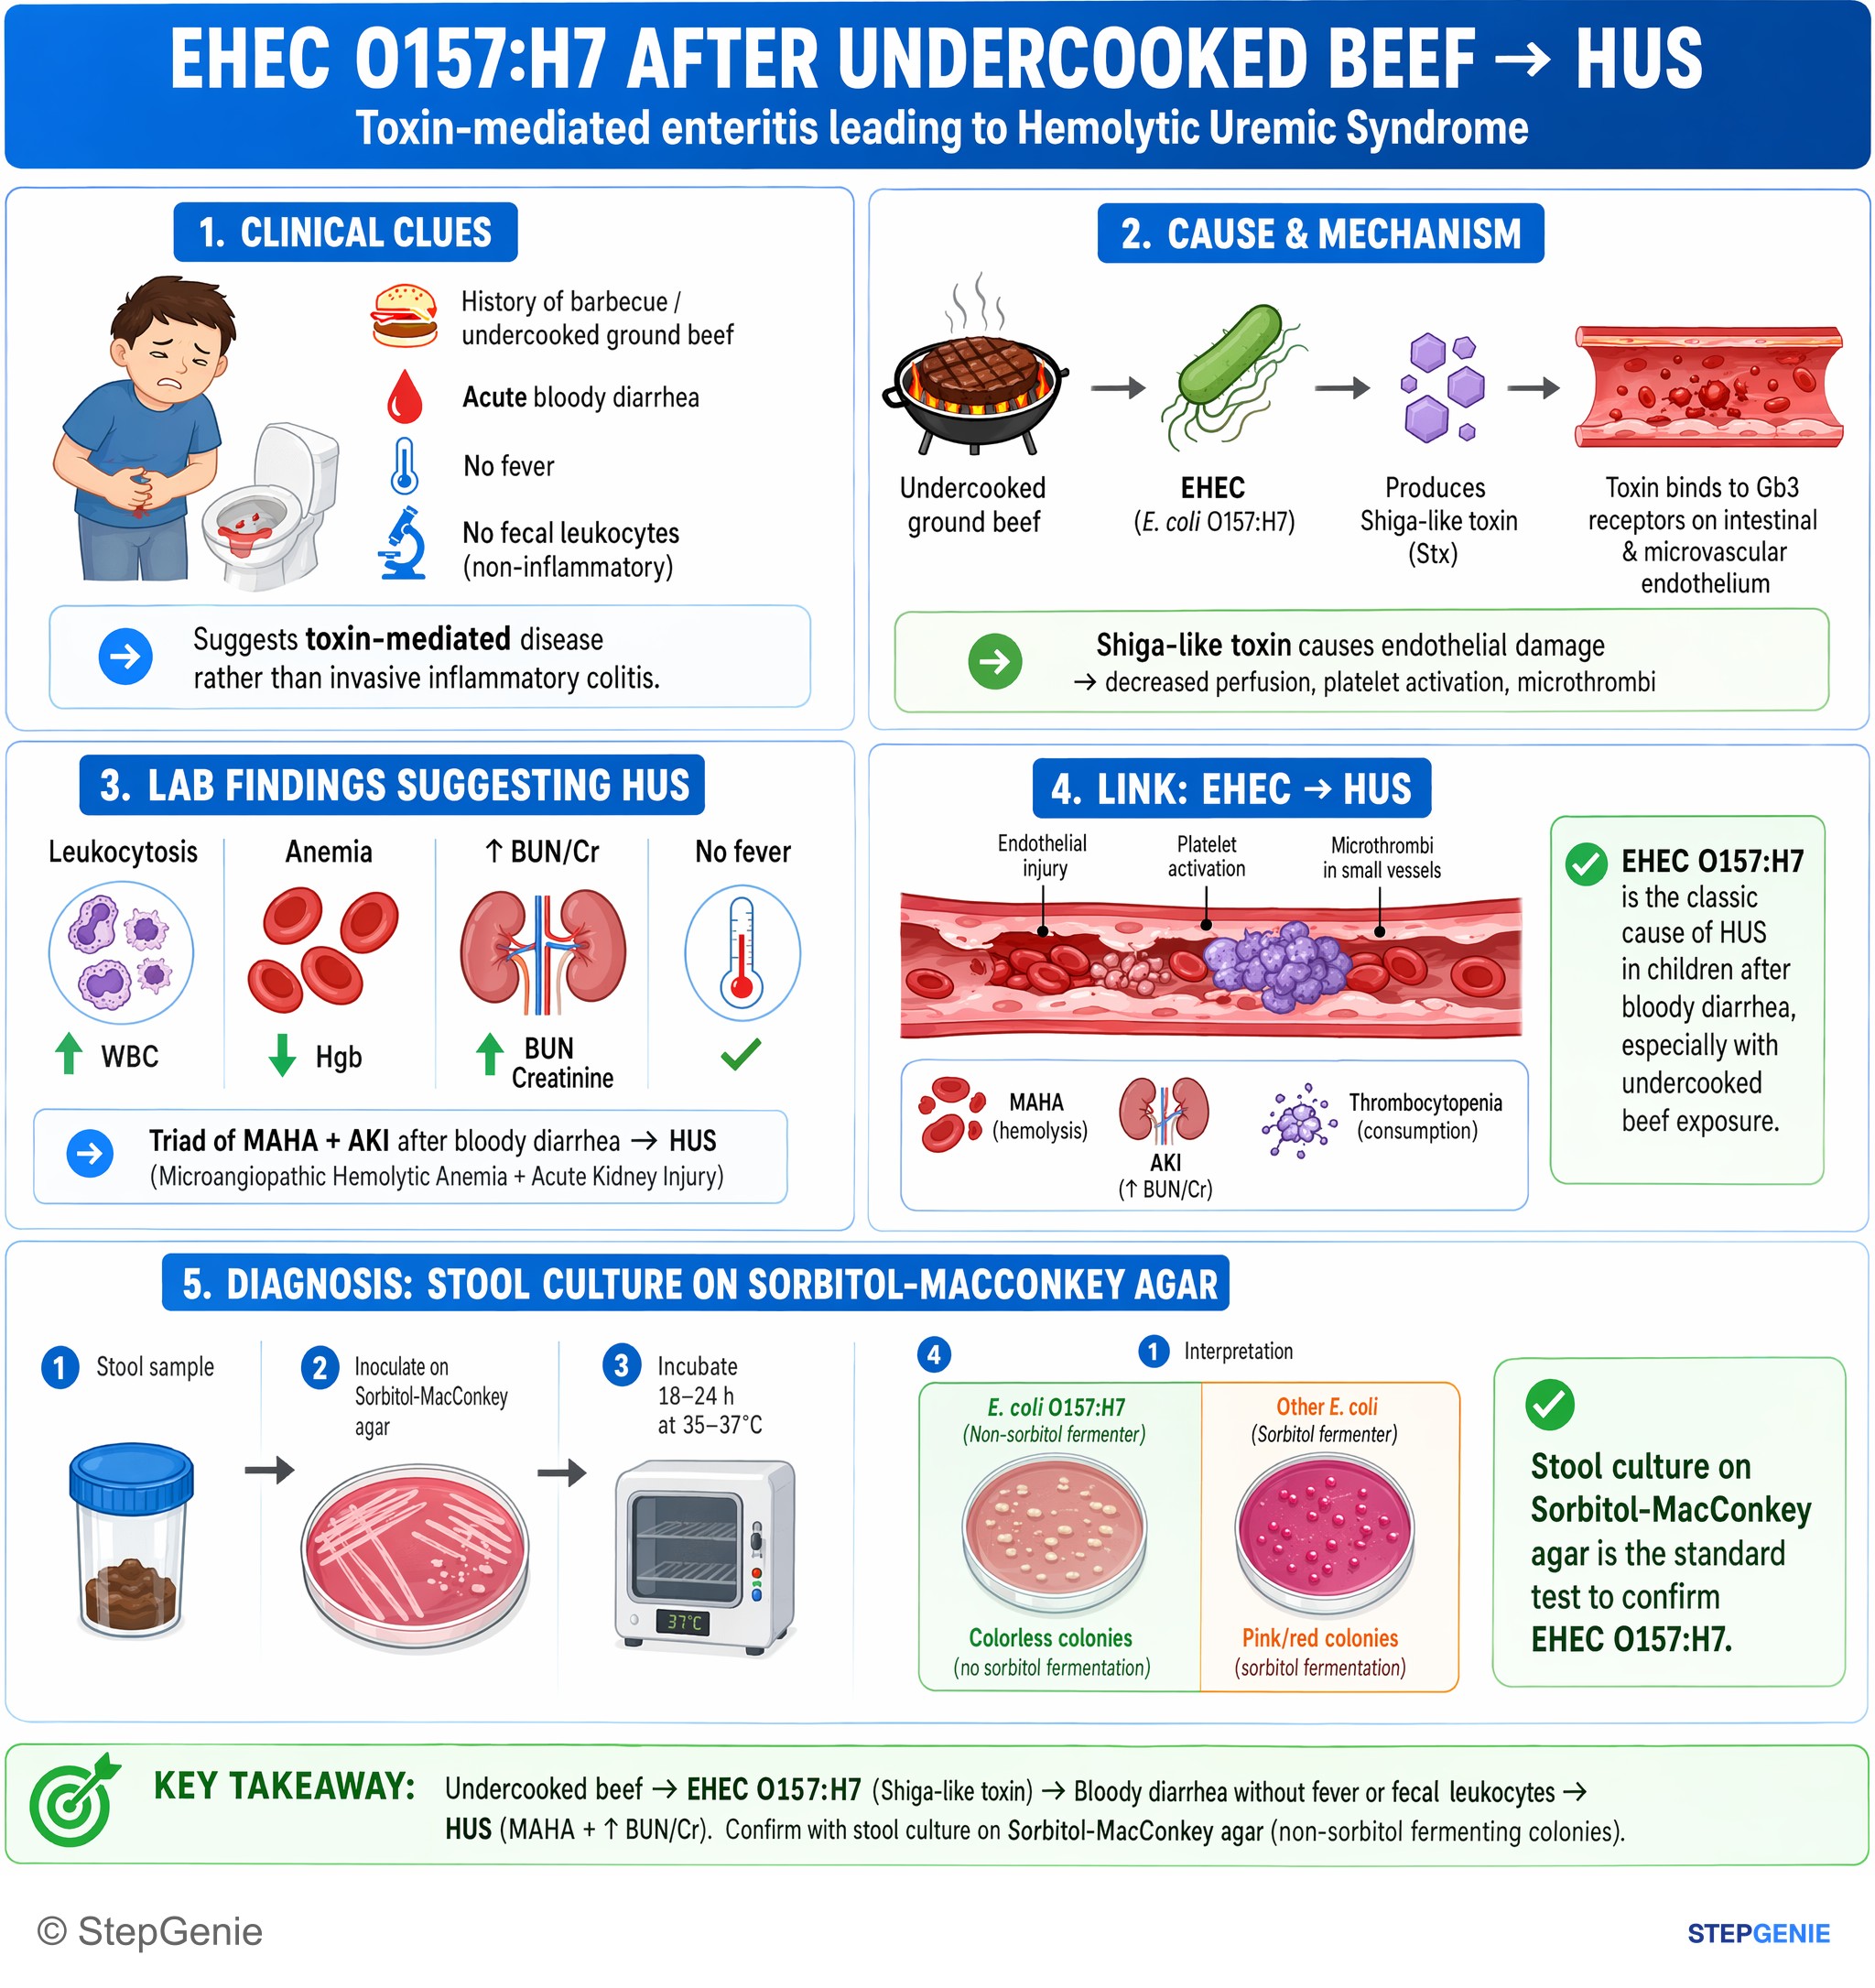
EHEC O157:H7 from undercooked beef → HUS (bloody diarrhea, anemia, ↑BUN/Cr, no fever, no fecal leukocytes); confirm with…
USMLE Step 1Frequently Asked Questions
What is the most likely E. coli cause of acute traveler’s diarrhea after a trip to Mexico?
Enterotoxigenic E. coli, or ETEC, is the most likely cause. It classically causes traveler’s diarrhea with profuse watery, non-bloody stools, little or no fever, and no fecal leukocytes. A shared exposure among multiple travelers also fits contaminated food or water. The illness is noninflammatory and often improves with oral rehydration, which matches this presentation.
Why does ETEC cause watery diarrhea without fecal leukocytes?
ETEC causes watery diarrhea because it produces enterotoxins rather than invading the intestinal mucosa. Its heat-labile toxin activates adenylate cyclase to increase cAMP, and its heat-stable toxin activates guanylate cyclase to increase cGMP. Both pathways increase chloride secretion, leading to secretory watery diarrhea. Because the process is noninflammatory, fecal leukocytes are typically absent.
How do you tell ETEC from EHEC on a question stem?
The key distinction is that ETEC usually causes watery traveler’s diarrhea, while EHEC usually causes bloody diarrhea with severe abdominal pain. ETEC is linked to contaminated food or water during travel and causes a noninflammatory illness. EHEC is associated with undercooked ground beef, unpasteurized juice, or petting zoos, and its major complication is hemolytic uremic syndrome.
How do you tell ETEC from EIEC when both are E. coli diarrhea choices?
ETEC causes a noninflammatory watery diarrhea, whereas EIEC causes an inflammatory dysentery-like illness. EIEC more often presents with fever, cramps, bloody diarrhea, and fecal leukocytes because it invades the intestinal mucosa. In contrast, an afebrile patient with watery stool and no fecal leukocytes points away from invasion and strongly toward ETEC.
When should you think of EPEC or EAEC instead of ETEC for watery diarrhea?
Think of EPEC when the patient is an infant or young child with watery non-bloody diarrhea, especially in a daycare outbreak. Think of EAEC when the watery diarrhea is persistent or prolonged, particularly in children, patients with HIV/AIDS, or travelers with ongoing symptoms. By contrast, acute traveler’s diarrhea after a trip is more typical of ETEC.