You just opened a Q-bank question that feels “too easy”… until you miss it because you didn’t slow down and read the clues. Clostridium perfringens is a classic USMLE organism because it shows up in multiple clinical contexts (gas gangrene, food poisoning, hemolysis), and the distractors are usually other Gram-positives that share just enough features to trick you. Let’s break it down the way you should on test day: one vignette, one correct answer, and every answer choice explained.
Tag: Microbiology > Gram-Positive Bacteria
The Clinical Vignette (Q-Bank Style)
A 42-year-old man is brought to the ED after a motorcycle crash. He has a deep laceration to his thigh that was contaminated with dirt. Twelve hours later, he has severe pain out of proportion to exam, swelling, and thin, brown, foul-smelling drainage from the wound. On palpation, there is crepitus. X-ray shows gas in the soft tissues. His temperature is 39.3°C (102.7°F). Gram stain from wound exudate shows large Gram-positive rods with few leukocytes.
Question: Which virulence factor is most responsible for this patient’s condition?
Correct Answer: Alpha toxin (lecithinase/phospholipase C)
Why the Correct Answer Is Correct: Clostridium perfringens in One Mental Snapshot
Key ID features
- Gram-positive rod
- Anaerobic
- Spore-forming (though spores are not always obvious on Gram stain)
- Classically associated with traumatic wound contamination → myonecrosis (gas gangrene)
Pathogenesis (the “why” behind the vignette)
- Alpha toxin = lecithinase (phospholipase C) damages cell membranes by cleaving phospholipids (e.g., lecithin).
- This causes:
- Myonecrosis (muscle destruction)
- Hemolysis (RBC membrane disruption) → can contribute to anemia, jaundice, hemoglobinuria in severe cases
- Tissue destruction and gas production (via anaerobic fermentation) → crepitus, radiolucent gas on imaging
The clues you should circle mentally
- Rapid onset after trauma (hours, not days)
- Pain out of proportion
- Crepitus + gas on imaging
- Foul-smelling discharge
- Large Gram-positive rods
- Few leukocytes can occur because toxin-mediated necrosis outpaces effective immune response
High-Yield: Lecithinase and the Nagler Reaction
A common Step-style lab tie-in:
| Test/Concept | What it shows | Why it matters |
|---|---|---|
| Egg yolk agar | Opalescence around colonies due to lecithinase activity | Suggests C. perfringens |
| Nagler reaction | Opalescence is inhibited by antitoxin on one side of the plate | Confirms alpha toxin effect |
Management Pearls (Step-Relevant)
You’re rarely asked for full management, but it’s fair game.
Gas gangrene treatment
- Urgent surgical debridement (source control is everything)
- High-dose penicillin + clindamycin
- Clindamycin helps suppress toxin production
- Hyperbaric oxygen may be used as adjunct in some cases
Now the Money Part: Why Every Distractor Matters
Below are common answer choices and how to eliminate them quickly.
Distractor 1: Tetanospasmin (blocks release of inhibitory neurotransmitters)
This points to: Clostridium tetani
Why it’s wrong here
- C. tetani causes spastic paralysis (trismus/lockjaw, risus sardonicus, opisthotonos).
- Mechanism: tetanospasmin cleaves SNARE proteins → prevents release of GABA and glycine from Renshaw cells.
- The vignette is myonecrosis + gas after wound contamination—not neuromuscular hyperactivity.
How Q-banks try to trick you
- Same genus (Clostridium), same “wound contamination” setup—but totally different clinical syndrome.
Distractor 2: Botulinum toxin (blocks ACh release at NMJ)
This points to: Clostridium botulinum
Why it’s wrong here
- C. botulinum causes flaccid paralysis (descending weakness, diplopia, dysphagia).
- Toxin blocks ACh release by cleaving SNARE proteins.
- No crepitus, no gas in tissues, no myonecrosis.
High-yield comparison
- Tetanus = spastic
- Botulism = flaccid
- Gas gangrene = necrosis + gas
Distractor 3: Enterotoxin that increases cAMP (profuse watery “rice-water” diarrhea)
This points to: Vibrio cholerae (not Gram-positive)
Why it’s wrong here
- Different organism (Gram-negative curved rod) and different presentation (watery diarrhea, dehydration).
- Your vignette is a wound infection with gas.
Test-taking move
- If the stem screams “soft tissue gas + trauma,” don’t get pulled into diarrhea toxin mechanisms.
Distractor 4: Cytolysin that forms pores causing β-hemolysis
This points to: Streptococcus pyogenes (Group A Strep)
Why it’s wrong here
- GAS can cause necrotizing fasciitis, which can involve severe pain and rapid progression.
- But GAS is Gram-positive cocci in chains, not large rods, and typically no prominent gas in soft tissue.
- Nec fasc: “dishwater” fluid and gray necrotic fascia can occur, but the classic “gas on x-ray + crepitus” leans strongly clostridial.
High-yield distinction
- Clostridial myonecrosis = muscle involvement + gas + anaerobe
- GAS nec fasc = fascia involvement + systemic toxicity; gas is not the defining clue
Distractor 5: Exotoxin that inactivates elongation factor-2 (EF-2)
This points to: Corynebacterium diphtheriae (or Pseudomonas exotoxin A—Gram-negative)
Why it’s wrong here
- Diphtheria: pseudomembrane, “bull neck,” myocarditis, neuropathy.
- Mechanism: ADP-ribosylation of EF-2 → decreased protein synthesis.
- Again: not a wound myonecrosis + gas picture.
USMLE hook
- EF-2 toxins: “Diphtheria” and “Pseudomonas” (ADP-ribosylation) — remember the mechanism, but match the syndrome.
Distractor 6: Ability to survive in oxygenated tissues via catalase
This points to: Staphylococcus aureus or other catalase-positive aerobes
Why it’s wrong here
- The case screams anaerobic (gas production) and Gram-positive rods, not catalase-positive cocci in clusters.
- S. aureus causes abscesses, cellulitis, osteomyelitis, endocarditis—not classic crepitus with soft tissue gas after trauma.
Distractor 7: Heat-stable toxin causing rapid-onset vomiting
This points to: Staphylococcus aureus food poisoning (preformed toxin)
Why it’s wrong here
- Different syndrome: abrupt vomiting within hours of ingestion.
- If the question were C. perfringens food poisoning, you’d expect:
- Watery diarrhea, abdominal cramps
- Usually 8–16 hours after eating
- Often reheated meats/gravy
- No vomiting as the dominant symptom
High-yield: C. perfringens GI disease
- Due to enterotoxin produced in the gut (not classically preformed like S. aureus).
- Typically self-limited.
Rapid-Fire High-Yield Table: Gram-Positive “Clues You Can’t Ignore”
| Bug | Morphology | Key toxin | Classic presentation |
|---|---|---|---|
| C. perfringens | G+ rod, anaerobe, spore-former | Alpha toxin (lecithinase) | Gas gangrene, myonecrosis, crepitus; late-onset diarrhea from meats |
| C. tetani | G+ rod, anaerobe, spore-former | Tetanospasmin (↓ GABA, glycine) | Spastic paralysis, lockjaw |
| C. botulinum | G+ rod, anaerobe, spore-former | Botulinum toxin (↓ ACh) | Flaccid paralysis, “floppy baby” |
| GAS (S. pyogenes) | G+ cocci in chains | Streptolysins, pyrogenic exotoxins | Strep throat, scarlet fever, nec fasc |
| S. aureus | G+ cocci in clusters | Many (TSST-1, enterotoxin, etc.) | Abscesses, pneumonia post-flu, endocarditis |
How to Lock This In for Test Day
When you see:
- Trauma + contamination
- Rapid progression
- Crepitus / gas on imaging
- Large Gram-positive rods
You should immediately think:
Clostridium perfringens → alpha toxin (lecithinase) → myonecrosis + hemolysis + gas
Then use distractors to prove to yourself why it’s not tetanus (spastic), botulism (flaccid), GAS (cocci/less gas), or toxin-mediated diarrhea syndromes.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
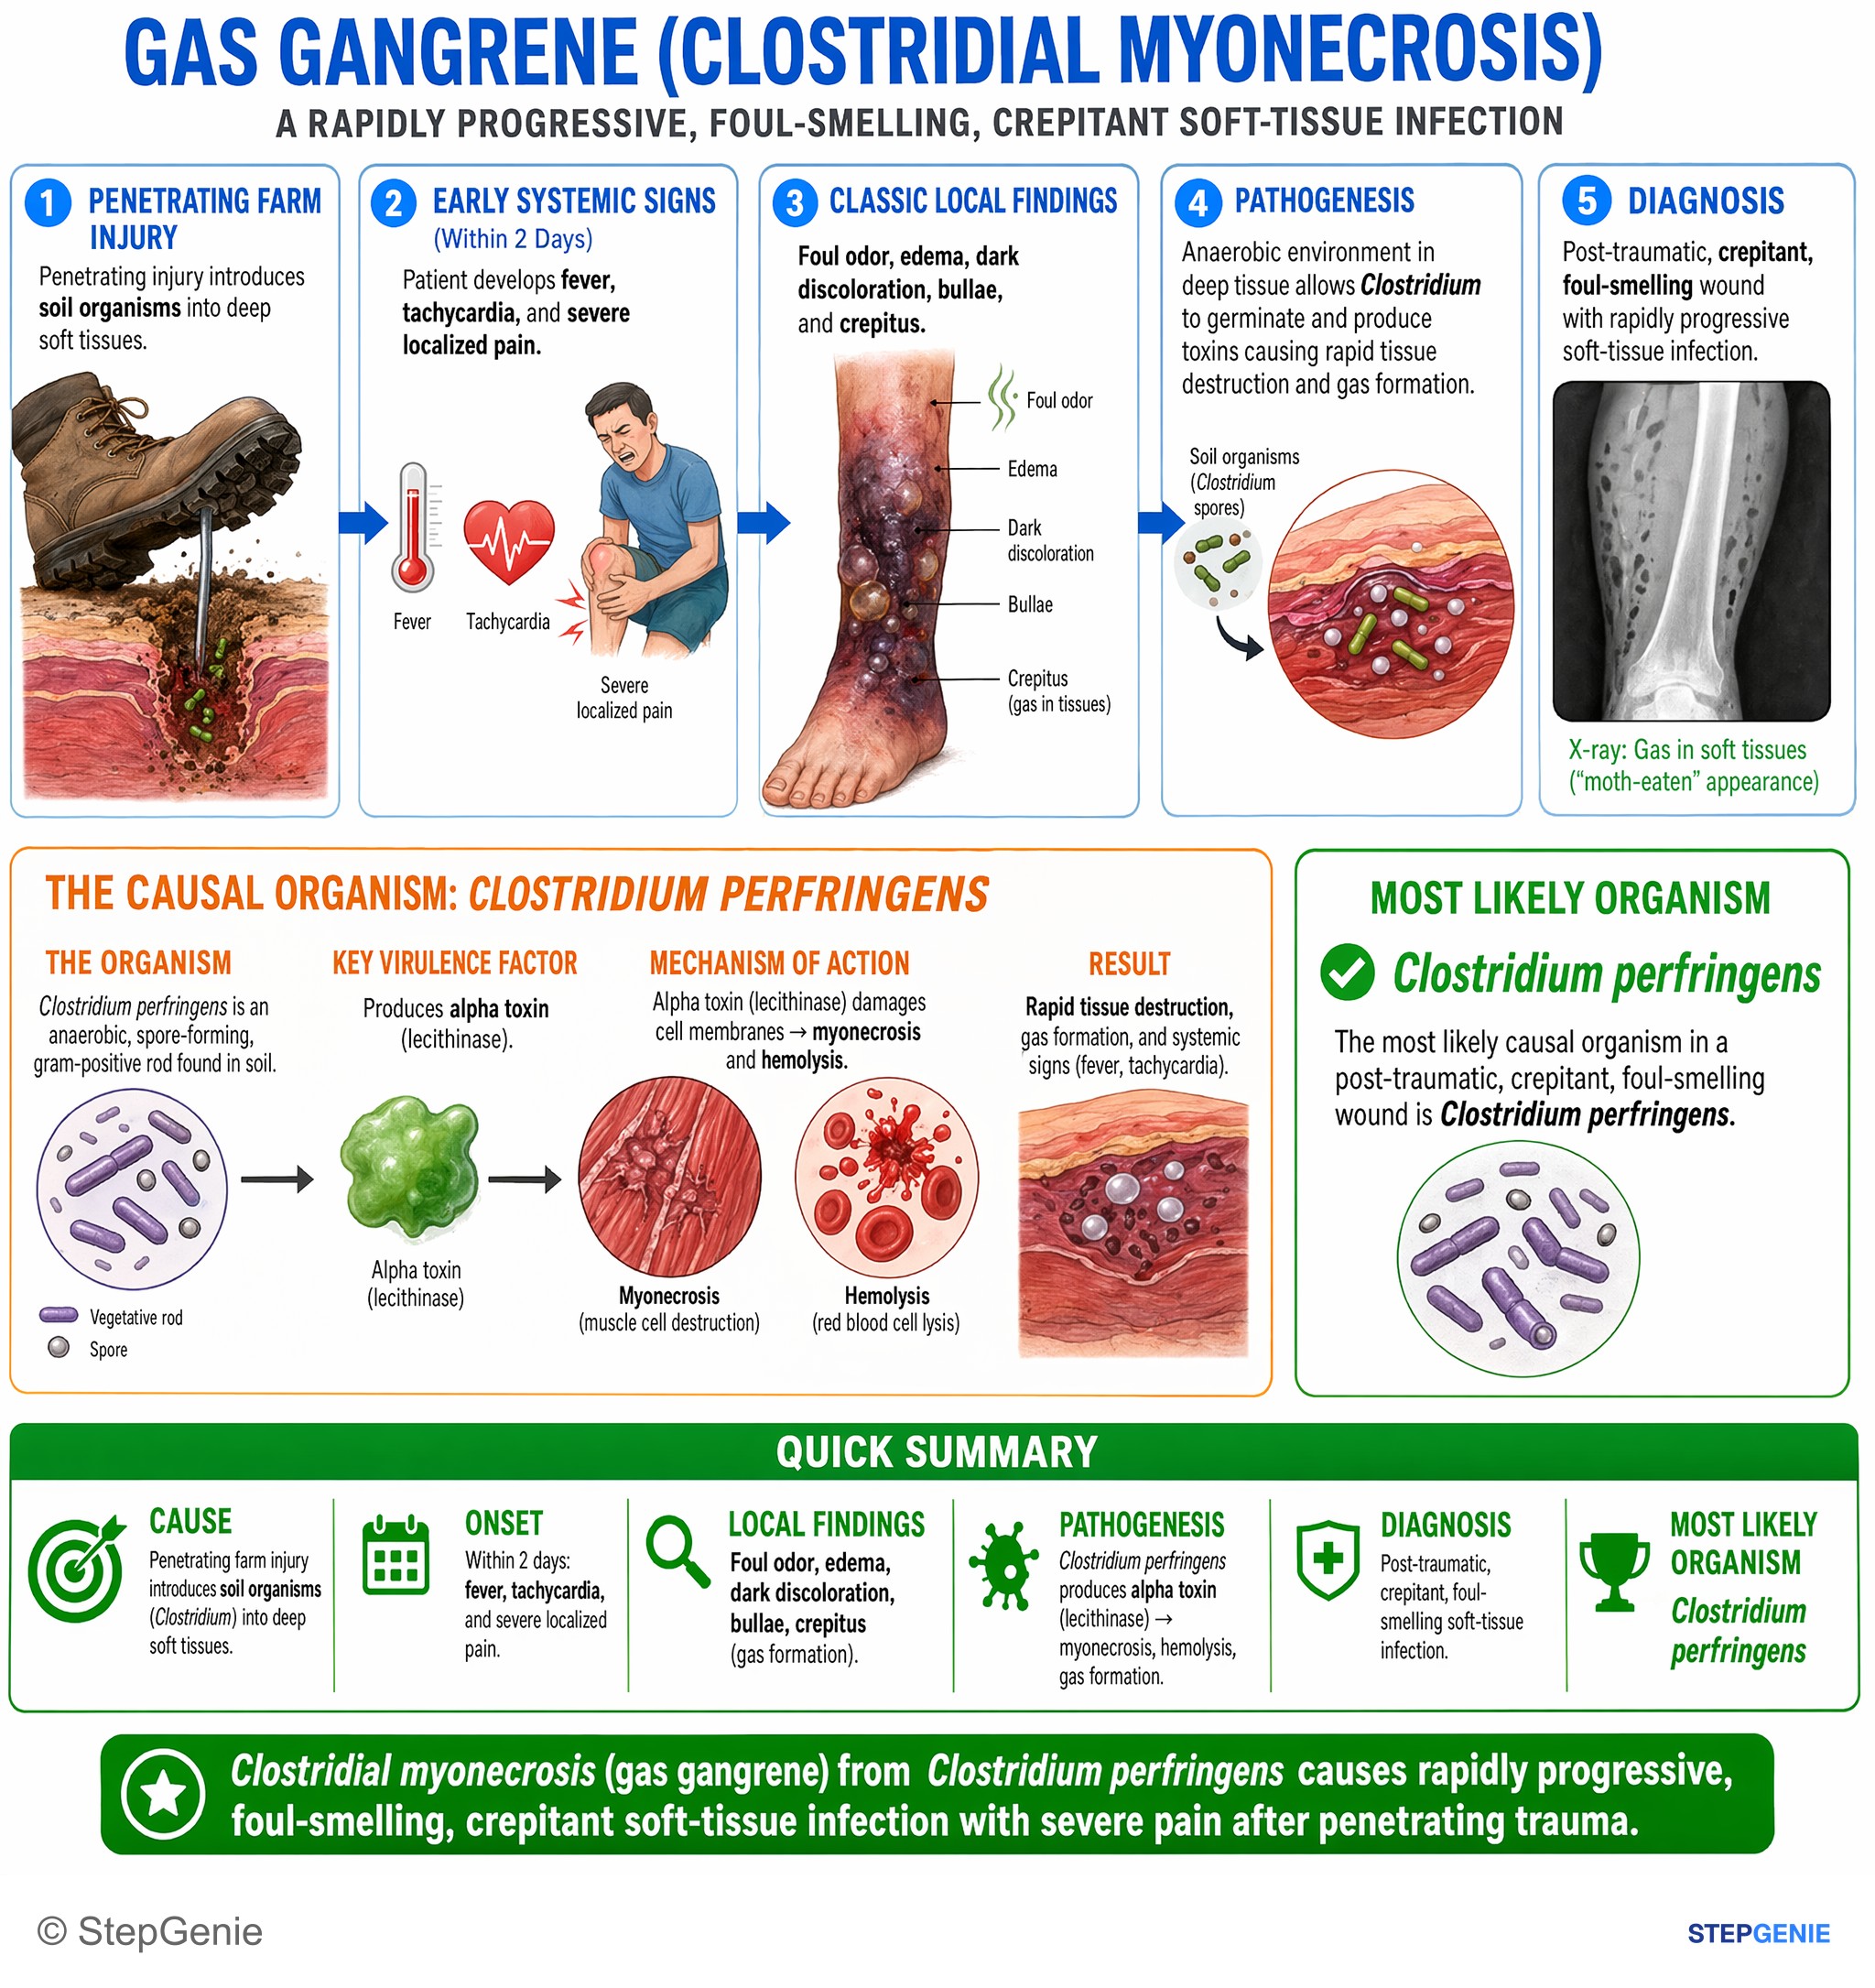
Clostridial myonecrosis (gas gangrene) from Clostridium perfringens causes rapidly progressive, foul-smelling, crepitant soft-tissue…
USMLE Step 1Frequently Asked Questions
What virulence factor causes Clostridium perfringens gas gangrene?
The key virulence factor is alpha toxin, also called lecithinase or phospholipase C. It cleaves phospholipids in cell membranes, which leads to myonecrosis, hemolysis, and major tissue destruction. In a trauma patient with rapid worsening pain, crepitus, foul-smelling drainage, gas in soft tissues, and large Gram-positive rods on stain, this toxin explains the syndrome.
How do you recognize Clostridium perfringens in a wound infection vignette?
You recognize Clostridium perfringens by the combination of traumatic wound contamination and rapid-onset myonecrosis with gas production. High-yield clues include severe pain out of proportion to exam, swelling, thin brown foul-smelling drainage, crepitus, gas on imaging, and large Gram-positive rods on Gram stain. Few leukocytes can also appear because toxin-mediated necrosis outpaces an effective immune response.
How do you tell Clostridium perfringens apart from tetanus or botulism on an exam?
Clostridium perfringens causes necrosis and gas in soft tissues, not paralysis. Tetanus presents with spastic paralysis such as trismus, risus sardonicus, and opisthotonos from blocked release of GABA and glycine, while botulism causes flaccid paralysis with descending weakness, diplopia, and dysphagia from blocked acetylcholine release. Crepitus, gas on imaging, and myonecrosis point instead to C. perfringens.
How do you distinguish Clostridium perfringens from group A strep necrotizing fasciitis?
Clostridium perfringens is favored when the stem emphasizes muscle involvement, anaerobic infection, and gas production. It appears as large Gram-positive rods and classically causes clostridial myonecrosis with crepitus and gas on x-ray. Group A strep necrotizing fasciitis involves Gram-positive cocci in chains, affects fascia rather than muscle, and gas is not the defining clue even though severe pain and rapid progression can overlap.
What is the treatment for Clostridium perfringens gas gangrene?
Treatment requires urgent surgical debridement plus high-dose penicillin and clindamycin. Surgical source control is essential because this is a rapidly destructive soft tissue infection. Clindamycin is useful because it helps suppress toxin production, and hyperbaric oxygen may be used as an adjunct in some cases.