Salmonella questions love to hide behind “just another gastroenteritis” stem—until you miss the one detail that screams typhoid fever. Here’s a fast, shareable memory palace to separate Salmonella typhi from non-typhi Salmonella (aka non-typhoidal Salmonella, NTS) with USMLE-level precision.
The Setup: Your “Salmonella House” Memory Palace
Picture one house with two rooms:
- The “Typhi Throne Room” = Salmonella typhi
- The “Gastro Kitchen” = Non-typhi Salmonella (NTS)
If the stem’s clues “belong” in the throne room → think typhoid fever. If they belong in the kitchen → think gastroenteritis.
Room 1: The Typhi Throne Room (S. typhi)
Visual mnemonic (place these objects in the room)
- A crown with a shield labeled “Vi” (the Vi capsule)
- A travel suitcase stamped “South Asia” (endemic/travel exposure)
- A rose bouquet on the royal robe (rose spots)
- A slow-dripping clock (insidious onset; systemic illness)
- A guard station in the gallbladder (carrier state: colonizes gallbladder)
One-liner (what to say to yourself)
“Typhi wears a Vi crown and causes systemic typhoid fever with rose spots and possible gallbladder carriage.”
High-yield USMLE facts
- Organism basics
- Gram-negative rod, motile, facultative intracellular
- H2S producer (classically on triple sugar iron agar)
- Typically lactose non-fermenter (grouped with other enteric pathogens)
- Pathogenesis & clinical
- Human-only reservoir
- Invades intestinal mucosa → survives in macrophages → disseminates hematogenously
- Classic findings: stepwise fevers, relative bradycardia (Faget sign), abdominal pain, hepatosplenomegaly
- Rose spots: faint salmon-colored macules on trunk
- Constipation can be early, diarrhea can occur later (“pea soup”)
- Complications
- Peyer patch necrosis → intestinal hemorrhage/perforation (late)
- Chronic carrier state in gallbladder, especially with gallstones
- Diagnosis (test-taking gold)
- Blood cultures early
- Stool cultures later
- Treatment & prevention (Step 2 flavor)
- Treat: often ceftriaxone or azithromycin (resistance patterns matter; fluoroquinolone resistance is common in many regions)
- Vaccines exist (not perfect): oral live-attenuated and IM Vi polysaccharide
Room 2: The Gastro Kitchen (Non-typhi Salmonella / NTS)
Visual mnemonic (place these objects in the kitchen)
- Undercooked eggs spilling onto the counter (classic association: eggs/poultry)
- A pet turtle in the sink (reptile exposure)
- A sign that says “Inflammation inside” (invasive inflammatory diarrhea)
- A baby bottle and a chemotherapy badge on the table (risk groups for bacteremia)
One-liner
“Non-typhi Salmonella is a food/reptile-associated inflammatory diarrhea that can seed the bloodstream in high-risk patients.”
High-yield USMLE facts
- Typical presentation
- Acute gastroenteritis: fever, abdominal cramps, watery ± bloody diarrhea
- Mechanism: mucosal invasion → neutrophils in stool (inflammatory)
- Classic exposures
- Poultry, eggs
- Reptiles (turtles/iguanas/snakes)
- Big complication to remember
- Bacteremia in:
- Infants
- Elderly
- Immunocompromised (including HIV, chemo, transplant)
- Sickle cell disease
- Can cause osteomyelitis (especially in sickle cell—yes, Salmonella and Staph aureus are both fair game)
- Bacteremia in:
- Treatment nuance
- Uncomplicated gastroenteritis is often supportive
- Antibiotics considered for severe disease or high-risk bacteremia patients (choice depends on susceptibilities; commonly ceftriaxone or ciprofloxacin/azithro depending on region)
Rapid-Fire Differentiator Table (Exam Mode)
| Feature | Salmonella typhi (Typhoid fever) | Non-typhi Salmonella (NTS) |
|---|---|---|
| Reservoir | Humans only | Animals (poultry, reptiles) + humans |
| Classic exposure | Travel/endemic regions, contaminated water/food | Eggs/poultry, reptiles |
| Main syndrome | Systemic febrile illness | Gastroenteritis |
| Skin finding | Rose spots | Not typical |
| Stool pattern | May start with constipation; later diarrhea | Inflammatory diarrhea (± bloody) |
| Special virulence | Vi capsule | No Vi capsule emphasis |
| Major complication | Intestinal perforation (Peyer patches), carrier state | Bacteremia, osteomyelitis (sickle cell) |
| Cultures | Blood early, stool later | Stool (often), blood if severe/high-risk |
The “Doorway Rule” (30-second recall)
Before you answer, stand at the doorway of the house and ask:
- Systemic travel fever + rose spots? → walk into the Throne Room → S. typhi
- Eggs/poultry or reptiles + acute diarrhea? → walk into the Kitchen → Non-typhi Salmonella
- Sickle cell + bone pain? → kitchen complication → NTS osteomyelitis
- Gallbladder carriage? → throne room → S. typhi
Mini Self-Check (USMLE-style micro-vignettes)
- “Returned from India, stepwise fever, relative bradycardia, rose spots.” → S. typhi
- “Toddler with pet turtle, fever and diarrhea.” → NTS
- “Sickle cell patient with osteomyelitis after diarrheal illness.” → NTS
- “Chronic carrier with gallstones and recurrent shedding.” → S. typhi
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
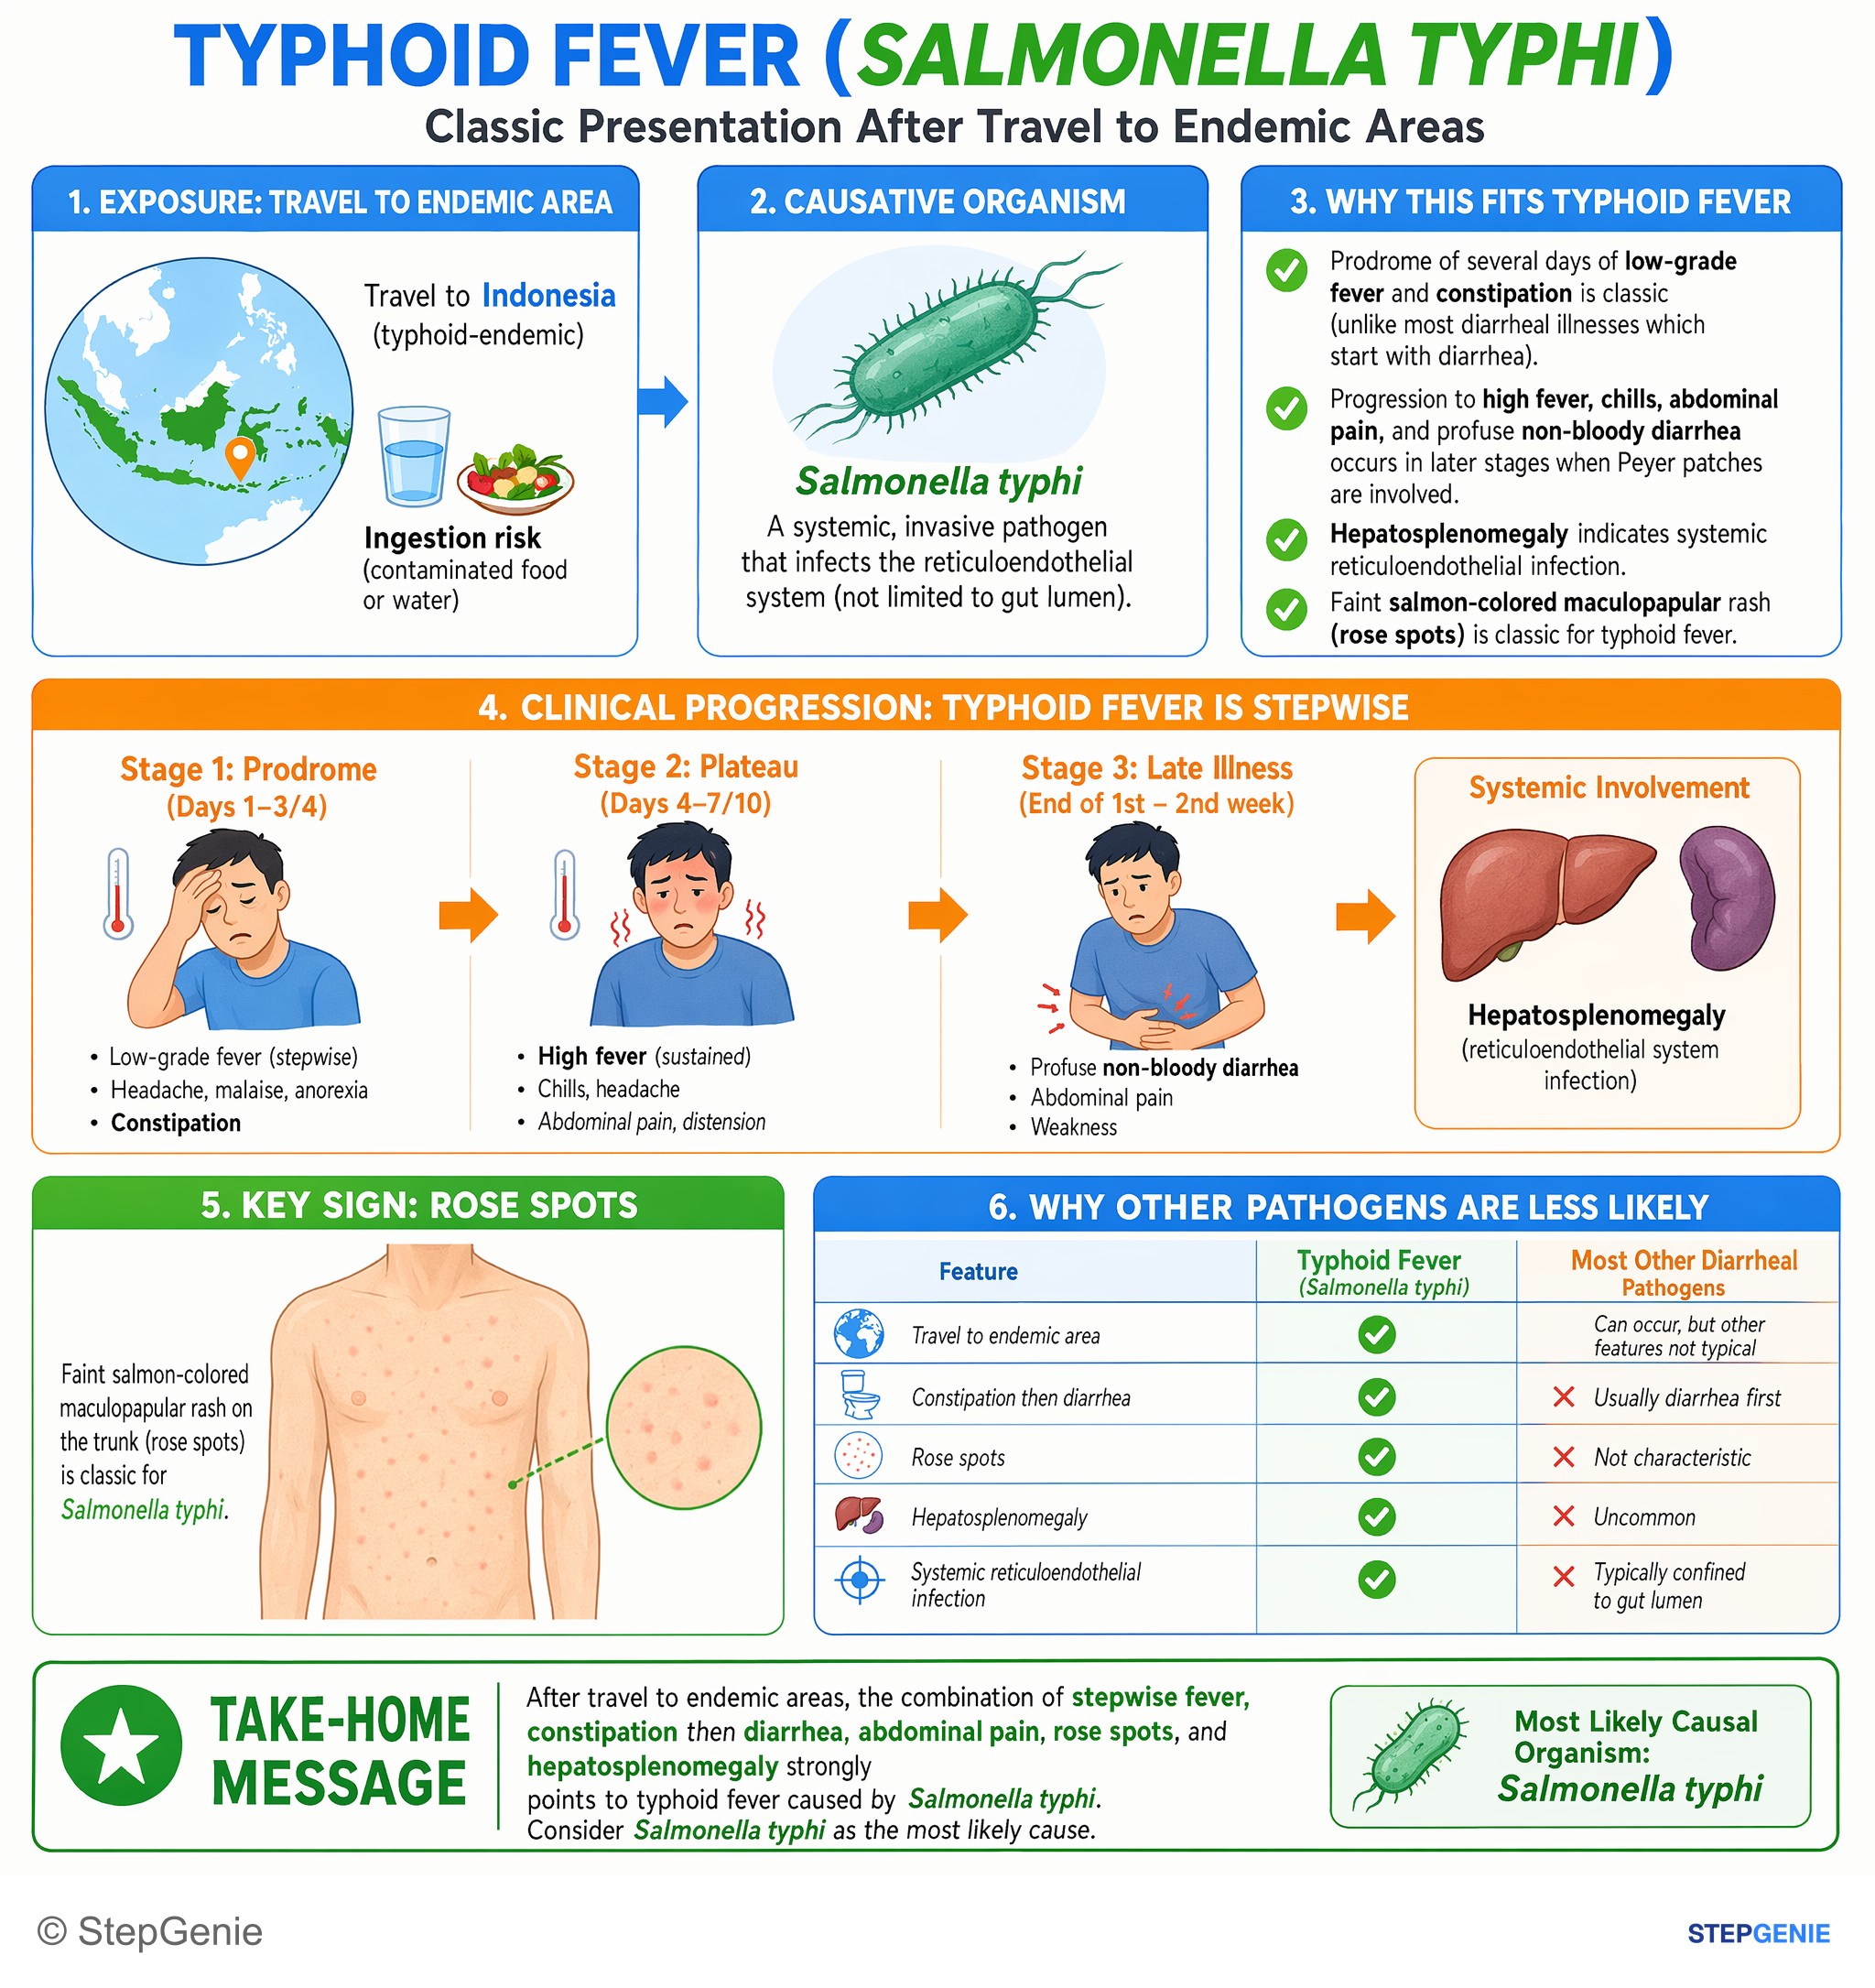
Typhoid fever (Salmonella typhi) causes stepwise fever, abdominal pain, constipation then diarrhea, rose spots, and hepatosplenomegaly…
USMLE Step 1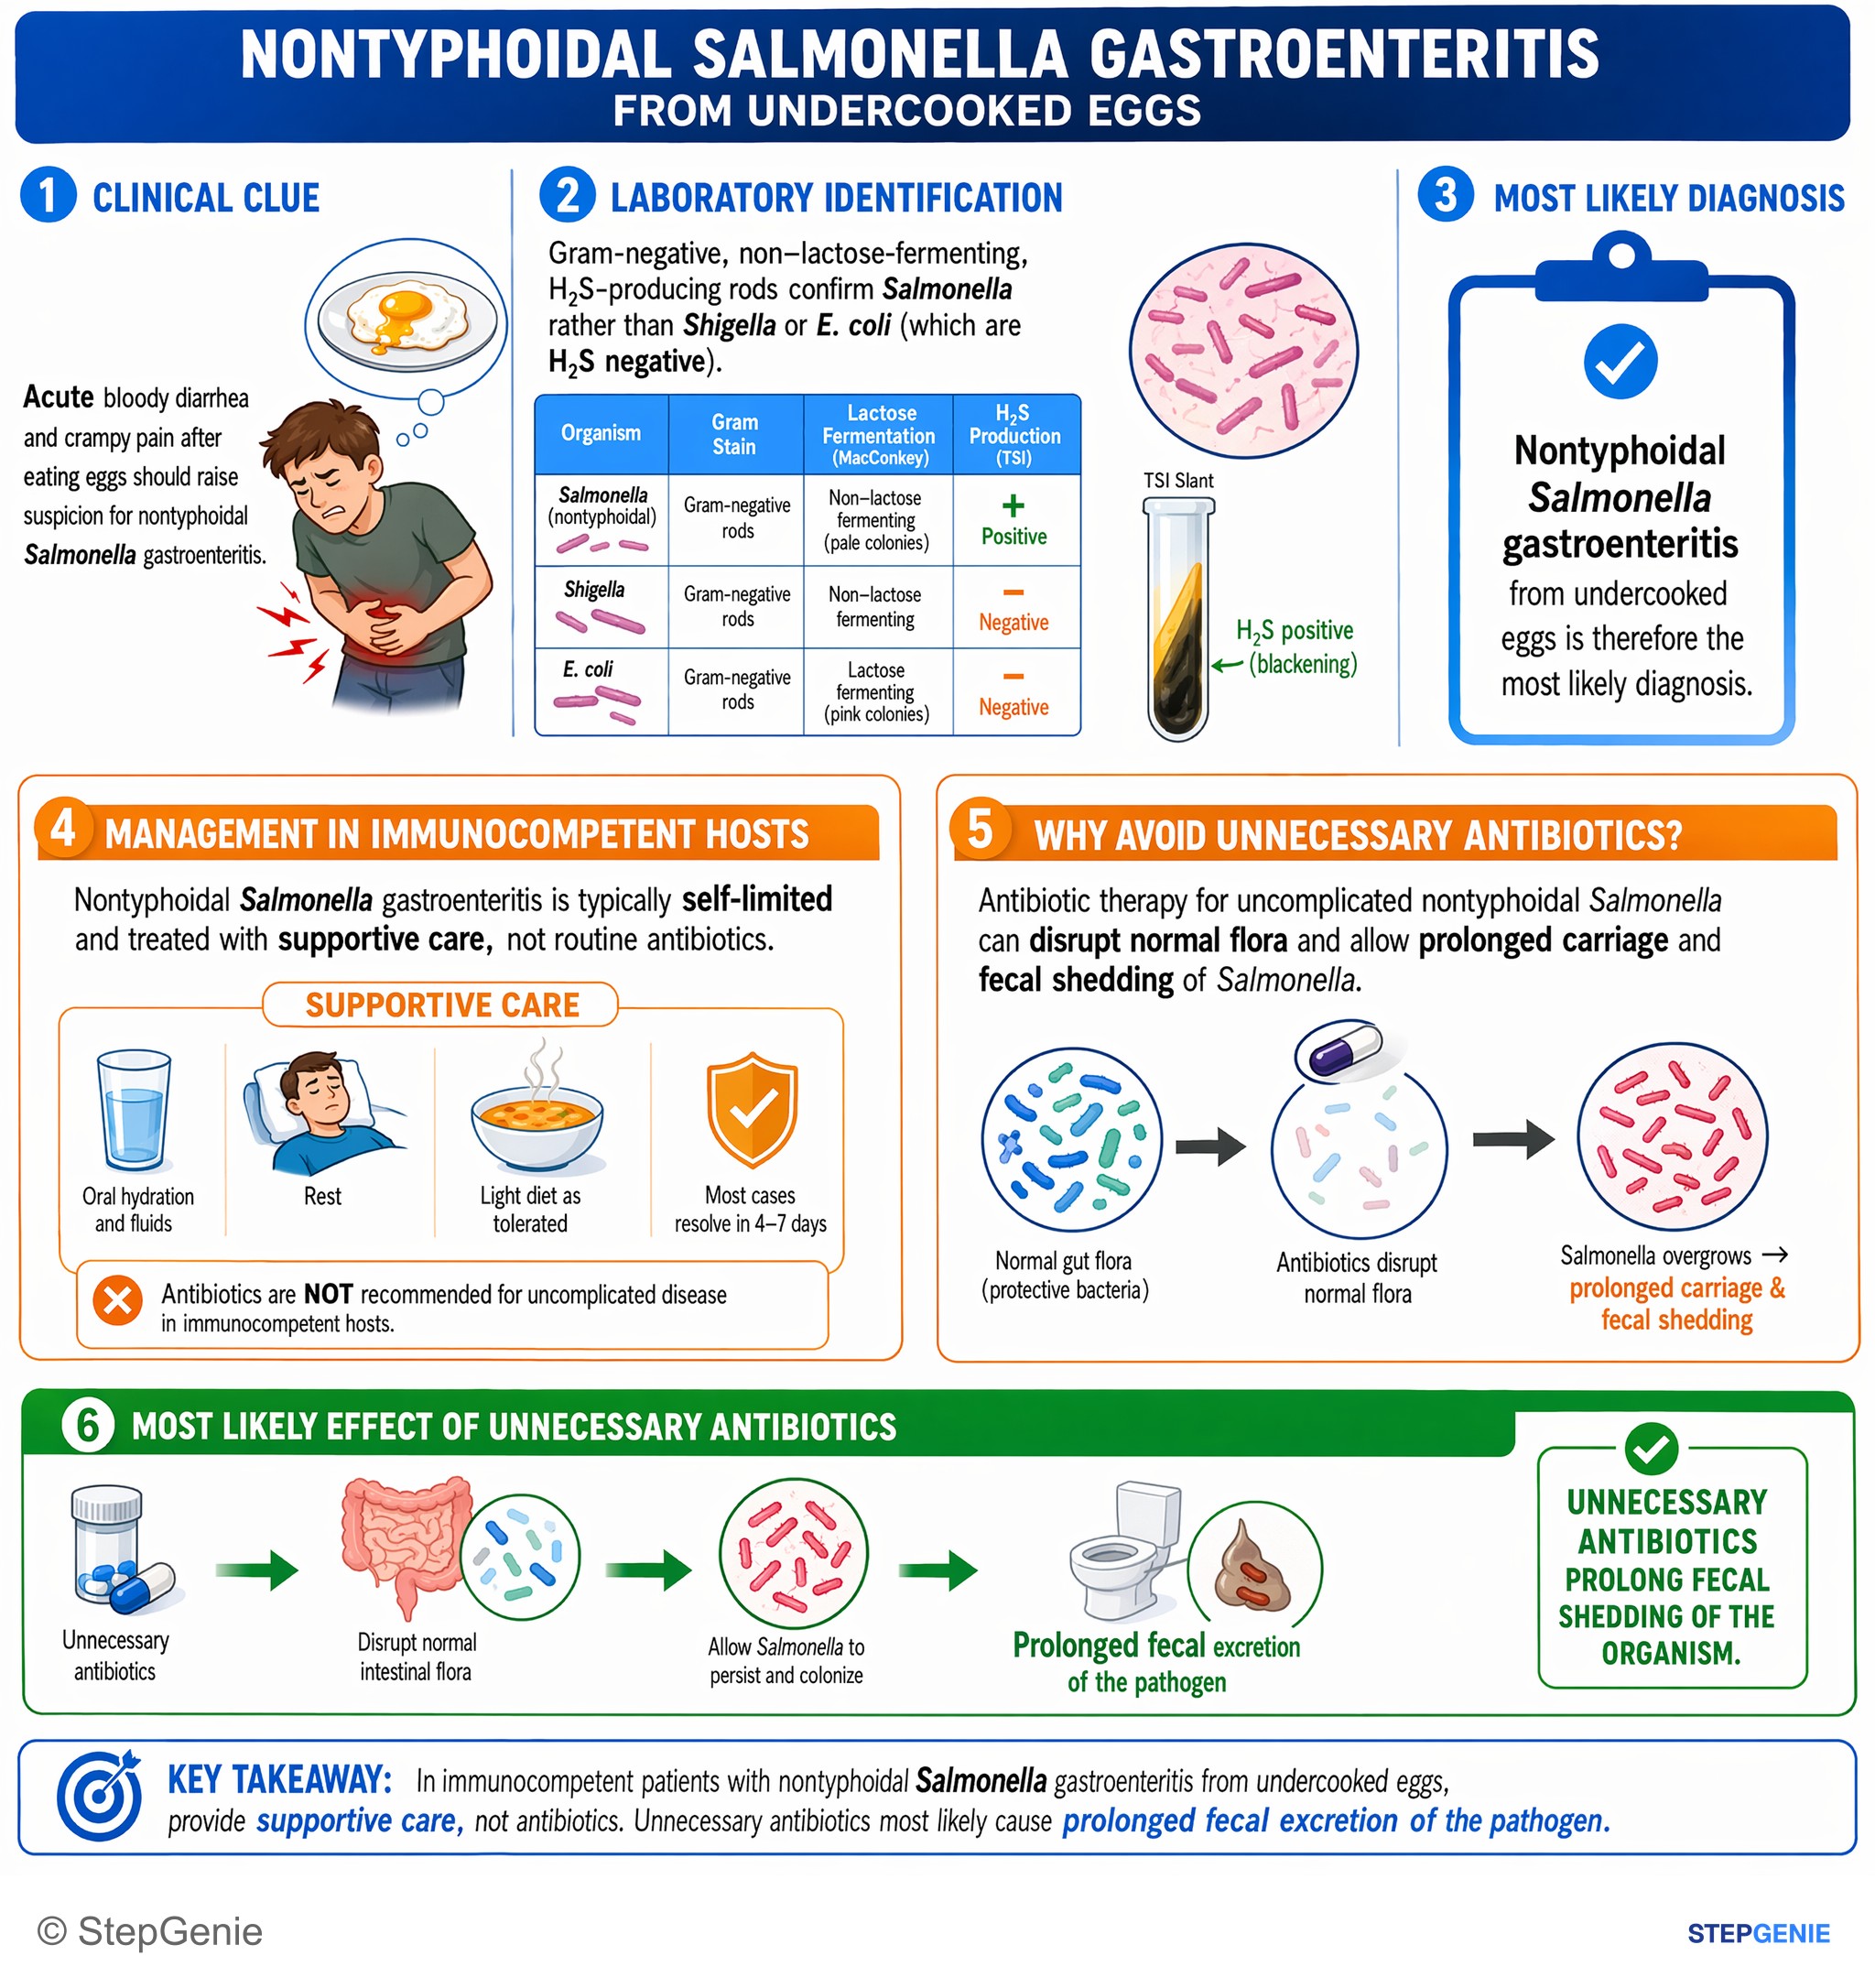
Nontyphoidal Salmonella gastroenteritis from undercooked eggs; unnecessary antibiotics prolong fecal shedding of the organism.
USMLE Step 1Frequently Asked Questions
How do you tell Salmonella typhi from non-typhi Salmonella on a USMLE-style question?
The quickest way is to separate systemic typhoid fever from food- or reptile-associated gastroenteritis. Salmonella typhi points to travel or endemic exposure, stepwise fevers, relative bradycardia, rose spots, and possible gallbladder carriage. Non-typhi Salmonella points to eggs, poultry, or reptiles plus acute inflammatory diarrhea, and it is the form more associated with bacteremia in high-risk patients and osteomyelitis in sickle cell disease.
Why does Salmonella typhi cause a systemic illness instead of just diarrhea?
Salmonella typhi causes a systemic illness because it invades the intestinal mucosa, survives in macrophages, and then disseminates hematogenously. That pattern produces typhoid fever rather than a limited gastroenteritis picture. Classic clues include stepwise fevers, relative bradycardia, abdominal pain, hepatosplenomegaly, and rose spots, with constipation sometimes appearing early before diarrhea develops later.
What are the classic exposure clues for non-typhi Salmonella?
The classic exposure clues for non-typhi Salmonella are undercooked eggs, poultry, and reptiles such as turtles. These exposures fit its usual presentation of acute gastroenteritis with fever, abdominal cramps, and watery or sometimes bloody diarrhea. On exams, a toddler with a pet turtle or a patient with recent egg or poultry exposure and inflammatory diarrhea should make non-typhi Salmonella rise to the top of the differential.
What are the key complications of Salmonella typhi vs non-typhi Salmonella?
Salmonella typhi is classically linked to intestinal hemorrhage or perforation from Peyer patch necrosis and to a chronic carrier state in the gallbladder, especially with gallstones. Non-typhi Salmonella is more associated with bacteremia in infants, the elderly, immunocompromised patients, and people with sickle cell disease. It can also cause osteomyelitis, particularly in sickle cell patients.
What is the usual diagnosis and treatment approach for Salmonella typhi vs non-typhi Salmonella?
For Salmonella typhi, blood cultures are most useful early, while stool cultures become more helpful later. Treatment commonly includes ceftriaxone or azithromycin, with resistance patterns mattering. For non-typhi Salmonella, stool testing is often used, and blood cultures are considered if disease is severe or the patient is high risk. Uncomplicated gastroenteritis is often treated supportively, while antibiotics are reserved for severe disease or high-risk bacteremia patients.