Streptococcus agalactiae (group B strep, GBS) is a beta-hemolytic, catalase-negative, gram-positive coccus in chains that is bacitracin resistant, PYR negative, and CAMP and hippurate positive. It colonizes the gut and vagina of 10-30% of pregnant women and is the leading cause of newborn infection: early-onset disease (first week, mostly in the first 12-48 hours) is sepsis and pneumonia, and late-onset disease (7-89 days) is bacteremia and meningitis. ACOG screens every pregnant woman with a vaginal-rectal swab at 36 0/7-37 6/7 weeks and gives IV penicillin during labor to carriers. That prevents early-onset disease but not late-onset disease.
Lab ID: how GBS differs from the other streptococci
| GBS (S. agalactiae) | GAS (S. pyogenes) | |
|---|---|---|
| Gram stain, catalase | Gram-positive cocci in chains, catalase negative | Same |
| Hemolysis | Beta (narrow zone; about 5-6% of screening isolates nonhemolytic) | Beta |
| Lancefield group | B | A |
| Bacitracin | Resistant | Sensitive |
| PYR | Negative | Positive |
| CAMP test | Positive | Negative |
| Extras | Hippurate positive; orange-red pigment on some media |
The other two classic gram-positive cocci separate on different tests: alpha-hemolytic S. pneumoniae is optochin sensitive and bile soluble, and group D Enterococcus hydrolyzes bile esculin and is PYR positive (UKHSA).
- Memory hook: "B-BRAS": group B is Bacitracin Resistant, group A is Sensitive. GBS goes to CAMP and hydrolyzes hippurate.
- CAMP test: GBS secretes CAMP factor (the cfb gene, a common PCR target), which enhances the beta-lysin of S. aureus: a streak of GBS next to S. aureus gives an arrowhead of extra hemolysis.
- Modern labs identify GBS by latex agglutination for the group B antigen, MALDI-TOF mass spectrometry or NAAT; ASM adds a PYR test to exclude PYR-positive look-alikes that also react with group B antisera.
- Compare the other cocci in the gram-positive vs gram-negative table, the 5-second rule for S. pyogenes and the S. pneumoniae sketch.
Pathogenesis: colonization, transmission, capsule
- Reservoir: the gastrointestinal tract, which seeds the genital tract; colonization may be intermittent, transient or persistent, and is more common in Black women.
- Vertical transmission: about 50% of colonized women pass GBS to their newborns during labor or after membranes rupture, and without prophylaxis 1-2% of those newborns develop early-onset disease (ACOG). Early-onset disease follows this vertical transmission and fetal or neonatal aspiration during labor and birth, which is why pneumonia is part of the picture.
- Capsule: the polysaccharide capsule defines 10 serotypes (Ia, Ib, II-IX). Low maternal levels of anticapsular antibody raise the newborn's risk (CDC 2010), because protective maternal IgG crosses the placenta.
- Risk factors for early-onset disease: maternal colonization (heaviest with GBS bacteriuria), preterm birth (<37 weeks), very low birth weight, prolonged rupture of membranes, intraamniotic infection, young maternal age, Black race and a previous infant with GBS disease.
Early-onset vs late-onset disease
| Early-onset disease | Late-onset disease | |
|---|---|---|
| Age | Birth to 6 days; most within 12-48 hours | 7-89 days |
| Source | Vertical, from the mother during labor | Mostly horizontal: mother, hospital or community |
| Picture | Sepsis, pneumonia (respiratory distress, apnea), less often meningitis | Bacteremia, meningitis; less often organ or soft tissue infection |
| Prevented by intrapartum antibiotics? | Yes (incidence fell more than 80%) | No |
- Numbers: early-onset disease fell from 1.8 per 1,000 live births in the 1990s to 0.23 per 1,000 in 2015 after intrapartum prophylaxis (ACOG). About 72% of cases occur in term babies, but mortality is far higher in preterm infants (19.2% vs 2.1%).
- Neonatal sepsis looks nonspecific: reduced activity, poor sucking, apnea, bradycardia, temperature instability and respiratory distress; fever is present in fewer than 10% of septic neonates (Merck).
- Meningitis: in neonatal bacterial meningitis a bulging fontanelle or neck stiffness appears in only about 20% of infants, and 20-50% of survivors have neurologic sequelae such as hearing loss, hydrocephalus or intellectual disability (Merck). Compare causes by age in the bacterial vs viral meningitis hub.
- Mothers and adults: in pregnancy GBS causes urinary tract infection, intraamniotic infection, bacteremia, preterm delivery and stillbirth, plus postpartum endometritis. Nonpregnant adults, especially those 65 or older or with diabetes, cardiovascular disease, cancer or obesity, get bacteremia and skin and soft tissue infections (CDC). About 5% of infants and adults with invasive disease die.
Screening in pregnancy (ACOG 2020, reaffirmed 2025)
- Who and when: every pregnant woman, regardless of planned mode of birth, at 36 0/7-37 6/7 weeks. The older CDC 2010 window was 35-37 weeks; the later window keeps the result valid (5 weeks) for births up to at least 41 0/7 weeks.
- How: one swab of the lower vagina and then the rectum (through the anal sphincter). The most common screening error is a vaginal swab without the rectal sample. The lab incubates the swab in enrichment broth and then subcultures it; NAAT on the broth is acceptable but gives no susceptibility results.
- Skip the swab when prophylaxis is already indicated: GBS bacteriuria in this pregnancy or a previous infant with GBS disease.
- Flag a penicillin allergy on the requisition so the lab tests the isolate for clindamycin susceptibility, including inducible resistance (D-zone test).
Who gets intrapartum antibiotic prophylaxis (IAP)
Give IAP for:
- Positive vaginal-rectal screen at 36 0/7-37 6/7 weeks (or within 5 weeks before birth)
- GBS bacteriuria at any concentration at any time in the current pregnancy: a marker of heavy colonization
- Previous infant with GBS disease
- Unknown GBS status at labor plus any of: labor or rupture of membranes before 37 0/7 weeks, rupture of membranes for 18 hours or more at term, intrapartum temperature 100.4°F (38°C) or higher, or a positive intrapartum NAAT
- Unknown status but GBS colonization in a previous pregnancy: reasonable to offer IAP (shared decision-making)
No IAP needed: a GBS-positive woman having a cesarean before labor with intact membranes, or a negative screen within 5 weeks.
Bacteriuria nuance: GBS at 10⁵ CFU/mL or more (or a symptomatic UTI) is treated when found and still triggers IAP in labor; lower counts in an asymptomatic woman need no antepartum treatment but still trigger IAP. Oral antibiotics, or antibiotics given before labor, do not replace IV prophylaxis in labor (CDC), and GBS typically recolonizes after a course of treatment.
Intraamniotic infection: if fever suggests chorioamnionitis, switch to broad-spectrum treatment that also covers GBS (generally ampicillin plus an aminoglycoside).
Which antibiotic, including penicillin allergy
| Situation | Drug |
|---|---|
| No penicillin allergy | IV penicillin G (first choice: 5 million units, then 2.5-3.0 million units every 4 hours until delivery); IV ampicillin (2 g, then 1 g every 4 hours) is an acceptable alternative |
| Low-risk penicillin allergy (nonurticarial rash without systemic symptoms, GI upset, family history only, unknown details) | IV cefazolin 2 g, then 1 g every 8 hours until delivery |
| High-risk allergy (anaphylaxis, angioedema, urticaria, respiratory distress, SJS, TEN or DRESS) and isolate clindamycin susceptible | IV clindamycin 900 mg every 8 hours until delivery |
| High-risk allergy and isolate resistant or susceptibility unknown | IV vancomycin 20 mg/kg every 8 hours (maximum 2 g per dose) |
- Penicillin allergy testing is safe in pregnancy and ACOG encourages it: 80-90% of people who report a penicillin allergy are not truly allergic.
- Erythromycin is no longer recommended. Clindamycin resistance in GBS now runs about 15% to over 40% (ASM).
- Timing: prophylaxis is most effective when started at least 4 hours before birth; even 2 hours lowers colony counts. Obstetric interventions such as oxytocin or a needed cesarean should not be delayed just to reach 4 hours.
- Penicillin hypersensitivity types are reviewed in the drug hypersensitivity examples.
Treating the infected newborn
- Empiric therapy for suspected neonatal sepsis or meningitis: ampicillin plus gentamicin, adding a third-generation cephalosporin if gram-negative meningitis is suspected (Merck).
- Once GBS is confirmed: penicillin G or ampicillin; gentamicin can be added for synergy at first. Meningitis needs at least 14 days of therapy.
How USMLE tests it
- Beta-hemolytic strep in a newborn's blood: GBS if bacitracin resistant and CAMP positive; GAS if bacitracin sensitive and PYR positive.
- Newborn with sepsis in the first day of life: GBS (with E. coli as the other major cause). The look-alike is Listeria monocytogenes: its colonies resemble beta-hemolytic strep, but it is a catalase-positive gram-positive rod (see Listeria monocytogenes for Step 1).
- A 5-week-old with meningitis whose mother received intrapartum penicillin: still GBS; prophylaxis does not prevent late-onset disease.
- "When do you screen?" 36 0/7-37 6/7 weeks, vaginal and rectal; not at the first visit and not with a vaginal swab alone.
- Planned cesarean, intact membranes, no labor: no GBS prophylaxis even if the screen is positive.
Practice question
A 29-year-old woman at 39 weeks' gestation presents in active labor. Her vaginal-rectal culture at 36 weeks grew group B streptococcus. She reports that penicillin given for a sore throat caused hives and swelling of her lips. Susceptibility testing showed that the isolate is resistant to erythromycin, with inducible clindamycin resistance on the D-zone test. Which is the most appropriate intrapartum prophylaxis?
A. IV penicillin G B. IV cefazolin C. IV clindamycin D. IV vancomycin E. Oral amoxicillin during labor
Answer: D. Hives and lip swelling (urticaria and angioedema) after penicillin are a high-risk penicillin allergy. With a high-risk allergy, clindamycin is used only if the isolate is susceptible; this isolate has inducible clindamycin resistance, so vancomycin (20 mg/kg IV every 8 hours, maximum 2 g per dose) is the validated alternative.
- A: penicillin is the first choice only if the allergy is ruled out (penicillin allergy testing, ideally before labor).
- B: cefazolin is for low-risk allergy histories, such as a nonurticarial rash without systemic symptoms.
- C: clindamycin requires a clindamycin-susceptible isolate; a positive D-zone test means it can fail.
- E: oral and intramuscular regimens, whether antepartum or intrapartum, have not been shown to be as effective as IV prophylaxis.
Key takeaways
- GBS lab ID: gram-positive cocci in chains, catalase negative, beta-hemolytic, bacitracin resistant, PYR negative, CAMP and hippurate positive.
- Early-onset (0-6 days): vertical transmission, sepsis and pneumonia, mostly in the first 12-48 hours. Late-onset (7-89 days): bacteremia and meningitis, not prevented by IAP.
- Screen at 36 0/7-37 6/7 weeks with a vaginal-rectal swab; skip it if there is GBS bacteriuria or a previous affected infant (they get IAP anyway).
- IAP: IV penicillin G (ampicillin acceptable), ideally 4 hours or more before birth; cefazolin for low-risk allergy; clindamycin (if susceptible) or vancomycin for high-risk allergy; erythromycin is no longer used.
- No IAP for a cesarean before labor with intact membranes.
- Sick neonate: ampicillin plus gentamicin, then penicillin G or ampicillin; at least 14 days for meningitis.
Sources
- Prevention of Group B Streptococcal Early-Onset Disease in Newborns: Committee Opinion No. 797 — American College of Obstetricians and Gynecologists (2020, reaffirmed 2025)
- Clinical Overview of Group B Strep — CDC (2025)
- Clinical Guidance for Group B Strep — CDC (2025)
- Preventing Group B Strep Disease — CDC (2025)
- Guidelines for the Detection and Identification of Group B Streptococcus — American Society for Microbiology (2021)
- UK SMI ID 4: Identification of Streptococcus Species, Enterococcus Species and Morphologically Similar Organisms — UK Health Security Agency (2026)
- Group B Streptococcus: Identification and Characterization — CDC Streptococcus Laboratory (2026)
- Prevention of Perinatal Group B Streptococcal Disease: Revised Guidelines from CDC, 2010 — MMWR Recommendations and Reports (2010)
- Neonatal Sepsis — Merck Manual Professional Edition (2026)
- Neonatal Bacterial Meningitis — Merck Manual Professional Edition (2026)
- Streptococcal Infections — Merck Manual Professional Edition (2025)
- UK SMI ID 3: Identification of Listeria Species and Other Non-Sporing Gram-Positive Rods — UK Health Security Agency (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.

Streptococcus agalactiae (Group B strep) causes early-onset neonatal sepsis/meningitis; shows CAMP test positivity with S aureus…
USMLE Step 1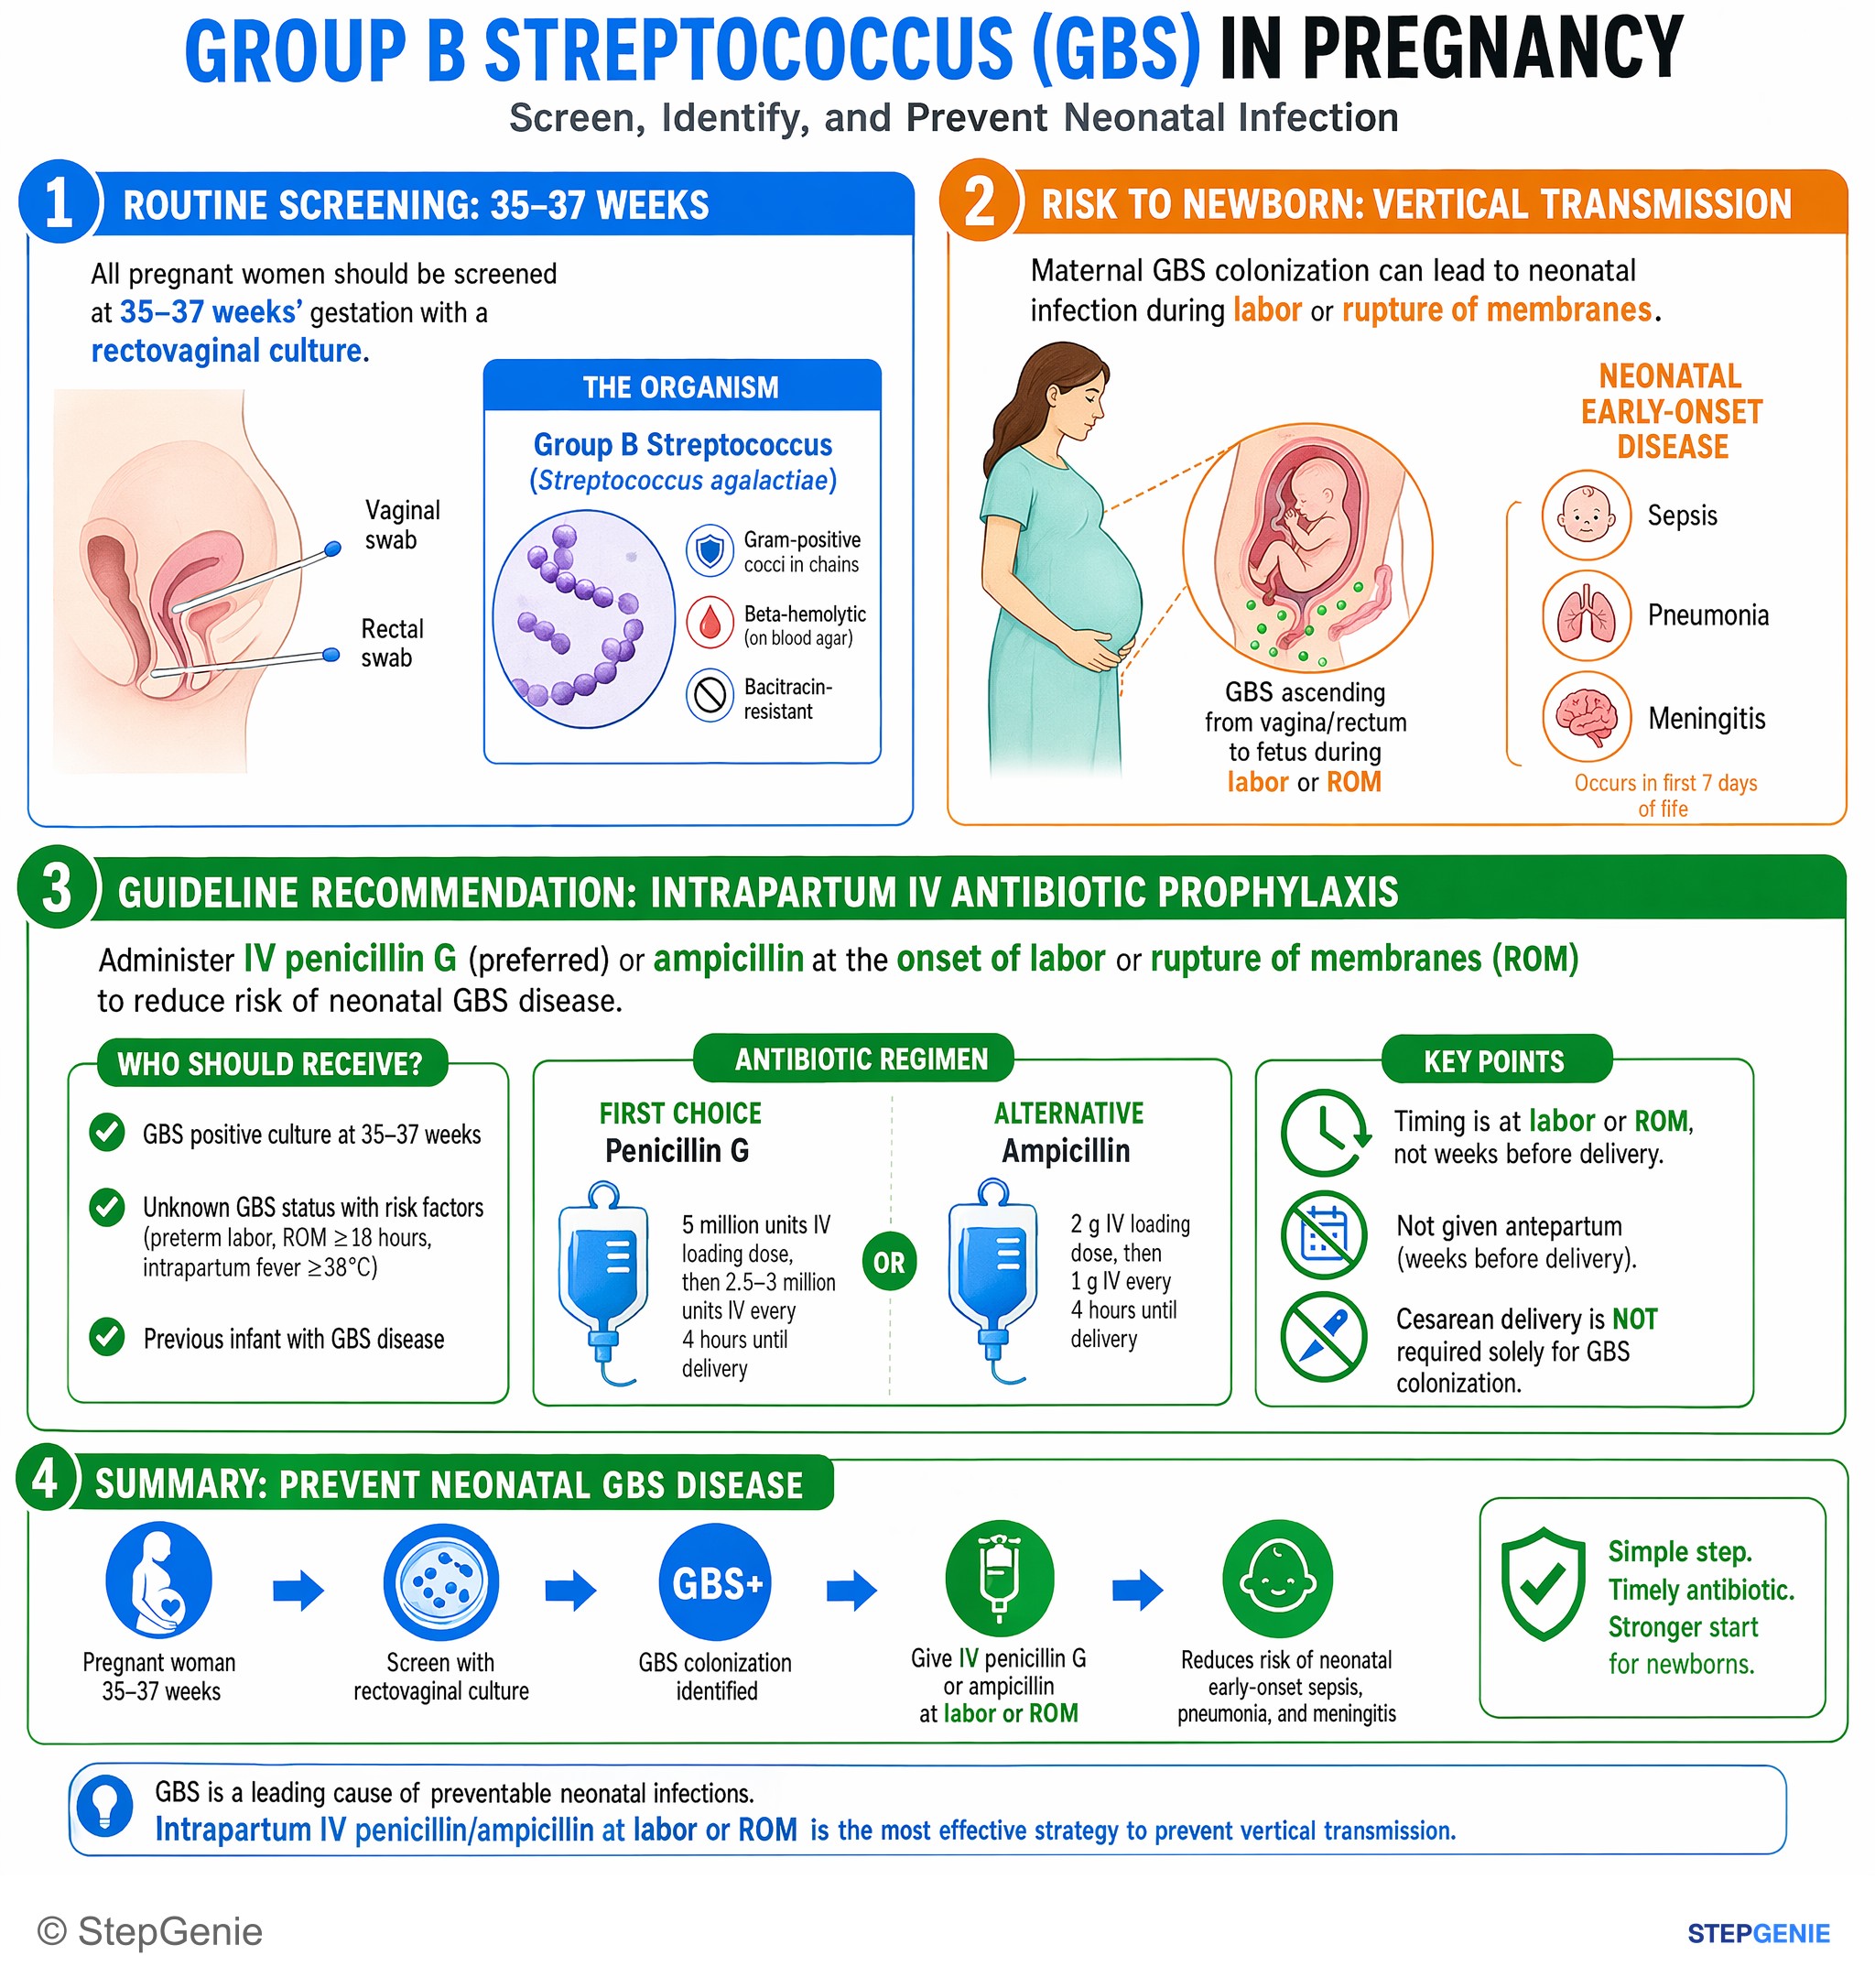
Group B Streptococcus colonization in pregnancy → give intrapartum IV penicillin/ampicillin prophylaxis at labor or ROM to prevent…
USMLE Step 2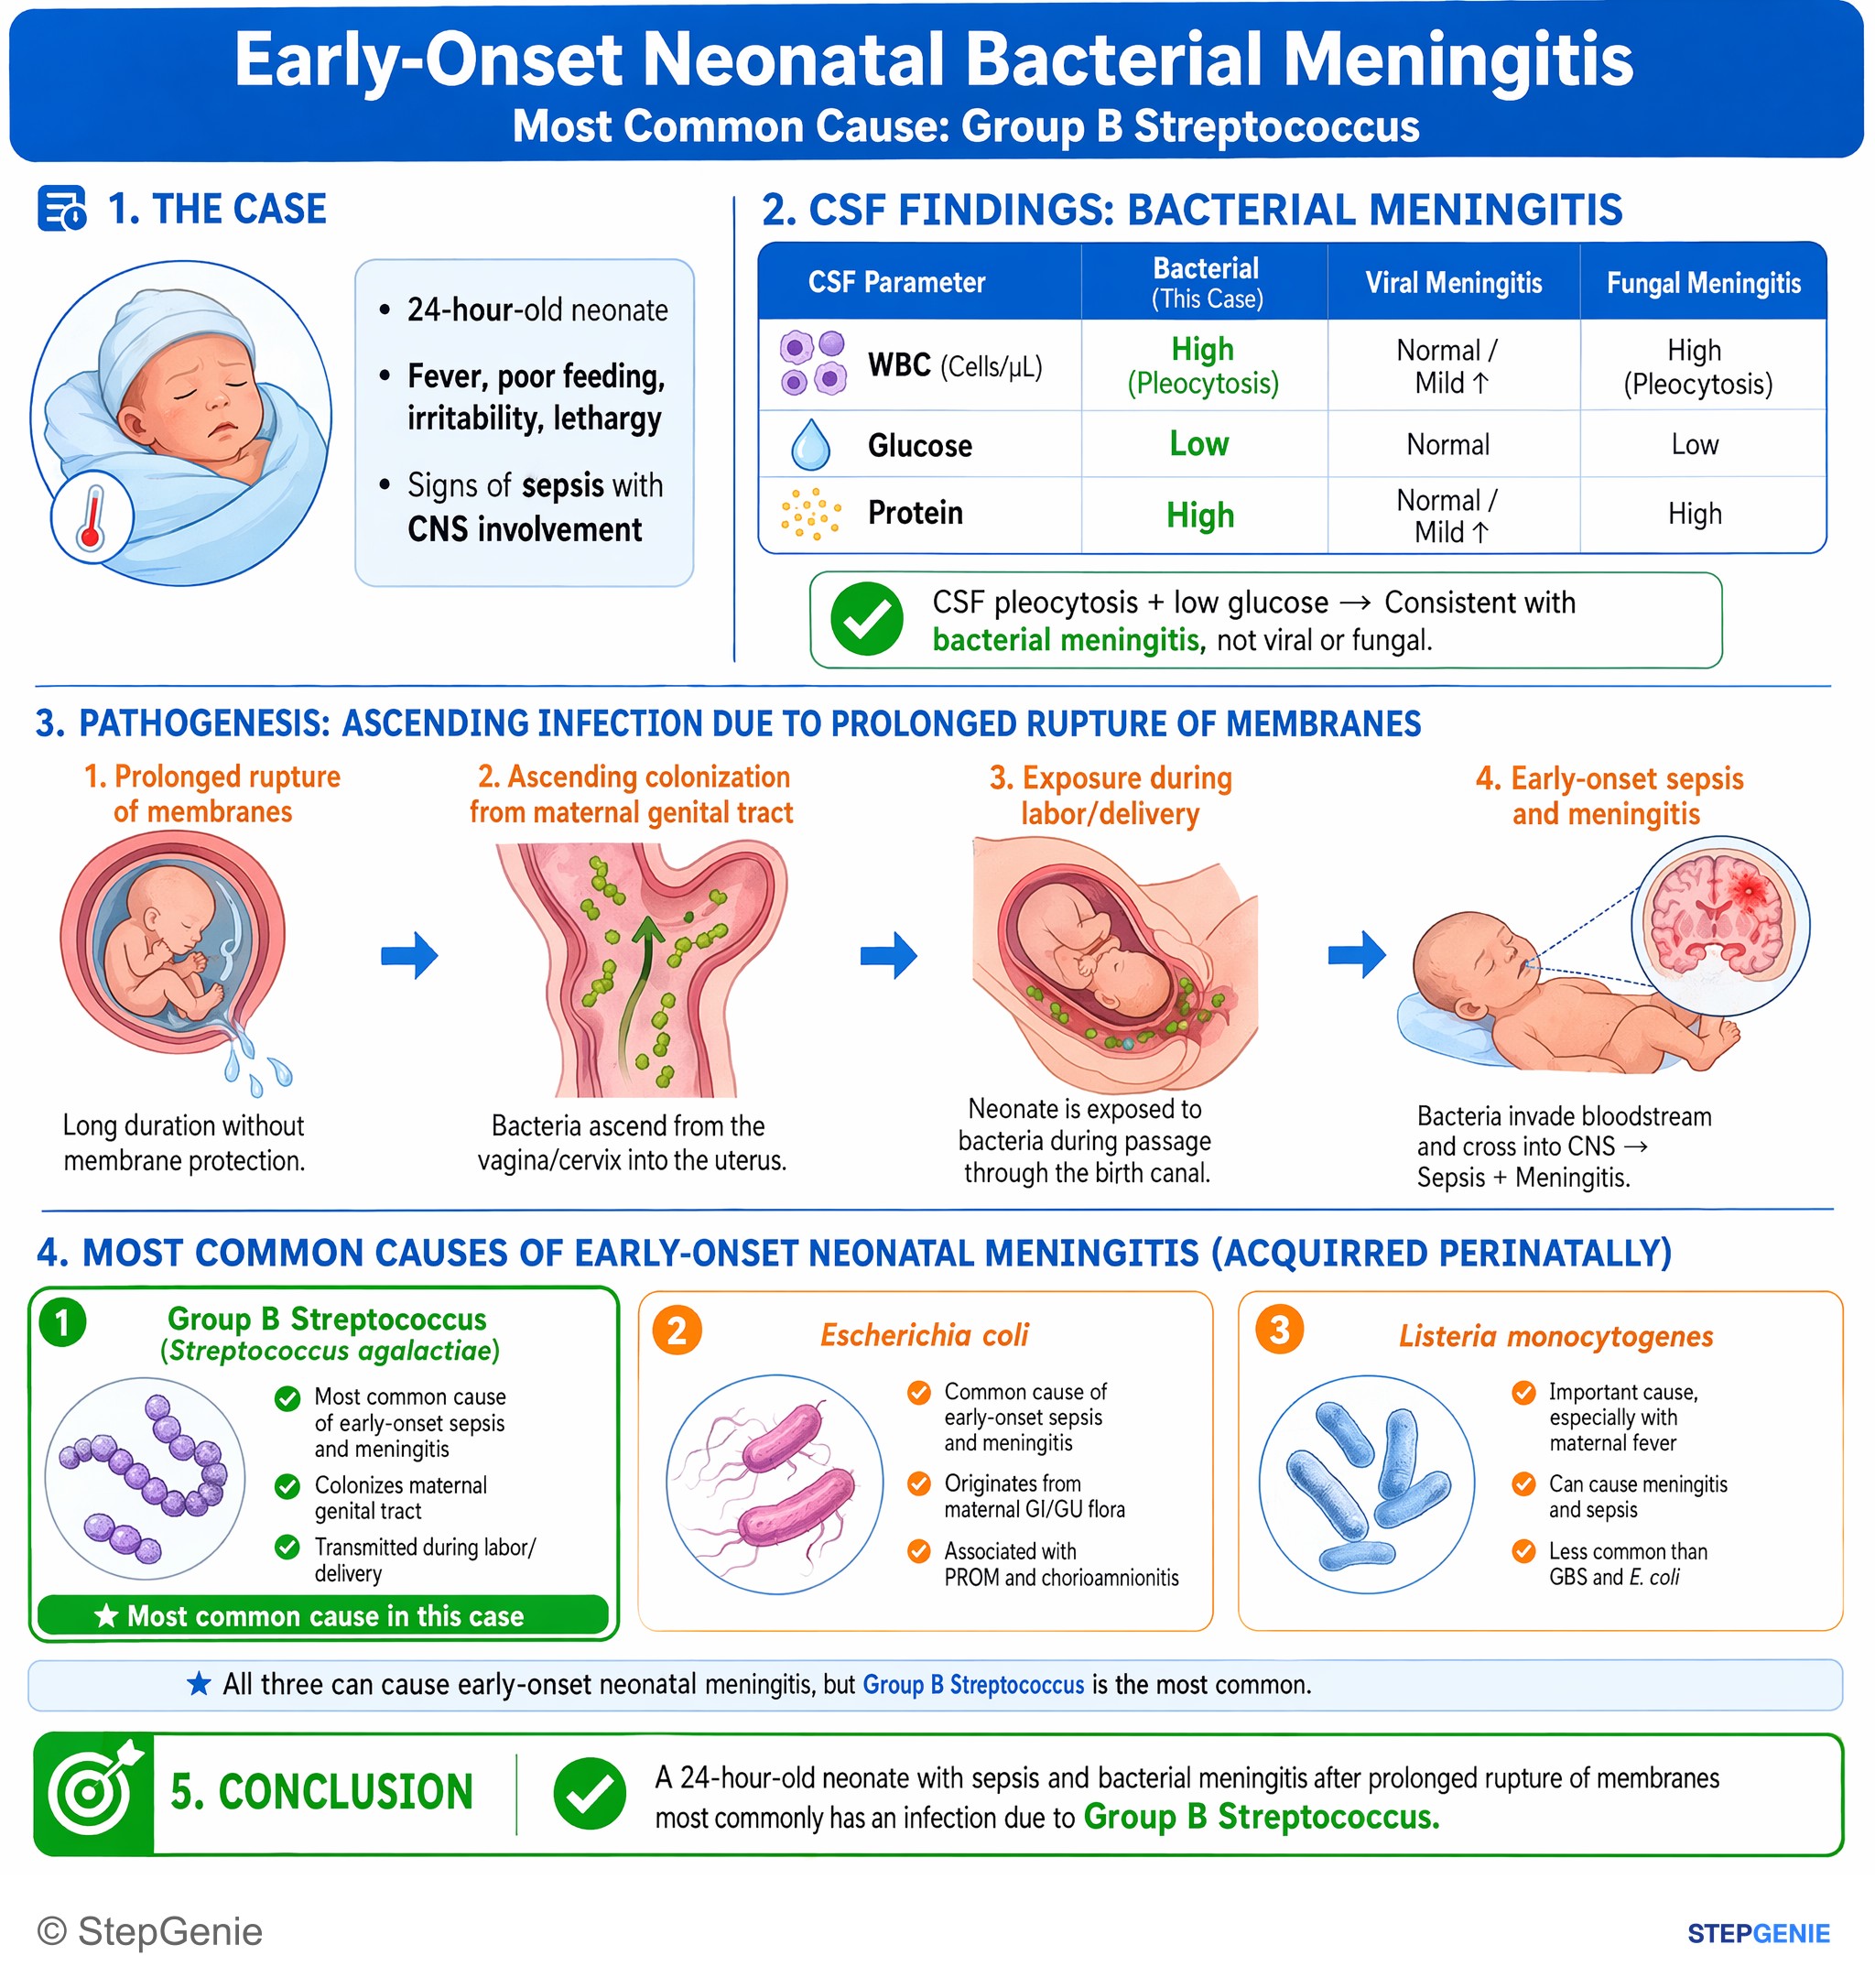
Neonatal bacterial meningitis (early-onset) with sepsis in a 24-hour-old, post–prolonged rupture of membranes is most commonly due to…
USMLE Step 1Frequently Asked Questions
How is Streptococcus agalactiae identified in the lab?
Group B streptococcus is a gram-positive coccus in chains that is catalase negative and usually shows a narrow zone of beta-hemolysis on blood agar, although about 5 to 6 percent of screening isolates are nonhemolytic. It carries the Lancefield group B antigen, is bacitracin resistant and PYR negative, and is CAMP and hippurate positive. In the CAMP test, CAMP factor from GBS enhances the beta-lysin of Staphylococcus aureus to give an arrowhead of hemolysis. Group A strep, by contrast, is bacitracin sensitive and PYR positive.
What is the difference between early-onset and late-onset GBS disease?
Early-onset disease starts in the first 6 days of life, most often within 12 to 48 hours, after vertical transmission and aspiration during labor and birth, and usually presents as sepsis or pneumonia, less often meningitis. Late-onset disease starts between 7 and 89 days of age, is mostly acquired from the mother, hospital or community after birth, and presents as bacteremia or meningitis. Intrapartum antibiotic prophylaxis prevents early-onset disease but does not prevent late-onset disease.
When and how is GBS screening done in pregnancy?
ACOG recommends screening every pregnant woman at 36 0/7 to 37 6/7 weeks of gestation, whatever the planned mode of birth. A single swab is taken from the lower vagina and then the rectum through the anal sphincter, without a speculum, and the lab grows it in enrichment broth. A result stays valid for 5 weeks. Women with GBS bacteriuria in the current pregnancy or a previous infant with GBS disease skip the swab because they receive intrapartum prophylaxis anyway.
Who needs intrapartum antibiotic prophylaxis for group B strep?
Intravenous prophylaxis during labor is given for a positive vaginal-rectal screen, GBS bacteriuria at any concentration during the current pregnancy, or a previous infant with GBS disease. If GBS status is unknown at labor, it is given for preterm labor or rupture of membranes before 37 weeks, membranes ruptured 18 hours or more, intrapartum temperature of 100.4 F (38 C) or higher, or a positive intrapartum NAAT. A GBS-positive woman having a cesarean before labor with intact membranes does not need it.
What antibiotic is used for GBS prophylaxis if the mother is allergic to penicillin?
It depends on the allergy history. A low-risk history, such as a nonurticarial rash without systemic symptoms, calls for IV cefazolin. A high-risk history, such as anaphylaxis, angioedema, hives, respiratory distress or a severe delayed reaction like Stevens-Johnson syndrome, calls for IV clindamycin only if the isolate is susceptible, and IV vancomycin if it is resistant or susceptibility is unknown. Erythromycin is no longer used, and ACOG encourages penicillin allergy testing, which is safe in pregnancy.
Does intrapartum penicillin prevent late-onset GBS disease?
No. Intrapartum antibiotic prophylaxis targets transmission during labor and has cut early-onset GBS disease by more than 80 percent, from 1.8 to 0.23 cases per 1,000 live births. Late-onset disease, which appears between 7 and 89 days of age as bacteremia or meningitis, is mostly acquired after birth from the mother, the hospital or the community, and CDC notes that no effective strategy has yet been identified to prevent it. A young infant with meningitis can still have GBS even if the mother was treated.