Enterococcus (mainly E. faecalis and E. faecium) is a catalase-negative, gram-positive coccus in pairs and short chains that carries the Lancefield group D antigen, hydrolyzes esculin in bile, grows in 6.5% NaCl and is PYR-positive. It is normal gut flora that causes hospital-acquired UTIs, bacteremia, subacute endocarditis and intra-abdominal infections, and it is intrinsically resistant to cephalosporins. For E. faecalis endocarditis, the AHA 2015 statement rates ampicillin plus ceftriaxone for 6 weeks and ampicillin (or penicillin) plus gentamicin as equally reasonable (Class IIa), and vancomycin-resistant enterococci (VRE), which build their cell wall with D-Ala-D-Lac, are treated with linezolid or daptomycin.
Lab ID in four steps
- Gram-positive cocci in pairs and short chains, catalase-negative: you are in the streptococcus/enterococcus branch. Staphylococci are catalase-positive and grow in clusters (review the branches in this gram-positive vs gram-negative bacteria table).
- Hemolysis: nonhemolytic (gamma) or alpha. It does not settle the answer.
- Bile esculin positive: a group D organism, either Enterococcus or Streptococcus gallolyticus (formerly S. bovis). Enterococci were once filed under the group D streptococci and still express the group D antigen, but they are now a separate genus.
- Growth in 6.5% NaCl and a positive PYR test: Enterococcus. No growth in salt and a negative PYR point to S. gallolyticus.
| Test or clue | Enterococcus | S. gallolyticus (S. bovis) |
|---|---|---|
| Gram stain | Gram-positive cocci in pairs and short chains | Gram-positive cocci in chains |
| Catalase | Negative | Negative |
| Lancefield group D antigen | Yes | Yes |
| Bile esculin | Positive | Positive |
| Growth in 6.5% NaCl | Yes | No |
| PYR | Positive | Negative |
| Penicillin | E. faecalis usually susceptible; E. faecium often resistant | Remains susceptible |
| Clinical hook | Nosocomial UTI, endocarditis after GU or GI procedures | Bacteremia or endocarditis with colon adenoma or cancer: order a colonoscopy |
Where it lives and who gets infected
Enterococci are normal flora of the intestine and the female genital tract, and they also live in soil and water. They survive on surfaces and spread on contaminated hands, equipment and surfaces, not through the air (VRE does not spread by coughing or sneezing). CDC lists these risk factors for VRE:
- Prior antibiotics, especially long courses, including vancomycin
- Hospital care, especially with a weakened immune system
- Urinary catheters and other medical devices, and surgery
Infections to recognize in a stem
- Urinary tract infection and prostatitis: a common hospital-acquired UTI, typically catheter-associated or after urologic instrumentation.
- Bacteremia: from IV catheters, the urinary tract, an intra-abdominal source or a wound.
- Endocarditis: a subacute course. The classic stem is an older patient with fever, fatigue and a new murmur weeks after a genitourinary or GI procedure (cystoscopy, prostate surgery, colonoscopy). Compare it with the other causes in this infective endocarditis Q-bank breakdown.
- Intra-abdominal and pelvic infections: often polymicrobial, mixed with other gut organisms.
- Skin, soft tissue and wound infections.
E. faecalis vs E. faecium
| Feature | E. faecalis | E. faecium |
|---|---|---|
| Frequency | Causes most enterococcal infections, including about 97% of enterococcal endocarditis | Less common overall, but the main multidrug-resistant species |
| Ampicillin | Mostly susceptible | Often resistant (penicillin resistance is common) |
| Vancomycin | Resistance uncommon | Resistance common; most VRE are E. faecium |
| Endocarditis therapy | Ampicillin + ceftriaxone, or ampicillin + gentamicin if no high-level resistance | Guided by susceptibility; VRE needs daptomycin or linezolid |
Resistance: intrinsic vs acquired
Intrinsic (expect it in every enterococcus):
- Most cephalosporins, plus nafcillin, oxacillin, aztreonam and ertapenem
- Clindamycin
- Aminoglycosides on their own: they enter the cell poorly without a cell wall–active partner
- Trimethoprim-sulfamethoxazole: can look active in vitro but fail in patients, because enterococci take up folate from outside the cell and bypass the block
Acquired:
- Vancomycin resistance (VRE): the vanA gene replaces the D-Ala-D-Ala end of the peptidoglycan precursor with D-Ala-D-Lac, which binds vancomycin with much lower affinity. In 2017, VRE caused an estimated 54,500 infections among hospitalized patients and 5,400 deaths in the United States (CDC).
- High-level aminoglycoside resistance (HLAR): abolishes beta-lactam–aminoglycoside synergy, so labs routinely test for it, along with penicillin and vancomycin susceptibility.
- Ampicillin resistance: common in E. faecium, uncommon in E. faecalis.
Why endocarditis needs two drugs
A cell wall–active drug alone (penicillin, ampicillin or vancomycin) does not reliably kill enterococci, and endocarditis needs bactericidal therapy. The classic fix is synergy: the cell wall–active drug lets gentamicin (or streptomycin) into the cell. HLAR breaks that partnership, and aminoglycosides bring kidney injury and often irreversible ototoxicity.
The newer fix is double beta-lactam therapy. Ceftriaxone is useless alone, but with ampicillin it is synergistic against E. faecalis, most likely because the two drugs saturate different penicillin-binding proteins. The AHA 2015 statement rates ampicillin + ceftriaxone for 6 weeks and ampicillin (or penicillin) + gentamicin as equally reasonable (Class IIa) and states no preference; the double beta-lactam is the regimen for HLAR strains or a creatinine clearance below 50 mL/min. In the studies it reviewed, cure rates were similar, and nephrotoxicity occurred in 23% of ampicillin + gentamicin patients but in none given ampicillin + ceftriaxone; for that reason many clinicians now choose it even without HLAR. See where each drug acts in this antibiotic mechanisms and coverage guide.
Treatment by scenario
| Scenario | Treatment | Key point |
|---|---|---|
| Cystitis, ampicillin-susceptible | Amoxicillin or ampicillin; nitrofurantoin or fosfomycin | Nitrofurantoin and fosfomycin are for lower UTI only |
| E. faecalis endocarditis | Ampicillin + ceftriaxone for 6 weeks | AHA 2015 Class IIa, rated equal to ampicillin + gentamicin; no aminoglycoside toxicity |
| Endocarditis, no HLAR (classic answer) | Ampicillin or penicillin + gentamicin for 4 weeks (native valve, symptoms under 3 months) or 6 weeks (longer symptoms or prosthetic valve) | AHA 2015 Class IIa; for creatinine clearance above 50 mL/min; watch kidneys and hearing |
| Endocarditis with HLAR | Ampicillin + ceftriaxone for 6 weeks | AHA 2015 Class IIa; the aminoglycoside cannot be used |
| Endocarditis, penicillin allergy | Vancomycin + gentamicin for 6 weeks | AHA 2015: vancomycin only if penicillin or ampicillin cannot be tolerated |
| VRE infection | Linezolid or daptomycin (if susceptible) | Not daptomycin for pneumonia |
| VRE colonization only | No antibiotics | Colonization does not need treatment |
VRE drug adverse effects to know:
- Linezolid: reversible myelosuppression (thrombocytopenia, usually after more than 2 weeks), peripheral and optic neuropathy with prolonged use, lactic acidosis, and serotonin syndrome with serotonergic drugs, because it is a nonselective MAO inhibitor.
- Daptomycin: not for pneumonia (pulmonary surfactant binds it), myopathy (check CK weekly; statins add risk) and eosinophilic pneumonia.
Exam traps
- Gram-positive cocci in chains that persist on ceftriaxone or cefepime: think Enterococcus. Cephalosporins do not cover it.
- "Susceptible" to trimethoprim-sulfamethoxazole in vitro does not mean it will work in the patient.
- Bile esculin positive is not enough: S. gallolyticus is positive too. Growth in 6.5% NaCl and PYR decide, and S. gallolyticus bacteremia or endocarditis calls for a colonoscopy.
- Ampicillin + gentamicin with HLAR: switch to ampicillin + ceftriaxone.
- VRE mechanism: D-Ala-D-Lac, not a beta-lactamase and not an efflux pump.
- Daptomycin for VRE pneumonia: wrong, because surfactant inactivates it.
- Endocarditis prophylaxis before cystoscopy or colonoscopy: the AHA (2007) does not recommend it for GI or GU procedures. The exception is a high-risk cardiac patient whose procedure is done during an established GI or GU infection; then the antibiotics should cover enterococci (amoxicillin or ampicillin, or vancomycin if penicillin-allergic).
Worked example
Vignette. A 74-year-old man has 3 weeks of low-grade fever, fatigue and weight loss. Six weeks ago he had a transurethral resection of the prostate. A new apical holosystolic murmur is heard. Three sets of blood cultures grow gram-positive cocci in pairs and short chains that are catalase-negative, bile esculin–positive and PYR-positive and grow in 6.5% NaCl. The isolate is E. faecalis, susceptible to ampicillin and vancomycin, with high-level gentamicin resistance. Transesophageal echocardiography shows a mitral valve vegetation. Which regimen is best?
Answer: Ampicillin plus ceftriaxone IV for 6 weeks.
Why the tempting distractors are wrong:
- Ampicillin + gentamicin: HLAR removes the synergy, and gentamicin adds kidney and ear toxicity for no benefit.
- Ceftriaxone alone: enterococci are intrinsically resistant to cephalosporins; ceftriaxone only helps when paired with ampicillin.
- Vancomycin alone: a cell wall–active drug alone is not reliably bactericidal against enterococci, and vancomycin is for beta-lactam allergy (with gentamicin).
- Linezolid or daptomycin: reserved for resistant strains such as VRE; this strain is ampicillin-susceptible.
- Colonoscopy as the answer: that is the move for S. gallolyticus, which would not grow in 6.5% NaCl.
Key takeaways
- Lab ID: catalase-negative gram-positive cocci in pairs and chains, group D, bile esculin–positive, 6.5% NaCl growth, PYR-positive.
- Settings: nosocomial UTI, bacteremia, subacute endocarditis after GU or GI procedures, polymicrobial abdominal infections.
- Intrinsic resistance: cephalosporins, clindamycin, aminoglycosides alone, trimethoprim-sulfamethoxazole in vivo.
- Endocarditis (AHA 2015): ampicillin + ceftriaxone for 6 weeks or ampicillin + gentamicin for 4–6 weeks, rated equally; the double beta-lactam is the choice with HLAR or poor kidney function.
- VRE: D-Ala-D-Lac, mostly E. faecium; treat with linezolid or daptomycin; colonization needs no antibiotics.
Sources
- Enterococcal Infections — Merck Manual Professional Edition
- Baddour LM, et al. Infective Endocarditis in Adults: Diagnosis, Antimicrobial Therapy, and Management of Complications — AHA Scientific Statement, Circulation (2015), PDF hosted by IDSA
- Infective Endocarditis — Merck Manual Professional Edition
- Vancomycin-resistant Enterococci (VRE) Basics — CDC
- Streptococcal Infections — Merck Manual Professional Edition
- Aminoglycosides — Merck Manual Professional Edition
- Cephalosporins — Merck Manual Professional Edition
- Clindamycin — Merck Manual Professional Edition
- Linezolid and Tedizolid — Merck Manual Professional Edition
- Daptomycin — Merck Manual Professional Edition
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
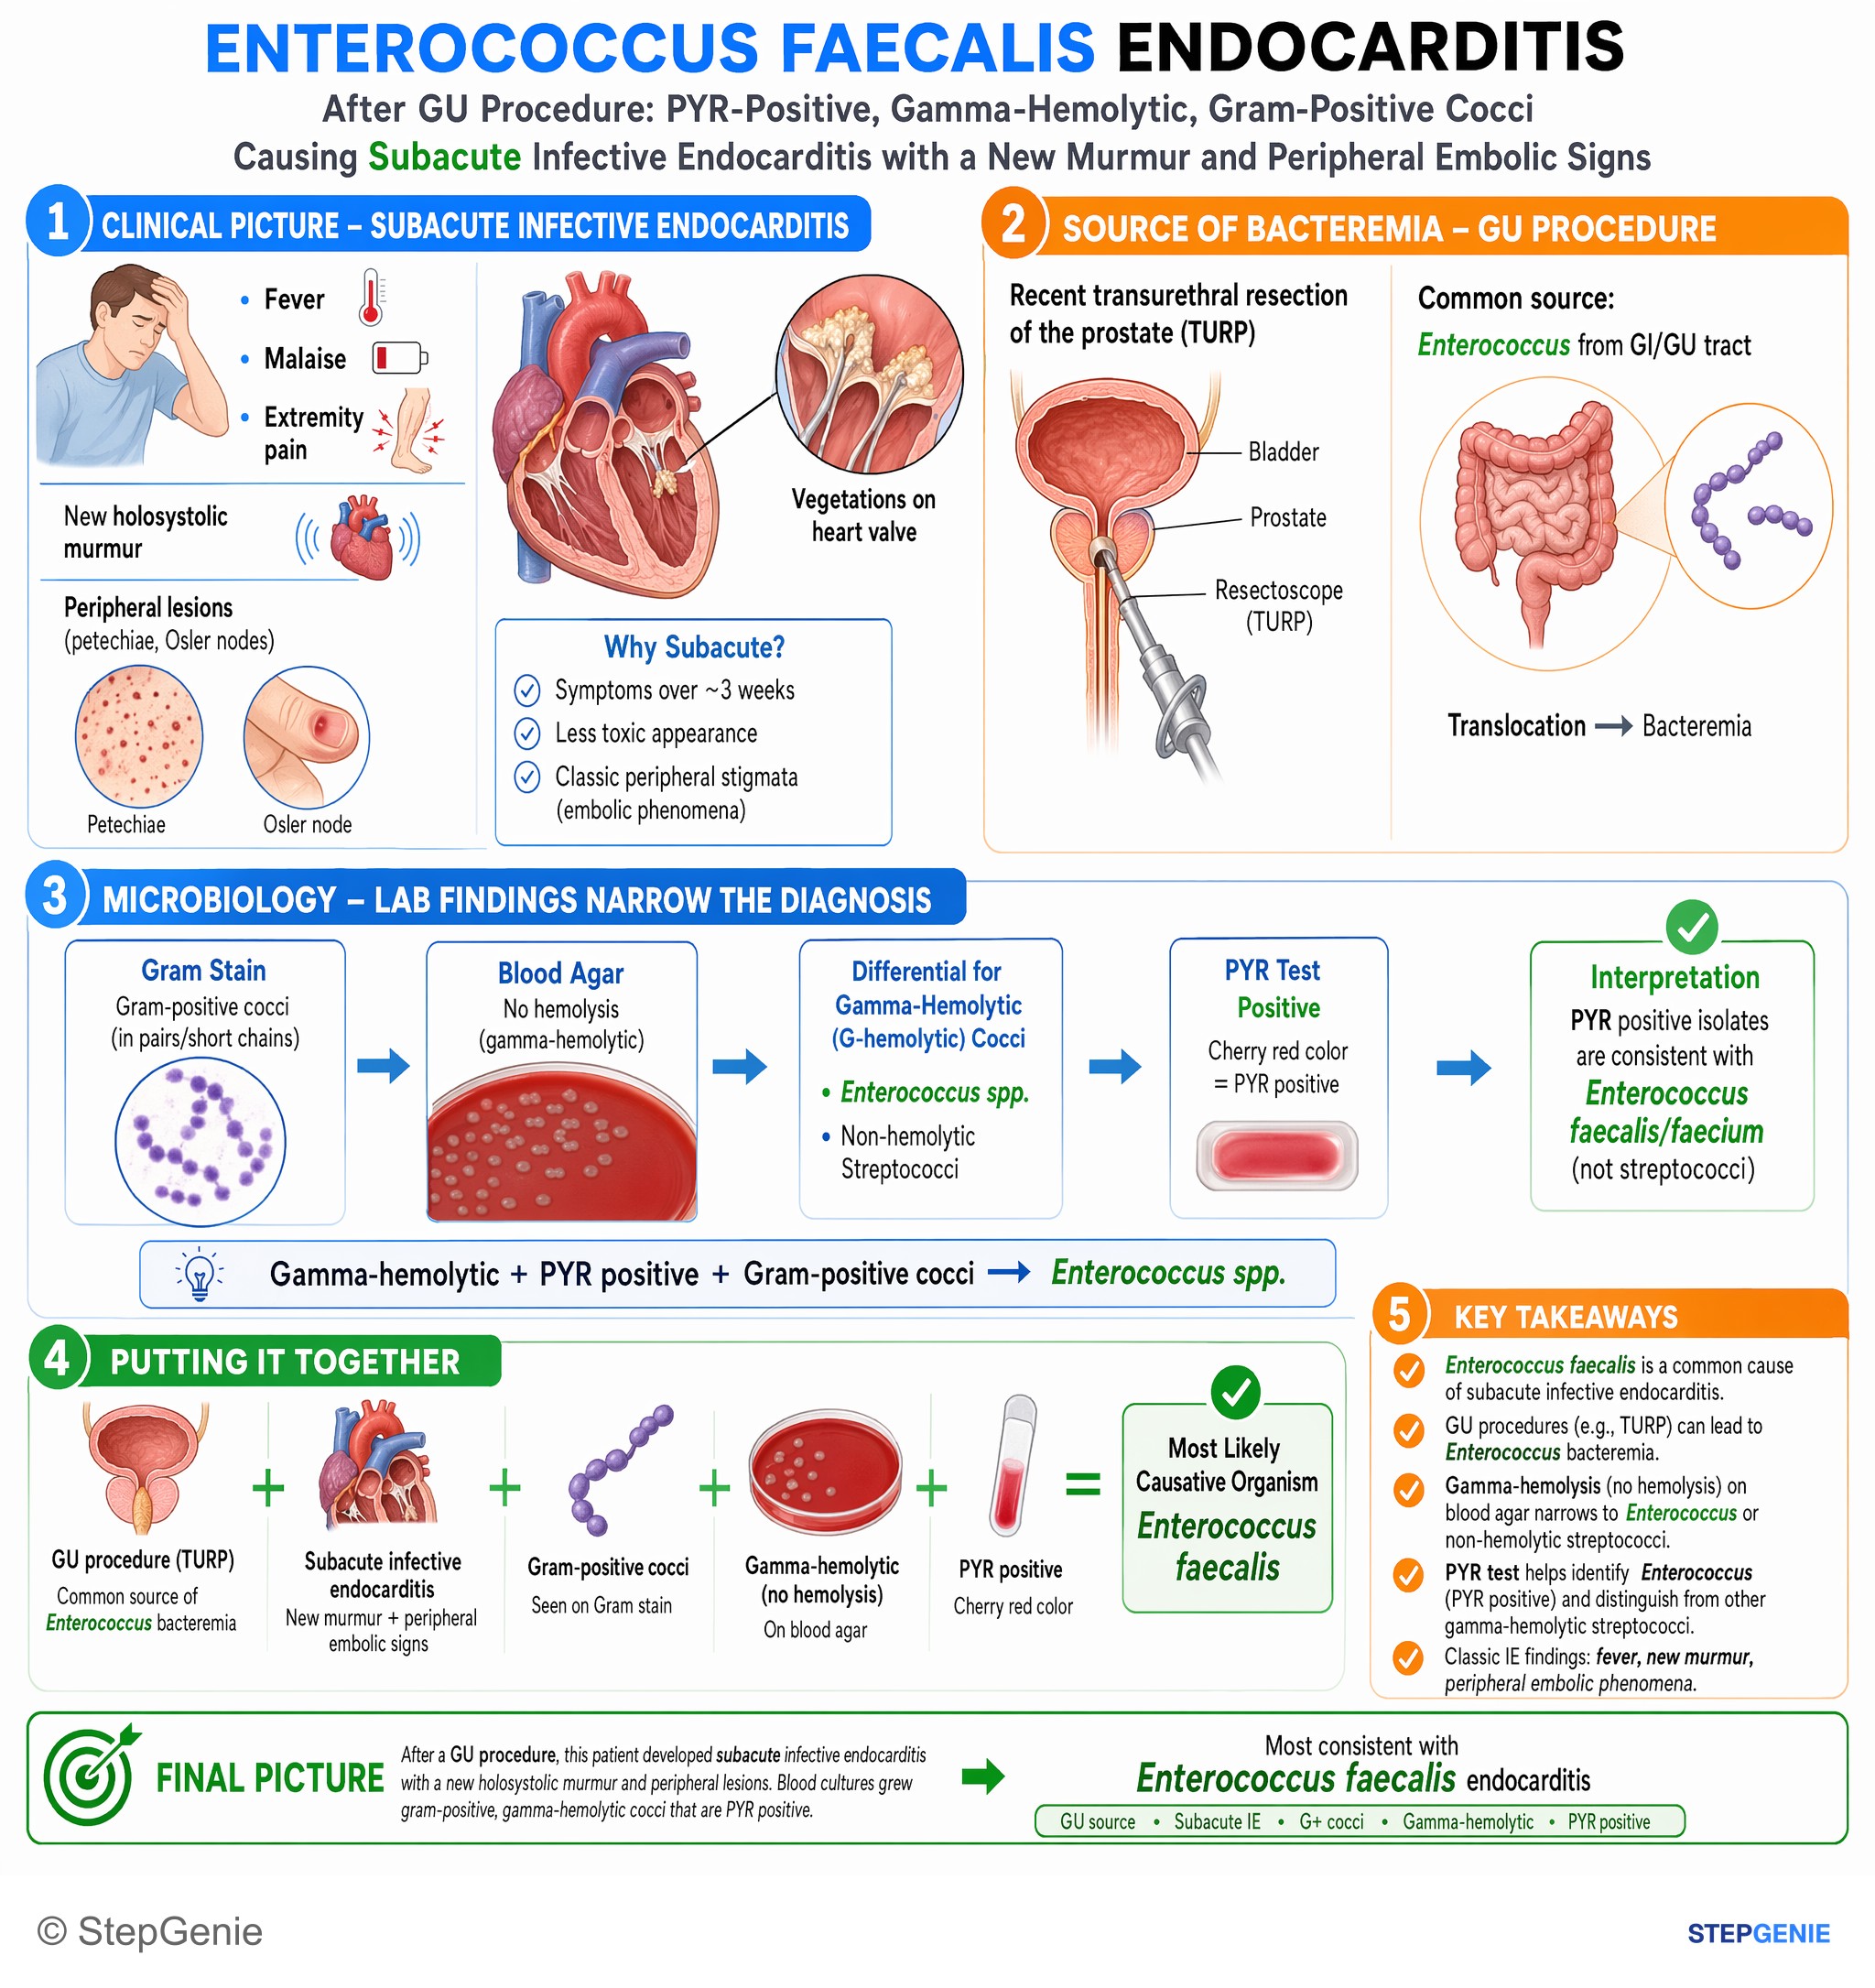
Enterococcus faecalis endocarditis after GU procedure: PYR-positive, gamma-hemolytic, Gram-positive cocci causing subacute infective…
USMLE Step 1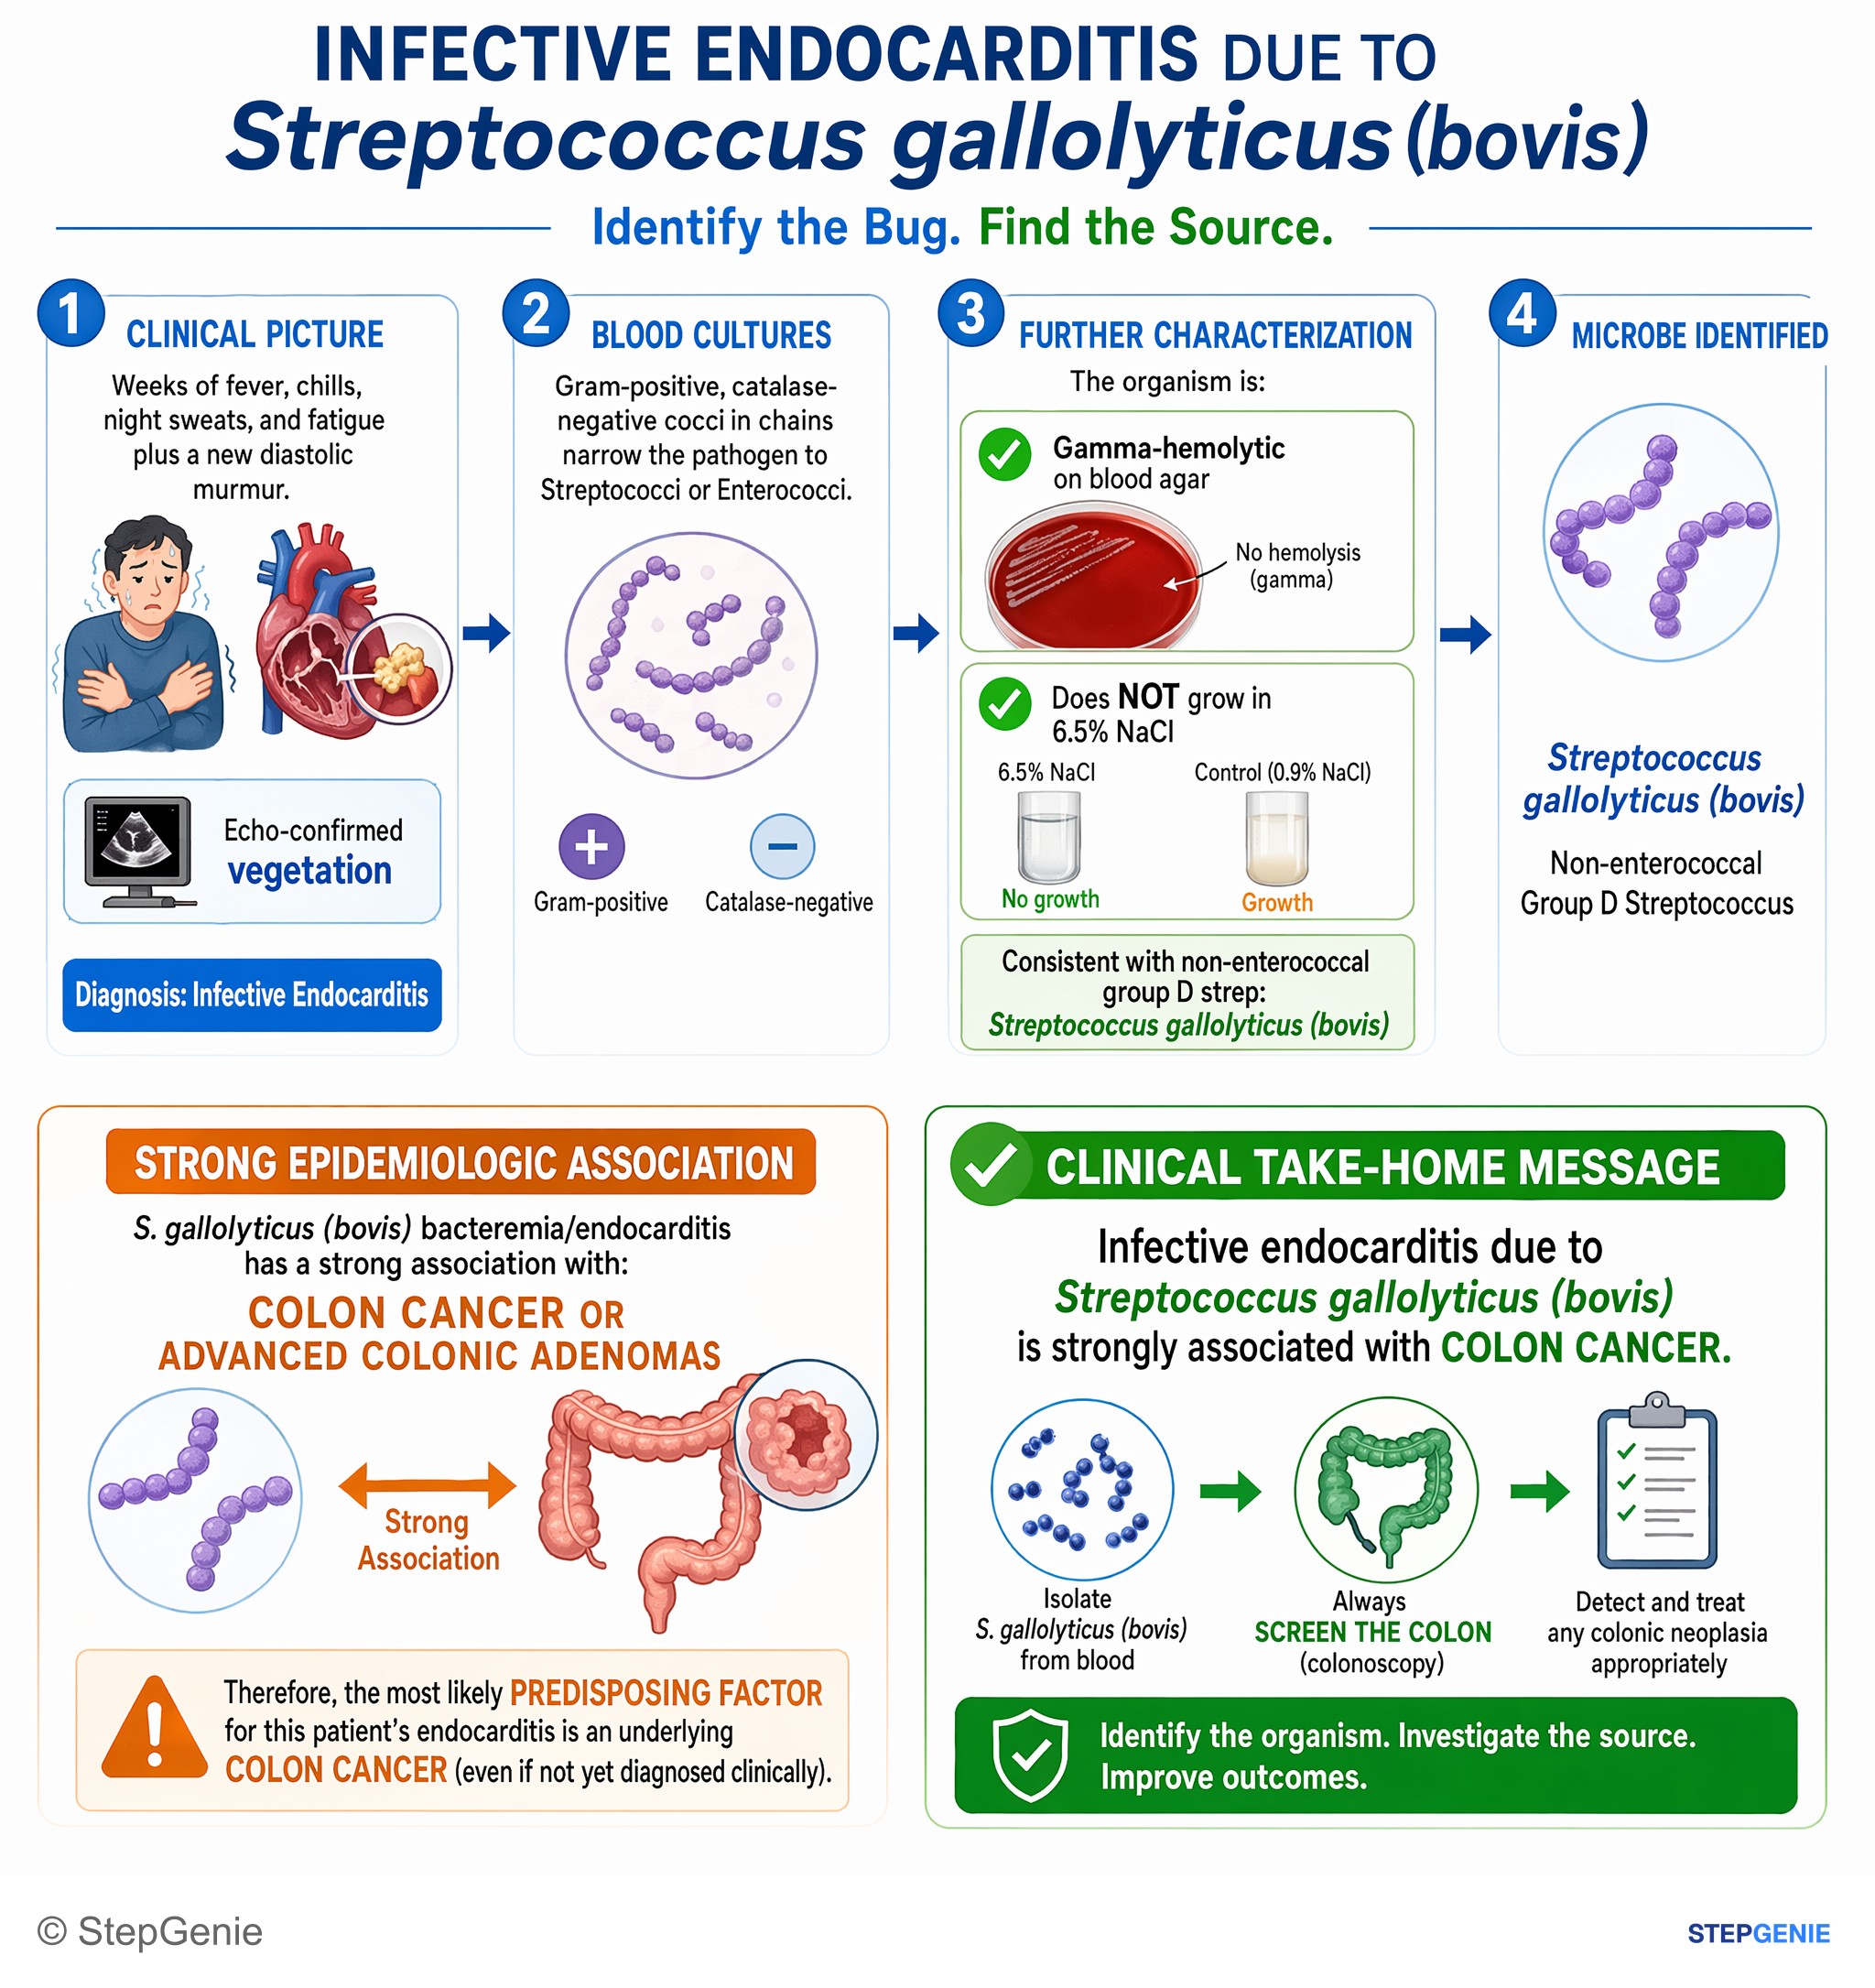
Infective endocarditis due to Streptococcus gallolyticus (bovis) is strongly associated with colon cancer; always screen the colon when…
USMLE Step 1Frequently Asked Questions
How do you tell Enterococcus from Streptococcus gallolyticus (S. bovis)?
Both are catalase-negative, carry the Lancefield group D antigen and are bile esculin–positive, so bile esculin alone cannot separate them. Enterococcus grows in 6.5% NaCl and is PYR-positive; S. gallolyticus does not grow in salt, is PYR-negative and stays penicillin-susceptible. The clinical follow-up differs too: S. gallolyticus bacteremia or endocarditis should prompt a colonoscopy to look for a colon adenoma or cancer.
Why don't cephalosporins work against Enterococcus?
Enterococci are intrinsically resistant to most cephalosporins, and also to nafcillin, oxacillin, aztreonam and ertapenem, so a patient who stays bacteremic with gram-positive cocci in chains on ceftriaxone or cefepime should make you think of Enterococcus. The one exception is combination therapy: ceftriaxone given together with ampicillin is synergistic against E. faecalis, and the AHA 2015 statement lists the pair as an endocarditis regimen.
What is the mechanism of vancomycin resistance in VRE?
Vancomycin normally binds the D-Ala-D-Ala end of the peptidoglycan precursor. In VRE, acquired genes such as vanA swap that end for D-Ala-D-Lac, which binds vancomycin with much lower affinity, so the drug cannot block cell wall synthesis. VRE is mostly E. faecium; infections are treated with linezolid or daptomycin, while colonization alone needs no antibiotics.
What is the difference between Enterococcus faecalis and Enterococcus faecium?
E. faecalis causes most enterococcal infections and is usually ampicillin-susceptible, so ampicillin-based regimens work. E. faecium is less common overall but far more resistant: penicillin and ampicillin resistance is common, and it accounts for most vancomycin-resistant enterococci. Species and susceptibility results therefore drive the choice between ampicillin, vancomycin, linezolid and daptomycin.
What is the treatment for Enterococcus faecalis endocarditis?
The AHA 2015 statement rates two regimens as equally reasonable (Class IIa) and states no preference: ampicillin plus ceftriaxone for 6 weeks, or ampicillin or penicillin plus gentamicin for 4 weeks (native valve, symptoms under 3 months) or 6 weeks (longer symptoms or a prosthetic valve). The double beta-lactam is the regimen for high-level aminoglycoside resistance or a creatinine clearance below 50 mL/min, and vancomycin plus gentamicin for 6 weeks is reserved for patients who cannot tolerate penicillin or ampicillin.