Tetanus is caused by tetanospasmin, a toxin made by Clostridium tetani, an obligate anaerobic, spore-forming gram-positive rod whose spores live in soil and animal feces and germinate in contaminated wounds. The toxin travels retrograde up motor axons to the spinal cord and brainstem, enters inhibitory interneurons and cleaves synaptobrevin (VAMP), so GABA and glycine are not released and motor neurons fire unchecked: trismus, risus sardonicus, opisthotonos and painful spasms in a patient who stays alert. Treatment is human tetanus immune globulin (TIG), wound debridement, metronidazole, benzodiazepines and airway support, and every survivor needs vaccination, because the disease does not confer immunity.
Clostridium tetani at a glance
| Feature | What to know |
|---|---|
| Organism | Obligate anaerobic, spore-forming gram-positive rod; the terminal spore gives a "tennis racket" or "drumstick" shape |
| Reservoir | Durable spores in soil and animal feces; not spread person to person |
| Way in | Puncture wounds, crush injuries, burns, necrotic tissue, foreign bodies, injection drug use, an unclean umbilical stump |
| Toxins | Tetanospasmin, the neurotoxin behind the clinical disease; C. tetani also makes a second exotoxin, tetanolysin |
| Incubation | 3-21 days (average 8); shorter incubation means more severe disease (CDC) |
| Diagnosis | Clinical; no lab test confirms or excludes it |
| Prevention | Toxoid vaccine (DTaP, Tdap, Td); recovery does not immunize |
How tetanospasmin causes spastic paralysis
- Germination: spores enter a wound and germinate where oxygen is low (dead tissue, deep punctures, foreign bodies).
- Uptake: tetanospasmin, a zinc-dependent protease, is taken up into the terminals of lower motor neurons.
- Retrograde transport: it travels backward along the axons to the spinal cord and brainstem.
- Jump to the brakes: it crosses the synapse into inhibitory interneurons that release GABA and glycine (First Aid's classic answer is Renshaw cells in the spinal cord).
- Cleavage: it cleaves synaptobrevin (VAMP), a SNARE protein that synaptic vesicles need to fuse with the membrane, so GABA and glycine are no longer released.
- Disinhibition: the lower motor neurons, freed from inhibition, fire continuously: rigidity, spasms and hyperreflexia (spastic paralysis). Loss of autonomic inhibition adds a catecholamine surge, with labile blood pressure, tachycardia and arrhythmias.
Why timing matters: toxin inside nerve terminals can no longer be neutralized, so TIG only mops up toxin that is still circulating. Spasms continue for 3-4 weeks, and full recovery can take months (Pink Book).
Tetanus vs botulism
| Feature | Tetanus (C. tetani) | Botulism (C. botulinum) |
|---|---|---|
| Where the toxin acts | CNS inhibitory interneurons, after retrograde transport | Peripheral cholinergic nerve terminals (neuromuscular junction) |
| SNARE cleaved | Synaptobrevin (VAMP) | SNAP-25, synaptobrevin or syntaxin, depending on serotype (type A cleaves SNAP-25; type B cleaves synaptobrevin) |
| Transmitter blocked | GABA and glycine (inhibitory) | Acetylcholine |
| Paralysis | Spastic: rigidity and spasms | Flaccid: symmetric, descending, always starting with the cranial nerves |
| Classic signs | Trismus, risus sardonicus, opisthotonos | Diplopia, ptosis, slurred speech, dysphagia; constipation and a weak cry in infants |
| Antitoxin | Human tetanus immune globulin | Heptavalent botulism antitoxin (HBAT) for non-infant botulism; BabyBIG for infants |
Both patients usually stay mentally clear. The difference is where the toxin works, not the protein family: botulinum toxin type B cleaves the same synaptobrevin as tetanus toxin. For the other clostridial toxin diseases, see the C. perfringens mnemonic.
Clinical forms
| Form | Key features |
|---|---|
| Generalized (more than 3 in 4 cases) | Classically descending: the Pink Book names trismus (lockjaw) as the first sign, followed by neck stiffness, trouble swallowing and abdominal rigidity, but CDC notes that abdominal rigidity is a common first sign in older children and adults; risus sardonicus (fixed grin, raised eyebrows); opisthotonos (arched back); painful spasms triggered by noise, a draft or movement; fever and autonomic instability; mental status usually clear |
| Localized | Painful spasms and spasticity of muscles near the wound, without trismus; can persist for weeks and can progress to generalized tetanus |
| Cephalic | Rarest; follows head or face wounds, sometimes otitis media; flaccid cranial nerve palsies, especially the facial nerve (CN VII), rather than spasm; can generalize |
| Neonatal | Generalized tetanus in a newborn of a nonimmune mother, from an infected umbilical stump (often cut with an unsterile instrument); onset 4-14 days after birth (average 7); inability to suck or feed, then rigidity and spasms; frequently fatal |
Complications: respiratory failure from laryngospasm or chest-wall rigidity (the most common cause of death, per Merck), fractures from violent spasms, hypertension and arrhythmias, aspiration pneumonia, pulmonary embolism and hospital-acquired infections. About 1 in 10 patients with generalized tetanus die even with intensive care (CDC). The US sees roughly 30 cases a year, mostly in adults who were never vaccinated or missed their 10-year boosters. Worldwide, neonatal tetanus killed just over 7,700 newborns in 2021, an 84% fall since 2000 (WHO).
Diagnosis and look-alikes
CDC states that no laboratory test can support or rule out tetanus: cultures can be falsely positive or falsely negative, and serology can't reliably judge an individual's immunity. C. tetani is recovered from the wound in only about 30% of cases (Pink Book; Merck). Diagnose it from the picture: a wound, a gap in vaccination and progressive rigidity with spasms in an alert patient.
| Look-alike | How to tell it apart |
|---|---|
| Hypocalcemic tetany | Carpopedal spasm, perioral tingling, Chvostek and Trousseau signs, low calcium |
| Strychnine poisoning | Ingested poison; symptoms within 15-60 minutes (CDC); blocks glycine receptors rather than glycine release (IPCS); usually lacks the autonomic instability of tetanus (StatPearls) |
| Acute dystonic reaction | Recent antipsychotic or antiemetic; torticollis, oculogyric crisis; responds to diphenhydramine or benztropine |
| Peritonsillar or retropharyngeal abscess | Trismus with fever, severe sore throat and a muffled voice |
| Neuroleptic malignant syndrome | Antipsychotic exposure, lead-pipe rigidity, high fever, confusion, high CK |
Treatment
- Neutralize unbound toxin: human TIG 500 IU IM once (CDC). Some experts infiltrate part of the dose around the wound, but the benefit is unproven; IV immune globulin (IGIV) is the fallback if TIG is unavailable, although FDA has not approved it for this use (CDC).
- Remove the source: clean the wound, debride necrotic tissue and remove foreign material.
- Kill the organism: metronidazole is the recommended antibiotic (Merck); StatPearls lists metronidazole or penicillin, typically for 7-10 days. Penicillin's theoretical GABA-A antagonism is the classic reason it is second choice, but comparative studies are inconclusive. Antibiotics matter less than debridement and supportive care (Merck).
- Control spasms: benzodiazepines (diazepam, or midazolam for long infusions) boost GABA-A signaling; see benzodiazepine pharmacology. Add neuromuscular blockade with mechanical ventilation when needed, and keep stimulation to a minimum.
- Protect the airway: early intubation or tracheostomy can be lifesaving, because laryngospasm and chest-wall rigidity cause respiratory failure.
- Calm the autonomic storm: magnesium sulfate infusion and short-acting beta-blockers such as esmolol (Merck).
- Vaccinate: start or complete the tetanus toxoid series once the patient is stable.
Wound management: Tdap/Td and TIG
| Prior tetanus toxoid doses | Clean, minor wound | All other wounds* |
|---|---|---|
| Unknown or fewer than 3 | Vaccine: yes; TIG: no | Vaccine: yes; TIG: yes |
| 3 or more | Vaccine only if 10 or more years since the last dose; TIG: no | Vaccine only if 5 or more years since the last dose; TIG: no |
*Wounds contaminated with dirt, feces, soil or saliva; puncture wounds; avulsions; and wounds from missiles, crushing, burns or frostbite (CDC Pink Book).
- Which vaccine: DTaP under age 7. From age 7, anyone not fully immunized gets Tdap, preferably as the first dose; at 11 or older, Tdap is preferred if never given; otherwise Td or Tdap (Pink Book).
- Immunodeficiency: people with HIV infection or severe immunodeficiency who have a contaminated wound (including a minor one) also get TIG, whatever their vaccine history.
- Passive plus active: in an unvaccinated patient with a dirty wound, TIG gives immediate antibody, and the toxoid starts the patient's own immunity.
Tetanus vaccine schedule
- DTaP: 5 doses at 2, 4 and 6 months, 15-18 months and 4-6 years.
- Tdap: 1 dose at 11-12 years; any adult who has never had Tdap gets one.
- Boosters: Td or Tdap every 10 years.
- Pregnancy: Tdap in every pregnancy, preferably early in weeks 27-36. Neonatal tetanus strikes newborns who lack passive protection from maternal antibodies, so immunizing mothers, plus clean delivery and cord care, prevents it (WHO).
- Unvaccinated adolescents and adults: a 3-dose series of tetanus- and diphtheria-containing vaccine, preferably starting with Tdap.
- How it works: the vaccine is a toxoid (inactivated toxin) that induces neutralizing IgG, the same strategy used against diphtheria toxin; acellular pertussis antigens ride along in DTaP and Tdap (Bordetella pertussis).
Practice question
A 41-year-old man who has never been vaccinated steps on a nail while cleaning a horse stall. Nine days later he develops jaw stiffness, followed by a stiff neck, difficulty swallowing and a board-like abdomen. Loud noises trigger painful generalized spasms with arching of the back. He is fully alert, and his serum calcium is normal.
Which mechanism best explains his symptoms?
- A. ADP-ribosylation of elongation factor 2
- B. Antibodies against postsynaptic acetylcholine receptors
- C. Cleavage of SNAP-25 at the neuromuscular junction, blocking acetylcholine release
- D. Cleavage of synaptobrevin in inhibitory interneurons, blocking glycine and GABA release
- E. Competitive antagonism of postsynaptic glycine receptors
Answer: D. This is generalized tetanus: a contaminated puncture wound, no vaccination, a descending pattern that starts with trismus, stimulus-triggered spasms and opisthotonos with a clear mind. Tetanospasmin travels retrograde to the spinal cord and brainstem and cleaves synaptobrevin in inhibitory interneurons. He also needs TIG, debridement, metronidazole, benzodiazepines and, once stable, a full toxoid series.
- A: diphtheria toxin (and Pseudomonas exotoxin A) inactivates EF-2 and halts protein synthesis: pseudomembrane, myocarditis and neuropathy, not spasms.
- B: this is myasthenia gravis: fatigable ptosis, diplopia and proximal weakness, not rigidity.
- C: botulinum toxin type A causes a descending flaccid paralysis that starts with the cranial nerves.
- E: strychnine: an ingestion with spasms within an hour; it blocks the glycine receptor rather than glycine release, and there is no wound or incubation period.
How USMLE tests tetanus
- Spastic = tetanus (no GABA or glycine release); flaccid = botulism (no acetylcholine release).
- Tetanus is not tetany: tetany is hypocalcemia with Chvostek and Trousseau signs.
- Dirty wound + unknown or fewer than 3 doses = vaccine + TIG; booster cut-offs are 5 years for dirty wounds and 10 years for clean ones.
- Surviving tetanus doesn't immunize: the Pink Book attributes this to the toxin's extreme potency.
- Rust is a red herring: the danger is spores from soil or animal feces in a deep, dirty or necrotic wound.
- Cephalic tetanus is the exception that causes a flaccid facial palsy.
Key takeaways
- C. tetani: obligate anaerobic, spore-forming gram-positive rod with a terminal "tennis racket" spore; disease is toxin-mediated and diagnosed clinically.
- Tetanospasmin goes retrograde to the CNS, cleaves synaptobrevin (VAMP) in inhibitory interneurons (Renshaw cells in First Aid's framing) and blocks GABA and glycine release, causing spastic paralysis.
- Signs: trismus, risus sardonicus, opisthotonos, stimulus-triggered spasms, autonomic instability, clear mind.
- Treat with TIG 500 IU IM, debridement, metronidazole, benzodiazepines, airway support, then vaccinate.
- Wound rule: TIG if fewer than 3 (or unknown) doses and a dirty wound, or for any contaminated wound in HIV or severe immunodeficiency; booster at 5 years (dirty) or 10 years (clean).
- DTaP x5, Tdap at 11-12, Td or Tdap every 10 years, Tdap in every pregnancy.
Sources
- Clinical Overview of Tetanus — CDC (2026)
- Clinical Features of Tetanus — CDC (2026)
- Clinical Care of Tetanus — CDC (2026)
- Tetanus — Pink Book: Epidemiology and Prevention of Vaccine-Preventable Diseases, CDC (2024)
- Pertussis Vaccination Recommendations — CDC (2025)
- Tetanus fact sheet — World Health Organization (2026)
- Tetanus — Merck Manual Professional Edition (2025)
- Tetanus (Clostridium tetani Infection) — StatPearls, NCBI Bookshelf (2024)
- Tetanus: Pathophysiology, Treatment, and the Possibility of Using Botulinum Toxin against Tetanus-Induced Rigidity and Spasms — Toxins (2013)
- Clinical Overview of Botulism — CDC (2024)
- Strychnine — CDC Chemical Emergencies (2026)
- Strychnine (PIM 507) — International Programme on Chemical Safety, WHO/INCHEM (1997)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
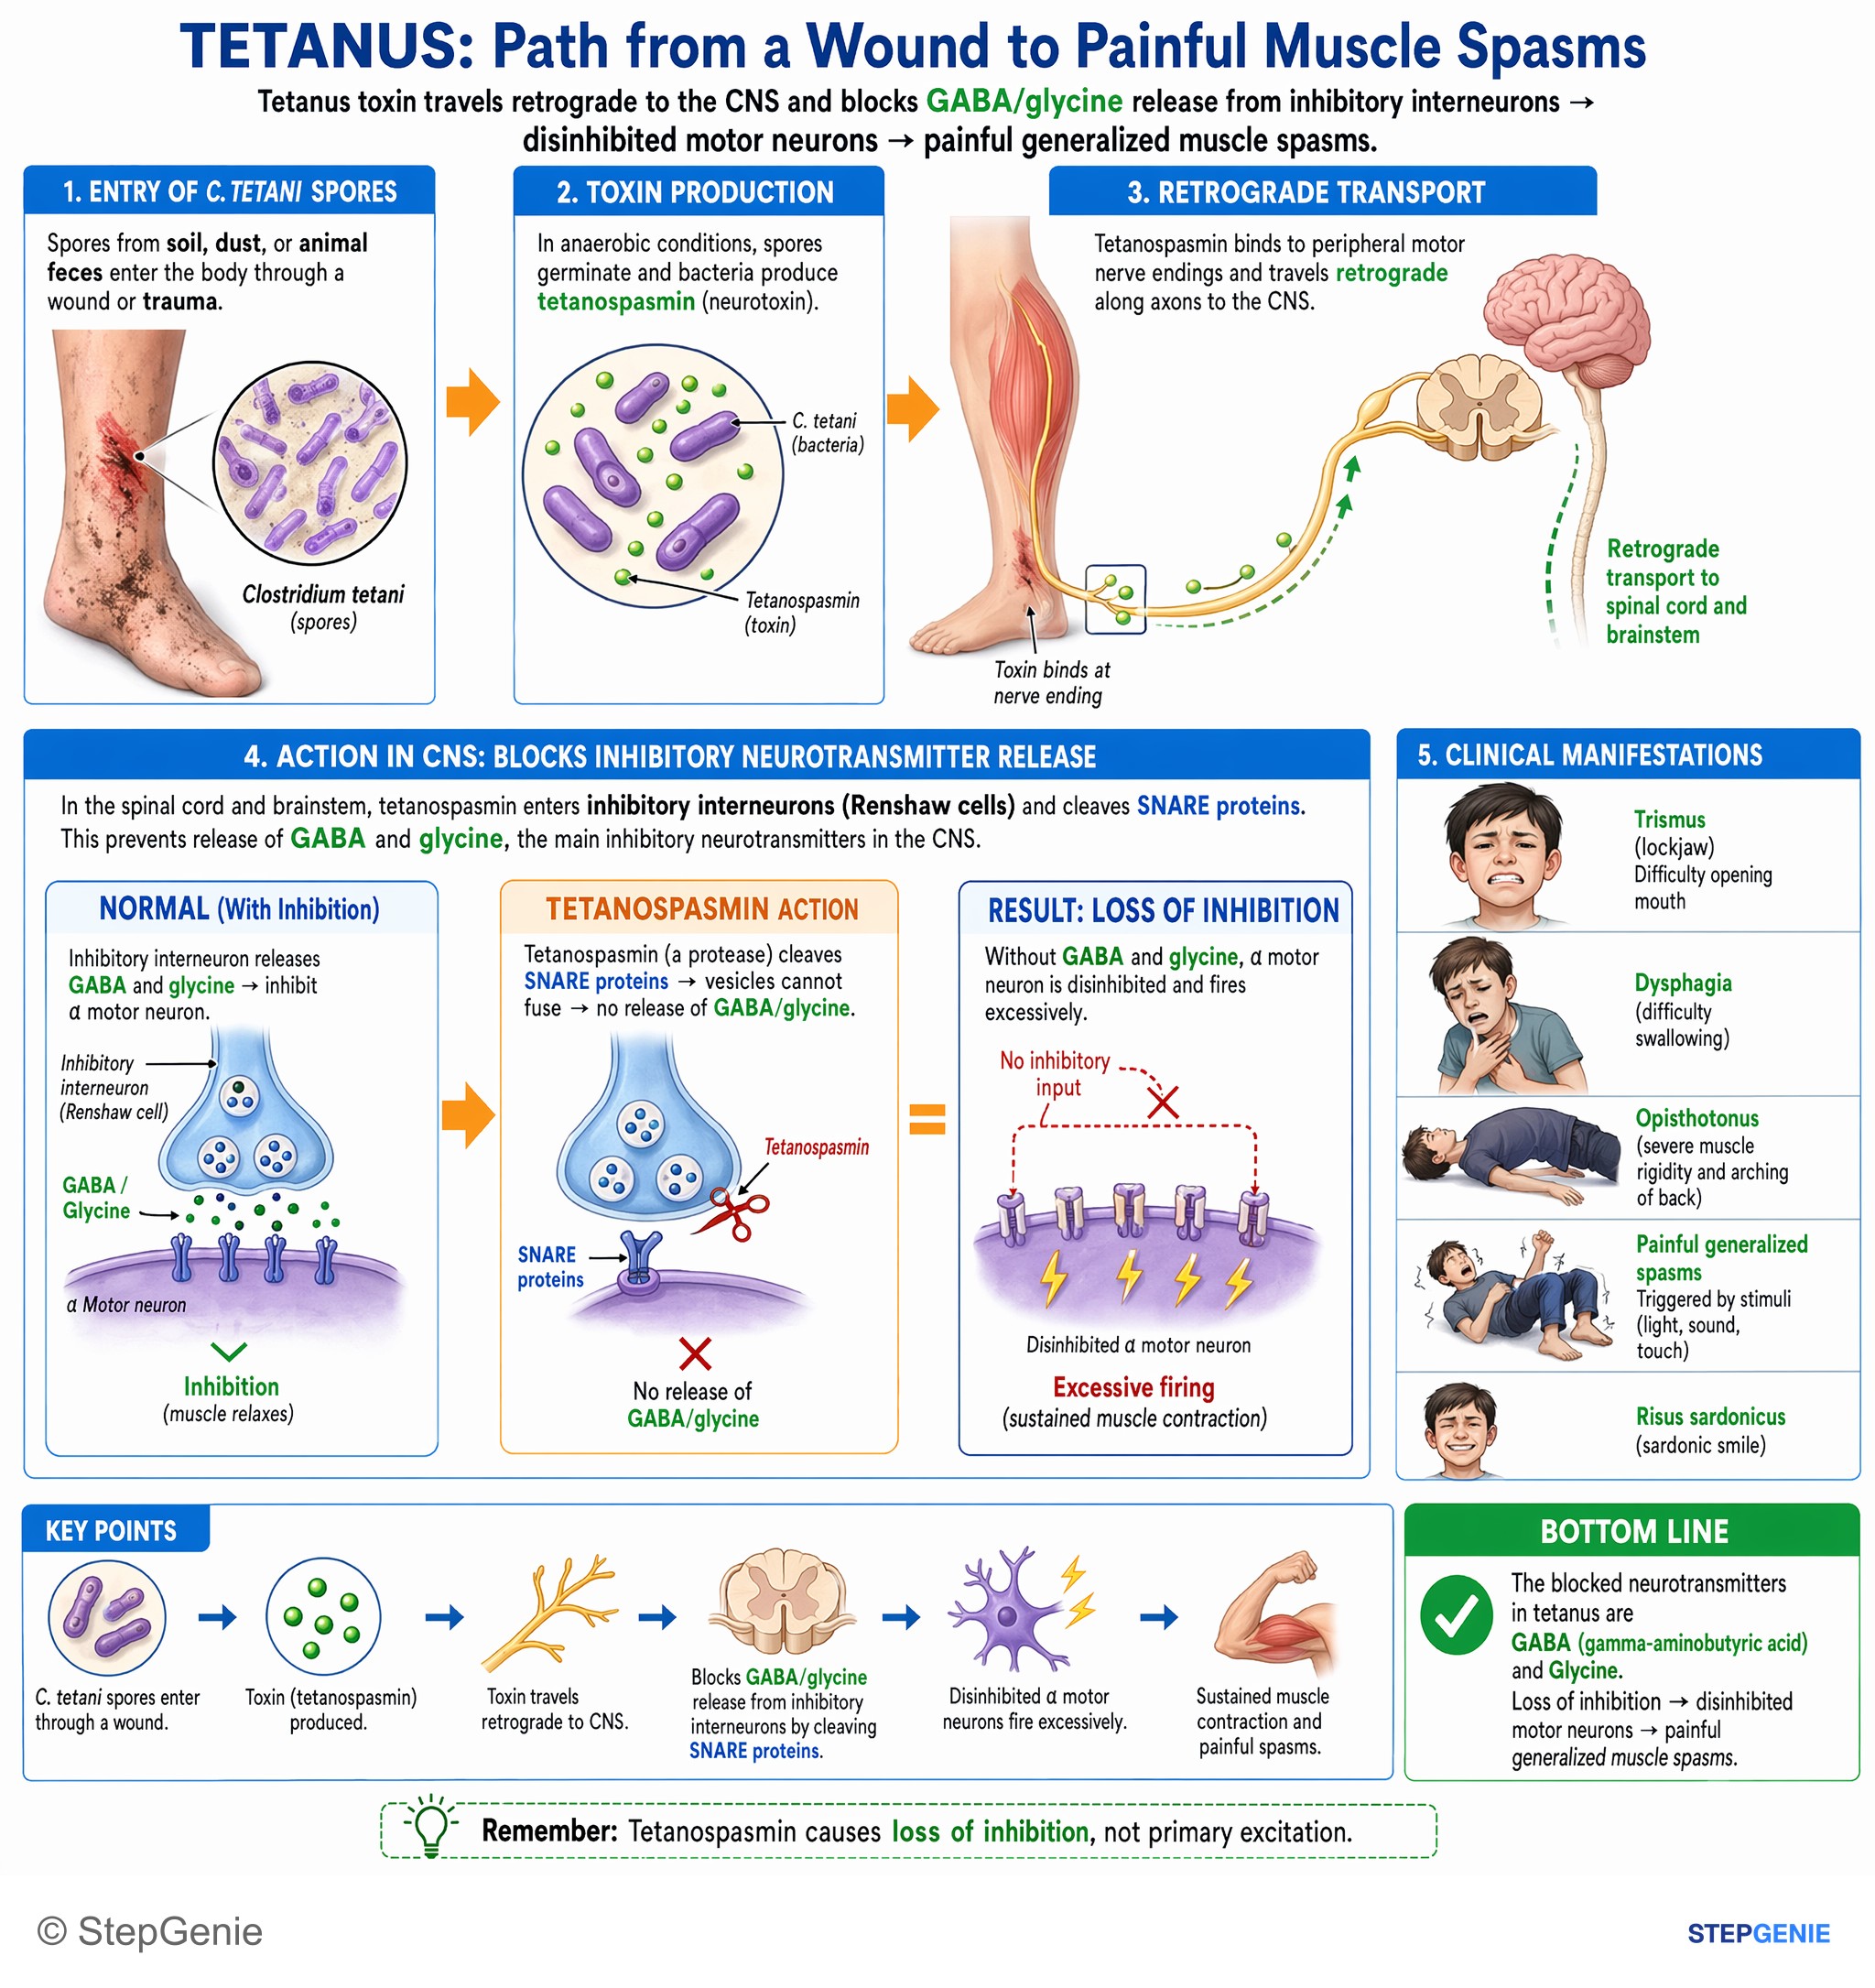
Tetanus toxin travels retrograde to CNS and blocks GABA/glycine release from inhibitory interneurons → disinhibited motor neurons →…
USMLE Step 1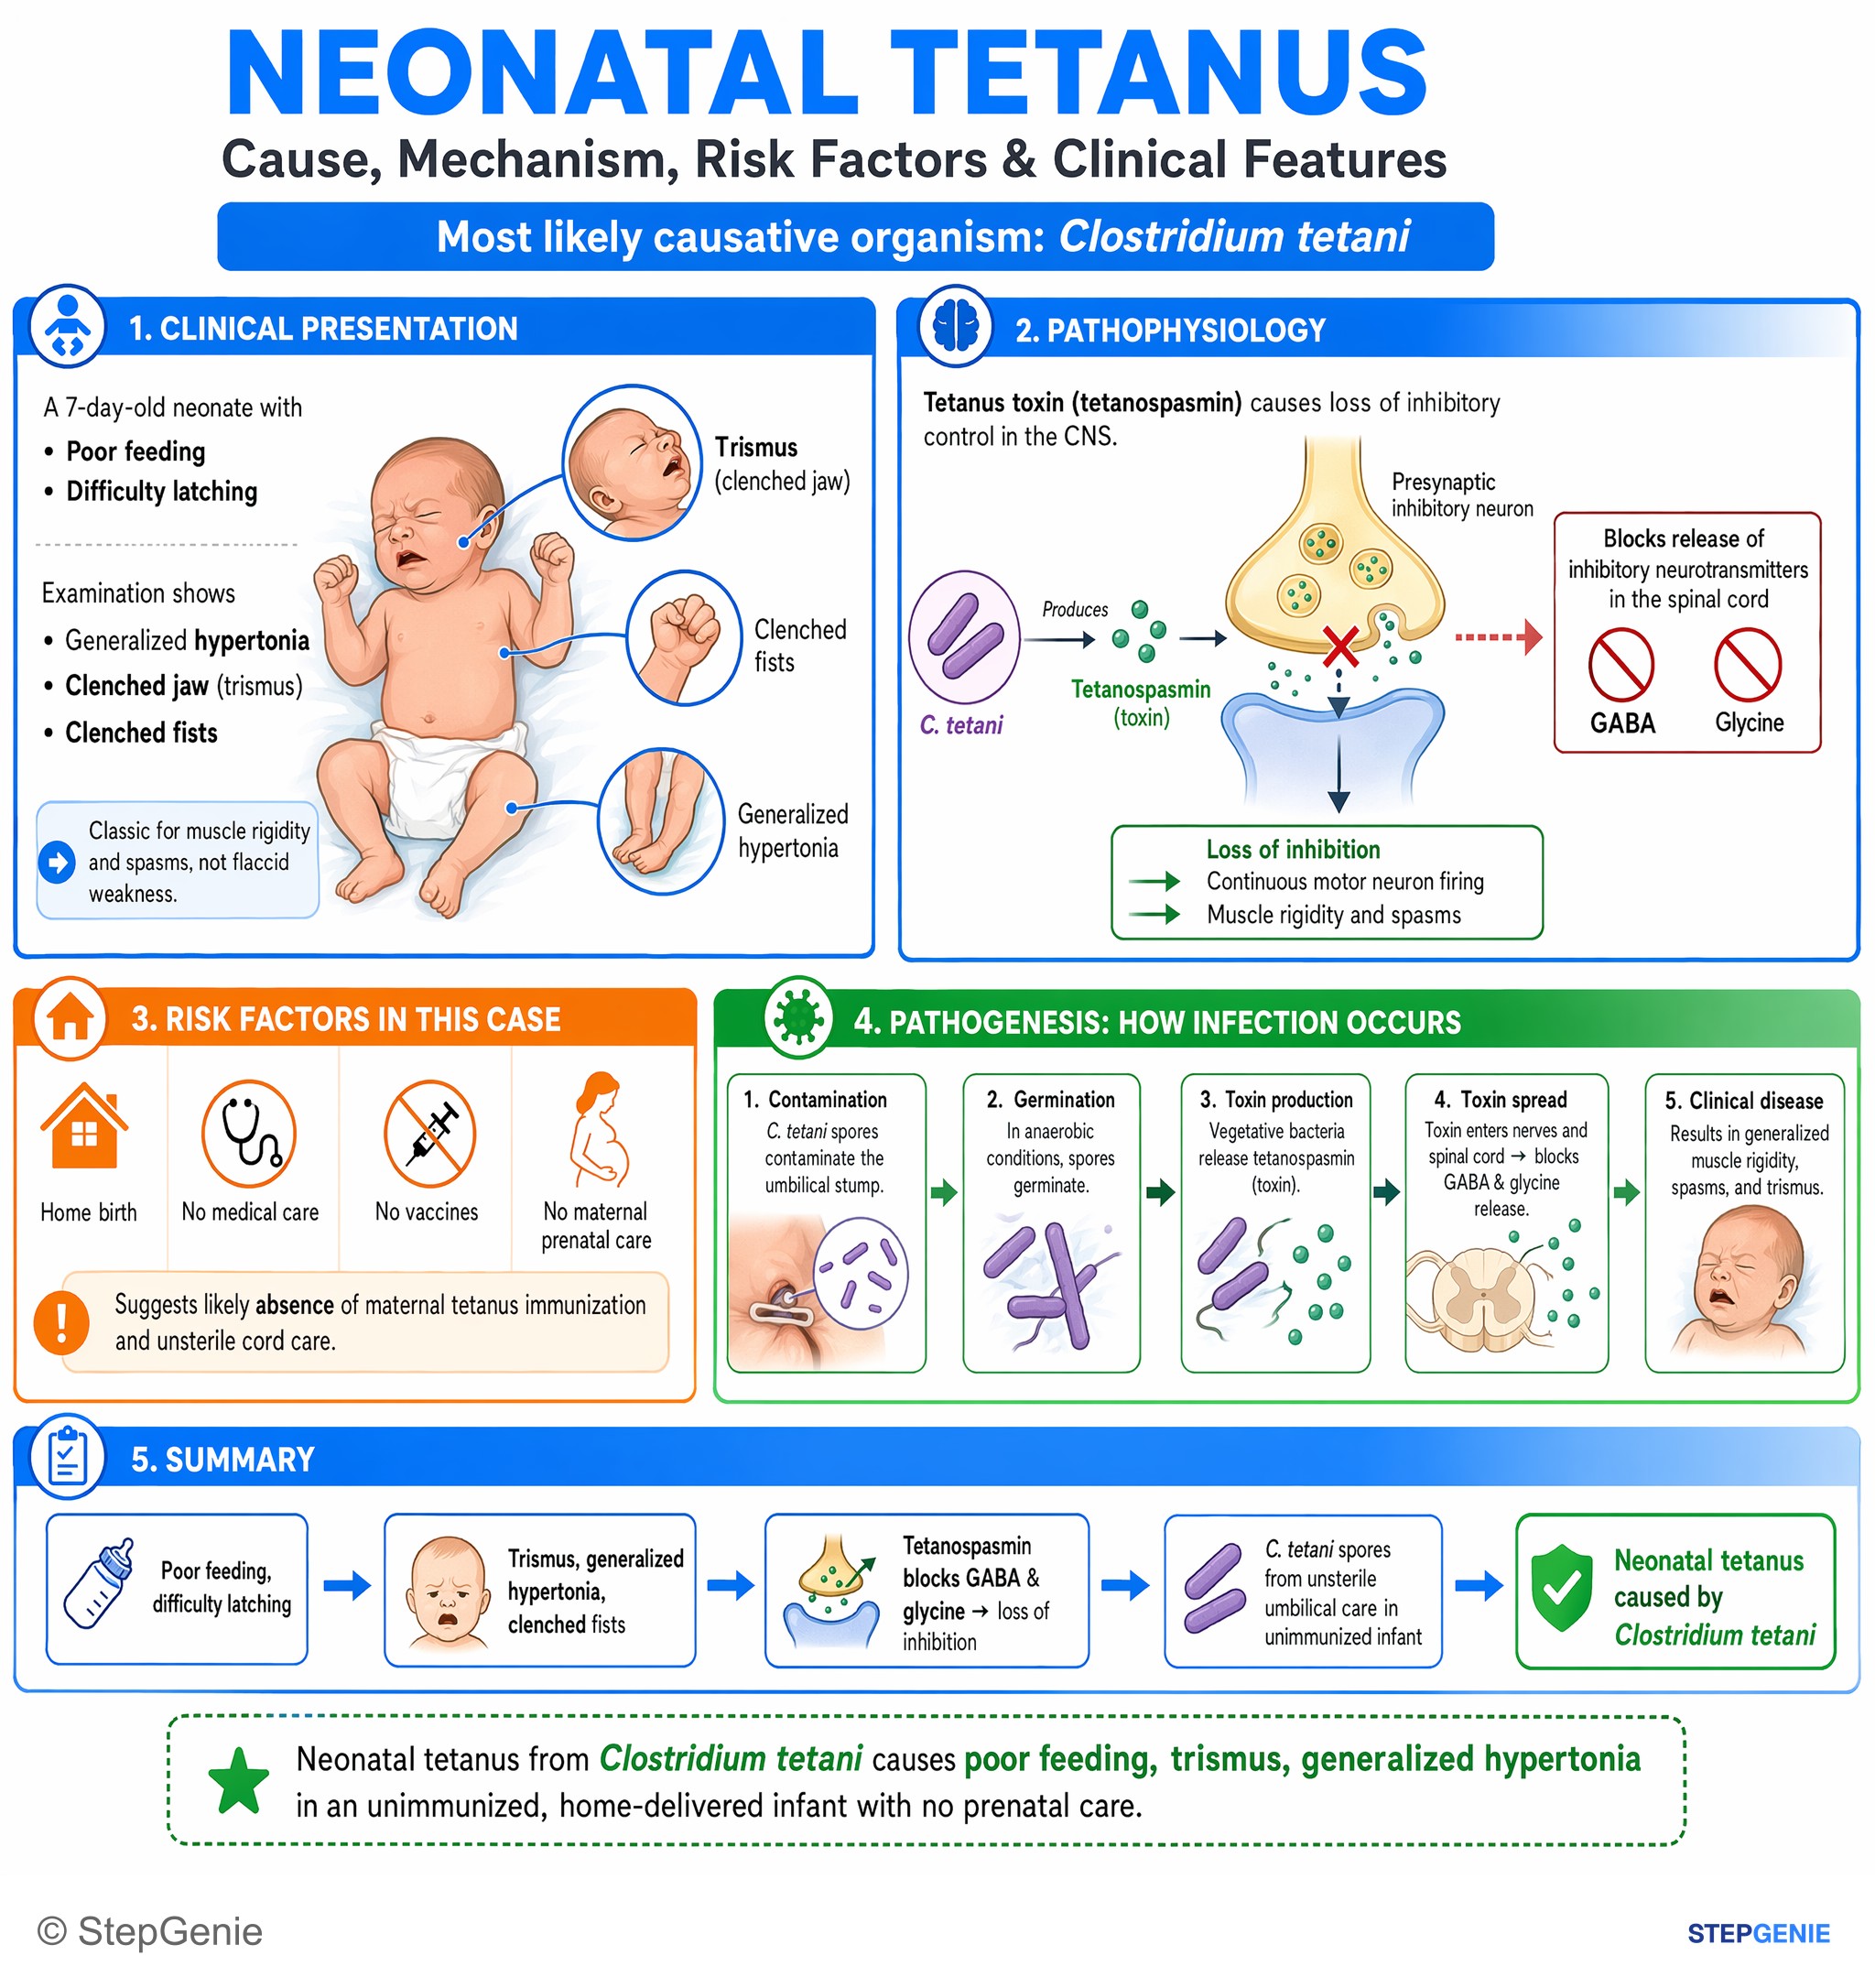
Neonatal tetanus from Clostridium tetani causes poor feeding, trismus, generalized hypertonia in an unimmunized, home-delivered infant…
USMLE Step 1Frequently Asked Questions
How does tetanus toxin cause spastic paralysis?
Tetanospasmin is taken up into lower motor neuron terminals near the wound and travels retrograde along the axons to the spinal cord and brainstem. There it crosses into inhibitory interneurons (First Aid's classic answer is Renshaw cells) and cleaves synaptobrevin (VAMP), a SNARE protein needed for vesicle release. Without GABA and glycine release, the motor neurons lose their brakes and fire continuously, producing rigidity, painful spasms, trismus and opisthotonos. Loss of autonomic inhibition adds labile blood pressure, tachycardia and sweating.
What is the difference between tetanus and botulism?
Both toxins cleave SNARE proteins, but they act in different places. Tetanus toxin travels to the central nervous system and blocks GABA and glycine release from inhibitory interneurons, causing spastic paralysis with trismus, risus sardonicus and opisthotonos. Botulinum toxin stays at peripheral cholinergic nerve terminals and blocks acetylcholine release, causing a symmetric, descending flaccid paralysis that starts with diplopia, ptosis, slurred speech and dysphagia. Patients with either disease usually stay mentally clear.
When does a wound need tetanus immune globulin (TIG)?
Under CDC's wound management table, TIG is given when the wound is not clean and minor (for example, contaminated with dirt, feces, soil or saliva, or a puncture, avulsion, crush, burn or frostbite injury) and the patient has had fewer than 3 doses of tetanus toxoid or the history is unknown. These patients also get a tetanus-containing vaccine. People with HIV infection or severe immunodeficiency who have a contaminated wound, even a minor one, get TIG regardless of their vaccine history.
When is a tetanus booster needed after an injury?
If the patient has had 3 or more doses of tetanus toxoid, a clean minor wound needs a booster only if 10 or more years have passed since the last dose, and any other wound needs one if 5 or more years have passed; TIG is not needed. If the history is unknown or fewer than 3 doses, give the vaccine for any wound. Use DTaP under age 7; from age 7, give Tdap to anyone not fully immunized, and prefer it at 11 or older if it has never been given; otherwise use Td or Tdap.
Does having tetanus make you immune?
No. Tetanus toxin is so potent that the amount that causes disease is too small to stimulate a protective antibody response, so recovering from tetanus does not give immunity. Patients should start or complete a full tetanus toxoid series once they are stable, even though they have just survived the disease. This is a classic exam point, and it is also why the vaccine is a toxoid that induces neutralizing antibodies.
How is tetanus treated?
Several measures are started together: a single intramuscular dose of human tetanus immune globulin (500 IU) to neutralize unbound toxin, cleaning and debridement of the wound, and metronidazole, with penicillin as the alternative. Benzodiazepines control rigidity and spasms, with neuromuscular blockade and mechanical ventilation if needed, and early airway protection is critical. Magnesium and short-acting beta-blockers help control autonomic instability, and the tetanus vaccine series is started once the patient is stable.