Clostridioides (formerly Clostridium) difficile is one of those “classic Step” organisms: you don’t just memorize it—you understand the toxin-mediated path, and suddenly the whole clinical picture (watery diarrhea after antibiotics, pseudomembranes, toxic megacolon) becomes inevitable. This post is your high-yield, Step 1–focused deep dive with the associations and “how they’ll test it” angles.
Where C. difficile Fits (Gram-Positive Overview)
Quick ID
- Gram-positive bacillus
- Obligate anaerobe
- Spore-forming
- Produces toxins (the real story)
Why Step loves it
Because it ties together:
- Antibiotic exposure → altered gut flora
- Spore transmission → hospital outbreaks
- Toxins → cytoskeleton disruption + inflammation
- Colonoscopy findings → pseudomembranes
- Complications → toxic megacolon, sepsis
Definition & Core Concept
Clostridioides difficile is an anaerobic, spore-forming gram-positive rod that causes antibiotic-associated colitis via toxin-mediated injury to colonic epithelial cells.
Classic buzz phrase: pseudomembranous colitis after antibiotics.
Transmission & Epidemiology (The “Spore” Angle)
Reservoir & spread
- Fecal–oral transmission
- Healthcare-associated is common (nursing homes, hospitals)
- Spores survive on surfaces for long periods
High-yield infection control
- Alcohol-based hand sanitizer does NOT kill spores well
- Use soap and water + contact precautions
- Environmental cleaning requires sporicidal agents (e.g., bleach)
Step hook: A patient gets recurrent C. diff despite “good hygiene”—then you notice the team uses only alcohol gel.
Pathophysiology: Toxins A & B (The Money Slide)
The key mechanism
C. difficile produces two exotoxins:
- Toxin A: traditionally labeled enterotoxin
- Toxin B: traditionally labeled cytotoxin
- Both are clinically important (many strains rely heavily on toxin B)
What the toxins do
They inactivate Rho GTPases via glucosylation, which leads to:
- Disruption of the actin cytoskeleton
- Loss of tight junction integrity
- Increased intestinal permeability
- Cell rounding and death
- Neutrophilic inflammation
Result: watery diarrhea + colitis, and in severe cases pseudomembranes.
One-liner to remember
Toxins A/B → Rho inactivation → actin depolymerization → leaky gut + inflammation.
Clinical Presentation (How It Shows Up on Questions)
Typical presentation
- Watery diarrhea (often profuse)
- Abdominal cramping/pain
- Fever
- Leukocytosis (can be striking)
Classic trigger
- Recent antibiotic use, especially:
- Clindamycin (very high-yield)
- Broad-spectrum beta-lactams (e.g., ampicillin/amoxicillin, cephalosporins)
- Fluoroquinolones
Key complication patterns
- Pseudomembranous colitis
- Endoscopy: yellow-white plaques (pseudomembranes)
- Toxic megacolon
- Severe colitis → colonic dilation + systemic toxicity
- Can progress to perforation, sepsis
- Recurrent infection
- Due to spores and incomplete restoration of normal flora
Pseudomembranes: What Are They?
Pseudomembranes are adherent inflammatory exudates composed of:
- Fibrin
- Mucus
- Necrotic epithelial cells
- Neutrophils
These appear as raised yellow-white plaques on colonoscopy.
High-yield contrast: This is not a true mucosal membrane like diphtheria—it's exudate sitting on injured mucosa.
Diagnosis (Step-Style Approach)
When to suspect it
- New-onset diarrhea (often ≥3 unformed stools/day) after antibiotics or during hospitalization
- Unexplained leukocytosis + abdominal symptoms in an inpatient
Best practical tests (common exam framing)
| Test | What it detects | Pros | Cons/Notes |
|---|---|---|---|
| NAAT (PCR) | Toxin genes (e.g., tcdB) | Very sensitive | Can detect colonization (not always active toxin production) |
| EIA for toxins A/B | Toxins in stool | More specific for active toxin | Less sensitive |
| GDH antigen | Glutamate dehydrogenase (organism marker) | Good screening | Needs confirmatory toxin/NAAT |
Common algorithm (you’ll see this in vignettes): GDH + toxin EIA (with NAAT arbitration) or NAAT-based testing depending on institution.
HY principle
- Don’t test asymptomatic patients. Colonization exists; testing is for symptomatic diarrhea.
Treatment (Step 1 High-Yield + Clinical Reality)
First step
- Stop the inciting antibiotic if possible
- Maintain hydration/electrolytes
Antibiotic therapy (current standards)
- Oral vancomycin or fidaxomicin are first-line for most cases
- Metronidazole: historically used; still may appear in older resources/questions (especially for mild disease), but it’s no longer preferred as first-line in many guidelines
Severe/fulminant disease (classic exam scenario)
Signs: hypotension, shock, ileus, toxic megacolon, peritonitis
- High-dose oral vancomycin (plus rectal vancomycin if ileus)
- IV metronidazole (adjunct, because oral meds may not reach colon well with ileus)
- Surgery consult if concern for perforation/megacolon
Recurrence
- May need vancomycin taper/pulse, fidaxomicin, and in multiple recurrences:
- Fecal microbiota transplantation (FMT) (high-yield concept: restores normal flora)
Do not use anti-motility agents (e.g., loperamide) in suspected severe colitis—risk of worsening/toxic megacolon.
High-Yield Associations & “They Love to Ask This” List
1) Antibiotic-associated diarrhea
- Clindamycin is the poster child
- Also ampicillin/amoxicillin, cephalosporins, fluoroquinolones
2) Hospital/outbreak + spores
- Survives routine cleaning
- Alcohol gel insufficient → soap and water
3) Toxin mechanism
- Inactivates Rho GTPases → actin depolymerization
- Explains epithelial barrier loss + inflammation
4) Colonoscopy finding
- Pseudomembranes (yellow-white plaques)
5) Complication: toxic megacolon
- Abdominal distention + systemic toxicity
- Think colonic dilation and risk of perforation
6) Treatment phrasing
- “Treat with oral vancomycin” is the safest Step answer in many modern question sets
- Know that older Step resources may list metronidazole; be ready to interpret based on question date/style
First Aid Cross-References (How to Anchor It in Your Book)
In First Aid (Microbiology → Gram-positive anaerobes), C. difficile is classically grouped with other clostridia and emphasized for:
- Antibiotic-associated pseudomembranous colitis
- Toxins A and B
- Diagnosis via toxin detection/PCR
- Treatment: oral vancomycin (± fidaxomicin); metronidazole historically
Tip: When you review that FA section, actively connect each fact to the mechanism:
“Rho GTPase inhibition” → “actin disruption” → “leaky junctions” → “watery diarrhea + pseudomembranes.”
That causal chain is what turns memorization into easy points.
Rapid Review Table (Final-Week Friendly)
| Feature | High-yield answer |
|---|---|
| Organism | Gram+ anaerobic spore-forming rod |
| Setting | Post-antibiotics, hospitalized, nursing home |
| Virulence | Toxin A/B |
| Mechanism | Rho GTPase inactivation → actin depolymerization |
| Presentation | Watery diarrhea, fever, abdominal pain, leukocytosis |
| Endoscopy | Pseudomembranes |
| Complications | Toxic megacolon, perforation, recurrence |
| Diagnosis | Stool toxin assay and/or NAAT (PCR) in symptomatic patients |
| Treatment | Stop offending abx; oral vancomycin or fidaxomicin; severe: + IV metronidazole; recurrent: consider FMT |
| Infection control | Soap & water (spores), contact precautions |
Common Step-Style Mini-Vignettes (Self-Check)
- After clindamycin, hospitalized patient has watery diarrhea + leukocytosis → C. diff.
- Diarrhea + colonoscopy shows yellow-white plaques → pseudomembranous colitis.
- Persistent outbreaks despite hand sanitizer → spores, need soap/water + sporicidal cleaning.
- Severe abdominal distention + systemic toxicity + colonic dilation → toxic megacolon (fulminant C. diff).
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
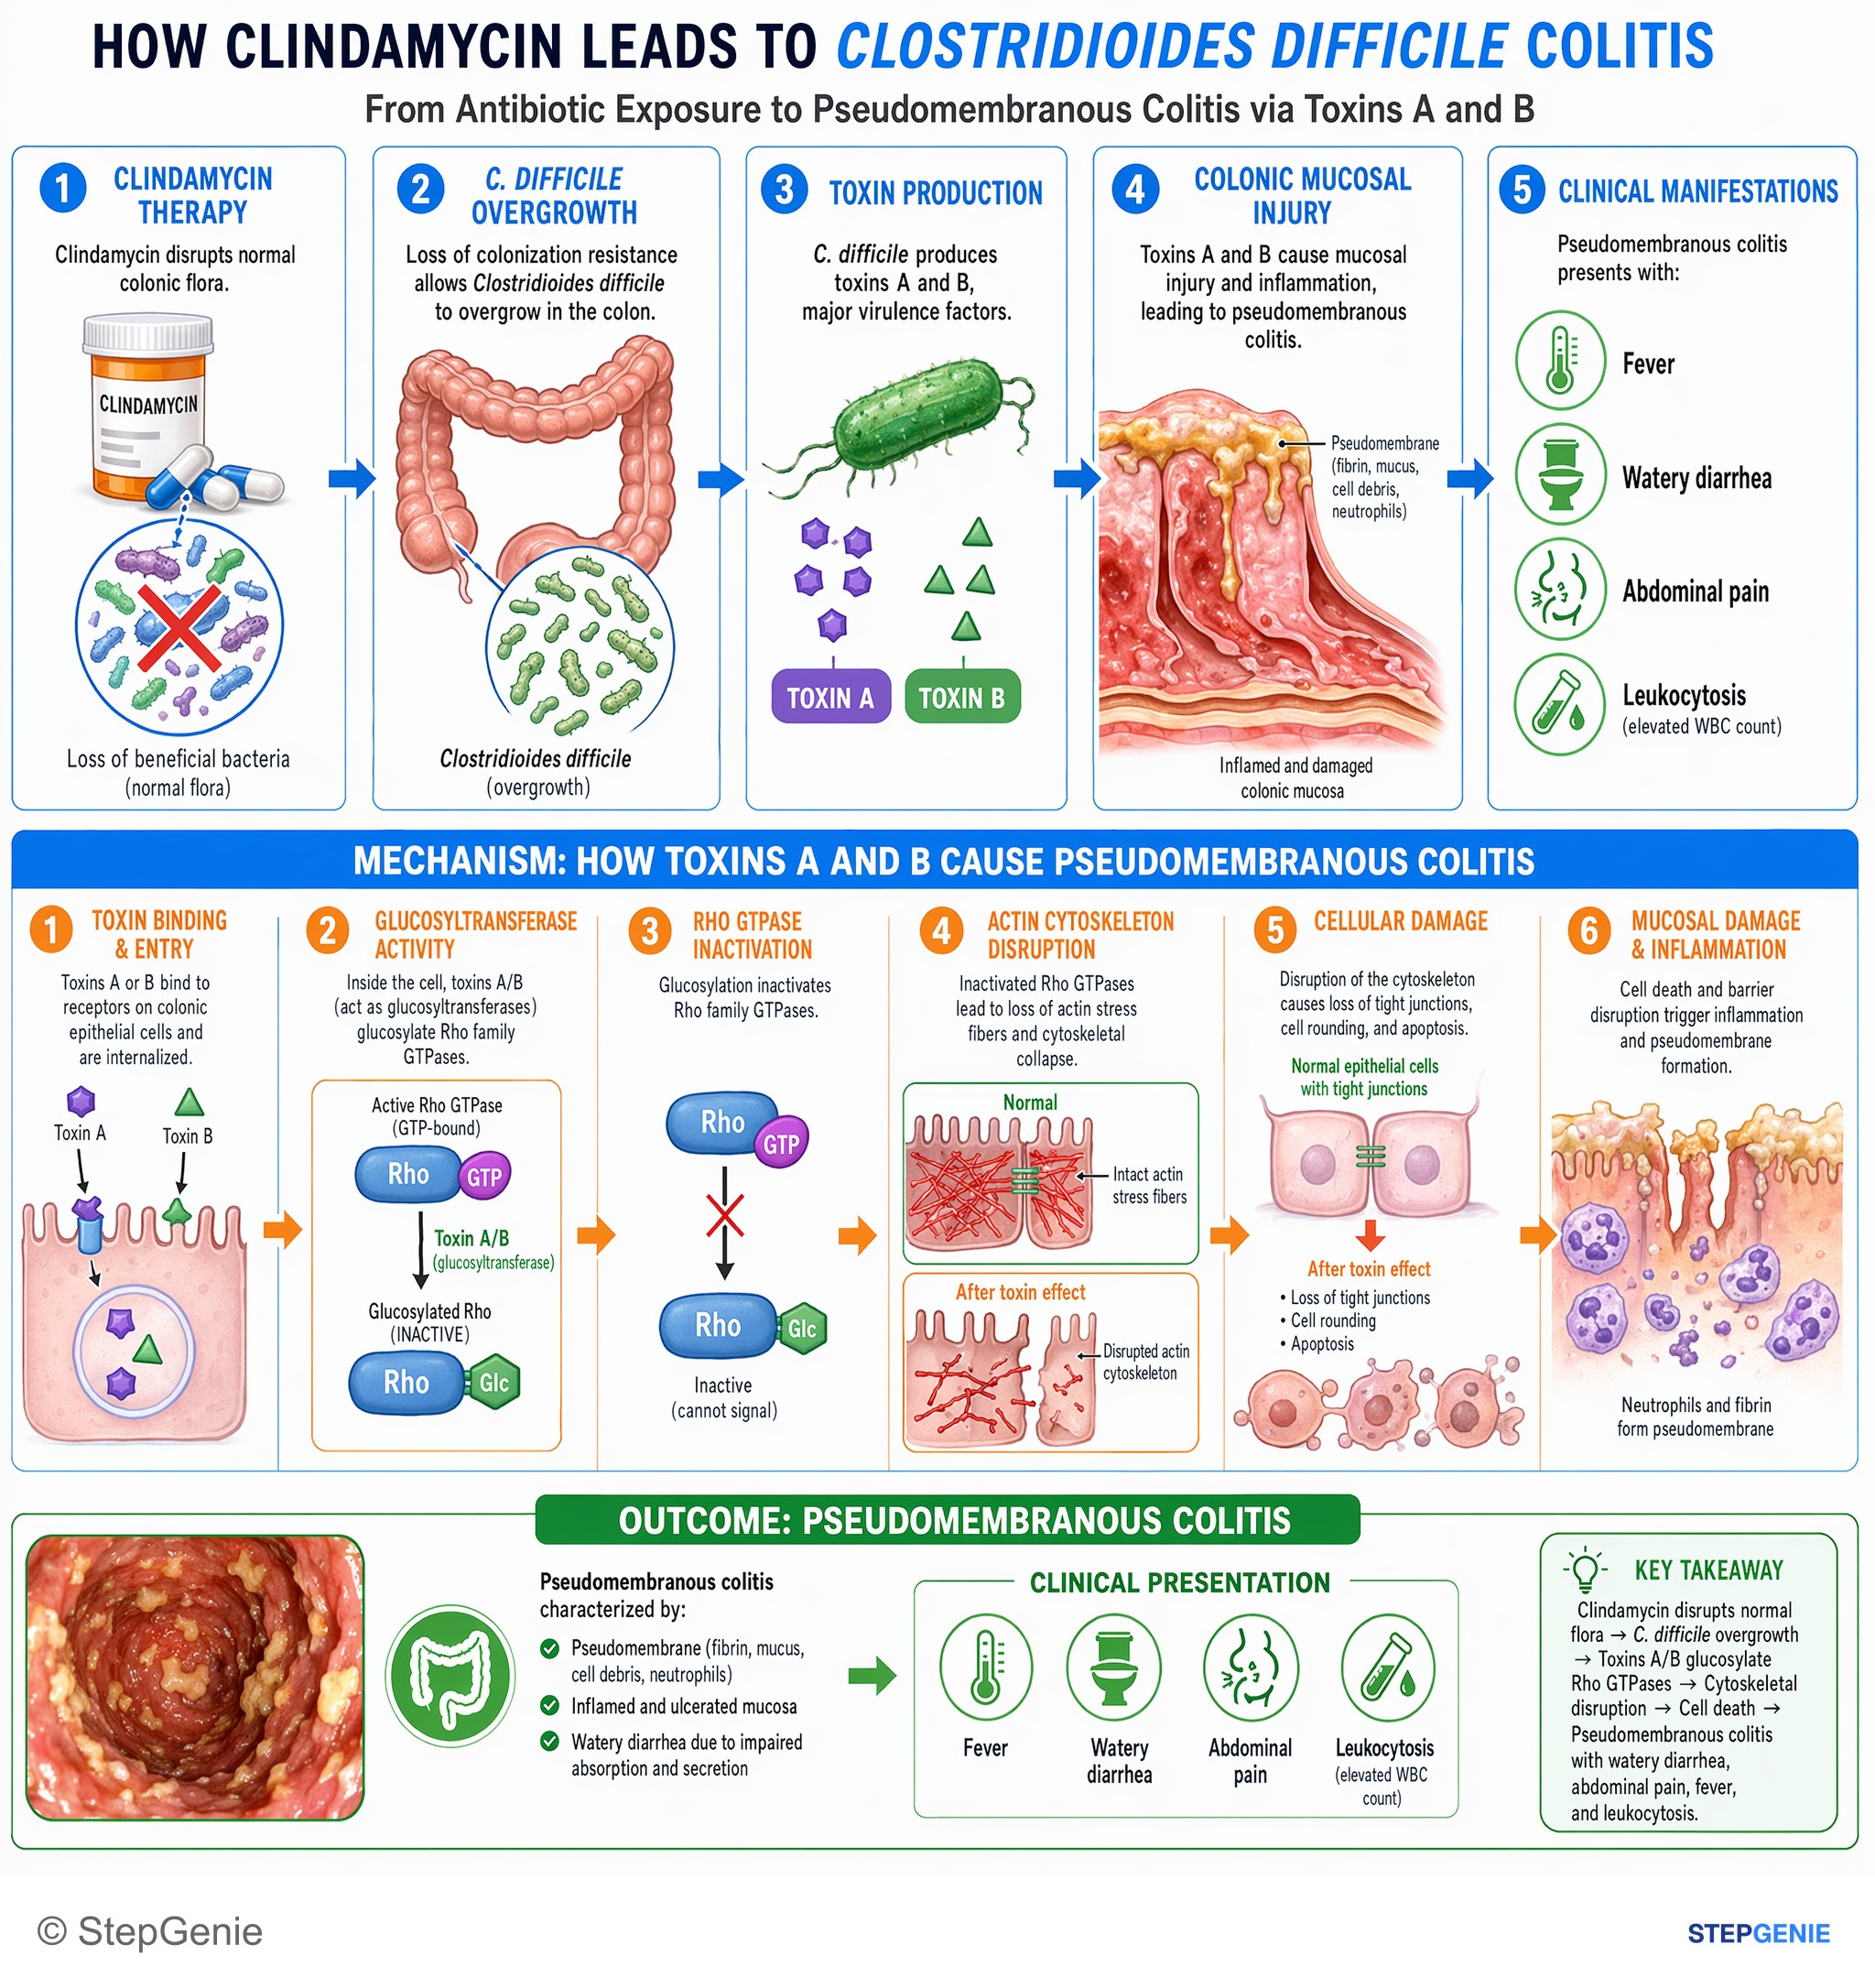
Clostridioides difficile colitis after clindamycin: toxins A/B glucosylate Rho GTPases, disrupting the cytoskeleton → cell death…
USMLE Step 1
Clostridioides difficile colitis, non-severe initial episode after clindamycin; treat with oral fidaxomicin (or oral vancomycin), not…
USMLE Step 2Frequently Asked Questions
Why does Clostridioides difficile cause watery diarrhea and pseudomembranous colitis after antibiotics?
Clostridioides difficile causes watery diarrhea and pseudomembranous colitis because antibiotic exposure disrupts normal gut flora, allowing this anaerobic, spore-forming gram-positive rod to overgrow and release toxins A and B. These toxins inactivate Rho GTPases by glucosylation, disrupting the actin cytoskeleton and tight junctions. The result is increased intestinal permeability, epithelial cell injury, neutrophilic inflammation, and in severe cases pseudomembrane formation.
How do C. difficile toxins A and B damage the colon?
C. difficile toxins A and B damage the colon by inactivating Rho GTPases through glucosylation. This leads to actin cytoskeleton disruption, loss of tight junction integrity, increased intestinal permeability, cell rounding and death, and neutrophilic inflammation. That toxin-mediated epithelial injury explains the classic clinical picture of watery diarrhea, colitis, and, in more severe disease, pseudomembranes.
What are pseudomembranes in C. difficile colitis?
Pseudomembranes in C. difficile colitis are adherent inflammatory exudates made of fibrin, mucus, necrotic epithelial cells, and neutrophils. On colonoscopy they appear as raised yellow-white plaques. They are called pseudomembranes because they are exudate sitting on injured mucosa rather than a true mucosal membrane, which is an important contrast point for exam questions.
How is C. difficile diagnosed on Step-style questions?
C. difficile is suspected in a patient with new-onset diarrhea after antibiotics or during hospitalization, especially with leukocytosis and abdominal symptoms. Common tests include NAAT or PCR for toxin genes, toxin A/B enzyme immunoassay, and GDH antigen testing with confirmatory studies. A key testing principle is not to test asymptomatic patients, because colonization can occur without active toxin-mediated disease.
What is the first-line treatment for C. difficile infection?
First-line treatment for most C. difficile infections is oral vancomycin or fidaxomicin, along with stopping the inciting antibiotic if possible and supporting hydration and electrolytes. In severe or fulminant disease, treatment escalates to high-dose oral vancomycin, with rectal vancomycin if ileus is present, plus IV metronidazole as an adjunct. Anti-motility drugs should be avoided in suspected severe colitis.