Neisseria meningitidis is one of those “know-it-cold” Step organisms: it shows up in stems about dorms, military recruits, asplenia, petechiae/purpura, and a rapidly crashing patient. Here are 3 quick, high-yield tips you can screenshot and keep moving.
Tip 1: Spot it fast — “Coffee bean diplococci that live in crowds”
Visual / mnemonic device
Picture two coffee beans wearing backpacks in a crowded dorm hallway.
One-liner
N. meningitidis = gram-negative, kidney-shaped diplococci that colonize the nasopharynx and spread via respiratory droplets in close quarters.
USMLE high-yield hits
- Gram-negative diplococci, often intracellular in neutrophils on smear.
- Oxidase-positive.
- Ferments maltose AND glucose
- (Contrast: N. gonorrhoeae ferments glucose only.)
- Humans only reservoir; nasopharyngeal carriage is common.
- Classic epidemiology: college dorms, military barracks, daycare, close-contact outbreaks.
Tip 2: The “Big 3” disease patterns — meningitis, meningococcemia, Waterhouse-Friderichsen
Visual / mnemonic device
Think “3 M’s + 1 adrenal meltdown”:
- Meningitis
- Meningococcemia
- Massive purpura (purpura fulminans/DIC)
- Adrenal hemorrhage (Waterhouse-Friderichsen)
One-liner
Its LOS endotoxin can trigger fulminant septic shock with petechiae/purpura, DIC, and bilateral adrenal hemorrhage.
USMLE high-yield hits
- Rapid onset fever + headache + nuchal rigidity → meningitis.
- Petechial rash that can progress to purpura fulminans is a huge clue.
- LOS (lipooligosaccharide) acts like endotoxin → cytokine surge → shock + DIC.
- Waterhouse-Friderichsen syndrome: bilateral adrenal hemorrhage → acute adrenal insufficiency + shock.
- Lumbar puncture for bacterial meningitis usually shows:
- ↑ neutrophils, ↑ protein, ↓ glucose, ↑ opening pressure.
Tip 3: Prevent the catastrophe — capsule, asplenia risk, vaccine + prophylaxis
Visual / mnemonic device
Imagine the organism wearing a clear “capsule cloak” and a spleen acting like a security guard. If the guard is gone (asplenia), the cloaked bug gets in easily.
One-liner
The polysaccharide capsule is the virulence key—patients with asplenia or complement (C5–C9) deficiency are at high risk, and close contacts need prophylaxis.
USMLE high-yield hits
- Polysaccharide capsule (major virulence factor)
- Helps evade phagocytosis; important for invasive disease.
- Risk groups
- Asplenia (including sickle cell functional asplenia)
- Terminal complement (C5–C9) deficiency → recurrent Neisseria infections
- Vaccines
- MenACWY (capsular serogroups) is standard for adolescents and high-risk groups.
- MenB vaccine for certain high-risk patients/outbreak settings.
- Post-exposure prophylaxis (close contacts)
- Rifampin or ciprofloxacin (commonly tested)
- Ceftriaxone is also used (e.g., pregnancy considerations).
- Treatment (active infection)
- Empiric bacterial meningitis regimens often include ceftriaxone/cefotaxime (plus age/risk-based additions like vancomycin/ampicillin depending on scenario).
- Narrow once organism identified and susceptibilities known.
15-second recap (what to blurt out on test day)
- GN diplococci, oxidase+, maltose + glucose; droplet spread, dorms/military.
- LOS endotoxin → petechiae/purpura, shock, DIC, Waterhouse-Friderichsen.
- Capsule is key; risk ↑ with asplenia and C5–C9 deficiency; vaccinate + prophylax close contacts.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
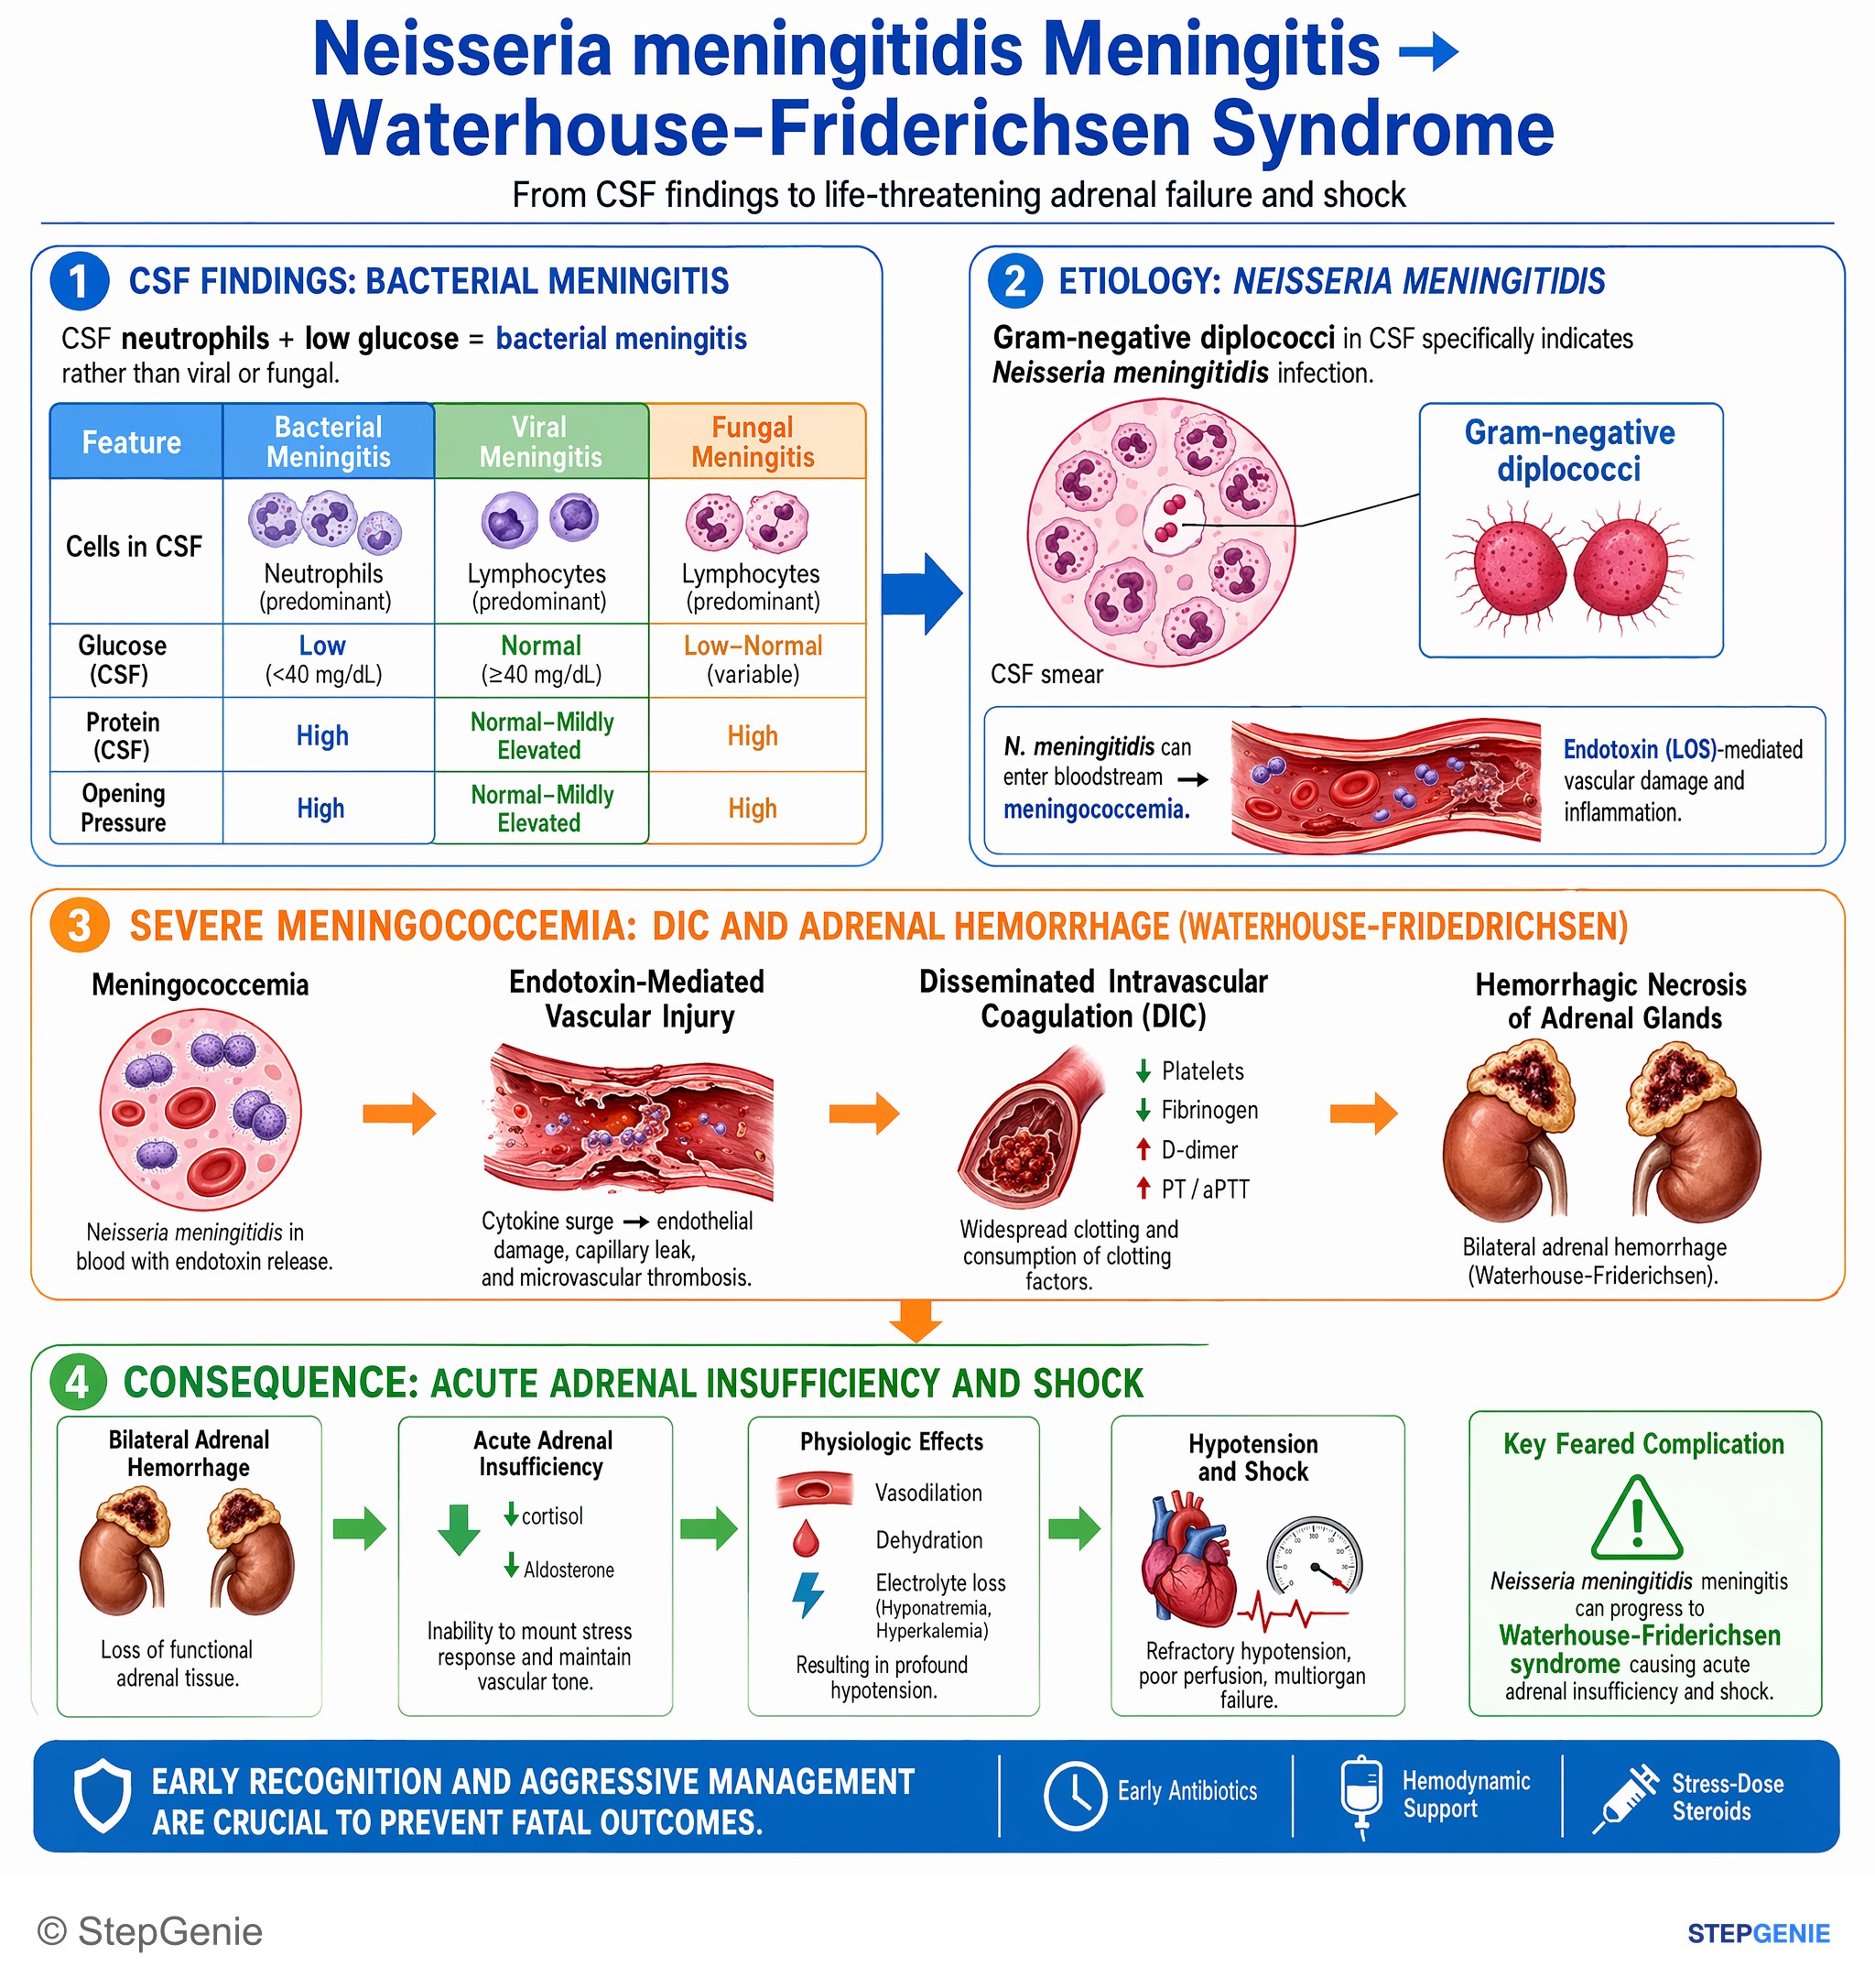
Neisseria meningitidis meningitis can progress to Waterhouse-Friderichsen syndrome (bilateral adrenal hemorrhage) causing acute adrenal…
USMLE Step 1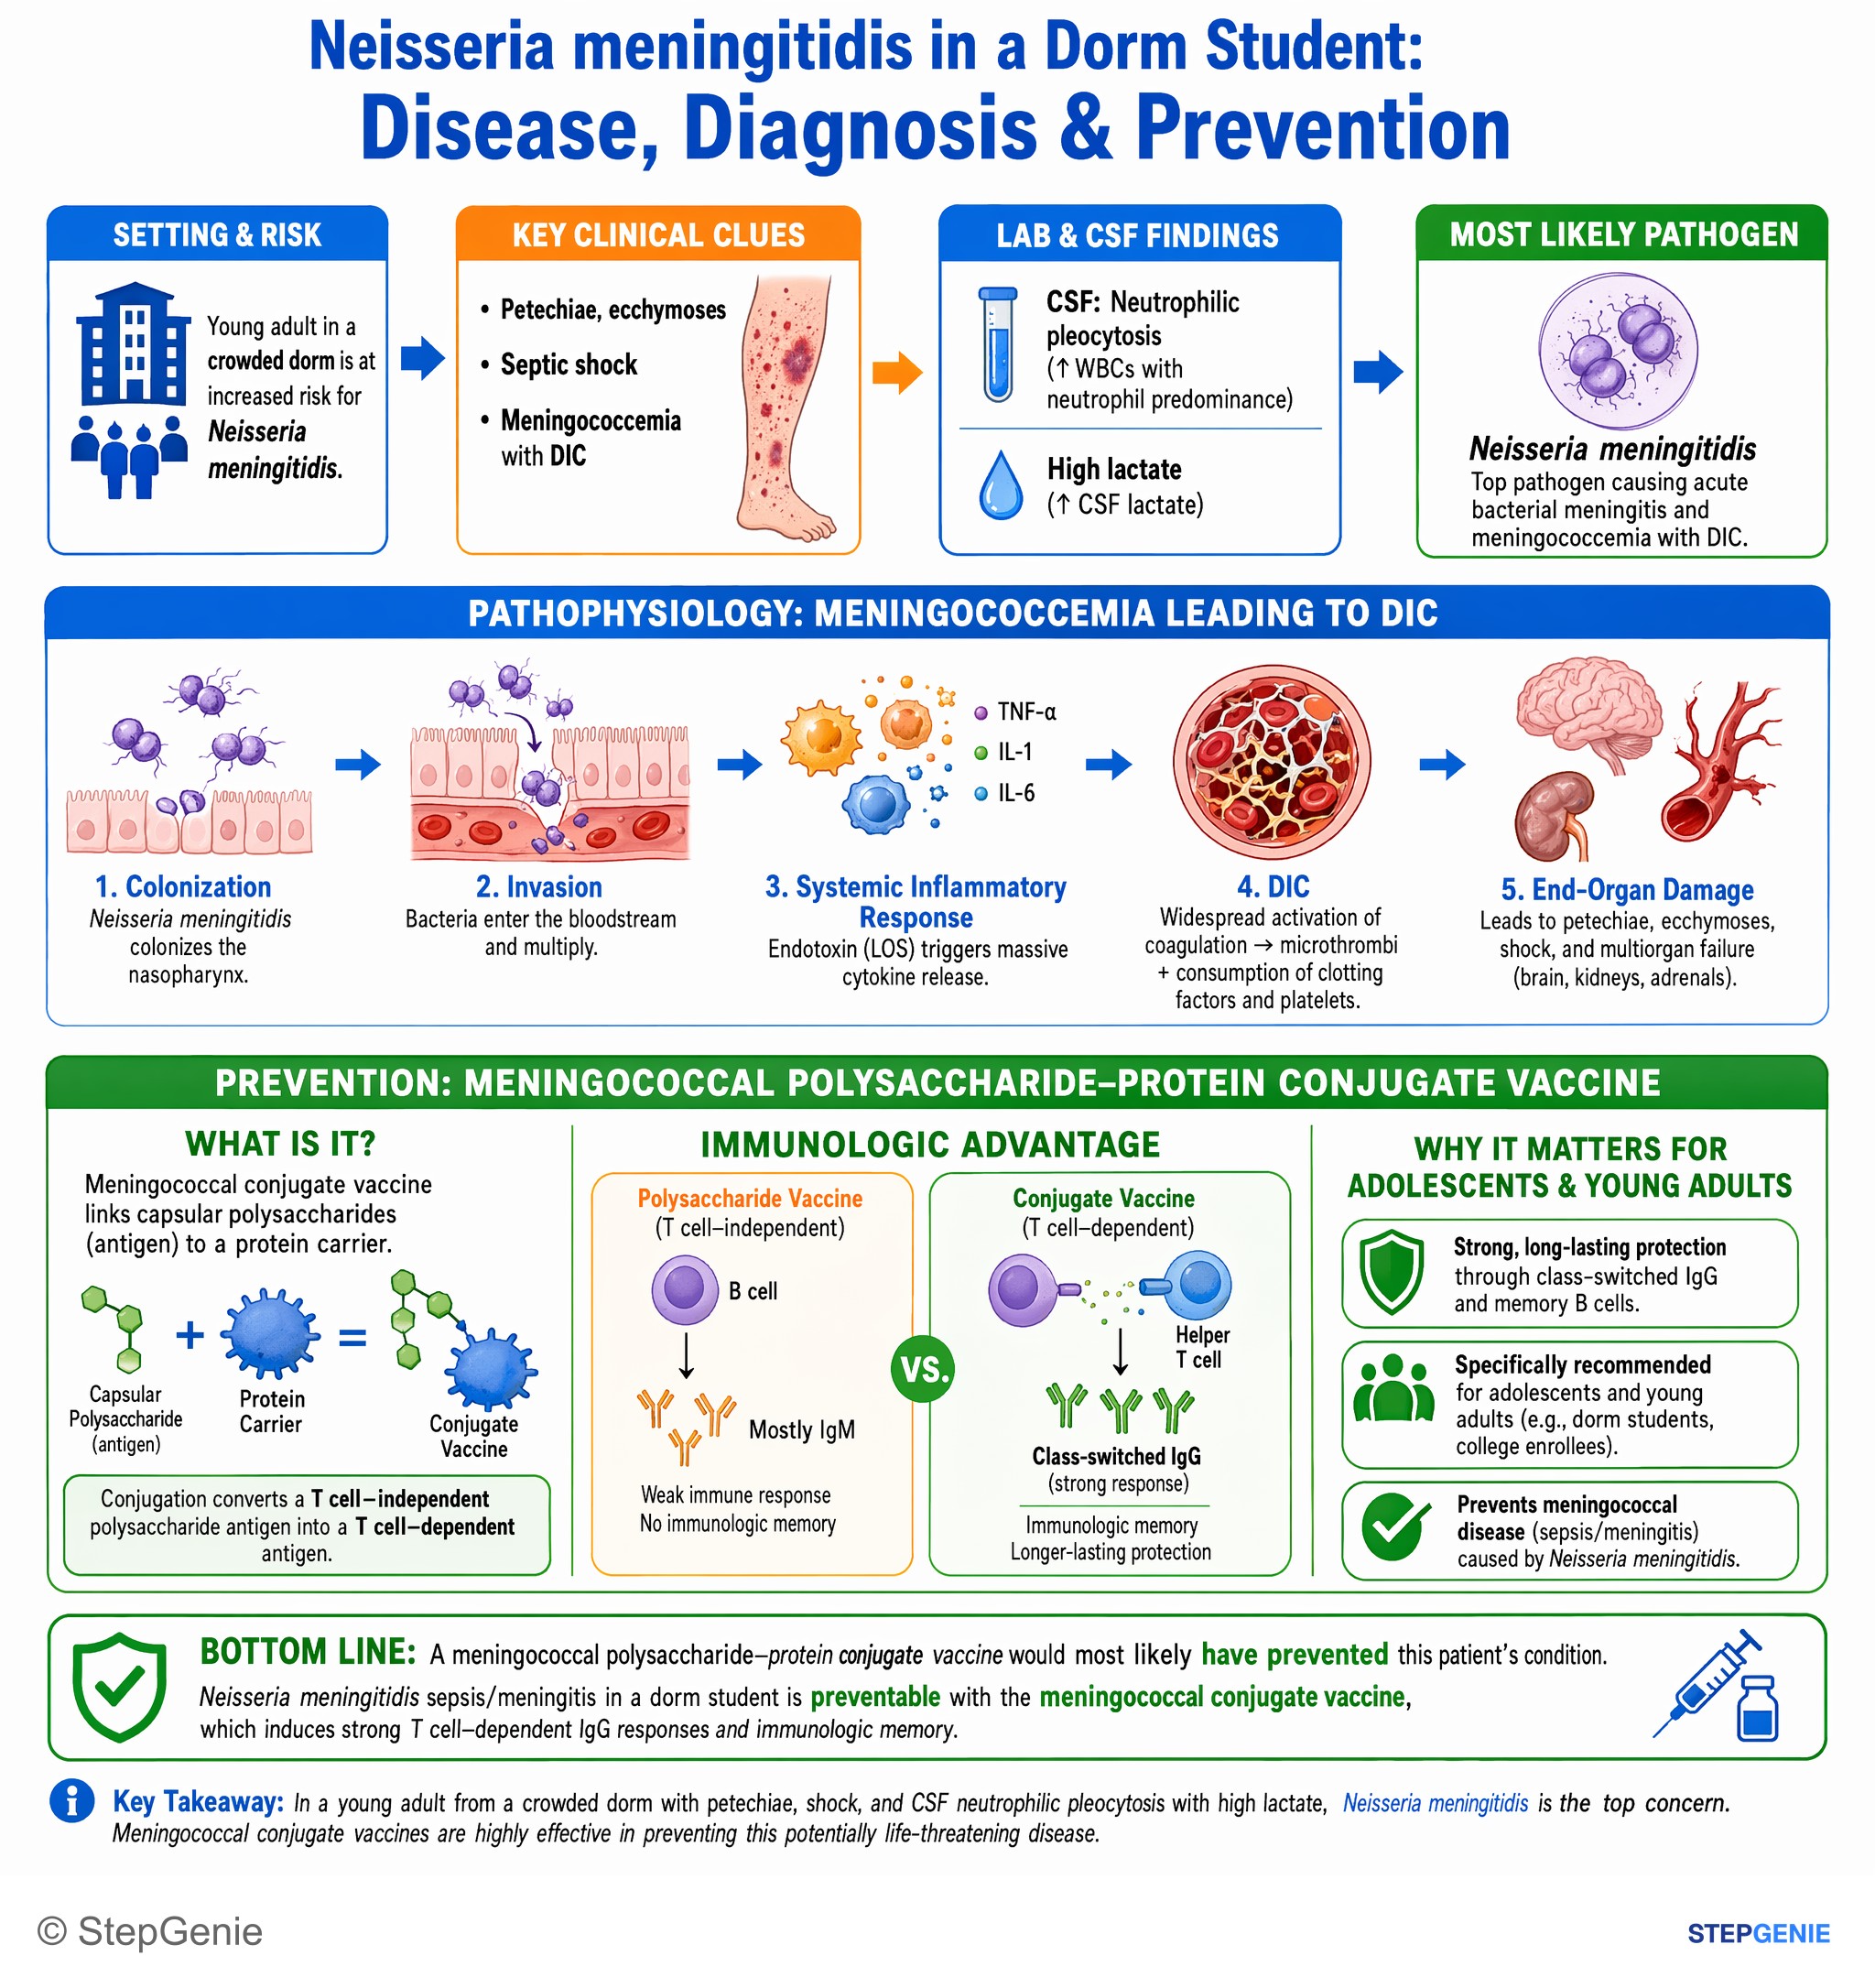
Neisseria meningitidis sepsis/meningitis in a dorm student is prevented by meningococcal polysaccharide–protein conjugate vaccine (induces…
USMLE Step 1Frequently Asked Questions
How do you tell Neisseria meningitidis from Neisseria gonorrhoeae on microbiology questions?
Neisseria meningitidis is distinguished by fermenting both maltose and glucose, whereas Neisseria gonorrhoeae ferments glucose only. N. meningitidis is also a gram-negative, kidney-shaped diplococcus that is often intracellular in neutrophils, is oxidase-positive, and classically appears in close-contact outbreak settings like dorms, military barracks, and daycare.
Why does Neisseria meningitidis cause petechiae, purpura, shock, and DIC?
Neisseria meningitidis causes these findings because its LOS acts as an endotoxin that triggers a cytokine surge. That inflammatory cascade can lead to fulminant septic shock and disseminated intravascular coagulation, which explains the classic petechial rash that may progress to purpura fulminans. This endotoxin-driven process is one of the key clinical clues for meningococcemia.
What is Waterhouse-Friderichsen syndrome in meningococcal infection?
Waterhouse-Friderichsen syndrome is bilateral adrenal hemorrhage caused by severe meningococcal infection. In Neisseria meningitidis disease, the endotoxin-mediated septic process can lead to shock and DIC, and one major complication is adrenal hemorrhage. The result is acute adrenal insufficiency along with shock, making it a classic emergency association with meningococcemia.
Why are patients with asplenia or C5-C9 deficiency at high risk for Neisseria meningitidis?
These patients are high risk because the polysaccharide capsule is the organism’s major virulence factor, and it helps Neisseria meningitidis evade phagocytosis and cause invasive disease. When splenic function is absent or reduced, as in asplenia or functional asplenia from sickle cell disease, protection is impaired. Terminal complement deficiency also predisposes to recurrent Neisseria infections.
What should you give close contacts of someone with Neisseria meningitidis?
Close contacts should receive post-exposure prophylaxis, typically rifampin or ciprofloxacin. Ceftriaxone is also used, including in situations such as pregnancy considerations. This is important because Neisseria meningitidis spreads through respiratory droplets and commonly causes outbreaks in close-contact settings like college dorms, military barracks, and daycare environments.