Molecular mimicry is autoimmunity that begins when a microbial antigen resembles a self antigen closely enough that the antibodies or T cells raised against the microbe also attack host tissue. The two USMLE classics are acute rheumatic fever, where immunity to group A streptococcal M protein and the group A carbohydrate (N-acetylglucosamine) cross-reacts with cardiac myosin, heart valves, synovium and basal ganglia neurons, and Guillain-Barré syndrome, where Campylobacter jejuni lipooligosaccharide mimics nerve gangliosides (GM1; GQ1b in the Miller Fisher variant). The trap to expect: post-streptococcal glomerulonephritis (PSGN) is not molecular mimicry but immune complex (type III) disease, with low C3 and granular deposits.
The Q-bank vignette
A 10-year-old girl is brought to the clinic because of fever and joint pain. Three weeks ago she had a sore throat and fever that went away without treatment. Over the past week her right knee, then her left ankle, then her left wrist became hot, swollen and very tender, each for a day or two. Temperature is 38.7°C (101.7°F). A soft holosystolic murmur is heard at the apex, radiating to the axilla. ECG shows a prolonged PR interval. ESR is 90 mm/h and the antistreptolysin O (ASO) titer is elevated. Serum C3 and urinalysis are normal.
Which mechanism best explains her cardiac findings?
- A. Deposition of circulating antigen–antibody complexes with complement activation
- B. Cross-reaction of antistreptococcal antibodies and T cells with cardiac proteins
- C. Direct streptococcal invasion of the mitral valve
- D. Nonspecific T-cell activation by a toxin bridging MHC class II and the T-cell receptor
- E. Exposure of a sequestered self antigen after tissue injury
Answer: B, molecular mimicry. This is acute rheumatic fever (ARF): two major Jones criteria (carditis, here new mitral regurgitation, and migratory polyarthritis), two minor criteria (fever ≥38.5°C and ESR ≥60 mm/h) and evidence of a recent group A strep infection (raised ASO). The prolonged PR interval fits, but under the 2015 Jones revision it cannot count as a minor criterion when carditis is already counted as a major one.
Why B is right: how mimicry damages the valve
- Antibodies start it. Antibodies against M protein and N-acetylglucosamine bind valve surface endothelium and exposed laminin in the basement membrane, inflaming the valve.
- T cells finish it. The inflamed endothelium expresses VCAM-1, which lets CD4+ T cells that cross-react with M protein and heart proteins enter the valve. They become Th1 cells making IFN-γ and drive valvular scarring (Cunningham, 2019).
- Where it hits: carditis occurs in about 50–70% of first attacks, mainly on the mitral and aortic valves. Acute lesions are regurgitant; the most common chronic lesion is mitral stenosis (compare the murmurs in the heart murmurs table). Aschoff bodies are the classic histology. As Merck puts it, ARF "licks the joints but bites the heart": the arthritis heals without damage, the valves scar.
- Why there is a delay: symptoms start about 2–3 weeks after the sore throat (CDC gives a 1–5-week range), consistent with an adaptive immune response rather than the infection itself. ASO titers peak 3–6 weeks after the infection, and about 80% of children with ARF have a clearly elevated ASO; adding anti-DNase B raises the yield.
- Why it recurs: after one attack, an untreated strep pharyngitis carries a recurrence risk approaching 50%. That is why secondary prophylaxis with benzathine penicillin G every 3–4 weeks follows: for 5 years or until age 21 (whichever is longer) without carditis, 10 years or until 21 with carditis but no residual damage, and longer with residual valve disease.
- Treating the attack: eradicate the strep (10 days of oral penicillin or amoxicillin, or one IM dose of benzathine penicillin G), give aspirin (naproxen is the best-studied alternative) for arthritis and mild carditis, and use oral prednisone instead for moderate-to-severe carditis.
Why every other answer choice is wrong
A. Immune complex deposition (type III). This is the mechanism of PSGN, the other post-strep complication. Complexes consume complement, so C3 is low, and the target is the glomerulus (cola-colored urine, RBC casts, edema, hypertension), not the valve. Her C3 and urinalysis are normal. Serum sickness is the systemic prototype of type III disease; see the serum sickness guide.
C. Direct streptococcal invasion (infective endocarditis). Endocarditis means organisms living on the valve, with positive blood cultures, infected vegetations and embolic phenomena. ARF is a nonsuppurative sequela: the strep infected the throat weeks earlier, and the valve damage is immunologic.
D. Superantigen. Toxins such as staphylococcal TSST-1 and streptococcal pyrogenic exotoxins bind MHC class II and the variable region of the TCR β chain outside the normal antigen-binding site, activating huge numbers of T cells without specific antigen recognition. The result is a cytokine storm (high fever, hypotension, shock, multiorgan failure) during the infection, not a targeted attack on one tissue weeks later.
E. Sequestered antigen release. Some self antigens are normally hidden from the immune system. When injury exposes them, autoimmunity can follow; the classic example is sympathetic ophthalmia, where trauma to one eye releases uveal antigens and inflammation affects both eyes. No microbe starts the response, so there is nothing to mimic.
Classic molecular mimicry examples
| Disease | Trigger | Microbial antigen | Host target | What you see |
|---|---|---|---|---|
| Rheumatic carditis | Group A strep pharyngitis | M protein; N-acetylglucosamine | Cardiac myosin, valve endothelium, laminin | Pancarditis; mitral and aortic regurgitation; later mitral stenosis |
| Rheumatic arthritis | Group A strep pharyngitis | M protein | Synovium | Migratory polyarthritis of large joints; heals without deformity |
| Sydenham chorea | Group A strep pharyngitis | N-acetylglucosamine | Lysoganglioside, tubulin, dopamine D1/D2 receptors on basal ganglia neurons | Chorea, "milkmaid's grip," often months after the infection |
| Guillain-Barré syndrome | Campylobacter jejuni enteritis | Lipooligosaccharide with GM1-like structures | Gangliosides (GM1) on peripheral nerve | Symmetric ascending flaccid weakness, lost reflexes |
| Miller Fisher syndrome | C. jejuni | GQ1b-like lipooligosaccharide | Ganglioside GQ1b | Ophthalmoparesis, ataxia, areflexia; anti-GQ1b antibodies in up to 90% (Leonhard et al., 2019) |
| Multiple sclerosis (research link) | Epstein-Barr virus | EBNA1 | GlialCAM, a CNS glial protein | A 2022 Nature study showed high-affinity cross-reactivity; a mechanism under study, not a settled cause |
The chorea-derived antibodies do more than bind: they signal through dopamine receptors and activate CaMKII, increasing dopamine release in the basal ganglia. Sydenham chorea appears in about 10–30% of children with ARF, and chorea alone fulfills the Jones criteria once other movement disorders are excluded. For the neuropathy, IVIG or plasma exchange are the treatments; corticosteroids do not help (more in the Guillain-Barré syndrome guide).
Rheumatic fever vs PSGN: same bug, different mechanism
| Feature | Acute rheumatic fever | Post-streptococcal GN |
|---|---|---|
| Mechanism | Molecular mimicry: cross-reactive antibodies and T cells | Immune complexes (type III) with complement activation |
| Preceding infection | Pharyngitis (classic teaching; CDC also includes skin infections such as impetigo) | Pharyngitis or skin infection (impetigo) |
| Latency | About 2–3 weeks | About 10 days after pharyngitis; up to 3 weeks after skin infection |
| Organs | Heart, joints, brain, skin | Kidney |
| Complement | Normal | Low C3 and CH50; normal again within 6–8 weeks in about 80% |
| Pathology | Aschoff bodies, valvulitis | Granular IgG and C3 on immunofluorescence; subepithelial humps on EM |
| Strep serology | ASO (plus anti-DNase B) | ASO after pharyngitis; anti-DNase B after skin infection, which often gives little ASO response |
| Does treating the strep prevent it? | Yes: antibiotics for strep throat reduce ARF risk | Unproven (CDC: insufficient evidence) |
| Outcome | Chronic rheumatic heart disease | More than 90% of children recover fully; adults fare worse |
Sources differ on skin infection: Merck states that nonpharyngitis group A strep infections do not lead to ARF, while CDC describes ARF as a delayed sequela of both pharyngitis and skin infections such as impetigo. On the exam, impetigo followed by nephritis means PSGN.
Worked example: the PSGN version
Vignette. A 7-year-old boy has puffy eyes and cola-colored urine. Three weeks ago he had crusted, honey-colored sores around his nose. Blood pressure is elevated for his age. Urinalysis shows RBC casts and mild proteinuria, C3 is low and anti-DNase B is elevated. What is the mechanism?
Answer: Immune complex deposition in the glomeruli (type III hypersensitivity), that is, PSGN after impetigo. Treatment is supportive (sodium and fluid restriction, control of edema and blood pressure) plus penicillin to clear any remaining strep.
Why not the others?
- Molecular mimicry: that is ARF, which spares the kidney and leaves complement normal.
- Anti-GBM antibodies (type II): antibodies against the α3 chain of type IV collagen give linear IgG staining, and often pulmonary hemorrhage as well as glomerulonephritis.
- IgA nephropathy: gross hematuria starts 1–2 days after a mucosal infection, with normal complement and mesangial IgA deposits.
The full nephritic differential is in the nephritic syndrome overview.
Mimicry vs look-alike mechanisms
| Mechanism | Antigen-specific? | Timing | Classic example |
|---|---|---|---|
| Molecular mimicry | Yes: the response to a microbe cross-reacts with self | Weeks after infection | ARF, GBS |
| Immune complex (type III) | Complexes are specific; the tissue is a bystander | Hours (Arthus) to days or weeks | PSGN, serum sickness, lupus |
| Type II autoantibody | Yes: antibody against a fixed self antigen | Variable | Anti-GBM disease, autoimmune hemolytic anemia |
| Superantigen | No: polyclonal T-cell activation | During the infection | Toxic shock syndrome |
| Sequestered antigen | Yes, but against self from the start | After tissue injury | Sympathetic ophthalmia |
Exam traps
- "Post-strep" does not mean mimicry. Heart, joints, chorea or skin findings with normal C3 point to ARF; nephritis with low C3 points to PSGN.
- Timing sorts the kidney cases: hematuria 1–2 days after a sore throat is IgA nephropathy; nephritis about 10 days to 3 weeks after a strep infection, with low C3, is PSGN.
- Molecular mimicry is a way of breaking tolerance, not a fifth hypersensitivity type. The damage is done by cross-reactive antibodies (type II-like) and T cells (type IV-like); review books usually file ARF under type II.
- Chorea can be the only sign and can appear months after the sore throat.
Key takeaways
- Molecular mimicry = a microbial antigen resembles self, so antibodies or T cells against the microbe attack host tissue, typically weeks after the infection.
- Acute rheumatic fever: group A strep M protein and N-acetylglucosamine vs cardiac myosin, valve endothelium, synovium and basal ganglia neurons; mitral valve most affected; complement normal.
- Guillain-Barré syndrome: C. jejuni lipooligosaccharide vs nerve gangliosides (GM1; GQ1b in Miller Fisher).
- PSGN is not mimicry: it is type III immune complex disease with low C3, granular deposits and subepithelial humps, after throat or skin infection.
- Prevention differs: treating strep throat reduces ARF risk, and benzathine penicillin G prophylaxis prevents recurrences; antibiotics have not been shown to prevent PSGN.
Sources
- Rheumatic Fever — Merck Manual Professional Edition
- Cunningham MW. Molecular Mimicry, Autoimmunity, and Infection: The Cross-Reactive Antigens of Group A Streptococci and their Sequelae — Microbiology Spectrum (2019)
- Diagnosing Acute Rheumatic Fever (2015 Jones criteria) — CDC
- Clinical Guidance for Acute Rheumatic Fever — CDC
- Postinfectious Glomerulonephritis (PIGN) — Merck Manual Professional Edition
- Clinical Guidance for Post-Streptococcal Glomerulonephritis — CDC
- Immunoglobulin A Nephropathy — Merck Manual Professional Edition
- Autoimmune Disorders — Merck Manual Professional Edition
- Leonhard SE, et al. Diagnosis and management of Guillain–Barré syndrome in ten steps — Nature Reviews Neurology (2019)
- Ang CW, et al. Structure of Campylobacter jejuni Lipopolysaccharides Determines Antiganglioside Specificity and Clinical Features of Guillain-Barré and Miller Fisher Patients — Infection and Immunity (2002)
- Lanz TV, et al. Clonally expanded B cells in multiple sclerosis bind EBV EBNA1 and GlialCAM — Nature (2022)
- T Lymphocytes and Cellular Immunity (superantigens) — OpenStax Microbiology
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
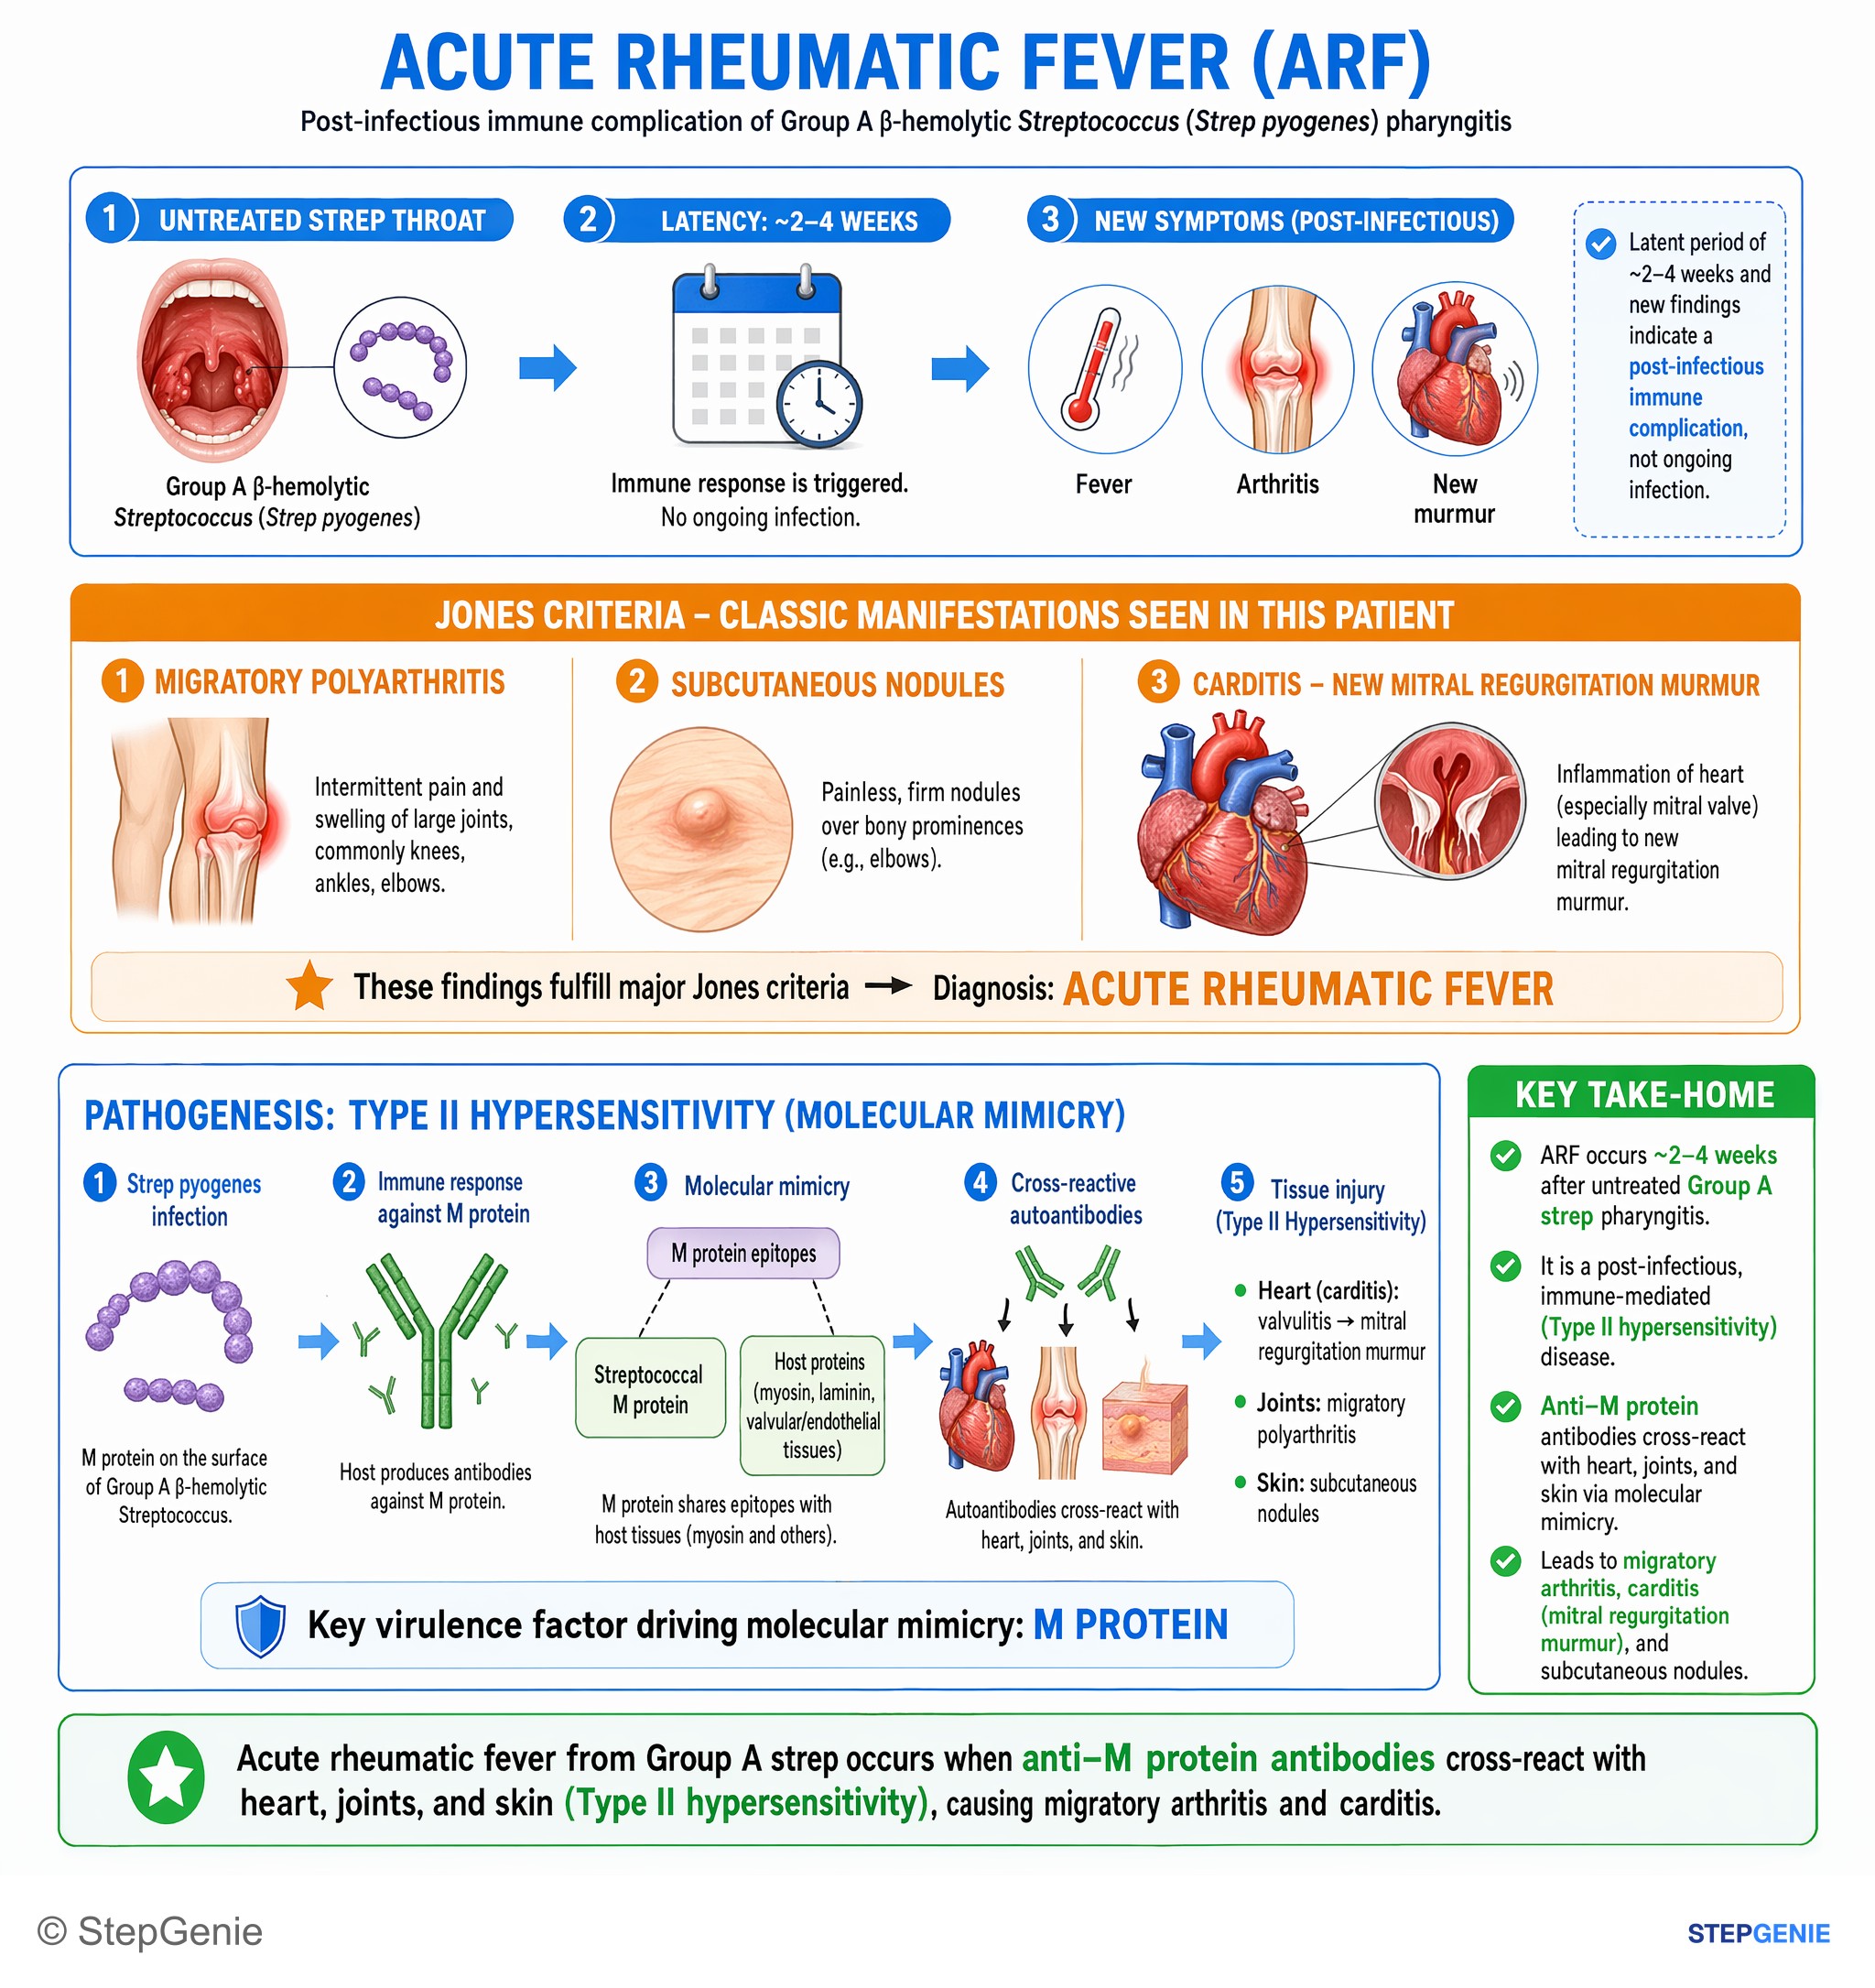
Acute rheumatic fever from group A strep: anti–M protein antibodies cross-react with heart, joints, skin (type II hypersensitivity)…
USMLE Step 1Frequently Asked Questions
What is molecular mimicry?
Molecular mimicry is a mechanism of autoimmunity in which a microbial antigen shares sequence or structural features with a self antigen. Antibodies or T cells made against the infection then cross-react with host tissue, usually weeks after the infection. Acute rheumatic fever after group A strep pharyngitis and Guillain-Barré syndrome after Campylobacter jejuni infection are the classic examples.
What are examples of molecular mimicry?
In acute rheumatic fever, antibodies and T cells against group A streptococcal M protein and N-acetylglucosamine cross-react with cardiac myosin, heart valves, joints and basal ganglia neurons. In Guillain-Barré syndrome, Campylobacter jejuni lipooligosaccharide mimics nerve gangliosides such as GM1, and GQ1b in the Miller Fisher variant. Research also links Epstein-Barr virus EBNA1 to the brain protein GlialCAM in multiple sclerosis, but that mechanism is still under study.
Is post-streptococcal glomerulonephritis caused by molecular mimicry?
No. Post-streptococcal glomerulonephritis is an immune complex (type III hypersensitivity) disease: streptococcal antigens and antibodies deposit in the glomeruli and activate complement, so C3 is low and immunofluorescence shows granular IgG and C3. It can follow a throat or skin infection. Molecular mimicry is the mechanism of acute rheumatic fever, which spares the kidney and leaves complement normal.
What type of hypersensitivity is rheumatic fever?
Rheumatic fever results from molecular mimicry and is usually taught as a type II, antibody-mediated reaction, because cross-reactive antibodies bind antigens fixed in heart tissue such as valve endothelium. Cross-reactive CD4+ Th1 cells then enter the valve and drive scarring, so a cell-mediated component contributes as well. Complement levels stay normal, unlike in immune complex disease.
How is molecular mimicry different from a superantigen?
In molecular mimicry, specific antibodies or T cells raised against a microbial antigen cross-react with a similar self antigen, causing targeted organ damage weeks after the infection. A superantigen, such as staphylococcal TSST-1 or a streptococcal pyrogenic exotoxin, binds MHC class II and the T-cell receptor beta chain outside the antigen-binding site and activates huge numbers of T cells regardless of their specificity. The result is a cytokine storm with fever, hypotension and shock during the infection itself.
Why does rheumatic fever need long-term penicillin prophylaxis?
After a first attack, a new untreated group A strep pharyngitis carries a recurrence risk approaching 50 percent, and each recurrence can damage the valves further. Secondary prophylaxis with benzathine penicillin G every 3 to 4 weeks prevents new infections. Merck advises continuing it for 5 years or until age 21 without carditis, 10 years or until age 21 after carditis without residual damage, and longer when valve disease persists.