You’re cruising through a Q-bank and you hit a question on immune tolerance—and suddenly every answer choice sounds kind of right. That’s not accidental: tolerance is a “web concept” in immunology where central vs peripheral, T vs B cells, and autoimmunity vs transplant all overlap. The quickest way to stop losing points is to learn how to prove the correct answer and disprove every distractor.
Tag: Immunology > Transplant & Autoimmune
The Clinical Vignette (Q-bank style)
A 28-year-old woman with a history of autoimmune thyroid disease receives a kidney transplant from a deceased donor. She is started on tacrolimus, mycophenolate mofetil, and prednisone. Six months later, she is clinically well. Labs show stable creatinine. A research team evaluates her immune profile and finds that recipient T cells specific for donor HLA are present but demonstrate poor proliferative response to donor antigen stimulation in vitro. The team also notes increased expression of CTLA-4 and expansion of CD4+ FOXP3+ T cells.
Which mechanism best explains this patient’s reduced T-cell response to donor antigens?
A. Deletion of autoreactive T cells in the thymic medulla via AIRE
B. Induction of T-cell anergy due to absent costimulation (B7–CD28 signaling)
C. Class switching of donor-specific B cells to IgG4
D. Hypermutation-driven affinity maturation in germinal centers
E. Complement-mediated lysis of donor antigen-presenting cells
The Correct Answer: B. Induction of T-cell anergy due to absent costimulation
This vignette points to peripheral tolerance, not central tolerance. The key clue is that donor-specific T cells still exist but are functionally “turned off” (poor proliferation). Add in the CTLA-4 mention and you’re being steered toward loss of costimulation.
Why anergy fits best
Naive T cells require two signals to activate:
- Signal 1: TCR recognizes peptide–MHC on APC
- Signal 2 (costimulation): B7 (CD80/86) on APC binds CD28 on T cell
If Signal 1 occurs without Signal 2, the T cell becomes anergic (functionally unresponsive), which is a major mechanism of peripheral tolerance.
How CTLA-4 locks this in
- CTLA-4 is an inhibitory receptor on T cells (especially Tregs) that binds B7 with higher affinity than CD28.
- When CTLA-4 engages B7, it reduces IL-2 production and T-cell proliferation.
High-yield tie-in:
- Abatacept / Belatacept are CTLA-4–Ig fusion proteins that bind B7 and block costimulation, used clinically to prevent transplant rejection.
“Why Every Answer Choice Matters”: Systematic Distractor Breakdown
A. Deletion of autoreactive T cells in the thymic medulla via AIRE (Central tolerance)
This is real—but it doesn’t match the scenario.
What AIRE actually does:
- Expresses peripheral tissue antigens in the thymus
- Promotes negative selection (apoptosis) of self-reactive T cells in the medulla
Why it’s wrong here:
- AIRE is about tolerance to self, not donor antigens.
- Central tolerance happens during T-cell development, not “6 months after transplant.”
- The stem of the question tells you donor-reactive T cells are present, suggesting they were not deleted.
Step 1 association: AIRE mutation → APECED (chronic mucocutaneous candidiasis, hypoparathyroidism, adrenal insufficiency).
C. Class switching of donor-specific B cells to IgG4
Class switching is important in humoral immunity, allergy, and some chronic antigen exposure settings—but this doesn’t explain poor T-cell proliferation to donor HLA.
High-yield facts:
- Class switching requires T-cell help (CD40–CD40L + cytokines).
- IgG4 is often associated with chronic antigen exposure and certain fibroinflammatory diseases (IgG4-related disease), not classic transplant tolerance.
Why it’s wrong here:
- The vignette’s key data are T-cell functional unresponsiveness plus CTLA-4/Treg signals.
- Donor-specific antibody biology matters in transplant (antibody-mediated rejection), but that’s not what’s being tested.
D. Hypermutation-driven affinity maturation in germinal centers
This is a frequent distractor because it sounds “immunology-smart,” but it’s the wrong compartment and wrong mechanism.
What it really is:
- Somatic hypermutation in germinal centers (AID enzyme)
- Produces higher-affinity antibodies
- Happens in B cells, not T cells
Why it’s wrong here:
- Affinity maturation increases the effectiveness of antibodies; it does not cause T-cell anergy.
- The clinical stem is pointing you to T-cell tolerance, not improved antibody binding.
Step 1 reminder: AID deficiency → Hyper-IgM syndrome type 2 (no class switching, no affinity maturation).
E. Complement-mediated lysis of donor antigen-presenting cells
Complement is a killer pathway, but it’s not a physiologic tolerance mechanism—if anything, complement activation tends to amplify inflammation and graft injury.
High-yield transplant tie-in:
- Hyperacute rejection: preformed IgG against donor ABO/HLA → complement activation → thrombosis/necrosis (minutes to hours)
- Antibody-mediated (humoral) rejection: C4d deposition, endothelial injury
Why it’s wrong here:
- She’s stable at 6 months with signs of immune quiescence, not acute inflammatory destruction.
- Complement lysis of APCs isn’t the classic explanation for donor-specific T-cell hyporesponsiveness.
The Bigger Concept: Central vs Peripheral Tolerance (Rapid Table)
| Feature | Central tolerance | Peripheral tolerance |
|---|---|---|
| Where | Thymus (T), bone marrow (B) | Peripheral tissues/lymph nodes |
| Target | Self-reactive lymphocytes | Self-reactive or persistently stimulated lymphocytes |
| Main mechanisms | Negative selection (apoptosis), receptor editing (B cells) | Anergy, deletion, Treg suppression |
| Classic buzzwords | AIRE, negative selection | CTLA-4, PD-1, FOXP3 Tregs, costimulation |
How This Shows Up on USMLE (High-Yield Patterns)
Pattern 1: “Signal 1 without Signal 2”
If they describe antigen recognition but absent costimulation → Anergy
- Missing B7 on APC (immature/resting APC)
- Blocking B7–CD28 (e.g., belatacept)
Pattern 2: “FOXP3+ Tregs increased”
Think immune suppression/tolerance, via:
- IL-10, TGF-β secretion
- CTLA-4–mediated inhibition of costimulation
- Suppression of effector T-cell activation
Step 1 association: FOXP3 mutation → IPEX (immune dysregulation, polyendocrinopathy, enteropathy; eczema, diabetes, diarrhea).
Pattern 3: PD-1 / checkpoint inhibitors
If they mention PD-1/PD-L1 or CTLA-4 blockade:
- Blocking checkpoints (ipilimumab, nivolumab, pembrolizumab) → increased T-cell activity → autoimmune-like toxicities
- Not tolerance; it’s the opposite.
Quick Takeaways (What to Remember Under Time Pressure)
- Anergy = Signal 1 without Signal 2 (B7–CD28 absent or blocked).
- CTLA-4 is inhibitory and competes with CD28 for B7 → decreased T-cell activation.
- AIRE = central tolerance (thymic negative selection to self-antigens).
- Germinal center processes (class switch, somatic hypermutation) are B-cell antibody optimization, not T-cell tolerance.
- Complement activation is usually a clue for antibody-mediated transplant injury, not tolerance.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
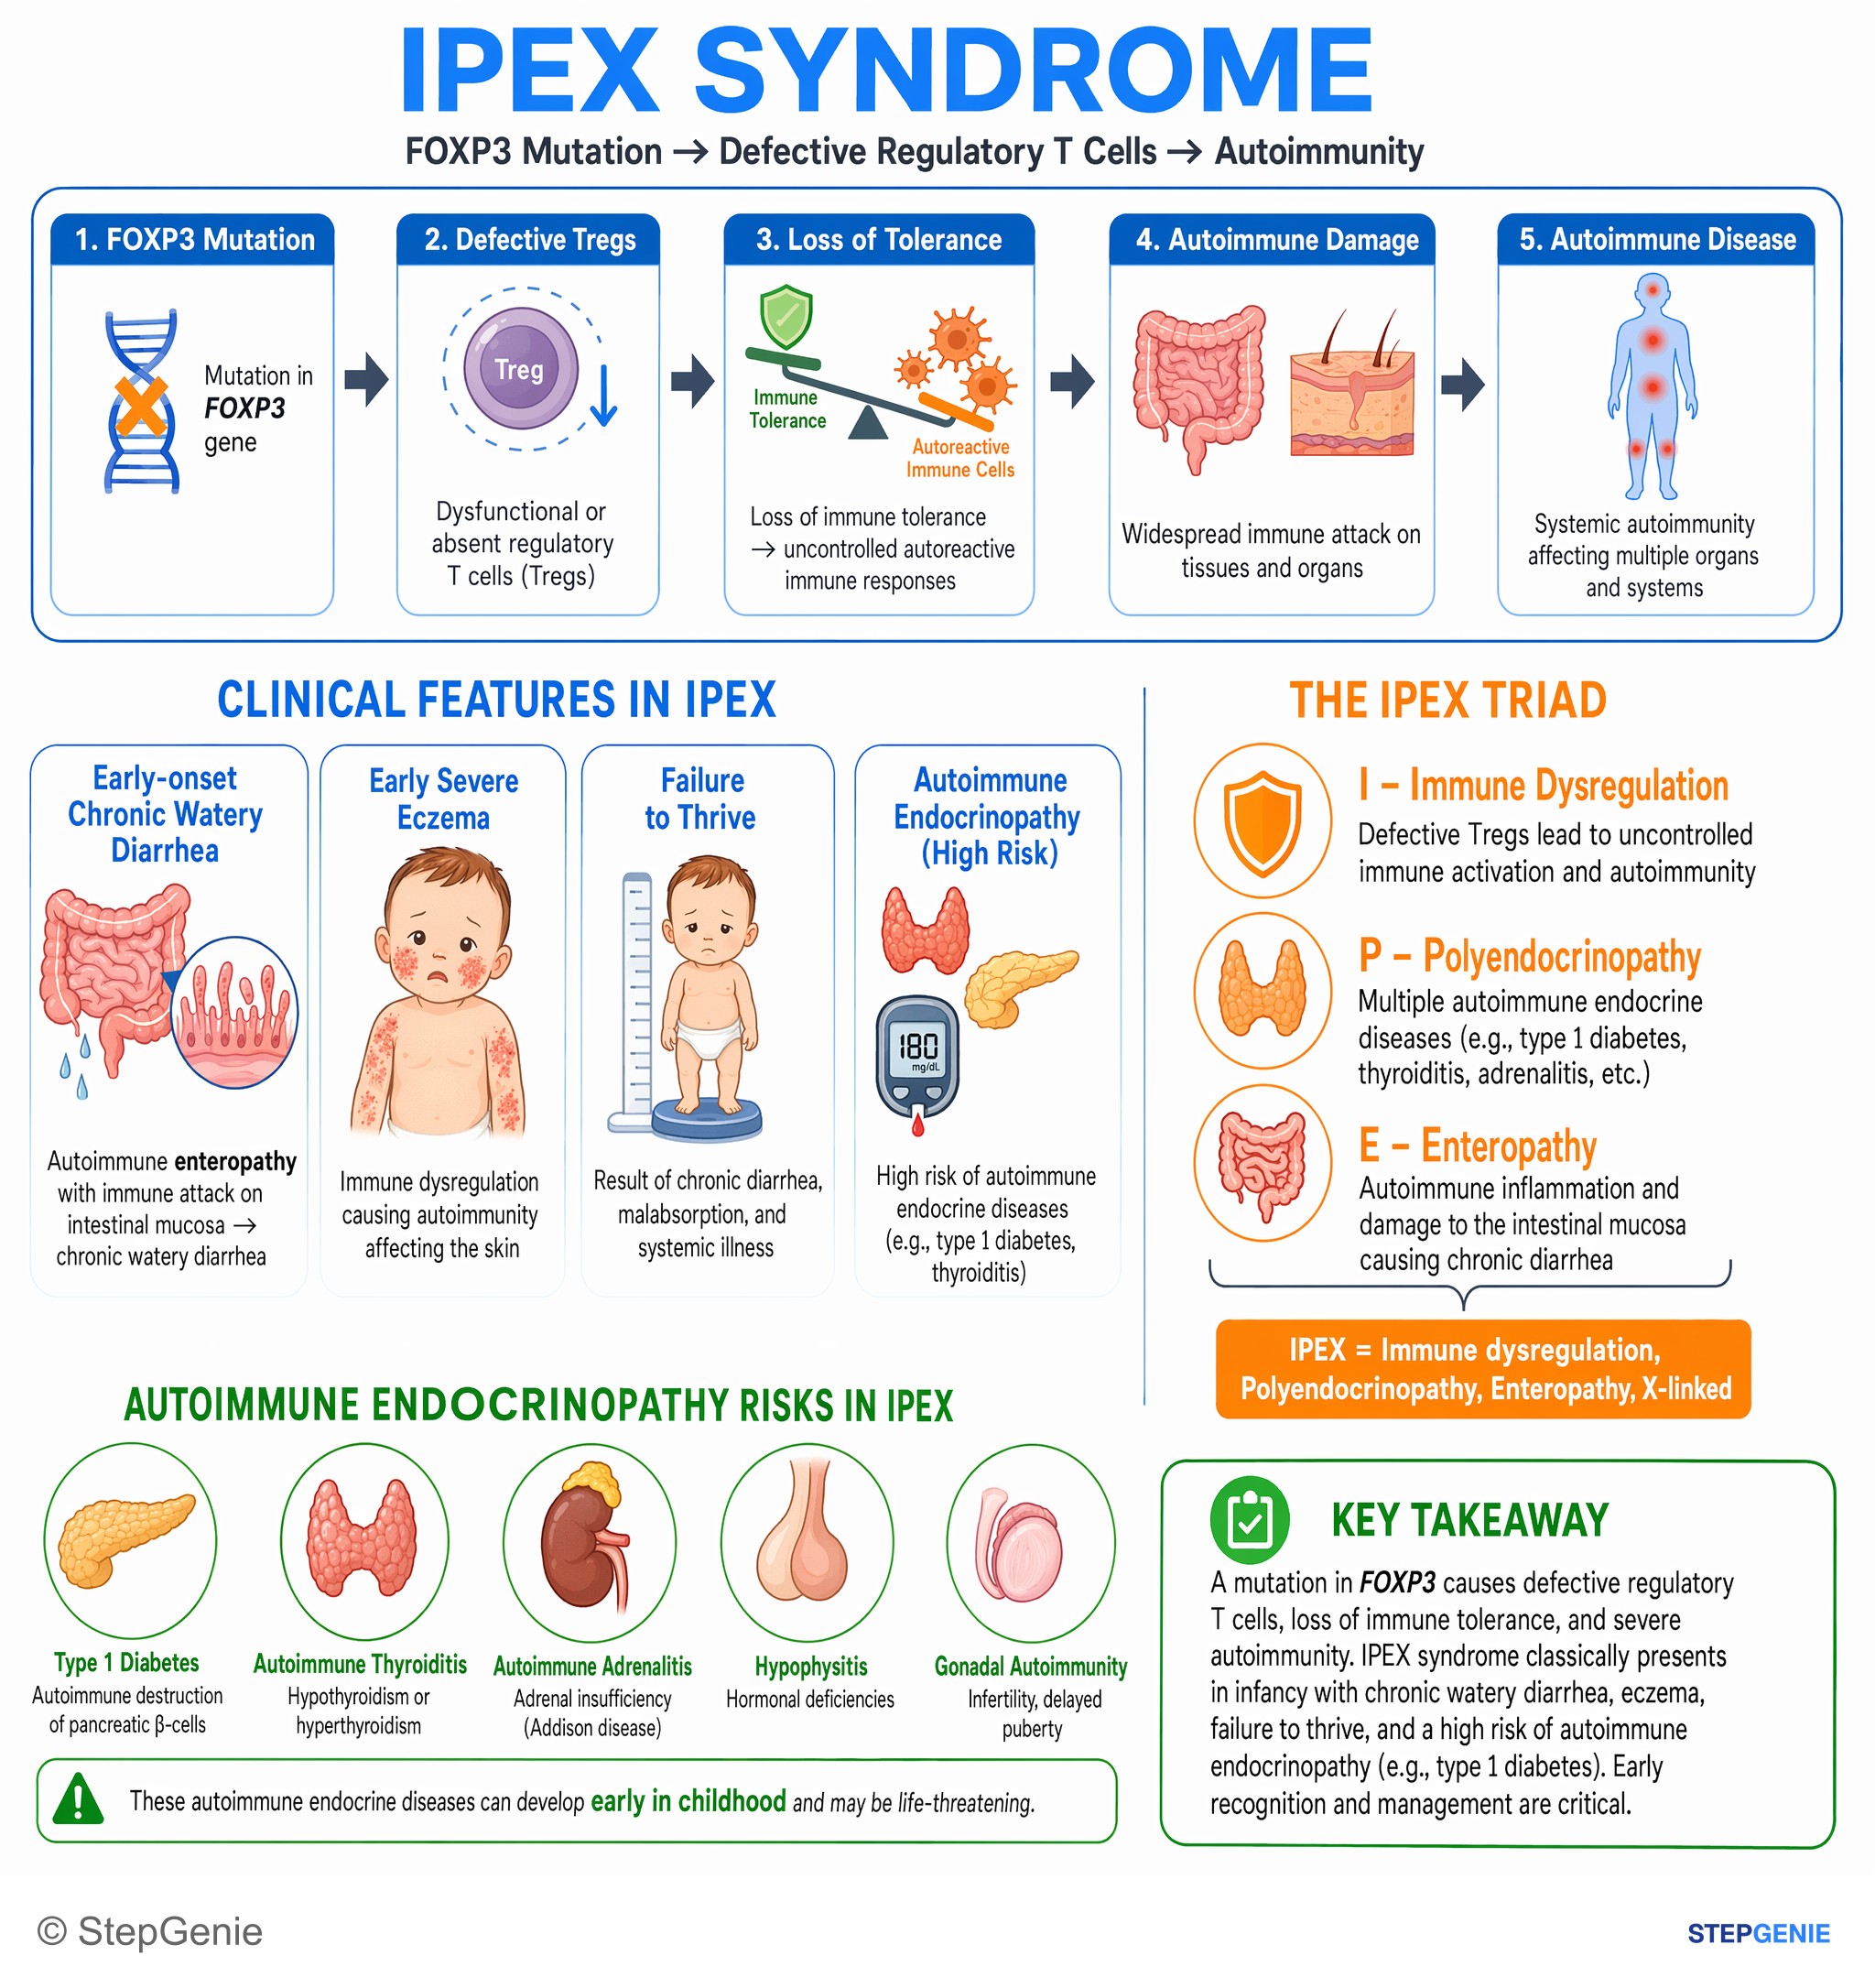
IPEX syndrome (FOXP3 mutation → defective regulatory T cells) causes early-onset diarrhea, eczema, failure to thrive, and severe…
USMLE Step 1Frequently Asked Questions
Why is absent costimulation the best explanation for reduced donor-specific T-cell proliferation after transplant?
Absent costimulation causes T-cell anergy, which best explains donor-specific T cells that are still present but proliferate poorly. Naive T cells need both TCR recognition of peptide-MHC and a second signal from B7 binding CD28. If signal 1 occurs without signal 2, the T cell becomes functionally unresponsive. In this setting, that pattern points to peripheral tolerance rather than deletion of the cells.
How does CTLA-4 reduce T-cell activation in transplant tolerance questions?
CTLA-4 reduces T-cell activation by competing with CD28 for B7 and delivering an inhibitory signal. It binds B7 with higher affinity than CD28, which decreases IL-2 production and T-cell proliferation. When a stem mentions increased CTLA-4 expression along with expansion of CD4+ FOXP3+ T cells, it strongly suggests peripheral tolerance through impaired costimulation and Treg-associated suppression.
How do you tell central tolerance from peripheral tolerance in an immunology vignette?
Central tolerance happens during lymphocyte development in the thymus or bone marrow, while peripheral tolerance happens later in peripheral tissues and lymph nodes. A vignette showing donor-specific T cells still present months after transplant but functionally turned off fits peripheral tolerance. Central tolerance would involve deletion of self-reactive cells during development, such as AIRE-mediated negative selection in the thymic medulla.
Why is AIRE-mediated deletion the wrong answer in a donor transplant tolerance question?
AIRE-mediated deletion is wrong because it is a central tolerance mechanism for self antigens, not donor antigens. AIRE promotes expression of peripheral tissue antigens in the thymus and drives negative selection of self-reactive T cells in the medulla. In a transplant stem months later, donor-reactive T cells are still detectable, so they were not deleted during development, making peripheral anergy a better fit.
Why are class switching or affinity maturation wrong when the stem focuses on poor T-cell proliferation?
They are wrong because class switching and affinity maturation are B-cell processes and do not explain T-cell anergy. Class switching requires T-cell help through CD40-CD40L plus cytokines, and somatic hypermutation in germinal centers produces higher-affinity antibodies. A stem centered on donor-specific T cells with poor proliferation, plus CTLA-4 and FOXP3 findings, is testing peripheral T-cell tolerance rather than antibody biology.