Hyperacute rejection destroys a graft within minutes to hours of reperfusion: preformed recipient antibodies against donor ABO or HLA antigens fix complement on the graft endothelium and clot its small vessels, a type II hypersensitivity reaction that ends with removal of the organ. Acute rejection appears over days to weeks and is either T-cell–mediated (lymphocytes invading tubules, treated with pulse steroids) or antibody-mediated by donor-specific antibodies, usually newly formed (C4d in peritubular capillaries, treated with plasma exchange and IVIG). Chronic rejection is a slow, largely irreversible loss of function over months to years, driven by intimal thickening and fibrosis that looks different in each organ. Timing narrows the answer choices; the pathology words pick the winner.
The Q-bank vignette
A 52-year-old man with end-stage renal disease receives a deceased-donor kidney transplant. He had several blood transfusions during years of dialysis and lost a first kidney transplant 9 years ago. Within minutes of release of the vascular clamps, the new kidney turns mottled and cyanotic and makes no urine. Doppler ultrasound shows little to no blood flow to the graft. The kidney is removed, and pathology shows widespread small-vessel thrombosis, fibrinoid necrosis of vessel walls and neutrophil infiltrates.
Which mechanism best explains this graft loss?
- A. Preformed recipient antibodies against donor ABO or HLA antigens that activate complement on the graft endothelium
- B. Recipient T cells that recognize donor MHC molecules and infiltrate the tubules and interstitium
- C. Newly formed donor-specific anti-HLA antibodies with C4d deposition in peritubular capillaries
- D. Progressive arterial intimal thickening and interstitial fibrosis from repeated immune injury
- E. Donor T cells attacking the recipient's skin, liver and gut
- F. Epstein-Barr virus–driven B-cell proliferation during immunosuppression
Answer: A, hyperacute rejection.
- Timing. The graft fails as soon as blood reaches it: StatPearls describes a kidney that turns "mottled, dusky, and black as soon as it is revascularized." Some definitions allow a wider window (within 24 hours in StatPearls' lung chapter, 48 hours in Merck's overview).
- Mechanism. Preexisting, complement-fixing antibodies bind donor antigens on the endothelium, causing endothelial injury, small-vessel thrombosis and graft infarction. Merck lists hyperacute graft rejection as a type II hypersensitivity example (see the type II breakdown).
- Sensitization. Anti-HLA antibodies come from transfusions, earlier transplants or pregnancies; this man has two of the three.
- Management. Nothing rescues the graft; it is removed. Prevention is everything: ABO compatibility and a negative crossmatch. With modern screening, hyperacute rejection has become rare (about 1% in Merck's overview).
Why every other answer choice is wrong
B. Acute T-cell–mediated rejection (TCMR). Recipient T cells must first recognize donor antigens and become activated (Merck: a T-cell–mediated delayed hypersensitivity, i.e., type IV, reaction), so TCMR appears days to weeks after transplant (Merck: from about day 5), though it can occur at any time, especially with nonadherence. Biopsy: lymphocytes in the interstitium and tubules (tubulitis), reaching the vessels in severe cases. Treatment: IV methylprednisolone pulses first; rabbit antithymocyte globulin (rATG) if rejection is steroid-resistant or recurs (KDIGO).
C. Acute antibody-mediated rejection (ABMR). The same weapon as hyperacute rejection, antibody plus complement, but the donor-specific antibodies (mainly against HLA) are usually made after the transplant (de novo) or were present only at low levels beforehand (StatPearls), so injury builds over days to weeks, not minutes. Biopsy: microvascular inflammation (glomerulitis, peritubular capillaritis) and linear C4d staining of peritubular capillaries; C4d is a complement degradation product that binds covalently to endothelium. C4d-negative ABMR is also recognized, so serum donor-specific antibody testing matters. Treatment: plasma exchange plus IVIG, often with rituximab (anti-CD20); bortezomib is also used.
D. Chronic rejection. A process of months to years: slowly rising creatinine, proteinuria, hypertension and irreversible fibrosis, not an infarcted graft on the operating table.
E. Graft-versus-host disease (GVHD). The direction is reversed: donor T cells attack the host. GVHD follows allogeneic hematopoietic stem cell transplant (occasionally liver or small-bowel transplant) and targets the skin, liver and gut. A failing kidney graft is host-versus-graft.
F. Post-transplant lymphoproliferative disorder (PTLD). A lymphoma-like proliferation, mainly of B cells, linked to Epstein-Barr virus (the belatacept label restricts that drug to EBV-seropositive recipients because those without EBV immunity are at particular risk). It develops during ongoing immunosuppression, sometimes within weeks, not at the moment of reperfusion.
Hyperacute vs acute vs chronic rejection
| Feature | Hyperacute | Acute T-cell–mediated | Acute antibody-mediated | Chronic |
|---|---|---|---|---|
| Timing | Minutes to hours (some definitions allow up to 24–48 h) | Days to weeks; can occur any time | Days to weeks; can occur later | Months to years |
| Effector | Preformed anti-ABO or anti-HLA antibodies + complement | Recipient T cells against donor antigens | Donor-specific antibodies, usually new (de novo), + complement | Antibody and T-cell injury plus nonimmune factors |
| Hypersensitivity | Type II | Type IV | Antibody-mediated, like hyperacute | Mixed |
| Pathology | Thrombosis, fibrinoid necrosis, neutrophils, infarction | Interstitial lymphocytes, tubulitis, vessels if severe | Glomerulitis, peritubular capillaritis, C4d+ capillaries | Intimal thickening, interstitial fibrosis, atrophy |
| Clue | Mottled, cyanotic graft at reperfusion | Rising creatinine, often without symptoms | Rising creatinine plus donor-specific antibodies | Slow decline, proteinuria, hypertension |
| Treatment | Remove graft; prevent with ABO match and crossmatch | Pulse steroids; rATG if steroid-resistant | Plasma exchange + IVIG ± rituximab | Prevention; poor response; retransplant |
In a kidney recipient, a sudden creatinine rise of more than 25% above baseline suggests rejection, and biopsy separates TCMR, ABMR and mimics (StatPearls). Merck also describes accelerated rejection at 3 to 5 days, from preexisting antibodies that do not fix complement.
Chronic rejection, organ by organ
| Organ | Name | Key pathology | Clinical clue |
|---|---|---|---|
| Kidney | Chronic active antibody-mediated or T-cell–mediated rejection | Interstitial fibrosis and tubular atrophy (IFTA), transplant glomerulopathy (duplicated GBM, "double contours"), arterial intimal fibrosis | Slowly rising creatinine; proteinuria above 500 mg/day may be an early marker; hypertension |
| Heart | Cardiac allograft vasculopathy (CAV) | Diffuse, progressive intimal thickening of epicardial and intramyocardial arteries | A leading cause of death after the first year; surveillance coronary angiography (IVUS if angiography is inconclusive) |
| Lung | Chronic lung allograft dysfunction, mainly bronchiolitis obliterans syndrome (BOS) | Obliterative bronchiolitis: fibrosis obliterating the lumen of small bronchioles | Sustained fall of 20% or more from the best post-transplant lung function, obstructive pattern; about 50% by 5 years |
| Liver | Chronic rejection (uncommon) | Bile duct loss in more than 50% of portal tracts; foam cell obliterative arteriopathy | Cholestatic liver tests (mainly GGT and alkaline phosphatase); about 2–5% of adult and up to 16% of pediatric recipients |
Kidney mimic: calcineurin inhibitor toxicity causes striped interstitial fibrosis and arteriolar hyalinosis, without transplant glomerulopathy or C4d (StatPearls).
Before the transplant: ABO, HLA and the crossmatch
- ABO compatibility comes first: an ABO mismatch can trigger hyperacute rejection of vascularized grafts.
- HLA typing covers six antigens: HLA-A, -B and -C (class I) and HLA-DP, -DQ and -DR (class II); see MHC I vs MHC II. Better matching helps, but mismatches no longer disqualify patients because immunosuppression has improved.
- Crossmatch: recipient serum is mixed with donor lymphocytes, classically with complement (a lymphocytotoxic test). A positive crossmatch means the recipient already has antibodies against donor ABO or class I HLA antigens and is an absolute contraindication to transplant in Merck's overview (except possibly in infants up to 14 months).
- Donor-specific antibodies (DSA) are measured with flow cytometry and single-antigen bead assays; DSA formed after transplant are a major cause of chronic graft loss.
- The liver is the exception: it is relatively immunologically privileged and can be transplanted successfully despite a positive crossmatch (2021 review).
GVHD: rejection in reverse
| Graft rejection | Graft-versus-host disease | |
|---|---|---|
| Who attacks whom | Recipient immune system attacks the graft | Donor T cells attack the recipient |
| Typical setting | Solid organ transplant | Allogeneic hematopoietic stem cell transplant; sometimes liver or small-bowel transplant |
| Targets | The graft | Acute: skin, liver, gut. Chronic: mainly skin and mucous membranes |
| Classic findings | Graft dysfunction | Acute (classically within 100 days): rash, hepatitis with hyperbilirubinemia, diarrhea, abdominal pain |
| Prevention | ABO and HLA matching, crossmatch, maintenance immunosuppression | Prophylactic immunosuppression, typically methotrexate plus cyclosporine (Merck) |
Chronic GVHD typically starts 4 to 7 months after transplant, with lichenoid or sclerotic skin, dry eyes and oral lichenoid lesions (Merck). The same donor T cells provide a helpful graft-versus-tumor effect.
Immunosuppressants: target and signature toxicity
| Drug | How it works | Signature toxicities |
|---|---|---|
| Tacrolimus | Binds FKBP-12 and inhibits calcineurin, so NFAT is not dephosphorylated and IL-2 is not produced | Nephrotoxicity, neurotoxicity (tremor, PRES), hyperkalemia, hypertension, new-onset diabetes (more than cyclosporine), QT prolongation |
| Cyclosporine | Binds cyclophilin; the complex inhibits calcineurin, so NFAT is not dephosphorylated and IL-2 is not produced | Nephrotoxicity (afferent arteriolar vasoconstriction), hypertension, tremor, gum hypertrophy, hirsutism, gout, diabetes |
| Mycophenolate | Inhibits inosine monophosphate dehydrogenase in the guanine nucleotide pathway, rate-limiting for lymphocyte proliferation | Leukopenia, nausea, vomiting, diarrhea |
| Azathioprine | Purine antagonist that blocks leukocyte proliferation | Bone marrow suppression, worst with TPMT deficiency; rarely hepatitis |
| Sirolimus, everolimus | Inhibit mTOR, arresting the cell cycle and the lymphocyte response to cytokines | Hyperlipidemia, pneumonitis, leg edema, impaired wound healing, cytopenias |
| Belatacept | Binds CD80/CD86 on APCs, blocking CD28 costimulation (signal 2) | PTLD, mainly in the CNS; used only in EBV-seropositive kidney recipients |
| Basiliximab | Antibody against the IL-2 receptor | Given at transplant; anaphylaxis |
| Antithymocyte globulin | Animal antisera against thymus cells; suppress cellular immunity | Induction; steroid-resistant rejection |
All of these raise the risk of infection (months 1 to 6 bring opportunists such as CMV, BK virus, EBV, Pneumocystis and Aspergillus, hence TMP-SMX prophylaxis) and cancer (especially squamous and basal cell skin cancer, B-cell lymphoproliferative disorders and Kaposi sarcoma). Tacrolimus and cyclosporine are metabolized by CYP3A, so strong CYP3A4 inhibitors and grapefruit juice raise their levels and inducers lower them; see CYP450 inducers and inhibitors.
How USMLE tests it
- Read the clock, then the pathology. Minutes = hyperacute; days to weeks = acute; months to years = chronic. Then confirm with the buzzword: preformed antibody or thrombosis → hyperacute; tubulitis → TCMR; C4d or donor-specific antibodies → ABMR; intimal thickening, IFTA or bronchiolitis obliterans → chronic.
- Hypersensitivity type: hyperacute = type II; acute cellular = type IV (compare the type IV breakdown).
- Creatinine rising on tacrolimus? Rejection, calcineurin inhibitor nephrotoxicity, BK polyomavirus and CMV all fit; biopsy decides.
- Belatacept blocks signal 2 (B7 to CD28); review the three signals in the T-cell activation mnemonic.
- Nonadherence is a major, modifiable risk factor for both acute and chronic rejection.
Key takeaways
- Hyperacute: minutes to hours; preformed anti-ABO or anti-HLA antibodies, complement, thrombosis; type II; remove the graft; prevent with ABO matching and a negative crossmatch.
- Acute TCMR: days to weeks; T cells, tubulitis; type IV; pulse steroids, rATG if resistant.
- Acute ABMR: donor-specific antibodies (usually de novo), C4d in peritubular capillaries; plasma exchange + IVIG ± rituximab.
- Chronic: months to years of intimal thickening and fibrosis: IFTA (kidney), CAV (heart), bronchiolitis obliterans (lung), bile duct loss (liver).
- GVHD is the reverse: donor T cells attack the host's skin, liver and gut after stem cell transplant.
- Calcineurin inhibitors are nephrotoxic; cyclosporine adds gum hypertrophy and hirsutism, tacrolimus more diabetes; belatacept is contraindicated in EBV-seronegative recipients because of its boxed warning for PTLD, mainly in the CNS.
Sources
- Overview of Transplantation — Merck Manual Professional Edition (2025)
- Acute Renal Transplantation Rejection — StatPearls, NCBI Bookshelf (2023)
- Chronic Kidney Transplant Rejection — StatPearls, NCBI Bookshelf (2025)
- KDIGO Clinical Practice Guideline for the Care of Kidney Transplant Recipients — KDIGO (2009, current version)
- Heart Transplantation Rejection — StatPearls, NCBI Bookshelf (2024)
- Lung Transplant Rejection — StatPearls, NCBI Bookshelf (2022)
- Chronic rejection after liver transplantation: Opening the Pandora's box — World Journal of Gastroenterology (2021)
- Hematopoietic Stem Cell Transplantation — Merck Manual Professional Edition (2022)
- Overview of Allergic and Atopic Disorders — Merck Manual Professional Edition (2026)
- PROGRAF (tacrolimus) prescribing information — DailyMed (2023)
- Cyclosporin A (CID 5284373): Mechanism of Action — PubChem, NIH/NLM
- NULOJIX (belatacept) prescribing information — DailyMed (2021)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
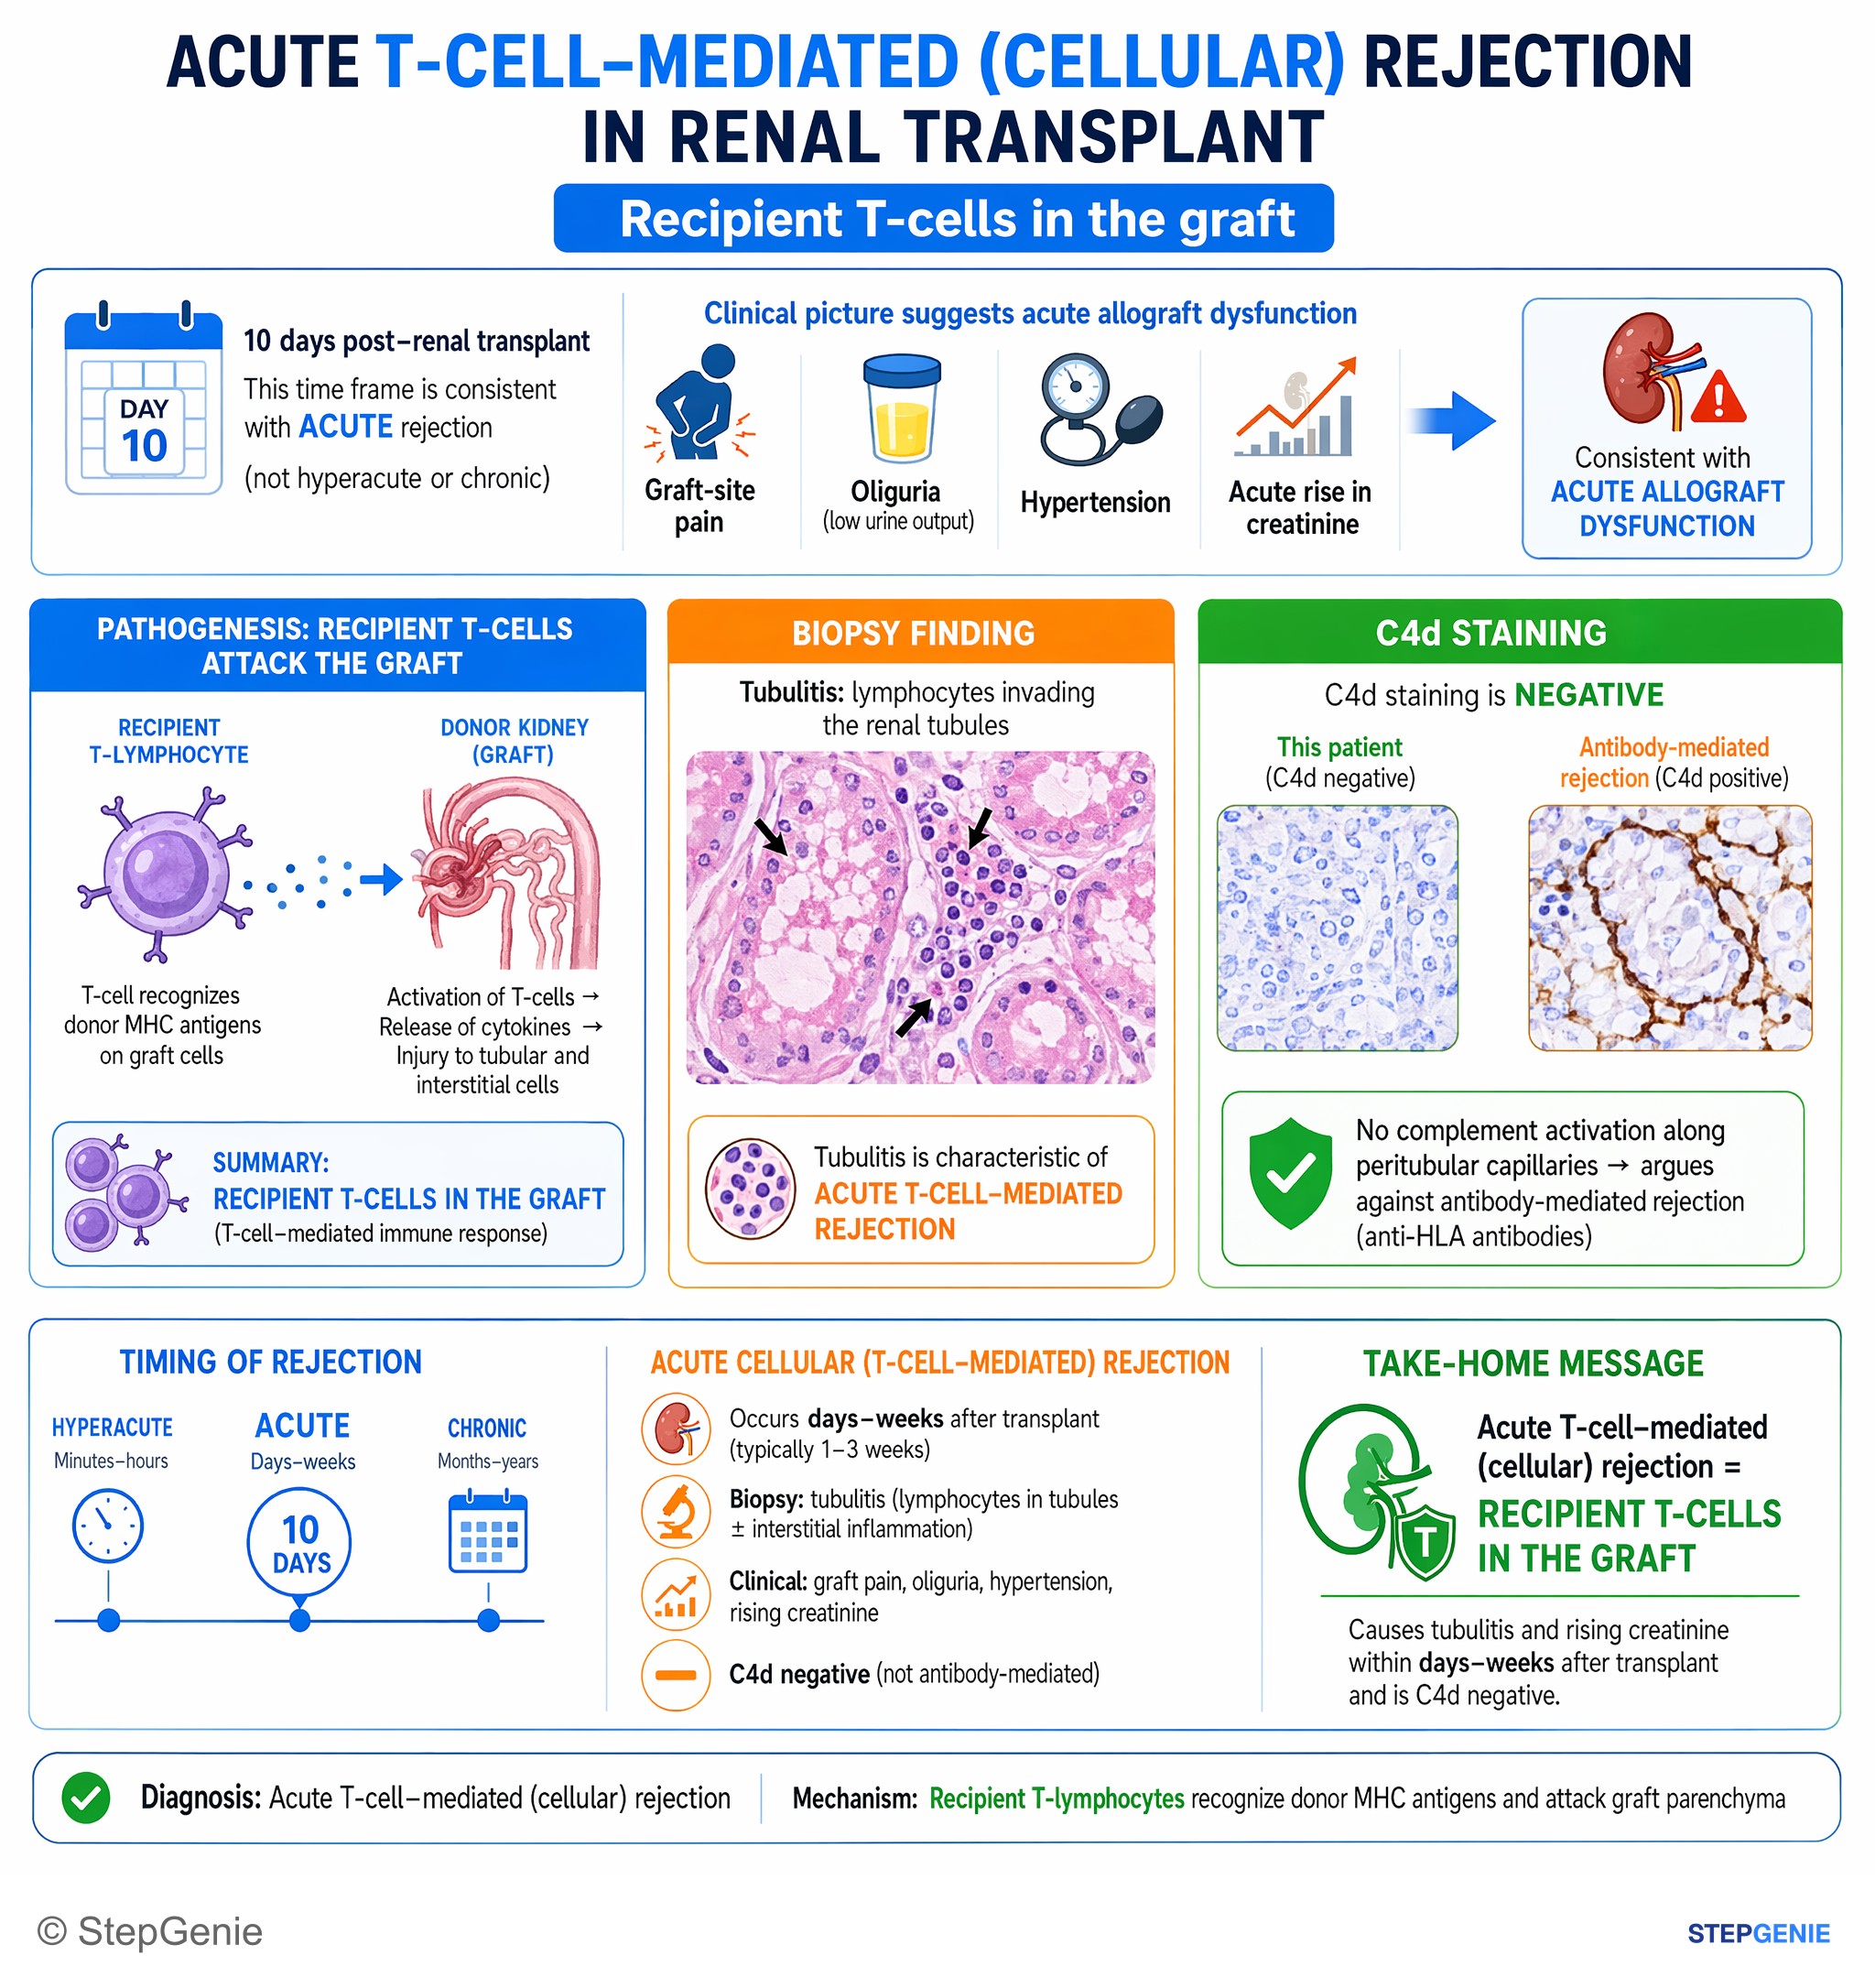
Acute cellular (T-cell–mediated) rejection causes tubulitis and rising creatinine days–weeks after transplant; C4d negative (not…
USMLE Step 1Frequently Asked Questions
What is the difference between hyperacute, acute and chronic transplant rejection?
They differ in timing and mechanism. Hyperacute rejection occurs within minutes to hours, when preformed recipient antibodies against donor ABO or HLA antigens activate complement and clot the graft's vessels. Acute rejection develops over days to weeks and is either T-cell mediated, with lymphocytes invading the tubules, or antibody mediated by donor-specific antibodies, usually newly formed, with C4d deposition. Chronic rejection unfolds over months to years as intimal thickening and fibrosis slowly destroy graft function.
Why is hyperacute rejection a type II hypersensitivity reaction?
Type II hypersensitivity means antibody binding to antigens on cell surfaces, followed by complement activation or antibody-dependent cell killing. In hyperacute rejection, the recipient already has complement-fixing antibodies, usually against donor ABO or HLA antigens, from earlier transfusions, transplants or pregnancies. These antibodies bind the graft endothelium as soon as blood flows, causing endothelial injury, small-vessel thrombosis and infarction. Acute T-cell-mediated rejection, by contrast, is a type IV reaction.
What does C4d staining mean on a transplant biopsy?
C4d is a degradation product of complement component C4 that binds covalently to endothelium when antibodies activate complement. Linear C4d staining of peritubular capillaries in a kidney transplant is highly suggestive of antibody-mediated rejection caused by donor-specific antibodies. It is not perfect: C4d-negative antibody-mediated rejection is now recognized, so pathologists also look for microvascular inflammation such as glomerulitis and peritubular capillaritis, and clinicians check serum donor-specific antibodies.
How is acute transplant rejection treated?
Treatment depends on the mechanism shown on biopsy. Acute T-cell-mediated rejection is treated first with high-dose IV methylprednisolone pulses; antithymocyte globulin is added when rejection does not respond to steroids or keeps recurring. Acute antibody-mediated rejection is treated by removing and neutralizing antibody with plasma exchange and IVIG, often with rituximab to deplete B cells; bortezomib is also used. Maintenance immunosuppression is also reviewed, and adherence is addressed because missed doses are a major risk factor.
What does chronic rejection look like in different organs?
In the kidney, chronic rejection causes interstitial fibrosis and tubular atrophy, transplant glomerulopathy with duplicated glomerular basement membranes and arterial intimal fibrosis, with slowly rising creatinine and proteinuria. In the heart it appears as cardiac allograft vasculopathy, a diffuse intimal thickening of the coronary arteries. In the lung it causes bronchiolitis obliterans, a fibrosis that obliterates small airways. In the liver it causes bile duct loss and cholestasis.
How is graft-versus-host disease different from transplant rejection?
In rejection, the recipient's immune system attacks the transplanted organ. In graft-versus-host disease, immunocompetent donor T cells attack the recipient's tissues. It mainly follows allogeneic hematopoietic stem cell transplantation and occasionally liver or small-bowel transplantation. Acute GVHD, classically within 100 days, causes rash, hepatitis with a high bilirubin, and diarrhea with abdominal pain. Prophylaxis typically combines methotrexate with a calcineurin inhibitor such as cyclosporine.