You’re deep in a Q-bank block and you hit another “Which HLA is associated with this disease?” question. Easy, right? The trap is that these questions aren’t just about the correct association—they’re about recognizing why each answer choice is wrong (and what it actually goes with). That skill is what stops you from falling for distractors on test day.
Tag: Immunology > Transplant & Autoimmune
The Clinical Vignette (Classic USMLE Style)
A 28-year-old man presents with 3 months of progressively worsening low back pain. He says it’s worse in the morning, improves with activity, and sometimes wakes him up at night. He also reports intermittent painful red eyes that improved with steroid eye drops. On exam, there is decreased lumbar flexion and tenderness over the sacroiliac joints. Pelvic X-ray shows bilateral sacroiliitis.
Question: Which HLA type is most strongly associated with this patient’s condition?
Answer choices:
- A. HLA-B27
- B. HLA-DR3
- C. HLA-DR4
- D. HLA-B8
- E. HLA-DQ2
Step-by-Step: Identify the Disease First
This vignette screams ankylosing spondylitis (AS):
- Inflammatory back pain: worse in AM, improves with exercise
- Sacroiliitis on imaging
- Anterior uveitis (painful red eye, photophobia)
- Young man (typical demographic)
Correct Answer: A. HLA-B27
Why HLA-B27 fits
HLA-B27 is a Class I MHC allele (presents antigen to CD8+ T cells). It’s strongly associated with the seronegative spondyloarthropathies, especially ankylosing spondylitis.
High-yield associations (know these cold)
HLA-B27 → “PAIR”
- Psoriatic arthritis
- Ankylosing spondylitis
- Inflammatory bowel disease–associated arthritis (Crohn/UC-associated)
- Reactive arthritis (Chlamydia, Salmonella, Shigella, Campylobacter, Yersinia)
Extra USMLE hooks:
- AS can cause aortitis → aortic regurgitation and conduction abnormalities.
- Reactive arthritis: can’t see, can’t pee, can’t climb a tree (conjunctivitis/uveitis, urethritis, arthritis).
Now the Real Value: Why Each Distractor Matters
B. HLA-DR3 — Wrong for AS; right for autoimmune endocrinopathies
HLA-DR3 is Class II MHC (presents to CD4+ T cells). It clusters with several autoimmune diseases—commonly tested as a set.
Think: DR3 = “diabetes + lupus”
- Type 1 diabetes mellitus (also DR4)
- SLE
- Autoimmune hepatitis
- Sjögren syndrome
- Graves disease
- Myasthenia gravis (classically associated with thymic hyperplasia)
How it tricks you: If you see “young patient + autoimmune symptom,” DR3 might feel plausible—unless you anchor to the MSK pattern and sacroiliitis.
C. HLA-DR4 — Wrong for AS; right for rheumatoid arthritis
HLA-DR4 is the classic association for:
- Rheumatoid arthritis
- Also: Type 1 diabetes mellitus (overlaps with DR3)
How to separate RA from AS fast
| Feature | Rheumatoid arthritis | Ankylosing spondylitis |
|---|---|---|
| Joint pattern | Symmetric small joints (MCP, PIP) | Axial spine + SI joints |
| Antibodies | RF, anti-CCP | Seronegative |
| Sex | F > M | M > F |
| Imaging | Erosions, joint space narrowing | Sacroiliitis, “bamboo spine” later |
| HLA | DR4 | B27 |
D. HLA-B8 — Wrong for AS; shows up in a few classic immune disorders
HLA-B8 is a Class I allele associated with certain autoimmune conditions, often tested less than the heavy hitters, but still fair game.
Commonly cited associations:
- Myasthenia gravis (also DR3 is common—test writers vary)
- Celiac disease can be associated with B8 in older references, but the testable must-know is DQ2/DQ8
- Addison disease (often bundled with autoimmune polyglandular syndromes)
Test-taking tip: If you see B8 in choices, it’s usually there to catch students who think “B = ankylosing,” but B27 is the one you want.
E. HLA-DQ2 — Wrong for AS; right for celiac disease
This is one of the most high-yield HLA facts on Step exams.
- Celiac disease: HLA-DQ2 (major) and HLA-DQ8
- Path: deamidated gliadin presented to CD4+ T cells → inflammation and villous atrophy
- Antibodies: anti–tissue transglutaminase (tTG), anti-endomysial, anti-deamidated gliadin
How it tricks you: If the vignette mentioned diarrhea, iron deficiency, dermatitis herpetiformis, or osteoporosis—DQ2 would jump out. But here, the story is axial inflammatory arthritis + uveitis.
Quick “One-Liner” Table: Match the HLA to the Disease
| HLA | Class | High-yield disease associations |
|---|---|---|
| B27 | I | Ankylosing spondylitis, reactive arthritis, psoriatic arthritis, IBD-associated arthritis |
| DR3 | II | Type 1 DM, SLE, Graves, Sjögren, autoimmune hepatitis, myasthenia gravis (often) |
| DR4 | II | Rheumatoid arthritis, Type 1 DM |
| DQ2 / DQ8 | II | Celiac disease |
| B8 | I | Myasthenia gravis, other autoimmune clustering (less commonly tested) |
Why This Matters in Transplant & Autoimmune Questions
Even though the vignette is autoimmune, HLA shows up constantly in transplant immunology too:
High-yield transplant tie-ins
- HLA-A, HLA-B, HLA-C are Class I on all nucleated cells → interact with CD8+ T cells
- HLA-DP, DQ, DR are Class II on APCs → interact with CD4+ T cells
- Graft rejection risk increases with HLA mismatch, especially HLA-A, HLA-B, HLA-DR mismatching in many organ transplants.
USMLE pearl:
- Hyperacute rejection: preformed anti-donor antibodies (often anti-ABO or anti-HLA) → thrombosis, necrosis minutes to hours.
- Acute rejection: T cell–mediated ± antibody-mediated → days to weeks (or later if immunosuppression is low).
- Chronic rejection: progressive fibrosis, arteriosclerosis → months to years.
Q-Bank Strategy: How to Avoid Getting HLA Questions Wrong
- Diagnose the disease first from the vignette (pattern recognition beats memorization).
- Class I vs Class II can help eliminate:
- Many autoimmune diseases skew Class II associations (DR/DQ).
- The spondyloarthropathies are the famous Class I exception: B27.
- Interrogate distractors: if you can say what each wrong option actually matches, you’re test-proof.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
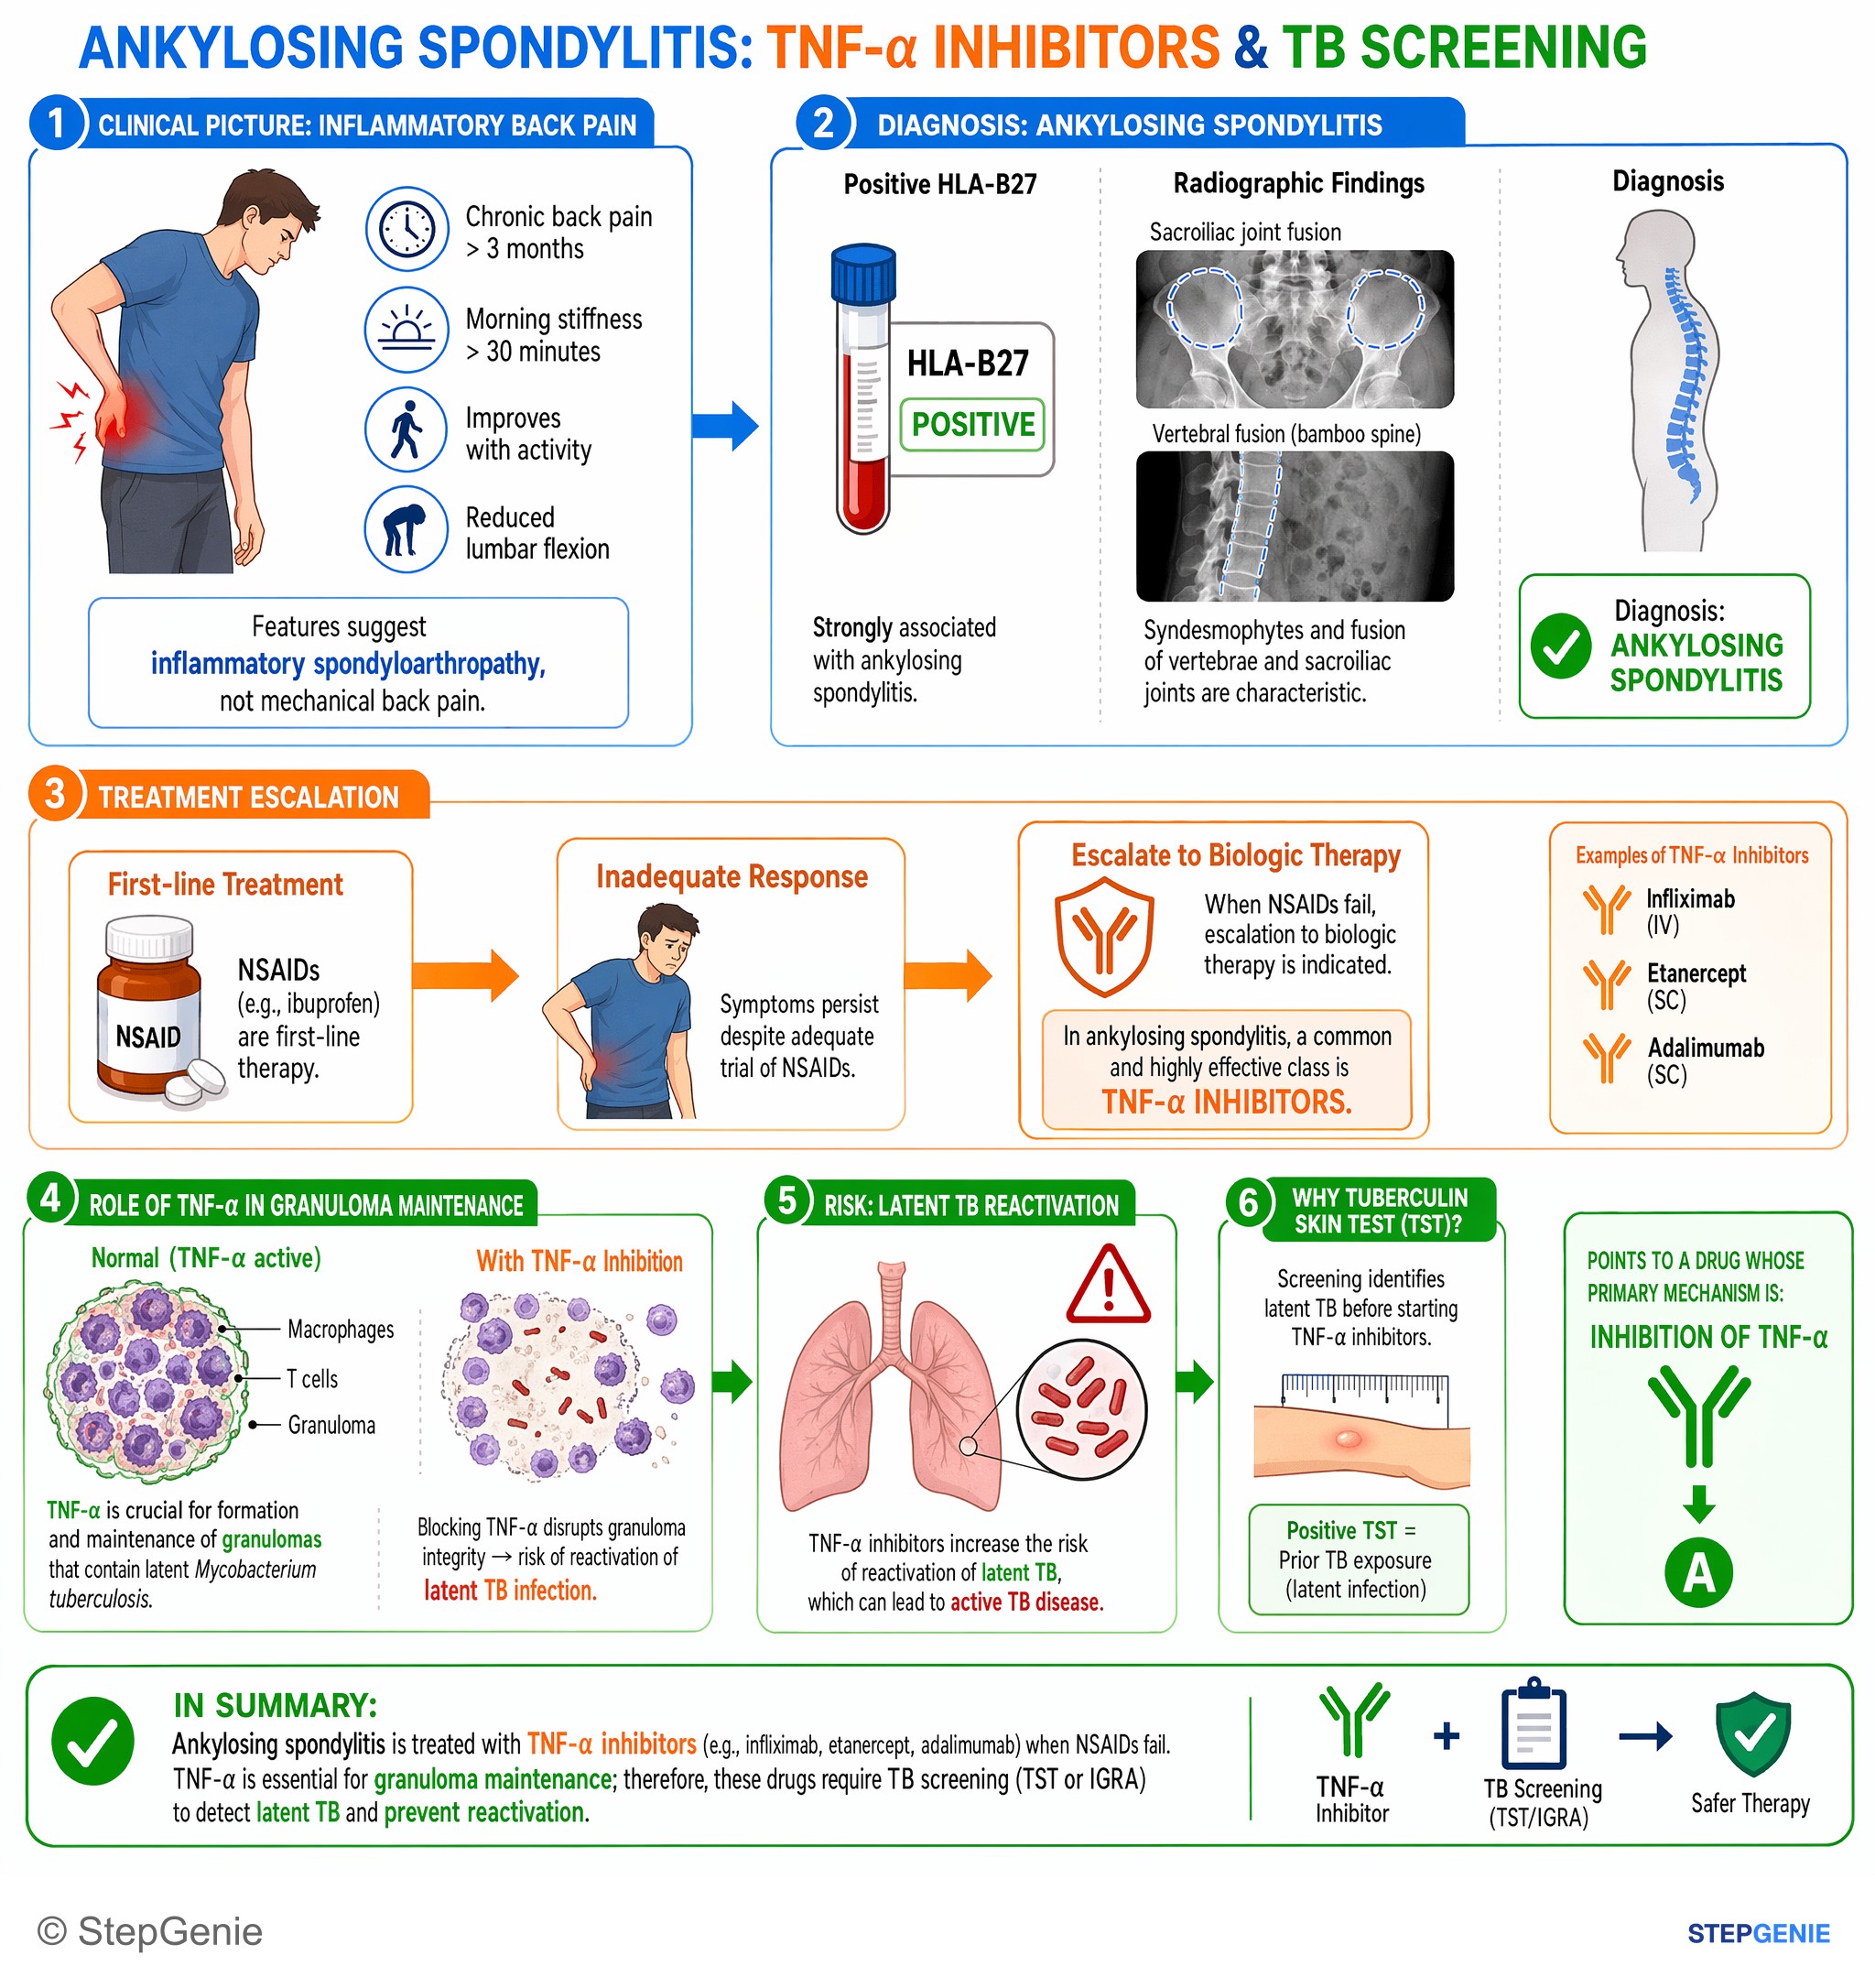
Ankylosing spondylitis is treated with TNF-α inhibitors, which require TB screening due to risk of latent TB reactivation from impaired…
USMLE Step 1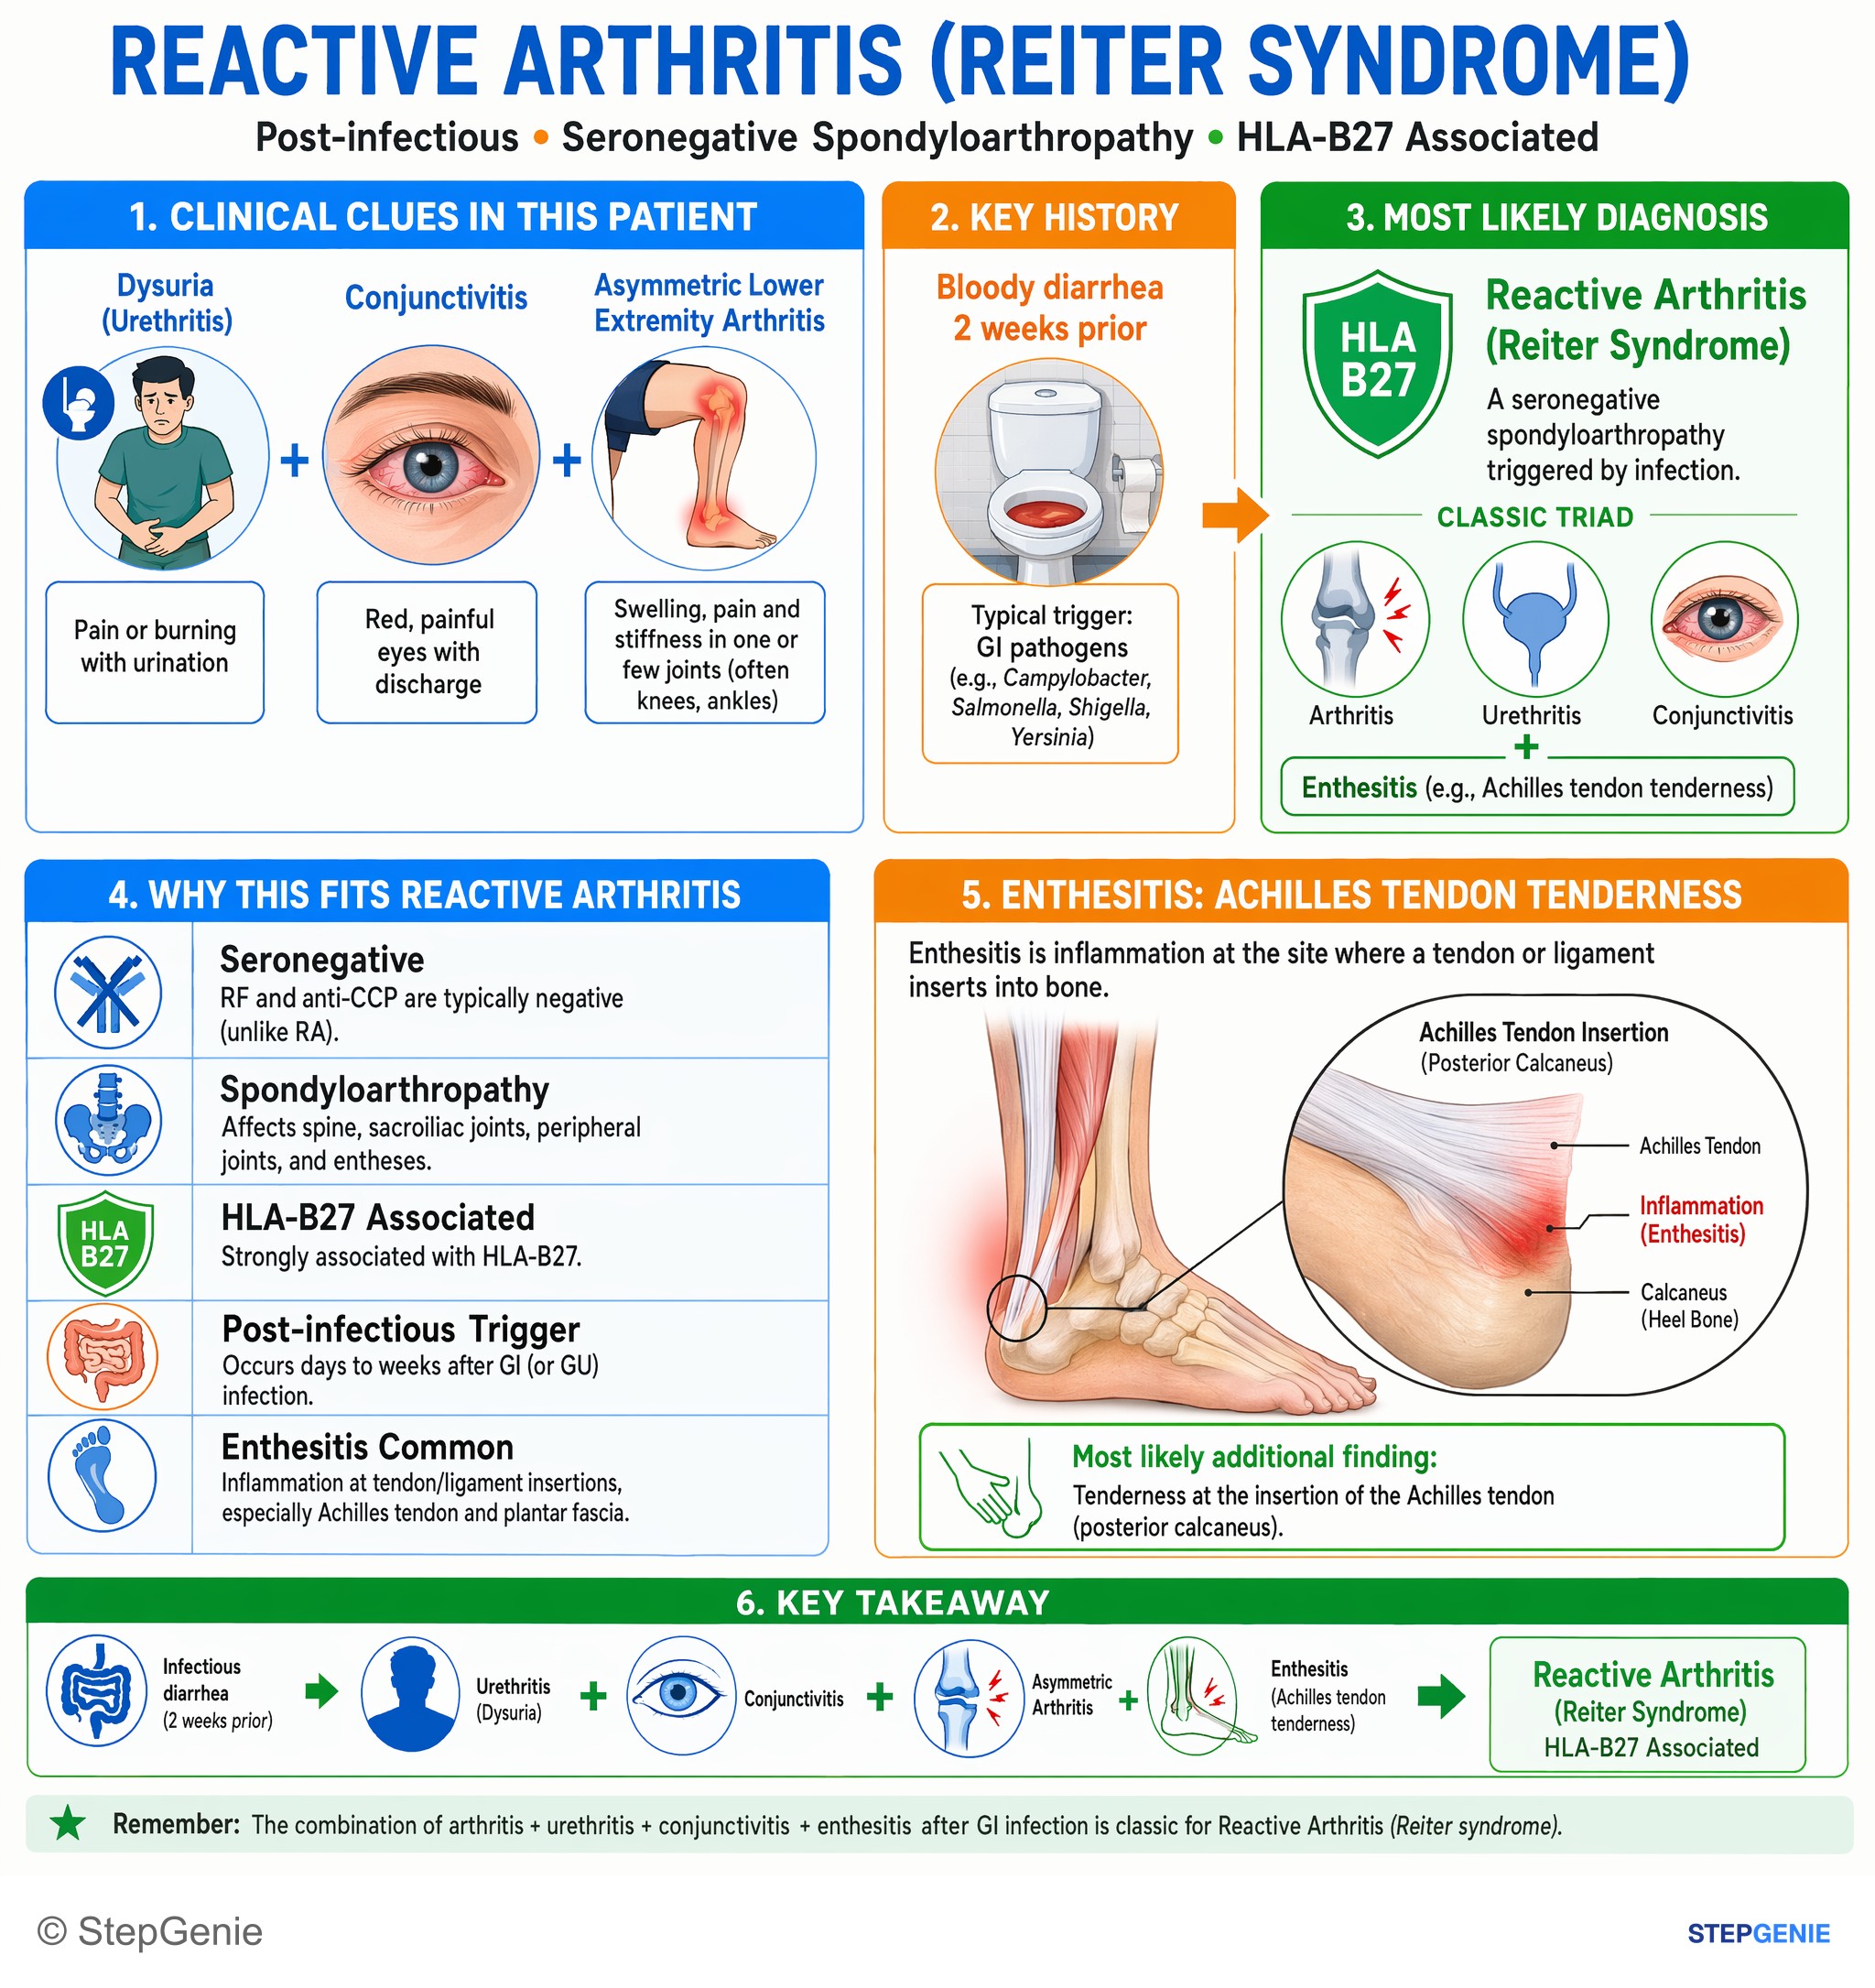
Reactive arthritis (Reiter syndrome) after infectious diarrhea: triad of arthritis, urethritis, conjunctivitis and enthesitis (Achilles…
USMLE Step 1Frequently Asked Questions
Which HLA type is most strongly associated with ankylosing spondylitis?
HLA-B27 is the HLA type most strongly associated with ankylosing spondylitis. The classic clue pattern is inflammatory back pain that is worse in the morning, improves with activity, bilateral sacroiliitis on imaging, and anterior uveitis causing painful red eyes. HLA-B27 is a Class I MHC allele and is strongly linked to the seronegative spondyloarthropathies.
How do you tell ankylosing spondylitis from rheumatoid arthritis on an HLA question?
Ankylosing spondylitis points to HLA-B27, while rheumatoid arthritis points to HLA-DR4. Ankylosing spondylitis typically affects the axial spine and sacroiliac joints, is seronegative, and is more common in men. Rheumatoid arthritis more often causes symmetric small-joint disease involving the MCP and PIP joints, has RF and anti-CCP antibodies, and shows erosions and joint space narrowing on imaging.
What diseases are classically associated with HLA-B27 besides ankylosing spondylitis?
HLA-B27 is classically associated with the seronegative spondyloarthropathies: psoriatic arthritis, ankylosing spondylitis, inflammatory bowel disease-associated arthritis, and reactive arthritis. A useful memory aid is PAIR. Extra test hooks include aortitis leading to aortic regurgitation in ankylosing spondylitis and the conjunctivitis or uveitis, urethritis, and arthritis pattern in reactive arthritis.
Why is HLA-DQ2 the wrong answer in a sacroiliitis and uveitis vignette?
HLA-DQ2 is wrong because it is the classic association for celiac disease, not ankylosing spondylitis. Celiac disease is linked to HLA-DQ2 and DQ8 and is associated with deamidated gliadin presentation to CD4+ T cells, inflammation, and villous atrophy. In contrast, a vignette centered on axial inflammatory arthritis, sacroiliitis, and uveitis fits ankylosing spondylitis and therefore HLA-B27.
How do HLA class I and class II molecules differ in autoimmune and transplant questions?
HLA class I molecules include HLA-A, HLA-B, and HLA-C, are found on all nucleated cells, and present antigen to CD8+ T cells. HLA class II molecules include HLA-DP, DQ, and DR, are found on antigen-presenting cells, and present to CD4+ T cells. In transplant questions, mismatch in HLA increases graft rejection risk, especially with HLA-A, HLA-B, and HLA-DR mismatching.