Autoimmune diseases injure tissue through three hypersensitivity mechanisms: type II, in which IgG or IgM binds a fixed antigen on a cell, basement membrane or receptor (anti-GBM disease, myasthenia gravis, Graves disease, pemphigus); type III, in which antigen-antibody immune complexes deposit in vessels and glomeruli and consume complement (SLE, post-streptococcal glomerulonephritis); and type IV, in which T cells do the damage without antibody (type 1 diabetes). On a kidney biopsy, linear IgG along the glomerular basement membrane means type II anti-GBM disease, while granular deposits with low C3 and C4 mean immune complex (type III) disease such as lupus nephritis. Autoimmunity itself begins when tolerance fails, through altered self-antigens, molecular mimicry, regulatory T-cell defects and HLA-linked genetic risk.
The case
A 29-year-old woman has fatigue, joint pain and a facial rash that worsens in the sun. She reports painless oral ulcers. Examination shows a malar rash and mild swelling of the PIP joints. ANA and anti-double-stranded DNA (anti-dsDNA) antibodies are positive, and serum C3 and C4 are low. Urinalysis shows proteinuria and red blood cell casts. A kidney biopsy shows granular deposits of IgG and C3 along the glomerular capillary walls on immunofluorescence.
Which immunologic mechanism best explains her kidney disease?
A. Type II hypersensitivity with antibodies against a fixed basement membrane antigen B. Type III hypersensitivity from immune complex deposition C. Type IV hypersensitivity from T-cell-mediated injury D. Autoantibodies against the acetylcholine receptor causing receptor blockade E. Autoantibodies against desmoglein causing loss of keratinocyte adhesion
Answer: B, type III (immune complex) hypersensitivity
This is SLE with lupus nephritis, the textbook type III disease:
- Complexes form: anti-dsDNA antibodies bind DNA and form immune complexes.
- Complexes deposit in the glomerulus (mesangial, subendothelial and subepithelial regions).
- Complement is activated through the classical pathway, generating C3a and C5a, which increase vascular permeability and recruit neutrophils and monocytes; their enzymes and reactive oxygen species injure the tissue.
- Complement is consumed: C3, C4 and CH50 fall. In SLE, C3 and C4 are often low in active disease and usually lowest with active nephritis.
| Clue in the stem | What it means |
|---|---|
| Photosensitive malar rash, oral ulcers, arthritis | Multisystem SLE; it is about 10 times more common in women, usually of child-bearing age |
| Positive ANA | Present in more than 95% of SLE; the 2019 EULAR/ACR criteria require ANA of 1:80 or higher to apply |
| Anti-dsDNA | Highly specific for SLE; rising titers (with falling C3 and C4) often signal active nephritis, though they may not track nonrenal flares |
| Low C3 and C4 | Complement consumed by immune complexes |
| Proteinuria with RBC casts | Active nephritis |
| Granular IgG and C3 | Immune complexes deposited in clumps, not antibody lined up along a fixed antigen |
Lupus nephritis biopsies can show IgG, IgA, IgM and complement components together. Class IV (diffuse) nephritis, involving 50% or more of glomeruli, is the most common and most severe class, and wire loops signal active disease; the classes are covered in the lupus nephritis breakdown.
Why every other choice is wrong
A. Type II, antibody to a fixed basement membrane antigen. This is anti-GBM disease: IgG against the noncollagenous (NC1) domain of the α3 chain of type IV collagen; the alveolar basement membrane shares the same collagen target. Immunofluorescence shows bright linear IgG and C3 along the GBM, and the clinical picture is rapidly progressive glomerulonephritis with crescents. Anti-GBM disease can be kidney-only; Goodpasture syndrome always includes pulmonary (alveolar) hemorrhage, seen in about 40-60% of cases. Age peaks fall around 30 and in the sixth decade, and smoking and hydrocarbon solvent exposure are triggers. Treatment is urgent plasmapheresis with glucocorticoids and cyclophosphamide. Wrong here because the deposits are granular and the serology is SLE.
C. Type IV, T-cell-mediated injury. Type IV reactions involve CD4+ and CD8+ T cells, cytokines and macrophages, usually 48-72 hours after antigen exposure, with no antibody. Classic examples: contact dermatitis, the tuberculin skin test, granulomas, transplant rejection, and drug reactions such as Stevens-Johnson syndrome and DRESS. The autoimmune example is type 1 diabetes, in which a primarily T-cell-mediated attack destroys beta cells (insulitis) and islet autoantibodies are markers rather than the cause. Wrong here because antibodies, complement consumption and immune deposits drive her disease.
D. Antibodies against the acetylcholine receptor. This is myasthenia gravis, a type II disease in which antibody- and cell-mediated damage destroys postsynaptic acetylcholine receptors. About 85% of patients with generalized disease have AChR antibodies; others have antibodies to MuSK or LRP4. Look for ptosis, diplopia and weakness that worsens with use and improves with rest; 65% have thymic hyperplasia and 10% a thymoma. Wrong here: she has no fatigable weakness, and her antibodies form complexes rather than blocking a receptor.
E. Antibodies against desmoglein. This is pemphigus vulgaris, a type II disease with IgG against desmoglein 3 (and sometimes desmoglein 1). Loss of keratinocyte adhesion (acantholysis) gives intraepidermal flaccid bullae, painful oral erosions that often come first, a positive Nikolsky sign and IgG bound to keratinocyte cell surfaces on immunofluorescence. Contrast bullous pemphigoid: IgG against hemidesmosome antigens (BP180, BP230), subepidermal tense bullae in patients usually over 60, rare mucosal blisters and linear IgG and complement along the basement membrane zone. Wrong here because she has no blistering disease. Both are compared in pemphigus vulgaris vs bullous pemphigoid.
How autoimmunity starts
Tolerance normally deletes or restrains self-reactive lymphocytes. Autoimmunity follows when that fails:
- Central tolerance (thymus): the AIRE protein helps developing T cells distinguish self from foreign and eliminates self-reactive T cells. AIRE variants cause APECED (autoimmune polyendocrinopathy-candidiasis-ectodermal dystrophy): chronic mucocutaneous candidiasis plus endocrine gland failure.
- Regulatory T cells: FOXP3 is essential for Treg development and function. FOXP3 variants cause IPEX, an X-linked recessive syndrome of autoimmune enteropathy (severe diarrhea), type 1 diabetes, eczema and thyroid disease.
- Lymphocyte apoptosis: FAS variants (about 75% of cases) cause autoimmune lymphoproliferative syndrome (ALPS): lymphadenopathy, splenomegaly, autoimmune hemolytic anemia and thrombocytopenia, and a high lymphoma risk.
- Altered self-antigens: chemicals binding to body proteins, or UV light changing keratinocytes, can make self-antigens immunogenic.
- Molecular mimicry: antibodies to a foreign antigen cross-react with self, as when antibodies to streptococcal M protein react with heart muscle in rheumatic fever (see molecular mimicry).
- Genes and sex: most autoimmune diseases are polygenic, HLA variants nearly always contribute (for example, HLA DR3-DQ2.5 or DR4-DQ8 in more than 90% of patients with type 1 diabetes before age 30), and women are affected more often than men.
More on these checkpoints is in the immune tolerance breakdown.
Autoimmune diseases by mechanism
| Type | Effector | How tissue is damaged | Autoimmune examples (target) |
|---|---|---|---|
| II, cytotoxic | IgG or IgM against a cell-surface or matrix antigen | Complement (membrane attack complex), opsonization and phagocytosis, antibody-dependent cellular cytotoxicity | Anti-GBM disease (type IV collagen), autoimmune hemolytic anemia (RBC antigens), ITP (platelet antigens), pemphigus vulgaris (desmoglein), bullous pemphigoid (BP180, BP230), acute rheumatic fever (mimicry) |
| II, receptor | IgG against a receptor | Changes receptor function without killing the cell | Graves disease (stimulates the TSH receptor), myasthenia gravis (AChR destruction and blockade) |
| III, immune complex | Antigen-antibody complexes | Deposition in vessels, glomeruli and joints; classical complement activation; neutrophils | SLE, post-streptococcal GN, serum sickness, Arthus reaction, polyarteritis nodosa (hepatitis B), cryoglobulinemia (hepatitis C), rheumatoid arthritis, IgA vasculitis |
| IV, T cell | CD4+ (Th1, Th2, Th17) and CD8+ T cells, macrophages | Cytokine-driven inflammation and direct killing; no antibody | Type 1 diabetes (beta cells); also contact dermatitis, tuberculin test, transplant rejection |
Most autoantibodies block or damage their targets; the antibody in Graves disease is the classic exception because it stimulates the TSH receptor, causing continuous thyroid hormone release.
Reading immunofluorescence: linear vs granular
| Pattern | Mechanism | Classic diseases |
|---|---|---|
| Linear IgG and C3 along the GBM | Type II: antibody bound evenly to a fixed antigen | Anti-GBM disease; Goodpasture syndrome when the lungs bleed |
| Linear IgG and complement along the epidermal basement membrane zone | Type II | Bullous pemphigoid |
| IgG on keratinocyte cell surfaces within the epidermis | Type II | Pemphigus vulgaris |
| Granular deposits | Type III: immune complexes deposited in clumps | Lupus nephritis, post-streptococcal GN |
Glomerular patterns, including the pauci-immune group, are sorted in rapidly progressive glomerulonephritis by immunofluorescence.
How USMLE tests it
- Ask two questions: is the damage done by antibody or by T cells? If antibody, does it bind a fixed antigen (type II) or form immune complexes (type III)?
- Low C3 and C4 point to complement consumption by immune complexes (type III), as in SLE and post-streptococcal GN.
- Linear vs granular on immunofluorescence separates anti-GBM disease from immune complex nephritis.
- Receptor antibodies are type II: stimulating in Graves disease, destructive and blocking in myasthenia gravis.
- Anti-dsDNA is highly specific for SLE, and rising titers often signal active nephritis (the classic "anti-dsDNA means nephritis" link); anti-Smith is highly specific but not sensitive; ANA is the sensitive screening test.
- Type 1 diabetes: islet autoantibodies help diagnose it, but beta cells are destroyed mainly by T cells.
Key takeaways
- Autoimmune damage is type II (antibody to a fixed antigen or receptor), type III (immune complexes) or type IV (T cells).
- Lupus nephritis = type III: anti-dsDNA immune complexes, granular deposits, low C3 and C4, RBC casts.
- Anti-GBM disease = type II: antibodies to type IV collagen, linear IgG, crescentic GN with or without lung hemorrhage.
- Pemphigus vulgaris (desmoglein, intraepidermal, flaccid, oral) vs bullous pemphigoid (hemidesmosome, subepidermal, tense, older adults).
- Myasthenia gravis blocks and destroys AChRs; Graves antibodies stimulate the TSH receptor.
- Tolerance failure: AIRE (APECED), FOXP3 (IPEX), FAS (ALPS), molecular mimicry and HLA risk.
Sources
- Autoimmune Disorders — Merck Manual Professional Edition (2026)
- Type II Hypersensitivity Reaction — StatPearls, NCBI Bookshelf (2025)
- Type III Hypersensitivity Reaction — StatPearls, NCBI Bookshelf (2025)
- Type IV Hypersensitivity Reaction — StatPearls, NCBI Bookshelf (2025)
- Systemic Lupus Erythematosus (SLE) — Merck Manual Professional Edition (2025)
- Lupus Nephritis — StatPearls, NCBI Bookshelf (2025)
- Rapidly Progressive Glomerulonephritis — StatPearls, NCBI Bookshelf (2024)
- Myasthenia Gravis — Merck Manual Professional Edition (2026)
- Pemphigus Vulgaris — Merck Manual Professional Edition (2024)
- Bullous Pemphigoid — Merck Manual Professional Edition (2024)
- Type 1 Diabetes Mellitus — Merck Manual Professional Edition (2025)
- IPEX Syndrome — MedlinePlus Genetics
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
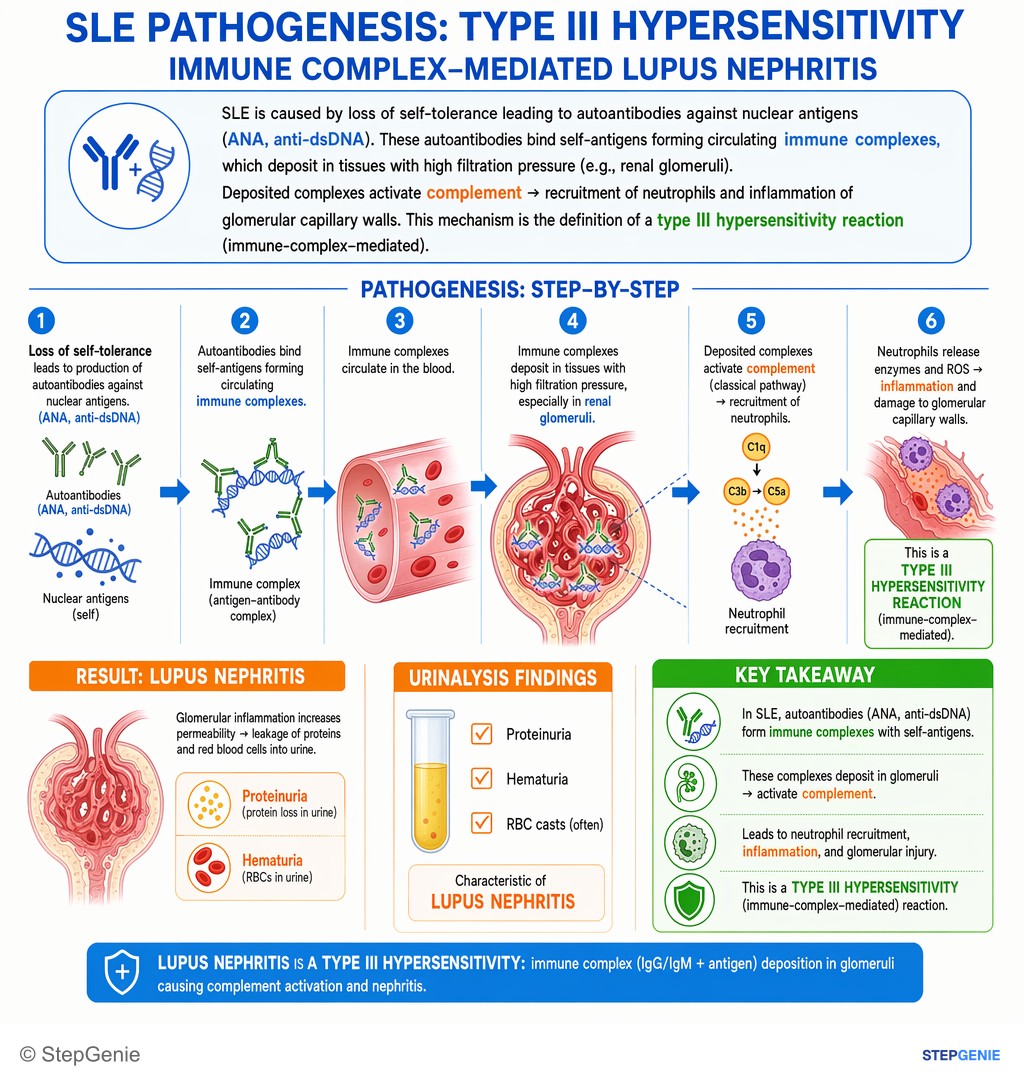
Lupus nephritis is a type III hypersensitivity: immune complex (IgG/IgM + antigen) deposition in glomeruli causing complement activation…
USMLE Step 1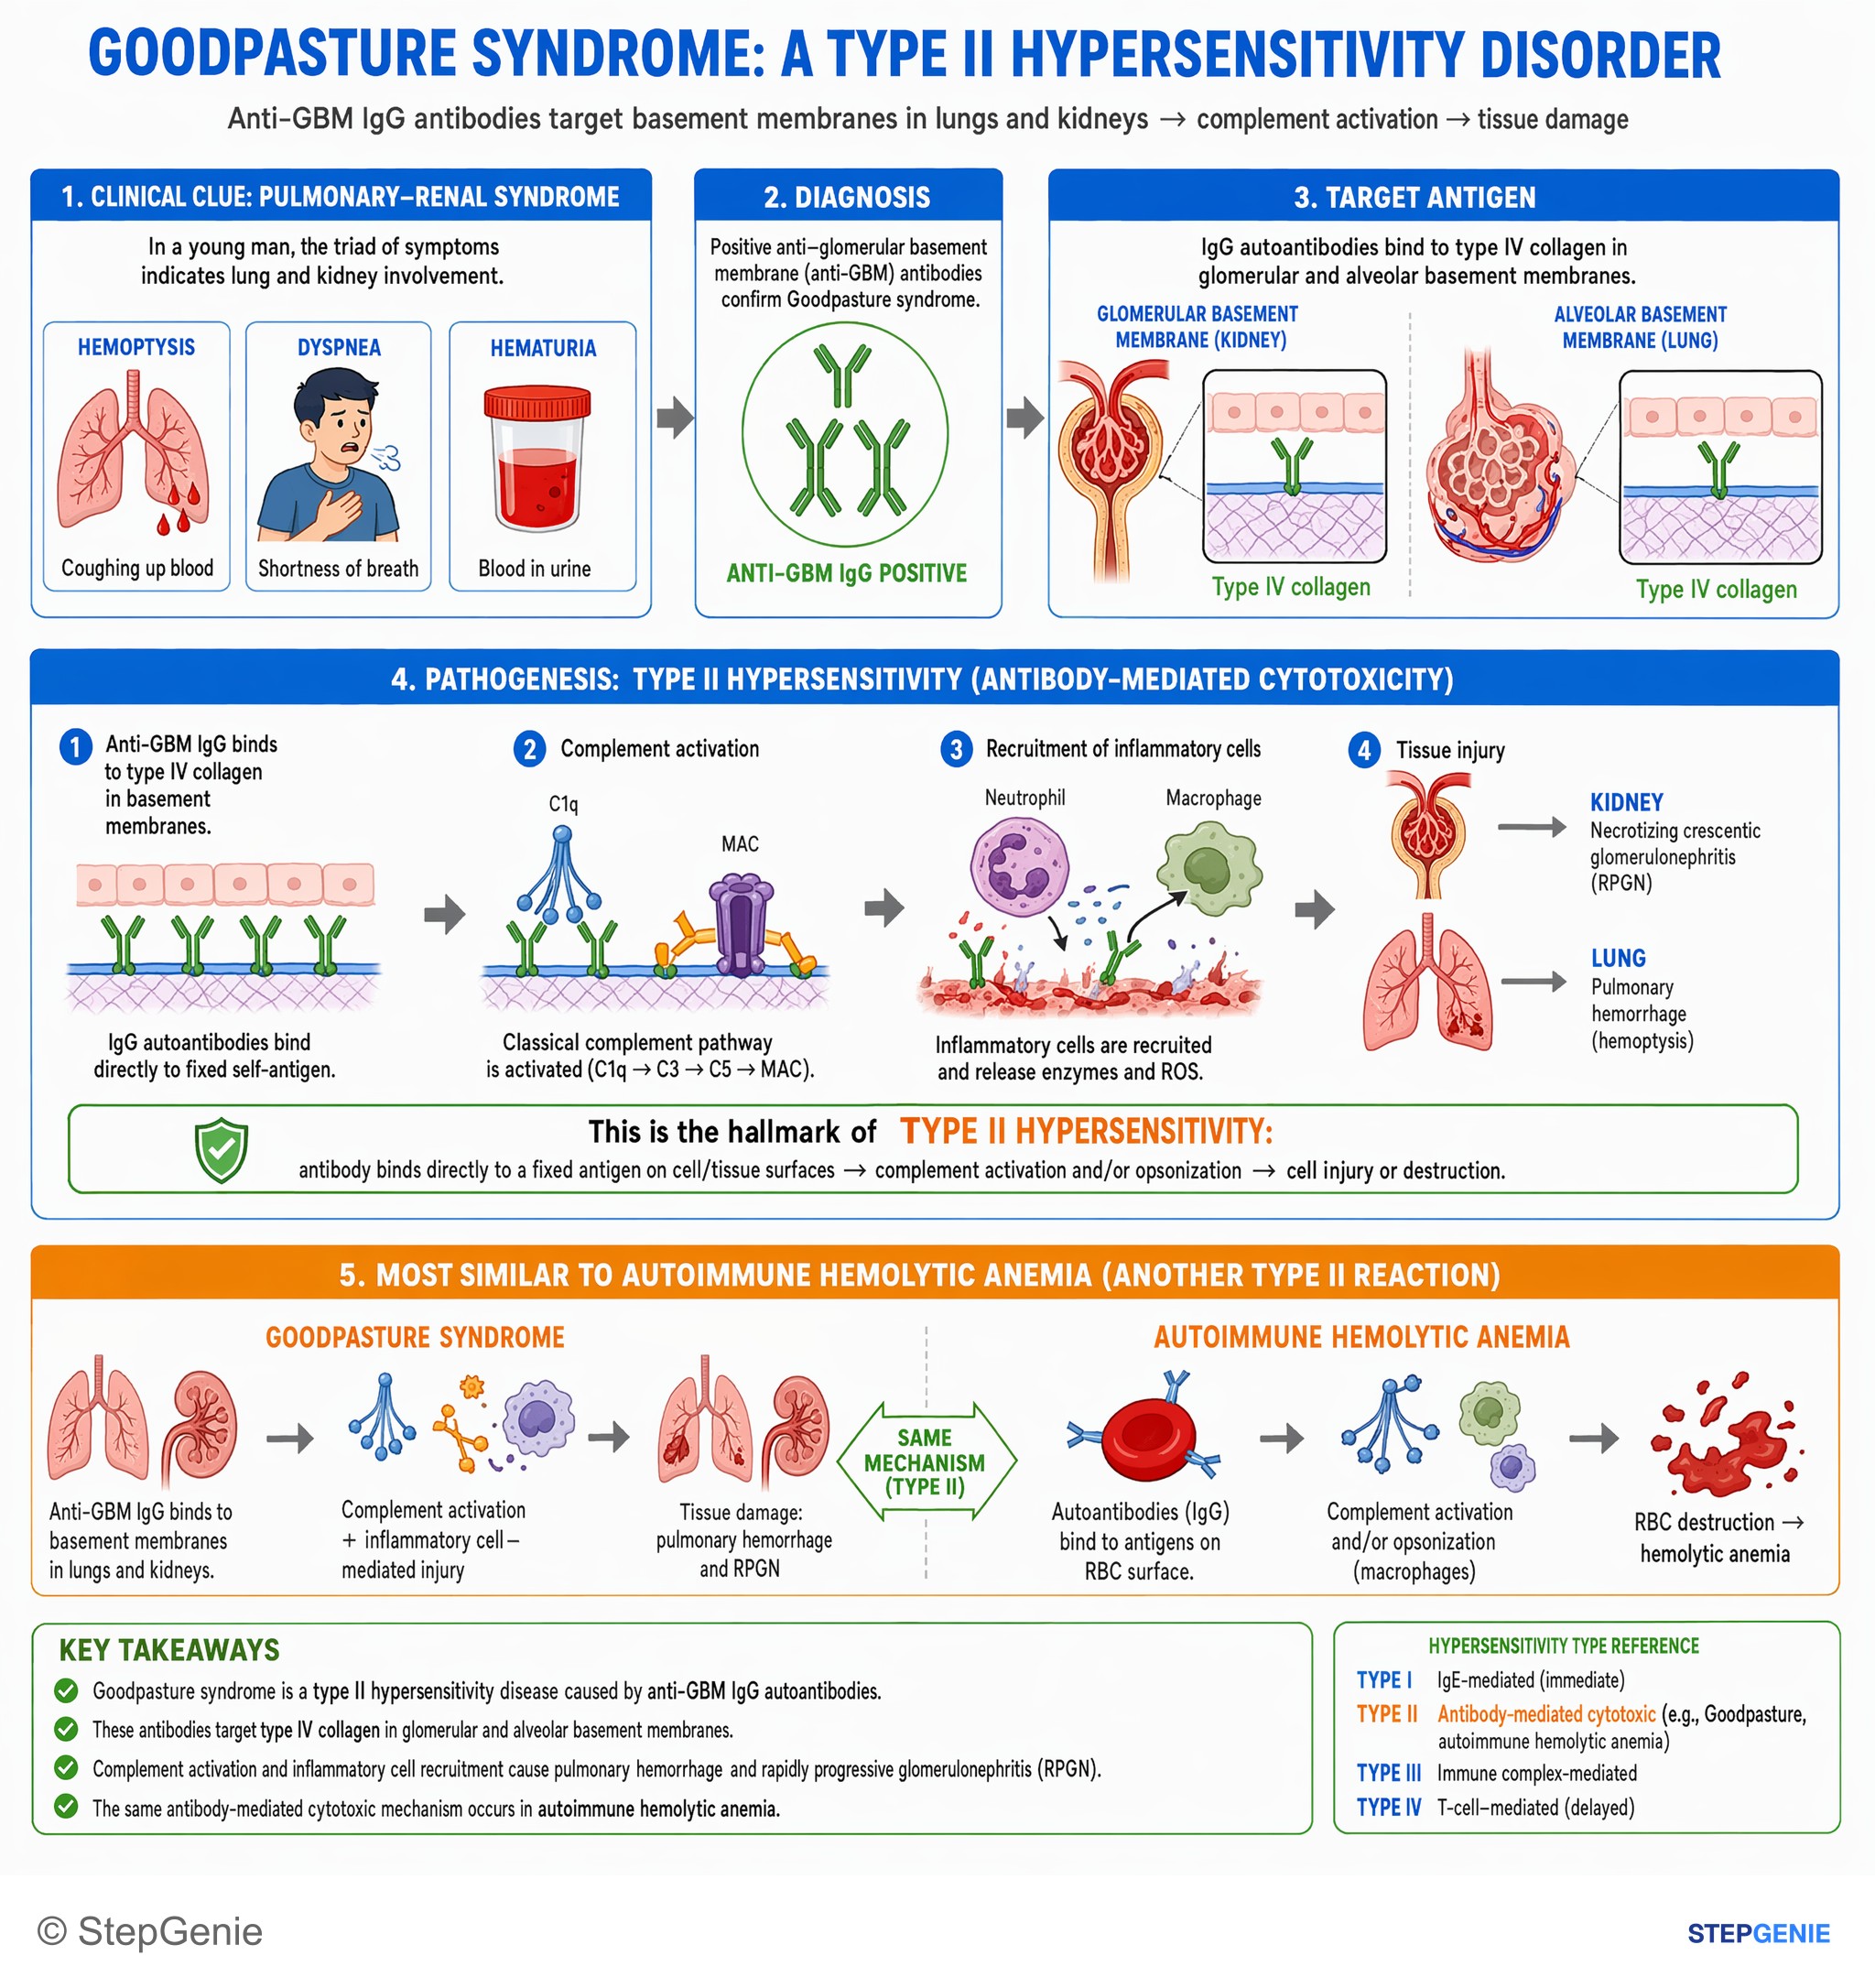
Goodpasture syndrome: type II hypersensitivity with anti-GBM IgG causing pulmonary hemorrhage and RPGN; mechanism mirrors other…
USMLE Step 1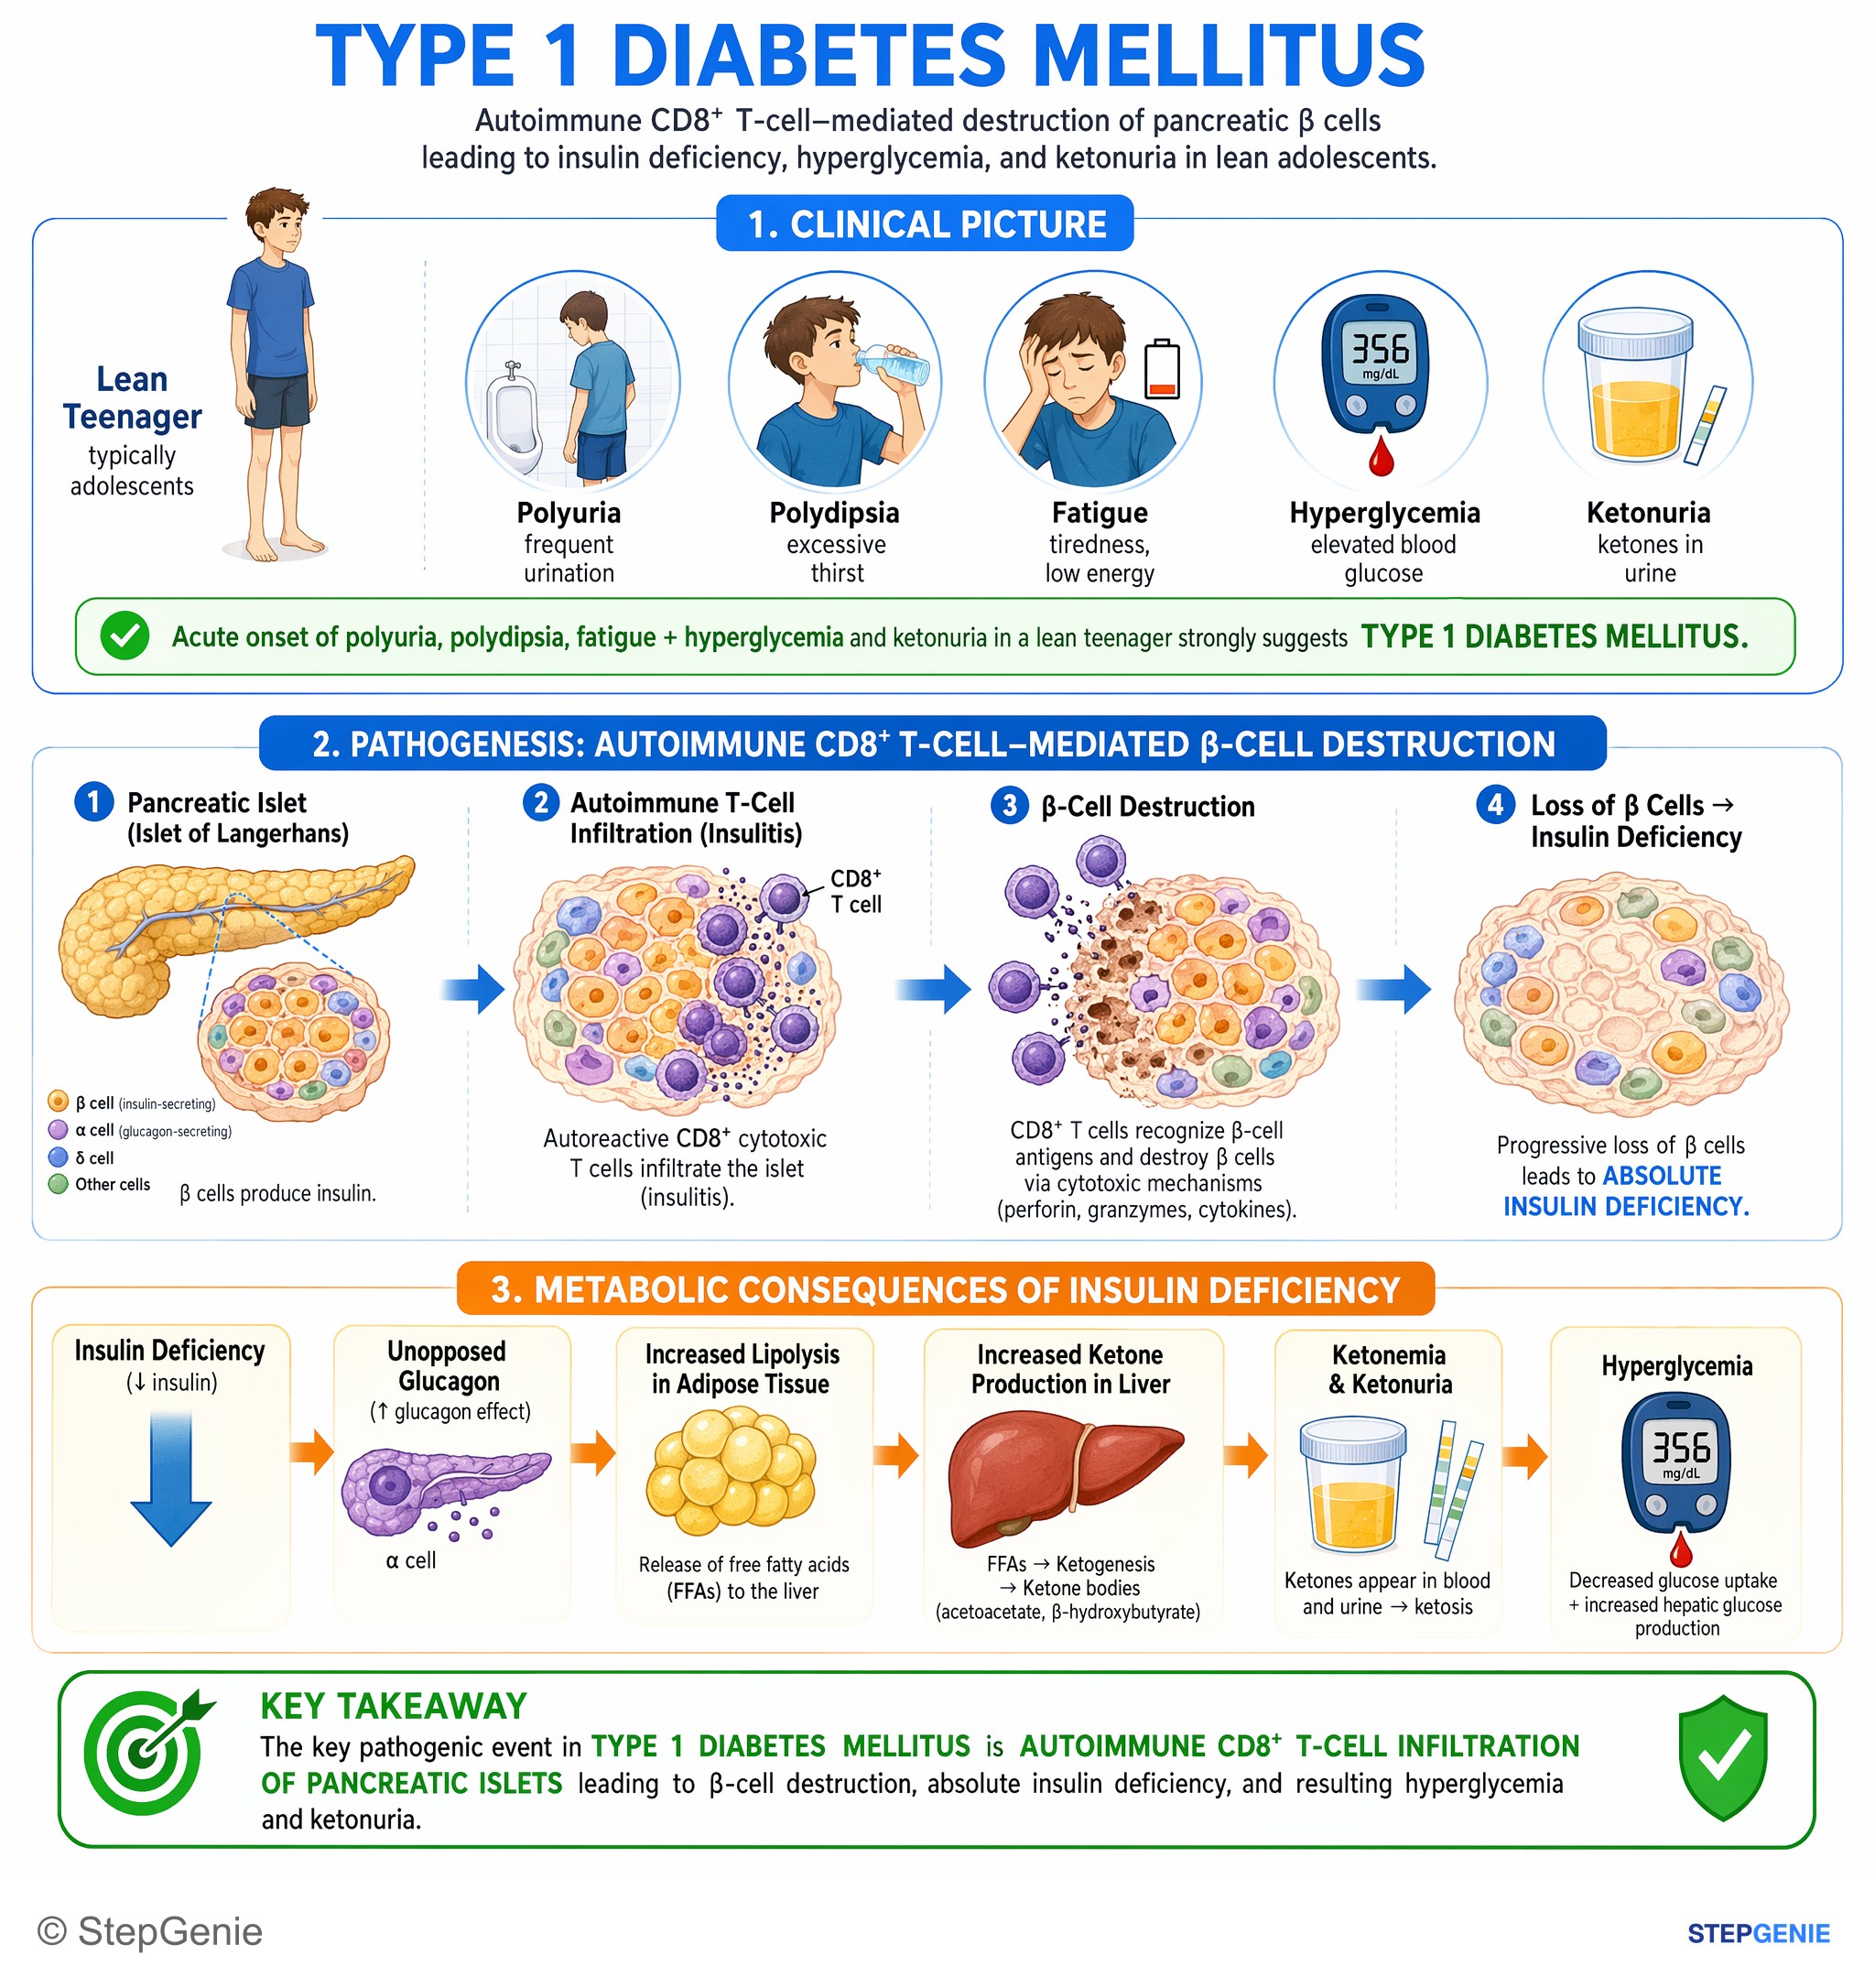
Type 1 diabetes mellitus: autoimmune CD8⁺ T-cell–mediated destruction of pancreatic β cells → insulin deficiency, hyperglycemia, ketonuria…
USMLE Step 1Frequently Asked Questions
What are the mechanisms of autoimmune disease?
Autoimmunity starts when tolerance fails: self-reactive T cells escape deletion in the thymus (AIRE), regulatory T cells fail (FOXP3), lymphocyte apoptosis fails (FAS), self-antigens are altered by chemicals or UV light, or antibodies against microbes cross-react with self (molecular mimicry). Genes, especially HLA variants, set the risk. Tissue damage then follows type II (antibody against a fixed antigen), type III (immune complex deposition) or type IV (T-cell) hypersensitivity.
What is the difference between type II and type III hypersensitivity?
In type II, IgG or IgM binds an antigen fixed on a cell surface, basement membrane or receptor, causing complement-mediated lysis, phagocytosis, cell-mediated cytotoxicity or a change in receptor function; examples are anti-GBM disease, myasthenia gravis, Graves disease and pemphigus vulgaris. In type III, antibodies and antigens form immune complexes that deposit in vessels, glomeruli and joints, activate complement and lower C3 and C4; examples are SLE, post-streptococcal glomerulonephritis and serum sickness.
Why does lupus nephritis show granular immunofluorescence while anti-GBM disease is linear?
In lupus nephritis, anti-dsDNA antibodies bind DNA to form immune complexes that deposit unevenly in mesangial, subendothelial and subepithelial sites, so immunofluorescence shows granular clumps of immunoglobulin and complement. In anti-GBM disease, antibodies bind the alpha-3 chain of type IV collagen that runs continuously along the glomerular basement membrane, so IgG and C3 line up in a smooth linear pattern. Goodpasture syndrome is anti-GBM disease with pulmonary hemorrhage.
Why is complement low in SLE?
Immune complexes deposited in tissues activate the classical complement pathway, and this consumption lowers serum C3, C4 and total hemolytic complement (CH50). In SLE, C3 and C4 are often low during active disease and are usually lowest in patients with active nephritis. Low complement is therefore a clue to an immune complex (type III) process, and it helps separate SLE and post-streptococcal glomerulonephritis from type II and T-cell-mediated diseases.
Is type 1 diabetes a type IV hypersensitivity?
Type 1 diabetes is the classic autoimmune example of T-cell-mediated injury: a primarily T-cell response destroys pancreatic beta cells, producing insulitis. Autoantibodies against islet antigens such as GAD65, insulin, IA-2 and ZnT8 are useful markers, but they seem to be a response to the destruction rather than its cause. HLA DR3-DQ2.5 and DR4-DQ8 haplotypes are present in more than 90% of patients with type 1 diabetes who are younger than 30.
Are myasthenia gravis and Graves disease type II hypersensitivity?
Yes. Both are antibody-mediated type II diseases in which IgG binds a cell-surface receptor. In myasthenia gravis, antibody- and cell-mediated damage destroys acetylcholine receptors at the neuromuscular junction, causing fatigable weakness, ptosis and diplopia. In Graves disease, the antibody (thyroid-stimulating immunoglobulin) is unusual because it stimulates the TSH receptor instead of inhibiting it, causing continuous thyroid hormone release and hyperthyroidism.