Streptococcus pneumoniae is a gram-positive, lancet-shaped diplococcus wrapped in a polysaccharide capsule. It is alpha-hemolytic, optochin-sensitive and bile-soluble, and its capsule swells in the quellung reaction. It causes MOPS (meningitis, otitis media, pneumonia, sinusitis) plus bacteremia, and the capsule makes it most dangerous for people who cannot opsonize or filter it: asplenia and sickle cell disease, antibody or complement deficiency, HIV, and the very young and old. Current CDC schedules give infants a 4-dose PCV15 or PCV20 series and recommend a conjugate vaccine for all adults 50 or older who have not had one: PCV20 or PCV21 alone, or PCV15 followed by PPSV23.
The 60-second sketch
Draw these seven pieces in order; each one is a testable fact.
- Two slightly pointed ovals side by side, colored purple. Gram-positive, lancet-shaped diplococci, about 0.5–1.25 µm. Write "catalase negative" underneath.
- A thick clear halo around the pair, with a dotted outer ring. The polysaccharide capsule: more than 100 serotypes, blocks phagocytosis, and is the antigen in every current vaccine. The dotted ring is the quellung reaction: the capsule swells when mixed with type-specific antiserum.
- A blood agar plate with a green ring around a dimpled colony. Alpha-hemolysis (partial, greenish). After 24–48 hours a pneumococcal colony flattens and its center sinks, a clue the WHO lab manual uses to separate it from viridans streptococci.
- A paper disk with a wide clear zone, next to a test tube that turns clear. Optochin: an inhibition zone larger than 14 mm around a 6-mm disk identifies pneumococci. Bile (deoxycholate) triggers autolysis, so a cloudy suspension clears.
- Scissors cutting a Y-shaped antibody, and a hole punch. IgA1 protease cleaves human IgA1, separating its Fc effector end from the antigen-binding end, which helps the bacterium colonize mucosa. Pneumolysin is a pore-forming toxin that damages host cells and drives inflammation.
- A head labeled M, O, P, S, with rust-colored sputum coming from the lungs. Meningitis, otitis media, pneumonia, sinusitis.
- A spleen with an X through it, and a syringe beside it. Without a spleen, encapsulated bacteria are poorly cleared; prevention is vaccination plus, in young asplenic children, daily penicillin.
One-liner to say out loud: "Purple lancets in a halo, green and dimpled on agar, stopped by optochin, dissolved by bile, cutting IgA, causing MOPS, deadly without a spleen."
Lab ID: pneumococcus vs viridans streptococci
Both are alpha-hemolytic, so hemolysis alone never settles it.
| Test | S. pneumoniae | Viridans streptococci |
|---|---|---|
| Hemolysis on blood agar | Alpha (green) | Alpha (green) |
| Colony at 24–48 hours | Flattens; center becomes depressed | No central depression |
| Optochin (6-mm disk) | Susceptible (zone > 14 mm) | Resistant |
| Bile (2% deoxycholate) | Soluble: cells lyse, tube clears | Insoluble |
| Quellung reaction | Positive (capsular swelling) | Negative |
Other bench facts: most isolates are alpha-hemolytic aerobically but can be beta-hemolytic when grown anaerobically, and the urine antigen test (C-polysaccharide) is more than 90% specific but only 50–80% sensitive.
Virulence factors worth drawing
| Factor | What it does | Exam tie-in |
|---|---|---|
| Polysaccharide capsule | Blocks phagocytosis; clearance needs opsonizing antibody and complement plus the spleen | Asplenia, sickle cell, hypogammaglobulinemia and complement deficiency raise risk; vaccine antigen; quellung |
| Pneumolysin | Pore-forming toxin: damages host cells, promotes adherence, boosts cytokines | Lung injury and inflammation |
| IgA1 protease | Cleaves human IgA1 so the antibody loses its effector (Fc) end | Mucosal colonization |
Carriage is common: 20–60% of school-age children and 5–10% of adults without children carry pneumococci in the nasopharynx, and spread is by respiratory droplets.
MOPS and more: how it shows up
| Disease | Classic stem | Key facts |
|---|---|---|
| Meningitis | Fever, headache, stiff neck; CSF with neutrophils, high protein, low glucose | Most common cause in middle-aged and older adults; leading cause of bacterial meningitis in US children under 5. Treat empirically with vancomycin plus ceftriaxone or cefotaxime (penicillin G only once the isolate proves susceptible), with dexamethasone just before or with the first antibiotic dose |
| Otitis media | Young child with ear pain after a cold | Pneumococci are found in 24–31% of middle-ear aspirates |
| Pneumonia | Abrupt fever and chills, pleuritic chest pain, rusty sputum, lobar consolidation | Incubation about 1–3 days; causes 10–30% of adult community-acquired pneumonia and is the most common bacterial cause of pneumonia requiring hospitalization |
| Sinusitis | Sinus pain and congestion, often after a cold | Common and less serious, like otitis media |
| Bacteremia and beyond | Sepsis, often with pneumonia | Case fatality about 12% overall (CDC Pink Book); also endocarditis, septic arthritis, rarely peritonitis |
Compare the other causes and CSF patterns in the bacterial meningitis Q-bank breakdown.
Resistance: about 2 in 5 pneumococcal infections are caused by strains non-susceptible to at least one antibiotic (CDC). Penicillin resistance comes from altered penicillin-binding proteins, not β-lactamase, so adding a β-lactamase inhibitor does not help; macrolide resistance is about 35% (Merck).
Who gets invasive disease, and why
A capsule means the bacterium must be coated with antibody and complement (opsonized) and then removed, largely by the spleen. Break any link and invasive disease follows.
- Asplenia, anatomic or functional: children with sickle cell disease or asplenia have invasive disease rates more than 50 times higher than other children in some studies (CDC Pink Book). Merck recommends oral penicillin V twice daily for asplenic children younger than 5. The spleen story is reviewed in the sickle cell disease Q-bank.
- Opsonization defects: hypogammaglobulinemia and complement deficiencies, laid out in the complement deficiencies table.
- Other CDC risk groups: age under 5 or 50 and older, HIV and other immunocompromising conditions, chronic heart, lung, liver or kidney disease, diabetes, alcoholism or smoking, CSF leak, and cochlear implants.
Vaccines: what CDC recommends now
Immunology first. PPSV23 is a plain polysaccharide: a T-cell-independent antigen with a poor response in children younger than 2 and no sustained booster effect. Conjugate vaccines (PCV) link polysaccharide to a protein carrier, giving a T-dependent response with memory and less nasopharyngeal carriage, the same logic as the Hib conjugate vaccine.
| Group | Current CDC recommendation |
|---|---|
| Infants and children younger than 5 | 4 doses of PCV15 or PCV20 at 2, 4, 6 and 12–15 months; catch-up doses depend on the age when vaccination starts |
| Children 2–18 years with a risk condition | May need extra PCV15, PCV20 or PPSV23 doses, depending on age and prior doses (CDC risk-based schedule) |
| Adults 50 or older who never received a PCV (or unknown) | PCV20 or PCV21 alone, or PCV15 then PPSV23 1 year later (minimum 8 weeks with an immunocompromising condition, cochlear implant or CSF leak) |
| Adults 19–49 with a risk condition | Same options as above |
| Adults 65 or older who had PCV13 (at any age) and PPSV23 at 65 or older | Shared clinical decision-making: a dose of PCV20 or PCV21, or no further pneumococcal vaccine |
After PCV20 or PCV21, no PPSV23 is needed. PCV21 appears only in CDC's adult recommendations; the infant series uses PCV15 or PCV20.
Practice question
A 6-year-old boy with sickle cell disease has fever, headache and neck stiffness. He stopped his daily penicillin a year ago, and his vaccine record is incomplete. CSF shows many neutrophils, low glucose and gram-positive lancet-shaped diplococci. Culture grows alpha-hemolytic colonies with sunken centers that are inhibited by an optochin disk and dissolve in deoxycholate. Which bacterial component explains his susceptibility and is the antigen in the vaccines that could have prevented this infection?
- A. Pneumolysin
- B. IgA1 protease
- C. Polysaccharide capsule
- D. Peptidoglycan cell wall
- E. Polyribosyl-ribitol phosphate (PRP)
Answer: C. The capsule blocks phagocytosis, and clearing it depends on opsonization and the spleen. Sickle cell disease causes functional asplenia, so encapsulated pneumococci invade. PCV15, PCV20, PCV21 and PPSV23 are all built from capsular polysaccharides.
- A: pneumolysin damages host cells and fuels inflammation, but it is not the vaccine antigen and does not explain why asplenia matters.
- B: IgA1 protease helps colonization of the mucosa by disabling IgA1; it is also not a vaccine component.
- D: peptidoglycan is the thick wall of every gram-positive bacterium and the target of β-lactams, not a vaccine.
- E: PRP is the type b capsule of Haemophilus influenzae and the Hib vaccine antigen; the organism here is gram-positive.
Key takeaways
- Sketch it: purple lancet diplococci, capsule halo with quellung ring, green dimpled colony, optochin zone and clearing bile tube, IgA scissors, MOPS head, crossed-out spleen.
- Vs viridans: both alpha-hemolytic; pneumococcus is optochin-susceptible, bile-soluble and quellung-positive.
- MOPS plus bacteremia; rusty sputum and lobar consolidation; empiric vancomycin plus ceftriaxone for meningitis.
- Capsule = virulence and vaccine target; asplenia and sickle cell disease raise invasive risk more than 50-fold in some studies of children.
- Penicillin resistance is from altered PBPs, not β-lactamase.
- Vaccines (CDC): infants get 4 doses of PCV15 or PCV20; adults 50 or older get PCV20 or PCV21 alone, or PCV15 then PPSV23.
Sources
- Pneumococcal Vaccine Recommendations — CDC (updated February 2026)
- Summary of Risk-based Pneumococcal Vaccination Recommendations — CDC (updated May 2026)
- Epidemiology and Prevention of Vaccine-Preventable Diseases (Pink Book), Chapter 17: Pneumococcal Disease — CDC
- Pink Book, Chapter 8: Haemophilus influenzae (conjugate vaccines and PRP) — CDC
- Clinical Overview of Pneumococcal Disease — CDC (2026)
- Antibiotic-resistant Streptococcus pneumoniae — CDC (2026)
- Pneumococcal Infections — Merck Manual Professional Edition
- Acute Bacterial Meningitis — Merck Manual Professional Edition
- Laboratory Methods for the Diagnosis of Meningitis Caused by Neisseria meningitidis, Streptococcus pneumoniae, and Haemophilus influenzae — World Health Organization (1999)
- Patterson MJ. Streptococcus, in Medical Microbiology, 4th ed. — NCBI Bookshelf (1996)
- Bacterial Infections of the Respiratory Tract (pneumolysin) — OpenStax Microbiology
- Janoff EN, et al. Pneumococcal IgA1 protease subverts specific protection by human IgA1 — Mucosal Immunology (2014)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
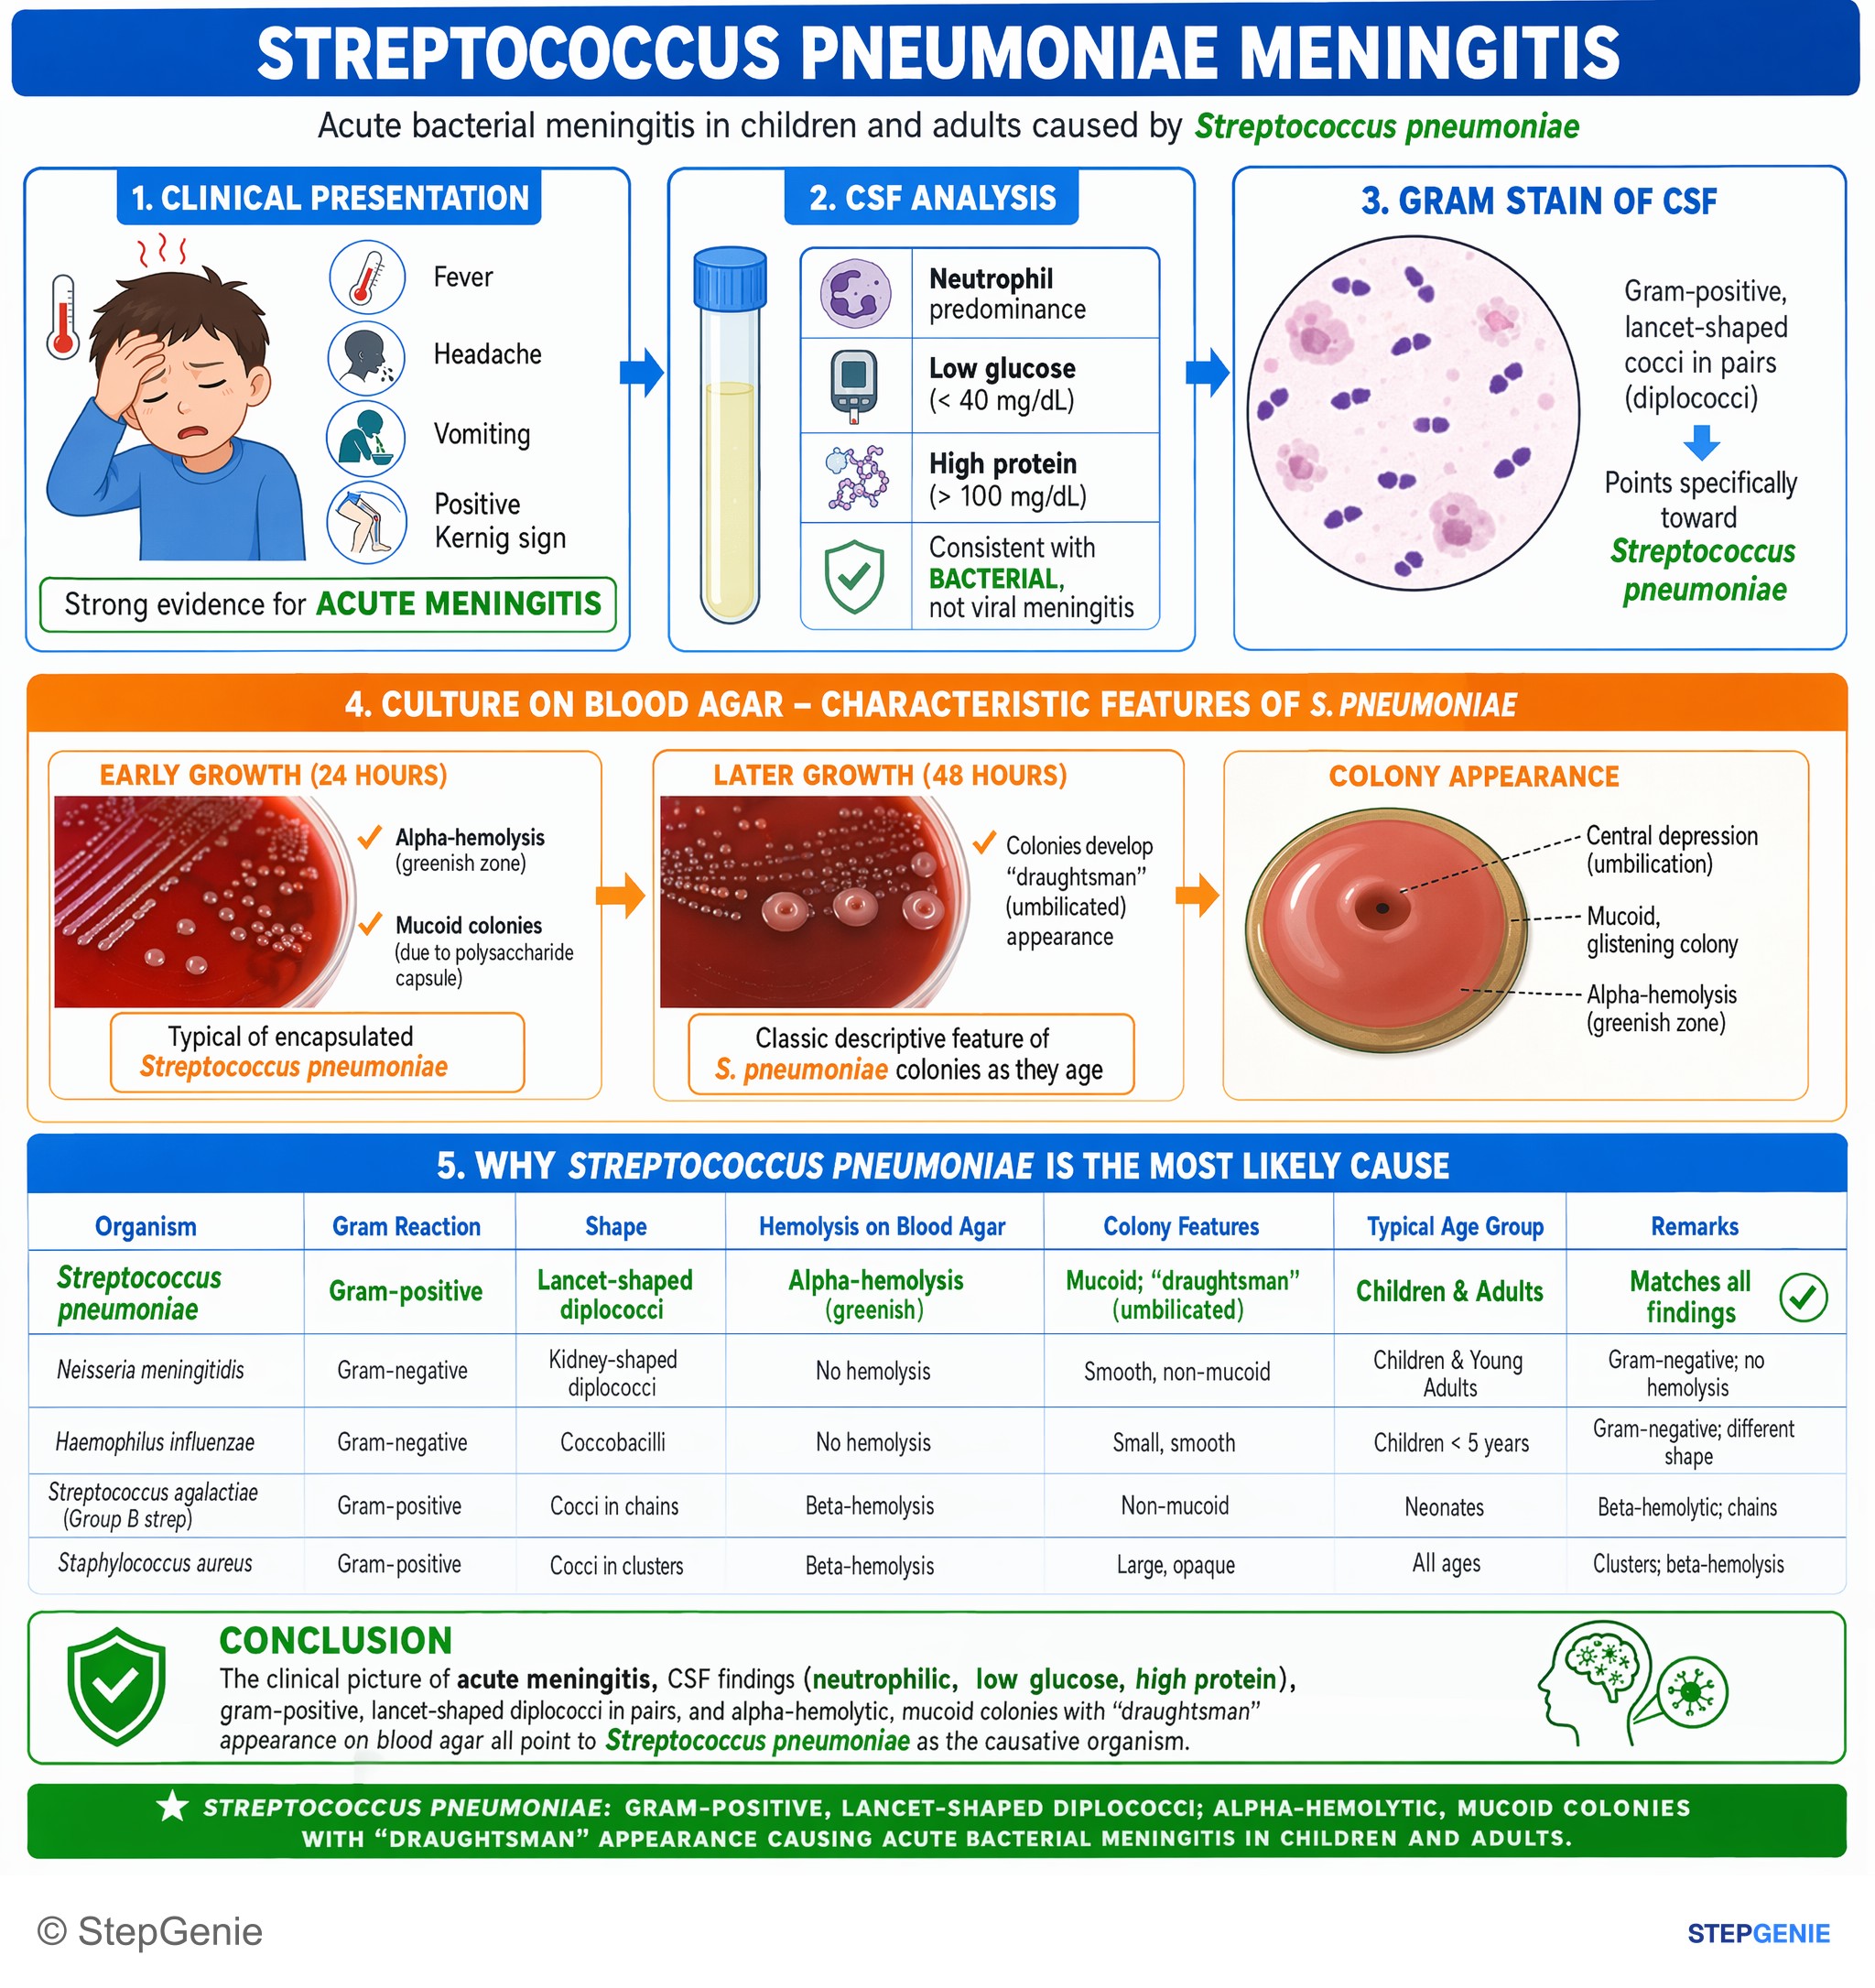
Streptococcus pneumoniae meningitis: gram-positive, lancet-shaped diplococci; alpha-hemolytic, mucoid colonies with “draughtsman”…
USMLE Step 1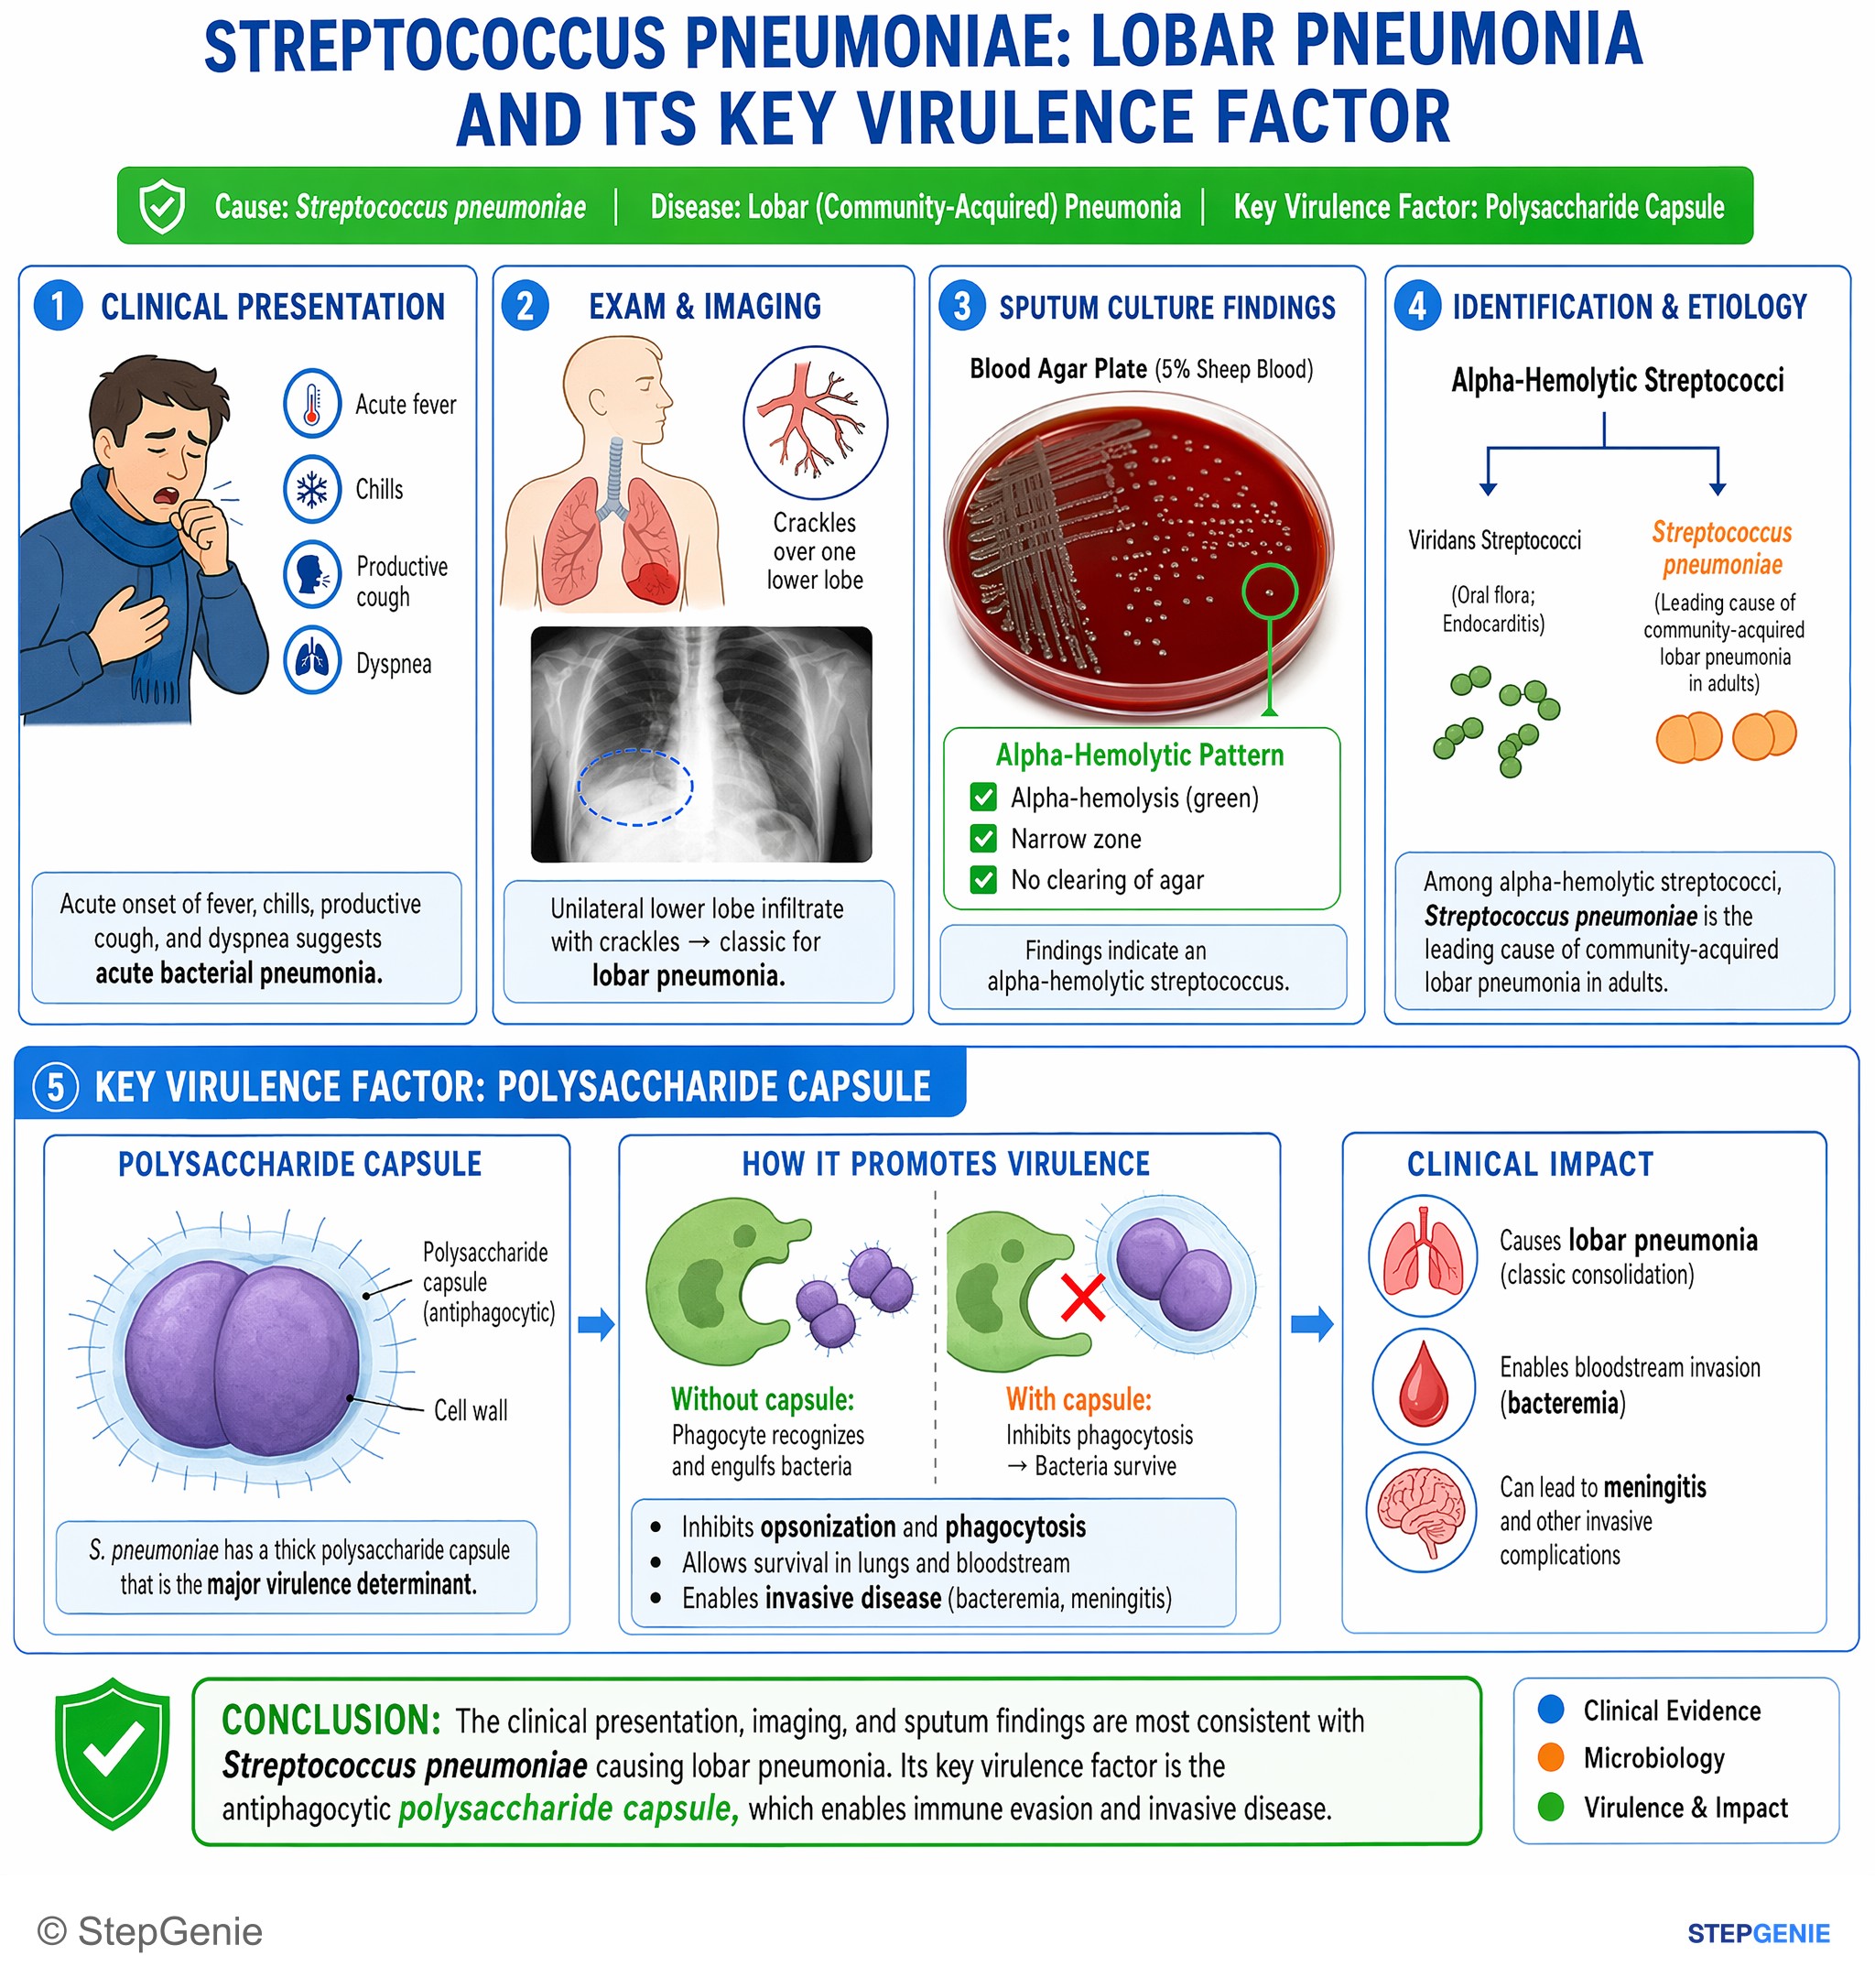
Streptococcus pneumoniae causes lobar pneumonia; its key virulence factor is an antiphagocytic polysaccharide capsule enabling immune…
USMLE Step 1Frequently Asked Questions
How do you tell Streptococcus pneumoniae from viridans streptococci?
Both are alpha-hemolytic, so hemolysis does not separate them. S. pneumoniae is optochin-susceptible (an inhibition zone larger than 14 mm around a 6-mm disk), bile-soluble (it lyses in deoxycholate) and quellung-positive because of its capsule. Viridans streptococci are optochin-resistant and bile-insoluble, and pneumococcal colonies, unlike viridans colonies, flatten and develop a sunken center after 24 to 48 hours.
Why are people without a spleen at high risk for pneumococcal infection?
The polysaccharide capsule of S. pneumoniae blocks phagocytosis, so the body must coat the bacteria with antibody and complement and clear them, largely in the spleen. Without a working spleen, as after splenectomy or in sickle cell disease, this clearance fails and invasive disease such as bacteremia and meningitis follows. The CDC Pink Book notes that children with sickle cell disease or asplenia have had invasive disease rates more than 50 times higher than other children in some studies.
What diseases does Streptococcus pneumoniae cause?
The classic list is MOPS: meningitis, otitis media, pneumonia and sinusitis, plus bacteremia. Pneumococcal pneumonia typically starts abruptly with fever, chills, pleuritic chest pain and rusty sputum, with lobar consolidation. Less often it causes endocarditis, septic arthritis and peritonitis.
What is the quellung reaction?
The quellung reaction is swelling of the pneumococcal capsule when the bacteria are mixed with type-specific anticapsular antiserum. It identifies S. pneumoniae, distinguishes it from viridans streptococci, and is a classic method for determining its serotype. More than 100 capsular serotypes have been identified.
Which pneumococcal vaccines does the CDC recommend now?
The CDC recommends a 4-dose series of PCV15 or PCV20 for infants at 2, 4, 6 and 12 to 15 months. Adults 50 or older who have never received a conjugate vaccine should get PCV20 or PCV21 alone, or PCV15 followed by PPSV23 one year later, and adults 19 to 49 with risk conditions such as asplenia, HIV, a CSF leak or a cochlear implant get the same options. Children and adolescents with risk conditions may need extra doses under CDC's risk-based schedule.
What is the difference between pneumococcal conjugate and polysaccharide vaccines?
PPSV23 contains plain capsular polysaccharide, a T-cell-independent antigen that gives a poor response in children younger than 2 and no sustained booster effect. Conjugate vaccines (PCV15, PCV20, PCV21) link the polysaccharide to a carrier protein, producing a T-cell-dependent response with memory and reducing nasopharyngeal carriage. Both target the capsule.