Staphylococcus aureus is the “high-yield chaos agent” of Gram-positive bugs: it colonizes skin/nose, loves broken barriers (IV lines, wounds), and its toxins turn routine infections into board-style vignettes. If you can (1) recognize MRSA patterns and (2) map toxin → symptom → mechanism, you’ll pick up easy points on both Step 1 and Step 2.
The 10-second ID: how to recognize S. aureus fast
Core lab identity
- Gram-positive cocci in clusters (“grapes”)
- Catalase-positive (bubbles with )
- Coagulase-positive (clots plasma)
- Often β-hemolytic, golden colonies
- Mannitol fermenter on MSA (turns yellow)
Classic clinical vibe
- Skin/soft tissue: abscesses, furuncles, carbuncles
- Invasive: bacteremia → endocarditis, osteomyelitis, septic arthritis
- Toxin-mediated: food poisoning, toxic shock, scalded skin
Visual mnemonic device: “MRSA wears a bulletproof VEST”
Picture S. aureus as a tough bouncer in a bulletproof vest:
VEST
- V = Vancomycin (classic severe MRSA therapy; not for simple MSSA if β-lactams work)
- E = Enterotoxin (preformed toxin → rapid vomiting)
- S = Superantigen (TSST-1 → toxic shock)
- T = Toxin that cleaves (exfoliative toxin cleaves desmoglein-1 → scalded skin)
One-liner: S. aureus causes abscesses + toxin syndromes, and MRSA is the strain where many β-lactams bounce off the “vest.”
Shareable comparison table: S. aureus (MSSA vs MRSA + toxins)
| Bucket | High-yield entity | Key virulence / mechanism | Classic presentation | Buzzwords / Step clues | First-line treatment (exam-style) |
|---|---|---|---|---|---|
| Baseline bug | S. aureus | Protein A binds Fc of IgG → blocks opsonization; coagulase forms fibrin clot “shell”; catalase+ | Abscesses, cellulitis, impetigo (bullous), pneumonia (post-flu), bacteremia | “Pus-forming,” clusters, coagulase+ | Depends on susceptibility + site |
| MSSA | Methicillin-susceptible S. aureus | No mecA-mediated PBP change | Typical SSTI, bacteremia, endocarditis | “Susceptible to nafcillin/oxacillin” | Nafcillin/oxacillin (or cefazolin) for serious disease |
| Community-acquired MRSA (CA-MRSA) | MRSA (often PVL+) | mecA → altered PBP (PBP2a) → β-lactam resistance; may have PVL leukocidin | Purulent skin abscesses, “spider bite” lesion; sometimes necrotizing pneumonia | Healthy person, contact sports, prison, military; recurrent abscesses | TMP-SMX, doxycycline, clindamycin (check local resistance); I&D for abscess |
| Hospital-acquired MRSA (HA-MRSA) | MRSA in healthcare | mecA; higher multidrug resistance | Line-associated bacteremia, VAP, postop wounds | Recent hospitalization, dialysis, nursing home | Vancomycin (or daptomycin for bacteremia/right-sided endocarditis; linezolid for pneumonia) |
| Enterotoxin (preformed) | Staph food poisoning | Heat-stable preformed toxin → stimulates vagal afferents + gut | Rapid-onset vomiting (1–6 hrs), watery diarrhea, no fever | “Picnic potato salad, creamy foods,” symptoms start fast | Supportive (fluids); antibiotics not helpful |
| TSST-1 (superantigen) | Toxic shock syndrome | Superantigen cross-links MHC II + TCR → massive cytokines | Fever, hypotension, diffuse macular rash → desquamation (palms/soles), multiorgan involvement | Tampons, nasal packing, wound infections | Source control + clindamycin (↓ toxin) + MRSA coverage (often vanc) |
| Exfoliative toxin | Staph scalded skin syndrome (SSSS) | Cleaves desmoglein-1 in superficial epidermis → intraepidermal split | Tender erythema → flaccid bullae, +Nikolsky; mucosa spared | Infants/young kids; widespread “burn-like” skin | Anti-staph antibiotics (cover MSSA/MRSA based on risk) + supportive care |
| α-toxin | Hemolysis/tissue injury | Pore-forming cytotoxin | Tissue necrosis, contributes to abscess | “Necrotic” lesions | Treat infection appropriately |
| PVL leukocidin | CA-MRSA virulence factor | Kills neutrophils | Severe skin necrosis, sometimes necrotizing pneumonia | Post-influenza, hemoptysis, leukopenia | MRSA therapy; consider linezolid in pneumonia (toxin suppression) |
Toxins: rapid pattern recognition (Step-friendly)
1) Enterotoxin → “Fast vomit”
- Preformed, heat-stable toxin
- Onset 1–6 hours
- Prominent vomiting (can have diarrhea)
- No need for antibiotics (toxin is the problem)
One-liner: If it hits fast after potato salad and it’s mostly vomiting, think preformed staph enterotoxin.
2) TSST-1 → “Superantigen shock + rash”
- Massive T-cell activation → cytokine storm
- Fever + hypotension + diffuse rash with later desquamation
- Often tied to tampons, nasal packing, surgical wounds
One-liner: TSST-1 superantigen makes you crash (shock) and peel (desquamation).
3) Exfoliative toxin → “Scalded skin, mucosa spared”
- Splits superficial epidermis at desmoglein-1
- Nikolsky positive
- Mucous membranes spared (helps distinguish from SJS/TEN)
One-liner: SSSS is a superficial split—kids peel, but mucosa stays intact.
MRSA vs MSSA: what the exam actually wants you to say
Mechanism that matters
- MRSA: mecA gene → altered penicillin-binding protein (PBP2a) → resistance to many β-lactams
Practical test-taking rules
- Serious MSSA infections (bacteremia/endocarditis): nafcillin/oxacillin or cefazolin beats vancomycin (more effective).
- MRSA concern (severe, hospitalized, line infection, high-risk): vancomycin is the classic go-to.
- Pneumonia + MRSA: linezolid is a common exam answer (good lung penetration; also suppresses toxin production).
High-yield clinical associations (quick list)
- Right-sided endocarditis: IV drug use → S. aureus (tricuspid), septic pulmonary emboli
- Osteomyelitis: hematogenous spread in kids; vertebral osteomyelitis in adults
- Septic arthritis: acute monoarthritis, hot swollen joint
- Post-influenza pneumonia: necrotizing pneumonia can be S. aureus
- Foreign bodies: catheters/prosthetics increase staph risk (biofilm is more classic for S. epidermidis, but S. aureus is common and aggressive)
Mini-self-check (2 vignette triggers)
- “Tampon + fever + hypotension + sunburn rash” → TSST-1 (superantigen)
- “Infant with diffuse erythema, flaccid bullae, +Nikolsky, no oral lesions” → SSSS (exfoliative toxin, desmoglein-1)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
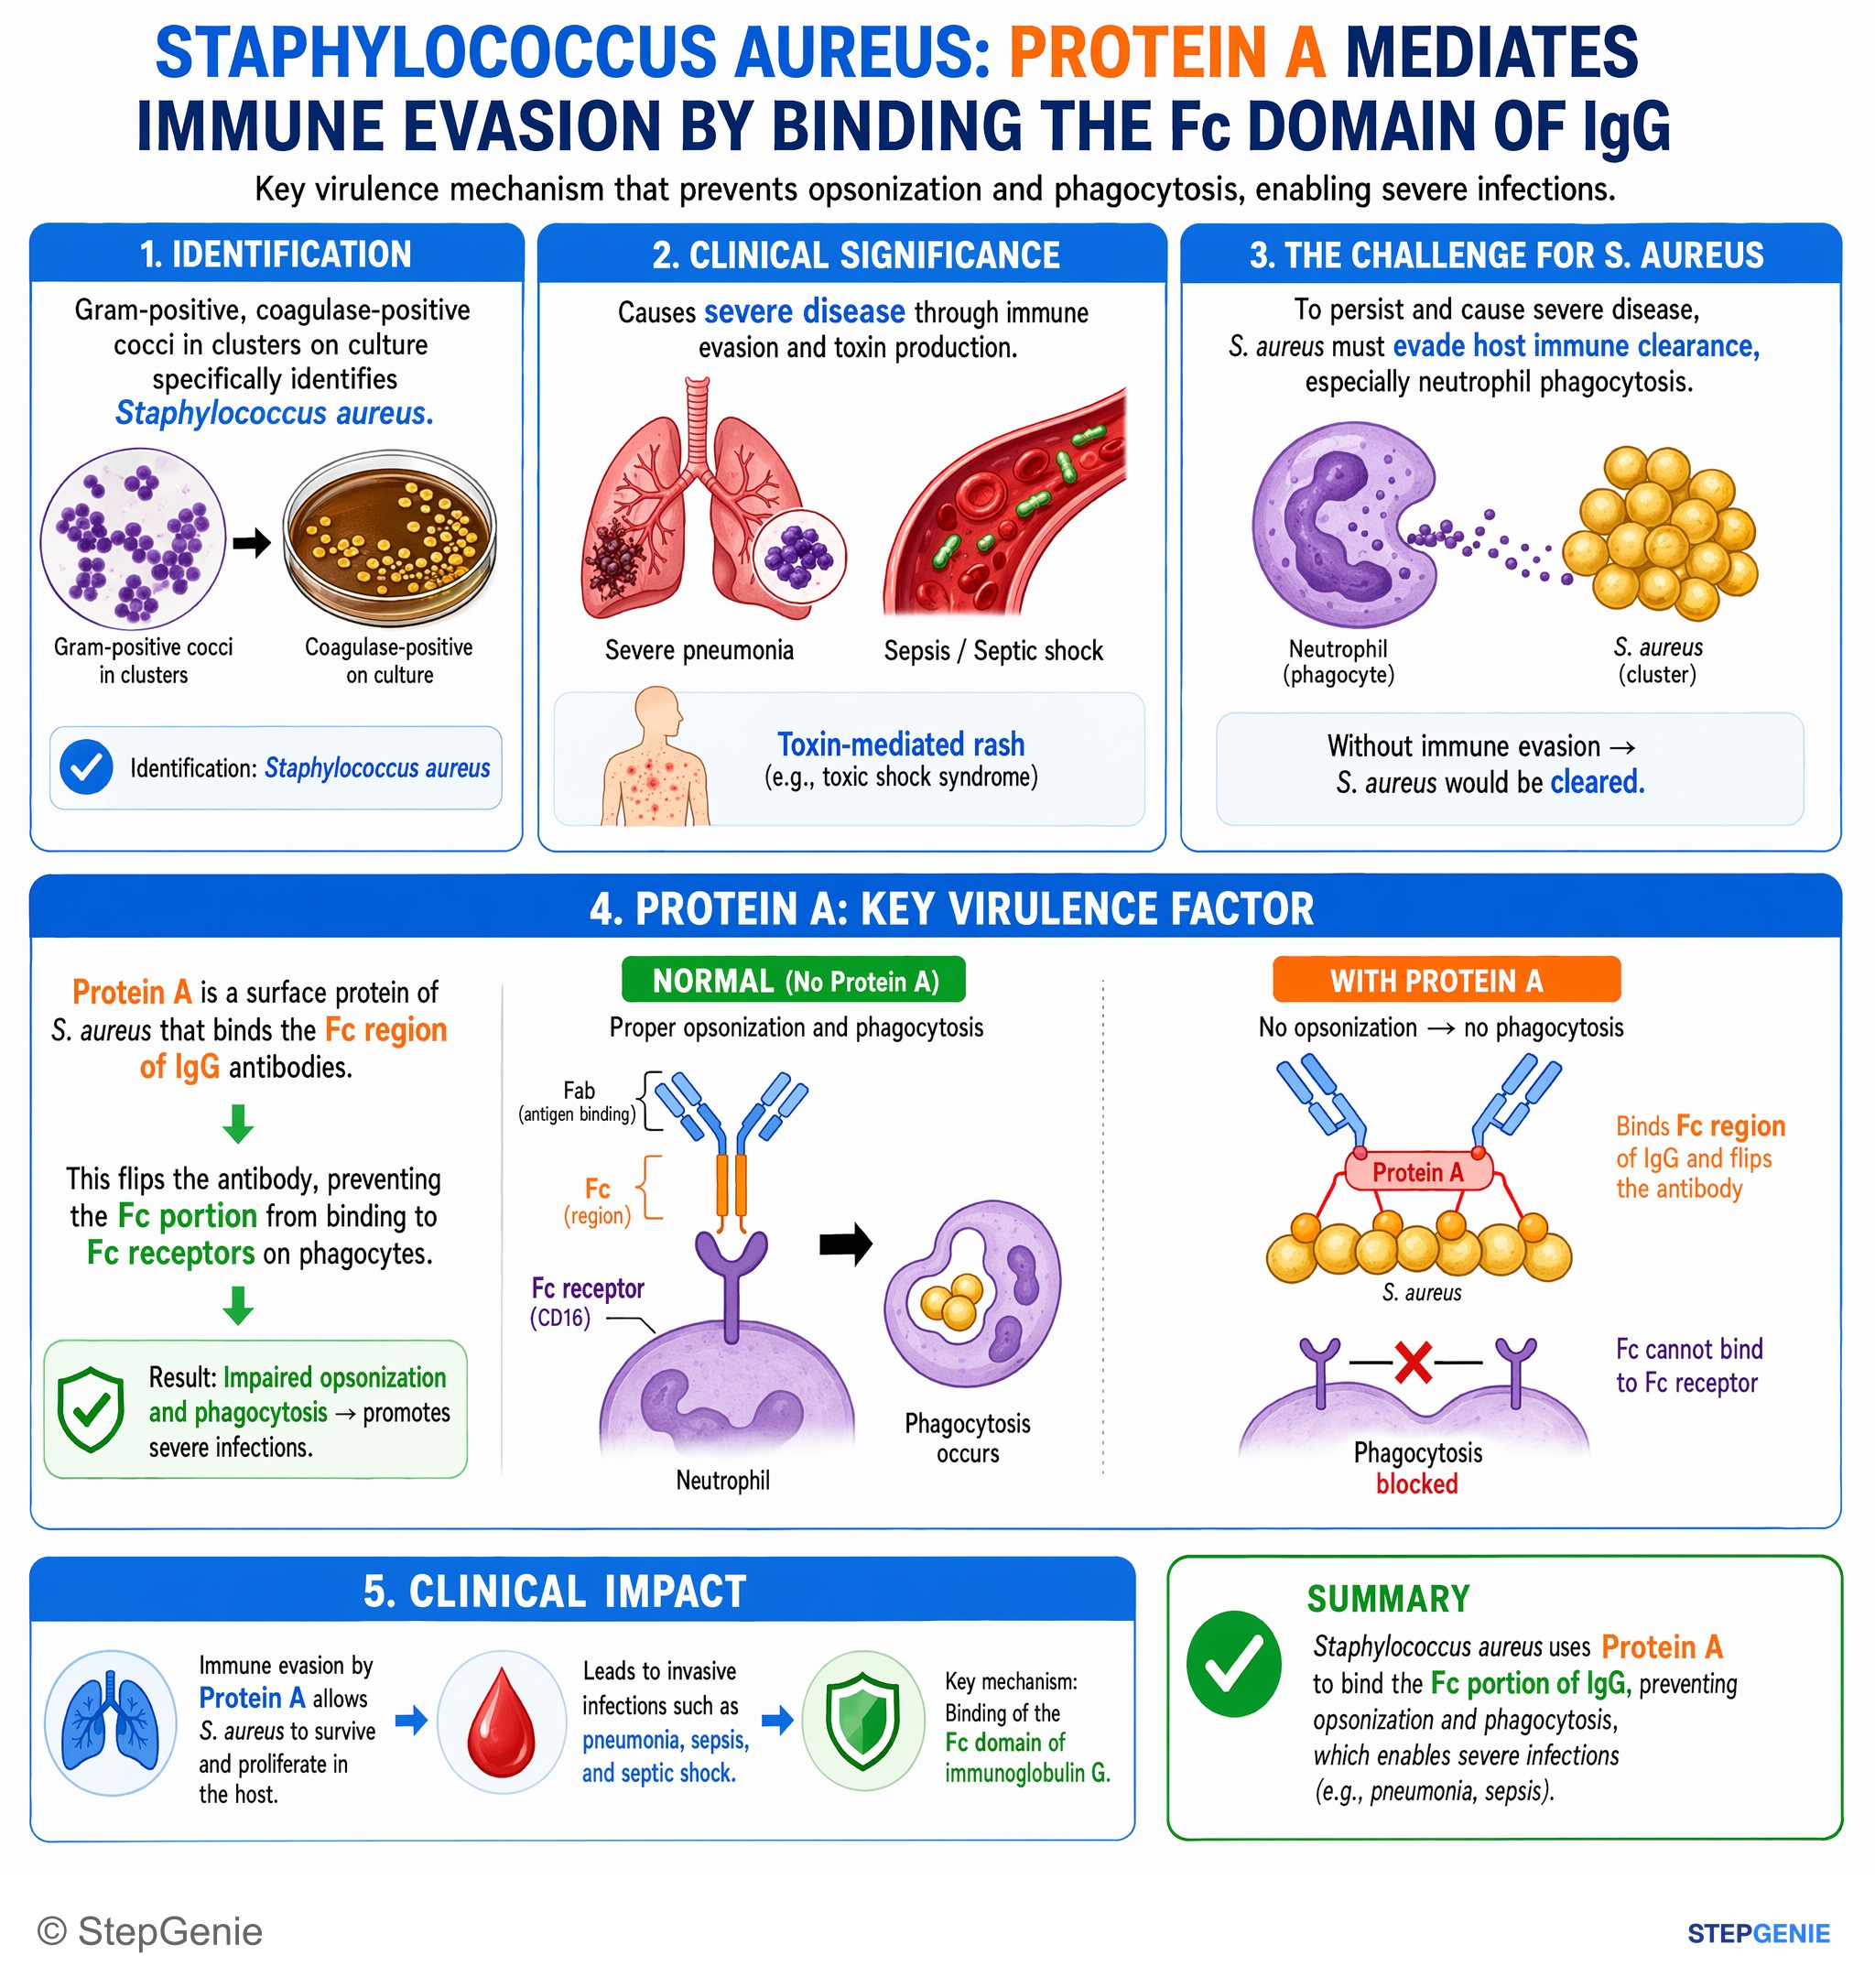
Staphylococcus aureus uses protein A to bind the Fc portion of IgG, preventing opsonization and phagocytosis in severe infections (e.g…
USMLE Step 1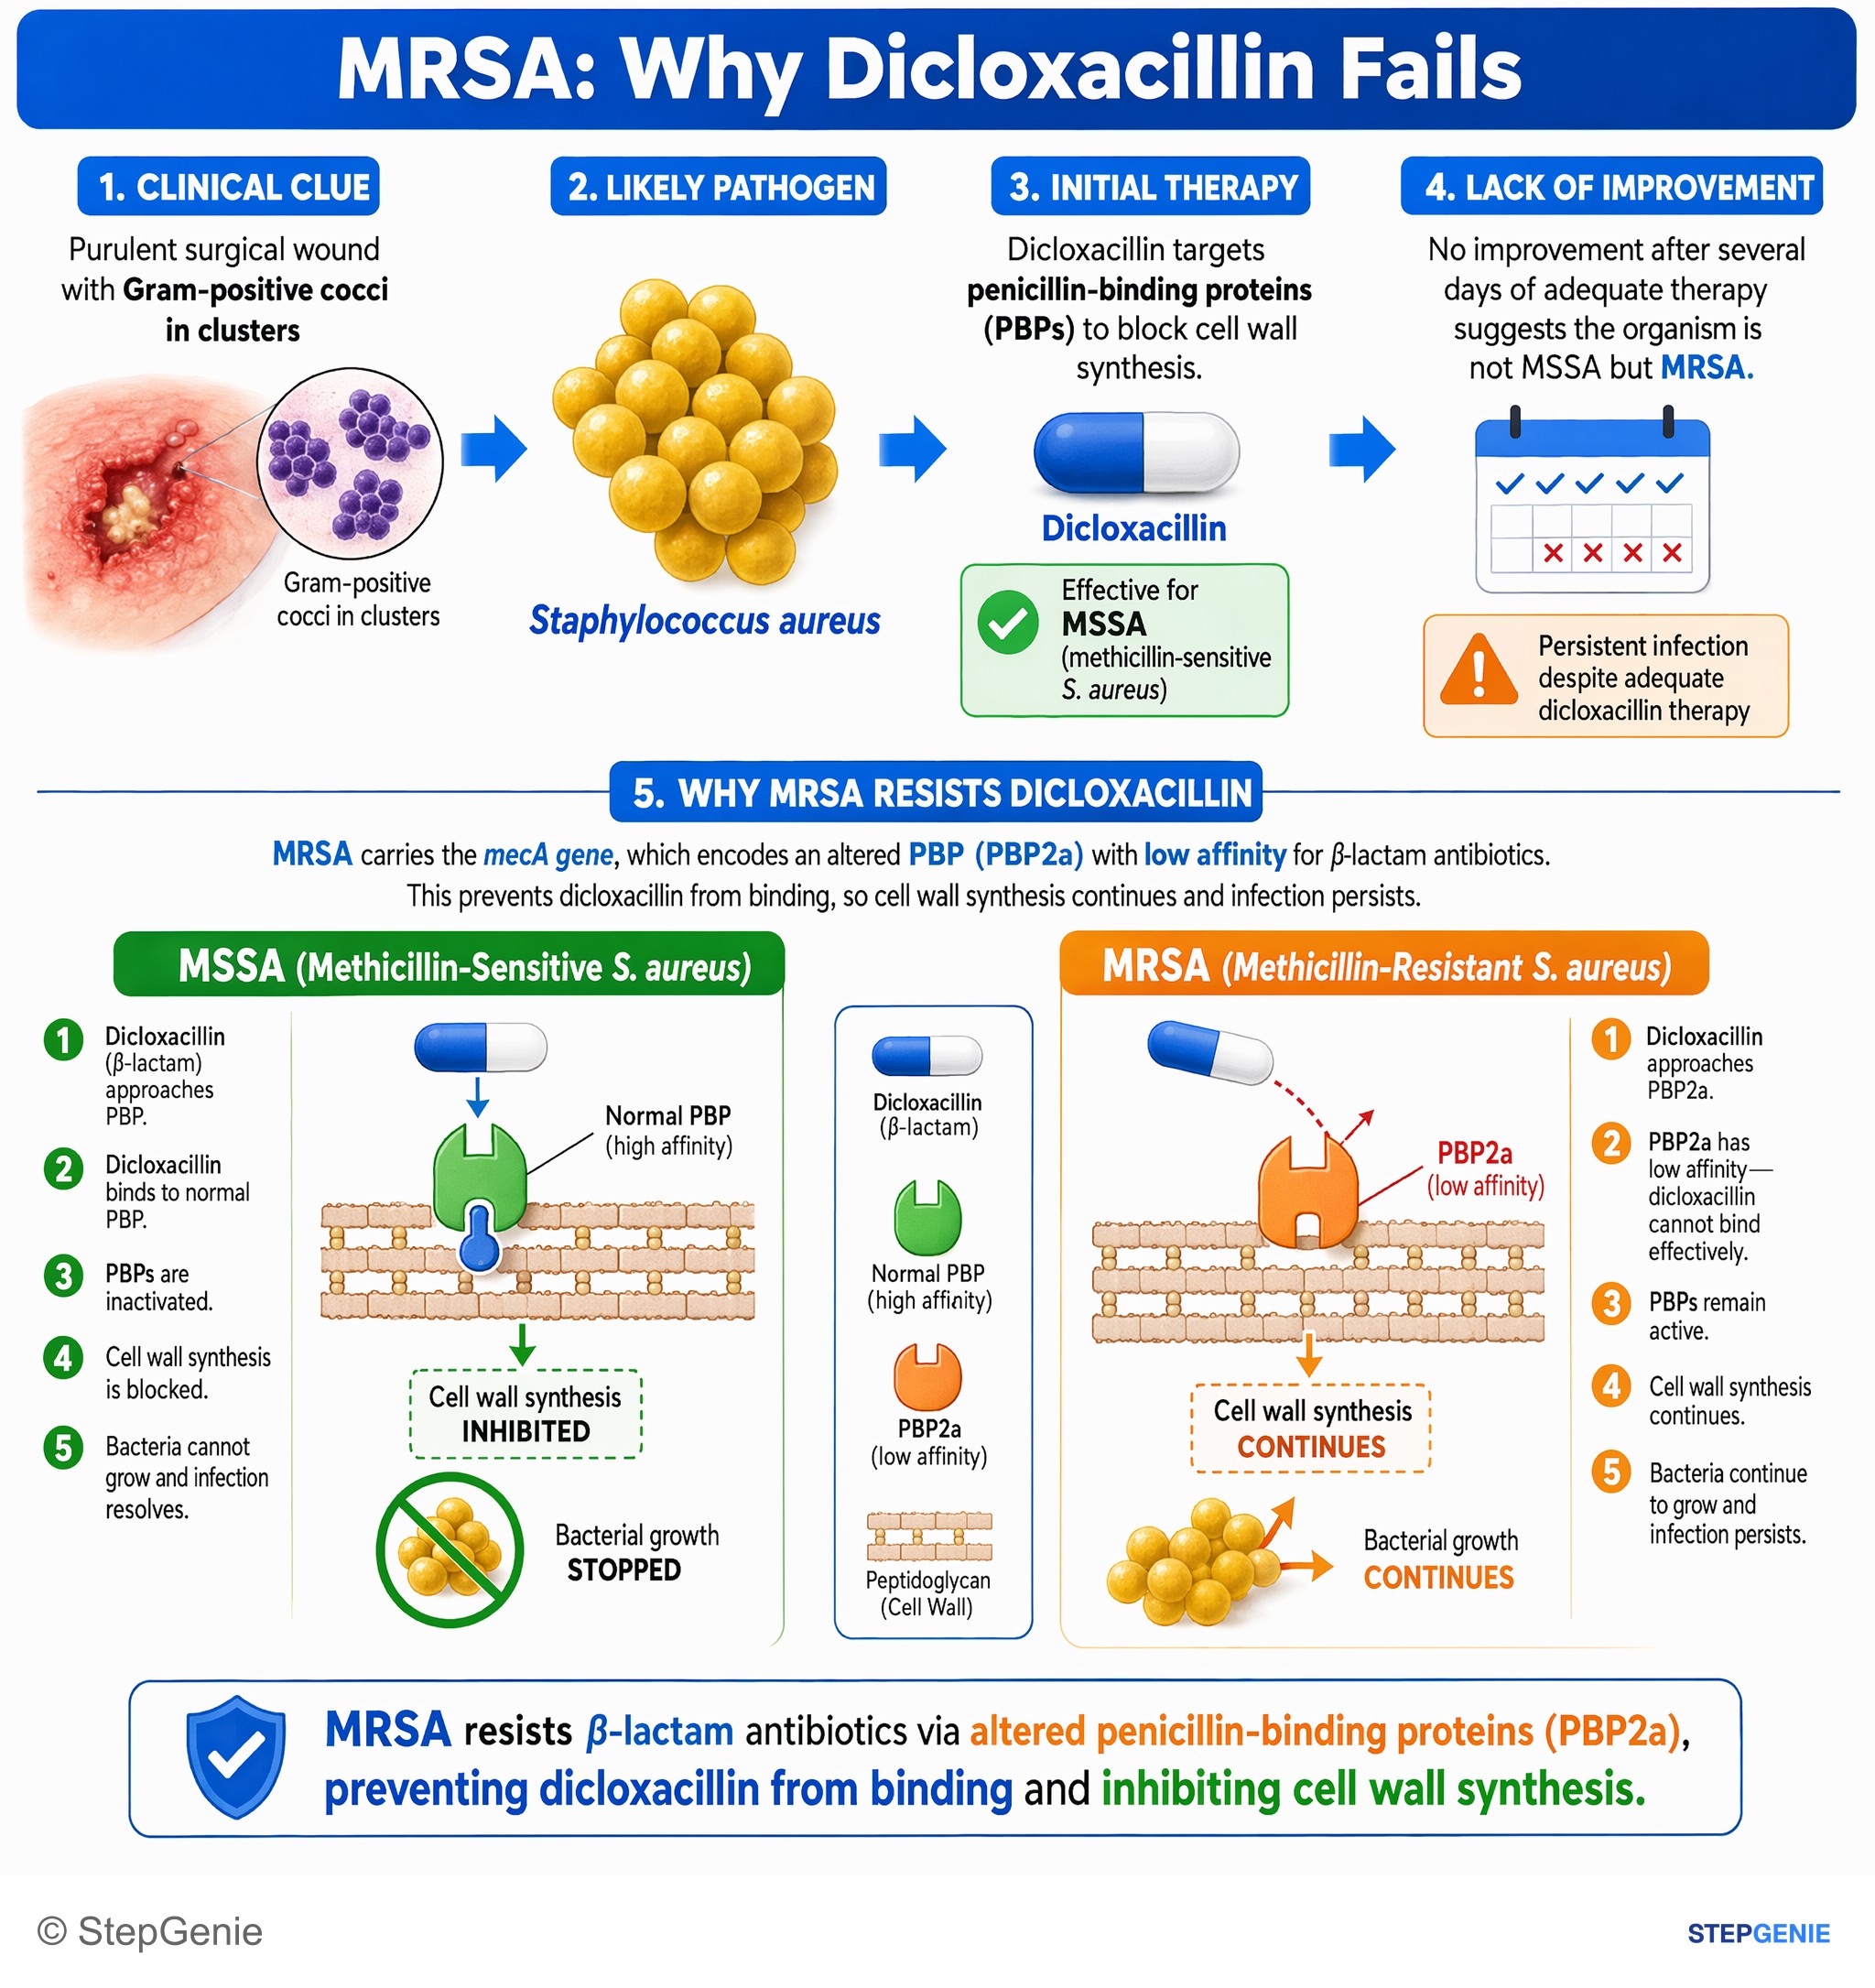
MRSA resists β-lactam antibiotics via altered penicillin-binding proteins (PBP2a), preventing dicloxacillin from binding and inhibiting…
USMLE Step 1
Staphylococcus aureus preformed enterotoxin → very rapid-onset vomiting and abdominal pain after picnic/deli foods (mayonnaise, cream…
USMLE Step 1Frequently Asked Questions
How do you recognize Staphylococcus aureus quickly on a micro question?
Staphylococcus aureus is identified by gram-positive cocci in clusters that are catalase-positive and coagulase-positive. It is often beta-hemolytic, forms golden colonies, and ferments mannitol on mannitol salt agar, turning the medium yellow. Clinically, it commonly causes pus-forming skin and soft tissue infections, invasive infections like bacteremia and endocarditis, and toxin-mediated syndromes such as food poisoning, toxic shock, and scalded skin syndrome.
Why is MRSA resistant to many beta-lactams?
MRSA resists many beta-lactams because it carries the mecA gene, which produces an altered penicillin-binding protein called PBP2a. That target change prevents many beta-lactam antibiotics from binding effectively. In exam terms, this is the key mechanism that separates MRSA from MSSA and explains why vancomycin is the classic treatment when severe MRSA infection is a concern.
How do you tell staph food poisoning from other causes of gastroenteritis?
Staph food poisoning is suggested by very rapid-onset vomiting, usually within 1 to 6 hours after eating, often with watery diarrhea and no fever. The illness is caused by a heat-stable preformed enterotoxin rather than bacterial invasion, which is why symptoms start so quickly. Classic clues include picnic potato salad or creamy foods, and treatment is supportive because antibiotics are not helpful.
How do you tell staphylococcal scalded skin syndrome from SJS or TEN?
Staphylococcal scalded skin syndrome is distinguished by superficial epidermal splitting with mucous membrane sparing. The exfoliative toxin cleaves desmoglein-1, causing tender erythema, flaccid bullae, and a positive Nikolsky sign, especially in infants and young children. The key differentiating clue is that the mucosa stays intact, which helps separate it from Stevens-Johnson syndrome or toxic epidermal necrolysis.
What is the first-line treatment for MSSA vs MRSA on exams?
For serious MSSA infections, nafcillin, oxacillin, or cefazolin is the preferred answer, and these are more effective than vancomycin when the strain is susceptible. For severe MRSA concerns, especially in hospitalized patients or line-associated infections, vancomycin is the classic go-to. If the question is MRSA pneumonia, linezolid is a common exam answer because it has good lung penetration and also suppresses toxin production.