Hyper-IgM syndrome is a failure of antibody class switching: serum IgM is normal or high while IgG, IgA and IgE are low or absent. Nearly 75% of cases are X-linked CD40 ligand (CD40L, CD154) deficiency; because activated CD4+ T cells also use CD40L to help macrophages and dendritic cells, affected boys get pyogenic sinopulmonary infections plus opportunistic Pneumocystis pneumonia and Cryptosporidium diarrhea, often with neutropenia and absent germinal centers. The rarer B-cell-intrinsic forms, AID and UNG deficiency (autosomal recessive), cause bacterial infections without opportunistic ones, plus lymphoid hyperplasia (with giant germinal centers in AID deficiency).
The mechanism in one picture
- T cell → B cell: an activated CD4+ T cell's CD40L binds CD40 on a B cell. That contact tells the B cell to switch from IgM to IgG, IgA or IgE (together with T-cell cytokines) and supports germinal centers and memory B cells.
- Inside the B cell: AID (activation-induced cytidine deaminase) converts cytidine to uracil in switch-region DNA; UNG removes the uracil, and the abasic sites left behind are cut into the DNA breaks that let the B cell recombine to a new constant region. AID also starts somatic hypermutation of the variable region.
- T cell → macrophage and dendritic cell: CD40L also drives T-cell interaction with monocyte-derived antigen-presenting cells. Losing it explains the opportunistic infections, which is why CD40L or CD40 defects look partly like a T-cell disorder and AID or UNG defects look like a pure antibody disorder.
- No switch = IgM stays: B cells still make IgM, the default isotype, so the name really means "low everything else"; IgM can be merely normal.
Review the costimulatory signals in the T-cell activation mnemonic and the B-cell side in B-cell activation and class switching.
Step-by-step flowchart
- Read the immunoglobulins.
- Low IgG, IgA and IgE with normal or high IgM → class-switch defect (hyper-IgM). Go to step 2.
- All isotypes low, including IgM → think XLA or CVID (table below), or SCID if T cells are low.
- Low IgM with high IgA and IgE → Wiskott-Aldrich syndrome.
- Check lymphocytes and B cells.
- Hyper-IgM: normal lymphocyte counts, normal total B cells but a marked drop in class-switched memory B cells; T-cell mitogen responses are normal.
- Absent B cells → XLA. Very low T cells → SCID.
- Sort by the infections.
- Opportunistic infections (Pneumocystis, Cryptosporidium, Cryptococcus, Histoplasma, CMV, Toxoplasma), neutropenia, small lymphoid tissue → CD40L–CD40 axis. Go to step 4.
- Only bacterial respiratory and GI infections, big lymph nodes and tonsils, sometimes autoimmunity → B-cell-intrinsic defect (AID or UNG). Go to step 5.
- CD40L–CD40 branch: confirm by flow cytometry.
- Boy, affected maternal relatives → stimulated CD4+ T cells fail to express CD40L → X-linked CD40L deficiency (CD40LG).
- Girl or consanguineous family with normal CD40L → CD40 absent on B cells → CD40 deficiency (autosomal recessive, clinically indistinguishable).
- Boy with hypohidrotic ectodermal dysplasia → NEMO (IKBKG) deficiency, an X-linked disorder that can also produce a hyper-IgM pattern.
- Lymph node histology: no germinal centers.
- AID or UNG branch: confirm by gene testing.
- AID deficiency (AICDA): IgM often much higher than in the X-linked form, lymphadenopathy, tonsillar hypertrophy, giant germinal centers, no somatic hypermutation, no neutropenia.
- UNG deficiency (UNG): autosomal recessive, with a similar class-switch defect and lymphoid hyperplasia.
- Predict the complications (CD40L deficiency).
- Chronic Cryptosporidium infection can cause sclerosing cholangitis; liver disease was once seen in more than 80% of affected males by age 20, a figure that may now be lower with screening and treatment of Cryptosporidium.
- Neutropenia in about 45–50%; chronic diarrhea in about 20–30%.
- Cancers in about 5%: bile duct and liver carcinomas, GI neuroendocrine tumors, colon cancer, and lymphoma.
- Treat.
- All forms: immunoglobulin (IgG) replacement.
- CD40L or CD40: TMP-SMX Pneumocystis prophylaxis, boiled or filtered water only and no swimming in non-chlorinated pools (Cryptosporidium), G-CSF for chronic neutropenia, no live vaccines (rotavirus, MMR, varicella, oral polio, BCG), and HSCT, the curative option.
- AID or UNG: immunoglobulin replacement is the mainstay.
Hyper-IgM types at a glance
| Form | Defect (gene) | Inheritance | Opportunistic infections | Lymphoid tissue | Other clues | Treatment |
|---|---|---|---|---|---|---|
| CD40L deficiency | CD40 ligand on activated CD4+ T cells (CD40LG) | X-linked recessive | Yes: Pneumocystis, Cryptosporidium, fungi | Small; absent germinal centers | Neutropenia; sclerosing cholangitis; liver and GI cancers | IgG replacement, TMP-SMX; HSCT is curative |
| CD40 deficiency | CD40 on B cells and antigen-presenting cells (CD40) | Autosomal recessive | Yes | Absent germinal centers | Clinically indistinguishable from CD40L deficiency | As for CD40L deficiency, including HSCT |
| AID deficiency | Activation-induced cytidine deaminase (AICDA) | Autosomal recessive | No | Lymphadenopathy, big tonsils, giant germinal centers | IgM often much higher; autoimmunity; no somatic hypermutation | IgG replacement |
| UNG deficiency | Uracil-DNA glycosylase (UNG) | Autosomal recessive | No | Lymphoid hyperplasia | Similar to AID deficiency | IgG replacement |
Hyper-IgM vs other antibody defects
| Disorder | Immunoglobulins | Lymphocytes | Distinguishing clue |
|---|---|---|---|
| Hyper-IgM (CD40L) | IgM normal or high; IgG, IgA and IgE low | Normal counts; normal total B cells, few class-switched memory B cells | Boys with Pneumocystis, Cryptosporidium, neutropenia |
| X-linked agammaglobulinemia | IgG, IgA and IgM all low | B cells absent (under 1% CD19+) | Encapsulated bacteria, enteroviruses; tiny tonsils, no lymph nodes |
| Common variable immunodeficiency | Low IgG plus low IgA and/or IgM | B cells present but fail to become antibody-producing cells | Onset usually ages 20–40; autoimmunity, granulomas; gastric cancer or lymphoma in about 10% |
| Wiskott-Aldrich syndrome | IgM low; IgA and IgE high; IgG low or normal | T-cell count and function decreased | Eczema, bleeding, small platelets |
X-linked inheritance links CD40L deficiency, XLA, the most common SCID and Wiskott-Aldrich syndrome; see the X-linked disorders flowchart for the pedigree logic.
Exam traps
- "Hyper" is misleading. IgM is normal or elevated, so a normal IgM with low IgG, IgA and IgE still fits.
- Infant boy with Pneumocystis: both X-linked SCID and CD40L deficiency qualify. A normal T-cell count and normal mitogen responses point to CD40L deficiency.
- Tiny tonsils: seen in XLA and in X-linked hyper-IgM. The B-cell count separates them (absent in XLA, normal in hyper-IgM).
- Chronic watery diarrhea plus cholestatic liver disease in a boy with low IgG: Cryptosporidium and sclerosing cholangitis from CD40L deficiency.
- Big lymph nodes and tonsils with no opportunistic infections point to AID or UNG deficiency, not CD40L deficiency.
- Reverse pattern: low IgM with high IgA and IgE plus eczema and small platelets is Wiskott-Aldrich syndrome; practice that stem in the Wiskott-Aldrich syndrome question.
Practice question
A 10-month-old boy has fever, tachypnea and hypoxemia; bronchoalveolar lavage shows Pneumocystis jirovecii. He has had two ear infections and a pneumonia. A maternal uncle died at age 12 of liver failure. His tonsils are barely visible. Absolute neutrophil count is 700/µL and platelets are normal. IgG is very low, IgA and IgE are undetectable, and IgM is mildly elevated. CD19+ B-cell count, T-cell count and T-cell mitogen responses are normal. Which protein is most likely defective?
- A. Activation-induced cytidine deaminase
- B. Bruton tyrosine kinase
- C. CD40 on B cells
- D. CD40 ligand on activated CD4+ T cells
- E. Common γ chain of the IL-2 receptor
- F. Wiskott-Aldrich syndrome protein
Answer: D. A boy with Pneumocystis pneumonia, sinopulmonary infections, neutropenia, low IgG, IgA and IgE with preserved IgM, normal B cells, and a maternal uncle who died of liver disease has X-linked CD40L deficiency.
- A (AID): autosomal recessive, with no opportunistic infections, no neutropenia, and big tonsils and lymph nodes rather than tiny ones.
- B (BTK, XLA): every isotype including IgM is low, and B cells are absent.
- C (CD40): clinically identical, but autosomal recessive; the X-linked pedigree favors CD40L, and flow cytometry (CD40L on activated T cells vs CD40 on B cells) separates them.
- E (common γ chain, X-linked SCID): also X-linked with Pneumocystis, but SCID has few or no T cells and absent mitogen responses.
- F (WASP): X-linked, but the clues are eczema, bleeding with small platelets, and low IgM with high IgA and IgE, the opposite IgM pattern.
Next steps after treating the pneumonia: IgG replacement, TMP-SMX prophylaxis, boiled or filtered water, G-CSF if neutropenia persists, and referral for HSCT.
Key takeaways
- Hyper-IgM = class-switch failure: IgM normal or high; IgG, IgA and IgE low or absent.
- Nearly 75% are X-linked CD40L deficiency; CD40 deficiency is its autosomal recessive twin.
- CD40L or CD40 defect: opportunistic Pneumocystis and Cryptosporidium, neutropenia, absent germinal centers, sclerosing cholangitis and liver or bile duct cancer.
- AID or UNG defect: bacterial infections only, lymphoid hyperplasia (giant germinal centers in AID deficiency), autoimmunity; AID deficiency also abolishes somatic hypermutation.
- Diagnose with flow cytometry for CD40L on activated CD4+ T cells (or CD40 on B cells) and gene testing.
- Treat with IgG replacement and TMP-SMX, protect against Cryptosporidium, avoid live vaccines, and use HSCT to cure CD40L deficiency.
Sources
- Dunn CP, de la Morena MT. CD40 Ligand Deficiency — GeneReviews, NCBI Bookshelf (updated 2025)
- Hyper-IgM Syndrome — Merck Manual Professional Edition
- X-linked hyper IgM syndrome — MedlinePlus Genetics
- Hyper IgM syndromes (HIGM) — Immune Deficiency Foundation
- Hyper-IgM syndrome with susceptibility to opportunistic infections — Orphanet
- Hyper-IgM syndrome without susceptibility to opportunistic infections — Orphanet
- Etzioni A, Ochs HD. The Hyper IgM Syndrome: An Evolving Story — Pediatric Research (2004)
- Çakan E, Gunaydin G. Activation induced cytidine deaminase: An old friend with new faces — Frontiers in Immunology (2022)
- Common Variable Immunodeficiency (CVID) — Merck Manual Professional Edition
- Wiskott-Aldrich Syndrome — Merck Manual Professional Edition
- X-Linked Agammaglobulinemia — Merck Manual Professional Edition
- Severe Combined Immunodeficiency (SCID) — Merck Manual Professional Edition
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
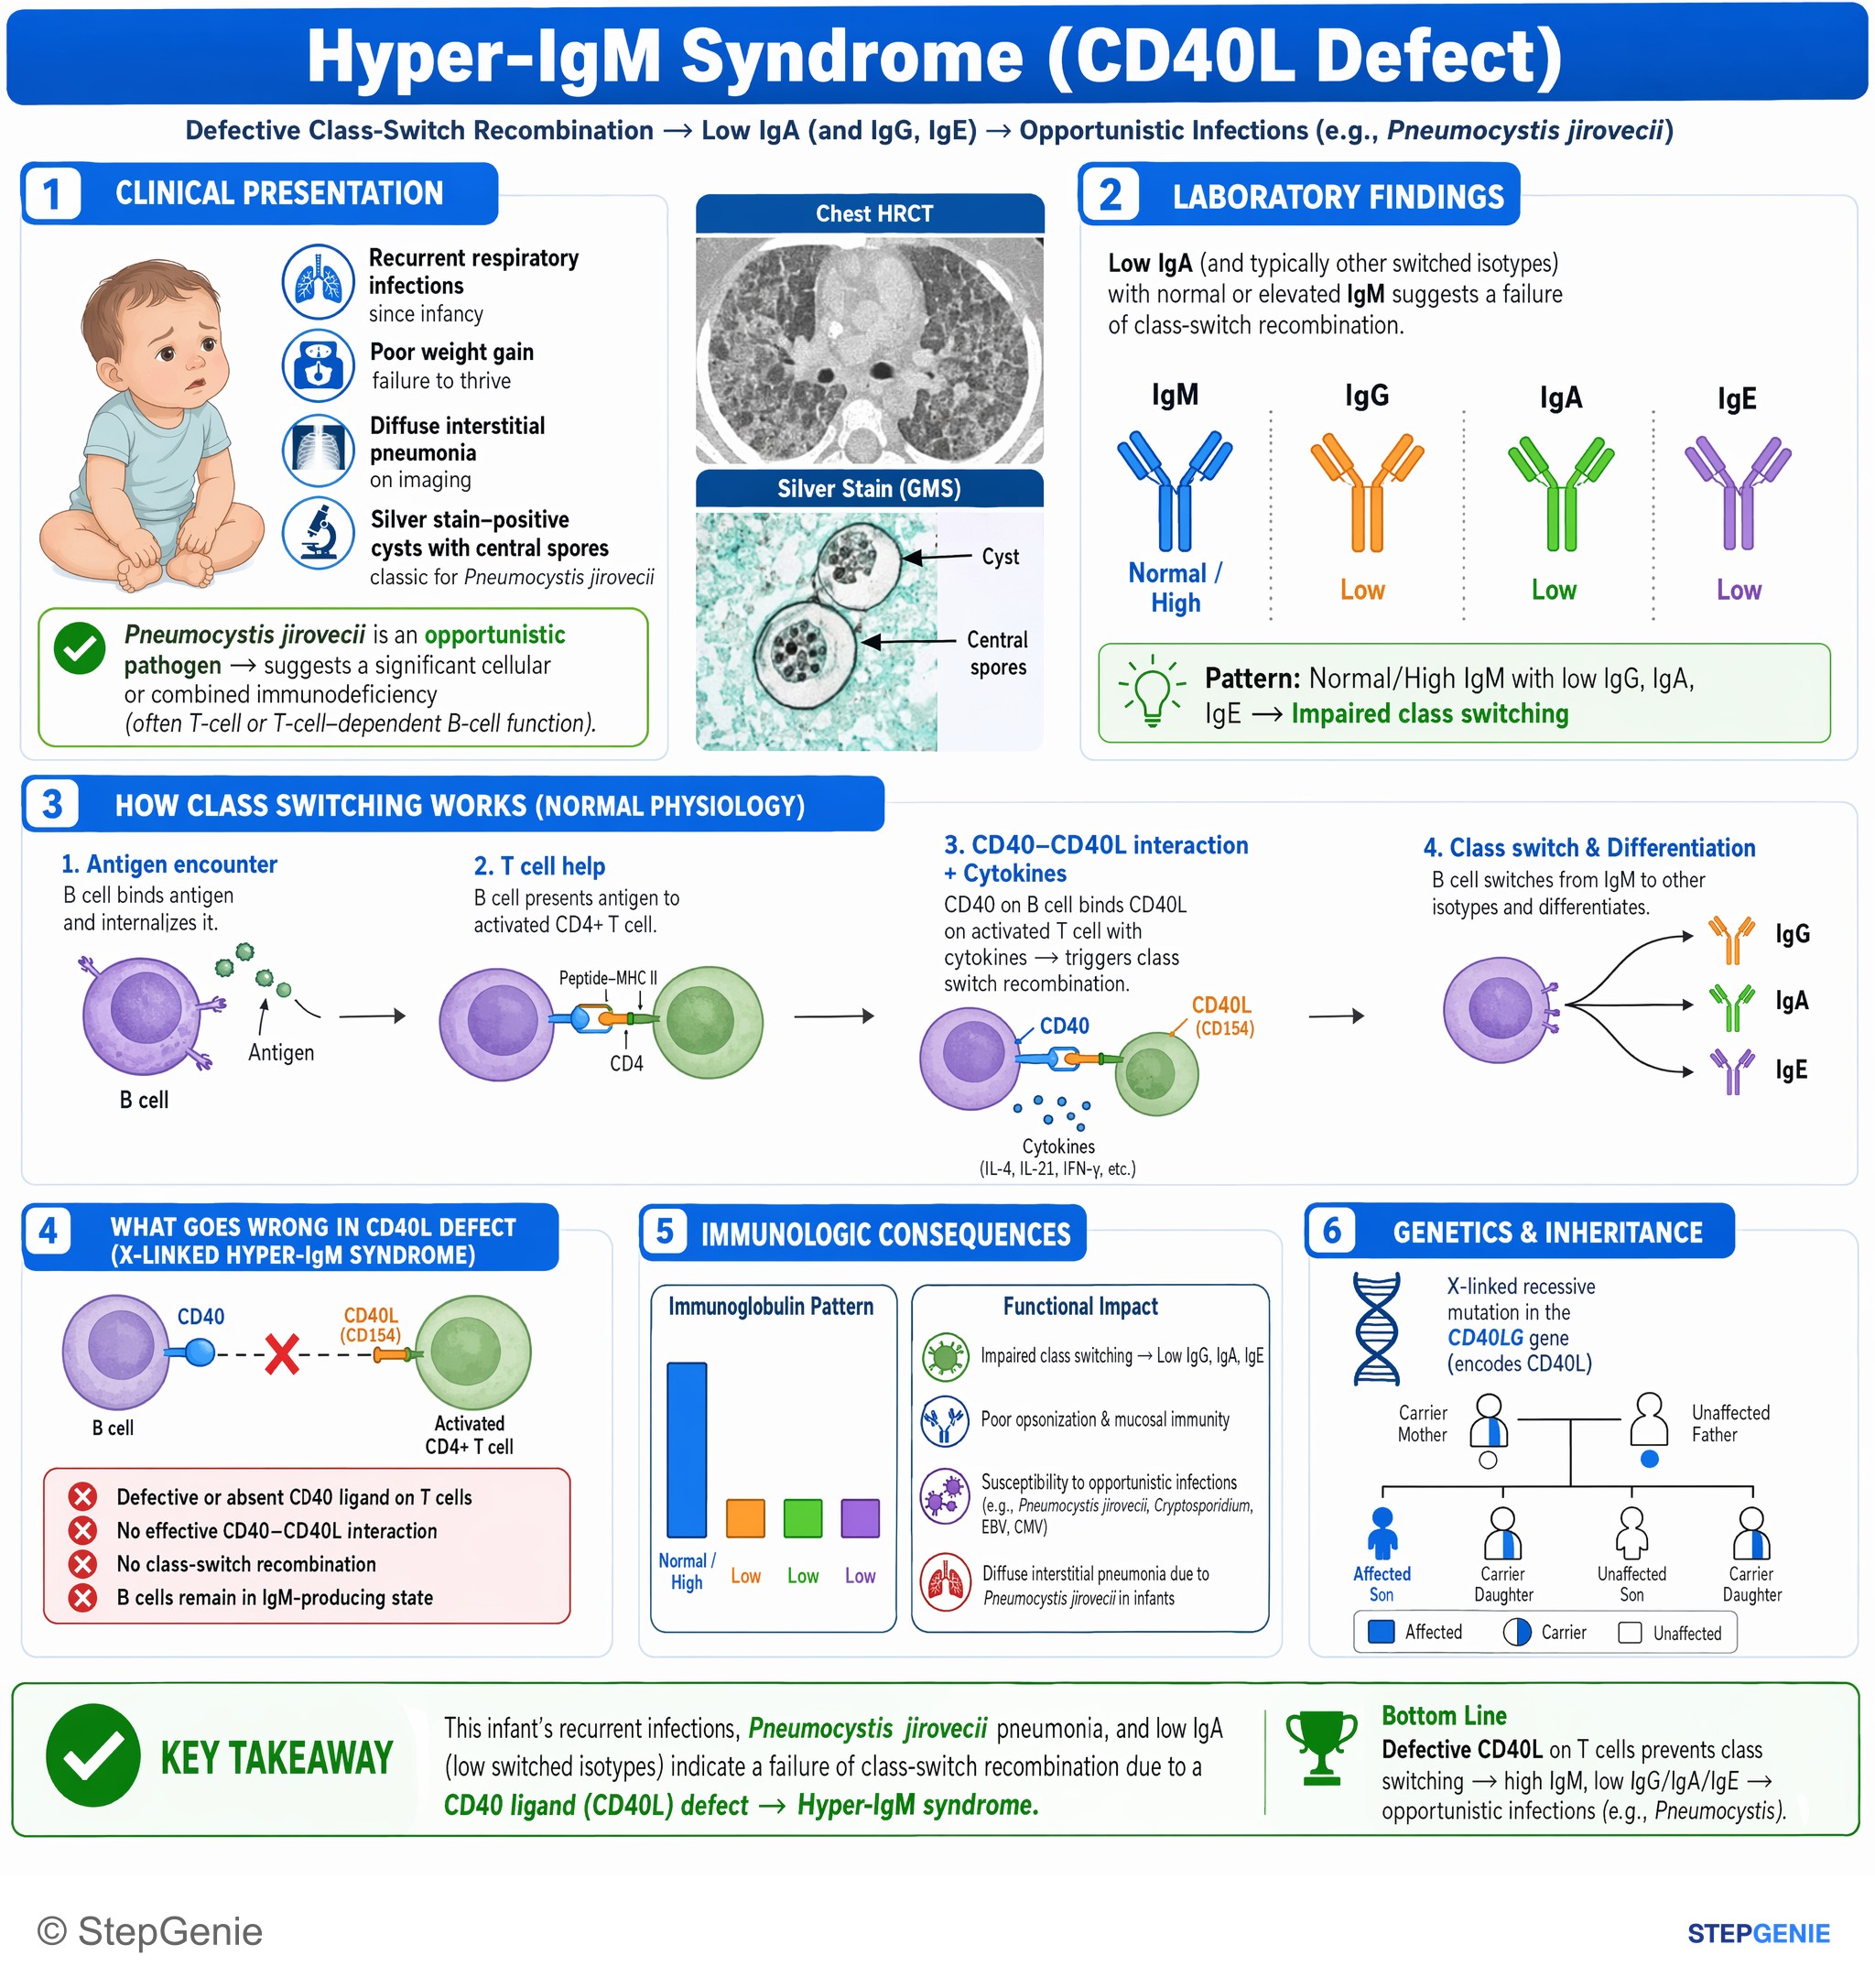
Hyper-IgM syndrome (CD40L defect) → impaired class switching, low IgA, opportunistic infections (e.g., Pneumocystis jirovecii) with…
USMLE Step 1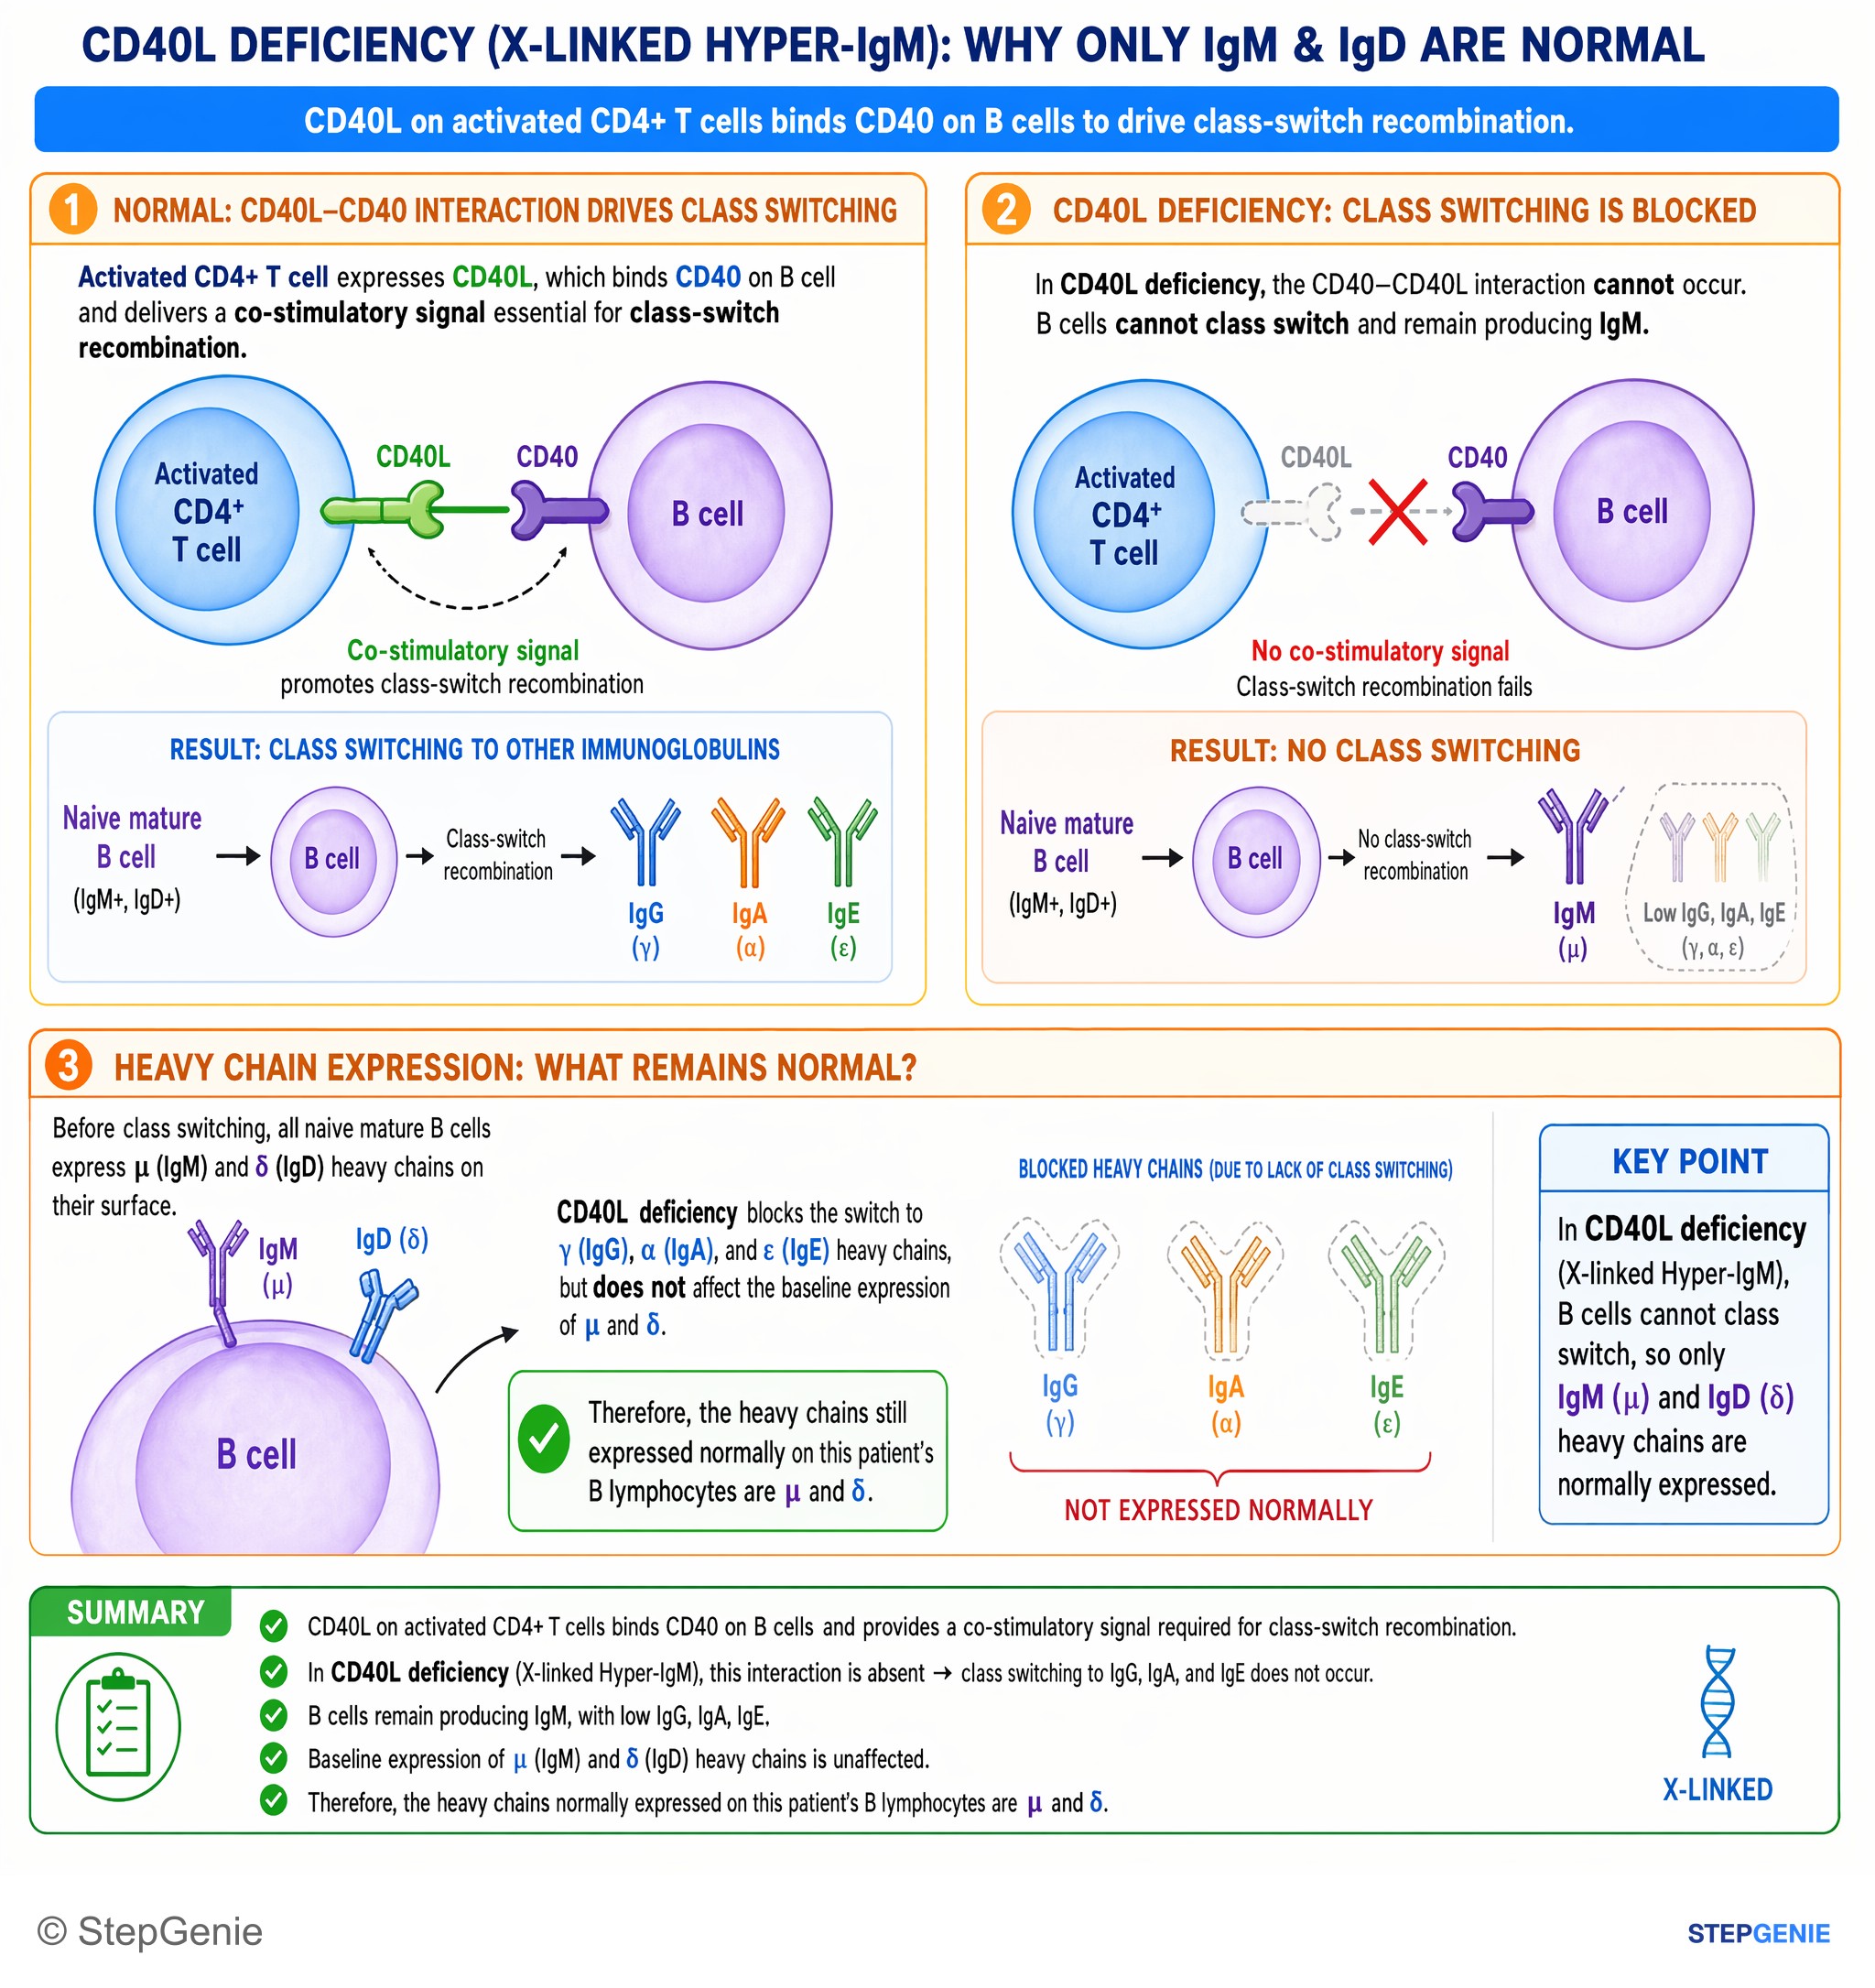
X-linked Hyper-IgM (CD40L deficiency): B cells cannot class switch, so only IgM (μ) and IgD (δ) heavy chains are normally expressed.
USMLE Step 1Frequently Asked Questions
What is hyper-IgM syndrome?
Hyper-IgM syndrome is a group of inherited immunodeficiencies in which B cells cannot switch from making IgM to making IgG, IgA or IgE. Serum IgM is normal or elevated while IgG, IgA and IgE are low or absent. Patients get recurrent bacterial sinopulmonary infections, and the forms caused by CD40 ligand or CD40 defects also cause opportunistic infections.
What is the most common cause of hyper-IgM syndrome?
Nearly 75% of cases are X-linked CD40 ligand deficiency, caused by variants in the CD40LG gene, so affected patients are almost always boys. CD40 ligand (CD154) on activated CD4+ T cells normally binds CD40 on B cells to trigger class switching. Autosomal recessive forms include CD40, AID and UNG deficiency.
Why does CD40 ligand deficiency cause opportunistic infections?
CD40 ligand is needed not only for T-cell help to B cells but also for T-cell interaction with monocyte-derived antigen-presenting cells such as macrophages and dendritic cells. Without it, cell-mediated defenses against opportunists fail as well as antibody production. More than 40% of affected infants first present with Pneumocystis jirovecii pneumonia, and Cryptosporidium can cause chronic diarrhea and sclerosing cholangitis.
How do you tell CD40 ligand deficiency from AID deficiency?
CD40 ligand deficiency is X-linked and causes opportunistic infections, neutropenia, small lymphoid tissue and absent germinal centers. AID deficiency is autosomal recessive and causes bacterial infections without opportunistic ones, with enlarged lymph nodes and tonsils, giant germinal centers, often higher IgM and sometimes autoimmunity. AID deficiency also abolishes somatic hypermutation.
How is hyper-IgM syndrome diagnosed?
The immunoglobulin pattern suggests it: low IgG, IgA and IgE with normal or high IgM, normal total B-cell numbers and few class-switched memory B cells. Flow cytometry showing that stimulated CD4+ T cells fail to express CD40 ligand points to the X-linked form, and absent CD40 on B cells points to CD40 deficiency. Genetic testing confirms the diagnosis and identifies the exact gene, including CD40LG, AICDA and UNG.
How is hyper-IgM syndrome treated?
All forms need immunoglobulin (IgG) replacement. Patients with CD40 ligand or CD40 deficiency also need trimethoprim-sulfamethoxazole prophylaxis against Pneumocystis, only boiled or filtered water to avoid Cryptosporidium, G-CSF for chronic neutropenia and no live vaccines. Hematopoietic stem cell transplantation can cure CD40 ligand deficiency, with a 5-year overall survival of 78.2% in a retrospective series of 130 patients cited by GeneReviews.