You just finished a question stem that feels like “allergies,” but the timing is weird, the rash isn’t urticarial, and the answer choices all sound plausible. That’s the sweet spot for Type IV (delayed-type) hypersensitivity questions: the only way to consistently get them right is to understand the mechanism, then use it to eliminate distractors with confidence.
Tag: Immunology > Hypersensitivity Reactions
The Vignette (Classic Q-Bank Style)
A 28-year-old medical student develops an intensely pruritic, erythematous rash with vesicles on the dorsal hands and wrists. Two days ago, she wore a new watch with a metal band and applied an over-the-counter topical antibiotic to a small cut. She is afebrile. Exam shows well-demarcated, edematous plaques with small vesicles localized to areas of contact. Which of the following best describes the underlying mechanism?
Answer choices:
A. Cross-linking of IgE on mast cells leading to histamine release
B. IgG binding to fixed antigens with complement-mediated cell lysis
C. Immune complex deposition with complement activation and neutrophil recruitment
D. T-cell–mediated cytokine release causing macrophage activation and tissue inflammation
E. Autoantibodies against desmosomes causing acantholysis
Step 1: Identify the Pattern
Key clues:
- Localized rash at contact sites (watch band; topical antibiotic)
- Pruritic + vesicular rash (think contact dermatitis)
- Timing: ~48 hours later → delayed
This is Type IV hypersensitivity: T-cell–mediated, not antibody-mediated.
Correct Answer: D. T-cell–mediated cytokine release causing macrophage activation and tissue inflammation
Why it’s right (high yield mechanism)
Type IV hypersensitivity is delayed (48–72 hours) and driven by T cells.
Two major subtypes to keep straight:
-
Allergic contact dermatitis (e.g., nickel, poison ivy, neomycin):
- Th1 / Th17 responses (and sometimes CD8+ involvement)
- Cytokines recruit/activate macrophages and other inflammatory cells
- Eczematous rash with erythema, pruritus, vesicles, and weeping/crusting
-
Granulomatous inflammation (e.g., TB skin test/PPD, sarcoidosis):
- Th1 → IFN-γ activates macrophages
- Leads to epithelioid histiocytes and giant cells
Ultra-high-yield associations
- Nickel (jewelry, watchbands, belt buckles) → Type IV contact dermatitis
- Poison ivy/oak (urushiol) → Type IV contact dermatitis
- Neomycin and other topical meds → Type IV contact dermatitis
- PPD test: induration at 48–72 hours = Type IV
- Transplant rejection (especially acute cellular) = T-cell mediated (Type IV conceptually)
Now Kill the Distractors (Why Each Answer Choice Matters)
A. Cross-linking of IgE on mast cells leading to histamine release
This is Type I hypersensitivity (immediate).
How it would look instead:
- Timing: minutes to hours (not 2 days)
- Findings: urticaria (hives), angioedema, wheezing/bronchospasm, anaphylaxis
- Classic triggers: peanuts, shellfish, latex, bee stings, allergic rhinitis, asthma
Rule of thumb:
If it’s “itchy,” don’t autopilot to Type I—ask: is it urticaria and immediate, or eczematous and delayed?
B. IgG binding to fixed antigens with complement-mediated cell lysis
This is Type II hypersensitivity (antibody against cell surface or ECM).
How it would look instead:
- Hemolysis or cytopenias: autoimmune hemolytic anemia, ITP
- Basement membrane targeting: Goodpasture (anti–type IV collagen)
- Receptor dysfunction: Graves (stimulates TSH receptor), myasthenia gravis (blocks ACh receptor)
- Can involve complement, opsonization, ADCC
Why it’s wrong here:
No anemia, no hematuria/hemoptysis, no thrombocytopenia, no neuromuscular weakness—just localized dermatitis after contact.
C. Immune complex deposition with complement activation and neutrophil recruitment
This is Type III hypersensitivity (immune complex–mediated).
How it would look instead:
- Often systemic: fever, arthralgias, malaise
- Can be vasculitis, glomerulonephritis, arthritis
- Examples: serum sickness, SLE, post-strep GN, hypersensitivity pneumonitis, Arthus reaction (localized)
Buzzwords that point to Type III:
- Low complement (consumption)
- Neutrophils, fibrinoid necrosis in vessel walls
- “Immune complex deposition”
Why it’s wrong here:
The rash is localized to contact sites and appears 48 hours later—that’s the tempo and distribution of contact dermatitis (Type IV), not immune complex disease.
E. Autoantibodies against desmosomes causing acantholysis
This describes pemphigus vulgaris (Type II, antibody-mediated).
How it would look instead:
- Flaccid bullae and erosions
- Mucosal involvement common (painful oral ulcers)
- Positive Nikolsky sign
- Path: IgG against desmoglein → loss of keratinocyte adhesion (acantholysis)
Why it’s wrong here:
Contact dermatitis causes eczema-like, pruritic, vesicular lesions at exposure sites—not flaccid bullae with mucosal involvement.
Quick Comparison Table: Hypersensitivity Types You Must Differentiate
| Type | Immune mediator | Timing | Hallmark mechanism | Classic examples |
|---|---|---|---|---|
| I | IgE, mast cells | Minutes | Histamine, leukotrienes | Anaphylaxis, allergic rhinitis, urticaria, asthma |
| II | IgG/IgM vs cell surface/ECM | Hours–days | Complement, opsonization, receptor effects | AIHA, ITP, Goodpasture, Graves, myasthenia |
| III | Immune complexes | Days–weeks | Complement activation → neutrophils | SLE, serum sickness, PSGN, Arthus reaction |
| IV | T cells (Th1/Th17, CD8+) | 48–72 h | Cytokines → macrophages/inflammation | Contact dermatitis, PPD, granulomas, acute cellular rejection |
How to Approach These on Test Day (A Repeatable Strategy)
- Look at timing
- Immediate (minutes)? Think Type I
- 48–72 hours? Think Type IV
- Look at lesion morphology
- Urticaria/wheals → Type I
- Eczema/vesicles/weeping at contact site → Type IV
- Bullae + mucosa → pemphigus (Type II)
- Look at distribution
- Localized to exposure → contact dermatitis (Type IV)
- Systemic with arthralgias/renal involvement → Type III
- Match to immune players
- Type IV = T cells + macrophages, no antibodies needed
High-Yield Pearl: “Induration” vs “Erythema” in PPD
For a TB skin test (PPD), the positive readout is induration, not redness.
- Mechanism: memory Th1 cells recognize antigen → IFN-γ → macrophage activation
- Timing: read at 48–72 hours
- Wrong trap: measuring erythema or reading it too early
Takeaway
Type IV hypersensitivity is the delayed, T-cell–mediated hypersensitivity that shows up as contact dermatitis and granulomatous inflammation. In a q-bank, the distractors are usually Type I–III mechanisms or a blistering autoimmune disease—your edge is using timing + morphology + immune mediator to knock them out quickly.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
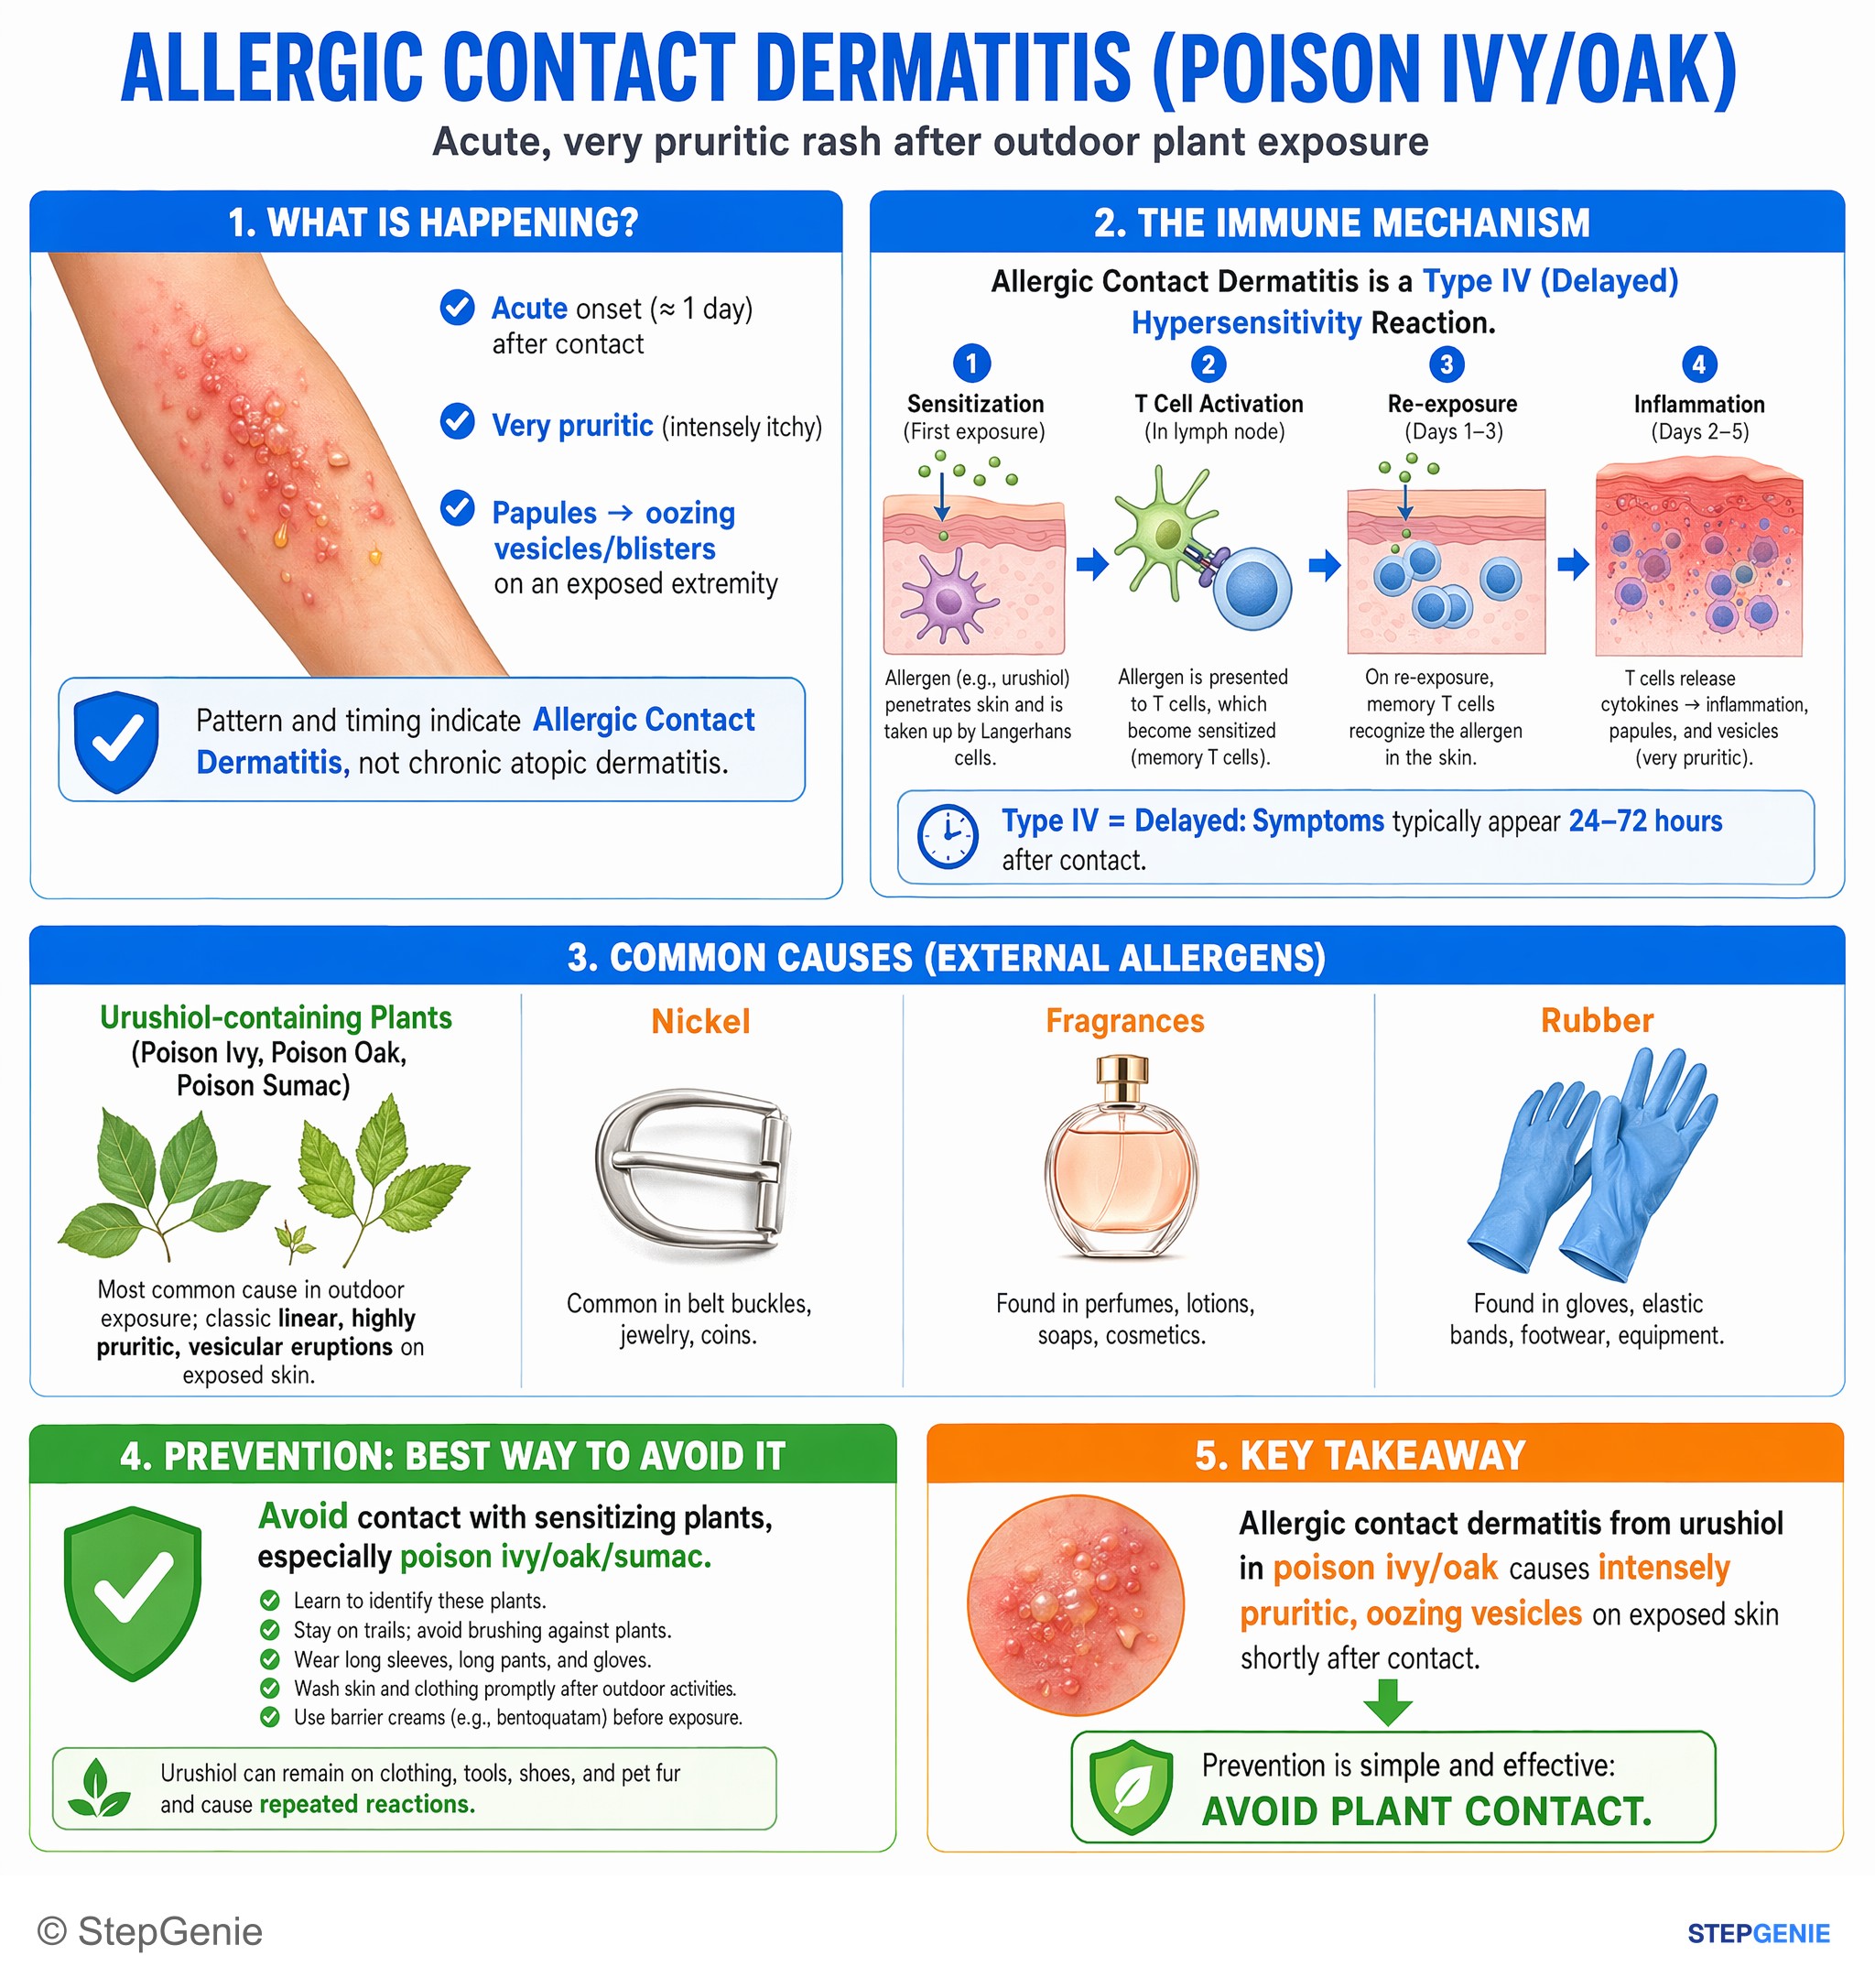
Allergic contact dermatitis from urushiol in poison ivy/oak causes intensely pruritic, oozing vesicles; prevention is by avoiding plant…
USMLE Step 1Frequently Asked Questions
How do you recognize Type IV contact dermatitis in a question stem?
Type IV contact dermatitis is suggested by a localized, pruritic, vesicular rash that appears at the site of exposure about 48 to 72 hours later. Classic clues include erythematous, well-demarcated, edematous plaques with small vesicles after contact with triggers such as nickel in watchbands, poison ivy, or topical neomycin. The delayed timing and contact-site distribution are the key pattern.
Why is contact dermatitis a Type IV hypersensitivity reaction instead of a Type I allergy?
Contact dermatitis is Type IV because it is driven by T cells and delayed cytokine-mediated inflammation, not immediate IgE-mediated mast cell degranulation. It typically appears 48 to 72 hours after exposure and causes an eczematous rash with erythema, pruritus, vesicles, and sometimes weeping or crusting. Type I reactions instead occur within minutes to hours and classically cause urticaria, angioedema, wheezing, or anaphylaxis.
What is the mechanism of Type IV hypersensitivity?
Type IV hypersensitivity is caused by T-cell–mediated cytokine release that activates macrophages and produces tissue inflammation. In allergic contact dermatitis, Th1 and Th17 responses, and sometimes CD8+ cells, recruit inflammatory cells and create an eczematous rash with erythema, pruritus, and vesicles. In granulomatous inflammation, Th1 cells produce IFN-γ, which activates macrophages and leads to epithelioid histiocytes and giant cells.
How do you tell Type IV contact dermatitis from pemphigus vulgaris?
Type IV contact dermatitis causes pruritic, eczema-like vesicular lesions localized to areas of exposure, often appearing 48 to 72 hours after contact. Pemphigus vulgaris instead is caused by IgG autoantibodies against desmoglein and presents with flaccid bullae, erosions, common mucosal involvement, and a positive Nikolsky sign. A localized itchy rash after nickel or topical medication points toward contact dermatitis, not pemphigus.
What are classic high-yield examples of Type IV hypersensitivity for Step 1?
Classic Type IV examples include allergic contact dermatitis from nickel, poison ivy or oak, and neomycin or other topical medications, as well as the PPD skin test and granulomatous inflammation. Acute cellular transplant rejection is also a T-cell–mediated Type IV concept. The shared theme is delayed, cell-mediated injury, usually appearing 48 to 72 hours after exposure or antigen challenge.