You just missed a question on Type II (cytotoxic) hypersensitivity, and now you’re staring at the explanation thinking, “Okay, but why were the other answer choices even there?” This post is the antidote to that frustration: we’ll walk through a classic clinical vignette, lock in the mechanism for the correct answer, and then systematically dismantle every distractor—because that’s exactly how you stop making the same mistake on test day.
Tag: Immunology > Hypersensitivity Reactions
The Q-Bank Vignette (Type II in the wild)
A 27-year-old woman with type 1 diabetes presents with fatigue and jaundice 2 days after receiving a transfusion following a motor vehicle accident. She reports dark urine and back pain. Vital signs are stable. Labs show decreased hemoglobin, increased LDH, increased indirect bilirubin, and decreased haptoglobin. A direct Coombs test is positive.
Question: What is the most likely mechanism of her condition?
Answer choices
A. IgE-mediated mast cell degranulation after cross-linking of surface-bound IgE
B. IgG/IgM antibodies against cell-surface antigens leading to complement activation and cell destruction
C. Immune complex deposition in tissues with complement activation and neutrophil recruitment
D. T-cell–mediated macrophage activation and cytokine-driven inflammation
E. Autoantibodies against desmosomes causing loss of cell-cell adhesion in epidermis
Step-by-step: Why the correct answer is B
This is acute hemolytic transfusion reaction—the classic setting for Type II hypersensitivity.
What in the vignette screams Type II?
- Timing: symptoms within hours to a couple days after transfusion (often rapid)
- Intravascular hemolysis clues:
- Back/flank pain, dark urine (hemoglobinuria)
- ↑ LDH, ↑ indirect bilirubin
- ↓ haptoglobin (it binds free hemoglobin, gets depleted)
- Direct Coombs (direct antiglobulin test) positive:
- Detects IgG and/or complement (C3) bound to the patient’s RBCs
Mechanism (what they’re testing)
Type II = antibody (IgG or IgM) directed against antigens on cell surfaces or extracellular matrix, causing injury via:
- Complement activation (especially with IgM; also IgG)
- Opsonization ( binding) → phagocytosis by splenic macrophages (extravascular hemolysis)
- ADCC (NK cells recognizing Fc portion of IgG)
In transfusion mismatch (often ABO):
- Recipient has preformed IgM against donor RBC antigens → complement-mediated intravascular hemolysis.
Therefore: B is correct.
High-yield Type II: How to recognize it fast
Two big Type II “flavors”
-
Cytotoxic / destructive
- Cells get destroyed
- Examples:
- Hemolytic transfusion reaction
- Hemolytic disease of the newborn (Rh)
- Autoimmune hemolytic anemia
- Immune thrombocytopenic purpura (ITP)
-
Non-cytotoxic / functional (receptor effects)
- Cells survive, but receptors are stimulated or blocked
- Examples:
- Graves disease (TSH receptor stimulated)
- Myasthenia gravis (ACh receptor blocked)
- (Often tested as “Type II” even though not “cytotoxic”)
Coombs tests in one table (very testable)
| Test | What it detects | Classic use |
|---|---|---|
| Direct Coombs | Antibodies and/or complement already bound to patient RBCs | Autoimmune hemolytic anemia, transfusion reactions, hemolytic disease of newborn |
| Indirect Coombs | Free antibodies in serum that could bind RBCs | Prenatal testing (Rh), pre-transfusion crossmatch |
Why each distractor is wrong (and what it would describe)
A. IgE-mediated mast cell degranulation → Type I
Why it’s tempting: “Transfusion reaction” makes people think “allergic reaction.”
Why it’s wrong here: This vignette is hemolysis, not histamine.
Type I tells:
- Minutes after exposure
- Urticaria, wheezing, hypotension, angioedema
- Eosinophils often relevant, elevated tryptase in anaphylaxis
- Mediators: histamine, leukotrienes, prostaglandins
Real-world transfusion tie-in: You can get an allergic transfusion reaction (Type I)—typically hives/itching without hemolysis. But the labs here (LDH, bilirubin, haptoglobin) scream RBC destruction.
C. Immune complex deposition → Type III
Why it’s tempting: Complement activation shows up in both Type II and III.
Why it’s wrong: Type III is soluble antigen–antibody complexes depositing in tissues—not antibodies binding directly to RBC surfaces.
Type III tells:
- Serum sickness (e.g., cefaclor, antitoxins) days after exposure
- Arthus reaction (localized)
- Post-strep GN, SLE, PAN (classics)
- Findings: vasculitis, nephritis, arthritis; low complement due to consumption
Key distinction
- Type II: antibodies bind a fixed target (cell surface/ECM)
- Type III: antibodies form complexes with soluble antigens that deposit in tissues
D. T-cell–mediated inflammation → Type IV
Why it’s tempting: Many vignettes involve “delayed” timing or inflammation.
Why it’s wrong: Positive direct Coombs proves antibody/complement on RBCs → not T-cell mediated.
Type IV tells:
- No antibodies required
- Delayed (48–72 hours) classically
- Examples:
- Contact dermatitis (poison ivy, nickel)
- PPD test
- Granulomatous disease (TB, sarcoid) via Th1 → IFN-γ → macrophage activation
- Type 1 diabetes and MS (autoimmune T-cell mediated)
Mnemonic anchor: Type IV = T cells (think “IV = cell-mediated”)
E. Autoantibodies against desmosomes → not the best match; it’s pemphigus vulgaris (still Type II, but wrong disease)
This is the “trick” distractor: it’s actually Type II immunology, just not the vignette.
- Pemphigus vulgaris: IgG against desmoglein (desmosomes)
- Flaccid bullae, mucosal involvement
- Nikolsky sign positive
- Net-like (“fishnet”) staining on immunofluorescence
- Your vignette: hemolysis + positive Coombs after transfusion
Test-day skill: When multiple choices share the same hypersensitivity type, you must match the organ system + clinical picture, not just the immunology category.
Rapid pattern recognition: Type II “buzzword” map
| Disease | Antibody target | Key clue |
|---|---|---|
| Acute hemolytic transfusion reaction | ABO antigens (often IgM) | Fever/chills, back pain, dark urine, DIC risk |
| Hemolytic disease of newborn | Rh(D) antigen (IgG) | Mom Rh−, baby Rh+, hydrops fetalis |
| Warm AIHA | IgG against RBCs | Extravascular hemolysis, spherocytes |
| Cold agglutinin disease | IgM against RBCs | Hemolysis worse in cold, acrocyanosis |
| Goodpasture | Type IV collagen in BM | Hemoptysis + hematuria; linear IF |
| ITP | GpIIb/IIIa | Isolated thrombocytopenia, mucocutaneous bleeding |
| Graves | TSH receptor | Hyperthyroid + pretibial myxedema |
| Myasthenia gravis | ACh receptor | Fatigable weakness, ptosis |
One more USMLE-level layer: transfusion reaction differentials
When you see “after transfusion,” quickly sort:
- Acute hemolytic (Type II): ABO mismatch, flank pain, hemoglobinuria, DIC risk
- Febrile non-hemolytic: cytokines from donor leukocytes; fever/chills; prevent with leukoreduction
- Allergic (Type I): urticaria/itching; treat with antihistamines
- TRALI: acute respiratory distress + noncardiogenic pulmonary edema within 6 hours; anti-HLA/anti-neutrophil antibodies
- TACO: volume overload; elevated BNP, JVD, improves with diuretics
Your vignette’s hemolysis labs + Coombs lock it into acute hemolytic (Type II).
Takeaway: How to stop missing these
When a stem suggests hemolysis or tissue-specific damage, ask two questions:
- Is the antibody binding directly to a cell/structure?
- Yes → think Type II
- Is the injury from immune complex deposition in tissues?
- Yes → think Type III
And if you see direct Coombs positivity, you should practically hear a bell: Type II antibody-mediated RBC problem until proven otherwise.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
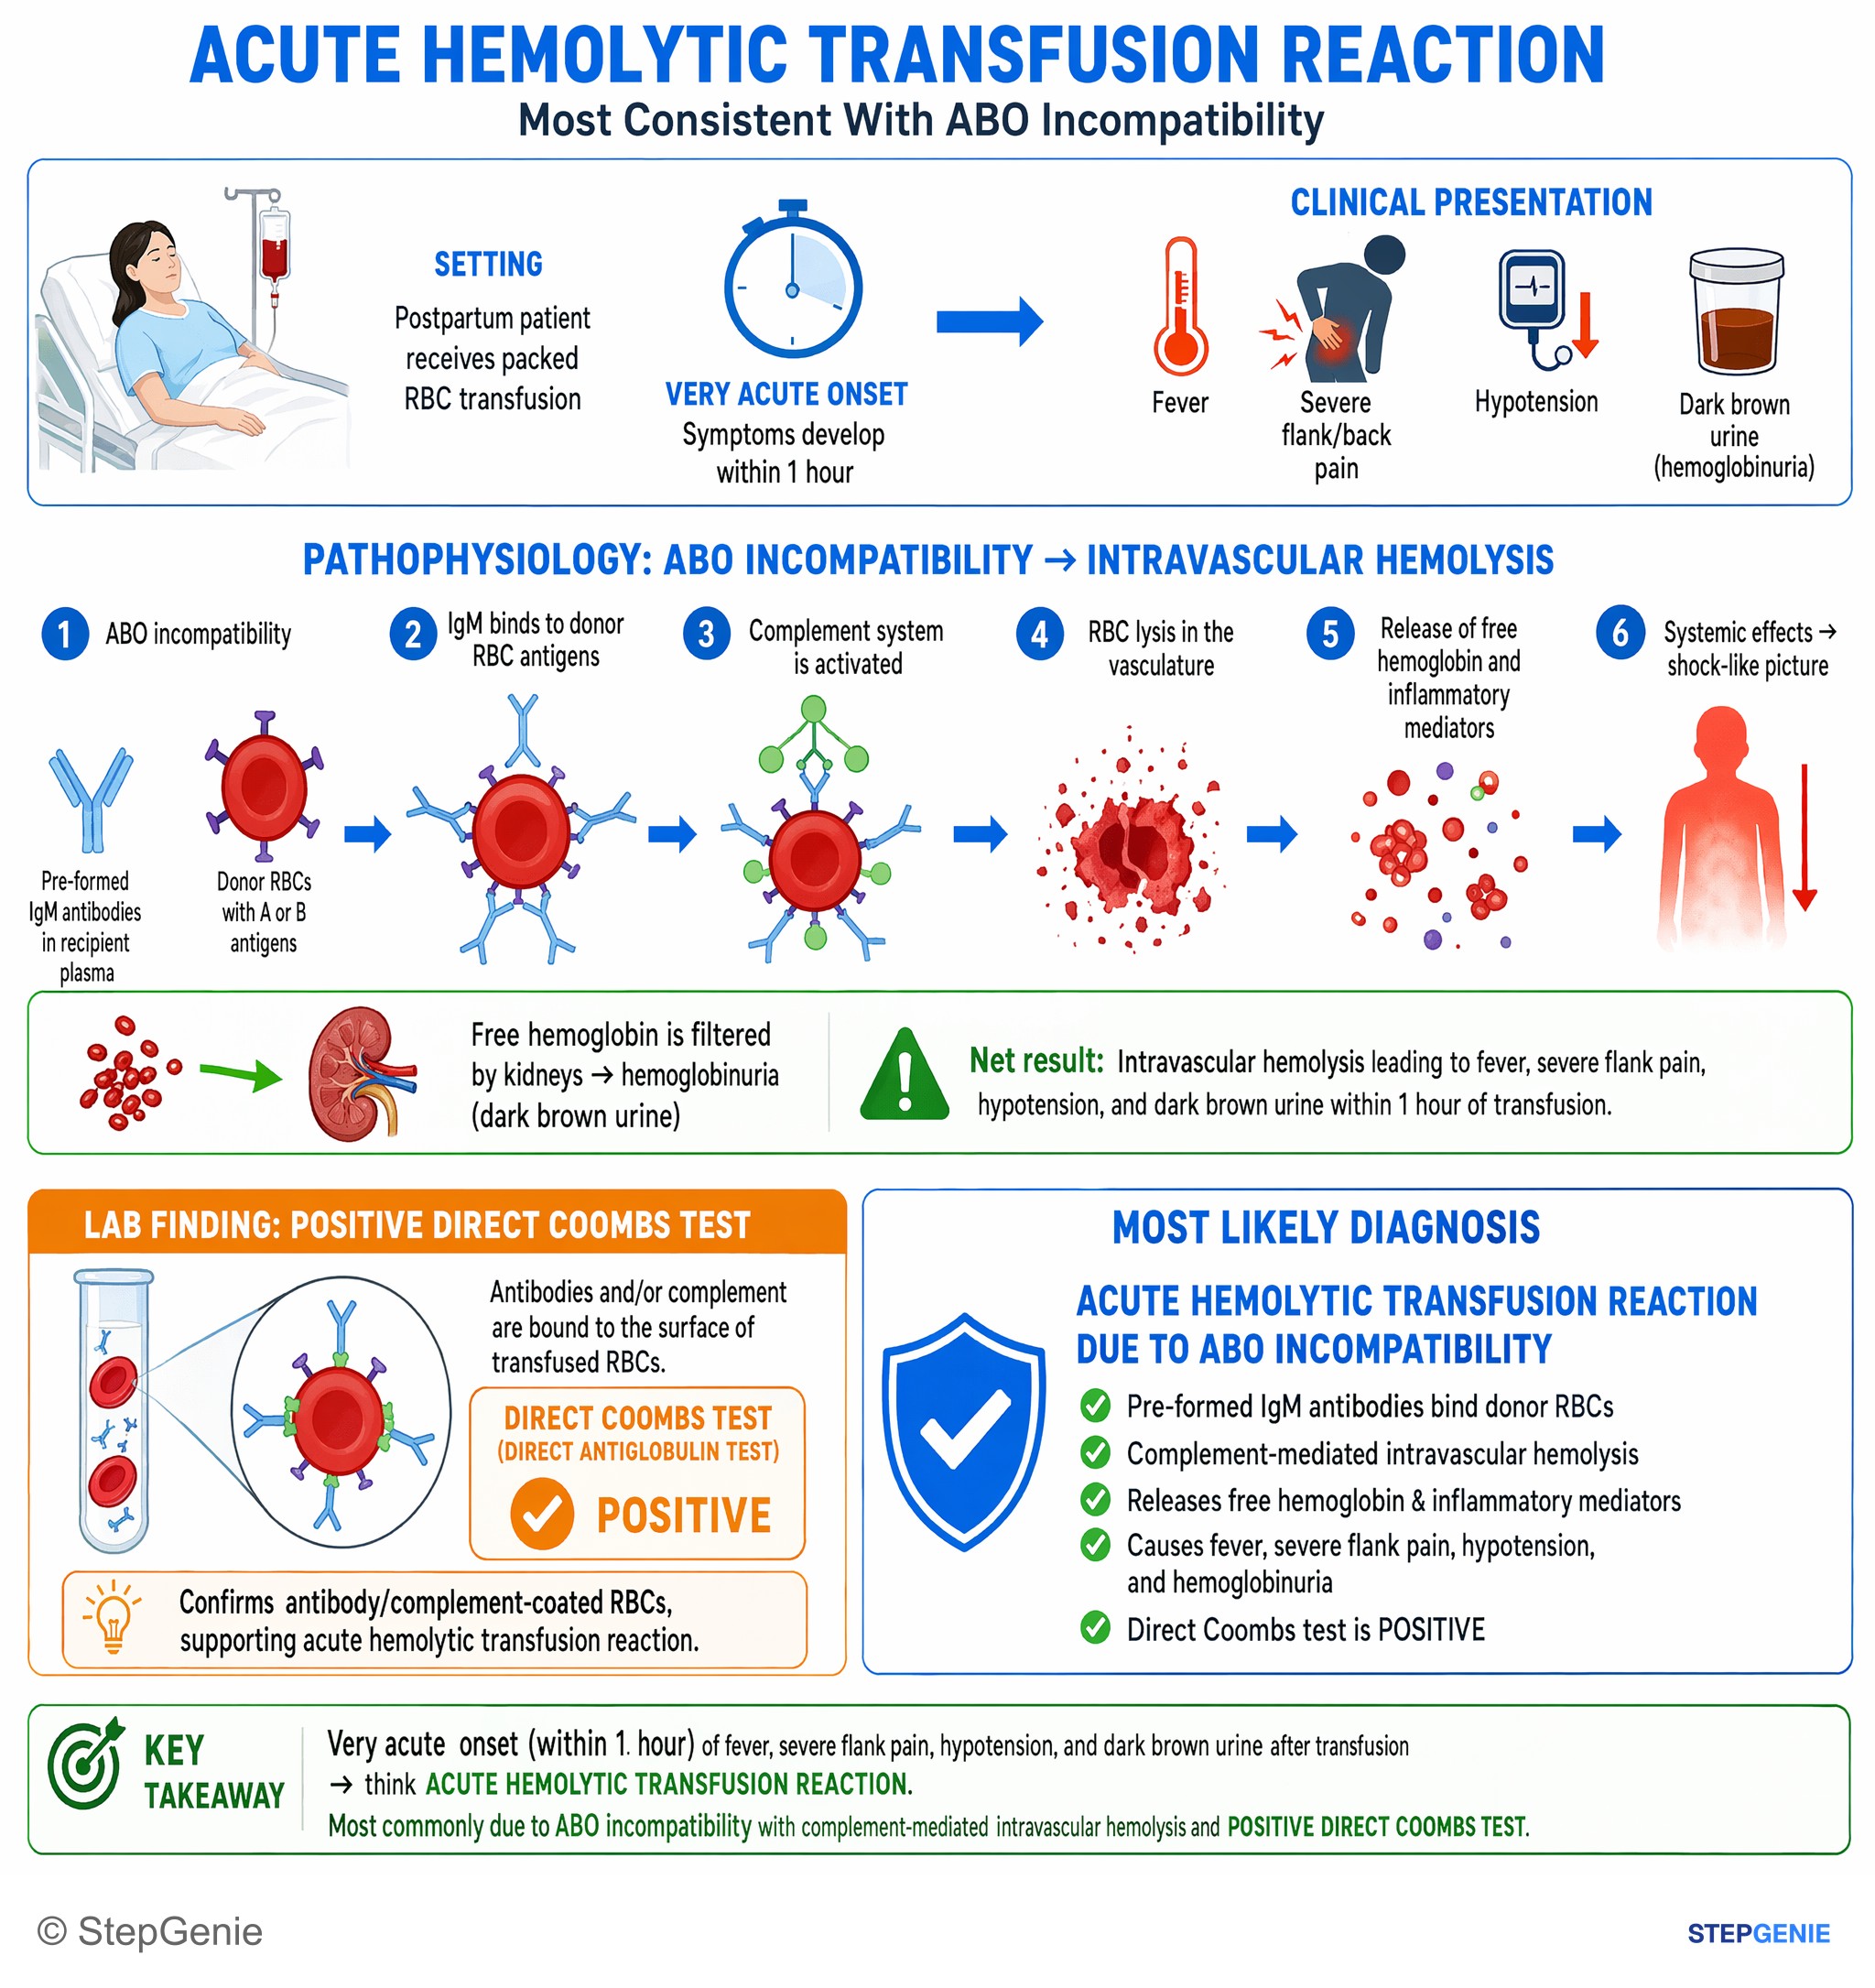
Acute hemolytic transfusion reaction due to ABO incompatibility: complement-mediated intravascular hemolysis → fever, flank pain…
USMLE Step 1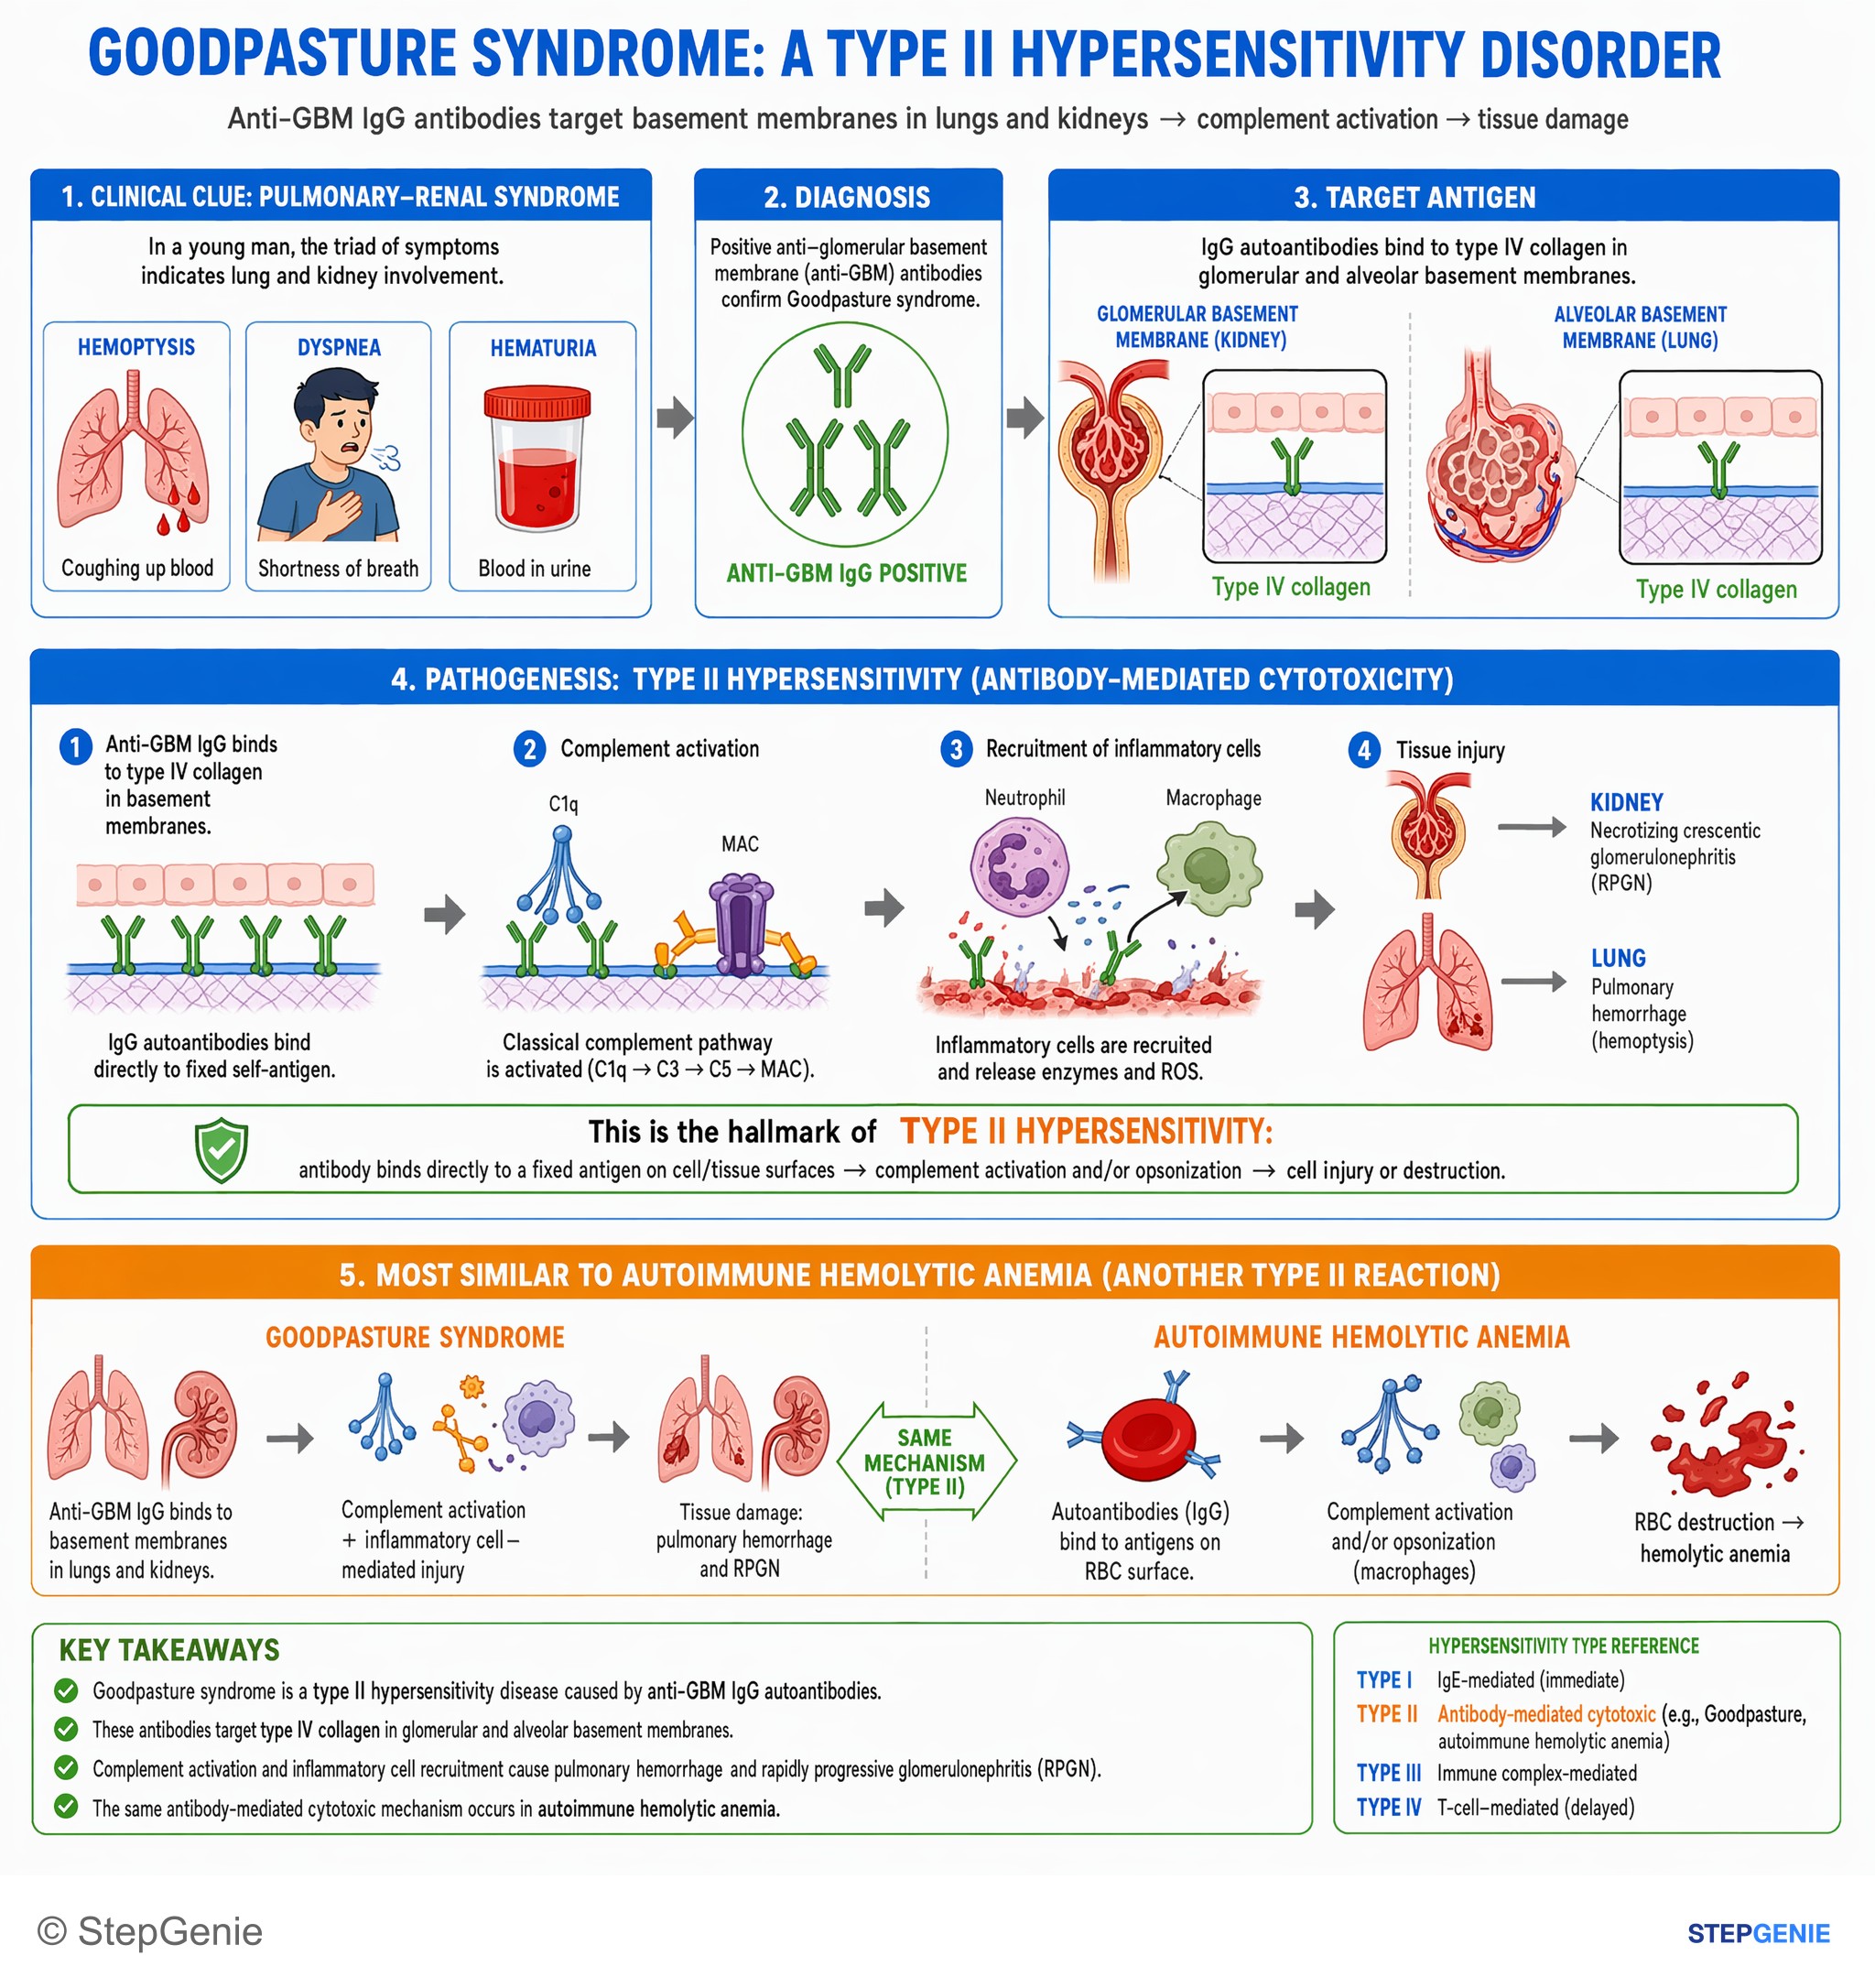
Goodpasture syndrome: type II hypersensitivity with anti-GBM IgG causing pulmonary hemorrhage and RPGN; mechanism mirrors other…
USMLE Step 1Frequently Asked Questions
What is the mechanism of an acute hemolytic transfusion reaction?
An acute hemolytic transfusion reaction is a Type II hypersensitivity reaction caused by IgG or IgM antibodies against cell-surface antigens on red blood cells. In transfusion mismatch, often ABO incompatibility, the recipient has preformed IgM against donor RBC antigens, which activates complement and leads to intravascular hemolysis. Type II injury can also involve opsonization and ADCC, but the classic transfusion mechanism is complement-mediated RBC destruction.
What findings point to Type II hypersensitivity in a transfusion question?
The key clues are rapid onset after transfusion plus evidence of hemolysis. High-yield findings include fatigue, jaundice, dark urine, back or flank pain, decreased hemoglobin, increased LDH, increased indirect bilirubin, and decreased haptoglobin. A positive direct Coombs test strongly supports Type II hypersensitivity because it detects IgG and or complement already bound to the patient’s red blood cells.
How do you tell Type II hypersensitivity from Type III on an exam?
Type II hypersensitivity involves antibodies binding a fixed target such as a cell surface or extracellular matrix, whereas Type III involves soluble antigen-antibody complexes depositing in tissues. In a transfusion reaction, the antibodies are directed against red blood cell surface antigens, making it Type II. Type III more often presents with vasculitis, nephritis, arthritis, or classic conditions like serum sickness, post-strep glomerulonephritis, SLE, and PAN.
Why isn’t an acute hemolytic transfusion reaction a Type I allergic reaction?
It is not Type I because the problem is hemolysis rather than mast cell degranulation. Type I reactions are IgE-mediated and classically cause minutes-after-exposure findings like urticaria, wheezing, hypotension, angioedema, and sometimes elevated tryptase in anaphylaxis. A transfusion can cause an allergic Type I reaction with hives and itching, but the presence of dark urine, abnormal hemolysis labs, and a positive direct Coombs points instead to red blood cell destruction.
What does a direct Coombs test detect, and when is it used?
A direct Coombs test detects antibodies and or complement already bound to a patient’s red blood cells. That makes it useful in autoimmune hemolytic anemia, transfusion reactions, and hemolytic disease of the newborn. In a hemolytic transfusion vignette, a positive direct Coombs test is a major clue because it shows the RBCs themselves are being targeted by immune factors consistent with Type II hypersensitivity.