You know that feeling when you know the vignette is Type I hypersensitivity… but the answer choices all sound vaguely immunology-ish? This is where most Q-bank points are lost: not on identifying “anaphylaxis,” but on proving why each distractor is wrong. Let’s walk through a classic Type I scenario and squeeze every drop of Step-level value out of it.
Tag: Immunology > Hypersensitivity Reactions
The Vignette (Classic Q-bank Style)
A 22-year-old woman with a history of eczema and seasonal allergies develops wheezing, diffuse urticaria, lip swelling, and hypotension minutes after eating a cookie at a party. She is tachycardic and in respiratory distress. She receives intramuscular epinephrine with rapid improvement.
Which of the following best explains the underlying mechanism of her reaction?
Correct Answer: IgE-Mediated Mast Cell Degranulation (Type I Hypersensitivity)
Why this is Type I (anaphylaxis/atopy)
Type I hypersensitivity is the “immediate” reaction: minutes after exposure in a previously sensitized person.
Core mechanism:
-
First exposure (sensitization):
- Allergen is presented to Th2 cells
- Th2 cytokines:
- IL-4 and IL-13 → B-cell class switching to IgE
- IL-5 → eosinophil activation (especially in late-phase responses like asthma)
- IgE binds FcRI receptors on mast cells/basophils
-
Re-exposure:
- Allergen cross-links IgE on mast cells → degranulation
What mast cells release (high yield)
Preformed mediators (immediate):
- Histamine → vasodilation, ↑ vascular permeability (edema), bronchoconstriction, pruritus
- Tryptase → often elevated in anaphylaxis (testable marker)
Newly synthesized mediators (minutes-hours):
- Leukotrienes (LTC4, LTD4, LTE4) → bronchoconstriction, mucus, vascular permeability (often more potent than histamine)
- Prostaglandins (PGD2) → bronchoconstriction
- Cytokines → recruit eosinophils and sustain inflammation
Why epinephrine works (and why it’s first-line)
- : vasoconstriction → raises BP, reduces mucosal edema
- : increases cardiac output
- : bronchodilation + stabilizes mast cells (decreases mediator release)
USMLE reflex: Anaphylaxis = IM epinephrine now. Adjuncts (H1/H2 blockers, steroids, albuterol, fluids) come after.
Answer Choice Autopsy: Why Every Distractor Is Wrong (or Not the Best)
Below is the “why it matters” part: Step questions love mixing hypersensitivity mechanisms with similar-sounding immunology buzzwords.
Distractor 1: IgG or IgM Against Cell Surface Antigens (Type II Hypersensitivity)
Why it’s tempting: You remember “antibodies cause damage” and might latch onto “hypotension = immune reaction.”
Why it’s wrong here:
- Type II is antibody-mediated cytotoxicity (IgG/IgM) against cell-bound or matrix antigens, not free allergens.
- Timing is not “within minutes after eating a cookie.”
- Doesn’t classically cause urticaria + bronchospasm immediately.
Type II high-yield examples:
- Autoimmune hemolytic anemia, ITP
- Goodpasture syndrome (anti-GBM)
- Pemphigus vulgaris (anti-desmoglein)
- Myasthenia gravis (anti-ACh receptor; functional blockade)
- Graves disease (TSI stimulation)
Board tip: If the stem screams “anaphylaxis,” do not overthink into Type II just because antibodies are involved. Type I = IgE, Type II = IgG/IgM against fixed targets.
Distractor 2: Immune Complex Deposition (Type III Hypersensitivity)
Why it’s tempting: “Systemic reaction” can make people think “immune complexes.”
Why it’s wrong here:
- Type III reactions take hours to days, not minutes.
- Mediated by IgG immune complexes depositing in tissues → complement activation → inflammation.
- Typical manifestations: fever, urticaria can occur, arthralgias, nephritis—often with hypocomplementemia—but not immediate airway compromise minutes after ingestion.
Type III high-yield examples:
- Serum sickness (e.g., antitoxins, monoclonal antibodies; classically 1–2 weeks after exposure)
- Arthus reaction (localized immune complex reaction)
- SLE
- Post-strep glomerulonephritis
- Polyarteritis nodosa (often HBV immune complexes)
Board tip: Timing is your cheat code:
- Minutes = Type I
- Hours-days = Type III / Type IV
Distractor 3: T-Cell–Mediated Delayed Hypersensitivity (Type IV)
Why it’s tempting: Atopy/eczema can blur into “T-cell inflammation,” and eczema has immune complexity.
Why it’s wrong here:
- Type IV is delayed (typically 48–72 hours) and not antibody-mediated.
- Driven by Th1/Th17 inflammation and cytotoxic T cells, not IgE on mast cells.
- The stem is an immediate systemic reaction with bronchospasm and hypotension → anaphylaxis.
Type IV high-yield examples:
- Contact dermatitis (poison ivy, nickel)
- TB skin test (PPD)
- Granulomatous inflammation (TB, sarcoid)
- Type 1 diabetes mellitus (T-cell mediated β-cell destruction)
- Multiple sclerosis
Board tip: If they mention CD8+ killing or macrophage activation with delayed timing, think Type IV—not acute hives + wheeze.
Distractor 4: Complement Deficiency / C1 Esterase Inhibitor Deficiency
Often shows up as a sneaky distractor because it can present with swelling.
Why it’s tempting: Lip swelling + airway risk → “angioedema.”
Why it’s wrong here (most likely):
- Hereditary angioedema (C1 esterase inhibitor deficiency) causes:
- swelling of lips/airway
- NO urticaria
- typically not triggered by food allergen exposure in a classic IgE pattern
- mediated by bradykinin, not histamine → does not respond well to epinephrine/antihistamines
- This patient has urticaria + wheezing + hypotension and responds to epi—very consistent with IgE mast cell degranulation.
High-yield distinction table:
| Feature | Histamine-mediated (Type I anaphylaxis) | Bradykinin-mediated (hereditary/ACEi angioedema) |
|---|---|---|
| Urticaria/pruritus | Yes | No |
| Bronchospasm/wheezing | Common | Less typical |
| Trigger | Foods, stings, drugs | Trauma, stress; ACE inhibitors |
| Mediator | Histamine, leukotrienes | Bradykinin |
| Response to epinephrine/antihistamines | Yes | Poor |
| Key treatment | IM epinephrine | C1 inhibitor, icatibant, ecallantide |
Distractor 5: Excess IgE Production Alone (Without Cross-Linking)
Sometimes answer choices say “increased IgE levels” generically.
Why it’s incomplete/wrong:
- The critical event is cross-linking of allergen-specific IgE bound to mast cells, triggering degranulation.
- Elevated IgE is associated with atopy, but symptoms occur when mast cells degranulate.
Board tip: Mechanism questions want verbs: cross-linking → degranulation.
Rapid-Fire High-Yield: Type I Hypersensitivity Associations
Atopy (the classic triad-ish pattern)
- Allergic rhinitis
- Asthma (often eosinophilic)
- Atopic dermatitis (eczema)
- Food allergies
Useful labs/markers
- Serum tryptase: suggests mast cell activation (anaphylaxis)
- Eosinophilia: supports allergic/atopic conditions (especially asthma)
- Specific IgE testing (blood) or skin prick testing (immediate wheal-and-flare)
Timing patterns you should memorize
- Immediate phase (minutes): histamine, tryptase → wheal-and-flare, bronchospasm, vasodilation
- Late phase (hours): eosinophils, cytokines → sustained bronchoconstriction, tissue inflammation (important in asthma)
Step-Style “If You See This, Think That”
- Minutes after exposure + urticaria + wheeze + hypotension → Type I anaphylaxis
- Eczema/asthma/allergic rhinitis → Th2 skewing (IL-4/IL-5/IL-13), IgE, eosinophils
- No hives + recurrent angioedema + poor response to antihistamines → bradykinin (C1 inhibitor deficiency or ACE inhibitor effect)
- 48–72 hr rash after poison ivy → Type IV
- Nephritis/arthralgia days after exposure → Type III
Quick Summary Table: Hypersensitivity at a Glance
| Type | Mediator | Timing | Classic Examples |
|---|---|---|---|
| I | IgE, mast cells, basophils | Minutes | Anaphylaxis, atopy, allergic rhinitis, asthma |
| II | IgG/IgM vs fixed antigens | Hours-days | AIHA, ITP, Goodpasture, Graves, MG |
| III | Immune complexes (IgG) | Hours-days | SLE, PSGN, serum sickness, Arthus |
| IV | T cells (Th1/Th17, CD8+) | 48–72 hr | Contact dermatitis, PPD, granulomas, T1DM |
Takeaway: How to “Win” These Questions
When a vignette screams Type I, don’t just select “IgE.” Lock it in by citing:
- Timing (minutes)
- Symptoms (urticaria + bronchospasm + hypotension)
- Mechanism (IgE cross-linking on mast cells → degranulation)
- Best acute treatment (IM epinephrine)
Then, eliminate distractors systematically using timing + mediator + clinical pattern. That skill generalizes to every immunology question set you’ll see.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
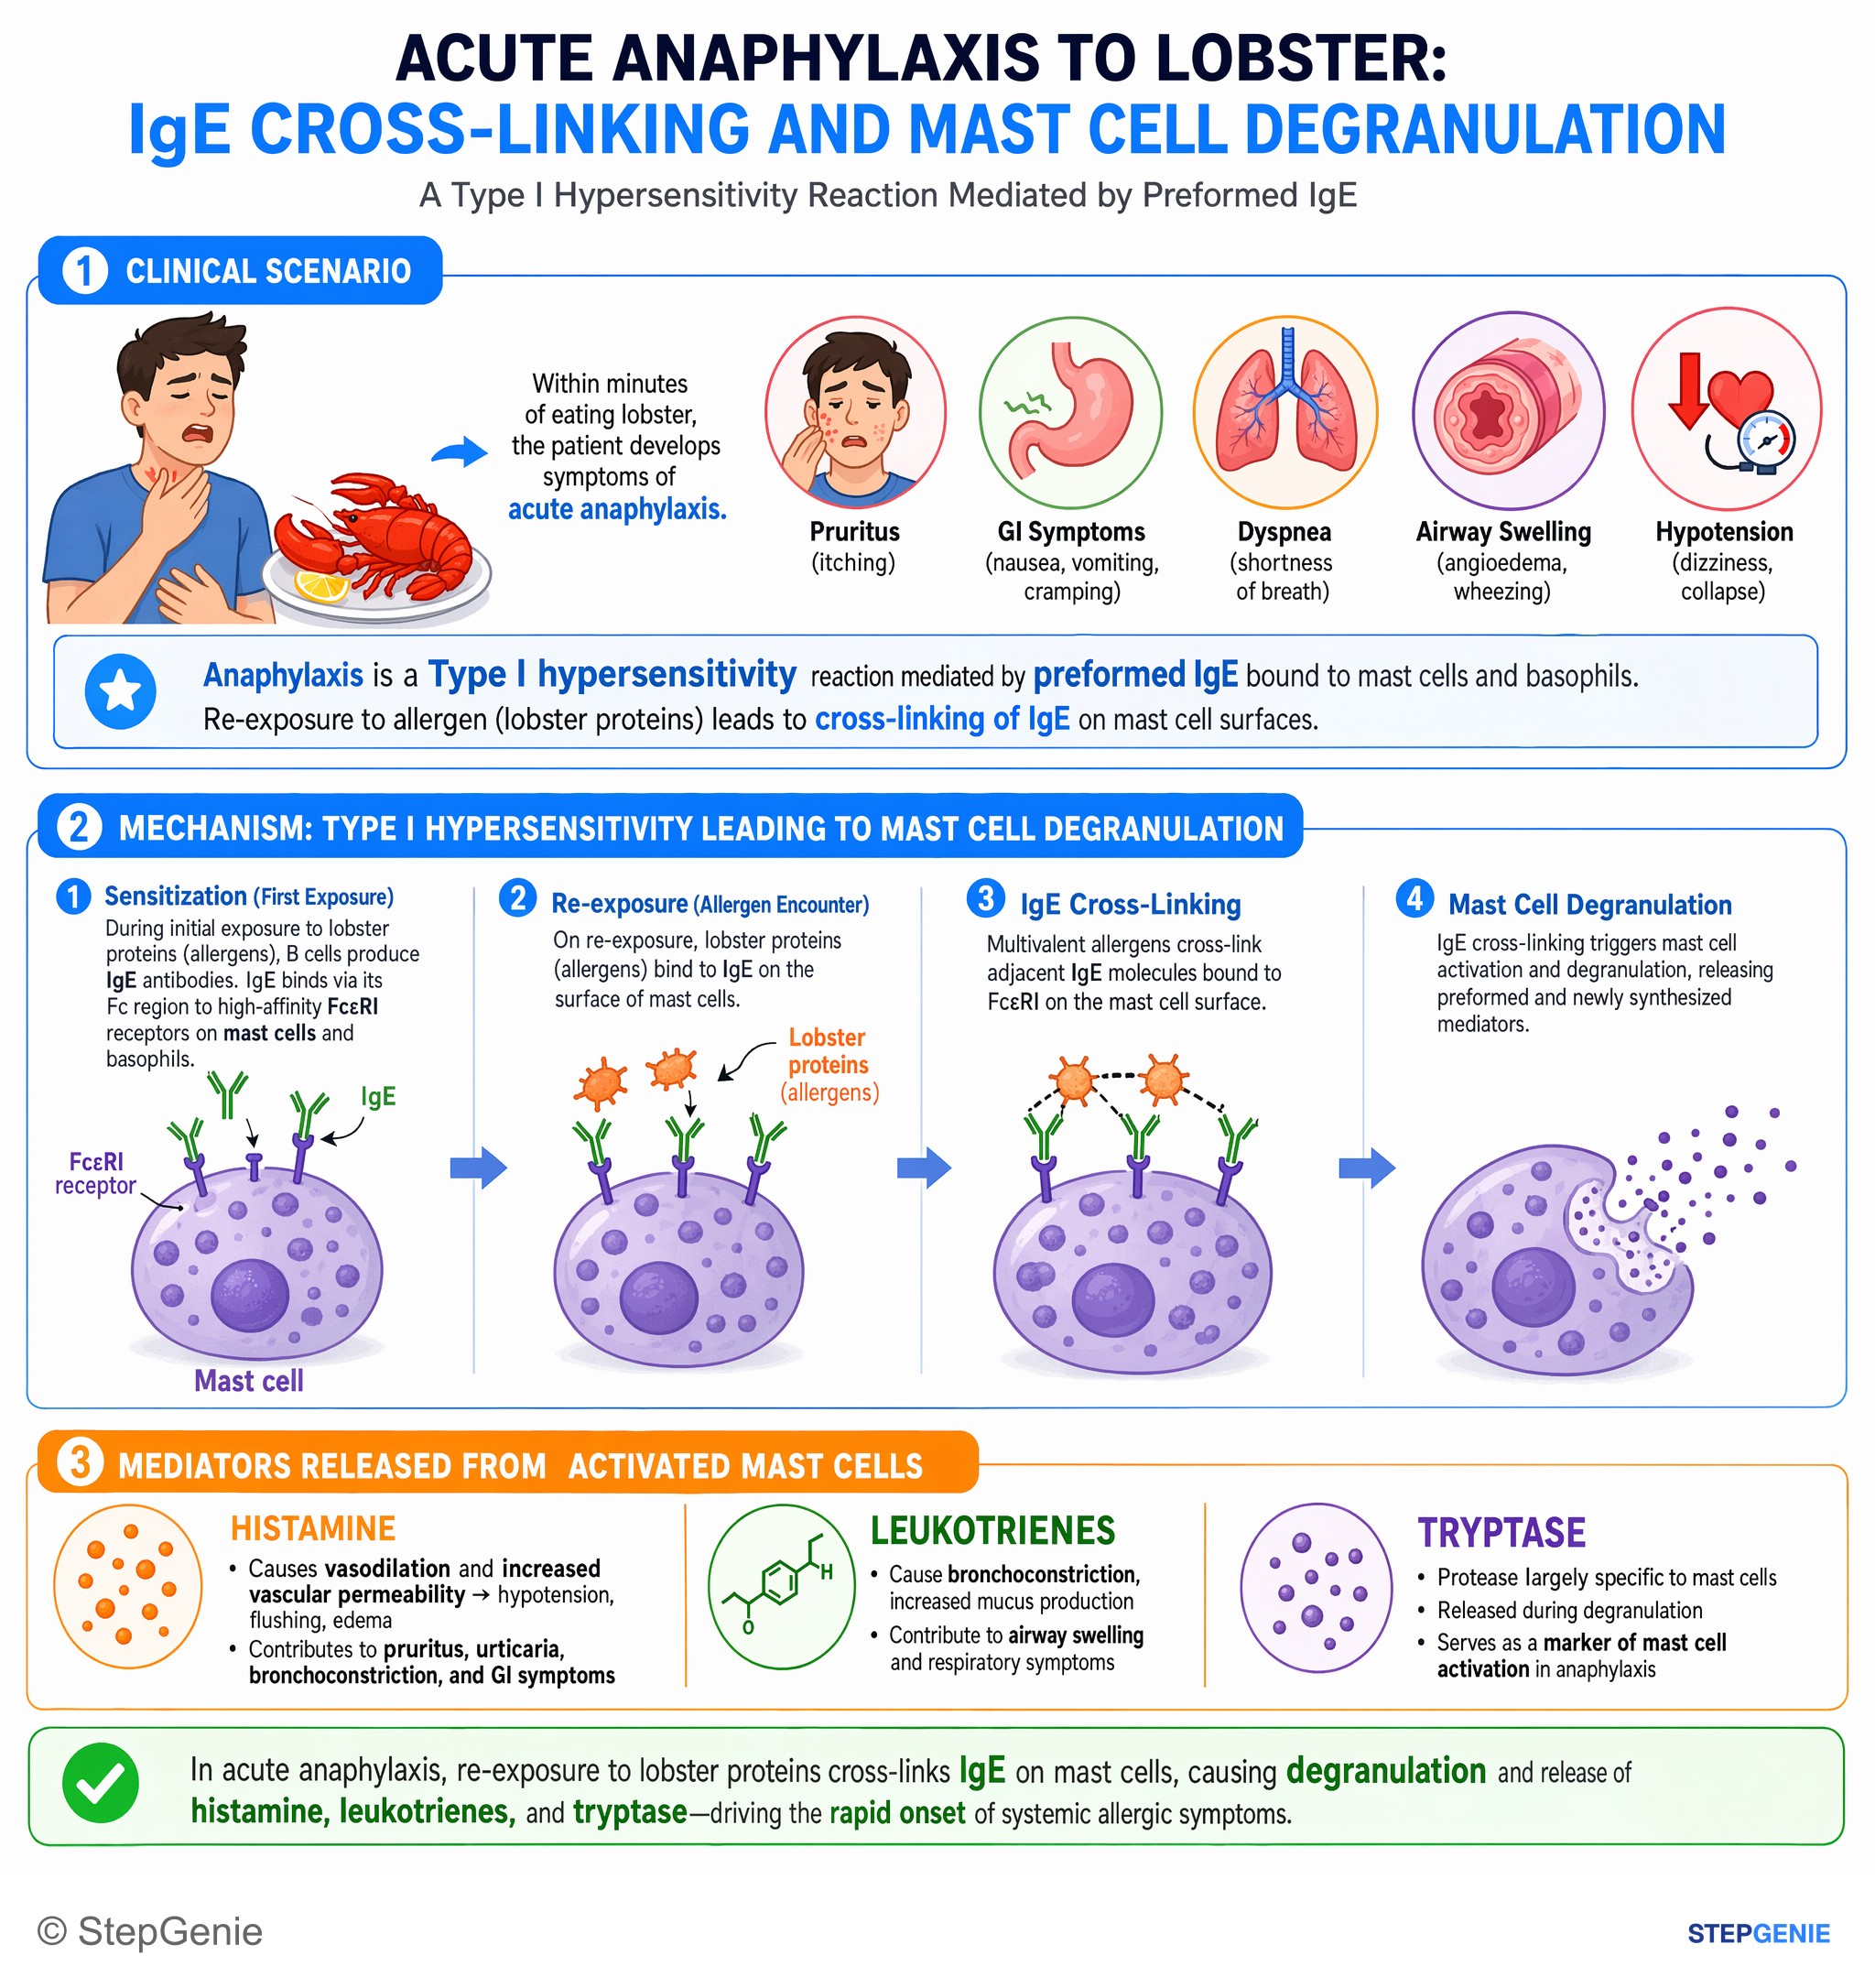
Type I hypersensitivity/anaphylaxis from IgE cross-linking on mast cells causes degranulation with release of histamine and tryptase.
USMLE Step 1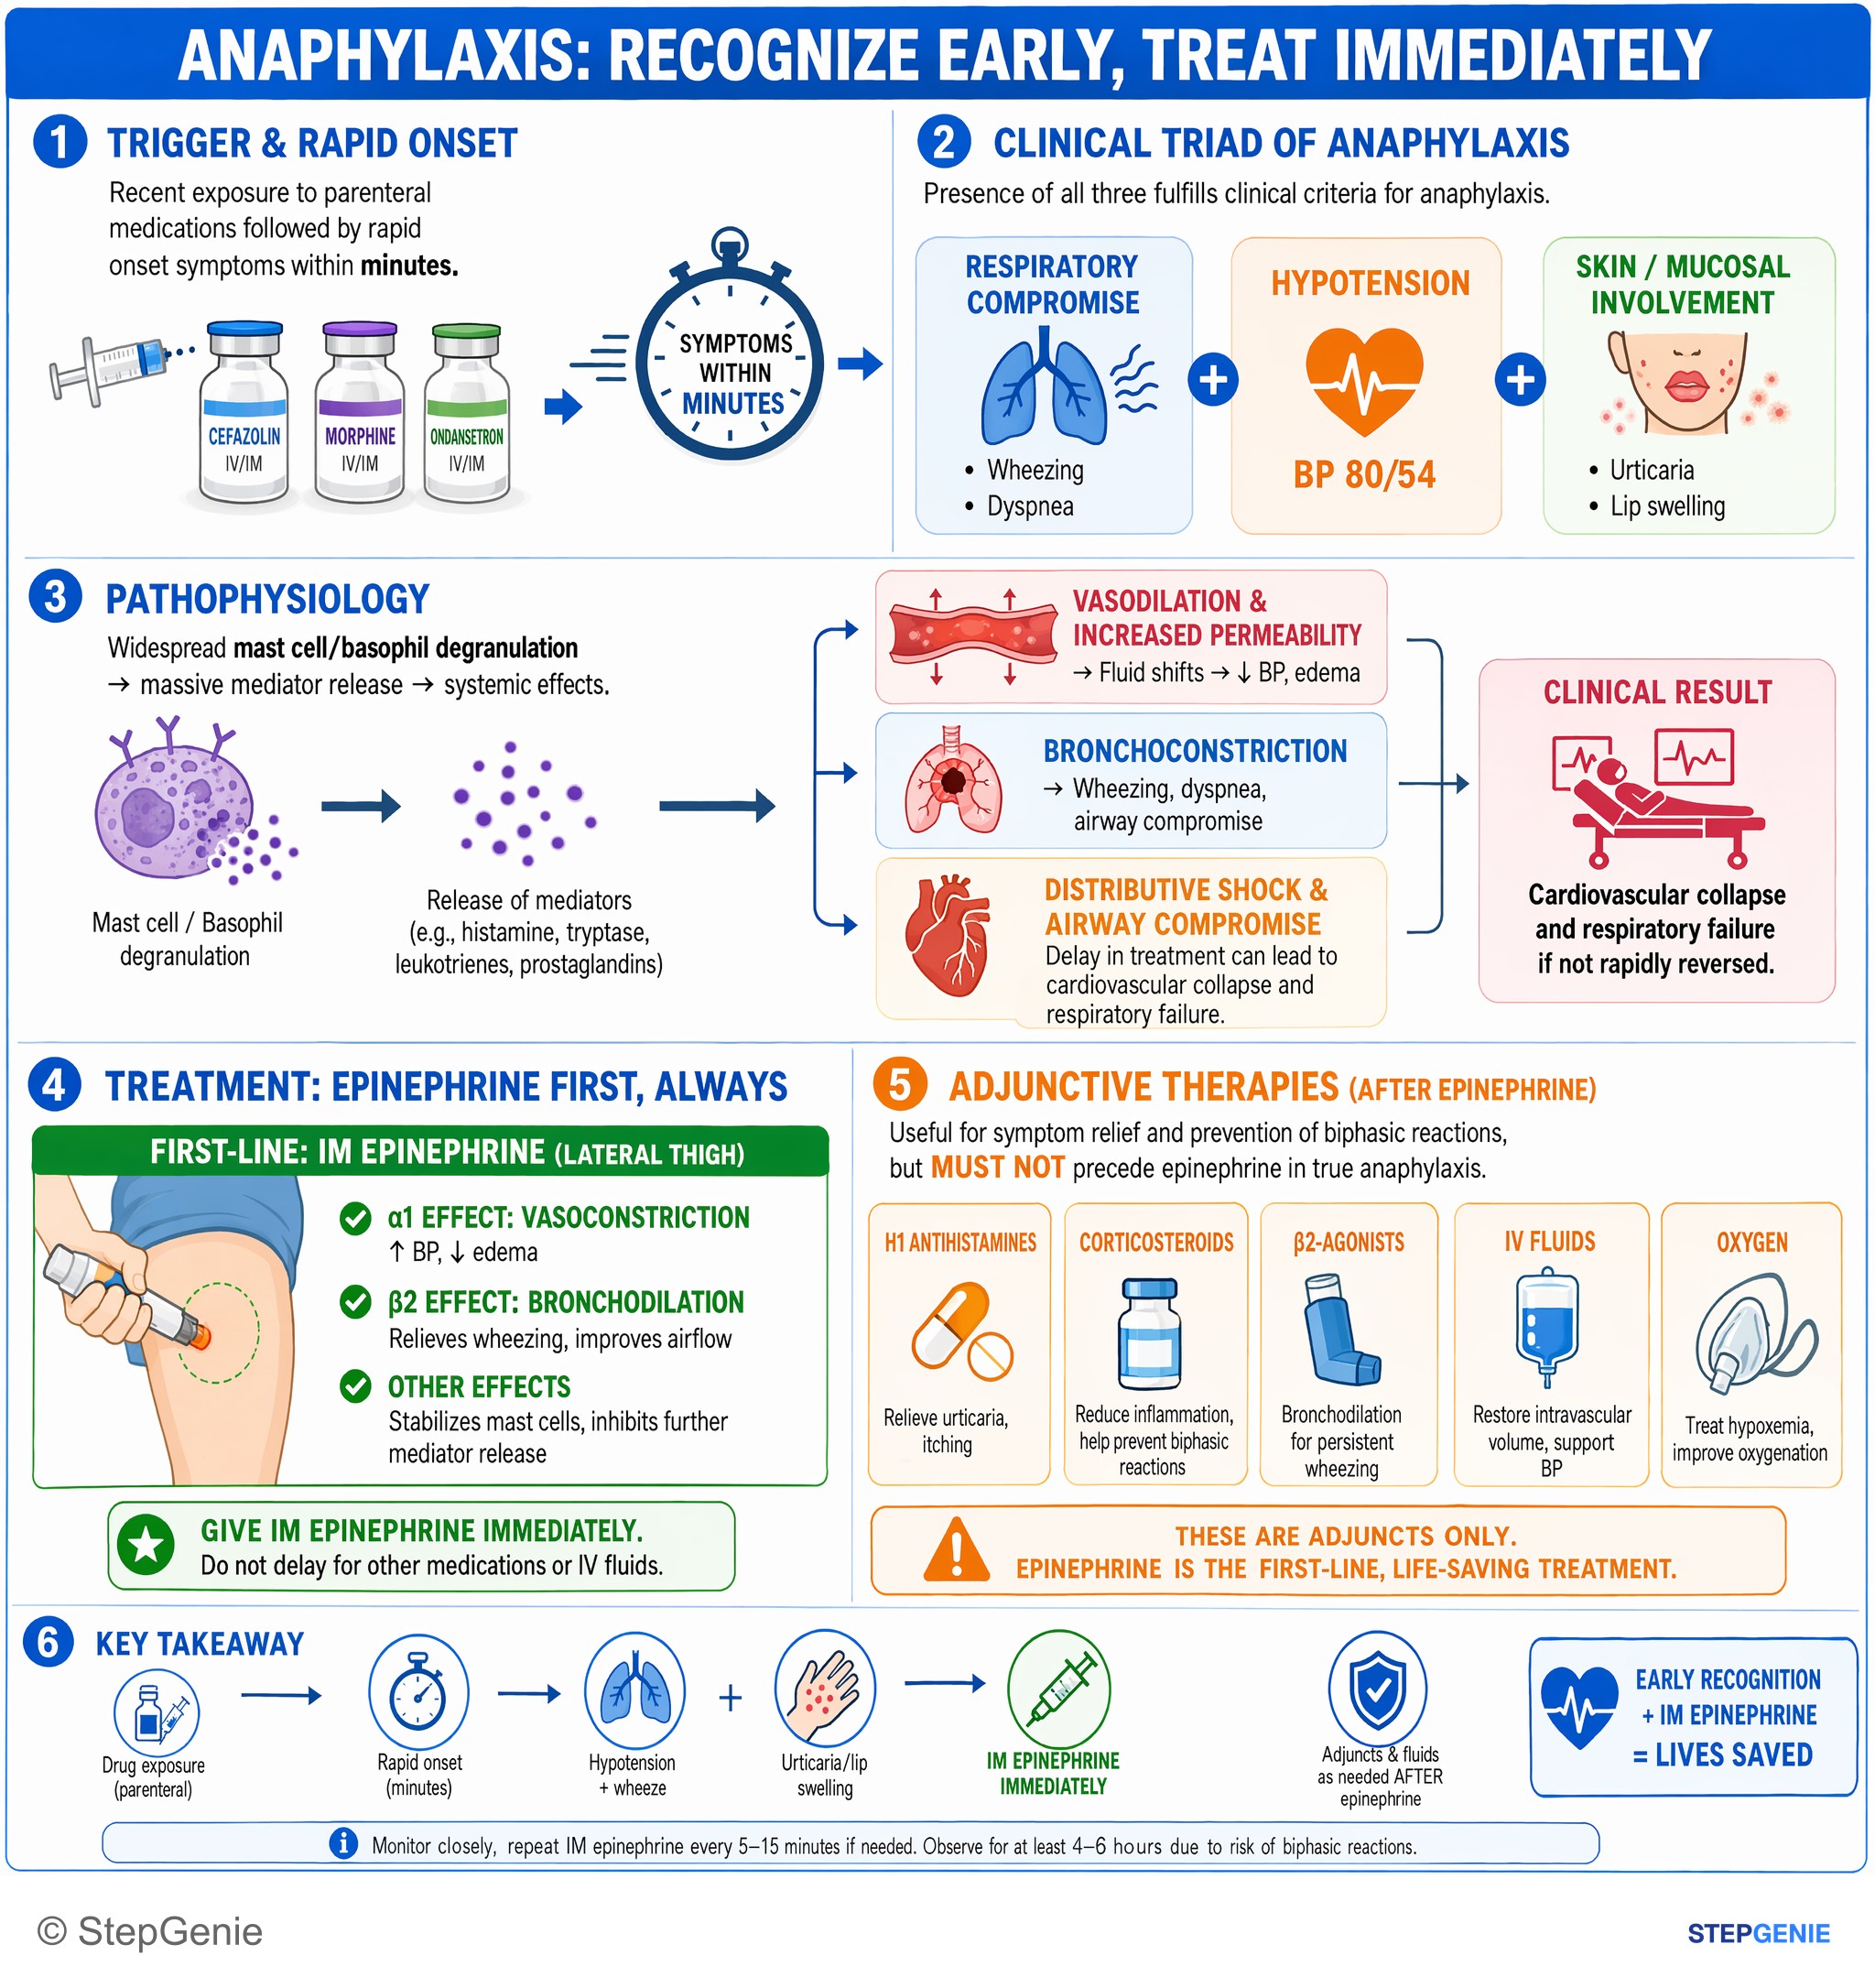
Anaphylaxis (hypotension, wheeze, urticaria after drug exposure) requires immediate IM epinephrine as first-line treatment, before…
USMLE Step 2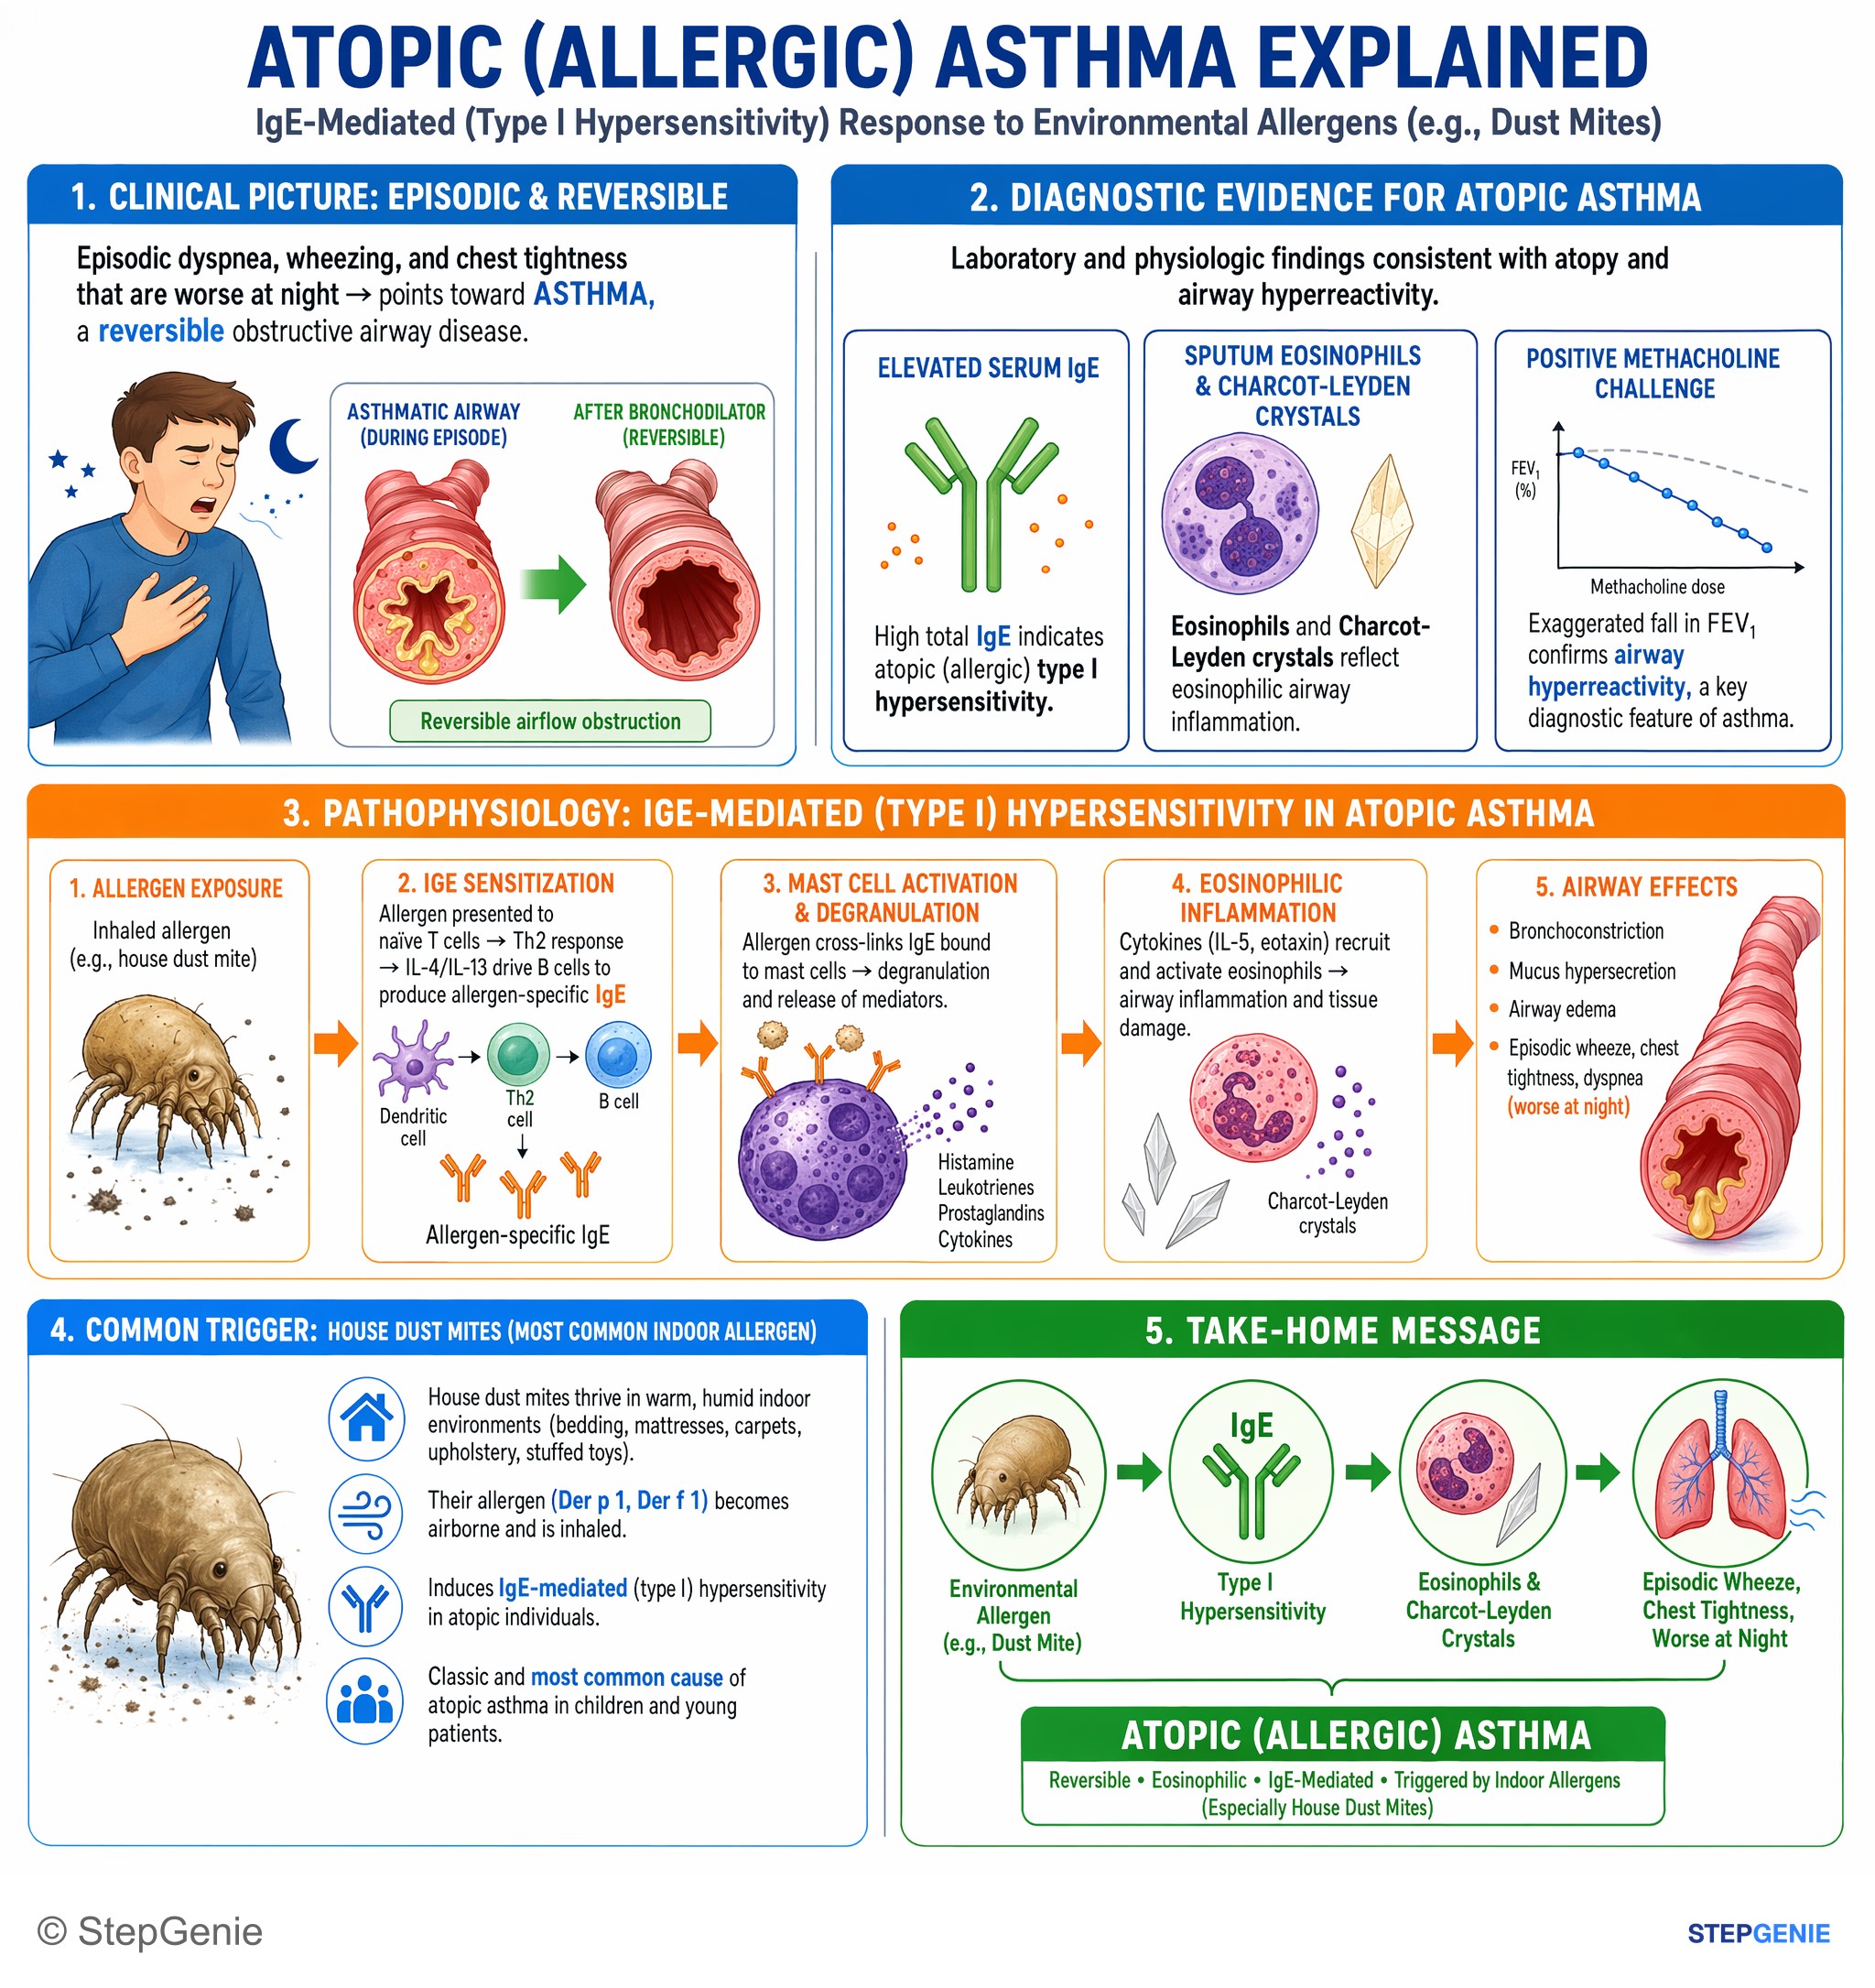
Allergic (atopic) asthma from environmental allergens (e.g., dust mites) → type I hypersensitivity with IgE, eosinophils, Charcot-Leyden…
USMLE Step 1Frequently Asked Questions
Why does this vignette point to Type I hypersensitivity instead of another immune reaction?
It points to Type I hypersensitivity because the reaction happens within minutes of allergen exposure in a previously sensitized person and causes wheezing, urticaria, lip swelling, and hypotension. That pattern reflects allergen cross-linking of IgE bound to FcεRI receptors on mast cells, which triggers immediate mast cell degranulation and the classic picture of anaphylaxis.
How do you tell Type I hypersensitivity from Type II, Type III, and Type IV on a question stem?
The fastest way to distinguish them is timing and mechanism. Type I is immediate and mediated by IgE on mast cells. Type II involves IgG or IgM against cell-bound or matrix antigens. Type III is due to IgG immune complex deposition and usually develops over hours to days. Type IV is delayed, typically 48 to 72 hours, and is driven by T cells rather than antibodies.
What mediators released from mast cells cause the symptoms of anaphylaxis?
The key mast cell mediators are histamine, tryptase, leukotrienes, prostaglandins, and cytokines. Histamine causes vasodilation, increased vascular permeability, bronchoconstriction, and pruritus. Tryptase is often elevated in anaphylaxis. Leukotrienes increase bronchoconstriction, mucus production, and vascular permeability, and prostaglandin D2 also contributes to bronchoconstriction, while cytokines recruit eosinophils and sustain inflammation.
Why is intramuscular epinephrine the first-line treatment for anaphylaxis?
Intramuscular epinephrine is first-line because it rapidly reverses the life-threatening features of anaphylaxis. Its α1 effect causes vasoconstriction, which raises blood pressure and reduces mucosal edema. Its β1 effect increases cardiac output. Its β2 effect causes bronchodilation and also stabilizes mast cells, decreasing further mediator release. Other treatments like antihistamines, steroids, albuterol, and fluids are adjuncts used after epinephrine.
How do you tell anaphylaxis from hereditary angioedema when both can cause lip swelling?
Anaphylaxis is more likely when lip swelling occurs with urticaria, wheezing, hypotension, and a clear food-triggered immediate reaction. Hereditary angioedema from C1 esterase inhibitor deficiency can cause lip or airway swelling, but it classically does not cause urticaria, is mediated by bradykinin rather than histamine, and does not respond well to epinephrine or antihistamines. Rapid improvement with epinephrine strongly supports anaphylaxis.