Drug hypersensitivity questions are stealthy because they’re really testing mechanism + timing + clinical pattern recognition—and then punishing you if you hand-wave the distractors. This post walks through a classic Q-bank-style vignette and then dissects every answer choice so you stop losing points to “sounds-right” options.
Tag: Immunology > Hypersensitivity Reactions
The Vignette (Q-bank style)
A 27-year-old woman is treated with trimethoprim-sulfamethoxazole for a urinary tract infection. Ten days later, she develops fever, a diffuse pruritic maculopapular rash, facial edema, and malaise. Labs show eosinophilia and elevated creatinine. Urinalysis reveals mild proteinuria and eosinophils. She has no mucosal erosions. Which immunologic mechanism best explains her condition?
A. IgE cross-linking on mast cells
B. Antibody binding to basement membrane with complement activation
C. Immune complex deposition in tissues
D. T-cell–mediated reaction to a drug-modified host protein
E. Defective NADPH oxidase leading to impaired killing
Step-by-Step: Identify the Syndrome First
This constellation is classic for DRESS (Drug Reaction with Eosinophilia and Systemic Symptoms):
- Timing: typically 2–8 weeks after starting a drug (but can present earlier; ~10 days can happen, especially with prior sensitization)
- Key features:
- Fever
- Diffuse morbilliform/maculopapular rash
- Facial edema
- Eosinophilia
- Internal organ involvement (kidney, liver, lung, heart)
- Common culprits: anticonvulsants (phenytoin, carbamazepine, lamotrigine), allopurinol, sulfonamides, some antibiotics (vancomycin), minocycline
The presence of eosinophils in urine + elevated creatinine also suggests drug-induced acute interstitial nephritis (AIN), which is often part of a T-cell–driven hypersensitivity picture.
Correct Answer: D. T-cell–mediated reaction to a drug-modified host protein
Why D is right
Many drug hypersensitivity reactions are Type IV (delayed) hypersensitivity:
- The drug (or metabolite) acts as a hapten, binding host proteins and creating a “new” antigen.
- This activates T cells, leading to cytokine release, inflammation, and tissue injury.
- Clinical manifestations include:
- Morbilliform drug eruption
- Contact dermatitis
- DRESS
- Stevens-Johnson syndrome / TEN (also T-cell–mediated, but different clinical picture)
High-yield association:
- Type IV = T cells (Th1/Th17 and/or CD8+)
- Often eosinophilia accompanies drug reactions due to cytokine signaling and recruitment.
Distractor Breakdown: Why the Others Are Wrong (and what they would describe)
A. IgE cross-linking on mast cells → Type I hypersensitivity
Why it’s wrong here:
Type I reactions are immediate (minutes to hours) and are mediated by IgE-bound mast cells releasing histamine and other mediators.
What you’d expect instead:
- Urticaria (hives), pruritus
- Angioedema
- Bronchospasm, wheeze
- Hypotension/anaphylaxis
- Timing: rapid after exposure (especially with re-exposure)
Classic drug examples:
- Penicillin anaphylaxis (true IgE)
- Neuromuscular blocking agents (perioperative anaphylaxis)
- Some cases of latex-related OR reactions (not a drug, but tested similarly)
USMLE tip: A diffuse morbilliform rash + fever + eosinophilia + organ involvement is not the Type I pattern.
B. Antibody binding to basement membrane with complement activation → Type II (anti-BM)
Why it’s wrong here:
This describes Goodpasture syndrome (anti–type IV collagen in basement membranes) or similarly targeted antibody injury.
What you’d expect instead:
- Hemoptysis + pulmonary hemorrhage
- Rapidly progressive glomerulonephritis
- Linear immunofluorescence along basement membrane
USMLE anchor:
- Type II = antibody against a fixed antigen on cells/tissues (or ECM), often with complement-mediated damage.
C. Immune complex deposition in tissues → Type III hypersensitivity
Why it’s wrong here:
Type III is about circulating immune complexes depositing in vessels/tissues → complement activation → inflammation.
What you’d expect instead (classic “serum sickness”-type picture):
- Fever
- Urticaria
- Arthralgias
- Lymphadenopathy
- Possible proteinuria
- Timing: often 1–2 weeks after exposure (fits timing better than Type I)
Drug examples:
- Penicillins, cephalosporins (serum sickness–like reactions)
- Sulfonamides can do this too (which is why this distractor is tempting)
How to separate from DRESS/AIN clinically:
- DRESS: eosinophilia + facial edema + organ involvement (esp liver/kidney) + diffuse morbilliform rash
- Serum sickness (Type III): immune complex features—arthralgias, urticarial rash, hypocomplementemia (often), less emphasis on eosinophilia/facial edema
E. Defective NADPH oxidase leading to impaired killing → Chronic granulomatous disease
Why it’s wrong here:
This is an inherited immunodeficiency, not a hypersensitivity mechanism.
What you’d expect instead:
- Recurrent catalase-positive infections (e.g., S. aureus, Serratia, Nocardia, Aspergillus)
- Granuloma formation
- Abnormal dihydrorhodamine test (decreased fluorescence)
USMLE trap: If the stem screams “drug reaction,” don’t let a random immunodeficiency mechanism hijack you.
High-Yield Table: Hypersensitivity Types You Actually Need on Test Day
| Type | Mechanism | Timing | Hallmark findings | Classic examples |
|---|---|---|---|---|
| I | IgE → mast cell degranulation | Minutes | Urticaria, anaphylaxis, bronchospasm | Anaphylaxis to penicillin; allergic rhinitis; asthma |
| II | IgG/IgM vs fixed antigen → complement/ADCC | Hours–days | Cytopenias, tissue-specific injury | Autoimmune hemolytic anemia; Goodpasture |
| III | Immune complexes deposit → complement | 1–2 weeks | Fever, urticaria, arthralgias, vasculitis | Serum sickness; SLE; post-strep GN |
| IV | T-cell mediated (delayed) | Days–weeks | Morbilliform rash, contact dermatitis, SJS/TEN, DRESS | Poison ivy; PPD test; DRESS |
Mini-Section: Where Drug Hypersensitivity Commonly Shows Up
1) Acute interstitial nephritis (AIN) (often Type IV)
Triad (board-famous):
- Fever
- Rash
- Eosinophilia
Common causes:
- NSAIDs
- Penicillins/cephalosporins
- Sulfonamides
- Rifampin
- PPIs
Clue in vignette: Urine eosinophils (not perfectly sensitive/specific, but heavily tested)
2) SJS/TEN (also Type IV, but different clinical severity)
Key differentiators from DRESS:
- Painful dusky rash, skin sloughing
- Mucosal involvement (oral/ocular/genital)
- Nikolsky sign may be positive
- Often within 1–3 weeks of drug initiation
Common drugs:
- Sulfonamides, allopurinol, anticonvulsants, NSAIDs (esp oxicams)
In our vignette: explicitly no mucosal erosions, pointing away from SJS/TEN.
How to Stop Missing These: A Simple Exam Strategy
- Lock timing first: minutes (Type I) vs 1–2 weeks (Type III) vs delayed (Type IV).
- Scan for buzz features:
- Eosinophilia + facial edema + organ injury → think DRESS (Type IV)
- Arthralgias + urticarial rash + low complement → think serum sickness (Type III)
- Mucosal involvement + skin sloughing → think SJS/TEN (Type IV)
- Then pick the immunologic mechanism—don’t do it in reverse.
Rapid-Fire Takeaways (what to remember on test day)
- DRESS = Type IV, delayed, eosinophilia + systemic involvement, facial edema is a huge clue.
- AIN often rides along with T-cell drug hypersensitivity; urine eosinophils are a classic clue.
- Serum sickness = Type III and often presents with arthralgias + urticaria after ~1–2 weeks.
- SJS/TEN = Type IV, but look for mucosal involvement and skin detachment.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
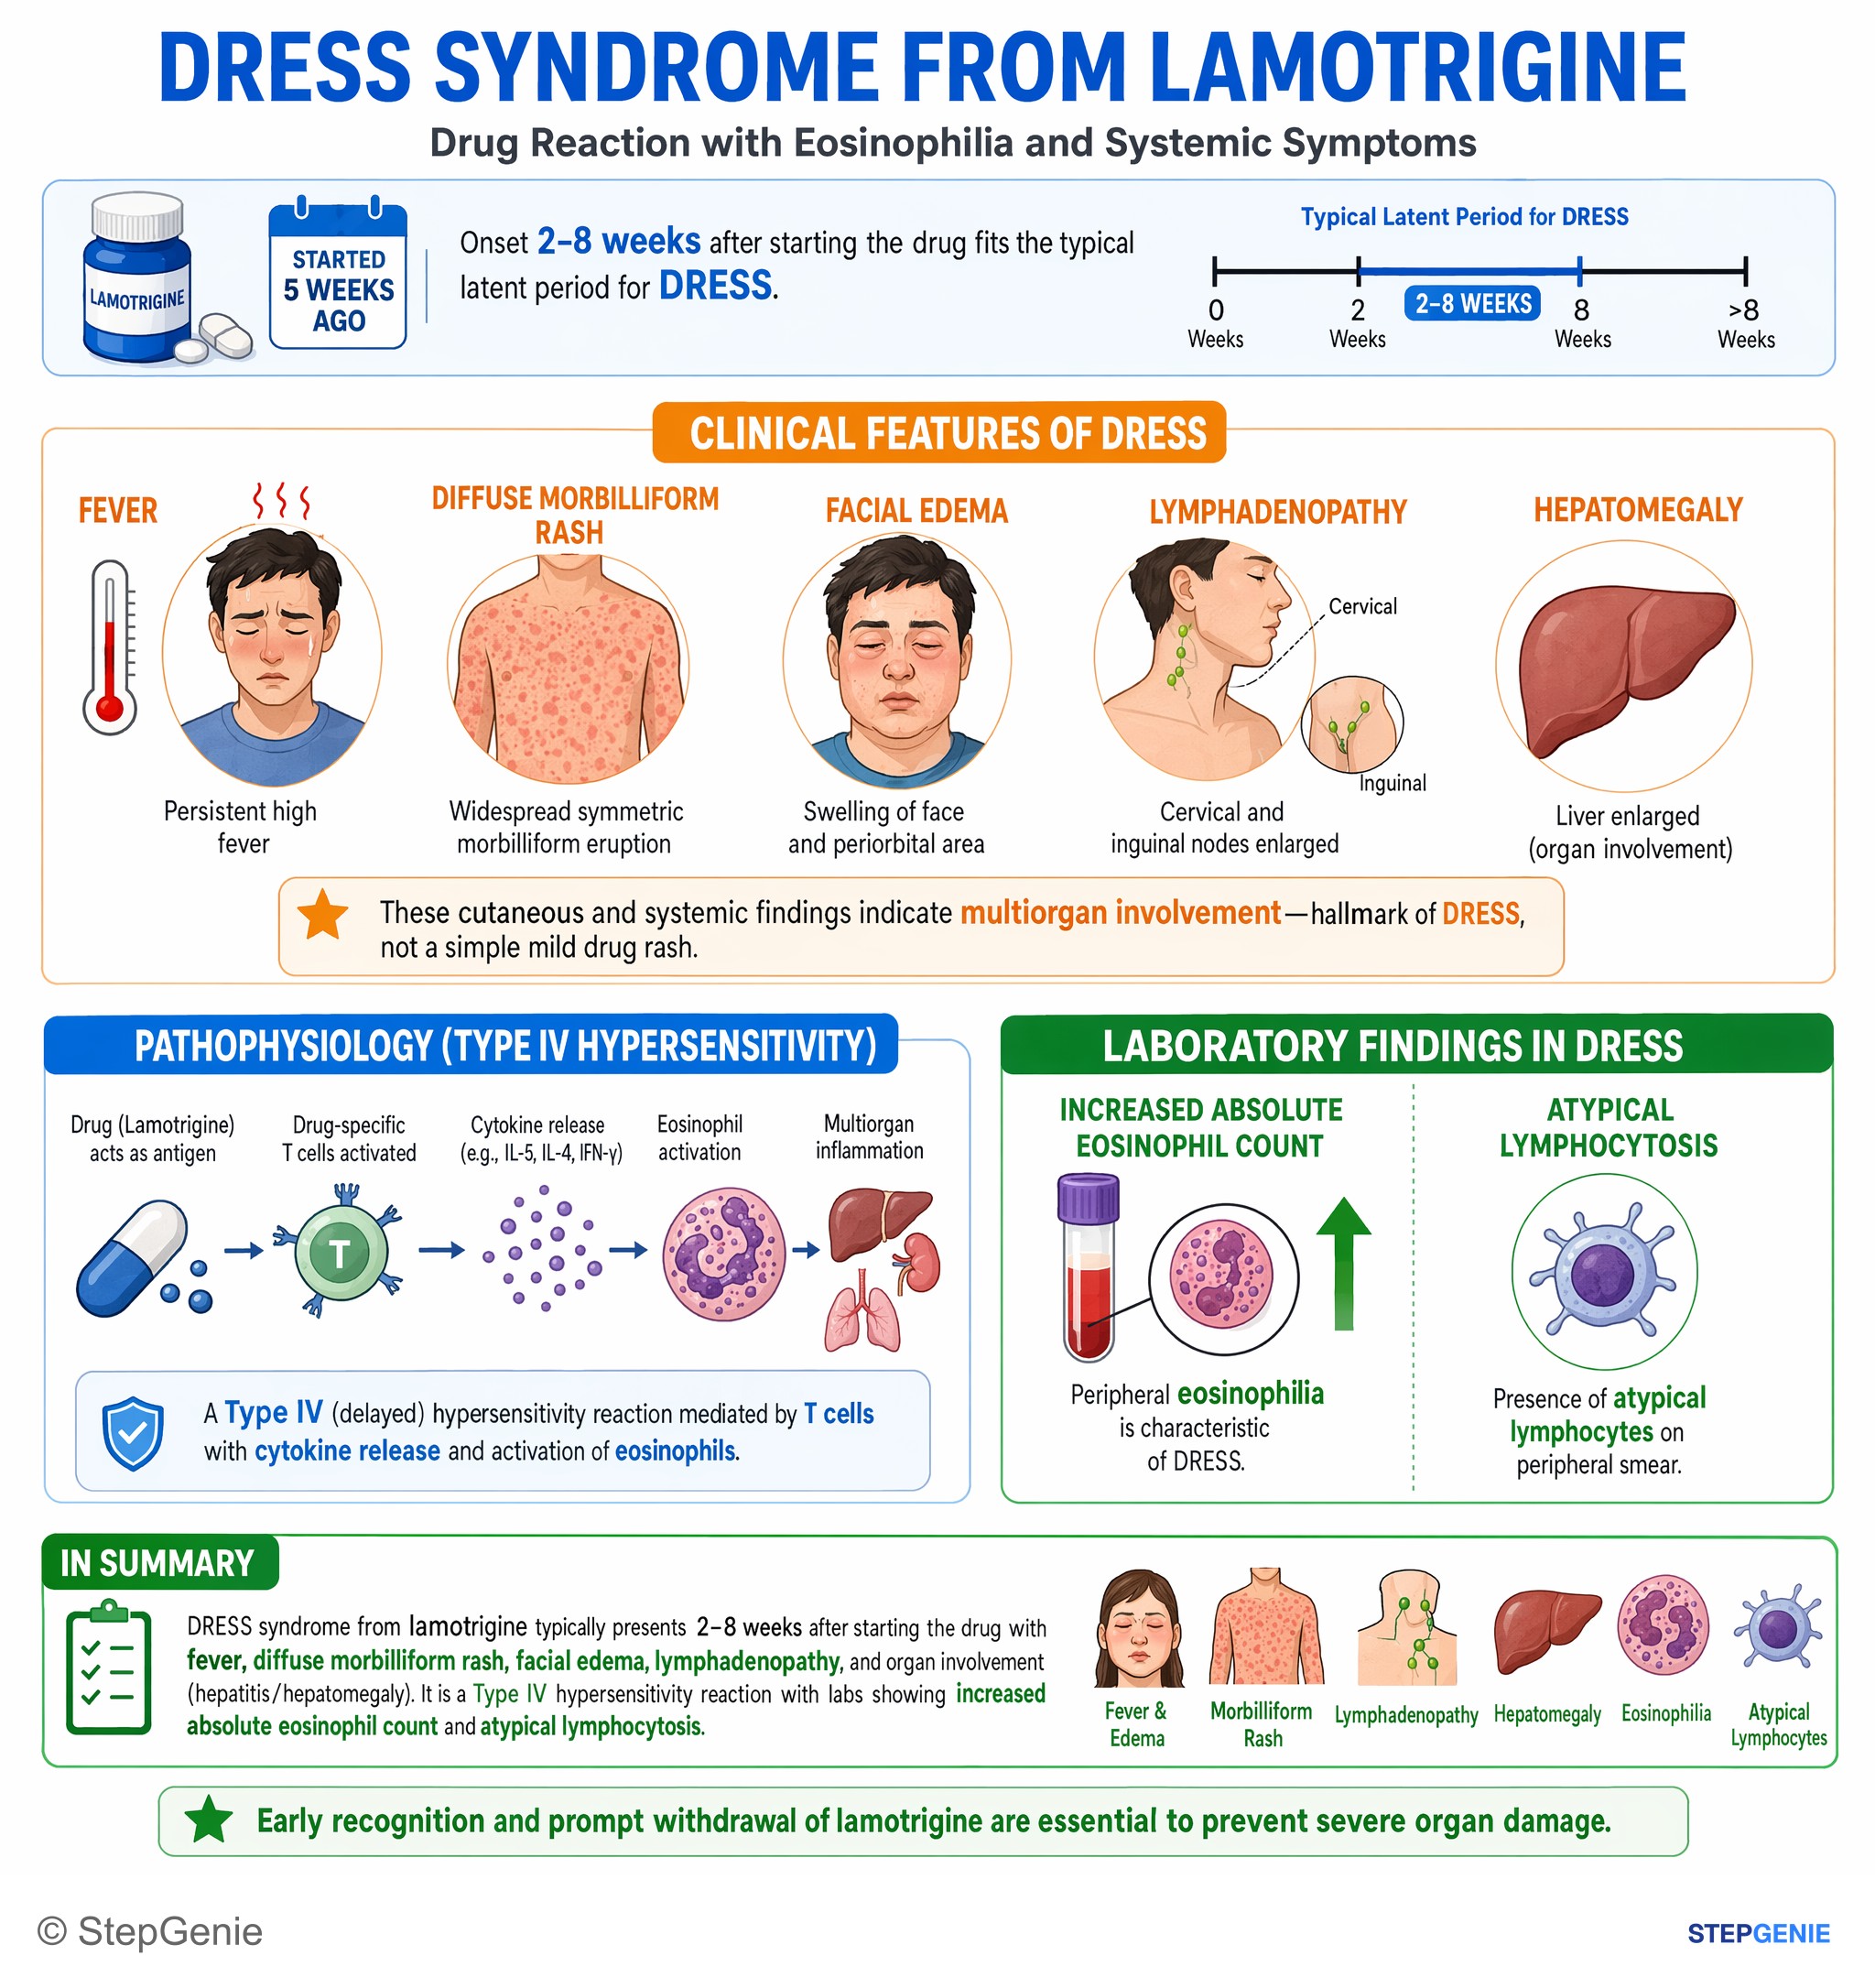
DRESS syndrome from lamotrigine: fever, morbilliform rash, facial edema, lymphadenopathy, organ involvement (hepatitis) → labs show…
USMLE Step 1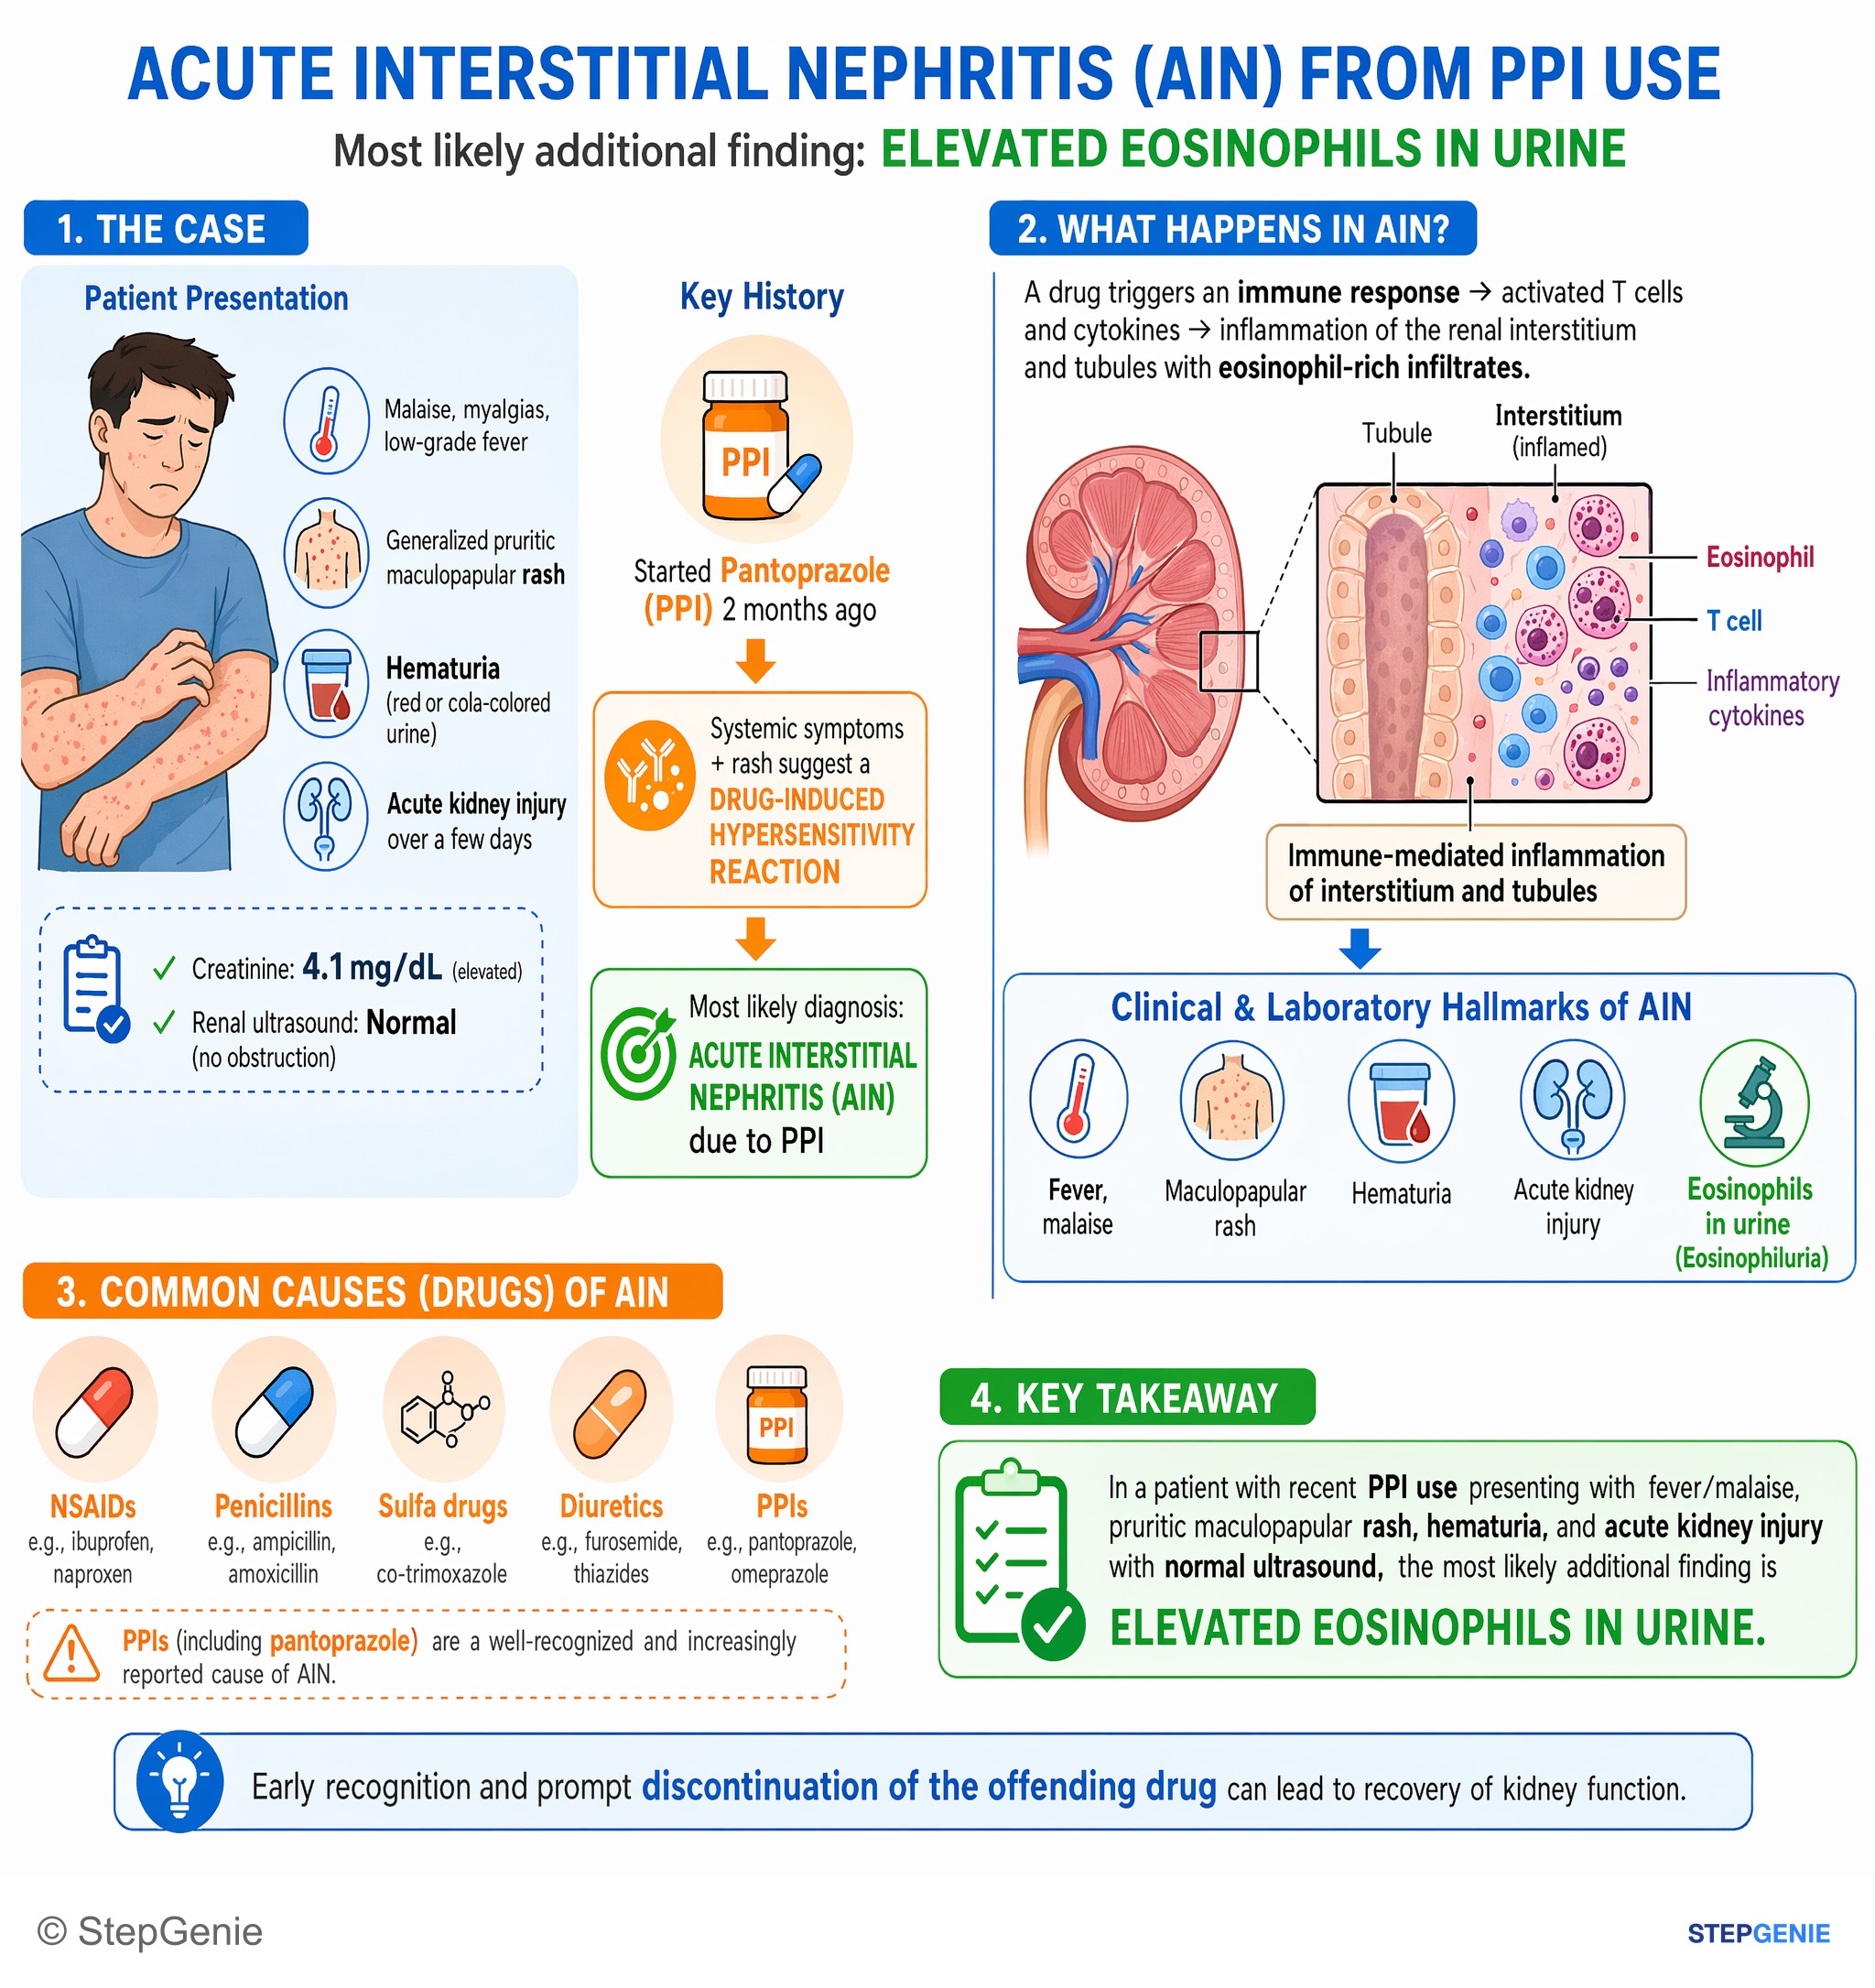
Acute interstitial nephritis from PPI use: fever/malaise, maculopapular rash, hematuria, acute kidney injury, and urinary eosinophils.
USMLE Step 1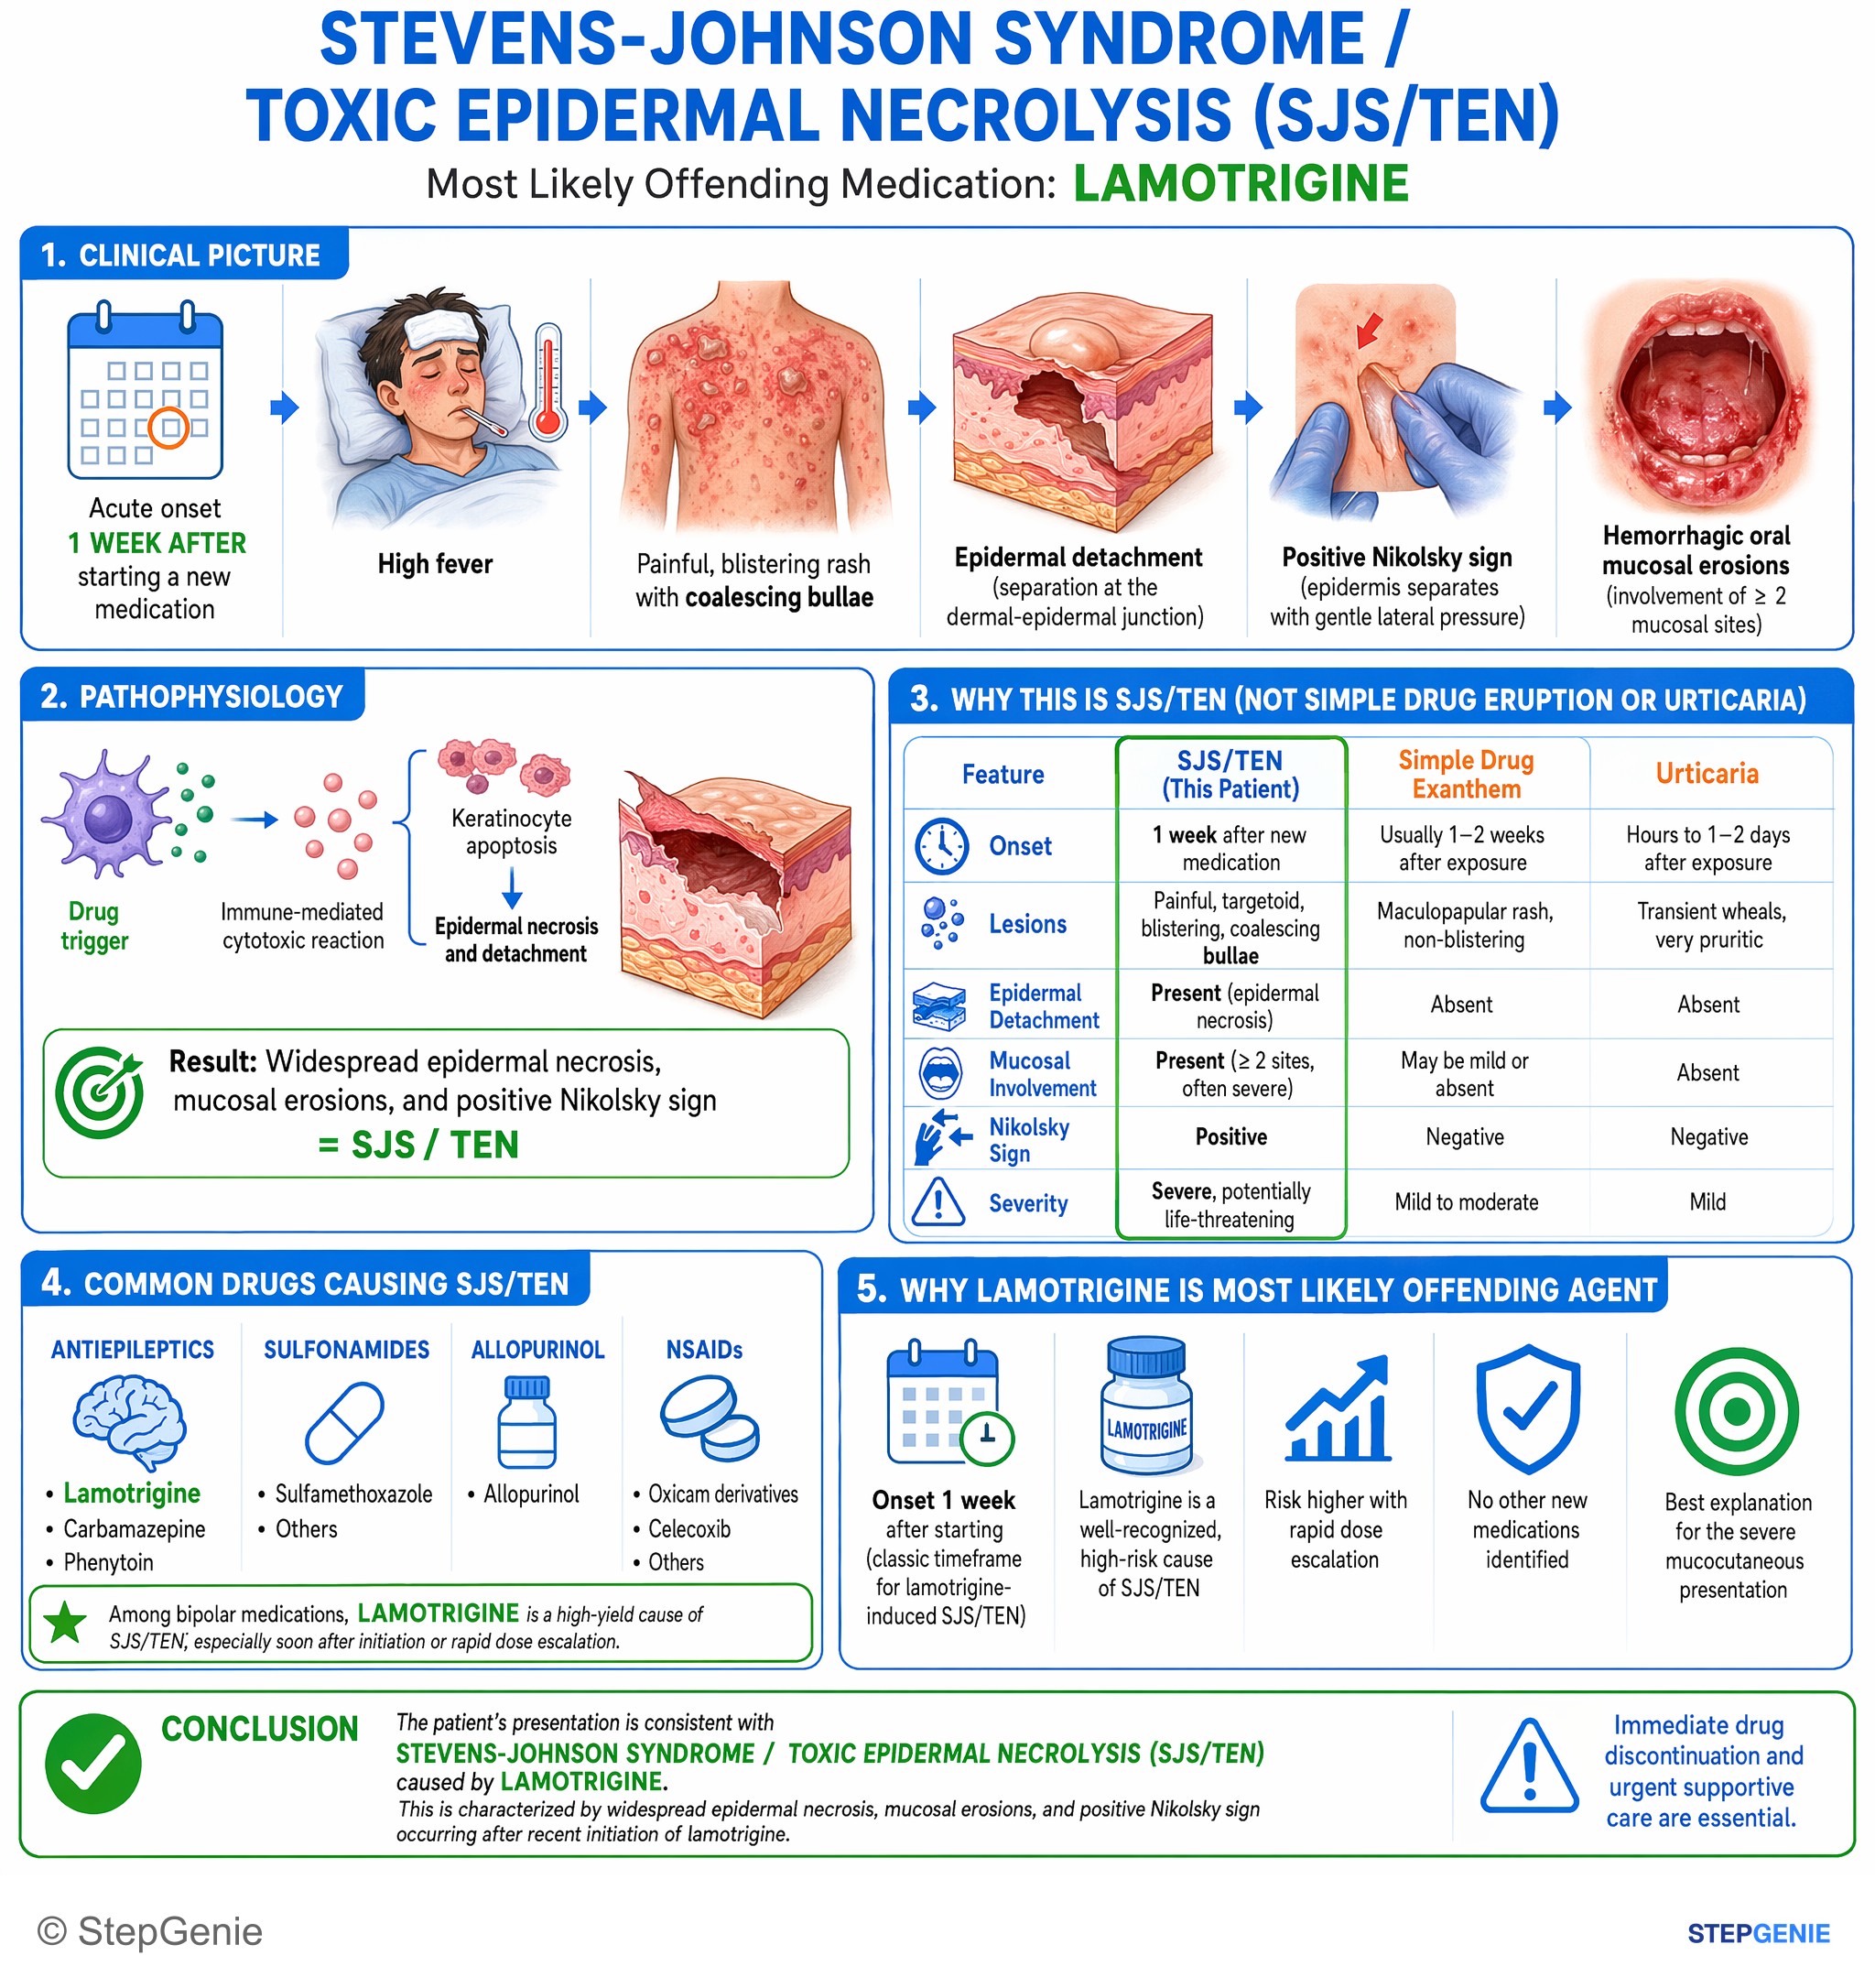
Stevens-Johnson syndrome/toxic epidermal necrolysis from lamotrigine: widespread epidermal necrosis, mucosal erosions, positive Nikolsky…
USMLE Step 1Frequently Asked Questions
What hypersensitivity mechanism causes DRESS from a drug like trimethoprim-sulfamethoxazole?
DRESS is caused by a Type IV, T-cell–mediated hypersensitivity reaction to a drug-modified host protein. The drug or its metabolite acts as a hapten, binds host proteins, and creates a new antigen that activates T cells. This leads to cytokine release, inflammation, and tissue injury, which explains the fever, morbilliform rash, eosinophilia, and internal organ involvement.
How do you tell DRESS from an IgE-mediated drug allergy?
DRESS is distinguished from an IgE-mediated reaction by its delayed timing and systemic pattern. IgE-mediated Type I reactions usually happen within minutes to hours and cause urticaria, angioedema, bronchospasm, or hypotension. DRESS instead presents days to weeks after starting the drug with diffuse maculopapular or morbilliform rash, fever, eosinophilia, facial edema, and organ involvement.
How do you differentiate DRESS from serum sickness on a hypersensitivity question?
DRESS is more likely when you see eosinophilia, facial edema, a diffuse morbilliform rash, and internal organ involvement, especially kidney or liver injury. Serum sickness is a Type III immune complex reaction that more classically causes fever, urticaria, arthralgias, lymphadenopathy, and sometimes proteinuria. Sulfonamides can tempt you toward either choice, so the clinical pattern is the key discriminator.
Why do eosinophils in the urine and elevated creatinine point toward acute interstitial nephritis in a drug reaction?
Eosinophils in the urine with elevated creatinine suggest drug-induced acute interstitial nephritis because they indicate kidney involvement within a T-cell–driven hypersensitivity picture. In the vignette, this fits with DRESS, which commonly includes internal organ injury. The renal findings support a delayed drug reaction rather than an immediate IgE-mediated allergy or a non-hypersensitivity disorder.
What clues make a drug rash more consistent with DRESS than Stevens-Johnson syndrome or toxic epidermal necrolysis?
The absence of mucosal erosions along with fever, diffuse pruritic maculopapular rash, facial edema, eosinophilia, and renal involvement makes DRESS more consistent than Stevens-Johnson syndrome or toxic epidermal necrolysis. Both DRESS and SJS/TEN are T-cell–mediated drug reactions, but the vignette’s combination of eosinophilia and systemic findings with no mucosal erosions points toward DRESS.