T cells are paranoid by design: they won’t fully activate just because they “see” an antigen. They require a second, independent confirmation signal—costimulation—to prevent accidental attacks on self. On Step 1, this shows up everywhere: transplant rejection, tumor immune evasion, CTLA-4 drugs, HIV, hyper-IgM, chronic granulomatous disease tie-ins (via T-cell help), and the classic “T cell becomes anergic without costimulation” vignette.
Big Picture: What Are Costimulatory Molecules?
Costimulatory molecules are receptor–ligand pairs that provide “Signal 2” (and additional tuning signals) during immune cell activation.
The classic 2-signal model (T cells)
- Signal 1 (specificity): TCR recognizes peptide presented on MHC
- Signal 2 (costimulation): ensures antigen recognition occurs in the right context (infection/danger)
- Signal 3 (cytokines): shapes differentiation (Th1/Th2/Th17/Tfh/Treg)
High-yield rule:
If a naive T cell receives Signal 1 without Signal 2 → anergy (functional unresponsiveness) or deletion/tolerance.
Core Costimulatory Pathways You Must Know
1) B7 (CD80/86) ↔ CD28 (activation)
- APC expresses: B7 (CD80/CD86)
- T cell expresses: CD28
- Result: IL-2 production, clonal expansion, survival
Where B7 comes from (Step logic):
APCs (especially dendritic cells) upregulate B7 when their PRRs (e.g., TLRs) sense microbes → links innate danger sensing to adaptive activation.
Vignette clue: “T cells fail to activate after exposure to antigen because APCs lack B7” → think impaired costimulation.
2) B7 (CD80/86) ↔ CTLA-4 (inhibition)
- CTLA-4 is upregulated after T-cell activation and is constitutively expressed on Tregs
- Binds B7 with higher affinity than CD28
- Function: “brake” at the priming phase (lymph nodes)
Clinical tie-in (HY):
- CTLA-4 inhibitor: Ipilimumab
- Boosts T-cell activation against cancer
- Causes immune-related adverse events (autoimmune-like): colitis, hepatitis, dermatitis, hypophysitis, thyroiditis
Board-style phrasing: “Checkpoint inhibitor causing severe diarrhea and colitis” → CTLA-4 (or PD-1/PD-L1) blockade.
3) CD40 (APC/B cell) ↔ CD40L (CD154 on Th cells) (help)
This is the most tested “T cell helps B cell / macrophage” interaction.
-
On B cells, CD40 signaling:
- Class switching (with cytokines)
- Germinal center formation
- Affinity maturation (with Tfh help)
-
On macrophages, CD40 signaling:
- “Licenses” macrophages—especially important in intracellular pathogens
- Works with IFN-γ from Th1 cells to enhance killing
Clinical tie-in (very HY): Hyper-IgM syndrome (X-linked)
- Defect: CD40L on Th cells
- Consequences:
- No class switching → ↑ IgM, ↓ IgG/IgA/IgE
- Absent germinal centers
- Susceptible to opportunistic infections (e.g., Pneumocystis, Cryptosporidium, CMV)
- Typical prompt: “Boy with recurrent pyogenic infections, no CD40L, high IgM, absent germinal centers.”
4) PD-1 (T cell) ↔ PD-L1/PD-L2 (inhibition in tissues)
- PD-1 is expressed on T cells (especially chronically stimulated/exhausted T cells)
- PD-L1 can be expressed on APCs and many tissues, including tumors
- Function: peripheral “brake” to reduce tissue damage; important in T-cell exhaustion (e.g., chronic viral infection)
Drugs (HY):
- Nivolumab, Pembrolizumab = anti–PD-1
- Atezolizumab, Durvalumab, Avelumab = anti–PD-L1
- Adverse effects similar to CTLA-4 inhibitors: autoimmune-like (pneumonitis, colitis, hepatitis, endocrinopathies)
Step pattern recognition: Tumor evades immune attack by expressing PD-L1 → blocking PD-1 restores T-cell function.
Costimulation: Pathophysiology & “Why It Matters”
Without costimulation: Anergy and tolerance
- In the absence of infection/danger, APCs present antigen with low B7 expression
- Naive T cells seeing antigen under these conditions become anergic
- This is a core mechanism of peripheral tolerance (prevents autoimmunity)
With costimulation: Productive immunity
- Infection → PRR signaling (TLRs, etc.) → ↑ B7 and cytokines
- T cells proliferate (IL-2), differentiate, and provide downstream help:
- Activate macrophages (Th1)
- Activate eosinophils and B cells (Th2)
- Recruit neutrophils (Th17)
- Support germinal centers (Tfh)
High-Yield Table: Signal Pairs, Cells, and Outcomes
| Pathway | Ligand (Cell) | Receptor (Cell) | Net Effect | HY Associations |
|---|---|---|---|---|
| B7 (CD80/86)–CD28 | B7 on APC | CD28 on T cell | Activates T cells (↑ IL-2) | Lack of B7 → anergy |
| B7–CTLA-4 | B7 on APC | CTLA-4 on T cell/Treg | Inhibits T-cell priming | Ipilimumab; autoimmune toxicities |
| CD40–CD40L (CD154) | CD40 on B cell/APC | CD40L on Th cell | Class switching, macrophage activation | Hyper-IgM (X-linked CD40L) |
| PD-1–PD-L1/PD-L2 | PD-L1 on tumor/APC/tissues | PD-1 on T cell | Inhibits in peripheral tissues; exhaustion | Pembrolizumab/Nivolumab; tumor evasion |
Clinical Presentation: How It Appears in Vignettes
A) “T cells don’t activate” → think missing costimulation
- Naive T cell recognizes peptide–MHC but fails to proliferate
- Lab clue: low IL-2, poor clonal expansion
- Mechanism: no B7–CD28 engagement → anergy
B) “High IgM, no class switching” → CD40L defect
- Recurrent sinopulmonary infections + opportunistic infections
- Lab: ↑ IgM, ↓ others
- Lymph node biopsy: absent germinal centers
C) “Checkpoint inhibitor side effects” → CTLA-4 or PD-1 blockade
- Patient on immunotherapy develops:
- Colitis (watery diarrhea)
- Hepatitis (↑ LFTs)
- Pneumonitis (cough, dyspnea)
- Endocrinopathies (hypophysitis, thyroiditis, adrenal insufficiency)
D) “Tumor expresses PD-L1” → immune evasion
- Reduced cytotoxic T-cell activity in the tumor microenvironment
- Responds to PD-1/PD-L1 inhibitors
Diagnosis: What You’d Actually Test (and What Step Expects)
Step-style “diagnosis” = interpret the immunology
You’re rarely ordering “B7 levels.” Instead, you infer defects based on:
- Flow cytometry markers (e.g., absent CD40L on Th cells)
- Immunoglobulin patterns (hyper-IgM profile)
- History of recurrent/opportunistic infections
- Drug exposure (checkpoint inhibitors) + autoimmune symptoms
Real-world confirmatory examples (for context)
- Hyper-IgM: flow cytometry for CD40L (CD154), genetic testing
- Checkpoint toxicity: clinical diagnosis + labs (LFTs, thyroid function), imaging for pneumonitis, colonoscopy if severe colitis
Treatment & Management (High Yield)
Hyper-IgM syndrome (CD40L deficiency)
- IVIG replacement (provides IgG)
- Prophylaxis against opportunistic infections (institution-specific; commonly TMP-SMX for Pneumocystis)
- Hematopoietic stem cell transplant can be curative in select cases
Checkpoint inhibitor toxicity
- Hold immunotherapy depending on severity
- Corticosteroids for moderate–severe immune-related adverse events
- Escalation (specialist-driven): e.g., infliximab for refractory colitis (avoid in some hepatitis settings)
Therapeutic exploitation of costimulation
- CTLA-4 and PD-1/PD-L1 inhibitors enhance anti-tumor immunity by removing inhibitory signals
Innate–Adaptive Bridge: Why APCs Control Costimulation
A common “concept integration” question is: Why doesn’t every antigen activate T cells?
- Dendritic cells sense microbes via TLRs/PRRs
- This induces:
- ↑ B7 (CD80/86)
- Cytokines that drive differentiation (Signal 3)
- Without those innate cues, antigen presentation is interpreted as “probably self” → tolerance
Translation: The innate immune system decides when the adaptive immune system is allowed to go loud.
Ultra–High-Yield Associations (Rapid Review)
- Signal 1 without Signal 2 → anergy
- B7 (CD80/86) on APC binds CD28 on T cell → activation (↑ IL-2)
- CTLA-4 competes with CD28 and turns off T cells; Ipilimumab blocks CTLA-4
- PD-1/PD-L1 suppresses T cells in tissues/tumors; Pembrolizumab/Nivolumab block PD-1
- CD40L (CD154) on Th cells is required for B-cell class switching; defect → Hyper-IgM syndrome
- Tregs use CTLA-4 as part of suppression (conceptual link to tolerance)
First Aid Cross-References (by topic area)
(Exact page numbers vary by edition—use these as “where to look” anchors.)
- T-cell activation & anergy: Immunology section on T-cell signaling (CD28/B7) and anergy
- Costimulatory molecules: tables/figures listing B7–CD28, CD40–CD40L, CTLA-4, PD-1
- Hyper-IgM syndrome: Immunodeficiencies (class switching defects; CD40L)
- Checkpoint inhibitors: Pharmacology—anticancer drugs/immunotherapy; adverse autoimmune toxicities
- T-helper subsets: Th1/Th2/Th17/Tfh cytokines (connect Signal 3 to function)
Quick Self-Check (Mini Vignettes)
-
Naive T cells exposed to antigen by resting APCs become unresponsive.
→ Missing B7–CD28 costimulation → anergy -
Boy with recurrent infections, high IgM, low IgG/IgA/IgE, absent germinal centers.
→ X-linked Hyper-IgM from CD40L defect -
Cancer patient on checkpoint therapy develops severe diarrhea and abdominal pain.
→ Immune-mediated colitis from CTLA-4 (ipilimumab) or PD-1 blockade -
Tumor biopsy shows high PD-L1 expression.
→ Tumor immune evasion; treat with anti–PD-1/PD-L1
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
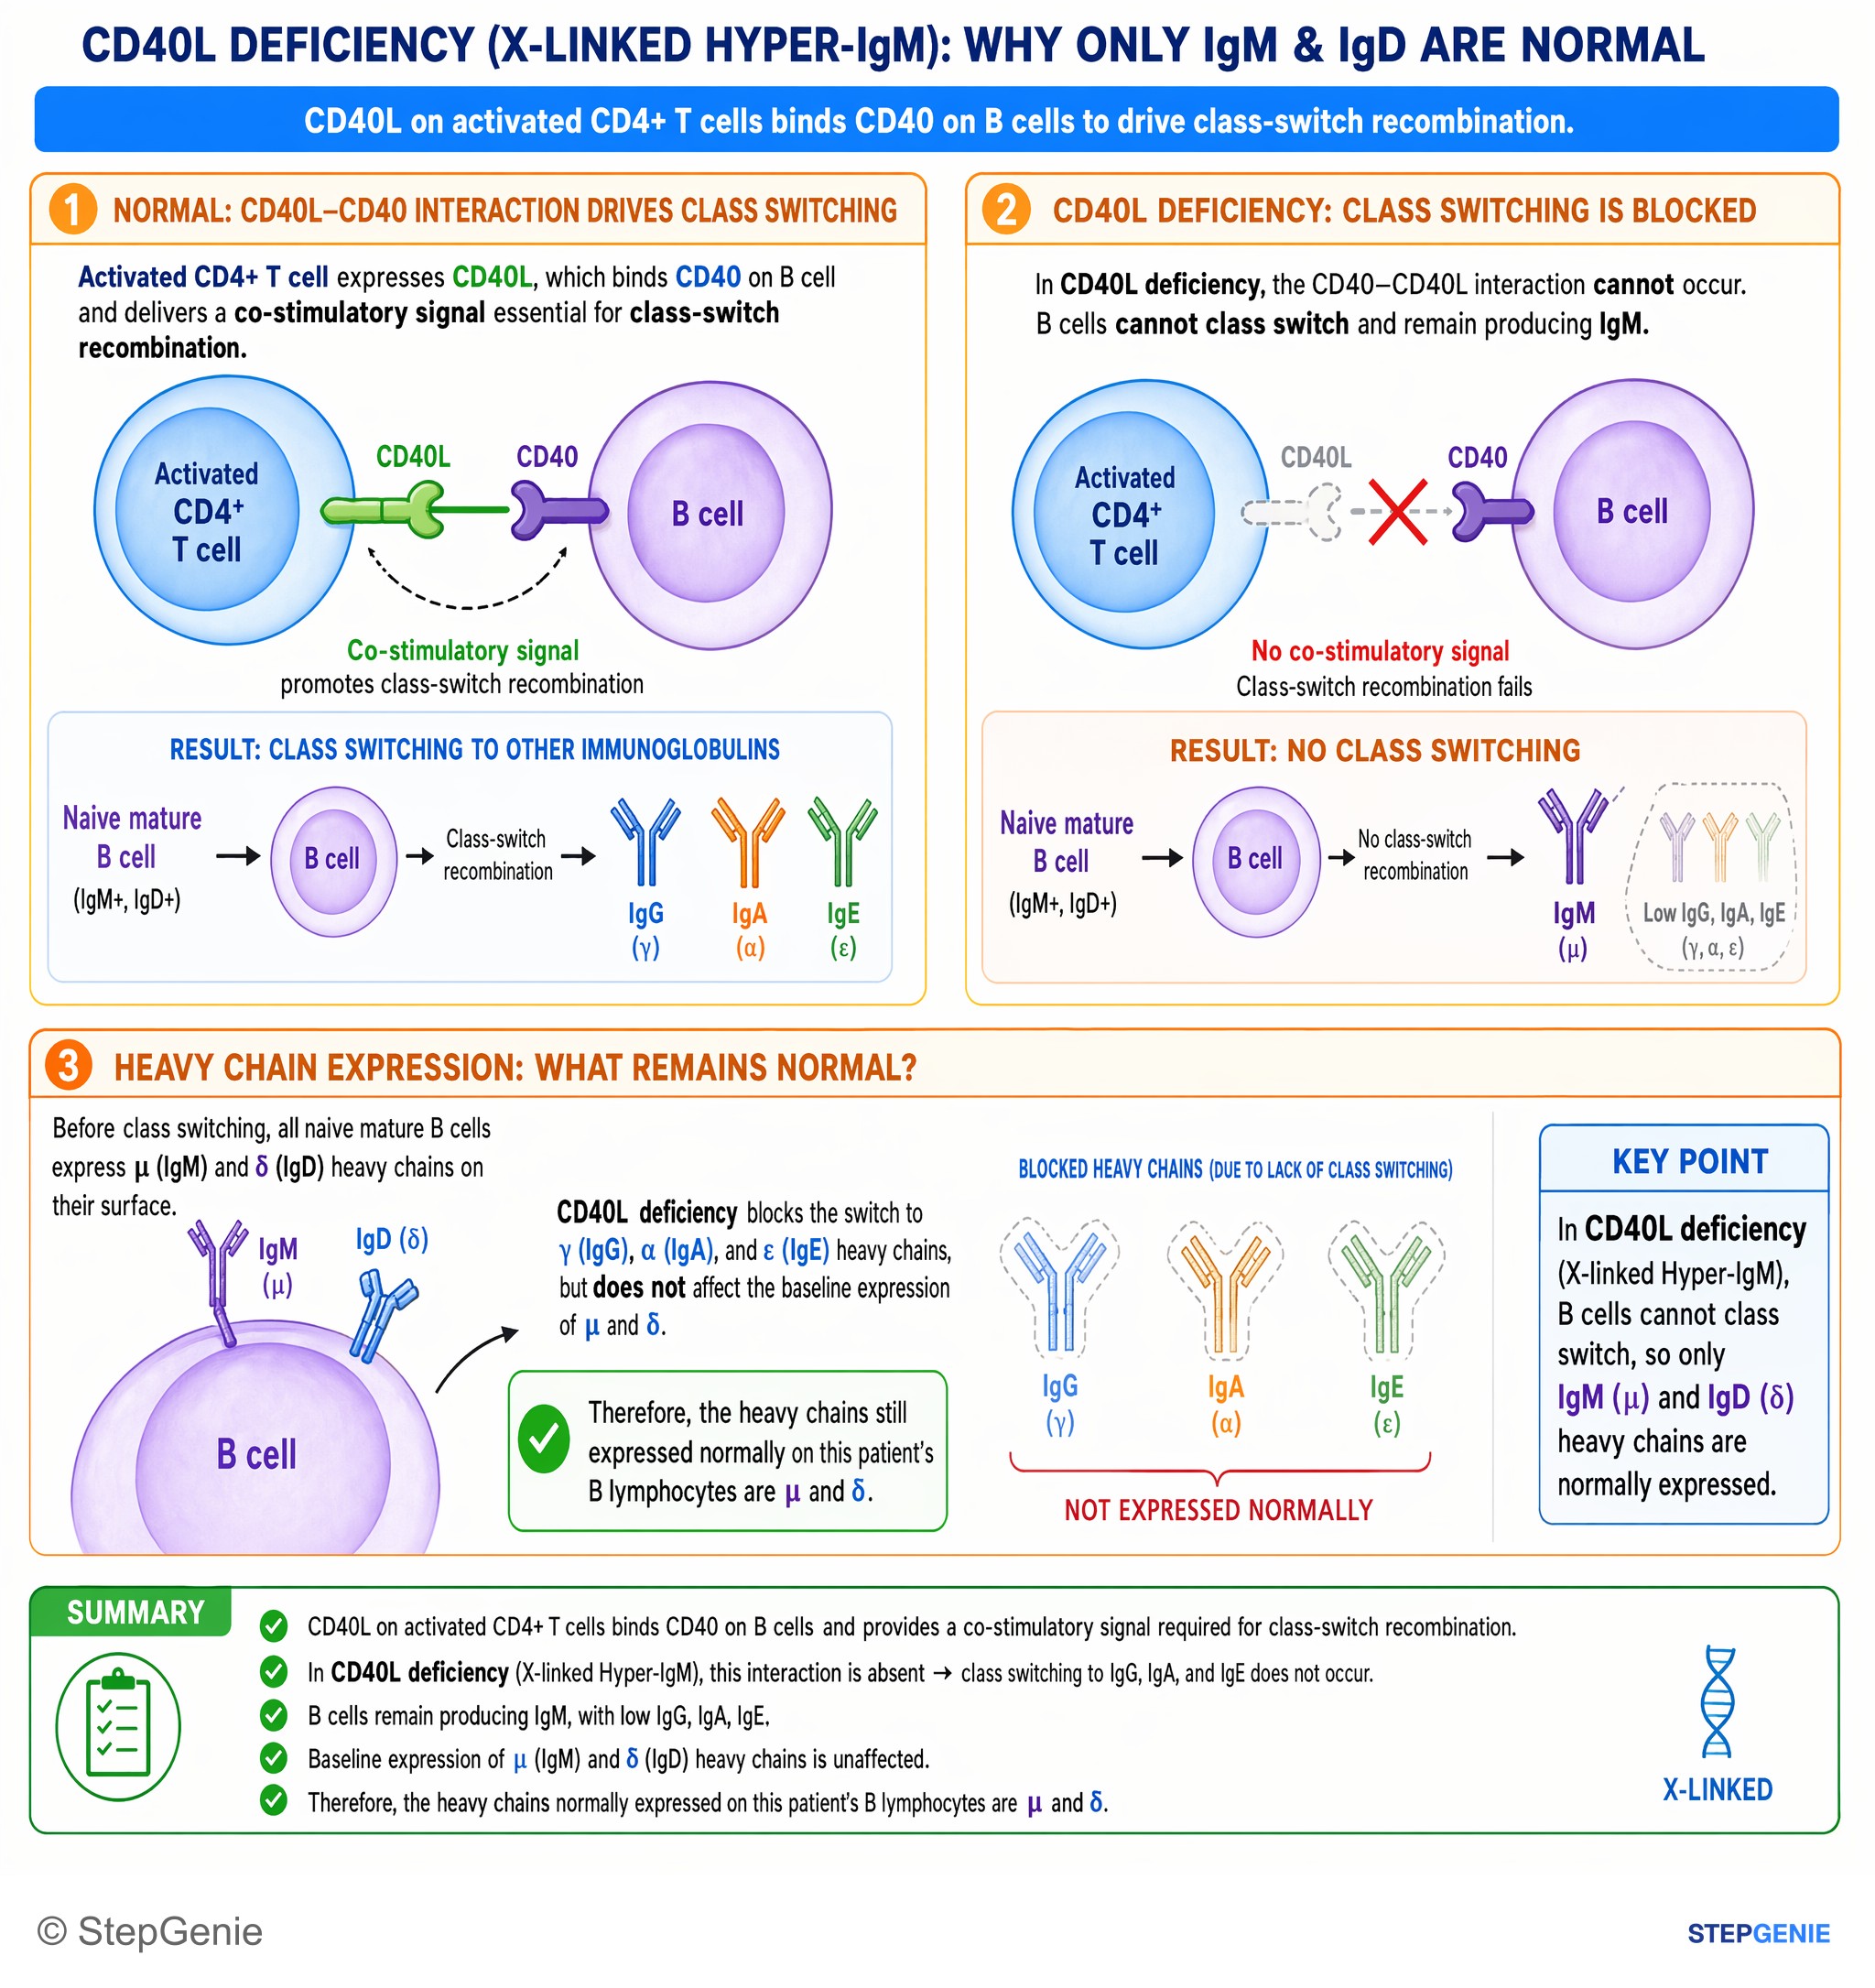
X-linked Hyper-IgM (CD40L deficiency): B cells cannot class switch, so only IgM (μ) and IgD (δ) heavy chains are normally expressed.
USMLE Step 1Frequently Asked Questions
Why does a naive T cell become anergic if it recognizes antigen without costimulation?
Because Signal 1 alone is not enough to fully activate a naive T cell. A naive T cell can recognize peptide on MHC through the TCR, but without the second signal from costimulatory molecules such as B7 binding CD28, it becomes functionally unresponsive or may be deleted. This is a key mechanism of peripheral tolerance that helps prevent accidental immune attacks on self.
How do you tell B7 binding CD28 from B7 binding CTLA-4 on Step 1?
B7 binding CD28 activates T cells, while B7 binding CTLA-4 inhibits them. APCs express B7, and when it engages CD28 on T cells it promotes IL-2 production, clonal expansion, and survival. CTLA-4 is upregulated after T-cell activation and is constitutively expressed on Tregs, binds B7 with higher affinity than CD28, and acts as a braking signal during the priming phase in lymph nodes.
What does CD40L deficiency cause, and why does it lead to high IgM?
CD40L deficiency causes X-linked hyper-IgM syndrome because T helper cells cannot provide the CD40-mediated help B cells need for class switching. Without this interaction, patients have increased IgM with decreased IgG, IgA, and IgE, absent germinal centers, and susceptibility to opportunistic infections such as Pneumocystis, Cryptosporidium, and CMV. CD40 signaling also supports affinity maturation and macrophage activation.
How do tumors use PD-L1 to evade the immune system?
Tumors can evade immune attack by expressing PD-L1, which binds PD-1 on T cells and inhibits their function in peripheral tissues. This pathway normally serves as a brake to reduce tissue damage and is important in chronically stimulated or exhausted T cells. On exams, a tumor expressing PD-L1 points to immune evasion that can be countered by blocking PD-1 or PD-L1.
What side effects should you think of with CTLA-4 or PD-1 checkpoint inhibitors?
Think autoimmune-like toxicities such as colitis, hepatitis, dermatitis, pneumonitis, and endocrinopathies. CTLA-4 inhibition with ipilimumab and PD-1 or PD-L1 blockade can boost antitumor T-cell responses, but removing these inhibitory brakes also increases the risk of immune-related adverse events. Board-style clues often include severe diarrhea, colitis, elevated liver tests, cough, dyspnea, hypophysitis, or thyroiditis after immunotherapy.