Turner syndrome is the complete or partial loss of the second sex chromosome in a phenotypic female, and its classic karyotype is 45,X. It causes short stature (one copy of SHOX), primary ovarian insufficiency with high FSH and LH, left-sided heart lesions (bicuspid aortic valve, coarctation) and lymphatic stigmata such as a webbed neck. Only 40–50% of patients are pure 45,X; the rest are mosaics (45,X/46,XX in 15–25%, a Y-containing line in 10–12%) or carry a structurally abnormal X, most often isochromosome Xq (about 15%). When a vignette pairs Turner-like features with a normal 46,XX karyotype, the exam wants Noonan syndrome if the clues are pulmonary stenosis, normal puberty or an affected parent (the same picture in a boy with a normal 46,XY karyotype is also Noonan), and mosaicism missed on a blood karyotype if the clues are ovarian failure and left-sided heart disease.
Turner syndrome at a glance
| Feature | High-yield fact |
|---|---|
| Definition (2024 guideline) | Phenotypic female with one intact X, complete or partial absence of the second sex chromosome, and at least one typical feature |
| Frequency | About 1 in 2,000–2,500 live-born girls; about 99% of 45,X conceptions miscarry |
| Origin | Random, almost never inherited; in about 80% of 45,X cases the paternal sex chromosome is the one lost |
| Hormones | High FSH and LH, low estradiol (hypergonadotropic hypogonadism) |
| Heart | Congenital heart disease in about half: bicuspid aortic valve in more than 25%, coarctation in 4–15% |
| Aorta | Dissection at about 164 vs 6 per 100,000 person-years (general population), mean age 30–35 |
| Kidney | Horseshoe kidney and duplicated collecting system, each in 15–20% |
| Diagnosis | Karyotype of at least 30 cells, which detects about 10% mosaicism with 95% confidence |
| Treatment | Growth hormone from age 2 if growth falters; low-dose estradiol at 11–12 years if FSH is high |
The vignette
A 15-year-old girl is brought to the physician because she has never had a menstrual period. She has always been the shortest in her class, and her height is below the 3rd percentile. She had frequent ear infections as a young child. Blood pressure in the right arm is 142/86 mm Hg, and the femoral pulses are weak and delayed. Examination shows a webbed neck with a low posterior hairline, a broad chest with widely spaced nipples, and an increased carrying angle at both elbows. Breast development is Tanner stage 1 and pubic hair is Tanner stage 2. Pelvic ultrasound shows a small uterus; the ovaries are not visualized. Serum FSH and LH are elevated, and estradiol is low.
Which of the following karyotypes is most likely?
- A. 45,X
- B. 46,XX
- C. 46,XY
- D. 45,X/46,XY
- E. 47,XXX
- F. 47,XXY
Correct answer: A. 45,X
At 15 with no menses and no breast development, she has primary amenorrhea (work-up in the amenorrhea flowchart), and every finding traces back to a missing second sex chromosome.
| Finding in the stem | What it means | Why 45,X explains it |
|---|---|---|
| Short since early childhood | Growth failure; untreated adults average about 20 cm below peers | One copy of SHOX, a pseudoautosomal gene with a working copy on each sex chromosome, is missing |
| No breasts, high FSH and LH, low estradiol | Hypergonadotropic hypogonadism | Oocytes are lost early and the ovaries become streaks, so estrogen feedback on the pituitary is lost |
| Small uterus, ovaries not seen | Müllerian structures are present | No testes means no anti-Müllerian hormone; the uterus is small because it has never seen estrogen |
| Tanner 2 pubic hair | Adrenarche has occurred | Pubic hair in girls depends mainly on adrenal androgens |
| Arm hypertension, weak and delayed femoral pulses | Coarctation of the aorta | At least 13% of newborn girls with coarctation have Turner syndrome |
| Webbed neck, low hairline | Remnant of fetal lymphedema (cystic hygroma) | A webbed neck carries 3.3 times the odds of coarctation or a bicuspid valve |
| Childhood ear infections | Recurrent otitis media | Hearing loss, conductive and sensorineural, affects 36–84% of patients |
Why not a mosaic? This is the full classic phenotype; 45,X/46,XX mosaics are milder, with fewer left-sided heart defects and more spontaneous puberty. More on the lesion in coarctation of the aorta for Step 1.
Why every other answer choice is wrong
B. 46,XX. A normal female karyotype cannot explain streak ovaries, SHOX-type short stature and coarctation together. Other 46,XX causes of amenorrhea look different: Müllerian agenesis (MRKH) has an absent uterus with normal breasts, pubic hair and ovaries; Kallmann syndrome has low FSH and LH with anosmia; and an FMR1 premutation (55–200 CGG repeats) causes ovarian insufficiency (irregular or absent periods with high FSH before 40) in about a quarter of female carriers, without Turner stigmata. If the lab truly reports 46,XX in a girl like this one, suspect missed mosaicism (decision table below).
C. 46,XY. This is the karyotype of complete androgen insensitivity syndrome (CAIS, X-linked AR variants). Testosterone is aromatized to estradiol, so breasts develop; androgen receptors do not respond, so pubic and axillary hair is sparse; and testicular anti-Müllerian hormone means no uterus or cervix, with a short blind-ending vagina. LH and testosterone are often elevated. A 46,XY girl with a uterus and streak gonads has Swyer syndrome (complete gonadal dysgenesis; SRY variants in about 15%): Turner's high-FSH profile without Turner stigmata, and the streak gonads are usually removed because of cancer risk.
D. 45,X/46,XY. This is still Turner syndrome when the phenotype is female, and 10–12% of patients carry Y material. The phenotype ranges from a typical Turner girl through ambiguous genitalia (mixed gonadal dysgenesis) to a male. The clue is virilization, and the stake is gonadoblastoma, which can become a dysgerminoma. The 2024 guideline recommends PCR (more sensitive than FISH) for Y material in a 45,X girl with virilization, not in every 45,X girl. Reported gonadoblastoma rates range from 0% to 100% and malignant transformation from 1% to 22%, usually after the second decade, so gonadectomy, the classic exam answer, is now an individualized decision on whether and when. This patient shows no androgen excess.
E. 47,XXX. Trisomy X affects about 1 in 1,000 girls, and its most common feature is tall stature. Most have normal puberty and fertility, though some develop ovarian insufficiency, and learning disabilities and speech delays are more common.
F. 47,XXY. Klinefelter syndrome is primary gonadal failure in a male: tall stature, small testes, low testosterone with high FSH and LH, gynecomastia and infertility. See the Klinefelter syndrome cheat sheet.
Barr body shortcut: every X beyond the first is inactivated as a Barr body, so 45,X has none, 46,XX and 47,XXY have one, and 47,XXX has two.
Turner karyotypes and what each one changes
| Karyotype | Share | What to know |
|---|---|---|
| 45,X | 40–50% | Usually nondisjunction in a parent's egg or sperm; most comorbidities and highest mortality |
| 45,X/46,XX | 15–25% | Cell-division error after fertilization; milder, with more spontaneous puberty, menarche and pregnancy |
| 46,X,i(Xq), isochromosome of the long arm | About 15% | 46 chromosomes but no second Xp, so no second SHOX; intermediate phenotype, less coarctation; loss of Xp is linked to autoimmunity |
| 45,X/46,XY | 10–12% | Virilization and gonadoblastoma risk; least autoimmune thyroid disease |
| 45,X/47,XXX | About 3% | Milder physical and cardiac picture; neurodevelopmental concerns remain |
| 45,X/46,X,r(X) | Rare | A ring X that has lost XIST gives a more severe cognitive phenotype |
Not Turner syndrome (2024 guideline): a small distal Xp22.33 deletion that removes SHOX (Léri–Weill dyschondrosteosis: short stature and skeletal changes, without the heart, cognitive or ovarian risks); an Xq deletion distal to Xq24 (ovarian insufficiency without short stature); and fewer than 5% 45,X cells in a woman over 50 (age-related X loss). For how a second cell line changes severity, see mosaicism compared.
How the diagnosis is made
- Who gets a karyotype: fetal cystic hygroma or hydrops, unexplained short stature, a left-sided outflow lesion other than a bicuspid valve (such as coarctation), delayed or stalled puberty, secondary amenorrhea, infertility, or typical facial and neck features. Two or more softer clues, such as a renal anomaly, Madelung deformity, multiple nevi, dysplastic nails, another heart defect, or hearing loss before 40 with short stature, also qualify. An isolated bicuspid valve (1–2% of everyone) does not.
- The test: a karyotype counting at least 30 metaphases. FISH, microarray or PCR give rapid answers (prenatal, newborn) but need karyotype confirmation, and microarray can miss 45,X mosaicism below about 10%.
- 46,XX but strong suspicion: count more cells, then karyotype or FISH a second tissue: skin, buccal cells or urine.
- Prenatal: increased nuchal translucency, a frank cystic hygroma, hydrops, left-sided heart lesions and low PAPP-A raise suspicion. Cell-free DNA screening is 98.8% sensitive and 99.4% specific, but its positive predictive value averages only about 25%, because of confined placental mosaicism, maternal mosaicism and vanished twins. A high-risk result needs counseling, a detailed ultrasound and an offer of CVS or amniocentesis (plus a maternal karyotype if the ultrasound is normal and fetal testing is normal or declined). Every prenatal diagnosis is confirmed by a postnatal blood karyotype.
- Gonadotropins are biphasic: high in infancy, often normal in mid-childhood and rising again near puberty, so a normal FSH at age 7 does not exclude Turner syndrome. LH, FSH and AMH are checked yearly from 8–9 to 11–12 years.
Findings by system and what to screen for
Surveillance follows the 2024 international guideline (Gravholt et al.) and applies to every karyotype.
| System | Finding | Screening or treatment |
|---|---|---|
| Growth | Untreated adult height 138–147 cm; cubitus valgus, Madelung deformity, short 4th metacarpals | Growth hormone (FDA-approved for Turner syndrome) from age 2 if growth falters, 45–50 µg/kg/day, until bone age ≥14 or growth below 2 cm/year: about 5–8 cm gained. Oxandrolone is no longer recommended (US approval withdrawn in 2023) |
| Ovaries | Ovarian insufficiency; over a third show some spontaneous puberty, about 1 in 5 reach menarche, about 10% conceive spontaneously | Low-dose 17β-estradiol, transdermal preferred, at 11–12 years if FSH is high twice, reaching adult dose over 2–4 years; cyclic progesterone after breakthrough bleeding (usually after 18–24 months); continue to about 50–55; early fertility counseling |
| Heart | Congenital heart disease in about half: bicuspid aortic valve, coarctation, partial anomalous pulmonary venous return (4–16%), elongated transverse arch | Echocardiogram at diagnosis (day 2–3 in newborns); cardiac MRI within 12 months of diagnosis in adolescents and adults (in young children, once possible without anesthesia); ECG; if normal, echo at 9–11 years and every 5–10 years in adults |
| Aorta and blood pressure | Lifetime thoracic aortic aneurysm about 25%; hypertension in 20–40% of children and up to 60% of adults | Index aortic diameter to body size (in adults, an aortic size index above 2.0 cm/m² is dilated and above 2.5 high risk; under 15, a Turner-specific Z-score); yearly blood pressure, ideally ambulatory; beta-blocker and/or ARB if dilated |
| Kidney | Congenital anomalies in 18–60% | Renal ultrasound at diagnosis |
| Ears | Recurrent otitis media in 24–48%; sensorineural loss in about a third | Audiometry every 2–3 years in childhood, every 5 years in adults |
| Autoimmune | Hashimoto thyroiditis (most common), celiac disease (about 1 in 22), inflammatory bowel disease | TSH every 1–2 years from age 2; tTG-IgA with total IgA from age 2, then every 2–5 years |
| Liver and metabolism | Raised liver enzymes in 40–80%; obesity; type 1 and type 2 diabetes; dyslipidemia | ALT every 1–2 years from age 10; HbA1c or fasting glucose every 1–2 years from age 10–12; lipids every 3 years |
| Lymphatics | Lymphedema in 12–27%, often at birth and improving by age 2; webbed neck in 18–25% | Compression garments, lymphatic massage |
| Bone | Low bone density, scoliosis | DXA after growth ends but before 21, then every 5–10 years |
| Brain | About 90% average intelligence; verbal strengths with visuospatial, math, attention and executive weaknesses; ADHD in 7–25% | Neurocognitive and psychosocial screening across the lifespan |
Related screening reviews: thyroid function tests and this celiac disease breakdown.
Aortic dissection and pregnancy
- The risk: dissections strike young (mean age 30–35), 70% start in the ascending aorta (type A; see Stanford A vs B), and they occur at smaller diameters than in other genetic aortopathies. Risk factors: dilation, bicuspid valve, coarctation, hypertension and growth of more than 3 mm a year.
- Before pregnancy or assisted reproduction: cardiac MRI or CT within the previous 2 years. With severe dilation (aortic size index above 2.5 cm/m²), especially plus another risk factor, the guideline suggests avoiding pregnancy.
- During pregnancy: blood pressure below 130/80 mm Hg in the peripartum period; an echocardiogram around 20 weeks if risk is low, and at least every 12 weeks with dilation or another risk factor.
- After delivery: the risk persists, so postpartum imaging and cardiology review are recommended.
- Obstetric risks: miscarriage after spontaneous conception in 29–48% (vs 15%), preeclampsia in 6.3–11% (vs 3%), and higher odds of preterm and small-for-gestational-age babies.
Turner features with a normal 46,XX karyotype: Noonan or mosaicism?
Read what the question asks. "What is the diagnosis?" with a right-sided heart lesion, normal puberty or an affected parent (or the same picture in a boy, whose karyotype is 46,XY): Noonan syndrome. "What explains the discrepancy?" in a girl with true Turner findings (high FSH, coarctation or a bicuspid valve, horseshoe kidney): mosaicism, an early embryonic cell-division error that left a 45,X line sparse in blood lymphocytes but present in other tissues.
| Clue in the stem | Best answer | Next step or reason |
|---|---|---|
| Pulmonary valve stenosis, hypertrophic cardiomyopathy, normal puberty, a boy, an affected parent | Noonan syndrome | Autosomal dominant RAS–MAPK disorder; karyotype normal |
| High FSH, left-sided heart lesion or horseshoe kidney, but "46,XX in blood" | 45,X/46,XX mosaicism | Count at least 30 cells, then karyotype or FISH on buccal cells, skin or urine |
| 46,X,i(Xq), 46,X,r(X) or 46,X,del(Xp) | Turner syndrome | 46 chromosomes, but part of an X is missing |
| Short stature and Madelung deformity, normal puberty and heart | SHOX deficiency (Léri–Weill) | Loss of one SHOX copy at Xp22.33; not Turner syndrome |
| Ovarian insufficiency only, normal height, 46,XX | 46,XX primary ovarian insufficiency | For example an Xq deletion distal to Xq24 or an FMR1 premutation |
Turner vs Noonan
| Feature | Turner syndrome | Noonan syndrome |
|---|---|---|
| Karyotype | 45,X, mosaic or structurally abnormal X | Normal (46,XX or 46,XY) |
| Genetics | Sporadic loss of all or part of a sex chromosome | Autosomal dominant; PTPN11 in about 50%, SOS1 in about 15% |
| Who | Phenotypic females | Both sexes; about 1 in 1,000–2,500 births |
| Heart | Bicuspid aortic valve, coarctation; aortic dilation and dissection | Pulmonary valve stenosis (50–60%); hypertrophic cardiomyopathy (about 20%) |
| Gonads | Ovarian insufficiency with high FSH | Girls: usually normal puberty and fertility; boys: cryptorchidism in about two-thirds |
| Stature | Short in nearly all | Short in about half |
| Intellect | About 90% average; visuospatial and math weaknesses | Intellectual disability, usually mild, in 10–20% |
| Other clues | Horseshoe kidney, hearing loss, hypothyroidism, celiac disease | Bleeding tendency, lymphedema, higher leukemia risk |
| Growth hormone | FDA-approved indication | FDA-approved indication |
The two murmurs are compared in the heart murmur chart.
Primary amenorrhea look-alikes
| Condition | Karyotype | Uterus | Breasts | Gonads and hormones | Key clue |
|---|---|---|---|---|---|
| Turner syndrome | 45,X or variant | Present, small | Absent | Streak ovaries; high FSH and LH | Short stature, webbed neck, coarctation |
| Swyer syndrome | 46,XY | Present | Absent | Streak gonads; high FSH | No Turner stigmata; tumor risk |
| Complete androgen insensitivity | 46,XY | Absent | Present | Testes; LH and testosterone often high | Scant pubic and axillary hair |
| Müllerian agenesis (MRKH) | 46,XX | Absent or rudimentary | Present | Normal ovaries and hormones | Normal pubic hair |
| Kallmann syndrome | 46,XX | Present | Absent | Low FSH and LH | Anosmia |
Exam traps
- A uterus is present in Turner and Swyer syndromes and absent in CAIS and Müllerian agenesis.
- Breasts track estrogen; pubic hair tracks adrenal androgens: Tanner 1 breasts with Tanner 2 hair fits Turner; full breasts with scant hair fits CAIS.
- Coarctation in a girl, or unexplained short stature, warrants a karyotype; an isolated bicuspid valve does not.
- Low FSH and LH point to the hypothalamus or pituitary, not the ovary.
Two more practice cases
Case 1. A 12-year-old girl at the 2nd percentile for height has a bicuspid aortic valve, a horseshoe kidney and an FSH of 70 mIU/mL. A blood karyotype of 20 cells is 46,XX. What is the next step?
Answer: Count at least 30 cells and, if still 46,XX, karyotype or FISH a second tissue (buccal cells, skin or urine). Together her findings are typical of Turner syndrome, and 20 cells cannot exclude low-level 45,X/46,XX mosaicism.
Case 2. A 13-year-old girl has short stature, a webbed neck, Tanner 3 breasts and a systolic ejection murmur at the left upper sternal border. Echocardiography shows pulmonary valve stenosis, her karyotype is 46,XX, and her short father had heart surgery as a child. What is the diagnosis?
Answer: Noonan syndrome, most often from a PTPN11 variant. A right-sided lesion, spontaneous puberty, a normal karyotype and an affected father all argue against Turner syndrome.
Key takeaways
- 45,X = short stature + ovarian insufficiency (high FSH and LH) + left-sided heart lesions + renal anomalies; only 40–50% of patients are pure 45,X.
- Diagnose with a 30-cell karyotype; if blood is 46,XX but suspicion stays high, test a second tissue; confirm any prenatal diagnosis with a postnatal blood karyotype.
- Turner features with a normal karyotype: Noonan syndrome on exams; missed mosaicism when ovarian failure and left-sided heart disease are present.
- Y material (10–12%) means gonadoblastoma risk: gonadectomy is the classic exam answer, and the 2024 guideline makes it an individualized decision.
- Lifelong surveillance covers the aorta (including around pregnancy), blood pressure, thyroid, celiac disease, hearing, liver and glucose. Growth hormone from age 2; estrogen at 11–12 years.
Sources
- Gravholt CH, et al. Clinical practice guidelines for the care of girls and women with Turner syndrome — European Journal of Endocrinology (2024)
- Turner Syndrome — StatPearls, NCBI Bookshelf (2026)
- Turner Syndrome — Merck Manual Professional Edition (2025)
- Turner syndrome — MedlinePlus Genetics (2023)
- Noonan syndrome — Orphanet (2020)
- Noonan syndrome — MedlinePlus Genetics (2018)
- Complete androgen insensitivity syndrome — NIH Genetic and Rare Diseases Information Center (2026)
- Swyer syndrome — MedlinePlus Genetics (2022)
- Trisomy X — MedlinePlus Genetics (2026)
- Klinefelter syndrome — MedlinePlus Genetics (2023)
- Mayer-Rokitansky-Küster-Hauser syndrome — MedlinePlus Genetics (2025)
- Fragile X-associated primary ovarian insufficiency — MedlinePlus Genetics (2020)
- Amenorrhea — Merck Manual Professional Edition (2026)
- NORDITROPIN (somatropin) prescribing information — DailyMed (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
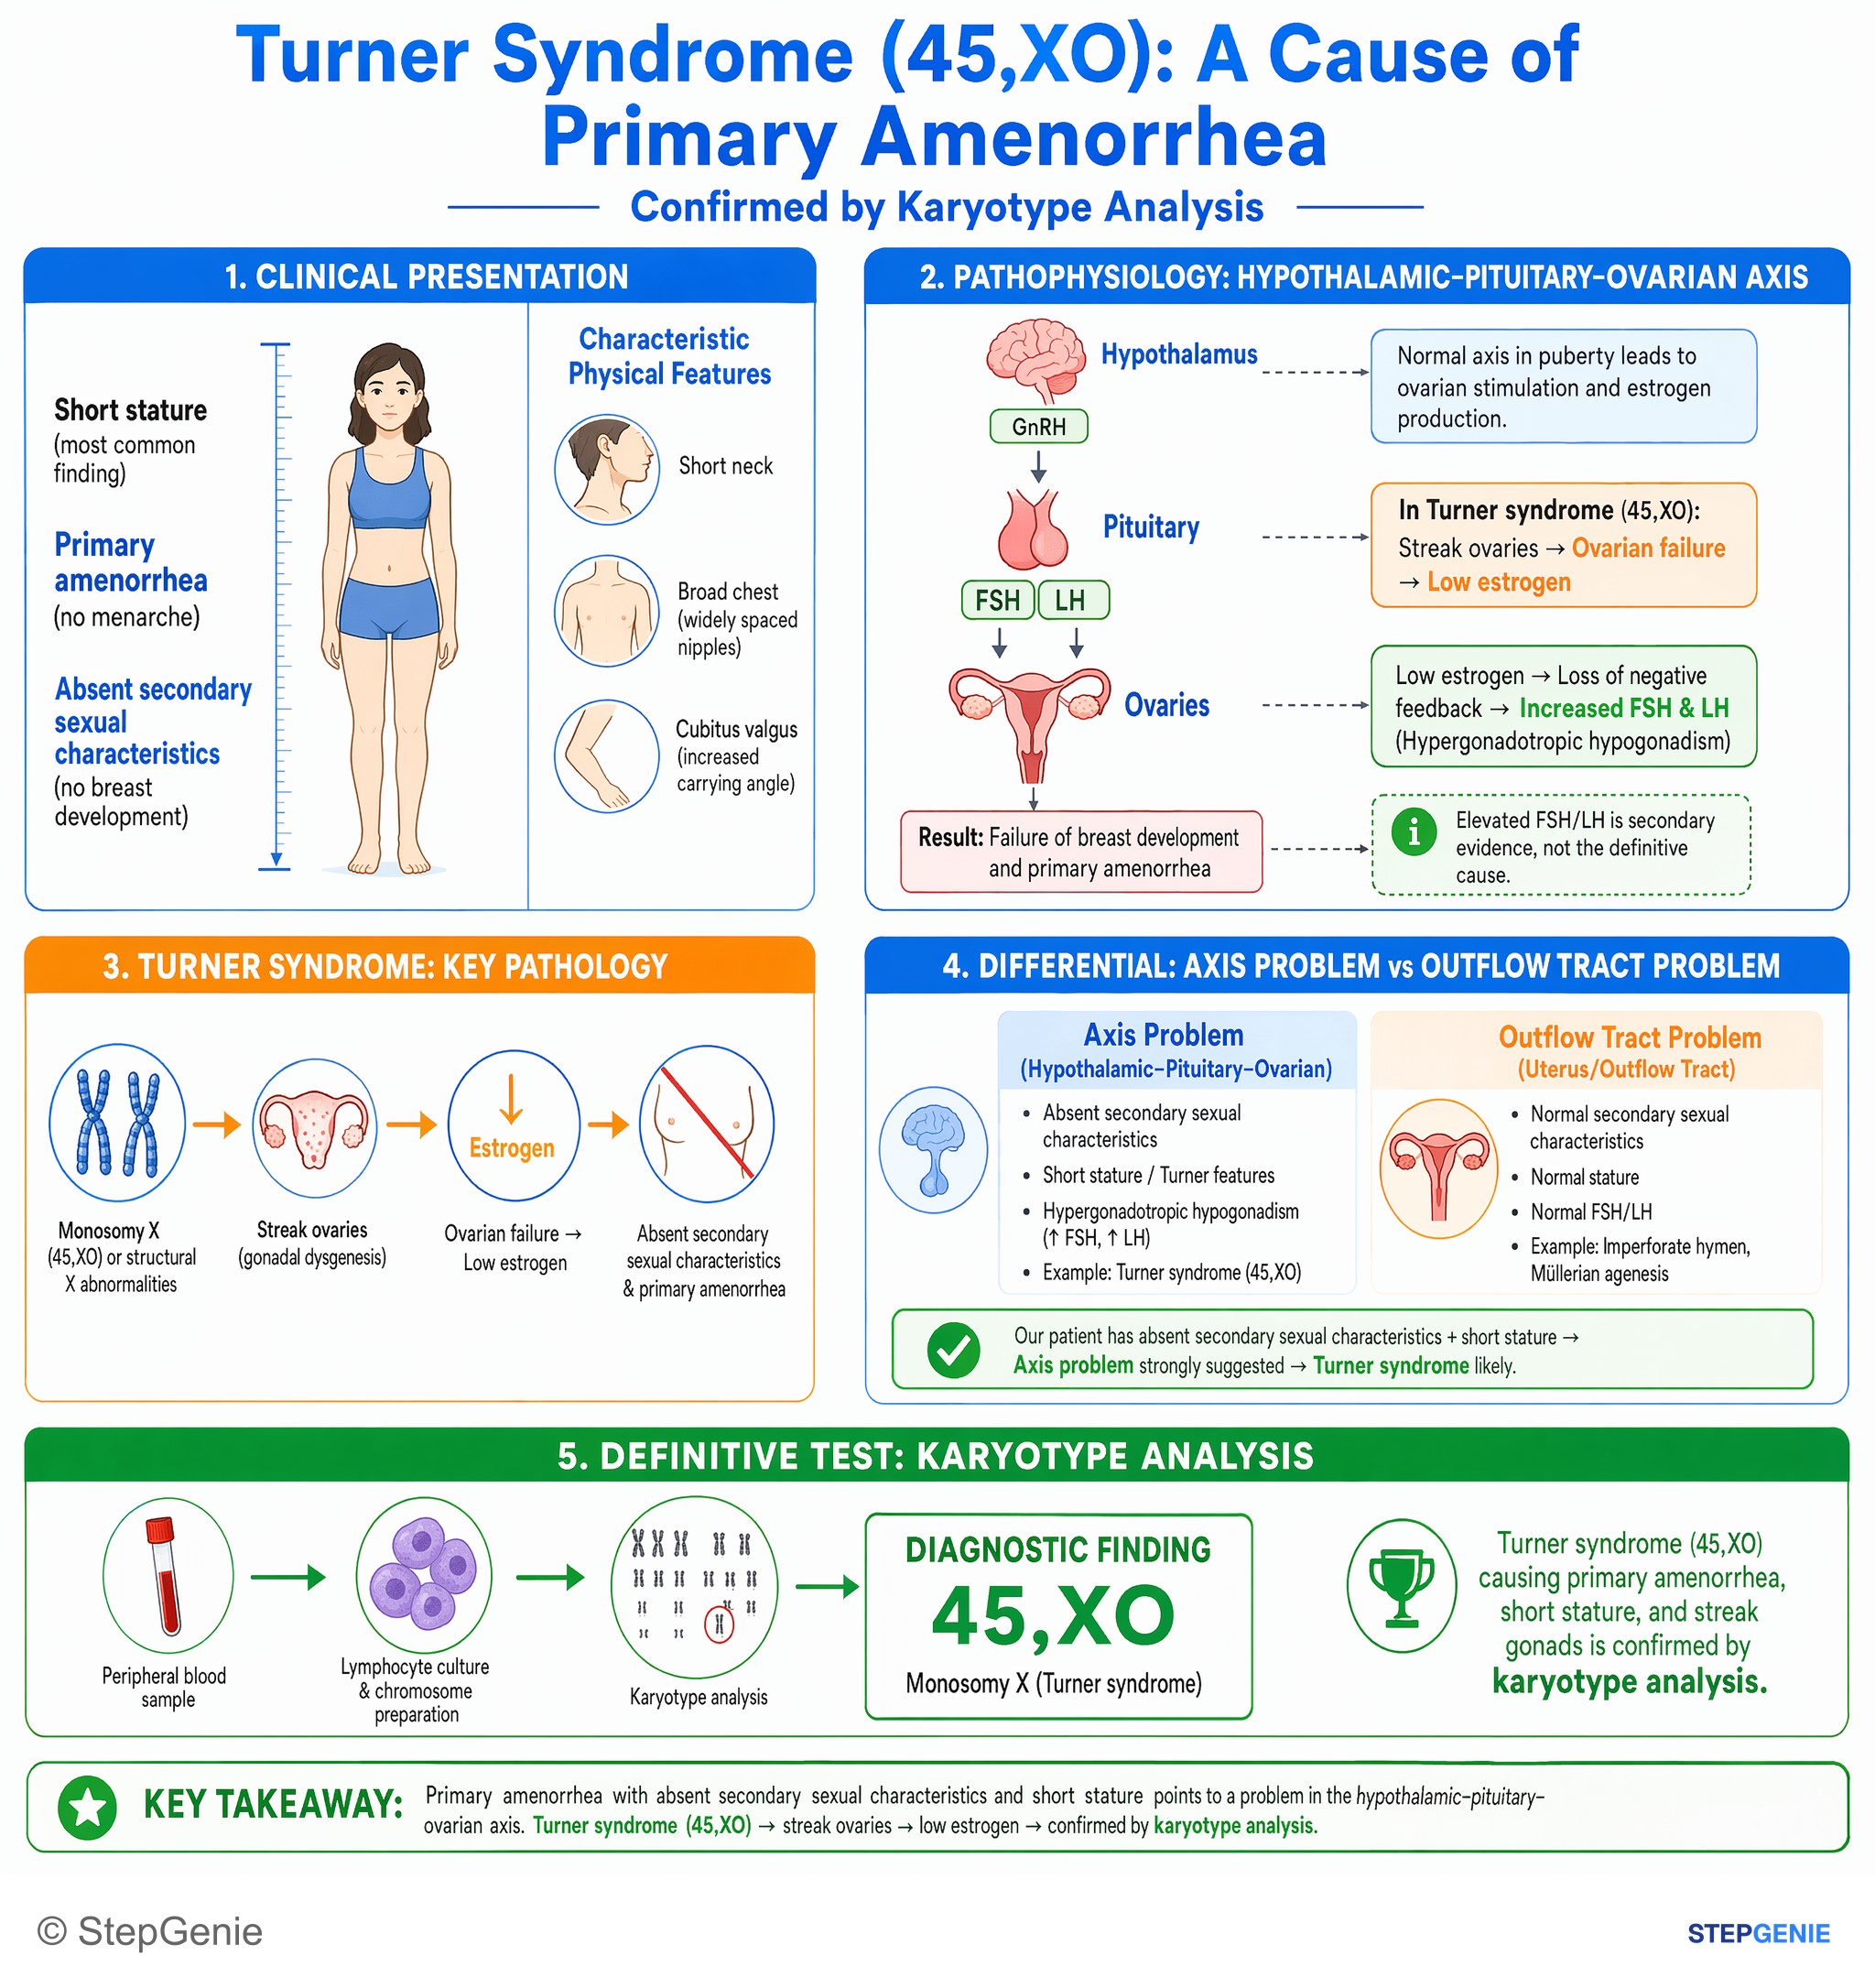
Turner syndrome (45,XO) causing primary amenorrhea, short stature, and streak gonads is confirmed by karyotype analysis.
USMLE Step 2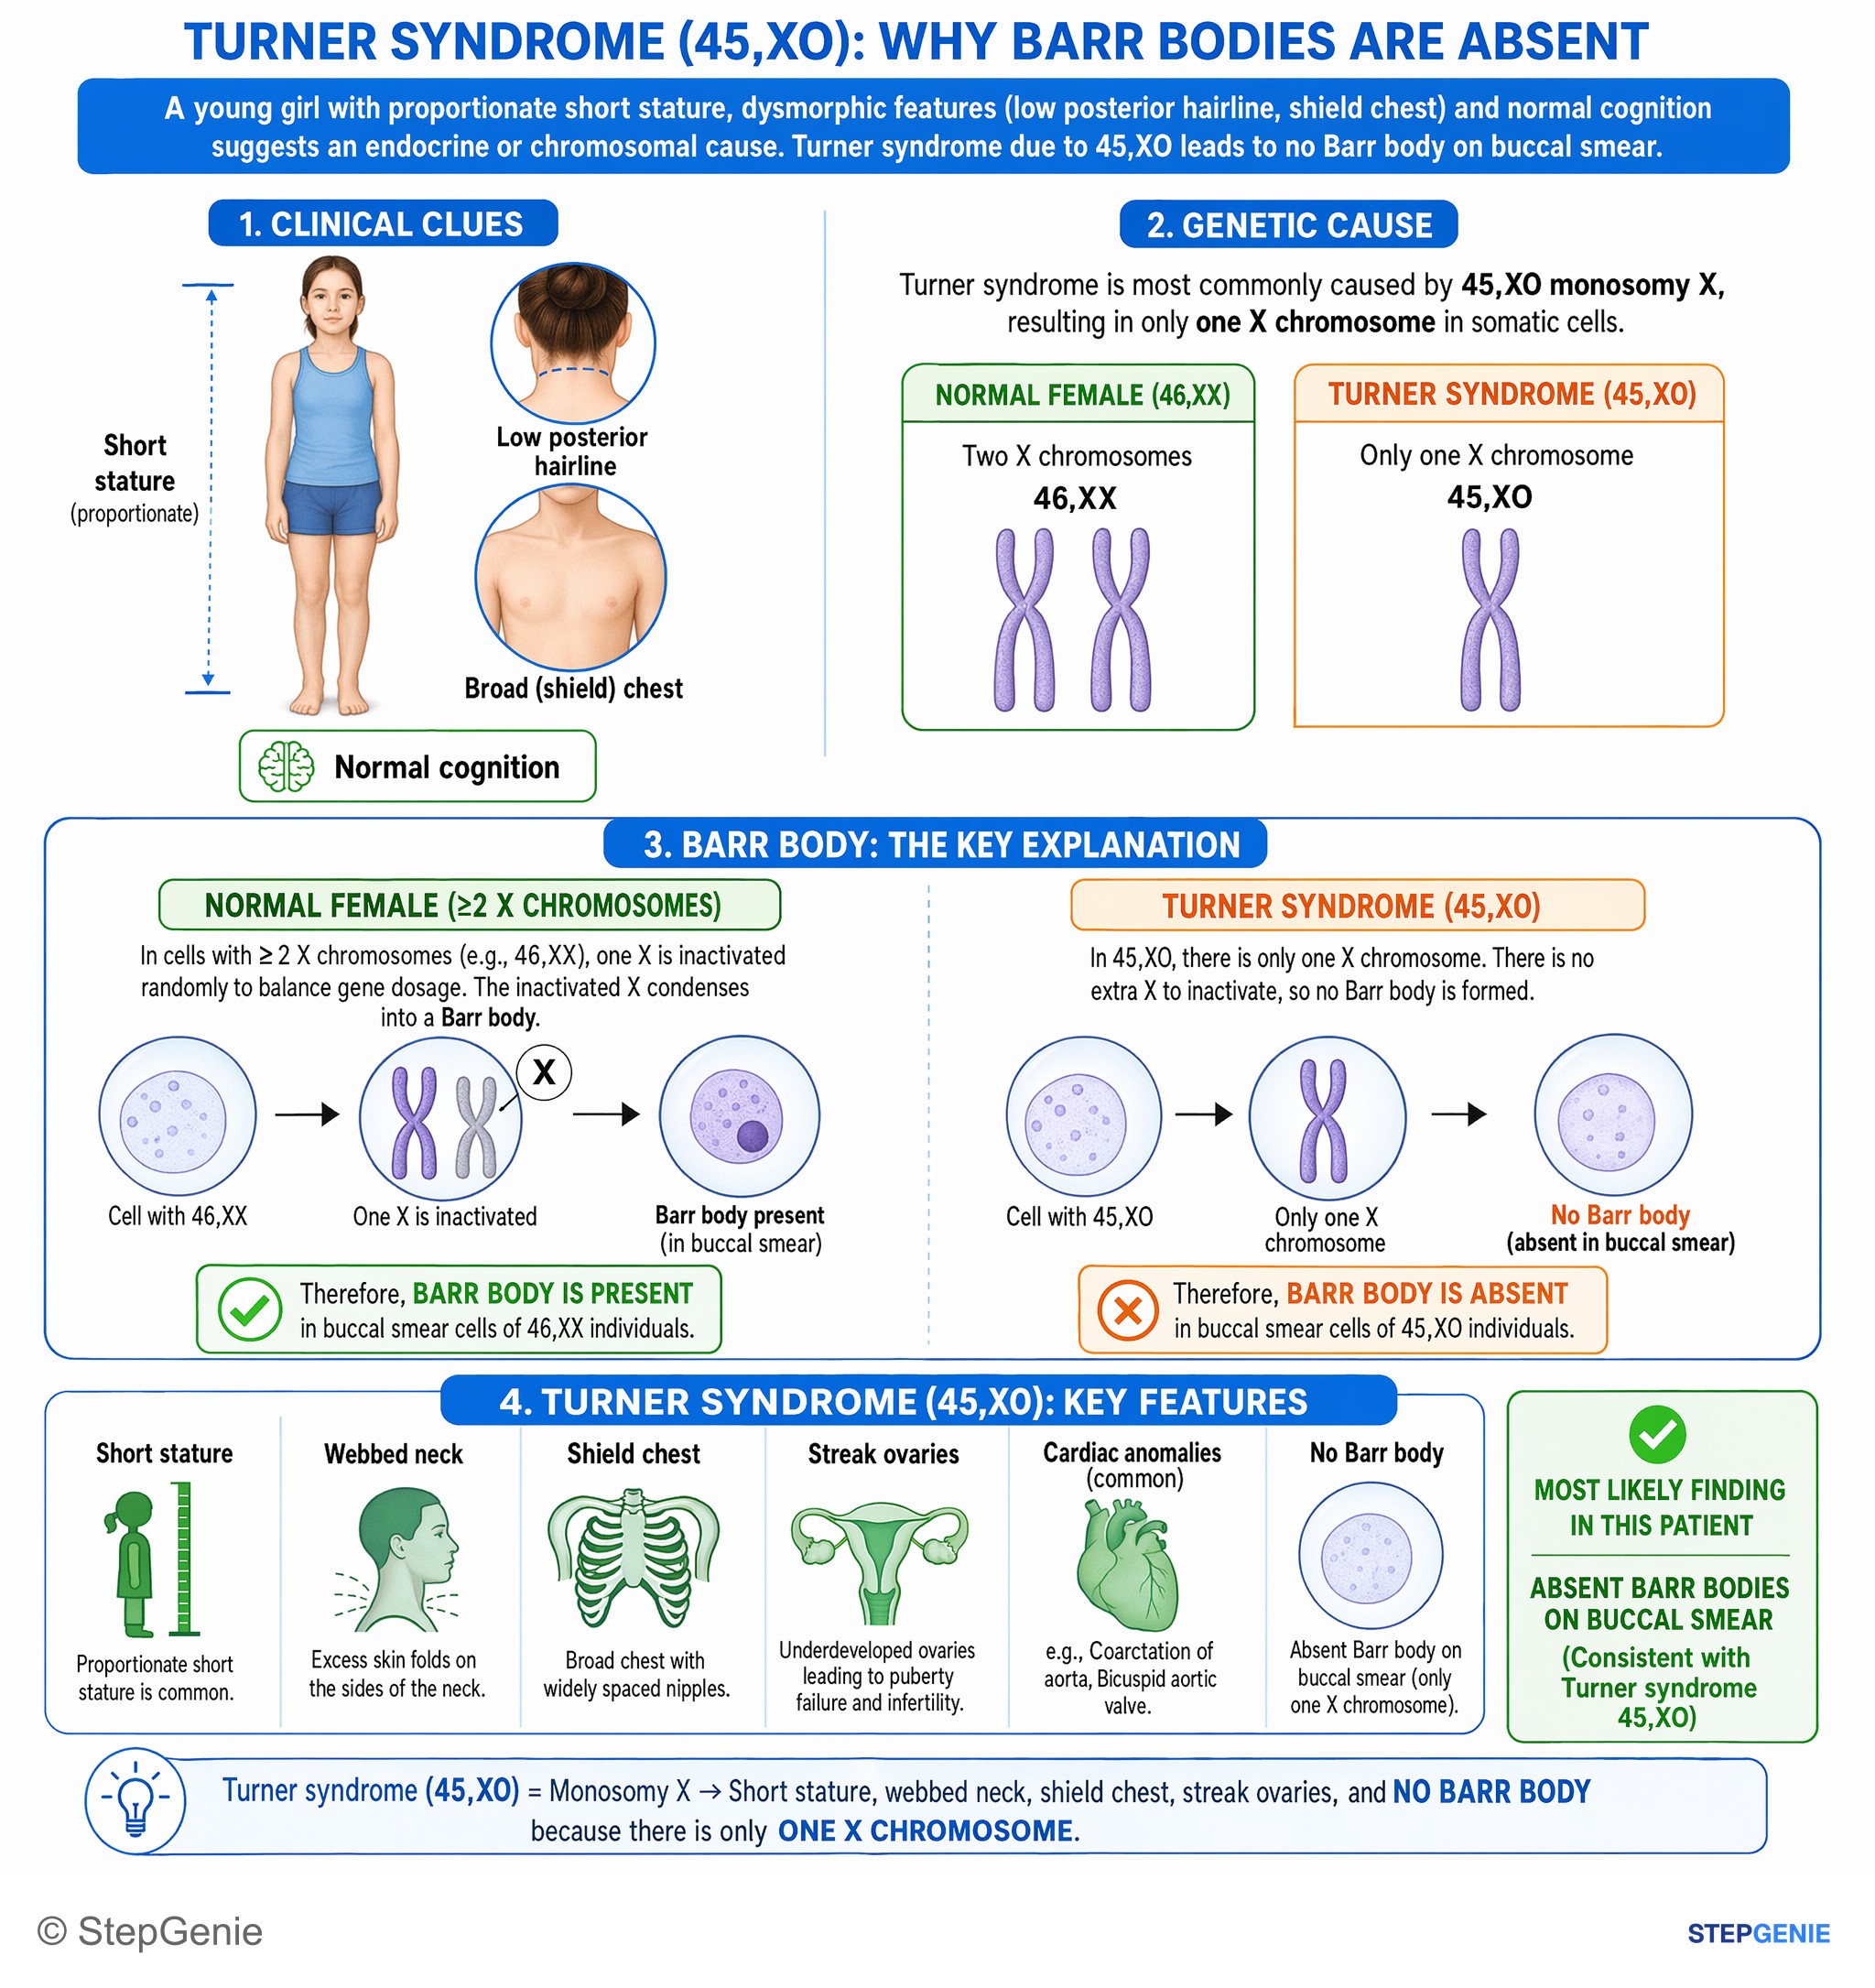
Turner syndrome (45,XO) causes short stature, webbed neck, shield chest, streak ovaries, and no Barr body (only one X chromosome).
USMLE Step 1Frequently Asked Questions
What is the most common karyotype in Turner syndrome?
The most common karyotype is 45,X, found in about 40–50% of patients. The rest are mosaic or structurally abnormal: 45,X/46,XX in 15–25%, isochromosome Xq in about 15%, a Y-containing line such as 45,X/46,XY in 10–12%, 45,X/47,XXX in about 3%, and rarely a ring X. In about 80% of 45,X cases the remaining X is maternal, so the lost sex chromosome usually came from the father. Most cases arise by chance and are not inherited.
What does it mean if a girl has Turner syndrome features but a normal 46,XX karyotype?
It depends on the features. Turner-like looks with pulmonary valve stenosis, normal puberty, or the same picture in a boy point to Noonan syndrome, an autosomal dominant RAS-MAPK disorder with a normal karyotype. If she has true Turner findings, such as ovarian failure with high FSH, coarctation or a bicuspid aortic valve, a normal blood result suggests missed 45,X/46,XX mosaicism. Guidelines advise counting at least 30 cells, then karyotyping or FISH on a second tissue such as buccal cells, skin or urine.
How do you tell Turner syndrome from Noonan syndrome?
Turner syndrome affects phenotypic females who are missing all or part of a sex chromosome. Noonan syndrome affects both sexes, has a normal karyotype and is autosomal dominant, with PTPN11 variants in about half of patients. The heart lesion is the fastest discriminator: Turner syndrome causes left-sided lesions such as bicuspid aortic valve and coarctation, while Noonan syndrome causes pulmonary valve stenosis and sometimes hypertrophic cardiomyopathy. Girls with Noonan syndrome usually have normal puberty and fertility, whereas Turner syndrome causes primary ovarian insufficiency with high FSH.
Why are FSH and LH elevated in Turner syndrome?
The ovaries form, but oocytes are lost early and the gonads become fibrous streaks that make little estrogen. Without estrogen feedback, the pituitary raises FSH and LH, producing hypergonadotropic hypogonadism (primary ovarian insufficiency). Gonadotropins are high in infancy, can fall to normal in mid-childhood and rise again near puberty, so a normal FSH at age 7 does not exclude Turner syndrome. Low FSH and LH in a girl with delayed puberty point instead to a hypothalamic or pituitary cause such as Kallmann syndrome.
What heart defects are associated with Turner syndrome?
About half of patients have congenital heart disease, mostly left-sided: a bicuspid aortic valve in more than 25% and coarctation of the aorta in about 4–15%, plus partial anomalous pulmonary venous return and an elongated transverse aortic arch. The aorta can dilate and dissect, at about 164 per 100,000 person-years versus 6 in the general population, so aortic imaging is lifelong, is done within 2 years before a planned pregnancy and is repeated after delivery. A girl diagnosed with coarctation should have a karyotype.
Do girls with Turner syndrome and Y chromosome material need their gonads removed?
About 10–12% of people with Turner syndrome carry Y material, which raises the risk of gonadoblastoma and dysgerminoma. PCR testing for Y material is recommended for 45,X girls with signs of virilization, not for every 45,X patient. Reported gonadoblastoma rates range from 0% to 100%, and malignant transformation from 1% to 22%, usually after the second decade. Prophylactic gonadectomy is the classic exam answer, but the 2024 international guideline recommends an individualized decision on whether and when to remove the gonads, weighing tumor risk against gonadal function and fertility.