All three complement pathways converge on C3. The classical pathway starts when C1q binds antigen-bound IgM or clustered IgG (or C-reactive protein); the lectin pathway starts when mannose-binding lectin (MBL) binds sugars on microbes and activates MASP proteases; the alternative pathway starts from spontaneous C3 "tickover," amplified on microbial surfaces by factor B, factor D and properdin. Each builds a C3 convertase (C4b2a for classical and lectin, C3bBb for alternative), then a C5 convertase, then the membrane attack complex (C5b-9). Deficiencies follow the map: early classical (C1, C2, C4) → lupus-like disease, C3 → recurrent pyogenic infections, C5-C9 → recurrent Neisseria, C1 inhibitor → hereditary angioedema, CD55/CD59 → PNH. C5-blocking drugs such as eculizumab recreate a terminal deficiency, hence their boxed warning for meningococcal infection.
The 5-second rule
Name the trigger, name the pathway: antibody = classical, sugar = lectin, bare microbial surface = alternative. Then every road runs C3 → C5 → C5b-9.
| Trigger in the stem | Pathway | Starter | Protease | C3 convertase |
|---|---|---|---|---|
| Antigen-bound IgM or clustered IgG; CRP | Classical | C1 (C1q, C1r, C1s) | C1s cleaves C4 and C2 | C4b2a |
| Mannose or other carbohydrate on microbes | Lectin | MBL | MASPs (MASP-2 is the effector enzyme) cleave C4 and C2 | C4b2a |
| Microbial surface, no antibody needed | Alternative | Spontaneous C3 hydrolysis ("tickover") | Factor D cleaves factor B to Bb | C3bBb, stabilized by properdin |
- Mnemonic for the classical pathway: "GM makes classic cars": IgG and IgM activate the classical pathway. Antigen-bound IgM engages C1 readily, whereas IgG must be aggregated (clustered).
- Lectin = classical without antibody: MASPs do C1s's job, so both make the same convertases.
- Alternative = always on, kept in check on host cells: C3b deposits constantly; regulators on our own cells remove it, while microbial surfaces (with properdin) let it amplify.
Convertases and the terminal pathway
| Classical and lectin | Alternative | |
|---|---|---|
| C3 convertase | C4b2a | C3bBb |
| C5 convertase (add a C3b) | C4b2a3b | C3bBb3b |
| Product | C5 → C5a + C5b | Same |
| Terminal step | C5b + C6, C7, C8, C9 → MAC (C5b-9) pore | Same |
Naming trap: the large C2 fragment was originally called C2a, which is why many texts (including Merck) write the convertase C4b2a. Some texts rename every large fragment "b," so the same enzyme appears as C4b2b and C4b2b3b. Same molecule, different label.
What complement does
- Opsonization: C3b coats microbes so phagocytes can eat them.
- Anaphylatoxins: C3a, C4a and C5a degranulate mast cells.
- Chemotaxis: C5a is the key neutrophil chemoattractant.
- Lysis: C5b-9 (MAC) punches pores; it is essential for clearing Neisseria.
- Immune complex clearance: early classical components help remove antigen-antibody complexes, which is why their loss causes lupus-like disease.
Regulators: what goes wrong when the brakes fail
| Regulator | Normal job | When it's missing |
|---|---|---|
| C1 inhibitor | Inhibits C1 and the contact system | Hereditary angioedema: bradykinin-mediated swelling |
| Factor H, factor I, MCP (CD46) | Factor I cleaves C3b, with factor H, MCP or CR1 as cofactors | Atypical HUS; factor H or I deficiency mimics C3 deficiency |
| DAF (CD55) | Displaces Bb and blocks convertases on host cells | With CD59, PNH; inherited CD55 deficiency causes CHAPLE disease (a protein-losing enteropathy) |
| CD59 | Blocks C9 binding, so no MAC on host cells | PNH (complement lyses red cells) |
Complement deficiencies in 5 seconds
| Deficiency | Result | Classic stem |
|---|---|---|
| C1q, C1r/s, C2, C4 (early classical) | Lupus-like immune complex disease | SLE features; 10-20% of people with C2 deficiency develop SLE |
| C3 | Recurrent pyogenic infections from birth, glomerulonephritis | Infant with repeated pneumonia and sepsis |
| C5-C9 (terminal) | Recurrent Neisseria meningitidis | Second meningococcal infection in an otherwise healthy person |
| Properdin (X-linked) | Fulminant neisserial infection | Boy with meningococcemia |
| Factor H or I | Like C3 deficiency; atypical HUS | Microangiopathic hemolysis, low platelets, AKI (see TTP vs HUS) |
| MBL | Recurrent pyogenic infections with encapsulated bacteria from infancy; unexplained sepsis | Child with frequent bacterial infections |
| C1 inhibitor (autosomal dominant) | Hereditary angioedema | Face or lip swelling and abdominal attacks without hives, low C4 |
| CD55 + CD59 (acquired PIGA mutation) | PNH | Intravascular hemolysis, thrombosis in odd sites, cytopenias; DAT-negative |
- HAE details: type 1 (85%) has low C1 inhibitor levels, type 2 normal levels with poor function; C4 is low even between attacks with normal C1q (C1q is low in acquired C1 inhibitor deficiency). Antihistamines, epinephrine and glucocorticoids usually don't work; attacks are treated with C1 inhibitor concentrate (plasma-derived or recombinant) or the bradykinin B2-receptor blocker icatibant, among other agents.
- Vaccines: CDC recommends MenACWY and MenB vaccines for people with complement component deficiencies (e.g., C5-C9, properdin, factor H, factor D) and for people taking complement inhibitors.
See the full deficiency grid in complement deficiencies table and mnemonics, the organism in Neisseria meningitidis tips, and the autoimmune side in the SLE guide.
Complement-inhibitor drugs (selected US labels, October 2026)
| Drug (brand) | Target | Main US indications |
|---|---|---|
| Eculizumab (Soliris; biosimilars Bkemv, Epysqli) | C5 | PNH; aHUS (not STEC-HUS); AChR-antibody-positive generalized myasthenia gravis; AQP4-antibody-positive NMOSD |
| Ravulizumab (Ultomiris) | C5, long-acting (IV every 4-8 weeks) | PNH; aHUS; AChR+ gMG; AQP4+ NMOSD |
| Crovalimab (PiaSky) | C5 | PNH (age 13 and older, at least 40 kg) |
| Zilucoplan (Zilbrysq) | C5 (subcutaneous) | AChR+ gMG |
| Pozelimab (Veopoz) | C5 | CHAPLE disease (CD55 deficiency) |
| Pegcetacoplan (Empaveli; Syfovre in the eye) | C3/C3b | PNH; C3 glomerulopathy or primary IC-MPGN (age 12 and older); geographic atrophy (Syfovre) |
| Iptacopan (Fabhalta, oral) | Factor B | PNH; IgA nephropathy; C3 glomerulopathy |
| Danicopan (Voydeya, oral) | Factor D | Add-on to eculizumab or ravulizumab for extravascular hemolysis in PNH |
| Sutimlimab (Enjaymo) | C1s (classical) | Hemolysis in cold agglutinin disease |
| Narsoplimab (Yartemlea) | MASP-2 (lectin) | Transplant-associated thrombotic microangiopathy (age 2 and older), approved 2025 |
| Avacopan (Tavneos, oral) | C5a receptor | Adjunct for severe active ANCA vasculitis (GPA, MPA). FDA's drug center proposed withdrawing approval in April 2026, citing unproven effectiveness and untrue statements in the application; per FDA (July 2026) it stays on the market until the company withdraws it or the Commissioner orders removal |
- The drug rule mirrors the deficiency rule. Eculizumab blocks C5 cleavage, so no C5a and no C5b-9: the boxed warning is serious meningococcal infection, with vaccination against serogroups A, C, W, Y and B at least 2 weeks before the first dose (unless delay is riskier) and a REMS program. Proximal blockers (pegcetacoplan, iptacopan, danicopan) carry boxed warnings for encapsulated bacteria. CDC warns that patients on complement inhibitors can get meningococcal disease even when fully vaccinated and on antibiotic prophylaxis.
- Link to hemolysis: C5 and proximal inhibitors treat PNH (see the PNH cheat sheet); sutimlimab treats cold agglutinin disease (see autoimmune hemolytic anemia).
How USMLE tests it
- Recurrent meningococcal disease with normal immunoglobulins and neutrophil function: terminal (C5-C9) or properdin deficiency.
- Meningococcal sepsis in a patient with PNH or myasthenia gravis: suspect a C5 inhibitor.
- Swelling without urticaria, abdominal attacks, no response to epinephrine, low C4: C1 inhibitor deficiency.
- Lupus-like disease in a patient missing C1q, C2 or C4: impaired immune complex clearance.
- Which fragment? C3b opsonizes, C5a recruits neutrophils, C3a/C4a/C5a degranulate mast cells, C5b-9 lyses.
- Which convertase? C4b2a for classical and lectin, C3bBb for alternative; add C3b to make the C5 convertase.
Practice question
A 19-year-old man is admitted with meningococcemia. At age 14 he had meningococcal meningitis, and his older sister had meningococcal disease at 16. He has had no other serious infections, rashes, joint pains or swelling episodes. Immunoglobulin levels, lymphocyte counts and the neutrophil oxidative burst are normal. A deficiency of which of the following is most likely?
A. C1 inhibitor B. C2 C. C3 D. C8 E. Mannose-binding lectin F. CD55 and CD59 (GPI-anchored regulators)
Answer: D. C8 is part of the membrane attack complex (C5b-9). Without it the MAC cannot form, and the MAC is what clears Neisseria, so meningococcal infections recur, here in two siblings. Everything else about his immune system is normal, which is the classic setup. He should receive MenACWY and MenB vaccines (CDC).
- A: C1 inhibitor deficiency causes hereditary angioedema: recurrent swelling without hives, abdominal attacks and a low C4, not infections.
- B: early classical deficiencies such as C2 mainly cause lupus-like disease (10-20% of C2-deficient people develop SLE); he has no autoimmune features.
- C: C3 deficiency causes recurrent pyogenic infections from birth plus glomerulonephritis, not a healthy childhood followed by isolated meningococcal disease.
- E: MBL deficiency causes recurrent pyogenic infections with encapsulated bacteria from infancy, not isolated meningococcal disease in an otherwise healthy teenager.
- F: loss of CD55 and CD59 (PNH) causes complement-mediated hemolysis, thrombosis and cytopenias, not recurrent Neisseria.
Key takeaways
- Antibody → classical (C1q), sugar → lectin (MBL/MASP), surface → alternative (B, D, properdin). All converge on C3, then C5, then C5b-9.
- Convertases: C4b2a (classical, lectin) and C3bBb (alternative); add C3b for the C5 convertase. C4b2b is the same enzyme under newer naming.
- Fragments: C3b opsonin; C3a, C4a, C5a anaphylatoxins; C5a neutrophil chemotaxis; C5b-9 lysis.
- Deficiencies: C1/C2/C4 → lupus-like; C3 → pyogenic infections and GN; C5-C9 or properdin → Neisseria; factor H/I → aHUS; C1 inhibitor → HAE (low C4); CD55/CD59 → PNH.
- Drugs: C5 blockers (eculizumab, ravulizumab, crovalimab, zilucoplan, pozelimab), C3 (pegcetacoplan), factor B (iptacopan), factor D (danicopan), C1s (sutimlimab), MASP-2 (narsoplimab). Systemic C5, C3, factor B and factor D blockers carry boxed warnings for meningococcal or other encapsulated-bacterial infection, so patients are vaccinated first.
Sources
- Complement System — Merck Manual Professional Edition (2026)
- Overview of Immunodeficiency Disorders (complement deficiencies) — Merck Manual Professional Edition (2025)
- The Complement System and Innate Immunity — Immunobiology, 5th edition, NCBI Bookshelf (2001)
- Hereditary and Acquired Angioedema — Merck Manual Professional Edition (2026)
- Paroxysmal Nocturnal Hemoglobinuria (PNH) — Merck Manual Professional Edition (2026)
- Complement Component 2 Deficiency — MedlinePlus Genetics, National Library of Medicine
- Meningococcal Vaccination: Risk-Based Indications — Centers for Disease Control and Prevention (2026)
- SOLIRIS (eculizumab): Prescribing Information — DailyMed (2026)
- FABHALTA (iptacopan): Prescribing Information — DailyMed (2026)
- Hemolytic-Uremic Syndrome (HUS) — Merck Manual Professional Edition (2026)
- YARTEMLEA (narsoplimab-wuug): Prescribing Information — DailyMed (2025)
- CDER Proposes to Withdraw Approval of TAVNEOS — U.S. Food and Drug Administration (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
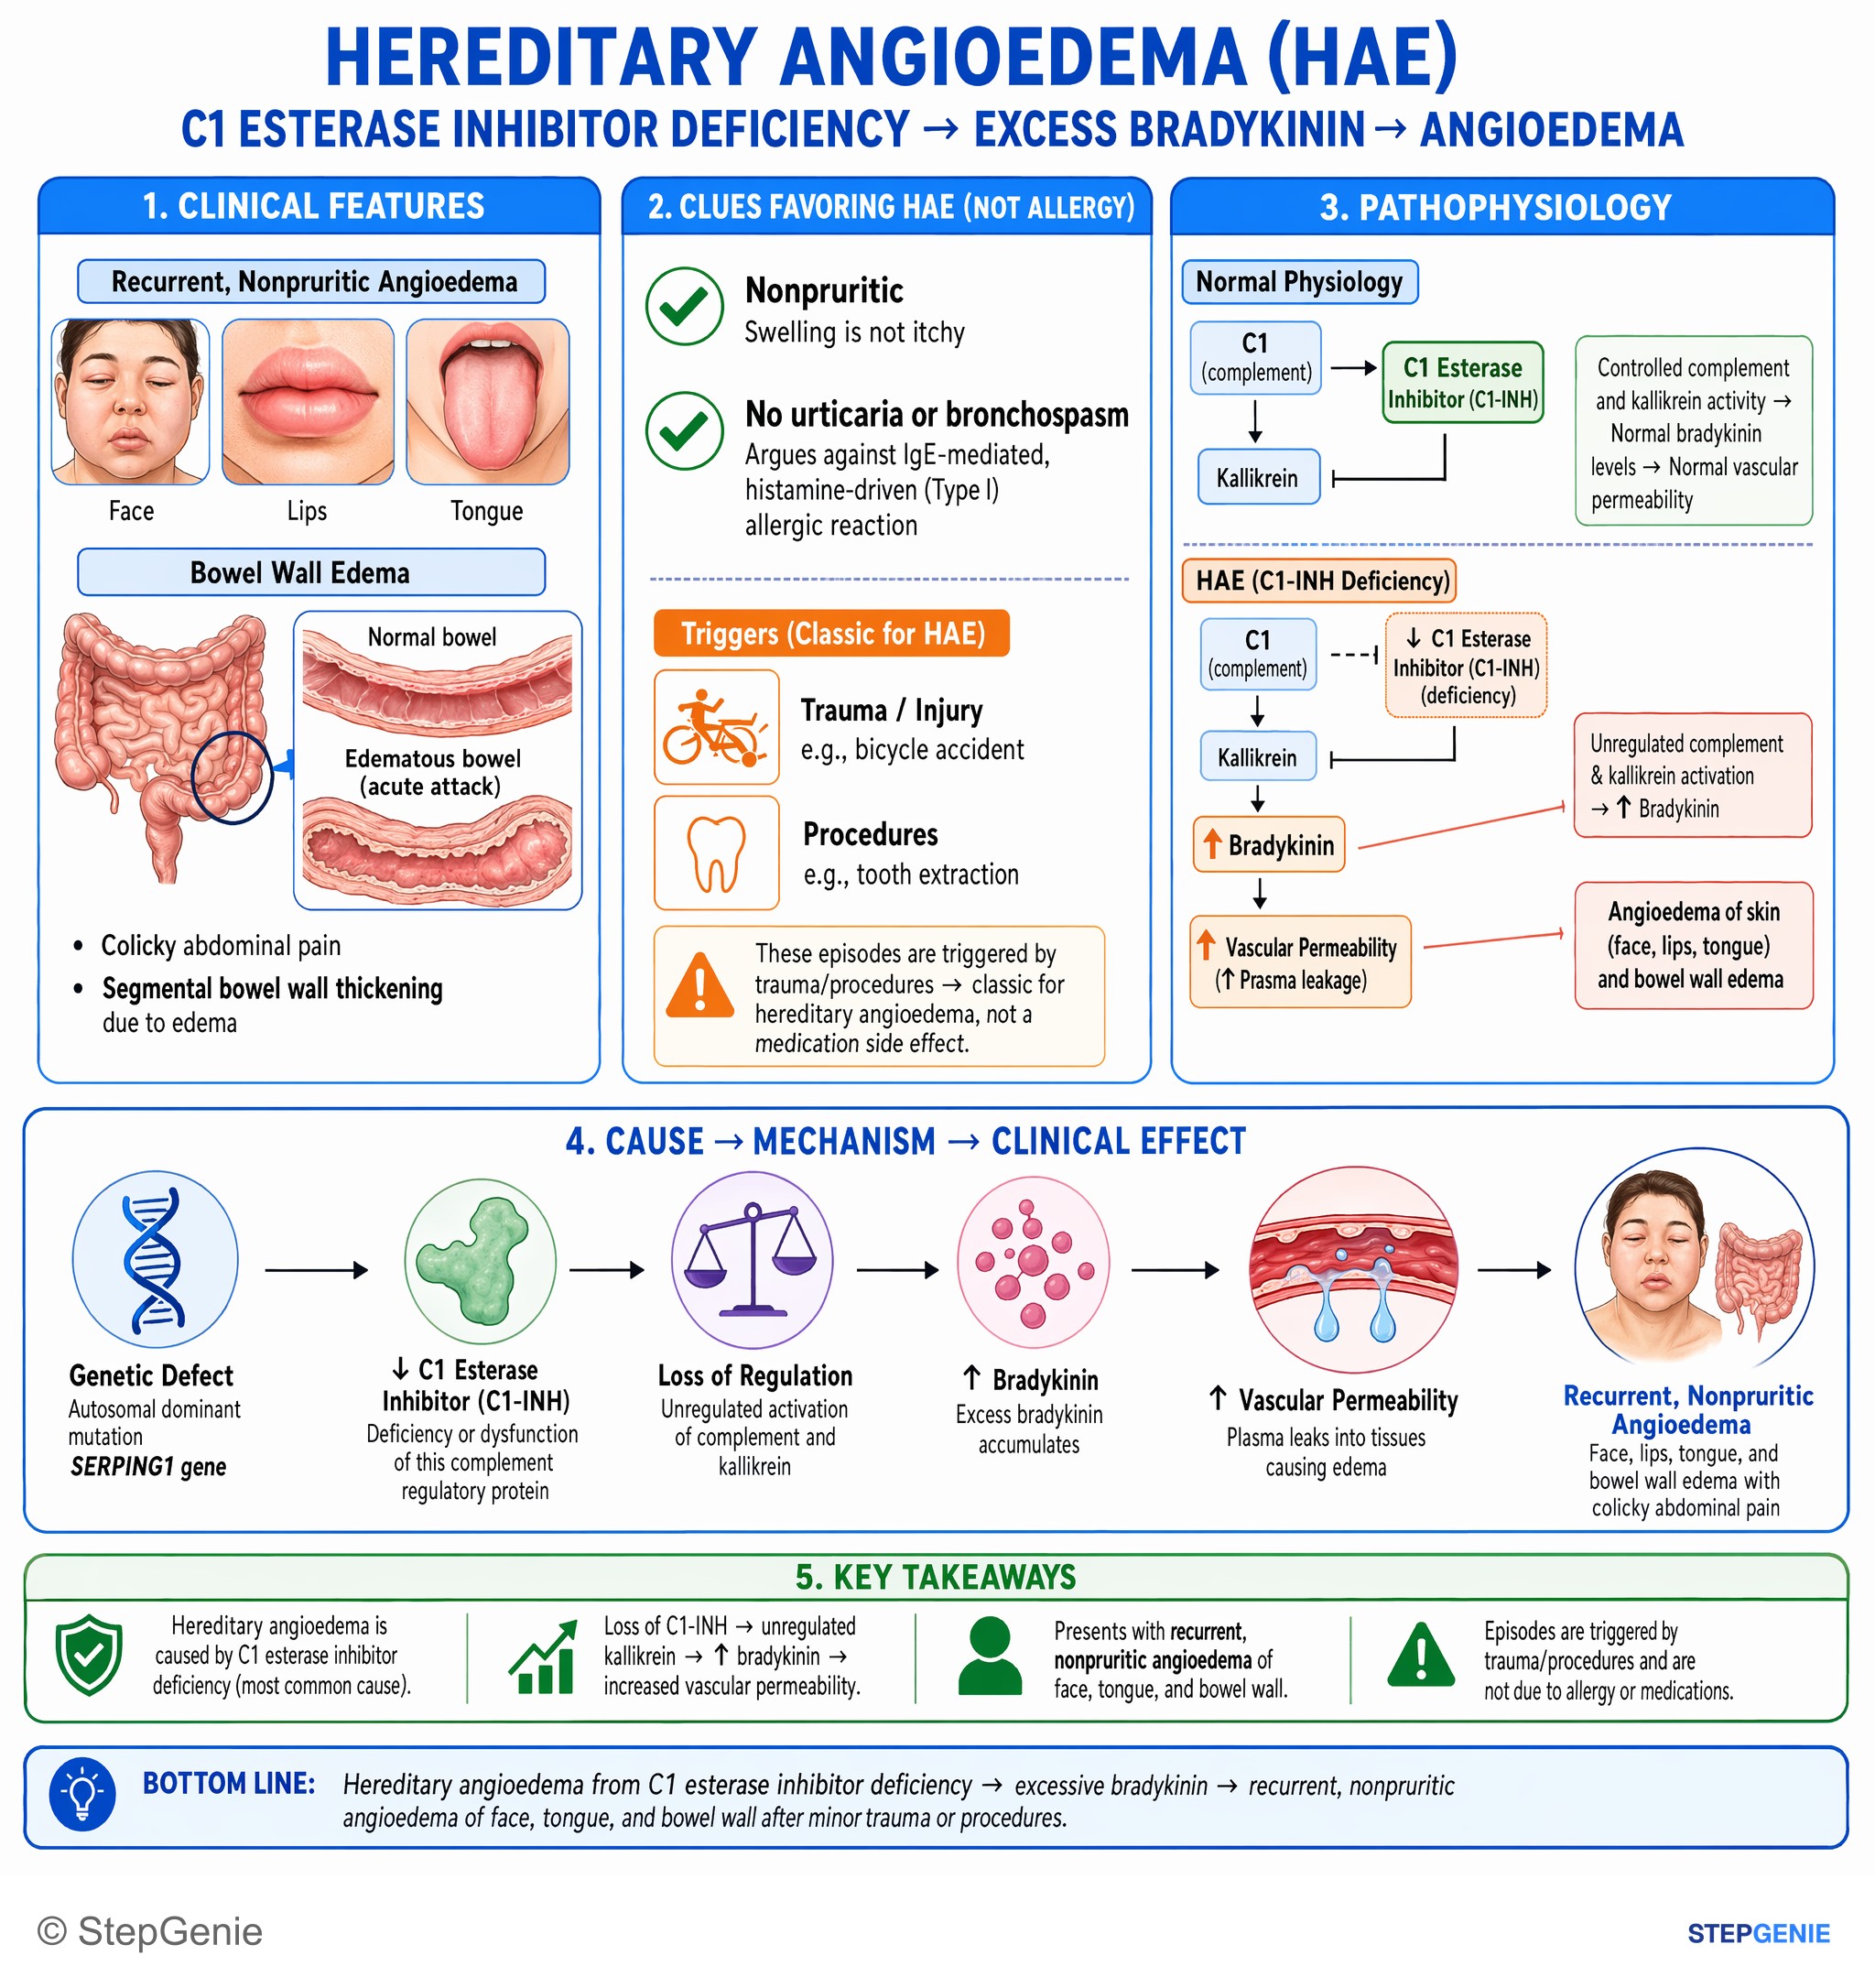
Hereditary angioedema from C1 esterase inhibitor deficiency → excessive bradykinin → recurrent, nonpruritic angioedema of face, tongue…
USMLE Step 1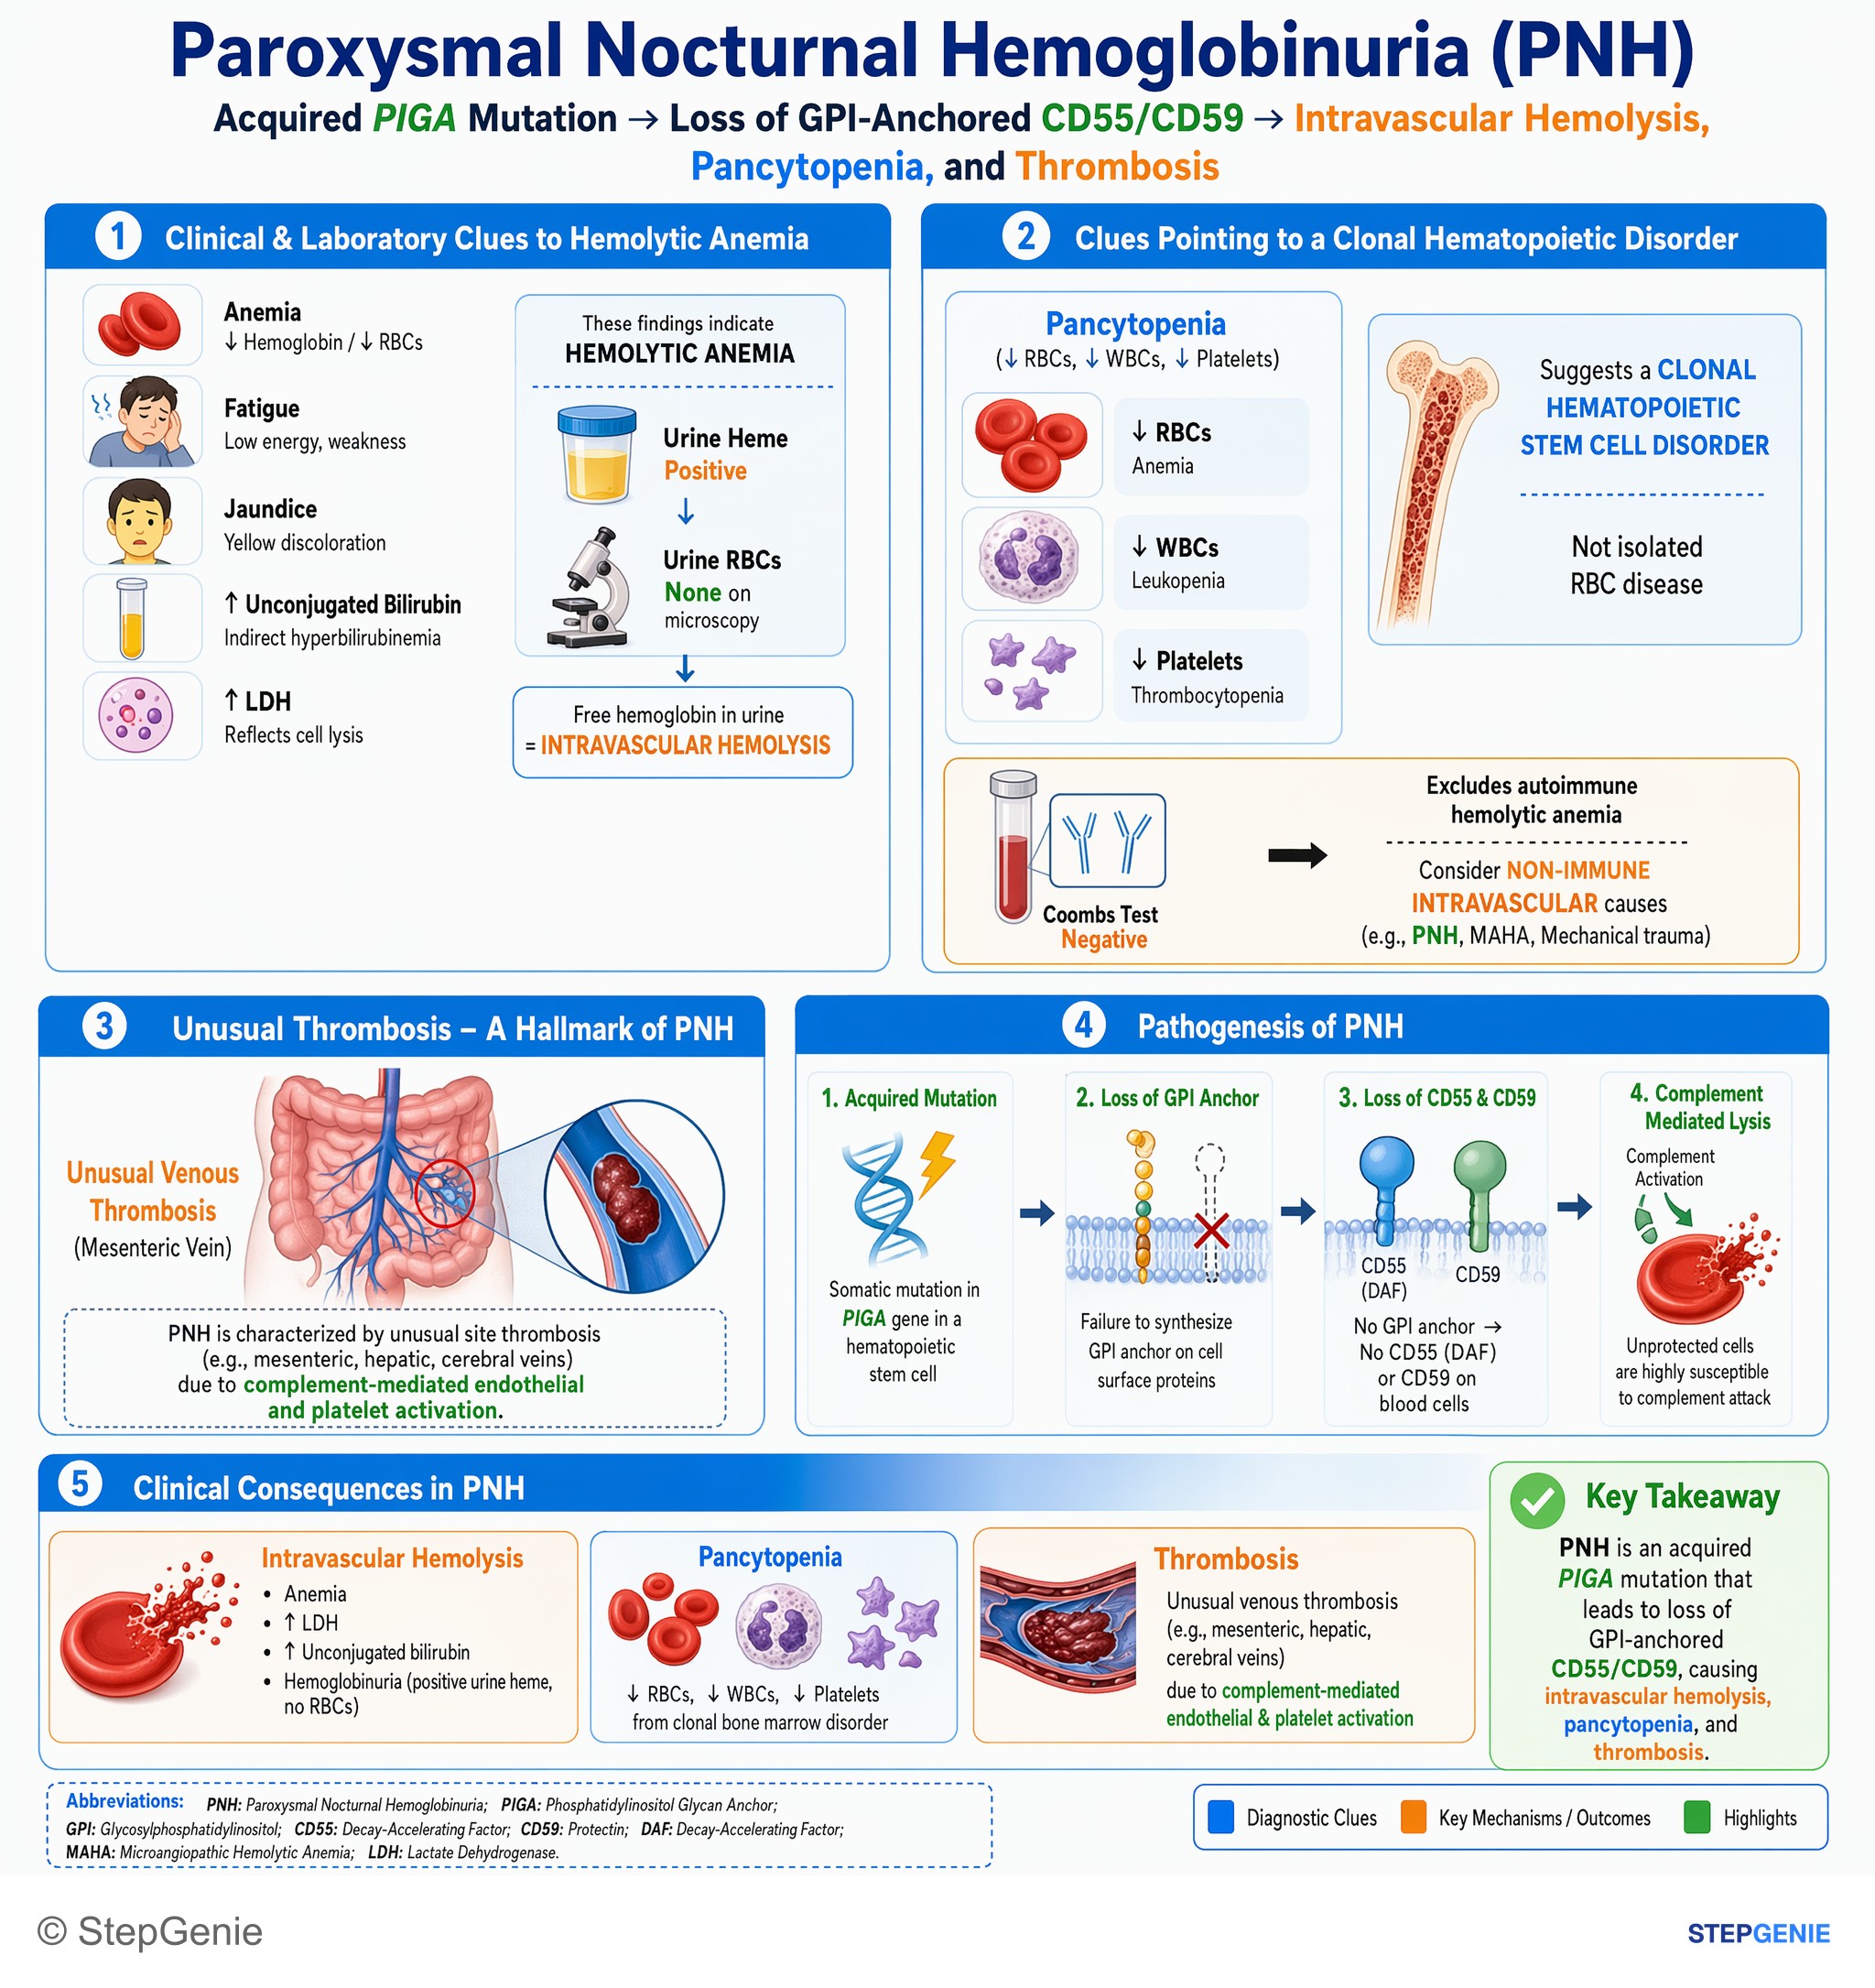
Paroxysmal nocturnal hemoglobinuria: acquired PIGA mutation → loss of GPI-anchored complement regulators (CD55/CD59) → intravascular…
USMLE Step 1Frequently Asked Questions
What are the three complement pathways and what activates each?
The classical pathway is activated when C1q binds antigen-bound IgM or aggregated IgG, or bound C-reactive protein. The lectin pathway is activated when mannose-binding lectin binds carbohydrates on microbes and activates MASP proteases. The alternative pathway runs continuously through spontaneous breakdown of C3 and is amplified on microbial surfaces by factor B, factor D and properdin. All three converge on C3, then C5, then the membrane attack complex.
What are the C3 and C5 convertases of each complement pathway?
The classical and lectin pathways share a C3 convertase, C4b2a, and a C5 convertase, C4b2a3b. The alternative pathway uses C3bBb as its C3 convertase and C3bBb3b as its C5 convertase, and properdin stabilizes it. Some textbooks call every large complement fragment b, so the classical enzyme also appears as C4b2b and C4b2b3b; these are the same enzymes under a different naming convention.
Which complement deficiency causes recurrent Neisseria infections?
Deficiency of any terminal component, C5 through C9, prevents formation of the membrane attack complex, which the body needs to clear Neisseria, so patients get recurrent meningococcal infections. Properdin deficiency, which is X-linked, also predisposes to fulminant neisserial infection. CDC recommends MenACWY and MenB vaccines for people with these deficiencies and for people taking complement inhibitors such as eculizumab or ravulizumab.
What happens in C3 deficiency compared with early complement deficiency?
C3 sits where all three pathways meet, so its absence removes the main opsonin, C3b, and every downstream step: patients have recurrent pyogenic infections from birth and glomerulonephritis. Deficiencies of the early classical components C1, C2 and C4 mainly impair clearance of immune complexes and cause lupus-like disease; between 10 and 20 percent of people with C2 deficiency develop systemic lupus erythematosus.
How does C1 inhibitor deficiency cause angioedema?
C1 inhibitor normally restrains C1 and the contact system. When it is missing or dysfunctional, as in autosomal dominant hereditary angioedema, uncontrolled contact activation generates bradykinin, which causes swelling of the face, lips, airway or gut without hives or itching. C4 is low even between attacks. Antihistamines, epinephrine and glucocorticoids usually do not work; C1 inhibitor concentrate or icatibant, a bradykinin B2-receptor blocker, treats attacks.
Which drugs inhibit the complement system?
C5 inhibitors include eculizumab, ravulizumab, crovalimab, zilucoplan and pozelimab; pegcetacoplan blocks C3, iptacopan blocks factor B and danicopan blocks factor D. Sutimlimab blocks C1s of the classical pathway in cold agglutinin disease, and narsoplimab, approved in 2025, blocks MASP-2 of the lectin pathway. Because blocking C5 recreates a terminal complement deficiency, eculizumab carries a boxed warning for meningococcal infection and requires vaccination.